
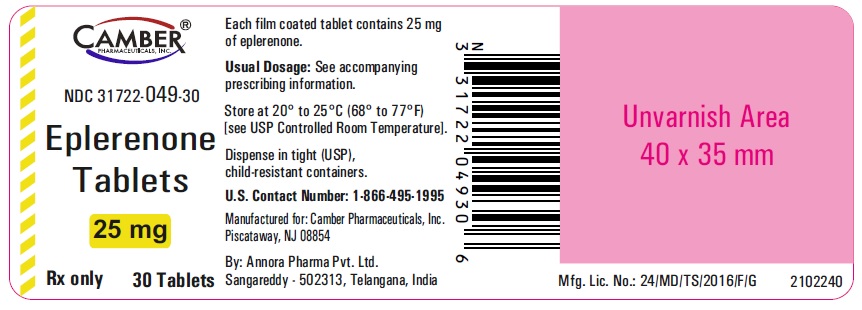
Eplerenone 25 mg Tablet, Film Coated, 30-count — NDC 31722-049-30 (Billing 31722-0049-30)
This is a package of 30 tablets of Eplerenone 25 mg Tablet, Film Coated from Camber Pharmaceuticals, Inc., marketed since Jun 2023 and currently FDA-listed; retail pharmacies pay about $0.3080 per tablet (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 31722-049-30 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 31722 labeler · 049 product · 30 package
- Package marketed since
- Jun 2, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 30 EA per package
- Barcode (UPC)
- 0331722049306
- Medicaid fills, this package
- 8,322 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 051036
- GCN: 91883
- GPI-14 (Medi-Span): 36250030000320
- HICL (First Databank): 024316
- AHFS class code: 24:32.20.08
- RxCUI (RxNorm): 351256
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Aldosterone Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats high blood pressure in adults. It is also used to improve survival in stable adults with heart failure and a weakened pumping heart after a heart attack.
- You swallow the tablet by mouth, and food doesn't change how well it works. Take it exactly as your prescriber directs. Your potassium will be checked before you start and from tim...
- The most common are high potassium and a rise in creatinine on blood tests. Some people get headache or dizziness. Men may notice breast enlargement, and women may have abnormal va...
- Yes. Strong CYP3A inhibitors such as ketoconazole, itraconazole, clarithromycin and ritonavir must not be used with it. Potassium supplements, potassium-sparing diuretics, NSAIDs,...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Eplerenone — tap one for details:
Eplerenone may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.308 | $9.24 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.6433 | $19.30 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.8345 | $25.04 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 31722-0049-30 You're viewing this Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | $0.3080 / ea | $9.24 | 2023-06-02 | — | Active |
| 31722-0049-90 31722-049-90 | 90 TABLET, FILM COATED in 1 BOTTLE | $0.3080 / ea | $27.72 | 2023-06-02 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
This pack has the lowest per-ea cost of the 2 priced pack sizes ($0.3080 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 71% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 31722-0049-90?
What NDC number is used to bill for this package of Eplerenone 25 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Eplerenone 25 mg 16571-0173-03 | Rising | 30 tablets | $0.308 | AB | Availability likely | — |
| Eplerenone 25 mg 16729-0293-10 | Accord | 30 tablets | $0.308 | AB | Availability likely | — |
| Eplerenone 25 mgthis 31722-0049-30 | Camber | 30 tablets | $0.308 | AB | Availability likely | — |
| Eplerenone 25 mg 59762-1107-02 | Mylan | 30 tablets | $0.308 | AB | Availability likely | — |
| Eplerenone 25 mg 60687-0451-21 | American | 1 tablet | $0.308 | AB | Availability likely | — |
| Eplerenone 25 mg 69367-0307-09 | Westminster | 90 tablets | $0.308 | AB | Availability likely | — |
| Eplerenone 25 mg 59762-1710-01 | Mylan | 1 tablet | $0.640 | AB | Discontinued | +108% |
| Inspra 25 mg 58151-0142-93 | Viatris | 30 tablets | $14.107 | AB | Availability likely | +4480% |
| Eplerenone 25 mg 42291-0454-30 | AvKARE | 30 tablets | — | AB | Discontinued | — |
| Eplerenone 25 mg 51991-0877-11 | Breckenridge | 10 tablets | — | AB | FDA listed | — |
| Eplerenone 25 mg 63629-9414-01 | Bryant | 90 tablets | — | AB | FDA listed | — |
| Eplerenone 25 mg 71205-0863-00 | Proficient | 100 tablets | — | AB | FDA listed | — |
| Eplerenone 25 mg 71335-2355-01 | Bryant | 90 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Camber Pharmaceuticals, Inc. labeler code 31722
- Mesalamine 1.2 g Tablet, Delayed Release NDC 31722-043-05
- Zileuton 600 mg Tablet, Film Coated, Extended Release NDC 31722-044-12
- sapropterin dihydrochloride 100 mg Tablet NDC 31722-045-12
- Diclofenac potassium 50 mg Powder, For Solution NDC 31722-046-31
- Sapropterin dihydrochloride 100 mg Powder, For Solution NDC 31722-047-30
- Sapropterin dihydrochloride 500 mg Powder, For Solution NDC 31722-048-30
- Eplerenone 50 mg Tablet, Film Coated NDC 31722-050-30
- Indomethacin 50 mg Suppository NDC 31722-051-31
- Dicyclomine hydrochloride 10 mg Capsule NDC 31722-052-01
- Ivabradine 5 mg Tablet, Film Coated NDC 31722-053-60
- Ivabradine 7.5 mg Tablet, Film Coated NDC 31722-054-60
- FAMOTIDINE 40 mg/5mL Powder, For Suspension NDC 31722-063-31
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Eplerenone tablets are an aldosterone antagonist indicated for: • Improving survival of stable patients with symptomatic heart failure with reduced ejection fraction (HFrEF) after an acute myocardial infarction. ( 1.1 ) • The treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. ( 1.2 )
1.1Heart Failure Post-Myocardial Infarction Eplerenone tablets are indicated to improve survival of stable patients with symptomatic heart failure with reduced ejection fraction (≤40%) (HFrEF) after an acute myocardial infarction (MI).
1.2Hypertension Eplerenone tablets are indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular (CV) events, primarily strokes and MI. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes.
Control of high blood pressure should be part of comprehensive CV risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than one drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program’s Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC).
Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce CV morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits. The largest and most consistent CV outcome benefit has been a reduction in the risk of stroke, but reductions in MI and CV mortality also have been seen regularly.
Elevated systolic or diastolic pressure causes increased CV risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. Eplerenone tablets may be used alone or in combination with other antihypertensive agents.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION HFrEF Post-MI: Initiate treatment with 25 mg once daily. Titrate to maximum of 50 mg once daily within 4 weeks, as tolerated. Dose adjustments may be required based on potassium levels.
( 2.1 ) Hypertension: 50 mg once daily, alone or combined with other antihypertensive agents. For inadequate response, increase to 50 mg twice daily. Higher dosages are not recommended.
( 2.2 ) For all patients: Measure serum potassium before starting eplerenone tablets and periodically thereafter. ( 2.3 )
2.1Heart Failure Post-Myocardial Infarction Initiate treatment at 25 mg once daily and titrate to the recommended dose of 50 mg once daily, preferably within 4 weeks as tolerated by the patient. Once treatment with eplerenone tablets has begun, adjust the dose based on the serum potassium level as shown in Table 1. Table 1.
Dose Adjustment in Heart Failure Post-MI Serum Potassium (mEq/L) Dose Adjustment <5.0 25 mg every other day to 25 mg once daily 25 mg once daily to 50 mg once daily 5.0 to
5.4No adjustment 5.5 to 5.9 50 mg once daily to 25 mg once daily 25 mg once daily to 25 mg every other day 25 mg every other day to withhold ≥6.0 Withhold and restart at 25 mg every other day when potassium levels fall to <5.5 mEq/L
2.2Hypertension The recommended starting dose of eplerenone tablets is 50 mg administered once daily. The full therapeutic effect of eplerenone tablets is apparent within 4 weeks. For patients with an inadequate blood pressure response to 50 mg once daily increase the dosage of eplerenone tablets to 50 mg twice daily.
Higher dosages of eplerenone tablets are not recommended because they have no greater effect on blood pressure than 100 mg and are associated with an increased risk of hyperkalemia [see Clinical Studies ( 14.2 )].
2.3Recommended Monitoring Measure serum potassium before initiating eplerenone tablets therapy, within the first week, and at one month after the start of treatment or dose adjustment. Assess serum potassium periodically thereafter. Check serum potassium and serum creatinine within 3 to 7 days of a patient initating a moderate CYP3A inhibitor ACE inhibitors, angiotensin-II blockers or non-steroidal-anti-inflammatories.
2.4Dose Modification for Use with Moderate CYP3A Inhibitors In post-MI HFrEF patients receiving a moderate CYP3A inhibitor (e.g., erythromycin, saquinavir, verapamil, and fluconazole), do not exceed 25 mg once daily. In patients with hypertension receiving a moderate CYP3A inhibitor, initiate at 25 mg once daily. For inadequate blood pressure response, dosing may be increased to a maximum of 25 mg twice daily [see Drug Interactions ( 7.1 )].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS • 25 mg tablets: Light yellow, Round, biconvex, film coated tablets debossed with "V" on one side and :68" on the other side. • 50 mg tablets: Light yellow, Round, biconvex, film coated tablets debossed with "V" on one side and "67" on the other side. Tablets: 25 mg, 50 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS For All Patients Eplerenone tablets are contraindicated in all patients with: • serum potassium >5.5 mEq/L at initiation, • creatinine clearance ≤30 mL/min, or • concomitant administration of strong CYP3A inhibitors (e.g., ketoconazole, itraconazole, nefazodone, troleandomycin, clarithromycin, ritonavir, and nelfinavir) [see Drug Interactions ( 7.1 ), Clinical Pharmacology ( 12.3 )]. For Patients Treated for Hypertension Eplerenone tablets are contraindicated for the treatment of hypertension in patients with: • type 2 diabetes with microalbuminuria, • serum creatinine >2.0 mg/dL in males or >1.8 mg/dL in females, • creatinine clearance <50 mL/min, or • concomitant administration of potassium supplements or potassium-sparing diuretics (e.g., amiloride, spironolactone, or triamterene) [see Warnings and Precautions ( 5.1 ), Adverse Reactions ( 6.2 ), Drug Interactions ( 7 ), and Clinical Pharmacology ( 12.3 )].
For all patients: • Serum potassium >5.5 mEq/L at initiation ( 4 ) • Creatinine clearance ≤30 mL/min ( 4 ) • Concomitant use with strong CYP3A inhibitors ( 4 , 7.1 ) For the treatment of hypertension: • Type 2 diabetes with microalbuminuria ( 4 ) • Serum creatinine >2.0 mg/dL in males, >1.8 mg/dL in females ( 4 ) • Creatinine clearance <50 mL/min ( 4 ) • Concomitant use of potassium supplements or potassium-sparing diuretics ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hyperkalemia: Patients with decreased renal function, diabetes, proteinuria or patients who are taking ACEs and ARBs, NSAIDs or moderate CYP3A inhibitors are at increased risk. Monitor serum potassium levels and adjust dose as needed. ( 5.1 )
5.1Hyperkalemia The risk of hyperkalemia is higher in patients with impaired renal function, proteinuria, diabetes and those concomitantly treated with ACEs, ARBs, NSAIDs and moderate CYP3A inhibitors. Minimize the risk of hyperkalemia with proper patient selection and monitoring [see Dosage and Administration ( 2.1 ), Contraindications ( 4 ), Adverse Reactions ( 6.2 ), and Drug Interactions ( 7 )]. Monitor patients for the development of hyperkalemia until the effect of eplerenone is established.
Patients who develop hyperkalemia (5.5 to 5.9 mEq/L) may continue eplerenone therapy with proper dose adjustment. Dose reduction decreases potassium levels. Patients on moderate CYP3A inhibitors that cannot be avoided should have their dose of eplerenone reduced [see Drug Interactions ( 7.2 )].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: • Hyperkalemia [see Warnings and Precautions ( 5.1 )] HFrEF Post-MI: Most common adverse reactions (>2% and more frequent than with placebo): hyperkalemia and increased creatinine. ( 6.1 ) Hypertension: In clinical studies, adverse reactions with eplerenone tablets were uncommon. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Annora Pharma Private Limited at 1-866-495-1995 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in clinical trials of another drug and may not reflect the rates observed in practice. Heart Failure Post-Myocardial Infarction In EPHESUS, safety was evaluated in 3,307 patients treated with eplerenone and 3,301 placebo-treated patients. The overall incidence of adverse events reported with eplerenone (78.9%) was similar to placebo (79.5%).
Adverse events occurred at a similar rate regardless of age, gender, or race. Patients discontinued treatment due to an adverse event at similar rates in either treatment group (4.4% eplerenone vs. 4.3% placebo), with the most common reasons for discontinuation being hyperkalemia, MI, and abnormal renal function.
Adverse reactions that occurred more frequently in patients treated with eplerenone than placebo were hyperkalemia (3.4% vs. 2.0%) and increased creatinine (2.4% vs. 1.5%).
Discontinuations due to hyperkalemia or abnormal renal function were less than 1.0% in both groups. Hypertension Eplerenone has been evaluated for safety in 3,091 patients treated for hypertension. A total of 690 patients were treated for over 6 months and 106 patients were treated for over 1 year.
In placebo-controlled studies, the overall rates of adverse events were 47% with eplerenone and 45% with placebo. Adverse events occurred at a similar rate regardless of age, gender, or race. Therapy was discontinued due to an adverse event in 3% of patients treated with eplerenone and 3% of patients given placebo.
The most common reasons for discontinuation of eplerenone were headache, dizziness, angina pectoris/MI, and increased GGT. Gynecomastia and abnormal vaginal bleeding were reported with eplerenone but not with placebo. The rates increased with increasing duration of therapy.
6.2Postmarketing Experience The following adverse reactions have been identified during postapproval use of eplerenone. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Skin: angioneurotic edema, rash
6.3Clinical Laboratory Test Findings Heart Failure Post-Myocardial Infarction Creatinine: Increases of more than 0.5 mg/dL were reported for 6.5% of patients administered eplerenone and for 4.9% of placebo-treated patients. Potassium : In EPHESUS [see Clinical Studies ( 14.1 )], the frequencies of patients with changes in potassium (<3.5 mEq/L or >5.5 mEq/L or ≥6.0 mEq/L) receiving eplerenone compared with placebo are displayed in Table 2. Table 2.
Hypokalemia (<3.5 mEq/L) or Hyperkalemia (>5.5 or ≥6.0 mEq/L) in EPHESUS Potassium (mEq/L) Eplerenone (N=3,251) n (%) Placebo (N=3,237) n (%) <3.5 273 (8.4) 424 (13.1) >5.5 508 (15.6) 363 (11.2) ≥6.0 180 (5.5) 126 (3.9) Rates of hyperkalemia increased with decreasing renal function. Table 3. Rates of Hyperkalemia ( >5.5 mEq/L) in EPHESUS by Baseline Creatinine Clearance* Baseline Creatinine Clearance Eplerenone (N=508) n (%) Placebo (N=363) n (%) ≤30 mL/min 160 (32) 82 (23) 31 to 50 mL/min 122 (24) 46 (13) 51 to 70 mL/min 86 (17) 48 (13) >70 mL/min 56 (11) 32 (9) * Estimated using the Cockroft-Gault formula.
The rates of hyperkalemia in EPHESUS in the eplerenone treated group vs. placebo were increas… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • CYP3A Inhibitors: In post-MI HFrEF patients do not exceed 25 mg once daily when used with moderate CYP3A inhibitors (e.g., verapamil, erythromycin, saquinavir, fluconazole). In patients with hypertension initiate at 25 mg once daily. For inadequate blood pressure response, dosing may be increased to a maximum of 25 mg twice daily. ( 2.4 , 7.1 , 12.3 )
7.1CYP3A Inhibitors Eplerenone metabolism is predominantly mediated via CYP3A. Do not use eplerenone with drugs that are strong inhibitors of CYP3A [see Contraindications ( 4 ) and Clinical Pharmacology ( 12.3 )]. In post-MI HFrEF patients taking a moderate CYP3A inhibitor, do not exceed 25 mg once daily.
In patients with hypertension taking a moderate CYP3A inhibitor, initiate at 25 mg once daily. For inadequate blood pressure response, dosing may be increased to a maximum of 25 mg twice daily [see Dosage and Administration ( 2.3 , 2.4 ) and Clinical Pharmacology ( 12.3 )].
7.2ACE Inhibitors and Angiotensin II Receptor Antagonists The risk of hyperkalaemia increase when eplerenone is used in combination with an ACE inhibitor and/or an ARB. A close monitoring of serum potassium and renal function is recommended, especially in patients at risk for impaired renal function, e.g., the elderly [see Warnings and Precautions ( 5.1 )].
7.3Lithium A drug interaction study of eplerenone with lithium has not been conducted. Lithium toxicity has been reported in patients receiving lithium concomitantly with diuretics and ACE inhibitors. Serum lithium levels should be monitored frequently if eplerenone is administered concomitantly with lithium.
7.4Nonsteroidal Anti-Inflammatory Drugs (NSAIDs) A drug interaction study of eplerenone with an NSAID has not been conducted. The administration of other potassium-sparing antihypertensives with NSAIDs has been shown to reduce the antihypertensive effect in some patients and result in severe hyperkalemia in patients with impaired renal function. Therefore, when eplerenone and NSAIDs are used concomitantly, monitor blood pressure and serum potassium levels.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary The available data from published case reports on eplerenone use during pregnancy are insufficient to establish a drug-associated risk of major birth defects, miscarriage, adverse maternal or fetal outcomes (see Clinical Considerations) . In animal studies, no adverse developmental effects were observed when eplerenone was administered to pregnant rats and rabbits during organogenesis at exposures 32 and 31 times, respectively the human exposure at the 100 mg/day therapeutic dose. The estimated background risk of major birth defects and miscarriage for the indicated population are unknown.
In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death.
Pregnant women with hypertension should be carefully monitored and managed accordingly. Pregnant women with heart failure are at increased risk for preterm birth. Stroke volume and heart rate increase during pregnancy, increasing cardiac output, especially during the first trimester.
Clinical classification of heart disease may worsen with pregnancy and lead to maternal death. Closely monitor pregnant patients for destabilization of their heart failure. Data Animal Data Embryo-fetal development studies were conducted with doses up to 1000 mg/kg/day in rats and 300 mg/kg/day in rabbits (exposures up to 32 and 31 times the human AUC for the 100 mg/day therapeutic dose, respectively) administered during organogenesis.
No teratogenic effects were seen in rats or rabbits, although decreased rat fetal weights were observed, and decreased body weight in maternal rabbits and increased rabbit fetal resorptions and post-implantation loss were observed at the highest administered dosages. In a pre-and postnatal development study pregnant rats were administered eplerenone at doses up to 1000 mg/kg/day from Gestation Day 6 through Lactation Day 20. Decreased pup weights were observed beginning at birth at 1000 mg/kg/day.
8.2Lactation Risk Summary There are no human data available on whether eplerenone is present in human milk, or has effects on breastfed infants or on milk production. Eplerenone was present in the milk of lactating rats. When a drug is present in animal milk, it is likely that the drug will be present in human milk.
8.3Females and Males of Reproductive Potential Infertility Based on animal data, use of eplerenone may compromise male fertility. In mature rats, male fertility was decreased with eplerenone exposure at 17 times the 100 mg/day human therapeutic dose. Reversibility of effects was not evaluated [see Nonclinical Toxicology ( 13.1 )].
8.4Pediatric Use In a 10-week study of 304 hypertensive pediatric patients age 4 to 16 years treated with eplerenone up to 100 mg per day, doses that produced exposure similar to that in adults, eplerenone did not lower blood pressure effectively. In this study and in a 1-year pediatric safety study in 149 patients (age range 5 to 17 years), the incidence of reported adverse events was similar to that of adults. Eplerenone has not been studied in hypertensive patients less than 4 years old because the study in older pediatric patients did not demonstrate effectiveness.
Eplerenone has not been studied in pediatric patients with heart failure.
8.5Geriatric Use Heart Failure Post-Myocardial Infarction Of the total number of patients in EPHESUS, 3,340 (50%) were 65 and over, while 1,326 (20%) were 75 and over. Patients greater than 75 years did not appear to benefit from the use of eplerenone [see… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The available data from published case reports on eplerenone use during pregnancy are insufficient to establish a drug-associated risk of major birth defects, miscarriage, adverse maternal or fetal outcomes (see Clinical Considerations) . In animal studies, no adverse developmental effects were observed when eplerenone was administered to pregnant rats and rabbits during organogenesis at exposures 32 and 31 times, respectively the human exposure at the 100 mg/day therapeutic dose. The estimated background risk of major birth defects and miscarriage for the indicated population are unknown.
In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death.
Pregnant women with hypertension should be carefully monitored and managed accordingly. Pregnant women with heart failure are at increased risk for preterm birth. Stroke volume and heart rate increase during pregnancy, increasing cardiac output, especially during the first trimester.
Clinical classification of heart disease may worsen with pregnancy and lead to maternal death. Closely monitor pregnant patients for destabilization of their heart failure. Data Animal Data Embryo-fetal development studies were conducted with doses up to 1000 mg/kg/day in rats and 300 mg/kg/day in rabbits (exposures up to 32 and 31 times the human AUC for the 100 mg/day therapeutic dose, respectively) administered during organogenesis.
No teratogenic effects were seen in rats or rabbits, although decreased rat fetal weights were observed, and decreased body weight in maternal rabbits and increased rabbit fetal resorptions and post-implantation loss were observed at the highest administered dosages. In a pre-and postnatal development study pregnant rats were administered eplerenone at doses up to 1000 mg/kg/day from Gestation Day 6 through Lactation Day 20. Decreased pup weights were observed beginning at birth at 1000 mg/kg/day.
🧒 Pediatric Use ▾
8.4Pediatric Use In a 10-week study of 304 hypertensive pediatric patients age 4 to 16 years treated with eplerenone up to 100 mg per day, doses that produced exposure similar to that in adults, eplerenone did not lower blood pressure effectively. In this study and in a 1-year pediatric safety study in 149 patients (age range 5 to 17 years), the incidence of reported adverse events was similar to that of adults. Eplerenone has not been studied in hypertensive patients less than 4 years old because the study in older pediatric patients did not demonstrate effectiveness.
Eplerenone has not been studied in pediatric patients with heart failure.
🧓 Geriatric Use ▾
8.5Geriatric Use Heart Failure Post-Myocardial Infarction Of the total number of patients in EPHESUS, 3,340 (50%) were 65 and over, while 1,326 (20%) were 75 and over. Patients greater than 75 years did not appear to benefit from the use of eplerenone [see Clinical Studies ( 14.1 )]. No differences in overall incidence of adverse events were observed between elderly and younger patients.
However, due to age-related decreases in creatinine clearance, the incidence of laboratory-documented hyperkalemia was increased in patients 65 and older [see Warnings and Precautions ( 5.1 )]. Hypertension Of the total number of subjects in clinical hypertension studies of eplerenone, 1,123 (23%) were 65 and over, while 212 (4%) were 75 and over. No overall differences in safety or effectiveness were observed between elderly subjects and younger subjects, however due to age-related decreases in creatine clearance, the risk of hyperkalemia may be increased [see Warnings and Precautions ( 5.1 )].
🆘 Overdosage ▾
10 OVERDOSAGE No cases of human overdosage with eplerenone have been reported. Lethality was not observed in mice, rats, or dogs after single oral doses that provided C max exposures at least 25 times higher than in humans receiving eplerenone 100 mg/day. Dogs showed emesis, salivation, and tremors at a C max 41 times the human therapeutic C max , progressing to sedation and convulsions at higher exposures.
The most likely manifestation of human overdosage would be anticipated to be hypotension or hyperkalemia. Eplerenone cannot be removed by hemodialysis. Eplerenone has been shown to bind extensively to charcoal.
If symptomatic hypotension should occur, supportive treatment should be instituted. If hyperkalemia develops, standard treatment should be initiated.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Eplerenone binds to the mineralocorticoid receptor and blocks the binding of aldosterone, a component of the renin-angiotensin-aldosterone-system (RAAS). Aldosterone synthesis, which occurs primarily in the adrenal gland, is modulated by multiple factors, including angiotensin II and non-RAAS mediators such as adrenocorticotropic hormone (ACTH) and potassium. Aldosterone binds to mineralocorticoid receptors in both epithelial (e.g., kidney) and nonepithelial (e.g., heart, blood vessels, and brain) tissues and increases blood pressure through induction of sodium reabsorption and possibly other mechanisms.
Eplerenone has been shown to produce sustained increases in plasma renin and serum aldosterone, consistent with inhibition of the negative regulatory feedback of aldosterone on renin secretion. The resulting increased plasma renin activity and aldosterone circulating levels do not overcome the effects of eplerenone. Eplerenone selectively binds to human mineralocorticoid receptors relative to its binding to recombinant human glucocorticoid, progesterone, and androgen receptors.
12.2Pharmacodynamics There was no significant change in average heart rate among patients treated with eplerenone in the combined clinical studies. No consistent effects of eplerenone on heart rate, QRS duration, or PR or QT interval were observed in 147 normal subjects evaluated for electrocardiographic changes during pharmacokinetic studies.
12.3Pharmacokinetics Eplerenone is cleared predominantly by cytochrome P450 (CYP) 3A4 metabolism, with an elimination half-life of 3 to 6 hours. Steady state is reached within 2 days. Absorption is not affected by food.
Inhibitors of CYP3A (e.g., ketoconazole, saquinavir) increase blood levels of eplerenone. Absorption and Distribution Mean peak plasma concentrations of eplerenone are reached approximately 1.5 to 2 hours following oral administration. Absorption is not affected by food.
The absolute bioavailability of eplerenone is 69% following administration of a 100 mg oral tablet. Both peak plasma levels (C max ) and area under the curve (AUC) are dose proportional for doses of 25 mg to 100 mg and less than proportional at doses above 100 mg. Upon repeat dosing, steady state levels are reached within 2 days.
The plasma protein binding of eplerenone is about 50% and it is primarily bound to alpha 1-acid glycoproteins. The apparent volume of distribution at steady state ranged from 42 to 90 L. Eplerenone does not preferentially bind to red blood cells.
Metabolism and Excretion Eplerenone metabolism is primarily mediated via CYP3A4. No active metabolites of eplerenone have been identified in human plasma. Less than 5% of an eplerenone dose is recovered as unchanged drug in the urine and feces.
Following a single oral dose of radiolabeled drug, approximately 32% of the dose was excreted in the feces and approximately 67% was excreted in the urine. The elimination half-life of eplerenone is approximately 3 to 6 hours. The apparent plasma clearance is approximately 10 L/hr.
Age, Gender, and Race The pharmacokinetics of eplerenone at a dose of 100 mg once daily has been investigated in the elderly (≥65 years), in males and females, and in Blacks. At steady state, elderly subjects had increases in C max (22%) and AUC (45%) compared with younger subjects (18 to 45 years). The pharmacokinetics of eplerenone did not differ significantly between males and females.
At steady state, C max was 19% lower and AUC was 26% lower in Blacks [see Dosage and Administration ( 2.4 ) and Use in Specific Populations ( 8.5 )]. Renal Impairment The pharmacokinetics of eplerenone was evaluated in patients with varying degrees of renal impairment and in patients undergoing hemodialysis. Compared with control subjects, steady state AUC and C max were increased by 38% and 24%, respectively, in patients with severe renal impairment and were decreased by 26% and 3%, respectively, in patients u… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Eplerenone binds to the mineralocorticoid receptor and blocks the binding of aldosterone, a component of the renin-angiotensin-aldosterone-system (RAAS). Aldosterone synthesis, which occurs primarily in the adrenal gland, is modulated by multiple factors, including angiotensin II and non-RAAS mediators such as adrenocorticotropic hormone (ACTH) and potassium. Aldosterone binds to mineralocorticoid receptors in both epithelial (e.g., kidney) and nonepithelial (e.g., heart, blood vessels, and brain) tissues and increases blood pressure through induction of sodium reabsorption and possibly other mechanisms.
Eplerenone has been shown to produce sustained increases in plasma renin and serum aldosterone, consistent with inhibition of the negative regulatory feedback of aldosterone on renin secretion. The resulting increased plasma renin activity and aldosterone circulating levels do not overcome the effects of eplerenone. Eplerenone selectively binds to human mineralocorticoid receptors relative to its binding to recombinant human glucocorticoid, progesterone, and androgen receptors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Eplerenone Tablets 25 mg are light yellow, round, biconvex, film coated tablets debossed with "V" on one side and "68" on the other side. Bottle of 30 NDC 31722-049-30 Bottle of 90 NDC 31722-049-90 Eplerenone Tablets 50 mg are light yellow, round, biconvex, film coated tablets debossed with "V" on one side and "67" on the other side. Bottle of 30 NDC 31722-050-30 Bottle of 90 NDC 31722-050-90 Store at 20 o to 25 o C (68 o to 77 o F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Eplerenone, a blocker of aldosterone binding at the mineralocorticoid receptor. Eplerenone is chemically described as (7α,11α,17α)-9,11-epoxy-17-hydroxy-3-oxopregn-4-ene-7,21-dicarboxylic acid-γ-lactone methyl ester. Its empirical formula is C 24 H 30 O 6 and it molecular weight of 414.5.
The structural formula of eplerenone is represented below: Eplerenone is a white, almost white (or) slightly yellow, crystalline powder and is soluble in methylene chloride. It’s pH is 5.82 (as it is 1% w/v aqueous suspension). Eplerenone tablets for oral administration contain 25 mg or 50 mg of eplerenone and the following inactive ingredients: croscarmellose sodium, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, sodium lauryl sulfate, talc.
The film-coating contains hypromellose, polyethylene glycol, polysorbate 80, red iron oxide, titanium dioxide, yellow iron oxide. eplerenonechemicalstrucyure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients receiving eplerenone: • Not to use potassium supplements or salt substitutes containing potassium without consulting the prescribing physician [see Warnings and Precautions ( 5.1 )]. • To call their physician if they experience dizziness, diarrhea, vomiting, rapid or irregular heartbeat, lower extremity edema, or difficulty breathing [see Warnings and Precautions ( 5.1 )]. Manufactured for: Camber Pharmaceuticals, Inc. Piscataway, NJ 08854 By: Annora Pharma Pvt.
Ltd. Sangareddy - 502313, Telangana, India Revised: 01/2023 camberlogo
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Eplerenone is cleared predominantly by cytochrome P450 (CYP) 3A4 metabolism, with an elimination half-life of 3 to 6 hours. Steady state is reached within 2 days. Absorption is not affected by food.
Inhibitors of CYP3A (e.g., ketoconazole, saquinavir) increase blood levels of eplerenone. Absorption and Distribution Mean peak plasma concentrations of eplerenone are reached approximately 1.5 to 2 hours following oral administration. Absorption is not affected by food.
The absolute bioavailability of eplerenone is 69% following administration of a 100 mg oral tablet. Both peak plasma levels (C max ) and area under the curve (AUC) are dose proportional for doses of 25 mg to 100 mg and less than proportional at doses above 100 mg. Upon repeat dosing, steady state levels are reached within 2 days.
The plasma protein binding of eplerenone is about 50% and it is primarily bound to alpha 1-acid glycoproteins. The apparent volume of distribution at steady state ranged from 42 to 90 L. Eplerenone does not preferentially bind to red blood cells.
Metabolism and Excretion Eplerenone metabolism is primarily mediated via CYP3A4. No active metabolites of eplerenone have been identified in human plasma. Less than 5% of an eplerenone dose is recovered as unchanged drug in the urine and feces.
Following a single oral dose of radiolabeled drug, approximately 32% of the dose was excreted in the feces and approximately 67% was excreted in the urine. The elimination half-life of eplerenone is approximately 3 to 6 hours. The apparent plasma clearance is approximately 10 L/hr.
Age, Gender, and Race The pharmacokinetics of eplerenone at a dose of 100 mg once daily has been investigated in the elderly (≥65 years), in males and females, and in Blacks. At steady state, elderly subjects had increases in C max (22%) and AUC (45%) compared with younger subjects (18 to 45 years). The pharmacokinetics of eplerenone did not differ significantly between males and females.
At steady state, C max was 19% lower and AUC was 26% lower in Blacks [see Dosage and Administration ( 2.4 ) and Use in Specific Populations ( 8.5 )]. Renal Impairment The pharmacokinetics of eplerenone was evaluated in patients with varying degrees of renal impairment and in patients undergoing hemodialysis. Compared with control subjects, steady state AUC and C max were increased by 38% and 24%, respectively, in patients with severe renal impairment and were decreased by 26% and 3%, respectively, in patients undergoing hemodialysis.
No correlation was observed between plasma clearance of eplerenone and creatinine clearance. Eplerenone is not removed by hemodialysis [see Warnings and Precautions ( 5.1 )]. Hepatic Impairment The pharmacokinetics of eplerenone 400 mg has been investigated in patients with moderate (Child-Pugh Class B) hepatic impairment and compared with normal subjects.
Steady state C max and AUC of eplerenone were increased by 3.6% and 42%, respectively. Heart Failure The pharmacokinetics of eplerenone 50 mg was evaluated in 8 patients with heart failure (NYHA classification II–IV) and 8 matched (gender, age, weight) healthy controls. Compared with the controls, steady state AUC and C max in patients with stable heart failure were 38% and 30% higher, respectively.
Drug-Drug Interactions Eplerenone is metabolized primarily by CYP3A4. Inhibitors of CYP3A cause increased exposure [see Drug Interactions ( 7.1 )]. Drug-drug interaction studies were conducted with a 100 mg dose of eplerenone.
Following a single dose of eplerenone 100 mg and CYP3A inhibitor ketoconazole 200 mg twice a day, eplerone's C max was 1.7-fold and AUC was 5.4-fold compared with eplerone alone. Administration of eplerenone with moderate CYP3A inhibitors (e.g., erythromycin 500 mg BID, verapamil 240 mg once daily, saquinavir 1200 mg three times a day, fluconazole 200 mg once daily) resulted in increases in C max of eplerenone ranging from 40% to 60% and AUC from 100% to 190%. Grapefruit jui… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics There was no significant change in average heart rate among patients treated with eplerenone in the combined clinical studies. No consistent effects of eplerenone on heart rate, QRS duration, or PR or QT interval were observed in 147 normal subjects evaluated for electrocardiographic changes during pharmacokinetic studies.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Heart Failure Post-Myocardial Infarction The eplerenone post-acute myocardial infarction heart failure efficacy and survival study (EPHESUS) was a multinational, multicenter, double-blind, randomized, placebo-controlled study in patients clinically stable 3 to 14 days after an acute MI with LV dysfunction (as measured by left ventricular ejection fraction [LVEF] ≤40%) and either diabetes or clinical evidence of HF (pulmonary congestion by exam or chest x-ray or S 3 ). Patients with HF of valvular or congenital etiology, patients with unstable post-infarct angina, and patients with serum potassium >5.0 mEq/L or serum creatinine >2.5 mg/dL were to be excluded.
Patients were allowed to receive standard post-MI drug therapy and to undergo revascularization by angioplasty or coronary artery bypass graft surgery. Patients randomized to eplerenone were given an initial dose of 25 mg once daily and titrated to the target dose of 50 mg once daily after 4 weeks if serum potassium was <5.0 mEq/L. Dosage was reduced or suspended anytime during the study if serum potassium levels were ≥5.5 mEq/L [see Dosage and Administration ( 2.1 )].
EPHESUS randomized 6,632 patients (9.3% U.S.) at 671 centers in 27 countries. The study population was primarily white (90%, with 1% Black, 1% Asian, 6% Hispanic, 2% other) and male (71%). The mean age was 64 years (range, 22 to 94 years).
The majority of patients had pulmonary congestion (75%) by exam or x-ray and were Killip Class II (64%). The mean ejection fraction was 33%. The average time to enrollment was 7 days post-MI.
Medical histories prior to the index MI included hypertension (60%), coronary artery disease (62%), dyslipidemia (48%), angina (41%), type 2 diabetes (30%), previous MI (27%), and HF (15%). The mean dose of eplerenone was 43 mg/day. Patients also received standard care including aspirin (92%), ACE inhibitors (90%), beta-blockers (83%), nitrates (72%), loop diuretics (66%), or HMG-CoA reductase inhibitors (60%).
Patients were followed for an average of 16 months (range, 0 to 33 months). The ascertainment rate for vital status was 99.7%. The co-primary endpoints for EPHESUS were (1) the time to death from any cause, and (2) the time to first occurrence of either cardiovascular mortality [defined as sudden cardiac death or death due to progression of HF, stroke, or other CV causes] or CV hospitalization (defined as hospitalization for progression of HF, ventricular arrhythmias, acute MI, or stroke).
For the co-primary endpoint for death from any cause, there were 478 deaths in the eplerenone group (14.4%) and 554 deaths in the placebo group (16.7%). The risk of death with eplerenone was reduced by 15% [hazard ratio equal to 0.85 (95% confidence interval 0.75 to 0.96; p = 0.008 by log rank test)]. Kaplan-Meier estimates of all-cause mortality are shown in Figure 1 and the components of mortality are provided in Table 5.
Figure 1. Kaplan-Meier Estimates of All-Cause Mortality Table 5. Components of All-Cause Mortality in EPHESUS Eplerenone (N=3,319) n (%) Placebo (N=3,313) n (%) Hazard Ratio p-value Death from any cause 478 (14.4) 554 (16.7) 0.85 0.008 CV Death 407 (12.3) 483 (14.6) 0.83 0.005 Non-CV Death 60 (1.8) 54 (1.6) Unknown or unwitnessed death 11 (0.3) 17 (0.5) Most CV deaths were attributed to sudden death, acute MI, and HF.
The time to first event for the co-primary endpoint of CV death or hospitalization, as defined above, was longer in the eplerenone group (hazard ratio 0.87, 95% confidence interval 0.79 to 0.95, p = 0.002). An analysis that included the time to first occurrence of CV mortality and all CV hospitalizations (atrial arrhythmia, angina, CV procedures, progression of HF, MI, stroke, ventricular arrhythmia, or other CV causes) showed a smaller effect with a hazard ratio of 0.92 (95% confidence interval 0.86 to 0.99; p = 0.028).
The combined endpoints, including combined all-cause hospitalization and mortality were driven primarily by CV mort… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Eplerenone was non-genotoxic in a battery of assays including in vitro bacterial mutagenesis (Ames test in Salmonella spp. and E. Coli ), in vitro mammalian cell mutagenesis (mouse lymphoma cells), in vitro chromosomal aberration (Chinese hamster ovary cells), in vivo rat bone marrow micronucleus formation, and in vivo/ex vivo unscheduled DNA synthesis in rat liver. There was no drug-related tumor response in heterozygous P53 deficient mice when tested for 6 months at dosages up to 1000 mg/kg/day (systemic AUC exposures up to 9 times the exposure in humans receiving the 100 mg/day therapeutic dose).
Statistically significant increases in benign thyroid tumors were observed after 2 years in both male and female rats when administered eplerenone 250 mg/kg/day (highest dose tested) and in male rats only at 75 mg/kg/day. These dosages provided systemic AUC exposures approximately 2 to 12 times higher than the average human therapeutic exposure at 100 mg/day. Repeat dose administration of eplerenone to rats increases the hepatic conjugation and clearance of thyroxin, which results in increased levels of TSH by a compensatory mechanism.
Drugs that have produced thyroid tumors by this rodent-specific mechanism have not shown a similar effect in humans. Male rats treated with eplerenone at 1000 mg/kg/day for 10 weeks (AUC 17 times that at the 100 mg/day human therapeutic dose) had decreased weights of seminal vesicles and epididymides and slightly decreased fertility. Dogs administered eplerenone at dosages of 15 mg/kg/day and higher (AUC 5 times that at the 100 mg/day human therapeutic dose) had dose-related prostate atrophy.
The prostate atrophy was reversible after daily treatment for 1 year at 100 mg/kg/day. Dogs with prostate atrophy showed no decline in libido, sexual performance, or semen quality. Testicular weight and histology were not affected by eplerenone in any test animal species at any dosage.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Eplerenone Tablets 25mg 30's Container label Eplerenone Tablets 50 mg 30's Container label eplerenonetablets25mg30scontainerlabel eplerenonetablets50mg30scontainerlabel.