
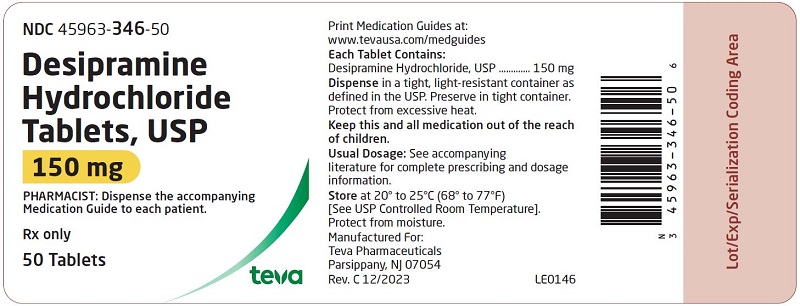
Desipramine Hydrochloride 150 mg Tablet, Film Coated, 50-count
Other active recalls for Desipramine Hydrochloride (different manufacturers) — 6 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Tricyclic Antidepressant class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Desipramine is used to treat depression. Desipramine is in a class of medications called tricyclic antidepressants. It works by increasing the amounts of certain natural substances in the brain that are needed for mental balance.
Read the full MedlinePlus article ↗- Desipramine is prescribed to treat depression. It's been around for decades and belongs to a group of older antidepressants called tricyclics. Brands you might see include Norprami...
- Some people notice small improvements within 2 to 5 days, but for most people the full benefit takes about 2 to 3 weeks. It's important not to stop taking it early just because you...
- How long does it take before I start feeling better?
- Common side effects include dry mouth, drowsiness, dizziness, constipation, and blurred vision — these often ease as your body adjusts. Call your doctor right away if you notice ch...
Patient education
Supplement & herbal interactions
Desipramine may be associated with lower levels of 3 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.832 | $41.59 / 50 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3132 | $15.66 / 50 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Desipramine Hydrochloride 150 mg 62135-0599-30 | Chartwell | 30 tablets | $0.671 | — | Availability likely | save 19% |
| Desipramine Hydrochloride 150 mgthis 45963-0346-50 | Actavis | 50 tablets | $0.832 | AB | Availability likely | — |
| Desipramine Hydrochloride 150 mg 50742-0117-50 | Ingenus | 50 tablets | $0.832 | AB | Availability likely | — |
| Desipramine Hydrochloride 150 mg 69238-1063-02 | Amneal | 50 tablets | $0.832 | AB | Availability likely | — |
| Norpramin 150 mg 30698-0021-50 | Validus | 50 tablets | — | — | FDA listed | — |
| Desipramine Hydrochloride 150 mg 46708-0320-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Desipramine Hydrochloride 150 mg 62332-0320-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 45963-0346-50 You're viewing this | 50 TABLET, FILM COATED in 1 BOTTLE (45963-346-50) | 2006-05-09 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
Suicidality and Antidepressant Drugs Antidepressants increased the risk compared to placebo of suicidal thinking and behavior (suicidality) in children, adolescents, and young adults in short-term studies of major depressive disorder (MDD) and other psychiatric disorders. Anyone considering the use of desipramine hydrochloride or any other antidepressant in a child, adolescent, or young adult must balance this risk with the clinical need. Short-term studies did not show an increase in the risk of suicidality with antidepressants compared to placebo in adults beyond age 24; there was a reduction in risk with antidepressants compared to placebo in adults aged 65 and older.
Depression and certain other psychiatric disorders are themselves associated with increases in the risk of suicide. Patients of all ages who are started on antidepressant therapy should be monitored appropriately and observed closely for clinical worsening, suicidality, or unusual changes in behavior. Families and caregivers should be advised of the need for close observation and communication with the prescriber.
Desipramine hydrochloride is not approved for use in pediatric patients (see WARNINGS : Clinical Worsening and Suicide Risk, PRECAUTIONS : Information for Patients, and PRECAUTIONS : Pediatric Use .)
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Desipramine hydrochloride tablets are indicated for the treatment of depression.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Not recommended for use in children (see WARNINGS ). Lower dosages are recommended for elderly patients and adolescents. Lower dosages are also recommended for outpatients compared to hospitalized patients, who are closely supervised.
Dosage should be initiated at a low level and increased according to clinical response and any evidence of intolerance. Following remission, maintenance medication may be required for a period of time and should be at the lowest dose that will maintain remission. Usual Adult Dose The usual adult dose is 100 mg to 200 mg per day.
In more severely ill patients, dosage may be further increased gradually to 300 mg/day if necessary. Dosages above 300 mg/day are not recommended. Dosage should be initiated at a lower level and increased according to tolerance and clinical response.
Treatment of patients requiring as much as 300 mg should generally be initiated in hospitals, where regular visits by the physician, skilled nursing care, and frequent electrocardiograms (ECGs) are available. The best available evidence of impending toxicity from very high doses of desipramine is prolongation of the QRS or QT intervals on the ECG. Prolongation of the PR interval is also significant, but less closely correlated with plasma levels.
Clinical symptoms of intolerance, especially drowsiness, dizziness, and postural hypotension, should also alert the physician to the need for reduction in dosage. Initial therapy may be administered in divided doses or a single daily dose. Maintenance therapy may be given on a once-daily schedule for patient convenience and compliance.
Adolescent and Geriatric Dose The usual adolescent and geriatric dose is 25 mg to 100 mg daily. Dosage should be initiated at a lower level and increased according to tolerance and clinical response to a usual maximum of 100 mg daily. In more severely ill patients, dosage may be further increased to 150 mg/day.
Doses above 150 mg/day are not recommended in these age groups. Initial therapy may be administered in divided doses or a single daily dose. Maintenance therapy may be given on a once-daily schedule for patient convenience and compliance.
Switching a Patient To or From a Monoamine Oxidase Inhibitor (MAOI) Intended to Treat Psychiatric Disorders : At least 14 days should elapse between discontinuation of an MAOI intended to treat psychiatric disorders and initiation of therapy with desipramine hydrochloride. Conversely, at least 14 days should be allowed after stopping desipramine hydrochloride before starting an MAOI intended to treat psychiatric disorders (see CONTRAINDICATIONS ). Use of Desipramine Hydrochloride With Other MAOI’s Such as Linezolid or Methylene Blue: Do not start desipramine hydrochloride in a patient who is being treated with linezolid or intravenous methylene blue because there is increased risk of serotonin syndrome.
In a patient who requires more urgent treatment of a psychiatric condition, other interventions, including hospitalization, should be considered (see CONTRAINDICATIONS ). In some cases, a patient already receiving desipramine hydrochloride therapy may require urgent treatment with linezolid or intravenous methylene blue. If acceptable alternatives to linezolid or intravenous methylene blue treatment are not available and the potential benefits of linezolid or intravenous methylene blue treatment are judged to outweigh the risks of serotonin syndrome in a particular patient, desipramine hydrochloride should be stopped promptly, and linezolid or intravenous methylene blue can be administered.
The patient should be monitored for symptoms of serotonin syndrome for 2 weeks or until 24 hours after the last dose of linezolid or intravenous methylene blue, whichever comes first. Therapy with desipramine hydrochloride may be resumed 24 hours after the last dose of linezolid or intravenous methylene blue (see WARNINGS ). The risk of administering methylene blue by non-intravenous routes (such as…
⛔ Contraindications ▾
CONTRAINDICATIONS The use of MAOIs intended to treat psychiatric disorders with desipramine hydrochloride or within 14 days of stopping treatment with desipramine hydrochloride is contraindicated because of an increased risk of serotonin syndrome. The use of desipramine hydrochloride within 14 days of stopping an MAOI intended to treat psychiatric disorders is also contraindicated (see WARNINGS and DOSAGE AND ADMINISTRATION ). Starting desipramine hydrochloride in a patient who is being treated with MAOIs such as linezolid or intravenous methylene blue is also contraindicated because of an increased risk of serotonin syndrome (see WARNINGS and DOSAGE AND ADMINISTRATION ).
Desipramine hydrochloride is contraindicated in the acute recovery period following myocardial infarction. It should not be used in those who have shown prior hypersensitivity to the drug. Cross-sensitivity between this and other dibenzazepines is a possibility.
⚠️ Warnings and Cautions ▾
WARNINGS Clinical Worsening and Suicide Risk Patients with major depressive disorder (MDD), both adult and pediatric, may experience worsening of their depression and/or the emergence of suicidal ideation and behavior (suicidality) or unusual changes in behavior, whether or not they are taking antidepressant medications, and this risk may persist until significant remission occurs. Suicide is a known risk of depression and certain other psychiatric disorders, and these disorders themselves are the strongest predictors of suicide.
There has been a long-standing concern, however, that antidepressants may have a role in inducing worsening of depression and the emergence of suicidality in certain patients during the early phases of treatment. Pooled analyses of short-term placebo-controlled trials of antidepressant drugs (selective serotonin re-uptake inhibitors [SSRIs] and others) showed that these drugs increase the risk of suicidal thinking and behavior (suicidality) in children, adolescents, and young adults (ages 18 to 24) with major depressive disorder (MDD) and other psychiatric disorders.
Short-term studies did not show an increase in the risk of suicidality with antidepressants compared to placebo in adults beyond age 24; there was a reduction with antidepressants compared to placebo in adults aged 65 and older. The pooled analyses of placebo-controlled trials in children and adolescents with MDD, obsessive compulsive disorder (OCD), or other psychiatric disorders included a total of 24 short-term trials of 9 antidepressant drugs in over 4400 patients. The pooled analyses of placebo-controlled trials in adults with MDD or other psychiatric disorders included a total of 295 short-term trials (median duration of 2 months) of 11 antidepressant drugs in over 77,000 patients.
There was considerable variation in risk of suicidality among drugs, but a tendency toward an increase in the younger patients for almost all drugs studied. There were differences in absolute risk of suicidality across the different indications, with the highest incidence in MDD. The risk differences (drug vs. placebo), however, were relatively stable within age strata and across indications.
These risk differences (drug-placebo difference in the number of cases of suicidality per 1000 patients treated) are provided in Table 1. Table 1 Age Range Drug-Placebo Difference in Number of Cases of Suicidality per 1000 Patients Treated Increases Compared to Placebo <18 14 additional cases 18 to 24 5 additional cases Decreases Compared to Placebo 25 to 64 1 fewer case ≥65 6 fewer cases No suicides occurred in any of the pediatric trials. There were suicides in the adult trials, but the number was not sufficient to reach any conclusion about drug effect on suicide.
It is unknown whether the suicidality risk extends to longer-term use, i.e., beyond several months. However, there is substantial evidence from placebo-controlled maintenance trials in adults with depression that the use of antidepressants can delay the recurrence of depression. All patients being treated with antidepressants for any indication should be monitored appropriately and observed closely for clinical worsening, suicidality, and unusual changes in behavior, especially during the initial few months of a course of drug therapy, or at times of dose changes, either increases or decreases.
The following symptoms, anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania, and mania, have been reported in adult and pediatric patients being treated with antidepressants for major depressive disorder as well as for other indications, both psychiatric and nonpsychiatric. Although a causal link between the emergence of such symptoms and either the worsening of depression and/or the emergence of suicidal impulses has not been established, there is concern that such symptoms may represent precursors to emerging suicidali…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Included in the following listing are a few adverse reactions that have not been reported with this specific drug. However, the pharmacologic similarities among the tricyclic antidepressant drugs require that each of the reactions be considered when desipramine hydrochloride is given. Cardiovascular: Hypotension, hypertension, palpitations, heart block, myocardial infarction, stroke, arrhythmias, premature ventricular contractions, tachycardia, ventricular tachycardia, ventricular fibrillation, sudden death There has been a report of an “acute collapse” and “sudden death” in an 8-year-old (18 kg) male, treated for 2 years for hyperactivity.
There have been additional reports of sudden death in children (see PRECAUTIONS - Pediatric Use ) . Psychiatric: Confusional states (especially in the elderly) with hallucinations, disorientation, delusions; anxiety, restlessness, agitation; insomnia and nightmares; hypomania; exacerbation of psychosis Neurologic: Numbness, tingling, paresthesias of extremities; incoordination, ataxia, tremors; peripheral neuropathy; extrapyramidal symptoms; seizures; alterations in EEG patterns; tinnitus. Symptoms attributed to Neuroleptic Malignant Syndrome have been reported during desipramine use with and without concomitant neuroleptic therapy.
Anticholinergic: Dry mouth, and rarely associated sublingual adenitis; blurred vision, disturbance of accommodation, mydriasis, increased intraocular pressure; constipation, paralytic ileus; urinary retention, delayed micturition, dilation of urinary tract Allergic: Skin rash, petechiae, urticaria, itching, photosensitization (avoid excessive exposure to sunlight), edema (of face and tongue or general), drug fever, cross-sensitivity with other tricyclic drugs Hematologic: Bone marrow depressions including agranulocytosis, eosinophilia, purpura, thrombocytopenia Gastrointestinal: Anorexia, nausea and vomiting, epigastric distress, peculiar taste, abdominal cramps, diarrhea, stomatitis, black tongue, hepatitis, jaundice (simulating obstructive), altered liver function, elevated liver function tests, increased pancreatic enzymes Endocrine: Gynecomastia in the male, breast enlargement and galactorrhea in the female; increased or decreased libido, impotence, painful ejaculation, testicular swelling; elevation or depression of blood sugar levels; syndrome of inappropriate antidiuretic hormone secretion (SIADH) Other: Weight gain or loss; perspiration, flushing; urinary frequency, nocturia; parotid swelling; drowsiness, dizziness, proneness to falling, weakness and fatigue, headache; fever; alopecia; elevated alkaline phosphatase, hyponatremia.
Withdrawal Symptoms: Though not indicative of addiction, abrupt cessation of treatment after prolonged therapy may produce nausea, headache, and malaise. To report SUSPECTED ADVERSE REACTIONS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
🆘 Overdosage ▾
OVERDOSAGE Deaths may occur from overdosage with this class of drugs. Overdose of desipramine has resulted in a higher death rate compared to overdoses of other tricyclic antidepressants. Multiple drug ingestion (including alcohol) is common in deliberate tricyclic antidepressant overdose.
As the management is complex and changing, it is recommended that the physician contact a poison control center for current information on treatment. Signs and symptoms of toxicity develop rapidly after tricyclic antidepressant overdose; therefore, hospital monitoring is required as soon as possible. There is no specific antidote for desipramine overdosage.
Oral LD 50 The oral LD 50 of desipramine is 290 mg/kg in male mice and 320 mg/kg in female rats. Manifestations of Overdosage Critical manifestations of overdose include: cardiac dysrhythmias, severe hypotension, convulsions, and CNS depression, including coma. Changes in the electrocardiogram, particularly in QRS axis or width, are clinically significant indicators of tricyclic antidepressant toxicity.
Early changes in the QRS complex include a widening of the terminal 40 msec with a rightward axis in the frontal plane, recognized by the presence of a terminal S wave in Lead 1 and AVL and an R wave in AVR. Other signs of overdose may include: confusion, disturbed concentration, transient visual hallucinations, dilated pupils, agitation, hyperactive reflexes, stupor, drowsiness, muscle rigidity, vomiting, hypothermia, hyperpyrexia, or any of the symptoms listed under ADVERSE REACTIONS . Management Aggressive supportive care and serum alkalinization are the mainstays of therapy.
General Obtain an ECG and immediately initiate cardiac monitoring. Protect the patient’s airway, establish an intravenous line, and initiate gastric decontamination. A minimum of 6 hours of observation with cardiac monitoring and observation for signs of CNS or respiratory depression, hypotension, cardiac dysrhythmias and/or conduction blocks, and seizures is necessary.
If signs of toxicity occur at any time during this period, extended monitoring is required. Follow ECG, renal function, CPK, and arterial blood gases as clinically indicated. There are case reports of patients succumbing to fatal dysrhythmias late after overdose; these patients had clinical evidence of significant poisoning prior to death, and most received inadequate gastrointestinal decontamination.
Monitoring of plasma drug levels should not guide management of the patient. Gastrointestinal Decontamination Emesis is contraindicated. Activated charcoal should be administered to patients who present early after an overdose.
Cardiovascular A maximal limb-lead QRS duration widening to greater than 100 msec is a significant indicator of toxicity, specifically for the risk of seizures and, eventually, cardiac dysrhythmias. Serum alkalinization with intravenous sodium bicarbonate and hyperventilation (as needed) should be instituted in patients manifesting significant toxicity such as QRS widening. Dysrhythmias despite adequate alkalemia may respond to overdrive pacing, beta-agonist infusions, and magnesium therapy.
Type 1A and 1C antiarrhythmics are generally contraindicated (e.g., quinidine, disopyramide, and procainamide). CNS In patients with CNS depression, early intubation is advised because of the potential for abrupt deterioration. Seizures should be controlled with benzodiazepines.
If these are ineffective or seizures recur, other anticonvulsants (e.g., phenobarbital, propofol) may be used. Psychiatric Follow-up Since overdosage is often deliberate, patients may attempt suicide by other means during the recovery phase. Psychiatric referral may be appropriate.
Pediatric Management The principles of management of child and adult overdosages are similar. It is strongly recommended that the physician contact the local poison control center for specific pediatric treatment.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Available evidence suggests that many depressions have a biochemical basis in the form of a relative deficiency of neurotransmitters such as norepinephrine and serotonin. Norepinephrine deficiency may be associated with relatively low urinary 3-methoxy-4-hydroxyphenyl glycol (MHPG) levels, while serotonin deficiencies may be associated with low spinal fluid levels of 5-hydroxyindoleacetic acid. While the precise mechanism of action of the tricyclic antidepressants is unknown, a leading theory suggests that they restore normal levels of neurotransmitters by blocking the re-uptake of these substances from the synapse in the central nervous system.
Evidence indicates that the secondary amine tricyclic antidepressants, including desipramine hydrochloride, may have greater activity in blocking the re-uptake of norepinephrine. Tertiary amine tricyclic antidepressants, such as amitriptyline, may have greater effect on serotonin re-uptake. Desipramine hydrochloride is not a monoamine oxidase inhibitor (MAOI) and does not act primarily as a central nervous system stimulant.
It has been found in some studies to have a more rapid onset of action than imipramine. Earliest therapeutic effects may occasionally be seen in 2 to 5 days, but full treatment benefit usually requires 2 to 3 weeks to obtain. Metabolism Tricyclic antidepressants, such as desipramine hydrochloride, are rapidly absorbed from the gastrointestinal tract.
Tricyclic antidepressants or their metabolites are to some extent excreted through the gastric mucosa and reabsorbed from the gastrointestinal tract. Desipramine is metabolized in the liver, and approximately 70% is excreted in the urine. The rate of metabolism of tricyclic antidepressants varies widely from individual to individual, chiefly on a genetically determined basis.
Up to a 36-fold difference in plasma level may be noted among individuals taking the same oral dose of desipramine. The ratio of 2-hydroxydesipramine to desipramine may be increased in the elderly, most likely due to decreased renal elimination with aging. Certain drugs, particularly the psychostimulants and the phenothiazines, increase plasma levels of concomitantly administered tricyclic antidepressants through competition for the same metabolic enzyme systems.
Concurrent administration of cimetidine and tricyclic antidepressants can produce clinically significant increases in the plasma concentrations of the tricyclic antidepressants. Conversely, decreases in plasma levels of the tricyclic antidepressants have been reported upon discontinuation of cimetidine, which may result in the loss of the therapeutic efficacy of the tricyclic antidepressant. Other substances, particularly barbiturates and alcohol, induce liver enzyme activity and thereby reduce tricyclic antidepressant plasma levels.
Similar effects have been reported with tobacco smoke. Research on the relationship of plasma level to therapeutic response with the tricyclic antidepressants has produced conflicting results. While some studies report no correlation, many studies cite therapeutic levels for most tricyclics in the range of 50 to 300 nanograms per milliliter.
The therapeutic range is different for each tricyclic antidepressant. For desipramine, an optimal range of therapeutic plasma levels has not been established.
🧬 Mechanism of Action ▾
Mechanism of Action Available evidence suggests that many depressions have a biochemical basis in the form of a relative deficiency of neurotransmitters such as norepinephrine and serotonin. Norepinephrine deficiency may be associated with relatively low urinary 3-methoxy-4-hydroxyphenyl glycol (MHPG) levels, while serotonin deficiencies may be associated with low spinal fluid levels of 5-hydroxyindoleacetic acid. While the precise mechanism of action of the tricyclic antidepressants is unknown, a leading theory suggests that they restore normal levels of neurotransmitters by blocking the re-uptake of these substances from the synapse in the central nervous system.
Evidence indicates that the secondary amine tricyclic antidepressants, including desipramine hydrochloride, may have greater activity in blocking the re-uptake of norepinephrine. Tertiary amine tricyclic antidepressants, such as amitriptyline, may have greater effect on serotonin re-uptake. Desipramine hydrochloride is not a monoamine oxidase inhibitor (MAOI) and does not act primarily as a central nervous system stimulant.
It has been found in some studies to have a more rapid onset of action than imipramine. Earliest therapeutic effects may occasionally be seen in 2 to 5 days, but full treatment benefit usually requires 2 to 3 weeks to obtain. Metabolism Tricyclic antidepressants, such as desipramine hydrochloride, are rapidly absorbed from the gastrointestinal tract.
Tricyclic antidepressants or their metabolites are to some extent excreted through the gastric mucosa and reabsorbed from the gastrointestinal tract. Desipramine is metabolized in the liver, and approximately 70% is excreted in the urine. The rate of metabolism of tricyclic antidepressants varies widely from individual to individual, chiefly on a genetically determined basis.
Up to a 36-fold difference in plasma level may be noted among individuals taking the same oral dose of desipramine. The ratio of 2-hydroxydesipramine to desipramine may be increased in the elderly, most likely due to decreased renal elimination with aging. Certain drugs, particularly the psychostimulants and the phenothiazines, increase plasma levels of concomitantly administered tricyclic antidepressants through competition for the same metabolic enzyme systems.
Concurrent administration of cimetidine and tricyclic antidepressants can produce clinically significant increases in the plasma concentrations of the tricyclic antidepressants. Conversely, decreases in plasma levels of the tricyclic antidepressants have been reported upon discontinuation of cimetidine, which may result in the loss of the therapeutic efficacy of the tricyclic antidepressant. Other substances, particularly barbiturates and alcohol, induce liver enzyme activity and thereby reduce tricyclic antidepressant plasma levels.
Similar effects have been reported with tobacco smoke. Research on the relationship of plasma level to therapeutic response with the tricyclic antidepressants has produced conflicting results. While some studies report no correlation, many studies cite therapeutic levels for most tricyclics in the range of 50 to 300 nanograms per milliliter.
The therapeutic range is different for each tricyclic antidepressant. For desipramine, an optimal range of therapeutic plasma levels has not been established.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED: Desipramine hydrochloride tablets, USP are supplied as follows: 10 mg – Each white to off-white, round, biconvex with flat edge, film-coated tablet, debossed with over 341 on one side and plain on the other side. Tablets are supplied in bottles of 100 (NDC 45963-341-02) with a non-child resistant closure. 25 mg – Each light blue, round, biconvex with flat edge, film-coated tablet, debossed with over 342 on one side and plain on the other side.
Tablets are supplied in bottles of 100 (NDC 45963-342-02) with a non-child resistant closure. 50 mg - Each blue, round, biconvex with flat edge, film-coated tablet, debossed with over 343 on one side and plain on the other side. Tablets are supplied in bottles of 100 (NDC 45963-343-02) with a non-child resistant closure.
75 mg – Each light blue, round, biconvex with flat edge, film-coated tablet, debossed with over 344 on one side and plain on the other side. Tablets are supplied in bottles of 100 (NDC 45963-344-02) with a non-child resistant closure. 100 mg – Each blue, round, biconvex with flat edge, film-coated tablet, debossed with over 345 on one side and plain on the other side.
Tablets are supplied in bottles of 100 (NDC 45963-345-02) with a non-child resistant closure. 150 mg – Each white to off-white, round, biconvex with flat edge, film-coated tablet, debossed with over 346 on one side and plain on the other side. Tablets are supplied in bottles of 50 (NDC 45963-346-50) with a non-child resistant closure.
Dispense in a tight, light-resistant container as defined in the USP. Preserve in tight container. Protect from excessive heat.
Storage: Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Protect from moisture. Rx Only Manufactured For: Teva Pharmaceuticals Parsippany, NJ 07054 Rev.
D 7/2025 9d202fae-figure-02 9d202fae-figure-03 9d202fae-figure-04 9d202fae-figure-05 9d202fae-figure-06 9d202fae-figure-07
📋 Description ▾
DESCRIPTION Desipramine hydrochloride, USP is an antidepressant drug of the tricyclic type, and is chemically: 5 H -Dibenz[ b,f ]azepine-5-propanamine,10,11-dihydro- N -methyl-, monohydrochloride. Inactive Ingredients The following inactive ingredients are contained in all dosage strengths: croscarmellose sodium, hypromellose, anhydrous lactose, magnesium stearate, polyethylene glycol, polysorbate 80, povidone, sodium lauryl sulfate and titanium dioxide. The 25 mg, 50 mg, 75 mg, and 100 mg tablets also contain FD&C Blue No.
1 Aluminum Lake. 9d202fae-figure-01
💬 Medication Guide ▾
MEDICATION GUIDE Desipramine Hydrochloride ( des ip′ ra meen hye′′ droe klor′ ide ) Tablets Antidepressant Medicines, Depression and other Serious Mental Illnesses, and Suicidal Thoughts or Actions Read the Medication Guide that comes with your or your family member’s, antidepressant medicine. This Medication Guide is only about the risk of suicidal thoughts and actions with antidepressant medicines. Talk to your or your family member’s, healthcare provider about: all risks and benefits of treatment with antidepressant medicines all treatment choices for depression or other serious mental illness What is the most important information I should know about antidepressant medicines, depression and other serious mental illnesses, and suicidal thoughts or actions?
Antidepressant medicines may increase suicidal thoughts or actions in some children, teenagers, and young adults within the first few months of treatment. Depression and other serious mental illnesses are the most important causes of suicidal thoughts and actions. Some people may have a particularly high risk of having suicidal thoughts or actions.
These include people who have (or have a family history of) bipolar illness (also called manic-depressive illness) or suicidal thoughts or actions. How can I watch for and try to prevent suicidal thoughts and actions in myself or a family member? Pay close attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings.
This is very important when an antidepressant medicine is started or when the dose is changed. Call the healthcare provider right away to report new or sudden changes in mood, behavior, thoughts, or feelings. Keep all follow-up visits with the healthcare provider as scheduled.
Call the healthcare provider between visits as needed, especially if you have concerns about symptoms. Who should not take desipramine hydrochloride tablets? You should not take desipramine hydrochloride tablets if you take a monoamine oxidase inhibitor (MAOI).
Ask your healthcare provider or pharmacist if you are not sure if you take an MAOI, including the antibiotic linezolid. Do not take an MAOI within 2 weeks of stopping desipramine hydrochloride tablets unless directed to do so by your physician. Do not start desipramine hydrochloride tablets if you stopped taking an MAOI in the last 2 weeks unless directed to do so by your physician.
Call a healthcare provider right away if you or your family member has any of the following symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling very agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood Low salt (sodium) levels in the blood.
Elderly people may be at greater risk for this. Symptoms may include: headache weakness or feeling unsteady confusion, problems concentrating or thinking or memory problems Visual Problems eye pain changes in vision swelling or redness in or around the eye Only some people are at risk for these problems. You may want to undergo an eye examination to see if you are at risk and receive preventative treatment if you are.
What else do I need to know about antidepressant medicines? Never stop an antidepressant medicine without first talking to a healthcare provider. Stopping an antidepressant medicine suddenly can cause other symptoms.
Antidepressants are medicines used to treat depression and other illnesses. It is important to discuss all the risks of treating depression and also the risks of not treating it. Patients and their families or other caregivers should discuss all treatment choices with the healthcare provider, not just the use of antidepressants.
Antidepressant medicines have other side effects. Talk to the health…