
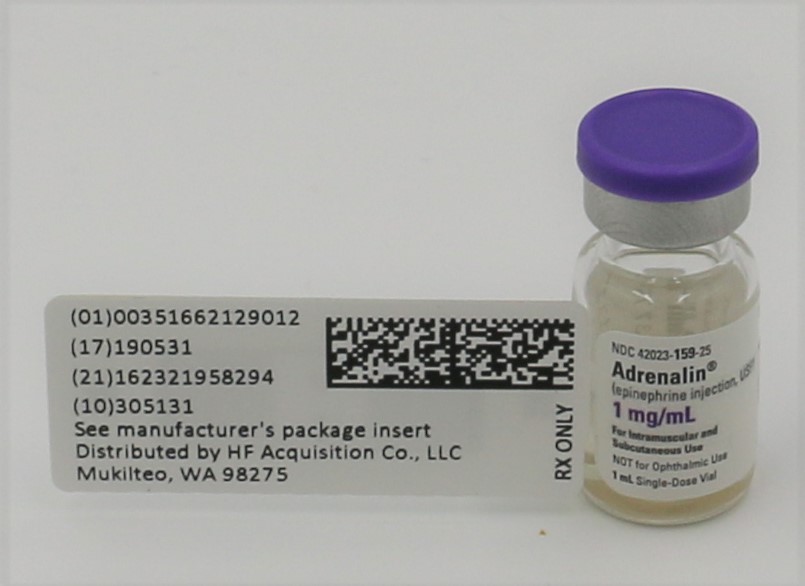
ADRENALIN (EPINEPHRINE) 1 mg/mL Injection, 1 mL — NDC 51662-1290-1 (Billing 51662-1290-01)
This is a package of 1 mL of ADRENALIN (EPINEPHRINE) 1 mg/mL Injection from HF Acquisition Co LLC, DBA HealthFirst, marketed since Sep 2018 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 1660014
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the alpha-Adrenergic Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Epinephrine injection is used along with emergency medical treatment to treat life-threatening allergic reactions caused by insect bites or stings, foods, medications, latex, and other causes. Epinephrine injection is also used to treat life-threatening low blood pressure associated with septic shock (a serious condition caused by a body-wide infection that can lead to dangerously low blood pressure and organ failure) in hospitalized patients. Epinephrine is in a class of medications called alpha- and beta-adrenergic agonists (sympathomimetic agents). It works by relaxing the muscles in the ai...
Read the full MedlinePlus article ↗- Epinephrine works fast but wears off quickly — sometimes in as little as 15 to 20 minutes. Anaphylaxis can come back (this is called a biphasic reaction), and you may need addition...
- Why do I need to go to the ER after using my EpiPen or Auvi-Q if I already feel better?
- Yes, it absolutely matters. Inject into the outer thigh — you can even go through your clothing if needed. Never inject into the buttocks (that spot carries a risk of serious infec...
- Where exactly do I inject it, and does it matter?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0169 | $0.783 / J0169 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51662-1290-01 You're viewing this Main listing | 1 mL in 1 VIAL, SINGLE-DOSE | 2018-09-21 | — | Active |
| 51662-1290-03 51662-1290-3 | 25 POUCH in 1 CASE / 1 mL in 1 POUCH | 2020-04-29 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 51662-1290-03?
What NDC number is used to bill for this package of ADRENALIN (EPINEPHRINE) 1 mg/mL Injection?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Adrenalin 1 mg/mL 42023-0159-25 | Par | 25 vials | $7.796 | AP | Availability likely | — |
| Epinephrine 1 mg/mL 00143-9476-25 | Hikma | 25 ampules | — | AP | FDA listed | — |
| Adrenalin 1 mg/mL 00404-9810-01 | Henry | 1 vial | — | AP | FDA listed | — |
| Epinephrine 1 mg/mL 00404-9857-01 | Henry | 1 ampule | — | AP | FDA listed | — |
| epinephrine 1 mg/mL 00517-1171-10 | American | 10 ampules | — | — | FDA listed | — |
| Epinephrine Professional 24357-0011-13 | Focus | 1 kit | — | AP | FDA listed | — |
| epinephrine 1 mg/mL 43066-0803-25 | Baxter | 25 vials | — | — | FDA listed | — |
| Epinephrine 1 mg/mL 50090-3039-00 | A-S | 25 ampules | — | AP | Discontinued | — |
| Adrenalin (Epinephrine) 1 mg/mLthis 51662-1290-01 | HF | 1 ml | — | AP | FDA listed | — |
| Epinephrine Convenience Kit 51662-1507-01 | HF | 1 vial | — | AP | FDA listed | — |
| Epinephrine 1 mg/mL 54288-0103-10 | BPI | 10 ampules | — | AP | FDA listed | — |
| Epinephrine 1 mg/mL 54288-0119-10 | BPI | 10 vials | — | AP | FDA listed | — |
| Epinephrine 1 mg/mL 63323-0696-25 | Fresenius | 25 vials | — | AP | FDA listed | — |
| epinephrine 1 mg/mL 68083-0591-10 | Gland | 10 ampules | — | AP | FDA listed | — |
| epinephrine 1 mg/mL 68462-0933-10 | GLENMARK | 10 ampules | — | AP | FDA listed | — |
| Adrenalin Vials 1 mg/mL 70385-2024-02 | Sina | 2 vials | — | AP | FDA listed | — |
| Adrenalin 1 mg/mL 70518-1342-00 | REMEDYREPACK | 25 vials | — | AP | Discontinued | — |
| Epinephrine 1 mg/mL 70518-4156-00 | REMEDYREPACK | 25 vials | — | AP | FDA listed | — |
| Epinephrine 1 mg/mL 70518-4274-00 | REMEDYREPACK | 25 vials | — | AP | FDA listed | — |
| Epinephrine 1 mg/mL 71872-7117-01 | Medical | 1 ampule | — | AP | FDA listed | — |
| Adrenalin 1 mg/mL 71872-7223-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Epinephrine 1 mg/mL 71872-7360-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Epinephrine 1 mg/mL 72572-0235-25 | CIVICA, | 25 vials | — | AP | Discontinued | — |
| Epinephrine 1 mg/mL 80830-1659-02 | Amneal | 25 vials | — | AP | FDA listed | — |
| Epinephrine 1 mg/mL 84549-0103-10 | ProPharma | 1 ml | — | AP | FDA listed | — |
| Adrenalin 1 mg/mL 84549-0159-25 | ProPharma | 1 ml | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9295657 ↗ | Method of use | U-1829 | Mar 13, 2035 |
| US 9119876 ↗ | Drug product | — | Mar 13, 2035 |
| US 12280024 ↗ | Drug product | — | Mar 13, 2035 |
Is there a generic version of this drug?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Adrenalin® is available as a single-use 1 mL vial and a multiple-use 30 mL vial for intramuscular and subcutaneous use. Emergency treatment of allergic reactions (Type I), including anaphylaxis, which may result from allergic reactions to insect stings, biting insects, foods, drugs, sera, diagnostic testing substances and other allergens, as well as idiopathic anaphylaxis or exercise-induced anaphylaxis. The signs and symptoms associated with anaphylaxis include flushing, apprehension, syncope, tachycardia, thready or unobtainable pulse associated with hypotension, convulsions, vomiting, diarrhea and abdominal cramps, involuntary voiding, airway swelling, laryngospasm, bronchospasm, pruritus, urticaria or angioedema, swelling of the eyelids, lips, and tongue.
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATIN Inject Adrenalin® intramuscularly or subcutaneously into the anterolateral aspect of the thigh, through clothing if necessary. When administering to a child, to minimize the risk of injection related injury, hold the leg firmly in place and limit movement prior to and during an injection. The injection may be repeated every 5 to 10 minutes as necessary.
For intramuscular administration, use a needle long enough (at least 1/2 inch to 5/8 inch) to ensure the injection is administered into the muscle. Monitor the patient clinically for the severity of the allergic reaction and potential cardiac effects of the drug, with repeat doses titrated to effect. Do not administer repeated injections at the same site, as the resulting vasoconstriction may cause tissue necrosis.
Inspect visually for particulate matter and discoloration prior to administration. Do not use if the solution is colored or cloudy, or if it contains particulate matter. Adults and Children 30 kg (66 lbs) or more: 0.3 to 0.5 mg (0.3 mL to 0.5 mL) of undiluted Adrenalin® administered intramuscularly or subcutaneously in the anterolateral aspect of the thigh, up to a maximum of 0.5 mg (0.5 mL) per injection, repeated every 5 to 10 minutes as necessary.
Monitor clinically for reaction severity and cardiac effects. Children less than 30 kg (66 lbs): 0.01 mg/kg (0.01 mL/kg) of undiluted Adrenalin® administered intramuscularly or subcutaneously in the anterolateral aspect of the thigh, up to a maximum of 0.3 mg (0.3 mL) per injection, repeated every 5 to 10 minutes as necessary. Monitor clinically for reaction severity and cardiac effects.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS Adrenalin® 1 mg/mL epinephrine injection, 1 mL solution in a single-use clear glass vial
⛔ Contraindications ▾
4 CONTRAINDICATIONS None.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS
5.1Incorrect Locations of Injection Injection into the anterolateral aspect of the thigh (vastus lateralis muscle) is the most appropriate location for administration because of its location, size, and available blood flow. Injection into (or near) smaller muscles, such as in the deltoid, is not recommended due to possible differences in absorption associated with this use. Do not administer repeated injections of epinephrine at the same site, as the resulting vasoconstriction may cause tissue necrosis.
Do not inject into buttock. Injection into the buttock may not provide effective treatment of anaphylaxis and has been associated with the development of Clostridial infections (gas gangrene). Cleansing with alcohol does not kill bacterial spores, and therefore, does not lower this risk.
Do not inject into digits, hands, or feet. Epinephrine is a strong vasoconstrictor. Accidental injection into the digits, hands or feet may result in loss of blood flow to the affected area and has been associated with tissue necrosis.
5.2Serious Infections at the Injection Site Rare cases of serious skin and soft tissue infections, including necrotizing fasciitis and myonecrosis caused by Clostridia (gas gangrene), have been reported at the injection site following epinephrine injection for anaphylaxis. Clostridium spores can be present on the skin and introduced into the deep tissue with subcutaneous or intramuscular injection. While cleansing with alcohol may reduce presence of bacteria on the skin, alcohol cleansing does not kill Clostridium spores.
To decrease the risk of Clostridium infection, do not inject Adrenalin® into the buttock [see Warnings and Precautions (5.1)]. Advise patients to seek medical care if they develop signs or symptoms of infection, such as persistent redness, warmth, swelling, or tenderness, at the epinephrine injection site.
5.3Disease Interactions Some patients may be at greater risk for developing adverse reactions after systemic epinephrine administration. Despite these concerns, the presence of these conditions is not a contraindication to epinephrine administration in an acute, life-threatening situation. Patients with Heart Disease Epinephrine should be administered with caution in patients who have heart disease, including patients with cardiac arrhythmias, coronary artery or organic heart disease, cerebrovascular disease, or hypertension.
In such patients, or in patients who are on drugs that may sensitize the heart to arrhythmias, epinephrine may precipitate or aggravate angina pectoris as well as produce ventricular arrhythmias [see Drug Interactions ( 7 ) and Adverse Reactions ( 6 )]. Other Patients and Diseases Epinephrine should be administered with caution to patients with hyperthyroidism, Parkinson's disease, diabetes mellitus, pheochromocytoma, elderly individuals, and pregnant women. Patients with Parkinson's disease may experience psychomotor agitation or notice a temporary worsening of symptoms.
Diabetic patients may experience transient increases in blood sugar.
5.4Allergic Reactions Associated with Sulfite Adrenalin® contains sodium bisulfite which may cause mild to severe allergic reactions including anaphylaxis or asthmatic episodes in susceptible individuals. However, the presence of bisulfite in this product should not preclude its use for the treatment of serious allergic or other emergency situations even if the patient is sulfite-sensitive, as the alternatives to using epinephrine in a life-threatening situation may not be satisfactory.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Common adverse reactions to systemically administered epinephrine include anxiety, apprehensiveness, restlessness, tremor, weakness, dizziness, sweating, palpitations, pallor, nausea and vomiting, headache, and respiratory difficulties. These symptoms occur in some persons receiving therapeutic doses of epinephrine, but are more likely to occur in patients with heart disease, hypertension, or hyperthyroidism [see Warnings and Precautions 5- (5.3)]. Due to the lack of randomized, controlled clinical trials of epinephrine for the treatment of anaphylaxis, the true incidence of adverse reactions associated with the systemic use of epinephrine is difficult to determine.
Adverse reactions reported in observational trials, case reports, and studies are listed below by body system: Cardiovascular: angina, arrhythmias, hypertension, pallor, palpitations, tachyarrhythmia, tachycardia, vasoconstriction, ventricular ectopy and stress cardiomyopathy. Angina may occur in patients with coronary artery disease [see Warnings and Precautions 5- (5.3)]. Arrhythmias, including fatal ventricular fibrillation, have occurred, particularly in patients with underlying organic heart disease or patients receiving drugs that sensitize the heart to arrhythmias [see Warnings and Precautions 5- (5.3)].
Rapid rises in blood pressure associated with epinephrine use have produced cerebral hemorrhage, particularly in elderly patients with cardiovascular disease [see Warnings and Precautions 5- (5.3)]. Respiratory: respiratory difficulties. Neurological: dizziness , disorientation , excitability , headache , impaired memory , lightheadedness , nervousness , panic, psychomotor agitation, sleepiness , tingling , tremor, and weakness.
Psychiatric: anxiety, apprehensiveness, restlessness. Gastrointestinal: nausea, vomiting. Other: Patients with Parkinson's disease may experience psychomotor agitation or a temporary worsening of symptoms [see Warnings and Precautions 5- (5.3)].
Diabetic patients may experience transient increases in blood sugar [see Warnings and Precautions 5- (5.3)]. Accidental injection into the digits, hands or feet may result in loss of blood flow to the affected area [see Warnings and Precautions 5- (5.1)]. Adverse events experienced as a result of an injection into these areas include increased heart rate, local reactions including injection site pallor, coldness, hypoesthesia, and tissue loss, or injury at the injection site resulting in bruising, bleeding, discoloration, erythema, and skeletal injury.
Injection into the buttock has resulted in cases of gas gangrene [see Warnings and Precautions 5- (5.1)]. Rare cases of serious skin and soft tissue infections, including necrotizing fasciitis and myonecrosis caused by Clostridia (gas gangrene), have been reported following epinephrine injection in the thigh [see Warnings and Precautions 5- (5.2)]. Skin: sweating.
To report SUSPECTED ADVERSE REACTIONS, contact Par Pharmaceutical at 1-800-828-9393 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Epinephrine should be administered cautiously to patients taking other sympathomimetic agents because of the possibility of additive effects. Patients who are concomitantly receiving cardiac glycosides, digitalis, diuretics, quinidine, and other antiarrhythmics should be observed carefully for the development of cardiac arrhythmias [see Warnings and Precautions 5- (5.3) and Adverse Reactions ( 6 )]. Administer epinephrine cautiously to patients receiving halogenated hydrocarbon general anesthetics, such as halothane, as coadministration may result in arrhythmias.
The effects of epinephrine may be potentiated by tricyclic antidepressants such as imipramine, monoamine oxidase inhibitors (MAOI), levothyroxine sodium, and certain antihistamines, notably diphenhydramine, tripelannamine, and dexchlorpheniramine. The cardiostimulating and bronchodilating effects of epinephrine are antagonized by beta-adrenergic blocking drugs, such as propranolol. The vasoconstricting and hypertensive effects of epinephrine are antagonized by alpha-adrenergic blocking drugs, such as phentolamine.
Ergot alkaloids may reverse the pressor effects of epinephrine. Epinephrine should not be used to counteract circulatory collapse or hypotension caused by phenothiazines, as a reversal of the pressor effects of epinephrine may result in further lowering of blood pressure.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Teratogenic Effects: Pregnancy Category C. There are no adequate and well-controlled studies in pregnant women. Epinephrine should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus (fetal anoxia, spontaneous abortion, or both).
Epinephrine is teratogenic in rabbits, mice and hamsters dosed during organogenesis. Epinephrine has been shown to have teratogenic effects (including gastroschisis and embryonic lethality) when administered subcutaneous in rabbits at approximately 15 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m2 basis at a maternal subcutaneous dose of 1.2 mg/kg/day for two to three days). In mice, teratogenic effects (including embryonic lethality) were observed at approximately 3 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m2 basis at maternal subcutaneous dose of 1 mg/kg/day for 10 days).
These effects were not seen in mice at approximately 2 times the maximum recommended daily intramuscular or subcutaneous dose (on a mg/m2 basis at a subcutaneous maternal dose of 0.5 mg/kg/day for 10 days). In hamsters, teratogenic effects were observed at approximately 2 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m2 basis at a maternal subcutaneous dose of 0.5 mg/kg/day for 4 days).
8.2Labor and Delivery Use with caution during labor and delivery. Although epinephrine improves maternal hypotension associated with anaphylaxis, it may result in uterine vasoconstriction, decreased uterine blood flow, and fetal anoxia.
8.3Nursing Mothers It is not known whether epinephrine is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when epinephrine is administered to a nursing woman.
8.4Pediatric Use Clinical use data support weight-based dosing for treatment of anaphylaxis in pediatric patients, and other reported clinical experience with the use of epinephrine suggests that the adverse reactions seen in children are similar in nature and extent to those both expected and reported in adults.
8.5Geriatric Use Clinical studies for the treatment of anaphylaxis have not been performed in subjects aged 65 and over to determine whether they respond differently from younger subjects. However, other reported clinical experience with use of epinephrine for the treatment of anaphylaxis has identified that geriatric patients may be particularly sensitive to the effects of epinephrine. Therefore, for the treatment of anaphylaxis, consider starting with a lower dose to take into account potential concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of epinephrine may produce extremely elevated arterial pressure, which may result in cerebrovascular hemorrhage, particularly in elderly patients. Overdosage may also result in pulmonary edema because of peripheral vascular constriction together with cardiac stimulation. Treatment consists of a rapidly acting α-adrenergic blocking drug and respiratory support.
Epinephrine is rapidly inactivated in the body and treatment following overdose with epinephrine is primarily supportive. If necessary, pressor effects may be counteracted by rapidly acting vasodilators or α-adrenergic blocking drugs. If prolonged hypotension follows such measures, it may be necessary to administer another pressor drug.
Epinephrine overdosage can also cause transient bradycardia followed by tachycardia and these may be accompanied by potentially fatal cardiac arrhythmias. Premature ventricular contractions may appear within one minute after injection and may be followed by multifocal ventricular tachycardia (prefibrillation rhythm). Subsidence of the ventricular effects may be followed by atrial tachycardia and occasionally by atrioventricular block.
Treatment of arrhythmias consists of administration of a beta-adrenergic blocking drug such as propranolol. Overdosage sometimes results in extreme pallor and coldness of the skin, metabolic acidosis due to elevated blood lactic acid levels, and kidney failure. Suitable corrective measures must be taken in such situations.
Myocardial ischemia, myocardial infarction and cardiomyopathy have been noted in the literature following overdose of epinephrine.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Epinephrine acts on both alpha and beta-adrenergic receptors.
12.2Pharmacodynamics Through its action on alpha-adrenergic receptors, epinephrine lessens the vasodilation and increased vascular permeability that occurs during anaphylaxis, which can lead to loss of intravascular fluid volume and hypotension. Through its action on beta-adrenergic receptors, epinephrine causes bronchial smooth muscle relaxation and helps alleviate bronchospasm, wheezing and dyspnea that may occur during anaphylaxis. Epinephrine also alleviates pruritus, urticaria, and angioedema and may relieve gastrointestinal and genitourinary symptoms associated with anaphylaxis because of its relaxer effects on the smooth muscle of the stomach, intestine, uterus and urinary bladder.
Epinephrine increases glycogenolysis, reduces glucose up take by tissues, and inhibits insulin release in the pancreas, resulting in hyperglycemia and increased blood lactic acid [see Warnings and Precautions 5-(5.3)]. Epinephrine causes mydriasis when administered parenterally.
12.3Pharmacokinetics When administered parenterally, epinephrine has a rapid onset and short duration of action.
📦 Storage and Handling ▾
16 HOW SUPPLIED/STORAGE & HANDLING Epinephrine Convenience Kit is supplied in the following dosage forms. NDC 51662-1507-1 (Epinephrine Convenience Kit) Kit Contains: Item #1007670-ADRENALIN® (EPINEPHRINE INJECTION, USP) 1mg/mL 1:1000 VIAL, NDC 51662-1290-1, 2 Total Item # 6985-EpiRite Syringe, 2 Total Item # 1005310-Needle 20Gx1 1/2", 2 Total N/A-Alcohol Prep Pad, 2 Total N/A- Package Insert, 1 Total HF Acquisition Co LLC, DBA HealthFirst Mukilteo, WA 98275 Adrenalin® 1 mL Single-Use Vials: Vial and contents must be discarded 30 days after initial use.
Store between 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Epinephrine is light sensitive. Protect from light and freezing.
📋 Description ▾
11 DESCRIPTION Adrenalin® (epinephrine injection, USP) is a clear, colorless, sterile solution containing 1 mg/mL epinephrine, packaged as 1 mL of solution in a single-use clear glass vial or 30 mL of solution in a multiple-dose amber glass vial. In the 1 mL vial, each 1 mL of Adrenalin® solution contains 1 mg epinephrine, 7.3 mg sodium chloride, 0.457 mg sodium metabisulfite, 1 mg sodium hydroxide, 2.25 mg tartaric acid, 0.20 mg disodium edetate dihydrate, hydrochloric acid to adjust pH, and water for injection. In the 30 mL vial, each 1 mL of Adrenalin® solution contains 1 mg epinephrine, 6.15 mg sodium chloride, 0.457 mg sodium metabisulfite, 0.920 mg sodium hydroxide, 2.25 mg tartaric acid, 0.20 mg disodium edetate dihydrate, hydrochloric acid to adjust pH, 5.25 mg chlorobutanol as a preservative and water for injection.
The pH range is 2.2-5.0. Epinephrine is a sympathomimetic catecholamine. The chemical name of epinephrine is: 1,2-Benzenediol, 4-[(1R)-1-hydroxy-2-(methylamino)ethyl]-, or (-)-3,4-Dihydroxy-α-[2-(methylamino)ethyl]benzyl alcohol.
The chemical structure of epinephrine is: The molecular weight of epinephrine is 183.2. Epinephrine solution deteriorates rapidly on exposure to air or light, turning pink from oxidation to adrenochrome and brown from the formation of melanin. STRUCTURE
💬 Medication Guide ▾
HIGHLIGHTS OF PRESCRIBING INFORMATION These highlights do not include all the information needed to use ADRENALIN safely and effectively. See full prescribing information for ADRENALIN. ADRENALIN (epinephrine injection) 1 mg/mL, for intramuscular, subcutaneous, and intravenous use Initial U.S.
Approval: 1939 RECENT MAJOR CHANGES Indications and Usage (1.2) 01/2019 Dosage and Administration (2.3) 01/2019 Warnings and Precautions (5.3, 5.4, 5.5, 5.6, 5.7) 01/2019 INDICATIONS AND USAGE Adrenalin® is a non-selective alpha and beta adrenergic agonist indicated for: Emergency treatment of allergic reactions (Type 1), including anaphylaxis ( 1- 1.1) To increase mean arterial blood pressure in adult patients with hypotension associated with septic shock ( 1- 1.2) DOSAGE AND ADMINISTRATION Anaphylaxis: Adults and Children 30 kg (66 lbs) or more: 0.3 mg to 0.5 mg (0.3 mL to 0.5 mL) intramuscularly or subcutaneously into anterolateral aspect of the thigh every 5 to 10 minutes as necessary ( 2- 2.2) Children 30 kg (66 lbs) or less: 0.01 mg/kg (0.01 mL/kg), up to 0.3 mg (0.3 mL), intramuscularly or subcutaneously into anterolateral aspect of the thigh every 5 to 10 minutes as necessary ( 2- 2.2) Hypotension associated with septic shock: Dilute epinephrine in dextrose solution prior to infusion ( 2- 2.3) Infuse epinephrine into a large vein ( 2- 2.3) Intravenous infusion rate of 0.05 mcg/kg/min to 2 mcg/kg/min, titrated to achieve desired mean arterial pressure ( 2- 2.3) Wean gradually ( 2- 2.3) See Full Prescribing Information for instructions on dilution and administration of the injection.
DOSAGE FORMS AND STRENGTHS Injection: 1 mg/mL single dose vial and 30 mg/30 mL (1 mg/mL) multiple dose vial ( 3 ) CONTRAINDICATIONS None ( 4 ) WARNINGS AND PRECAUTIONS Do not inject into buttocks, digits, hands, or feet ( 5- 5.1) Avoid extravasation into tissues, which can cause local necrosis ( 5- 5.3) May aggravate angina pectoris or produce ventricular arrhythmias ( 5- 5.7) ADVERSE REACTIONS Common adverse reactions to systemically administered epinephrine include anxiety, tremor, weakness, dizziness, sweating, palpitations and pallor ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Par Pharmaceutical at 1-800-828-9393 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
DRUG INTERACTIONS Drugs that counter the pressor effects of epinephrine include alpha blockers, vasodilators such as nitrates, diuretics, antihypertensives and ergot alkaloids. ( 7- 7.1) Drugs that potentiate the effects of epinephrine include sympathomimetics, beta blockers, tricyclic antidepressants, MAO inhibitors, COMT inhibitors, clonidine, doxapram, oxytocin, levothyroxine sodium, quinidine and certain antihistamines. ( 7- 7.2) Drugs that increase the arrhythmogenic potential of epinephrine include beta blockers, cyclopropane and halogenated hydrocarbon anesthetics, antihistamines, exogenous thyroid hormones, diuretics, and cardiac glycosides.
Observe for development of cardiac arrhythmias. ( 7- 7.3) Potassium-depleting drugs, including corticosteroids, diuretics, and theophylline, potentiate the hypokalemic effects of epinephrine. ( 7- 7.4) USE IN SPECIFIC POPULATIONS Elderly patients and pregnant women may be at greater risk of developing adverse reactions when epinephrine is administered parenterally ( 8- 8.1, 8- 8.5) Pregnancy: May cause fetal harm ( 8- 8.1) See 17 for PATIENT COUNSELING INFORMATION.
Revised: 1/2019
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long- term studies to evaluate the carcinogenic potential of epinephrine have not been conducted. Epinephrine and other catecholamines have been shown to have mutagenic potential in vitro. Epinephrine was positive in the Salmonella bacterial reverse mutation assay, positive in the mouse lymphoma assay, and negative in the in vivo micronucleus assay.
Epinephrine is an oxidative mutagen based on the E. coli WP2 Mutoxitest bacterial reverse mutation assay. This should not prevent the use of epinephrine under the conditions noted under Indications and Usage ( 1). The potential for epinephrine to impair reproductive performance has not been evaluated, but epinephrine has been shown to decrease implantation in female rabbits dosed subcutaneously with 1.2 mg/kg/day (15-fold the highest human intramuscular or subcutaneous daily dose) during gestation days 3 to 9.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - EPINEPHRINE KIT LABELING NDC 51662-1507-1 EPI CONVENIENCE KIT LABELING
PRINCIPAL DISPLAY PANEL - HYPODERMIC Needle 20Gx1 1/2" LABELING HYPODERMIC NEEDLE LABELING
PRINCIPAL DISPLAY PANEL - EpiRite Syringe LABELING EPIRITE SYRINGE LABELING
PRINCIPAL DISPLAY PANEL - Alcohol Prep Pad LABELING ALCOHOL PREP PAD - FRONT ALCOHOL PREP PAD - BACK
PRINCIPAL DISPLAY PANEL - VIAL LABEL VIAL LABEL
PRINCIPAL DISPLAY PANEL - SERIALIZED VIAL LABELING 51662-1290-1 SERIALIZED VIAL LABELING
Principal Display Panel - Serialization Example Labeling Example of 51662-1507-1 Serialized Labeling Serialization Example Labeling
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |