
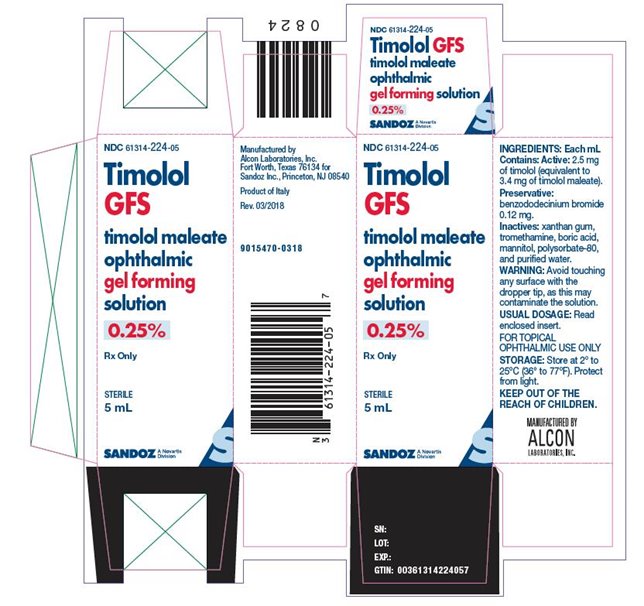
Timolol GFS timolol maleate 2.5 mg/mL Solution, Gel Forming / Drops, 2.5 mL — NDC 61314-224-25 (Billing 61314-0224-25)
This is a package of 2.5 mL of Timolol GFS timolol maleate 2.5 mg/mL Solution, Gel Forming / Drops from Sandoz Inc, marketed since Dec 1998 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 61314-224-25 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 61314 labeler · 224 product · 25 package
- Package marketed since
- Dec 24, 1998
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 6131422425 5
- FDA record last changed
- Jul 24, 2026
Other active recalls for Timolol Maleate (different manufacturers) — 6 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 021400
- GCN: 32822
- GPI-14 (Medi-Span): 86250030107620
- HICL (First Databank): 002105
- AHFS class code: 52:40.08.00
- RxCUI (RxNorm): 313407
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Ophthalmic timolol is used to treat glaucoma, a condition in which increased pressure in the eye can lead to gradual loss of vision. Timolol is in a class of medications called beta-blockers. It works by decreasing the pressure in the eye.
Read the full MedlinePlus article ↗- It depends on the form. The eye drops lower high pressure in the eye from ocular hypertension or open-angle glaucoma. The tablets treat high blood pressure, lower the risk of death...
- Put the drop in the affected eye as directed, usually once or twice a day depending on your product. If yours is a gel-forming type, shake the closed bottle once first. Wait at lea...
- Burning or stinging right after the drops go in is the most common. Blurred vision, redness, itching and headache can also happen. Call your doctor if you notice wheezing, a very s...
- If your drops contain benzalkonium chloride, soft lenses can absorb it. Take your lenses out before using the drops and wait 15 minutes before putting them back in.
Patient education
Supplement & herbal interactions
Timolol may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 61314-0224-05 61314-224-05 Main listing | 5 mL in 1 BOTTLE | $6.38 / mL | $31.88 | 1998-12-24 | — | Active |
| 61314-0224-25 You're viewing this | 2.5 mL in 1 BOTTLE | — | — | 1998-12-24 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 61314-0224-05?
What NDC number is used to bill for this package of Timolol GFS timolol maleate 2.5 mg/mL Solution, Gel Forming / Drops?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Timolol Maleate 2.5 mg/mL 25021-0008-05 | Sagent | 1 bottle | $6.376 | AB | Availability likely | — |
| Timolol Maleate Ophthalmic Gel Forming Solution 0.25% 2.5 mg/mL 43598-0747-11 | Dr. | 1 bottle | $6.376 | AB | Availability likely | — |
| Timolol Maleate Ophthalmic Gel Forming Solution, 0.25% 2.5 mg/mL 62332-0545-05 | Alembic | 1 bottle | $6.376 | AB | Availability likely | — |
| Timolol Maleate Ophthalmic Gel Forming Solution 2.5 mg/mL 72266-0199-01 | FOSUN | 1 bottle | $6.376 | AB | Availability likely | — |
| Timolol Maleate Ophthalmic Gel Forming Solution 0.25% 2.5 mg/mL 72603-0162-01 | NorthStar | 1 bottle | $6.376 | AB | Availability likely | — |
| Timolol Maleate 2.5 mg/mL 82260-0818-25 | Bausch | 1 bottle | $6.376 | AB | Availability likely | — |
| Timoptic-XE 2.5 mg/mL 24208-0814-25 | Bausch | 1 bottle | — | AB | FDA listed | — |
| Timolol Maleate Ophthalmic Gel Forming Solution, 0.25% 2.5 mg/mL 46708-0545-05 | Alembic | 1 bottle | — | AB | FDA listed | — |
| Timolol GFS 2.5 mg/mLthis 61314-0224-25 | Sandoz | 2.5 ml | — | AB | FDA listed | — |
| timolol maleate ophthalmic gel forming solution 2.5 mg/mL 68083-0457-01 | Gland | 1 bottle | — | AB | FDA listed | — |
| Timolol Maleate 2.5 mg/mL 70069-0241-01 | Somerset | 1 bottle | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Timolol inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII IRY12B2TQ6
A synthetic antimicrobial chemical used as a preservative to prevent bacterial and fungal growth in liquid medicines and topical products during storage and use.
-
UNII R57ZHV85D4
Boric acid is a weak acid derived from boron. In medicines, it typically serves as a buffer to help maintain the product's pH level and may act as a preservative in certain formulations.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 023C2WHX2V
Tromethamine is a chemical buffer that helps maintain the proper acidity level in liquid medicines. It neutralizes acids and stabilizes the solution so the medication remains effective and safe throughout its shelf life.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
-
UNII TTV12P4NEE
Xanthan gum is a thickening and stabilizing ingredient made from fermented corn or other sugars. It's added to medicines to improve texture, prevent separation of liquids and solids, and help the product stay consistent.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Sandoz Inc labeler code 61314
- KETOROLAC TROMETHAMINE 5 mg/mL Solution NDC 61314-126-05
- Brimonidine Tartrate 2 mg/mL Solution NDC 61314-143-05
- Brimonidine Tartrate 1.5 mg/mL Solution NDC 61314-144-05
- Pilocarpine Hydrochloride 10 mg/mL Solution/ Drops NDC 61314-203-15
- Pilocarpine Hydrochloride 20 mg/mL Solution/ Drops NDC 61314-204-15
- Pilocarpine Hydrochloride 40 mg/mL Solution/ Drops NDC 61314-206-15
- Timolol GFS timolol maleate 5 mg/mL Solution, Gel Forming / Drops NDC 61314-225-05
- Timolol Maleate 2.5 mg/mL Solution NDC 61314-226-05
- Timolol Maleate 5 mg/mL Solution NDC 61314-227-05
- WYOST denosumab 120 mg/1.7mL Injection NDC 61314-228-94
- Cromolyn Sodium 40 mg/mL Solution/ Drops NDC 61314-237-10
- Carteolol Hydrochloride 10 mg/mL Solution NDC 61314-238-05
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Timolol GFS 0.25% and 0.5% are indicated for the treatment of elevated intraocular pressure in patients with ocular hypertension or open-angle glaucoma. Timolol GFS is a beta adrenergic blocker indicated for the treatment of elevated intraocular pressure in patients with ocular hypertension or open-angle glaucoma ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Instill one drop of Timolol GFS (either 0.25% or 0.5%) in the affected eye(s) once daily. Shake once before each use. Timolol GFS may be used alone or in combination with other intraocular pressure lowering medications. Concomitant topical ophthalmic medications should be administered at least 10 minutes before instilling Timolol GFS. Instill one drop in the affected eye(s) once daily ( 2 ).
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Ophthalmic gel forming solution: slightly opalescent, colorless to nearly colorless solution containing 0.25% or 0.5% of timolol. Available in 5 mL size bottle filled with 2.5 mL or 5 mL solution. Ophthalmic gel forming solution containing 0.25% or 0.5% of timolol ( 3 ).
⛔ Contraindications ▾
4 CONTRAINDICATIONS Timolol GFS is contraindicated in patients with: • bronchial asthma • history of bronchial asthma • severe chronic obstructive pulmonary disease • sinus bradycardia • second or third degree atrioventricular block • overt cardiac failure • cardiogenic shock • hypersensitivity to any component of this product. • Bronchial asthma (or history of) ( 4 ) • Severe chronic obstructive pulmonary disease ( 4 ) • Sinus bradycardia ( 4 ) • Second or third degree atrioventricular block ( 4 ) • Overt cardiac failure ( 4 ) • Cardiogenic shock ( 4 ) • Hypersensitivity to any component of this product ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Same adverse reactions found with systemic administration of beta-adrenergic receptor inhibitors may occur with topical ophthalmic administration ( 5.1 ). • Beta-adrenergic receptor inhibitors may mask signs and symptoms of hypoglycemia and should be administered with caution in diabetic patients subject to hypoglycemia ( 5.5 ). • Beta-adrenergic receptor inhibitors may mask certain clinical signs (e.g. tachycardia) of hyperthyroidism ( 5.6 ).
5.1Systemic Absorption As with many topically applied ophthalmic drugs, Timolol GFS is absorbed systemically. The same adverse reactions found with systemic administration of beta-adrenergic receptor inhibitors may occur with topical ophthalmic administration. For example, severe respiratory reactions and cardiac reactions, including death due to bronchospasm in patients with asthma, and death due to cardiac failure, have been reported following systemic or ophthalmic administration of timolol maleate [see Contraindications (4) ].
5.2Cardiac Failure Sympathetic stimulation may be essential for support of the circulation in individuals with diminished myocardial contractility, and its inhibition by beta-adrenergic receptor blockade may precipitate more severe failure. In patients without a history of cardiac failure, continued depression of the myocardium with beta-adrenergic receptor inhibitors over a period of time can, in some cases, lead to cardiac failure. At the first sign or symptom of cardiac failure, Timolol GFS should be discontinued.
5.3Bronchospasm and Obstructive Pulmonary Disease Bronchospasm may occur. Patients with chronic obstructive pulmonary disease (e.g., chronic bronchitis, emphysema) of mild or moderate severity, bronchospastic disease, or a history of bronchospastic disease (other than bronchial asthma or a history of bronchial asthma, in which Timolol GFS is contraindicated [see Contraindications (4) ] ) should, in general, not receive beta-adrenergic receptor inhibitors, including Timolol GFS.
5.4Surgical Anesthesia The necessity or desirability of withdrawal of beta-adrenergic receptor inhibitors prior to major surgery is controversial. Beta-adrenergic receptor blockade impairs the ability of the heart to respond to beta-adrenergically mediated reflex stimuli. This may augment the risk of general anesthesia in surgical procedures.
Some patients receiving beta-adrenergic receptor inhibitors have experienced protracted, severe hypotension during anesthesia. Difficulty in restarting and maintaining the heartbeat has also been reported. In patients undergoing elective surgery, consider gradual withdrawal of beta-adrenergic receptor inhibitors.
If necessary during surgery, the effects of beta-adrenergic receptor inhibitors may be reversed by sufficient doses of adrenergic agonists.
5.5Diabetes Mellitus Beta-adrenergic receptor inhibitors should be administered with caution in diabetic patients subject to hypoglycemia who are receiving insulin or oral hypoglycemic agents. Beta-adrenergic receptor inhibitors may mask the signs and symptoms of acute hypoglycemia.
5.6Thyrotoxicosis Beta-adrenergic receptor inhibitors may mask certain clinical signs (e.g. tachycardia) of hyperthyroidism. Patients suspected of developing thyrotoxicosis should be managed carefully to avoid abrupt withdrawal of beta-adrenergic receptor inhibitors that might precipitate a thyroid storm.
5.7Cerebrovascular Insufficiency Because of potential effects of beta-adrenergic receptor inhibitors on blood pressure and pulse, these agents should be used with caution in patients with cerebrovascular insufficiency. If signs or symptoms suggesting reduced cerebral blood flow develop following initiation of therapy with Timolol GFS, alternative therapy should be considered.
5.8Bacterial Keratitis Bacterial keratitis may occur with use of multiple dose containers of topical ophthalmic products when these containers are inadvertently contaminated by patients who, in most cas… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (1% to 5%) occur upon instillation and include transient blurred vision, burning, and stinging ( 6.1 ). To report SUSPECTED ADVERSE REACTIONS, contact Sandoz Inc. at 1-800-525-8747 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In clinical trials with Timolol GFS, transient blurred vision upon instillation of the drop was reported in approximately one in three patients. The frequency of patients reporting burning and stinging upon instillation was approximately one in eight patients which was comparable to that observed for TIMOPTIC*.
Adverse reactions reported in 1% to 5% of patients were: Ocular: Blepharitis, conjunctivitis, crusting, discomfort, foreign body sensation, hyperemia, pruritus and tearing; Systemic: Headache, hypertension, and upper respiratory infections. In a 3-month, double-masked, active-controlled, multicenter study in pediatric patients, the adverse reactions profile of Timolol GFS 0.25% and 0.5% was comparable to that seen in adult patients.
6.2Additional Potential Adverse Reactions Associated with Timolol Maleate The following additional adverse experiences have been reported with the ocular administration of this or other timolol maleate formulations: BODY AS A WHOLE Asthenia/fatigue and chest pain. CARDIOVASCULAR Bradycardia, arrhythmia, hypotension, hypertension, syncope, heart block, cerebral vascular accident, cerebral ischemia, cardiac failure, worsening of angina pectoris, palpitation, cardiac arrest, pulmonary edema, dizziness, edema, claudication, Raynaud's phenomenon, and cold hands and feet.
DIGESTIVE Nausea, diarrhea, dyspepsia, anorexia, and dry mouth. IMMUNOLOGIC Systemic lupus erythematosus. NERVOUS SYSTEM/PSYCHIATRIC Increase in signs and symptoms of myasthenia gravis, paresthesia, somnolence, insomnia, nightmares, behavioral changes and psychic disturbances including confusion, hallucinations, anxiety, depression, disorientation, nervousness, and memory loss.
SKIN Alopecia and psoriasiform rash or exacerbation of psoriasis. HYPERSENSITIVITY Signs and symptoms of systemic allergic reactions, including anaphylaxis, angioedema, urticaria and localized and generalized rash. RESPIRATORY Bronchospasm (predominantly in patients with pre-existing bronchospastic disease), respiratory failure, dyspnea, nasal congestion, and cough.
ENDOCRINE Masked symptoms of hypoglycemia in diabetic patients [see Warnings and Precautions (5.5) ] . SPECIAL SENSES Signs and symptoms of ocular irritation including blepharitis, keratitis, and dry eyes; ptosis; decreased corneal sensitivity; cystoid macular edema; visual disturbances including refractive changes and diplopia; pseudopemphigoid; choroidal detachment following filtration surgery [see Warnings and Precautions (5.9 )] ; and tinnitus. UROGENITAL Retroperitoneal fibrosis, decreased libido, impotence and Peyronie's disease.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Oral beta-adrenergic receptor inhibitors may have additive effects ( 7.1 ) • Digitalis and calcium antagonists may have additive effects ( 7.2 ) • Catecholamine-depleting drugs may have additive effects ( 7.3 ) • Quinidine may have additive effects ( 7.4 )
7.1Oral Beta-Adrenergic Receptor Inhibitors Patients who are receiving a beta-adrenergic receptor inhibiting agent orally and Timolol GFS should be observed for potential additive effects of beta-blockade, both systemic and on intraocular pressure. Patients should not usually receive two topical ophthalmic beta-adrenergic receptor inhibiting agents concurrently.
7.2Digitalis and Calcium Antagonists The concomitant use of beta-adrenergic receptor inhibiting agents with digitalis and calcium antagonists may have additive effects in prolonging atrioventricular conduction time. Caution should be used in the co-administration of beta-adrenergic receptor inhibitors, such as Timolol GFS, and oral or intravenous calcium antagonists because of possible atrioventricular conduction disturbances, left ventricular failure, or hypotension. In patients with impaired cardiac function, co-administration should be avoided.
7.3Catecholamine-Depleting Drugs Close observation of the patient is recommended when a beta receptor inhibitor is administered to patients receiving catecholamine-depleting drugs such as reserpine, because of possible additive effects and the production of hypotension and/or marked bradycardia, which may result in vertigo, syncope, or postural hypotension.
7.4Quinidine Potentiated systemic beta-blockade (e.g., decreased heart rate) has been reported during combined treatment with quinidine and timolol, possibly because quinidine inhibits the metabolism of timolol via the P-450 enzyme, CYP2D6.
7.5Clonidine Oral beta-adrenergic receptor inhibiting agents may exacerbate the rebound hypertension which can follow the withdrawal of clonidine. There have been no reports of exacerbation of rebound hypertension with ophthalmic timolol maleate.
7.6Injectable Epinephrine Patients may be unresponsive to the usual doses of epinephrine used to treat anaphylactic reactions. [See Warnings and Precautions (5.11) ]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies in pregnant women with timolol maleate to inform a drug-associated risk. Administration of oral timolol maleate to pregnant mice, rats and rabbits did not produce teratogenicity at clinically relevant systemic exposures (see Data). Because animal reproductive studies are not always predictive of human response, Timolol GFS should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data Teratogenicity studies with timolol in mice, rats, and rabbits at oral doses up to 50 mg/kg/day (7,000 times the systemic exposure following the maximum recommended human ophthalmic dose) demonstrated no evidence of fetal malformations. Although delayed fetal ossification was observed at this dose in rats, there were no adverse effects on postnatal development of offspring.
Doses of 1,000 mg/kg/day (142,000 times the systemic exposure following the maximum recommended human ophthalmic dose) were maternotoxic in mice and resulted in an increased number of fetal resorptions. Increased fetal resorptions were also seen in rabbits at doses of 14,000 times the systemic exposure following the maximum recommended human ophthalmic dose, in this case without apparent maternotoxicity.
8.2Lactation Risk Summary Timolol maleate has been detected in human milk following oral and ophthalmic drug administration. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for Timolol GFS and any potential adverse effects on the breastfed child from Timolol GFS.
8.4Pediatric Use The safety and IOP-lowering effect of Timolol GFS 0.25% and 0.5% have been demonstrated in pediatric patients in a 3-month, multicenter, double-masked, active-controlled trial.
8.5Geriatric Use No overall differences in safety or effectiveness have been observed between elderly and younger patients.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies in pregnant women with timolol maleate to inform a drug-associated risk. Administration of oral timolol maleate to pregnant mice, rats and rabbits did not produce teratogenicity at clinically relevant systemic exposures (see Data). Because animal reproductive studies are not always predictive of human response, Timolol GFS should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data Teratogenicity studies with timolol in mice, rats, and rabbits at oral doses up to 50 mg/kg/day (7,000 times the systemic exposure following the maximum recommended human ophthalmic dose) demonstrated no evidence of fetal malformations. Although delayed fetal ossification was observed at this dose in rats, there were no adverse effects on postnatal development of offspring.
Doses of 1,000 mg/kg/day (142,000 times the systemic exposure following the maximum recommended human ophthalmic dose) were maternotoxic in mice and resulted in an increased number of fetal resorptions. Increased fetal resorptions were also seen in rabbits at doses of 14,000 times the systemic exposure following the maximum recommended human ophthalmic dose, in this case without apparent maternotoxicity.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and IOP-lowering effect of Timolol GFS 0.25% and 0.5% have been demonstrated in pediatric patients in a 3-month, multicenter, double-masked, active-controlled trial.
🧓 Geriatric Use ▾
8.5Geriatric Use No overall differences in safety or effectiveness have been observed between elderly and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE No data are available with regard to human overdose with, or accidental oral ingestion of Timolol GFS. There have been reports of inadvertent overdose with Timolol maleate ophthalmic solution resulting in systemic effects similar to those seen with systemic beta-adrenergic receptor inhibitors such as dizziness, headache, shortness of breath, bradycardia, bronchospasm, and cardiac arrest [see also Adverse Reactions (6) ]. Overdosage has been reported with timolol maleate tablets.
A 30-year old female ingested 650 mg of timolol maleate tablets (maximum recommended oral daily dose is 60 mg) and experienced second and third degree heart block. She recovered without treatment but approximately two months later developed irregular heartbeat, hypertension, dizziness, tinnitus, faintness, increased pulse rate, and borderline first degree heart block. An in vitro hemodialysis study, using 14 C timolol added to human plasma or whole blood, showed that timolol was readily dialyzed from these fluids; however, a study of patients with renal failure showed that timolol did not dialyze readily.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Timolol maleate is a beta 1 and beta 2 (non-selective) adrenergic receptor inhibitor that does not have significant intrinsic sympathomimetic, direct myocardial depressant, or local anesthetic (membrane-stabilizing) activity. Timolol GFS, when applied topically to the eye, has the action of reducing elevated, as well as normal, intraocular pressure, whether or not accompanied by glaucoma. Elevated intraocular pressure is a major risk factor in the pathogenesis of glaucomatous visual field loss and optic nerve damage.
The precise mechanism of the ocular hypotensive action of Timolol GFS is not clearly established at this time. Tonography and fluorophotometry studies of Timolol GFS in man suggest that its predominant action may be related to reduced aqueous formation. However, in some studies, a slight increase in outflow facility was also observed.
Beta-adrenergic receptor blockade reduces cardiac output in both healthy subjects and patients with heart disease. In patients with severe impairment of myocardial function beta-adrenergic receptor inhibitors may inhibit the stimulatory effect of the sympathetic nervous system necessary to maintain adequate cardiac function. Beta-adrenergic receptor blockade in the bronchi and bronchioles results in increased airway resistance from unopposed parasympathetic activities.
Such an effect in patients with asthma or other bronchospastic conditions is potentially dangerous.
12.2Pharmacodynamics Because in some patients the intraocular pressure-lowering response to Timolol GFS may require a few weeks to stabilize, evaluation should include a determination of intraocular pressure after approximately 4 weeks of treatment with Timolol GFS. If the patient's intraocular pressure is still not at a satisfactory level on this regimen, concomitant therapy can be considered.
12.3Pharmacokinetics Following topical ocular administration of timolol to humans, low concentrations of drug are found in plasma. After bilateral administration of a 0.5% timolol maleate solution to healthy volunteers, maximum plasma concentrations were generally below 5 ng/mL. Dosages higher than one drop of 0.5% Timolol GFS once daily have not been studied.
Pharmacokinetic studies in humans using this gel forming solution formulation were not performed. However, systemic uptake from a gel matrix is expected to be slower than from a non-gel forming solution based on studies using other gel forming solutions. The maximum plasma timolol concentration from the gel forming drop is not expected to exceed those of the 0.5% timolol maleate solution.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Timolol maleate is a beta 1 and beta 2 (non-selective) adrenergic receptor inhibitor that does not have significant intrinsic sympathomimetic, direct myocardial depressant, or local anesthetic (membrane-stabilizing) activity. Timolol GFS, when applied topically to the eye, has the action of reducing elevated, as well as normal, intraocular pressure, whether or not accompanied by glaucoma. Elevated intraocular pressure is a major risk factor in the pathogenesis of glaucomatous visual field loss and optic nerve damage.
The precise mechanism of the ocular hypotensive action of Timolol GFS is not clearly established at this time. Tonography and fluorophotometry studies of Timolol GFS in man suggest that its predominant action may be related to reduced aqueous formation. However, in some studies, a slight increase in outflow facility was also observed.
Beta-adrenergic receptor blockade reduces cardiac output in both healthy subjects and patients with heart disease. In patients with severe impairment of myocardial function beta-adrenergic receptor inhibitors may inhibit the stimulatory effect of the sympathetic nervous system necessary to maintain adequate cardiac function. Beta-adrenergic receptor blockade in the bronchi and bronchioles results in increased airway resistance from unopposed parasympathetic activities.
Such an effect in patients with asthma or other bronchospastic conditions is potentially dangerous.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Timolol GFS (timolol maleate ophthalmic gel forming solution) 0.25% and 0.5%, are both supplied as either a 2.5 mL or 5 mL slightly opalescent, colorless to nearly colorless solution in a 5 mL white polyethylene bottle with a natural polyethylene dropper tip and a yellow polypropylene overcap. Tamper evidence is provided with a shrink band around the closure and neck area of the bottle. • 0.25% 2.5 mL fill NDC 61314-224-25 5 mL fill NDC 61314-224-05 • 0.5% 2.5 mL fill NDC 61314-225-25 5 mL fill NDC 61314-225-05 Storage and Handling Store at 2°C to 25°C (36°F to 77°F).
After opening, Timolol GFS can be used until the expiration date on the bottle. Protect from light.
📋 Description ▾
11 DESCRIPTION Timolol GFS (timolol maleate ophthalmic gel forming solution) is a non-selective beta-adrenergic receptor inhibitor. Its chemical name is (-)-1-( tert -butylamino)-3-[(4-morpholino-1,2,5-thia diazol-3-yl)oxy]-2-propanol maleate (1:1) (salt). Timolol maleate possesses an asymmetric carbon atom in its structure and is provided at the levo-isomer.
The nominal optical rotation of timolol maleate is: [α] 25° in 0.1N HCl (C=5%) = -12.2° 405 nm Its molecular formula is C 13 H 24 N 4 O 3 S·C 4 H 4 O 4 and its structural formula is: Timolol maleate has a molecular weight of 432.50. It is a white, odorless, crystalline powder which is soluble in water, methanol, and alcohol. Timolol GFS is a colorless to nearly colorless, slightly opalescent, and slightly viscous, is supplied as a sterile, isotonic, buffered, aqueous topical ophthalmic solution of timolol maleate in two dosage strengths.
Timolol GFS has a pH of approximately 6.9 and an osmolality of approximately 290 mOsmol/kg. Each mL of Timolol GFS 0.25% contains 2.5 mg of timolol (3.4 mg of timolol maleate). Each mL of Timolol GFS 0.5% contains 5 mg of timolol (6.8 mg of timolol maleate).
Inactive ingredients: boric acid, mannitol, polysorbate-80, tromethamine, xanthan gum, and purified water. Preservative: benzododecinium bromide 0.012%. Xanthan gum is a purified high molecular weight polysaccharide gum produced from the fermentation by bacterium Xanthomonas campestris.
An aqueous solution of xanthan gum, in the presence of tear protein (lysozyme), forms a gel. Upon contact with the precorneal tear film, Timolol GFS forms a gel that is subsequently removed by the flow of tears. chemical
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION How to Use the Timolol GFS solution? The bottle is designed to assure the delivery of a precise dose of medication. Before using your bottle, read the complete instructions carefully.
1. If you use other topically applied ophthalmic medications, they should be administered at least 10 minutes before Timolol GFS. 2.
Wash hands before each use. 3. Before using the medication for the first time, be sure the Safety Seal on the bottle is unbroken.
4. Tear off the Safety Seal to break the seal. 5.
Before each use, shake once and remove the screw cap. 6. Invert the bottle and hold the bottle between your thumb and middle finger, with the tips of the fingers pointing towards you.
7. Tilt your head back and position the bottle above the affected eye. DO NOT TOUCH THE EYE WITH THE TIP OF THE DROPPER.
8. With the opposite hand, place a finger under the eye. Gently pull down until a "V" pocket is made between your eye and lower lid.
9. With the hand holding the bottle, place your index finger on the bottom of the bottle. Push the bottom of the bottle to dispense one drop of medication.
DO NOT SQUEEZE THE SIDES OF THE BOTTLE. 10. Repeat 6, 7, 8, and 9 with other eye if instructed to do so.
11. Replace screw cap by turning until firmly touching the bottle. Avoiding Contamination of the Product Instruct patients to avoid allowing the tip of the dispensing container to contact the eye(s) or surrounding structures.
Advise patients that ocular solutions, if handled improperly, could become contaminated by common bacteria known to cause ocular infections. Serious damage to the eye(s) and subsequent loss of vision may result from using contaminated solutions [see Warnings and Precautions (5.8) ]. When to Seek Physician Advice Advise patients that if they have ocular surgery or develop an intercurrent ocular condition (e.g., trauma or infection), they should immediately seek their physician's advice concerning the continued use of the present multidose container.
Administration Instructions Instruct patients to invert the closed container and shake once before each use. It is not necessary to shake the container more than once. Instruct patients requiring concomitant topical ophthalmic medications to administer these at least 10 minutes before instilling Timolol GFS.
Asthma, COPD, Sinus Bradycardia, AV Block, Cardiac Failure, Cardiogenic Shock Advise patients with bronchial asthma, a history of bronchial asthma, severe chronic obstructive pulmonary disease, sinus bradycardia, second or third degree atrioventricular block, or cardiac failure to not use Timolol GFS [see Contraindications (4) ]. Temporary Blurred Vision Advise patients that transient blurred vision or visual disturbance, generally lasting from 30 seconds to 5 minutes, following instillation may impair the ability to perform hazardous tasks such as operating machinery or driving a motor vehicle. *TIMOPTIC is a Registered trademark of Merck & Co., Inc.
Manufactured by: Alcon Laboratories, Inc. Fort Worth, Texas 76134 for Sandoz Inc. Princeton, NJ 08540 300066885-0524 bottle eye
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following topical ocular administration of timolol to humans, low concentrations of drug are found in plasma. After bilateral administration of a 0.5% timolol maleate solution to healthy volunteers, maximum plasma concentrations were generally below 5 ng/mL. Dosages higher than one drop of 0.5% Timolol GFS once daily have not been studied.
Pharmacokinetic studies in humans using this gel forming solution formulation were not performed. However, systemic uptake from a gel matrix is expected to be slower than from a non-gel forming solution based on studies using other gel forming solutions. The maximum plasma timolol concentration from the gel forming drop is not expected to exceed those of the 0.5% timolol maleate solution.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Because in some patients the intraocular pressure-lowering response to Timolol GFS may require a few weeks to stabilize, evaluation should include a determination of intraocular pressure after approximately 4 weeks of treatment with Timolol GFS. If the patient's intraocular pressure is still not at a satisfactory level on this regimen, concomitant therapy can be considered.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES In controlled, double-masked, multicenter clinical studies, Timolol GFS administered once daily was compared to equivalent concentrations of TIMOPTIC* (timolol maleate ophthalmic solution) administered twice daily. Timolol GFS once daily was shown to be equally effective in lowering intraocular pressure as the equivalent concentration of TIMOPTIC administered twice daily. The effect of timolol in lowering intraocular pressure was evident for 24 hours with a single dose of Timolol GFS.
Repeated observations over a three-month study period indicate that the intraocular pressure-lowering effect of Timolol GFS was consistent. The results from the clinical trials are shown in the following figures. Timolol GFS administered once daily had a safety profile similar to that of an equivalent concentration of TIMOPTIC administered twice daily.
Due to the physical characteristics of the formulation, transient blurred vision was reported more frequently in patients administered Timolol GFS [see Adverse Reactions (6) ]. Timolol GFS has not been studied in patients wearing contact lenses. figures
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In a two-year study of timolol maleate administered orally to rats, there was a statistically significant increase in the incidence of adrenal pheochromocytomas in male rats administered 300 mg/kg/day (approximately 42,000 times the systemic exposure following the maximum recommended human ophthalmic dose). Similar differences were not observed in rats administered oral doses equivalent to approximately 14,000 times the maximum recommended human ophthalmic dose.
In a lifetime oral study in mice, there were statistically significant increases in the incidence of benign and malignant pulmonary tumors, benign uterine polyps, and mammary adenocarcinomas in female mice at 500 mg/kg/day (approximately 71,000 times the systemic exposure following the maximum recommended human ophthalmic dose), but not at 5 or 50 mg/kg/day (approximately 700 or 7,000, respectively, times the systemic exposure following the maximum recommended human ophthalmic dose). In a subsequent study in female mice, in which postmortem examinations were limited to the uterus and the lungs, a statistically significant increase in the incidence of pulmonary tumors was again observed at 500 mg/kg/day.
The increased occurrence of mammary adenocarcinomas was associated with elevations in serum prolactin, which occurred in female mice administered oral timolol at 500 mg/kg/day, but not at oral doses of 5 or 50 mg/kg/day. An increased incidence of mammary adenocarcinomas in rodents has been associated with administration of several other therapeutic agents that elevate serum prolactin, but no correlation between serum prolactin levels and mammary tumors has been established in humans. Furthermore, in adult human female subjects who received oral dosages of up to 60 mg of timolol maleate (the maximum recommended human oral dosage), there were no clinically meaningful changes in serum prolactin.
Mutagenesis Timolol maleate was devoid of mutagenic potential when tested in vivo (mouse) in the micronucleus test and cytogenetic assay (doses up to 800 mg) and in vitro in a neoplastic cell transformation assay (up to 100 mcg/mL). In Ames tests, the highest concentrations of timolol employed, 5,000 or 10,000 mcg/plate, were associated with statistically significant elevations of revertants observed with tester strain TA 100 (in seven replicate assays), but not in the remaining three strains. In the assays with tester strain TA 100, no consistent dose-response relationship was observed, and the ratio of test to control revertants did not reach 2.
A ratio of 2 is usually considered the criterion for a positive Ames test. Impairment of Fertility Reproduction and fertility studies in rats demonstrated no adverse effect on male or female fertility at doses up to 21,000 times the systemic exposure following the maximum recommended human ophthalmic dose.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In a two-year study of timolol maleate administered orally to rats, there was a statistically significant increase in the incidence of adrenal pheochromocytomas in male rats administered 300 mg/kg/day (approximately 42,000 times the systemic exposure following the maximum recommended human ophthalmic dose). Similar differences were not observed in rats administered oral doses equivalent to approximately 14,000 times the maximum recommended human ophthalmic dose.
In a lifetime oral study in mice, there were statistically significant increases in the incidence of benign and malignant pulmonary tumors, benign uterine polyps, and mammary adenocarcinomas in female mice at 500 mg/kg/day (approximately 71,000 times the systemic exposure following the maximum recommended human ophthalmic dose), but not at 5 or 50 mg/kg/day (approximately 700 or 7,000, respectively, times the systemic exposure following the maximum recommended human ophthalmic dose). In a subsequent study in female mice, in which postmortem examinations were limited to the uterus and the lungs, a statistically significant increase in the incidence of pulmonary tumors was again observed at 500 mg/kg/day.
The increased occurrence of mammary adenocarcinomas was associated with elevations in serum prolactin, which occurred in female mice administered oral timolol at 500 mg/kg/day, but not at oral doses of 5 or 50 mg/kg/day. An increased incidence of mammary adenocarcinomas in rodents has been associated with administration of several other therapeutic agents that elevate serum prolactin, but no correlation between serum prolactin levels and mammary tumors has been established in humans. Furthermore, in adult human female subjects who received oral dosages of up to 60 mg of timolol maleate (the maximum recommended human oral dosage), there were no clinically meaningful changes in serum prolactin.
Mutagenesis Timolol maleate was devoid of mutagenic potential when tested in vivo (mouse) in the micronucleus test and cytogenetic assay (doses up to 800 mg) and in vitro in a neoplastic cell transformation assay (up to 100 mcg/mL). In Ames tests, the highest concentrations of timolol employed, 5,000 or 10,000 mcg/plate, were associated with statistically significant elevations of revertants observed with tester strain TA 100 (in seven replicate assays), but not in the remaining three strains. In the assays with tester strain TA 100, no consistent dose-response relationship was observed, and the ratio of test to control revertants did not reach 2.
A ratio of 2 is usually considered the criterion for a positive Ames test. Impairment of Fertility Reproduction and fertility studies in rats demonstrated no adverse effect on male or female fertility at doses up to 21,000 times the systemic exposure following the maximum recommended human ophthalmic dose.
📄 Package Label / Principal Display Panel ▾
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL Fdgdfgdf 0.5mg-5ml-carton
Package/Label Display Panel Vfdgvdfsg 0.25mg-5ml-carton
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |