
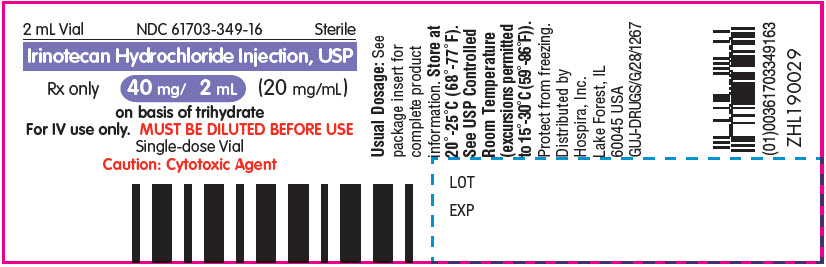
Irinotecan Hydrochloride 20 mg/mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Topoisomerase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Irinotecan is a chemotherapy that targets cancer cells directly. Depending on which product you're receiving, it's used to treat metastatic colorectal cancer (cancer of the colon o...
- What exactly is irinotecan treating in my body?
- The two biggest ones to know are diarrhea and low white blood cell counts. Diarrhea that starts more than 24 hours after your infusion can be serious — start loperamide (Imodium) a...
- What side effects should I really be watching out for?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Irinotecan Hydrochloride — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
0.9 mg / 1 mL
UNII 33X04XA5AT
Lactic acid is a naturally occurring organic acid derived from milk or plant sources. It lowers and maintains pH in formulations, helps preserve the product, and can enhance ingredient stability and absorption.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
45 mg / 1 mL
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $41.65 | $83.30 / 2 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9206 | $1.851 / J9206 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Irinotecan Hydrochloride 20 mg/mL 00143-9583-01 | Hikma | 5 ml | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mL 00143-9701-01 | Hikma | 5 ml | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mL 00143-9702-01 | Hikma | 2 ml | — | AP | FDA listed | — |
| Irinotecan hydrochloride 20 mg/mL 16714-0027-01 | Northstar | 1 vial | — | AP | FDA listed | — |
| Irinotecan hydrochloride 20 mg/mL 16714-0131-01 | Northstar | 1 vial | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mL 67184-0511-01 | Qilu | 1 vial | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mL 67184-0512-01 | Qilu | 1 vial | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mL 67184-0513-01 | Qilu | 1 vial | — | AP | FDA listed | — |
| Irinotecan hydrochloride 20 mg/mL 68083-0382-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mL 63323-0193-52 | Fresenius | 1 vial | — | AP | FDA listed | — |
| Irinotecan hydrochloride 20 mg/mL 45963-0614-85 | Actavis | 1 vial | — | AP | Discontinued | — |
| Camptosar 20 mg/mL 00009-7529-03 | Pharmacia | 1 vial | — | AP | Discontinued | — |
| Irinotecan Hydrochloride 20 mg/mL 55150-0353-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Irinotecan hydrochloride 20 mg/mL 70700-0170-22 | Xiromed | 1 vial | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mL 55150-0355-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mL 25021-0230-02 | Sagent | 1 vial | — | — | FDA listed | — |
| Camptosar 20 mg/mL 00009-0082-02 | Pharmacia | 1 vial | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mL 55150-0354-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mLthis 61703-0349-16 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Camptosar 20 mg/mL 00009-0112-05 | Pharmacia | 1 vial | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mL 60505-6128-00 | Apotex | 1 vial | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mL 60505-6272-01 | Apotex | 1 vial | — | AP | FDA listed | — |
| Irinotecan Hydrochloride 20 mg/mL 55150-0352-01 | Eugia | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 61703-0349-09 | 1 VIAL, SINGLE-DOSE in 1 CARTON (61703-349-09) / 5 mL in 1 VIAL, SINGLE-DOSE | 2008-02-27 | Active |
| 61703-0349-16 You're viewing this | 1 VIAL, SINGLE-DOSE in 1 CARTON (61703-349-16) / 2 mL in 1 VIAL, SINGLE-DOSE | 2008-02-27 | Active |
| 61703-0349-36 | 1 VIAL, SINGLE-DOSE in 1 CARTON (61703-349-36) / 25 mL in 1 VIAL, SINGLE-DOSE | 2008-02-27 | Active |
This pack accounts for about 10% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 61703-0349-16?
What NDC number is used to bill for this package of Irinotecan Hydrochloride 20 mg/mL Injection, Solution?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: DIARRHEA and MYELOSUPPRESSION • Early and late forms of diarrhea can occur. Early diarrhea may be accompanied by cholinergic symptoms which may be prevented or ameliorated by atropine. Late diarrhea can be life threatening and should be treated promptly with loperamide.
Monitor patients with diarrhea and give fluid and electrolytes as needed. Institute antibiotic therapy if patients develop ileus, fever, or severe neutropenia. Interrupt Irinotecan Hydrochloride Injection, USP and reduce subsequent doses if severe diarrhea occurs [see Dosage and Administration (2.2) and Warnings and Precautions (5.1) ]. • Severe myelosuppression may occur [see Warnings and Precautions (5.2) ].
WARNING: DIARRHEA and MYELOSUPPRESSION See full prescribing information for complete boxed warning. • Early and late forms of diarrhea can occur. Early diarrhea may be accompanied by cholinergic symptoms which may be prevented or ameliorated by atropine. Late diarrhea can be life threatening and should be treated promptly with loperamide.
Monitor patients with diarrhea and give fluid and electrolytes as needed. Institute antibiotic therapy if patients develop ileus, fever, or severe neutropenia. Interrupt Irinotecan Hydrochloride Injection, USP and reduce subsequent doses if severe diarrhea occurs.
( 2.2 , 5.1 ) • Severe myelosuppression may occur. ( 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE • Irinotecan Hydrochloride Injection, USP is indicated as a component of first-line therapy in combination with 5-fluorouracil (5-FU) and leucovorin (LV) for patients with metastatic carcinoma of the colon or rectum. • Irinotecan Hydrochloride Injection, USP is indicated for patients with metastatic carcinoma of the colon or rectum whose disease has recurred or progressed following initial fluorouracil-based therapy. Irinotecan Hydrochloride Injection, USP is a topoisomerase inhibitor indicated for: • First-line therapy in combination with 5-fluorouracil and leucovorin for patients with metastatic carcinoma of the colon or rectum.
( 1 ) • Patients with metastatic carcinoma of the colon or rectum whose disease has recurred or progressed following initial fluorouracil-based therapy. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Colorectal cancer combination regimen 1: Irinotecan Hydrochloride Injection, USP 125 mg/m 2 intravenous infusion over 90 minutes on days 1, 8,15, 22 with LV 20 mg/m 2 intravenous bolus infusion on days 1, 8, 15, 22 followed by 5-FU intravenous bolus infusion on days 1, 8, 15, 22 every 6 weeks. ( 2.1 ) • Colorectal cancer combination regimen 2: Irinotecan Hydrochloride Injection, USP 180 mg/m 2 intravenous infusion over 90 minutes on days 1, 15, 29 with LV 200 mg/m 2 intravenous infusion over 2 hours on days 1, 2, 15, 16, 29, 30 followed by 5-FU 400 mg/m 2 intravenous bolus infusion on days 1, 2, 15, 16, 29, 30 and 5-FU 600 mg/m 2 intravenous infusion over 22 hours on days 1, 2, 15, 16, 29, 30.
( 2.1 ) • Colorectal cancer single agent regimen 1: Irinotecan Hydrochloride Injection, USP 125 mg/m 2 intravenous infusion over 90 minutes on days 1, 8, 15, 22 then 2-week rest. ( 2.2 ) • Colorectal cancer single agent regimen 2: Irinotecan Hydrochloride Injection, USP 350 mg/m 2 intravenous infusion over 90 minutes on day 1 every 3 weeks. ( 2.2 )
2.1Colorectal Cancer Combination Regimens 1 and 2 Administer Irinotecan Hydrochloride Injection, USP as a 90-minute intravenous infusion followed by LV and 5-FU. The currently recommended regimens are shown in Table 1. A reduction in the starting dose by one dose level of Irinotecan Hydrochloride Injection, USP may be considered for patients with any of the following conditions: prior pelvic/abdominal radiotherapy, performance status of 2, or increased bilirubin levels.
Dosing for patients with bilirubin >2 mg/dL cannot be recommended because there is insufficient information to recommend a dose in these patients. Table 1. Combination-Agent Dosage Regimens and Dose Modifications Dose reductions beyond Dose Level –2 by decrements of ≈ 20% may be warranted for patients continuing to experience toxicity.
Provided intolerable toxicity does not develop, treatment with additional cycles may be continued indefinitely as long as patients continue to experience clinical benefit. Regimen 1 6-wk cycle with bolus 5-FU/LV (next cycle begins on day 43) Irinotecan Hydrochloride Injection, USP LV 5-FU 125 mg/m 2 intravenous infusion over 90 minutes, days 1,8,15,22 20 mg/m 2 intravenous injection bolus, days 1,8,15,22 500 mg/m 2 intravenous injection bolus, days 1,8,15,22 Starting Dose & Modified Dose Levels (mg/m 2 ) Starting Dose Dose Level -1 Dose Level -2 Irinotecan Hydrochloride Injection, USP 125 100 75 LV 20 20 20 5-FU 500 400 300 Regimen 2 6-wk cycle with infusional 5-FU/LV (next cycle begins on day 43) Irinotecan Hydrochloride Injection, USP LV 5-FU Bolus 5-FU Infusion Infusion follows bolus administration.
180 mg/m 2 intravenous infusion over 90 minutes, days 1,15,29 200 mg/m 2 intravenous infusion over 2 hours, days 1,2,15,16,29,30 400 mg/m 2 intravenous injection bolus, days 1,2,15,16,29,30 600 mg/m 2 intravenous infusion over 22 hours, days 1,2,15,16,29,30 Starting Dose & Modified Dose Levels (mg/m 2 ) Starting Dose Dose Level -1 Dose Level -2 Irinotecan Hydrochloride Injection, USP 180 150 120 LV 200 200 200 5-FU Bolus 400 320 240 5-FU Infusion 600 480 360 Dosing for patients with bilirubin >2 mg/dL cannot be recommended because there is insufficient information to recommend a dose in these patients [see Warnings and Precautions (5.10) , Use in Specific Populations (8.7) and Clinical Pharmacology (12.3) ] .
Dose Modifications Based on recommended dose levels described in Table 1, Combination Regimens of Irinotecan Hydrochloride Injection, USP and Dose Modifications, subsequent doses should be adjusted as suggested in Table 2, Recommended Dose Modifications for Combination Regimens. All dose modifications should be based on the worst preceding toxicity. Table 2.
Recommended Dose Modifications for Irinotecan Hydrochloride Injection, USP /5-Fluorouracil (5-FU)/Leucovorin (LV) Combination Schedules Patients should return to pre-treatment bowel function without requiring…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 40 mg/2 mL (20 mg/mL), 100 mg/5 mL (20 mg/mL), and 500 mg/25 mL (20 mg/mL) sterile, pale yellow, clear, aqueous solution in a single-dose vial. Injection: 40 mg/2 mL (20 mg/mL), 100 mg/5 mL (20 mg/mL), and 500 mg/25 mL (20 mg/mL) solution in a single-dose vial. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS • Irinotecan Hydrochloride Injection, USP is contraindicated in patients with a known hypersensitivity to the drug or its excipients. • Hypersensitivity to Irinotecan Hydrochloride Injection, USP or its excipients ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Diarrhea and Cholinergic Reactions: Early diarrhea (occurring during or shortly after infusion of Irinotecan Hydrochloride Injection, USP) is usually transient and may be accompanied by cholinergic symptoms. Consider prophylactic or therapeutic administration of 0.25 mg to 1 mg of intravenous or subcutaneous atropine (unless clinically contraindicated). Late diarrhea (generally occurring more than 24 hours after administration of Irinotecan Hydrochloride Injection, USP) can occur.
Monitor and replace fluid and electrolytes. Treat with loperamide. Use antibiotic support for ileus and fever.
Interrupt Irinotecan Hydrochloride Injection, USP and reduce subsequent doses if severe diarrhea occurs. ( 5.1 ) • Myelosuppression: Manage promptly with antibiotic support. Interrupt Irinotecan Hydrochloride Injection, USP and reduce subsequent doses if necessary.
( 5.2 ) • Increased Risk of Neutropenia in Patients With Reduced UGT1A1 Activity: Individuals with UGT1A1*28/*28, or *6/*6, or *6/*28 genotypes are at increased risk for severe neutropenia during Irinotecan Hydrochloride Injection, USP treatment. ( 5.3 ) • Hypersensitivity: Hypersensitivity reactions including severe anaphylactic or anaphylactoid reactions have been observed. Discontinue Irinotecan Hydrochloride Injection, USP if this occurs.
( 5.4 ) • Renal Impairment/Renal Failure: Rare cases of renal impairment and acute renal failure have been identified, usually in patients who became volume depleted from severe vomiting and/or diarrhea. ( 5.5 ) • Pulmonary Toxicity: Interstitial Pulmonary Disease (IPD)-like events, including fatalities, have occurred. Interrupt for new or progressive dyspnea, cough, and fever pending evaluation.
If IPD diagnosed, discontinue and institute appropriate treatment as needed. ( 5.6 ) • Toxicity of the 5 Day Regimen: Irinotecan Hydrochloride Injection, USP should not be used in combination with a regimen of 5-FU/LV administered for 4–5 consecutive days every 4 weeks outside of a clinical study. ( 5.7 ) • Embryo-Fetal Toxicity: Irinotecan Hydrochloride Injection, USP can cause fetal harm.
Advise females of reproductive potential of the potential risk to a fetus and to use effective contraception. Advise male patients with female partners of reproductive potential to use condoms. ( 5.9 , 8.1 , 8.3 ) • Patients With Hepatic Impairment: In clinical trials, Irinotecan Hydrochloride Injection, USP has not been administered to patients with serum bilirubin >2.0 mg/dL, or transaminases >3 times ULN if no liver metastases, or transaminases >5 times ULN if liver metastases.
With the weekly dosage schedule, patients with total bilirubin levels 1.0–2.0 mg/dL had greater likelihood of grade 3–4 neutropenia. ( 5.10 )
5.1Diarrhea and Cholinergic Reactions Early diarrhea (occurring during or shortly after infusion of Irinotecan Hydrochloride Injection, USP) is usually transient and infrequently severe. It may be accompanied by cholinergic symptoms of rhinitis, increased salivation, miosis, lacrimation, diaphoresis, flushing, and intestinal hyperperistalsis that can cause abdominal cramping. Bradycardia may also occur.
Early diarrhea and other cholinergic symptoms may be prevented or treated. Consider prophylactic or therapeutic administration of 0.25 mg to 1 mg of intravenous or subcutaneous atropine (unless clinically contraindicated). These symptoms are expected to occur more frequently with higher irinotecan doses.
Late diarrhea (generally occurring more than 24 hours after administration of Irinotecan Hydrochloride Injection, USP) can be life threatening since it may be prolonged and may lead to dehydration, electrolyte imbalance, or sepsis. Grade 3–4 late diarrhea occurred in 23–31% of patients receiving weekly dosing. In the clinical studies, the median time to the onset of late diarrhea was 5 days with 3-week dosing and 11 days with weekly dosing.
Late diarrhea can be complicated by colitis, ulceration, bleeding, ileus, obstru…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Common adverse reactions (≥30%) observed in combination therapy clinical studies are: nausea, vomiting, abdominal pain, diarrhea, constipation, anorexia, mucositis, neutropenia, leukopenia (including lymphocytopenia), anemia, thrombocytopenia, asthenia, pain, fever, infection, abnormal bilirubin, alopecia. ( 6.1 ) Common adverse reactions (≥30%) observed in single agent therapy clinical studies are: nausea, vomiting, abdominal pain, diarrhea, constipation, anorexia, neutropenia, leukopenia (including lymphocytopenia), anemia, asthenia, fever, body weight decreasing, alopecia.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Hospira, Inc. at 1-800-441-4100, or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Studies Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Common adverse reactions (≥30%) observed in combination therapy clinical studies are: nausea, vomiting, abdominal pain, diarrhea, constipation, anorexia, mucositis, neutropenia, leukopenia (including lymphocytopenia), anemia, thrombocytopenia, asthenia, pain, fever, infection, abnormal bilirubin, and alopecia.
Common adverse reactions (>30%) observed in single agent therapy clinical studies are: nausea, vomiting, abdominal pain, diarrhea, constipation, anorexia, neutropenia, leukopenia (including lymphocytopenia), anemia, asthenia, fever, body weight decreasing, and alopecia. First-Line Combination Therapy A total of 955 patients with metastatic colorectal cancer received the recommended regimens of irinotecan in combination with 5-FU/LV, 5-FU/LV alone, or irinotecan alone. In the two phase 3 studies, 370 patients received irinotecan in combination with 5-FU/LV, 362 patients received 5-FU/LV alone, and 223 patients received irinotecan alone [see Dosage and Administration (2) ] .
In Study 1, 49 (7.3%) patients died within 30 days of last study treatment: 21 (9.3%) received irinotecan in combination with 5-FU/LV, 15 (6.8%) received 5-FU/LV alone, and 13 (5.8%) received irinotecan alone. Deaths potentially related to treatment occurred in 2 (0.9%) patients who received irinotecan in combination with 5-FU/LV (2 neutropenic fever/sepsis), 3 (1.4%) patients who received 5-FU/LV alone (1 neutropenic fever/sepsis, 1 CNS bleeding during thrombocytopenia, 1 unknown) and 2 (0.9%) patients who received irinotecan alone (2 neutropenic fever).
Deaths from any cause within 60 days of first study treatment were reported for 15 (6.7%) patients who received irinotecan in combination with 5-FU/LV, 16 (7.3%) patients who received 5-FU/LV alone, and 15 (6.7%) patients who received irinotecan alone. Discontinuations due to adverse events were reported for 17 (7.6%) patients who received irinotecan in combination with 5FU/LV, 14 (6.4%) patients who received 5-FU/LV alone, and 26 (11.7%) patients who received irinotecan alone. In Study 2, 10 (3.5%) patients died within 30 days of last study treatment: 6 (4.1%) received irinotecan in combination with 5-FU/LV and 4 (2.8%) received 5-FU/LV alone.
There was one potentially treatment-related death, which occurred in a patient who received irinotecan in combination with 5-FU/LV (0.7%, neutropenic sepsis). Deaths from any cause within 60 days of first study treatment were reported for 3 (2.1%) patients who received irinotecan in combination with 5-FU/LV and 2 (1.4%) patients who received 5-FU/LV alone. Discontinuations due to adverse events were reported for 9 (6.2%) patients who received irinotecan in combination with 5FU/LV and 1 (0.7%) patient who received 5-FU/LV alone.
The most clinically significant adverse events for patients receiving irinotecan-based therapy were diarrhea, nausea, vomiting, neutropenia, and alopecia. The most clinically significant adverse events for pati…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong CYP3A4 Inducers: Do not administer strong CYP3A4 inducers with Irinotecan Hydrochloride Injection, USP. ( 7.2 ) • Strong CYP3A4 Inhibitors: Do not administer strong CYP3A4 inhibitors with Irinotecan Hydrochloride Injection, USP. ( 7.3 ) 7.1 5-Fluorouracil (5-FU) and Leucovorin (LV) In a phase 1 clinical study involving irinotecan, 5-fluorouracil (5-FU), and leucovorin (LV) in 26 patients with solid tumors, the disposition of irinotecan was not substantially altered when the drugs were co-administered.
Although the C max and AUC 0–24 of SN-38, the active metabolite, were reduced (by 14% and 8%, respectively) when irinotecan was followed by 5-FU and LV administration compared with when irinotecan was given alone, this sequence of administration was used in the combination trials and is recommended [see Dosage and Administration (2) ] . Formal in vivo or in vitro drug interaction studies to evaluate the influence of irinotecan on the disposition of 5-FU and LV have not been conducted.
7.2Strong CYP3A4 Inducers Exposure to irinotecan or its active metabolite SN-38 is substantially reduced in adult and pediatric patients concomitantly receiving the CYP3A4 enzyme-inducing anticonvulsants phenytoin, phenobarbital, carbamazepine, or St. John's wort. The appropriate starting dose for patients taking these or other strong inducers such as rifampin and rifabutin has not been defined.
Consider substituting non-enzyme inducing therapies at least 2 weeks prior to initiation of irinotecan therapy. Do not administer strong CYP3A4 inducers with irinotecan unless there are no therapeutic alternatives.
7.3Strong CYP3A4 or UGT1A1 Inhibitors Irinotecan and its active metabolite, SN-38, are metabolized via the human cytochrome P450 3A4 isoenzyme (CYP3A4) and uridine diphosphate-glucuronosyl transferase 1A1 (UGT1A1), respectively, [see Clinical Pharmacology (12.3) ] . Patients receiving concomitant ketoconazole, a CYP3A4 and UGT1A1 inhibitor, have increased exposure to irinotecan and its active metabolite SN-38. Coadministration of irinotecan with other inhibitors of CYP3A4 (e.g., clarithromycin, indinavir, itraconazole, lopinavir, nefazodone, nelfinavir, ritonavir, saquinavir, telaprevir, voriconazole) or UGT1A1 (e.g., atazanavir, gemfibrozil, indinavir) may increase systemic exposure to irinotecan or SN-38.
Discontinue strong CYP3A4 inhibitors at least 1 week prior to starting irinotecan therapy. Do not administer strong CYP3A4 or UGT1A1 inhibitors with irinotecan unless there are no therapeutic alternatives.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Advise not to breastfeed. ( 8.2 ) • Geriatric Use: Closely monitor patients greater than 65 years of age because of a greater risk of early and late diarrhea in this population. ( 8.5 ) • Patients With Renal Impairment: Use caution and do not use in patients on dialysis. ( 8.6 ) • Patients With Hepatic Impairment: Use caution. ( 2.1 , 5.10 , 8.7 , 12.3 )
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action, Irinotecan Hydrochloride Injection, USP can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . Available postmarketing and published data reporting the use of Irinotecan Hydrochloride Injection, USP in pregnant women, are insufficient and confounded by the concomitant use of other cytotoxic drugs, to evaluate for any drug-associated risk for major birth defects, miscarriage, or adverse maternal or fetal outcomes.
In animal studies, intravenous administration of irinotecan to rats and rabbits during the period of organogenesis resulted in embryofetal mortality and teratogenicity in pregnant animals at exposures lower than the human exposure based on AUC at the clinical dose of 125 mg/m 2 ( see Data ). Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data Radioactivity related to 14 C-irinotecan crosses the placenta of rats following intravenous administration. Intravenous administration of irinotecan to rats at a dose of 6 mg/kg/day (approximately 0.2 times the clinical exposure (AUC) at the 125 mg/m 2 dose based on exposure data from a separate rat study) during the period of organogenesis resulted in increased post-implantation loss and decreased numbers of live fetuses; at doses ≥ 1.2 mg/kg/day (approximately 0.03 times the clinical exposure (AUC) at the 125 mg/m 2 dose based on exposure data from a separate rat study) there were increases in a variety of external, visceral, and skeletal abnormalities.
Administration of irinotecan to pregnant rabbits at a dose of 6 mg/kg (approximately half of the clinical dose of 125 mg/m 2 based on BSA) resulted in similar findings to those in rats, with increased post-implantation loss, decreased live fetuses, and increased external, visceral, and skeletal abnormalities. Irinotecan administered to rat dams for the period following organogenesis through weaning at doses of 6 mg/kg/day caused decreased learning ability and decreased female body weights in the offspring.
8.2Lactation Risk Summary Irinotecan and its metabolites are present in human milk. There is no information regarding the effects of irinotecan on the breastfed infant, or on milk production. Because of the potential for serious adverse reactions from Irinotecan Hydrochloride Injection, USP in the breastfed child, advise lactating women not to breastfeed during treatment with Irinotecan Hydrochloride Injection, USP and for 7 days after the final dose.
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify the pregnancy status in female patients of reproductive potential prior to initiating Irinotecan Hydrochloride Injection, USP. Contraception Irinotecan Hydrochloride Injection, USP can cause fetal harm when administered to a pregnant woman. Females Advise female patients of reproductive potential to use effective contraception during treatment and for 6 months after the final dose of Irinotecan Hydrochloride Injection, USP [see Use in Specific Populations (8.1) and Nonclinical Toxicology (13.1) ] .
Males Due to the potential for genotoxicity, advise male patients with female partners of reproductive potential to use condoms during treatment and for 3 months after the final dose of Irinotecan Hydrochloride Injection, USP [see Nonclinical Toxicology (13.1) ]. Infertility Females Based on…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action, Irinotecan Hydrochloride Injection, USP can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . Available postmarketing and published data reporting the use of Irinotecan Hydrochloride Injection, USP in pregnant women, are insufficient and confounded by the concomitant use of other cytotoxic drugs, to evaluate for any drug-associated risk for major birth defects, miscarriage, or adverse maternal or fetal outcomes.
In animal studies, intravenous administration of irinotecan to rats and rabbits during the period of organogenesis resulted in embryofetal mortality and teratogenicity in pregnant animals at exposures lower than the human exposure based on AUC at the clinical dose of 125 mg/m 2 ( see Data ). Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data Radioactivity related to 14 C-irinotecan crosses the placenta of rats following intravenous administration. Intravenous administration of irinotecan to rats at a dose of 6 mg/kg/day (approximately 0.2 times the clinical exposure (AUC) at the 125 mg/m 2 dose based on exposure data from a separate rat study) during the period of organogenesis resulted in increased post-implantation loss and decreased numbers of live fetuses; at doses ≥ 1.2 mg/kg/day (approximately 0.03 times the clinical exposure (AUC) at the 125 mg/m 2 dose based on exposure data from a separate rat study) there were increases in a variety of external, visceral, and skeletal abnormalities.
Administration of irinotecan to pregnant rabbits at a dose of 6 mg/kg (approximately half of the clinical dose of 125 mg/m 2 based on BSA) resulted in similar findings to those in rats, with increased post-implantation loss, decreased live fetuses, and increased external, visceral, and skeletal abnormalities. Irinotecan administered to rat dams for the period following organogenesis through weaning at doses of 6 mg/kg/day caused decreased learning ability and decreased female body weights in the offspring.
🧒 Pediatric Use ▾
8.4Pediatric Use The effectiveness of irinotecan in pediatric patients has not been established. Results from two open-label, single arm studies were evaluated. One hundred and seventy children with refractory solid tumors were enrolled in one phase 2 trial in which 50 mg/m 2 of irinotecan was infused for 5 consecutive days every 3 weeks.
Grade 3–4 neutropenia was experienced by 54 (31.8%) patients. Neutropenia was complicated by fever in 15 (8.8%) patients. Grade 3–4 diarrhea was observed in 35 (20.6%) patients.
This adverse event profile was comparable to that observed in adults. In the second phase 2 trial of 21 children with previously untreated rhabdomyosarcoma, 20 mg/m 2 of irinotecan was infused for 5 consecutive days on weeks 0, 1, 3 and 4. This single agent therapy was followed by multimodal therapy.
Accrual to the single agent irinotecan phase was halted due to the high rate (28.6%) of progressive disease and the early deaths (14%). The adverse event profile was different in this study from that observed in adults; the most significant grade 3 or 4 adverse events were dehydration experienced by 6 patients (28.6%) associated with severe hypokalemia in 5 patients (23.8%) and hyponatremia in 3 patients (14.3%); in addition Grade 3–4 infection was reported in 5 patients (23.8%) (across all courses of therapy and irrespective of causal relationship).
Pharmacokinetic parameters for irinotecan and SN-38 were determined in 2 pediatric solid-tumor trials at dose levels of 50 mg/m 2 (60-min infusion, n=48) and 125 mg/m 2 (90-min infusion, n=6). Irinotecan clearance (mean ± S.D.) was 17.3 ±
6.7L/h/m 2 for the 50 mg/m 2 dose and 16.2 ±
4.6L/h/m 2 for the 125 mg/m 2 dose, which is comparable to that in adults. Dose-normalized SN-38 AUC values were comparable between adults and children. Minimal accumulation of irinotecan and SN-38 was observed in children on daily dosing regimens [daily × 5 every 3 weeks or (daily × 5) × 2 weeks every 3 weeks].
🧓 Geriatric Use ▾
8.5Geriatric Use Patients greater than 65 years of age should be closely monitored because of a greater risk of early and late diarrhea in this population [see Clinical Pharmacology (12.3) and Adverse Reactions (6.1) ] . The starting dose of Irinotecan Hydrochloride Injection, USP in patients 70 years and older for the once-every-3-week-dosage schedule should be 300 mg/m 2 [see Clinical Pharmacology (12.3) and Dosage and Administration (2) ] . The frequency of grade 3 and 4 late diarrhea by age was significantly greater in patients ≥65 years than in patients <65 years (40% [53/133] versus 23% [40/171]; p=0.002).
In another study of 183 patients treated on the weekly schedule, the frequency of grade 3 or 4 late diarrhea in patients ≥65 years of age was 28.6% [26/91] and in patients <65 years of age was 23.9% [22/92].
🆘 Overdosage ▾
10 OVERDOSAGE In U.S. phase 1 trials, single doses of up to 345 mg/m 2 of irinotecan were administered to patients with various cancers. Single doses of up to 750 mg/m 2 of irinotecan have been given in non-U.S. trials. The adverse events in these patients were similar to those reported with the recommended dosage and regimen.
There have been reports of overdosage at doses up to approximately twice the recommended therapeutic dose, which may be fatal. The most significant adverse reactions reported were severe neutropenia and severe diarrhea. There is no known antidote for overdosage of Irinotecan Hydrochloride Injection, USP.
Maximum supportive care should be instituted to prevent dehydration due to diarrhea and to treat any infectious complications.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Irinotecan is a derivative of camptothecin. Camptothecins interact specifically with the enzyme topoisomerase I, which relieves torsional strain in DNA by inducing reversible single-strand breaks. Irinotecan and its active metabolite SN-38 bind to the topoisomerase I-DNA complex and prevent religation of these single-strand breaks.
Current research suggests that the cytotoxicity of irinotecan is due to double-strand DNA damage produced during DNA synthesis when replication enzymes interact with the ternary complex formed by topoisomerase I, DNA, and either irinotecan or SN-38. Mammalian cells cannot efficiently repair these double-strand breaks.
12.2Pharmacodynamics Irinotecan serves as a water-soluble precursor of the lipophilic metabolite SN-38. SN-38 is formed from irinotecan by carboxylesterase-mediated cleavage of the carbamate bond between the camptothecin moiety and the dipiperidino side chain. SN-38 is approximately 1000 times as potent as irinotecan as an inhibitor of topoisomerase I purified from human and rodent tumor cell lines.
In vitro cytotoxicity assays show that the potency of SN-38 relative to irinotecan varies from 2- to 2000-fold; however, the plasma area under the concentration versus time curve (AUC) values for SN-38 are 2% to 8% of irinotecan and SN-38 is 95% bound to plasma proteins compared to approximately 50% bound to plasma proteins for irinotecan [see Clinical Pharmacology (12.3) ] . The precise contribution of SN-38 to the activity of Irinotecan Hydrochloride Injection, USP is thus unknown. Both irinotecan and SN-38 exist in an active lactone form and an inactive hydroxy acid anion form.
A pH-dependent equilibrium exists between the two forms such that an acid pH promotes the formation of the lactone, while a more basic pH favors the hydroxy acid anion form. Administration of irinotecan has resulted in antitumor activity in mice bearing cancers of rodent origin and in human carcinoma xenografts of various histological types.
12.3Pharmacokinetics After intravenous infusion of irinotecan in humans, irinotecan plasma concentrations decline in a multiexponential manner, with a mean terminal elimination half-life of about 6 to 12 hours. The mean terminal elimination half-life of the active metabolite SN-38 is about 10 to 20 hours. The half-lives of the lactone (active) forms of irinotecan and SN-38 are similar to those of total irinotecan and SN-38, as the lactone and hydroxy acid forms are in equilibrium.
Over the recommended dose range of 50 to 350 mg/m 2 , the AUC of irinotecan increases linearly with dose; the AUC of SN-38 increases less than proportionally with dose. Maximum concentrations of the active metabolite SN-38 are generally seen within 1 hour following the end of a 90-minute infusion of irinotecan. Pharmacokinetic parameters for irinotecan and SN-38 following a 90-minute infusion of irinotecan at dose levels of 125 and 340 mg/m 2 determined in two clinical studies in patients with solid tumors are summarized in Table 9: Table 9.
Summary of Mean (±Standard Deviation) Irinotecan and SN-38 Pharmacokinetic Parameters in Patients With Solid Tumors Dose (mg/m 2 ) Irinotecan SN-38 C max (ng/mL) AUC 0–24 (ng∙h/mL) t 1/2 (h) V z (L/m 2 ) CL (L/h/m 2 ) C max (ng/mL) AUC 0–24 (ng∙h/mL) t 1/2 (h) C max - Maximum plasma concentration AUC 0–24 - Area under the plasma concentration-time curve from time 0 to 24 hours after the end of the 90-minute infusion t 1/2 - Terminal elimination half-life V z - Volume of distribution of terminal elimination phase CL - Total systemic clearance 125 (N = 64) 1,660 ±797 10,200 ±3,270
5.8Plasma specimens collected for 24 hours following the end of the 90-minute infusion. ±0.7 110 ±48.5 13.3 ±6.01 26.3 ±11.9 229 ±108 10.4 ±3.1 340 (N = 6) 3,392 ±874 20,604 ±6,027
11.7Plasma specimens collected for 48 hours following the end of the 90-minute infusion. Because of the longer collection period, these values provide a mor…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Irinotecan is a derivative of camptothecin. Camptothecins interact specifically with the enzyme topoisomerase I, which relieves torsional strain in DNA by inducing reversible single-strand breaks. Irinotecan and its active metabolite SN-38 bind to the topoisomerase I-DNA complex and prevent religation of these single-strand breaks.
Current research suggests that the cytotoxicity of irinotecan is due to double-strand DNA damage produced during DNA synthesis when replication enzymes interact with the ternary complex formed by topoisomerase I, DNA, and either irinotecan or SN-38. Mammalian cells cannot efficiently repair these double-strand breaks.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Irinotecan Hydrochloride Injection, USP is available as a sterile, pale yellow, clear, aqueous solution in a vial packaged within a carton in the following packaging configurations: • Single-dose amber glass vials: • NDC 61703-349-16, 40 mg/2 mL (20 mg/mL) • NDC 61703-349-09, 100 mg/5 mL (20 mg/mL) • NDC 61703-349-36, 500 mg/25 mL (20 mg/mL) Store at 20° to 25°C (68° to 77°F). See USP Controlled Room Temperature (excursions permitted to 15° to 30°C (59° to 86°F)). Protect from light.
It is recommended that the vial should remain in the carton until the time of use. Protect from freezing. Store Upright.
Inspect the vial for damage and visible signs of leaks before removing from the carton. If damaged, incinerate the unopened package. Irinotecan Hydrochloride Injection, USP is a hazardous drug.
Follow special handling and disposal procedures. 1
📦 Storage and Handling ▾
Store at 20° to 25°C (68° to 77°F). See USP Controlled Room Temperature (excursions permitted to 15° to 30°C (59° to 86°F)). Protect from light.
It is recommended that the vial should remain in the carton until the time of use. Protect from freezing. Store Upright.
Inspect the vial for damage and visible signs of leaks before removing from the carton. If damaged, incinerate the unopened package. Irinotecan Hydrochloride Injection, USP is a hazardous drug.
Follow special handling and disposal procedures. 1
📋 Description ▾
11 DESCRIPTION Irinotecan Hydrochloride Injection, USP is an antineoplastic agent of the topoisomerase I inhibitor class. Irinotecan Hydrochloride Injection, USP is supplied as a sterile, pale yellow, clear, aqueous solution. Each milliliter of solution contains 20 mg of irinotecan hydrochloride (on the basis of the trihydrate salt), 45 mg of sorbitol, NF, and 0.9 mg of lactic acid, USP and Water for Injection, USP.
The pH of the solution has been adjusted to 3.5 (range, 3.0 to 3.8) with sodium hydroxide or hydrochloric acid. Irinotecan Hydrochloride Injection, USP is intended for dilution with 5% Dextrose Injection, USP (D5W), or 0.9% Sodium Chloride Injection, USP, prior to intravenous infusion. The preferred diluent is 5% Dextrose Injection, USP.
Irinotecan hydrochloride is a semisynthetic derivative of camptothecin, an alkaloid extract from plants such as Camptotheca acuminata or is chemically synthesized. The chemical name is ( S ) -4,11-diethyl-3,4,12,14-tetrahydro-4-hydroxy-3,14-dioxo1 H- pyrano[3',4':6,7]-indolizino[1,2-b]quinolin-9-yl-[1,4'bipiperidine]-1'-carboxylate, monohydrochloride, trihydrate. Its empirical formula is C 33 H 38 N 4 O 6 ∙HCl∙3H 2 O and molecular weight is 677.19.
It is slightly soluble in water and organic solvents. Its structural formula is as follows: Irinotecan Hydrochloride Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION • Patients and caregivers should be informed of gastrointestinal complications, such as nausea, vomiting, abdominal cramping, and diarrhea. Patients should have loperamide readily available to begin treatment for late diarrhea (generally occurring more than 24 hours after administration of Irinotecan Hydrochloride Injection, USP). Begin loperamide at the first episode of poorly formed or loose stools or the earliest onset of bowel movements more frequent than normal.
One dosage regimen for loperamide is 4 mg at the first onset of late diarrhea and then 2 mg every 2 hours until the patient is diarrhea-free for at least 12 hours. Loperamide is not recommended to be used for more than 48 consecutive hours at these doses, because of the risk of paralytic ileus. During the night, the patient may take 4 mg of loperamide every 4 hours.
Patients should contact their physician if any of the following occur: diarrhea for the first time during treatment; black or bloody stools; symptoms of dehydration such as lightheadedness, dizziness, or faintness; inability to take fluids by mouth due to nausea or vomiting; or inability to get diarrhea under control within 24 hours. • Patients should be warned about the potential for dizziness or visual disturbances which may occur within 24 hours following the administration of Irinotecan Hydrochloride Injection, USP. • Explain the significance of routine blood cell counts.
Instruct patients to monitor their temperature frequently and immediately report any occurrence of fever or infection. • Embryo-Fetal Toxicity [see Warnings and Precautions (5.9) , Use in Specific Populations (8.1 , 8.3) , Clinical Pharmacology (12.1) and Nonclinical Toxicology (13.1) ] • Advise pregnant women and females of reproductive potential of the potential risk to a fetus and to inform their healthcare provider of a known or suspected pregnancy. • Advise females of reproductive potential to use effective contraception during treatment with Irinotecan Hydrochloride Injection, USP and for 6 months after the final dose. • Advise male patients with female partners of reproductive potential to use condoms during treatment and for 3 months after the final dose of Irinotecan Hydrochloride Injection, USP. • Lactation • Advise women not to breastfeed during treatment with Irinotecan Hydrochloride Injection, USP and for at least 7 days after the final dose [see Use in Specific Populations (8.2) ] . • Infertility • Advise females and males of reproductive potential that Irinotecan Hydrochloride Injection, USP may impair fertility [see Use in Specific Populations (8.3) ]. • Patients should be alerted to the possibility of alopecia. • Contains sorbitol.