
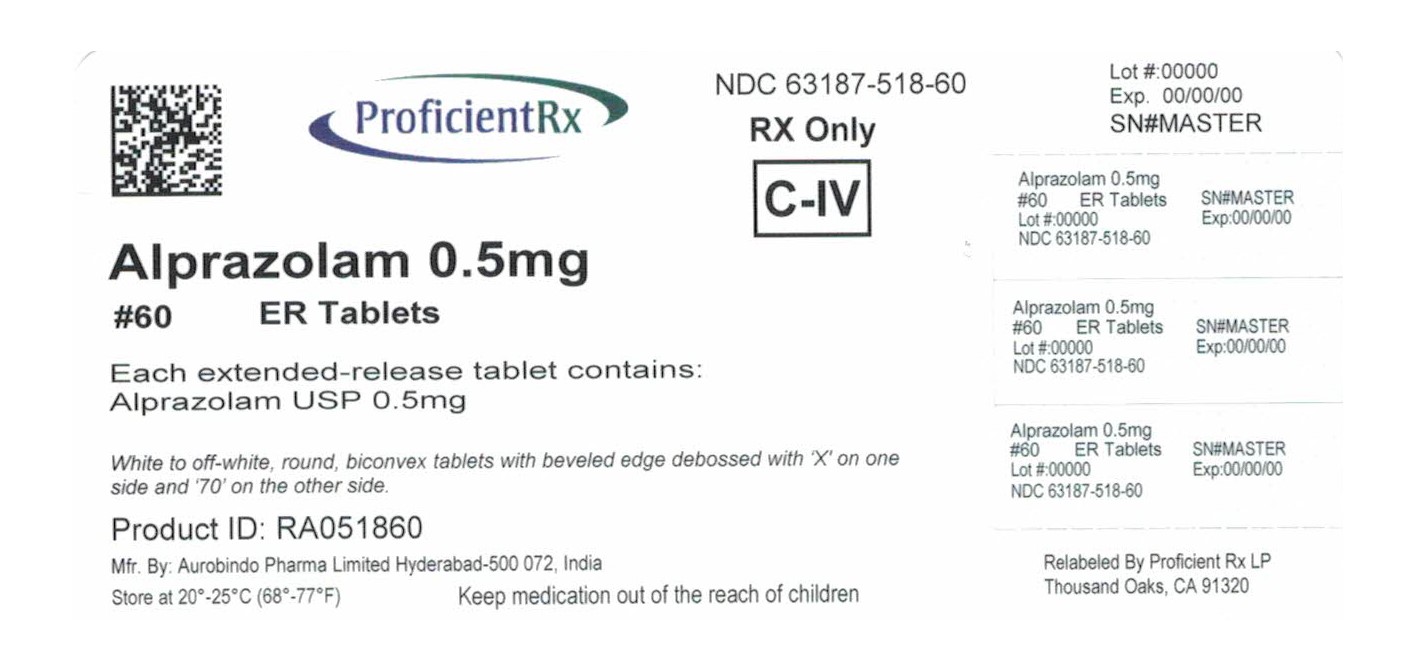
Alprazolam .5 mg Tablet, Extended Release, 60-count
Other active recalls for Alprazolam (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Benzodiazepine class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Alprazolam is used to treat anxiety disorders and panic disorder (sudden, unexpected attacks of extreme fear and worry about these attacks). Alprazolam is in a class of medications called benzodiazepines. It works by decreasing abnormal excitement in the brain.
Read the full MedlinePlus article ↗- Alprazolam is used to treat generalized anxiety disorder (GAD) and panic disorder — including panic disorder that involves a fear of being in public places (agoraphobia). Different...
- It can, especially when you first start taking it or if your dose changes. Sedation, sleepiness, and memory or concentration issues are among the most commonly reported side effect...
- Will alprazolam make me feel drowsy or foggy?
- Please don't stop on your own — this is really important. Your body can become physically dependent on alprazolam even after short-term use, and stopping suddenly can trigger serio...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Alprazolam — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII B1QE5P712K
Hypromellose 2208 is a plant-derived thickening agent that dissolves in water. It's used as a binder to help hold tablet ingredients together and as a coating on pills to control how quickly the medicine releases in your body.
-
UNII 39J80LT57T
Hypromellose 2208 is a plant-derived thickening agent used as a binder and film-coating material. It helps hold tablet ingredients together and creates a protective coating on pills to control how quickly medicine dissolves.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.5455 | $32.73 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Alprazolam XR .5 mg 59762-0057-01 | Mylan | 60 tablets | $0.148 | AB | Availability likely | — |
| Alprazolam .5 mg 65862-0454-60 | Aurobindo | 60 tablets | $0.148 | — | Availability likely | — |
| Alprazolam Extended Release .5 mg 00228-3083-06 | Actavis | 60 tablets | $0.157 | AB | Discontinued | — |
| Xanax XR .5 mg 58151-0503-91 | Viatris | 60 tablets | — | AB | Discontinued | — |
| Alprazolam .5 mgthis 63187-0518-60 | Proficient | 60 tablets | — | AB | FDA listed | — |
| Alprazolam .5 mg 65162-0809-03 | Amneal | 30 tablets | — | AB | FDA listed | — |
| Alprazolam Extended Release .5 mg 71335-1129-01 | Bryant | 60 tablets | — | AB | Discontinued | — |
| Alprazolam .5 mg 71335-1669-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Alprazolam Extended Release .5 mg 72162-1059-02 | Bryant | 45 tablets | — | AB | FDA listed | — |
| Alprazolam .5 mg 76420-0652-30 | Asclemed | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 63187-0518-30 | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE (63187-518-30) | 2018-12-01 | Active |
| 63187-0518-60 You're viewing this | 60 TABLET, EXTENDED RELEASE in 1 BOTTLE (63187-518-60) | 2018-12-01 | Active |
| 63187-0518-90 | 90 TABLET, EXTENDED RELEASE in 1 BOTTLE (63187-518-90) | 2018-12-01 | Active |
You're viewing one of 3 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 63187-0518-60?
What is the difference between NDC 63187-0518-60 and NDC 63187-0518-30?
What NDC number is used to bill for this package of Alprazolam .5 mg Tablet, Extended Release?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Alprazolam extended-release tablets USP are indicated for the treatment of panic disorder, with or without agoraphobia. This claim is supported on the basis of two positive studies with alprazolam extended-release tablets USP conducted in patients whose diagnoses corresponded closely to the DSM-III-R/IV criteria for panic disorder (see CLINICAL EFFICACY TRIALS ). Panic disorder (DSM-IV) is characterized by recurrent unexpected panic attacks, i.e., a discrete period of intense fear or discomfort in which four (or more) of the following symptoms develop abruptly and reach a peak within 10 minutes: (1) palpitations, pounding heart, or accelerated heart rate; (2) sweating; (3) trembling or shaking; (4) sensations of shortness of breath or smothering; (5) feeling of choking; (6) chest pain or discomfort; (7) nausea or abdominal distress; (8) feeling dizzy, unsteady, lightheaded, or faint; (9) derealization (feelings of unreality) or depersonalization (being detached from oneself); (10) fear of losing control; (11) fear of dying; (12) paresthesias (numbness or tingling sensations); (13) chills or hot flushes.
The longer-term efficacy of alprazolam extended-release tablets USP has not been systematically evaluated. Thus, the physician who elects to use this drug for periods longer than 8 weeks should periodically reassess the usefulness of the drug for the individual patient.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Alprazolam extended-release tablets may be administered once daily, preferably in the morning. The tablets should be taken intact; they should not be chewed, crushed, or broken. The suggested total daily dose ranges between 3 to 6 mg/day.
Dosage should be individualized for maximum beneficial effect. While the suggested total daily dosages given will meet the needs of most patients, there will be some patients who require doses greater than 6 mg/day. In such cases, dosage should be increased cautiously to avoid adverse effects.
Dosing in Special Populations In elderly patients, in patients with advanced liver disease, or in patients with debilitating disease, the usual starting dose of alprazolam extended-release tablets is 0.5 mg once daily. This may be gradually increased if needed and tolerated (see Dose Titration ). The elderly may be especially sensitive to the effects of benzodiazepines.
Dose Titration Treatment with alprazolam extended-release tablets may be initiated with a dose of 0.5 mg to 1 mg once daily. Depending on the response, the dose may be increased at intervals of 3 to 4 days in increments of no more than 1 mg/day. Slower titration to the dose levels may be advisable to allow full expression of the pharmacodynamic effect of alprazolam extended-release tablets.
Generally, therapy should be initiated at a low dose to minimize the risk of adverse responses in patients especially sensitive to the drug. Dose should be advanced until an acceptable therapeutic response (i.e., a substantial reduction in or total elimination of panic attacks) is achieved, intolerance occurs, or the maximum recommended dose is attained. Dose Maintenance In controlled trials conducted to establish the efficacy of alprazolam extended-release tablets in panic disorder, doses in the range of 1 to 10 mg/day were used.
Most patients showed efficacy in the dose range of 3 to 6 mg/day. Occasional patients required as much as 10 mg/day to achieve a successful response. The necessary duration of treatment for panic disorder patients responding to alprazolam extended-release tablets is unknown.
However, periodic reassessment is advised. After a period of extended freedom from attacks, a carefully supervised tapered discontinuation may be attempted, but there is evidence that this may often be difficult to accomplish without recurrence of symptoms and/or the manifestation of withdrawal phenomena. Dose Reduction Because of the danger of withdrawal, abrupt discontinuation of treatment should be avoided (see WARNINGS , PRECAUTIONS , and DRUG ABUSE AND DEPENDENCE ).
In all patients, dosage should be reduced gradually when discontinuing therapy or when decreasing the daily dosage. Although there are no systematically collected data to support a specific discontinuation schedule, it is suggested that the daily dosage be decreased by no more than 0.5 mg every three days. Some patients may require an even slower dosage reduction.
In any case, reduction of dose must be undertaken under close supervision and must be gradual. If significant withdrawal symptoms develop, the previous dosing schedule should be reinstituted and, only after stabilization, should a less rapid schedule of discontinuation be attempted. In a controlled postmarketing discontinuation study of panic disorder patients which compared this recommended taper schedule with a slower taper schedule, no difference was observed between the groups in the proportion of patients who tapered to zero dose; however, the slower schedule was associated with a reduction in symptoms associated with a withdrawal syndrome.
It is suggested that the dose be reduced by no more than 0.5 mg every three days, with the understanding that some patients may benefit from an even more gradual discontinuation. Some patients may prove resistant to all discontinuation regimens. Switch from Alprazolam (Immediate-Release) Tablets to Alprazolam Extended-Release Tablets Patients who are currently…
⛔ Contraindications ▾
CONTRAINDICATIONS Alprazolam extended-release tablets are contraindicated in patients with known sensitivity to this drug or other benzodiazepines. Alprazolam extended-release tablets may be used in patients with open angle glaucoma who are receiving appropriate therapy, but is contraindicated in patients with acute narrow angle glaucoma. Alprazolam extended-release tablets are contraindicated with ketoconazole and itraconazole, since these medications significantly impair the oxidative metabolism mediated by cytochrome P450 3A (CYP3A) (see CLINICAL PHARMACOLOGY , WARNINGS and PRECAUTIONS–Drug Interactions ).
⚠️ Warnings ▾
WARNINGS Dependence and Withdrawal Reactions, Including Seizures Certain adverse clinical events, some life-threatening, are a direct consequence of physical dependence to alprazolam. These include a spectrum of withdrawal symptoms; the most important is seizure (see DRUG ABUSE AND DEPENDENCE ). Even after relatively short-term use at doses of ≤ 4 mg/day, there is some risk of dependence.
Spontaneous reporting system data suggest that the risk of dependence and its severity appear to be greater in patients treated with doses greater than 4 mg/day and for long periods (more than 12 weeks). However, in a controlled postmarketing discontinuation study of panic disorder patients who received alprazolam tablets, the duration of treatment (3 months compared to 6 months) had no effect on the ability of patients to taper to zero dose. In contrast, patients treated with doses of alprazolam tablets greater than 4 mg/day had more difficulty tapering to zero dose than those treated with less than 4 mg/day.
Relapse or return of illness was defined as a return of symptoms characteristic of panic disorder (primarily panic attacks) to levels approximately equal to those seen at baseline before active treatment was initiated. Rebound refers to a return of symptoms of panic disorder to a level substantially greater in frequency, or more severe in intensity than seen at baseline. Withdrawal symptoms were identified as those which were generally not characteristic of panic disorder and which occurred for the first time more frequently during discontinuation than at baseline.
The rate of relapse, rebound, and withdrawal in patients with panic disorder who received alprazolam extended-release tablets has not been systematically studied. Experience in randomized placebo-controlled discontinuation studies of patients with panic disorder who received alprazolam tablets showed a high rate of rebound and withdrawal symptoms compared to placebo treated patients. In a controlled clinical trial in which 63 patients were randomized to alprazolam tablets and where withdrawal symptoms were specifically sought, the following were identified as symptoms of withdrawal: heightened sensory perception, impaired concentration, dysosmia, clouded sensorium, paresthesias, muscle cramps, muscle twitch, diarrhea, blurred vision, appetite decrease, and weight loss.
Other symptoms, such as anxiety and insomnia, were frequently seen during discontinuation, but it could not be determined if they were due to return of illness, rebound, or withdrawal. In two controlled trials of 6 to 8 weeks duration where the ability of patients to discontinue medication was measured, 71% to 93% of patients treated with alprazolam tablets tapered completely off therapy compared to 89% to 96% of placebo treated patients. In a controlled postmarketing discontinuation study of panic disorder patients treated with alprazolam tablets, the duration of treatment (3 months compared to 6 months) had no effect on the ability of patients to taper to zero dose.
Seizures were reported for three patients in panic disorder clinical trials with alprazolam extended-release. In two cases, the patients had completed 6 weeks of treatment with alprazolam extended-release 6 mg/day before experiencing a single seizure. In one case, the patient abruptly discontinued alprazolam extended-release, and in both cases, alcohol intake was implicated.
The third case involved multiple seizures after the patient completed treatment with alprazolam extended-release 4 mg/day and missed taking the medication on the first day of taper. All three patients recovered without sequelae. Seizures have also been observed in association with dose reduction or discontinuation of alprazolam tablets, the immediate release form of alprazolam.
Seizures attributable to alprazolam were seen after drug discontinuance or dose reduction in 8 of 1980 patients with panic disorder or in patients participating in clinical trials where doses of alprazo…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The information included in the subsection on Adverse Events Observed in Short-Term, Placebo-Controlled Trials with alprazolam extended-release tablets is based on pooled data of five 6- and 8-week placebo-controlled clinical studies in panic disorder. Adverse event reports were elicited either by general inquiry or by checklist, and were recorded by clinical investigators using terminology of their own choosing. The stated frequencies of adverse events represent the proportion of individuals who experienced, at least once, a treatment-emergent adverse event of the type listed.
An event was considered treatment emergent if it occurred for the first time or worsened during therapy following baseline evaluation. In the tables and tabulations that follow, standard MedDRA terminology (version 4.0) was used to classify reported adverse events. Adverse Events Observed in Short-Term, Placebo-Controlled Trials of Alprazolam Extended-Release Adverse Events Reported as Reasons for Discontinuation of Treatment in Placebo-Controlled Trials Approximately 17% of the 531 patients who received alprazolam extended-release in placebo-controlled clinical trials for panic disorder had at least one adverse event that led to discontinuation compared to 8% of 349 placebo-treated patients.
The most common events leading to discontinuation and considered to be drug-related (i.e., leading to discontinuation in at least 1% of the patients treated with alprazolam extended-release at a rate at least twice that of placebo) are shown in the following table. Common Adverse Events Leading to Discontinuation of Treatment in Placebo-Controlled Trials System Organ Class/ Adverse Event Percentage of Patients Discontinuing Due to Adverse Events Alprazolam Extended-Release (n=531) Placebo (n=349) Nervous system disorders Sedation Somnolence Dysarthria Coordination abnormal Memory impairment 7.5 3.2 2.1 1.9 1.5 0.6 0.3 0 0.3
0.3General disorders/administration site conditions Fatigue 1.7
0.6Psychiatric disorders Depression 2.5
1.2Adverse Events Occurring at an Incidence of 1% or More Among Patients Treated with Alprazolam Extended-Release The prescriber should be aware that adverse event incidence cannot be used to predict the incidence of adverse events in the course of usual medical practice where patient characteristics and other factors differ from those which prevailed in the clinical trials. Similarly, the cited frequencies cannot be compared with event incidence obtained from other clinical investigations involving different treatments, uses, and investigators.
The cited values, however, do provide the prescribing physician with some basis for estimating the relative contribution of drug and non-drug factors to the adverse event incidence rate in the population studied. The following table shows the incidence of treatment-emergent adverse events that occurred during 6- to 8-week placebo-controlled trials in 1% or more of patients treated with alprazolam extended-release where the incidence in patients treated with alprazolam extended-release was greater than the incidence in placebo-treated patients.
The most commonly observed adverse events in panic disorder patients treated with alprazolam extended-release (incidence of 5% or greater and at least twice the incidence in placebo patients) were: sedation, somnolence, memory impairment, dysarthria, coordination abnormal, ataxia, libido decreased (see table). Treatment-Emergent Adverse Events: Incidence in Short-Term, Placebo-Controlled Clinical Trials with Alprazolam Extended-Release System Organ Class/Adverse Event Percentage of Patients Reporting Adverse Event Alprazolam Extended Release (n=531) Placebo (n=349) Nervous system disorders Sedation Somnolence Memory impairment Dysarthria Coordination abnormal Mental impairment Ataxia Disturbance in attention Balance impaired Paresthesia Dyskinesia Hypoesthesia Hypersomnia 45.2 23 15.4 10.9 9.4 7.2 7.2 3.2 3.2 2.4 1.7 1.3 1.3 22.6 6 6.9 2.6 0.…
🔄 Drug Interactions ▾
Drug Interactions Use with Other CNS Depressants If alprazolam extended-release tablets are to be combined with other psychotropic agents or anticonvulsant drugs, careful consideration should be given to the pharmacology of the agents to be employed, particularly with compounds which might potentiate the action of benzodiazepines. The benzodiazepines, including alprazolam, produce additive CNS depressant effects when coadministered with other psychotropic medications, anticonvulsants, antihistaminics, ethanol and other drugs which themselves produce CNS depression.
Use with Imipramine and Desipramine The steady state plasma concentrations of imipramine and desipramine have been reported to be increased an average of 31% and 20%, respectively, by the concomitant administration of alprazolam tablets in doses up to 4 mg/day. The clinical significance of these changes is unknown. Drugs that inhibit alprazolam metabolism via cytochrome P450 3A The initial step in alprazolam metabolism is hydroxylation catalyzed by cytochrome P450 3A (CYP3A).
Drugs which inhibit this metabolic pathway may have a profound effect on the clearance of alprazolam (see CONTRAINDICATIONS and WARNINGS for additional drugs of this type). Drugs demonstrated to be CYP3A inhibitors of possible clinical significance on the basis of clinical studies involving alprazolam (caution is recommended during coadministration with alprazolam) Fluoxetine — Coadministration of fluoxetine with alprazolam increased the maximum plasma concentration of alprazolam by 46%, decreased clearance by 21%, increased half-life by 17%, and decreased measured psychomotor performance.
Propoxyphene — Coadministration of propoxyphene decreased the maximum plasma concentration of alprazolam by 6%, decreased clearance by 38%, and increased half-life by 58%. Oral Contraceptives — Coadministration of oral contraceptives increased the maximum plasma concentration of alprazolam by 18%, decreased clearance by 22%, and increased half-life by 29%. Drugs and other substances demonstrated to be CYP3A inhibitors on the basis of clinical studies involving benzodiazepines metabolized similarly to alprazolam or on the basis of in vitro studies with alprazolam or other benzodiazepines (caution is recommended during coadministration with alprazolam) Available data from clinical studies of benzodiazepines other than alprazolam suggest a possible drug interaction with alprazolam for the following: diltiazem, isoniazid, macrolide antibiotics such as erythromycin and clarithromycin, and grapefruit juice.
Data from in vitro studies of alprazolam suggest a possible drug interaction with alprazolam for the following: sertraline and paroxetine. However, data from an in vivo drug interaction study involving a single dose of alprazolam 1 mg and steady state doses of sertraline (50 to 150 mg/day) did not reveal any clinically significant changes in the pharmacokinetics of alprazolam. Data from in vitro studies of benzodiazepines other than alprazolam suggest a possible drug interaction for the following: ergotamine, cyclosporine, amiodarone, nicardipine, and nifedipine.
Caution is recommended during the coadministration of any of these with alprazolam (see WARNINGS ). Drugs demonstrated to be inducers of CYP3A Carbamazepine can increase alprazolam metabolism and therefore can decrease plasma levels of alprazolam.
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions Although interactions between benzodiazepines and commonly employed clinical laboratory tests have occasionally been reported, there is no consistent pattern for a specific drug or specific test.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Pregnancy Category D (see WARNINGS section). Nonteratogenic Effects It should be considered that the child born of a mother who is receiving benzodiazepines may be at some risk for withdrawal symptoms from the drug during the postnatal period. Also, neonatal flaccidity and respiratory problems have been reported in children born of mothers who have been receiving benzodiazepines.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness of alprazolam in individuals below 18 years of age have not been established.
🧓 Geriatric Use ▾
Geriatric Use The elderly may be more sensitive to the effects of benzodiazepines. They exhibit higher plasma alprazolam concentrations due to reduced clearance of the drug as compared with a younger population receiving the same doses. The smallest effective dose of alprazolam should be used in the elderly to preclude the development of ataxia and oversedation (see CLINICAL PHARMACOLOGY and DOSAGE AND ADMINISTRATION ).
🆘 Overdosage ▾
OVERDOSAGE Clinical Experience Overdosage reports with alprazolam tablets are limited. Manifestations of alprazolam overdosage include somnolence, confusion, impaired coordination, diminished reflexes, and coma. Death has been reported in association with overdoses of alprazolam by itself, as it has with other benzodiazepines.
In addition, fatalities have been reported in patients who have overdosed with a combination of a single benzodiazepine, including alprazolam, and alcohol; alcohol levels seen in some of these patients have been lower than those usually associated with alcohol-induced fatality. Animal experiments have suggested that forced diuresis or hemodialysis are probably of little value in treating overdosage. General Treatment of Overdose As in all cases of drug overdosage, respiration, pulse rate, and blood pressure should be monitored.
General supportive measures should be employed, along with immediate gastric lavage. Intravenous fluids should be administered and an adequate airway maintained. If hypotension occurs, it may be combated by the use of vasopressors.
Dialysis is of limited value. As with the management of intentional overdosing with any drug, it should be borne in mind that multiple agents may have been ingested. Flumazenil, a specific benzodiazepine receptor antagonist, is indicated for the complete or partial reversal of the sedative effects of benzodiazepines and may be used in situations when an overdose with a benzodiazepine is known or suspected.
Prior to the administration of flumazenil, necessary measures should be instituted to secure airway, ventilation, and intravenous access. Flumazenil is intended as an adjunct to, not as a substitute for, proper management of benzodiazepine overdose. Patients treated with flumazenil should be monitored for re-sedation, respiratory depression, and other residual benzodiazepine effects for an appropriate period after treatment.
The prescriber should be aware of a risk of seizure in association with flumazenil treatment, particularly in long-term benzodiazepine users and in cyclic antidepressant overdose. The complete flumazenil package insert including CONTRAINDICATIONS, WARNINGS, and PRECAUTIONS should be consulted prior to use.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Pharmacodynamics CNS agents of the 1,4 benzodiazepine class presumably exert their effects by binding at stereospecific receptors at several sites within the central nervous system. Their exact mechanism of action is unknown. Clinically, all benzodiazepines cause a dose-related central nervous system depressant activity varying from mild impairment of task performance to hypnosis.
Pharmacokinetics Absorption Following oral administration of alprazolam (immediate-release) tablets, alprazolam is readily absorbed. Peak concentrations in the plasma occur in one to two hours following administration. Plasma levels are proportional to the dose given; over the dose range of 0.5 to 3 mg, peak levels of 8 to 37 ng/mL were observed.
Using a specific assay methodology, the mean plasma elimination half-life of alprazolam has been found to be about 11.2 hours (range: 6.3 to 26.9 hours) in healthy adults. The mean absolute bioavailability of alprazolam from alprazolam extended-release tablets is approximately 90%, and the relative bioavailability compared to alprazolam tablets is 100%. The bioavailability and pharmacokinetics of alprazolam following administration of alprazolam extended-release tablets are similar to that for alprazolam tablets, with the exception of a slower rate of absorption.
The slower absorption rate results in a relatively constant concentration that is maintained between 5 and 11 hours after the dosing. The pharmacokinetics of alprazolam and two of its major active metabolites (4-hydroxyalprazolam and α-hydroxyalprazolam) are linear, and concentrations are proportional up to the recommended maximum daily dose of 10 mg given once daily. Multiple dose studies indicate that the metabolism and elimination of alprazolam are similar for the immediate-release and the extended-release products.
Food has a significant influence on the bioavailability of alprazolam extended-release tablets. A high-fat meal given up to 2 hours before dosing with alprazolam extended-release tablets increased the mean C max by about 25%. The effect of this meal on T max depended on the timing of the meal, with a reduction in T max by about 1/3 for subjects eating immediately before dosing and an increase in T max by about 1/3 for subjects eating 1 hour or more after dosing.
The extent of exposure (AUC) and elimination half-life (t 1/2 ) were not affected by eating. There were significant differences in absorption rate for the alprazolam extended-release tablet, depending on the time of day administered, with the C max increased by 30% and the T max decreased by an hour following dosing at night, compared to morning dosing. Distribution The apparent volume of distribution of alprazolam is similar for alprazolam extended-release and alprazolam tablets.
In vitro , alprazolam is bound (80%) to human serum protein. Serum albumin accounts for the majority of the binding. Metabolism Alprazolam is extensively metabolized in humans, primarily by cytochrome P450 3A4 (CYP3A4), to two major metabolites in the plasma: 4-hydroxyalprazolam and α-hydroxyalprazolam.
A benzophenone derived from alprazolam is also found in humans. Their half-lives appear to be similar to that of alprazolam. The pharmacokinetic parameters at steady-state for the two hydroxylated metabolites of alprazolam (4-hydroxyalprazolam and α-hydroxyalprazolam) were similar for alprazolam and alprazolam extended-release tablets, indicating that the metabolism of alprazolam is not affected by absorption rate.
The plasma concentrations of 4-hydroxyalprazolam and α-hydroxyalprazolam relative to unchanged alprazolam concentration after both alprazolam extended-release and alprazolam tablets were always less than 10% and 4%, respectively. The reported relative potencies in benzodiazepine receptor binding experiments and in animal models of induced seizure inhibition are 0.2 and 0.66, respectively, for 4-hydroxyalprazolam and α-hydroxyalprazolam. Such low concentrations and the…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Alprazolam Extended-Release Tablets USP, 0.5 mg are white to off-white, round, biconvex tablets with beveled edge debossed with ‘X’ on one side and ‘70’ on the other side. Bottles of 30 NDC 63187-518-30 Bottles of 60 NDC 63187-518-60 Bottles of 90 NDC 63187-518-90 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
DESCRIPTION Alprazolam extended-releasetablets USP contain alprazolam which is a triazolo analog of the 1,4 benzodiazepine class of central nervous system-active compounds. The chemical name of alprazolam is 8-chloro-1-methyl-6-phenyl-4 H - s -triazolo [4,3-α] [1,4] benzodiazepine. The molecular formula is C 17 H 13 ClN 4 which corresponds to a molecular weight of 308.76.
The structural formula is represented below: Alprazolam USP is a white to off-white, crystalline powder, which is soluble in methanol or ethanol but which has no appreciable solubility in water at physiological pH. Each alprazolam extended-release tablet USP, for oral administration, contains 0.5 mg, 1 mg, 2 mg, or 3 mg of alprazolam. The inactive ingredients are colloidal silicon dioxide, hypromellose, lactose monohydrate, and magnesium stearate.
In addition, the 1 mg and 3 mg tablets contain D&C Yellow No. 10 aluminum lake and the 2 mg and 3 mg tablets contain FD&C Blue No. 2 lake.
Meets USP Dissolution Test 4. Chemical Structure
💬 Information for Patients ▾
Information for Patients To assure safe and effective use of alprazolam extended-release, the physician should provide the patient with the following guidance. • Inform your physician about any alcohol consumption and medicine you are taking now, including medication you may buy without a prescription. Alcohol should generally not be used during treatment with benzodiazepines. • Not recommended for use in pregnancy. Therefore, inform your physician if you are pregnant, if you are planning to have a child, or if you become pregnant while you are taking this medication. • Inform your physician if you are nursing. • Until you experience how this medication affects you, do not drive a car or operate potentially dangerous machinery, etc. • Do not increase the dose even if you think the medication “does not work anymore” without consulting your physician.
Benzodiazepines, even when used as recommended, may produce emotional and/or physical dependence. • Do not stop taking this medication abruptly or decrease the dose without consulting your physician, since withdrawal symptoms can occur. • Some patients may find it very difficult to discontinue treatment with alprazolam extended-release due to severe emotional and physical dependence. Discontinuation symptoms, including possible seizures, may occur following discontinuation from any dose, but the risk may be increased with extended use at doses greater than 4 mg/day, especially if discontinuation is too abrupt.
It is important that you seek advice from your physician to discontinue treatment in a careful and safe manner. Proper discontinuation will help to decrease the possibility of withdrawal reactions that can range from mild reactions to severe reactions such as seizure.