
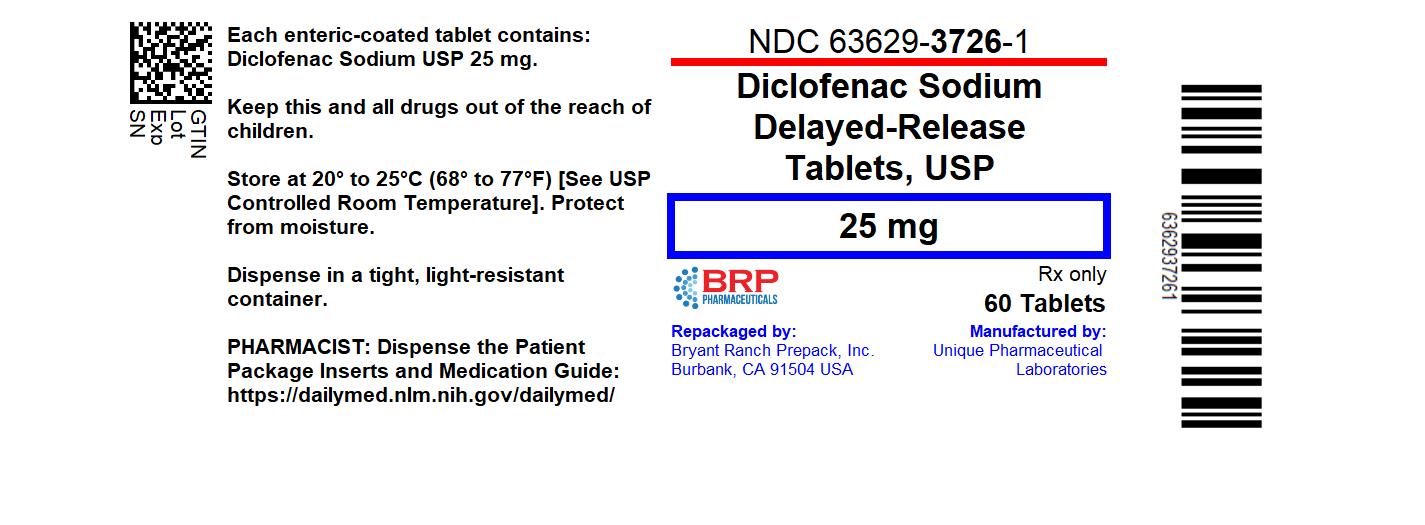
Diclofenac Sodium 25 mg Tablet, Delayed Release, 60-count
Other active recalls for Diclofenac Sodium (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nonsteroidal Anti-inflammatory Drug class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Diclofenac capsules (Zipsor, Zorvolex) and tablets (Cataflam) are used to relieve mild to moderate pain. Diclofenac extended-release tablets (Voltaren XR), tablets (Cataflam), and delayed-release tablets (available generically) are used to relieve pain, tenderness, swelling, and stiffness caused by osteoarthritis (arthritis caused by a breakdown of the lining of the joints), and rheumatoid arthritis (arthritis caused by swelling of the lining of the joints). Diclofenac extended-release tablets and delayed-release tablets are also used to treat ankylosing spondylitis (arthritis that mainly affe...
Read the full MedlinePlus article ↗- An actinic keratosis — often just called an AK — is a rough, scaly patch on the skin caused by years of sun exposure. These patches are considered precancerous, meaning they could...
- What exactly is an actinic keratosis, and why do I need a prescription gel for it?
- The typical treatment course runs 60 to 90 days of twice-daily application — that's a solid commitment, but it's necessary for the gel to do its job. Here's the thing: even after y...
- How long do I need to use this gel, and how will I know it's working?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Diclofenac Sodium — tap one for details:
Diclofenac Sodium may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII NX76LV5T8J
A synthetic plastic polymer made from methacrylic acid and ethyl acrylate. It's used as a coating or binder to control how and where the medicine dissolves in your digestive system.
-
UNII 7T9FYH5QMK
A plant-derived powder that serves as a binder and filler in tablets and capsules. It helps hold ingredients together, adds bulk, and aids in smooth tablet disintegration when swallowed.
-
UNII 30IQX730WE
Polyethylene glycol 6000 is a synthetic polymer made from ethylene glycol units. It acts as a binder, filler, and solubilizer in medicines to help hold ingredients together, add bulk, and improve how well active drugs dissolve and absorb.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
14 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1933 | $11.60 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Diclofenac Sodium 25 mg 16571-0203-10 | Rising | 100 tablets | $0.667 | AB | Availability likely | — |
| Diclofenac Sodium Delayed Release 25 mg 61442-0101-01 | Carlsbad | 100 tablets | $0.667 | AB | Discontinued | — |
| Diclofenac Sodium 25 mg 68001-0279-00 | BluePoint | 100 tablets | $0.667 | AB | Availability likely | — |
| Diclofenac Sodium 25 mg 72603-0600-01 | NorthStar | 100 tablets | $0.667 | AB | Availability likely | — |
| Diclofenac Sodium Delayed Release 25 mg 51407-0536-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Diclofenac Sodium 25 mg 60290-0082-01 | Umedica | 100 tablets | — | AB | FDA listed | — |
| Diclofenac Sodium 25 mgthis 63629-3726-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Diclofenac Sodium 25 mg 72888-0109-00 | Advagen | 1000 tablets | — | AB | FDA listed | — |
| Diclofenac Sodium 25 mg 76420-0571-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 63629-3726-01 You're viewing this | 60 TABLET, DELAYED RELEASE in 1 BOTTLE (63629-3726-1) | 2024-04-02 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISK OF SERIOUS CARDIOVASCULAR AND GASTROINTESTINAL EVENTS Cardiovascular Thrombotic Events Nonsteroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use (see WARNINGS ). Diclofenac sodium delayed-release tablets are contraindicated in the setting of coronary artery bypass graft (CABG) surgery (see CONTRAINDICATIONS and WARNINGS ).
Gastrointestinal Bleeding, Ulceration, and Perforation NSAIDs cause an increased risk of serious gastrointestinal (GI) adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal. These events can occur at any time during use and without warning symptoms. Elderly patients and patients with a prior history of peptic ulcer disease and/or GI bleeding are at greater risk for serious GI events (see WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Carefully consider the potential benefits and risks of diclofenac sodium delayed-release tablets and other treatment options before deciding to use diclofenac sodium delayed-release tablets. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals (see WARNINGS: Gastrointestinal Bleeding, Ulceration and Perforation ). Diclofenac sodium delayed-release tablets are indicated: For relief of the signs and symptoms of osteoarthritis For relief of the signs and symptoms of rheumatoid arthritis For acute or long-term use in the relief of signs and symptoms of ankylosing spondylitis
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Carefully consider the potential benefits and risks of diclofenac sodium delayed-release tablets and other treatment options before deciding to use diclofenac sodium delayed-release tablets. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals (see WARNINGS: Gastrointestinal Bleeding, Ulceration, and Perforation ). After observing the response to initial therapy with diclofenac sodium delayed-release tablets, the dose and frequency should be adjusted to suit an individual patient’s needs.
For the relief of osteoarthritis, the recommended dosage is 100 to 150 mg/day in divided doses (50 mg twice a day or three times a day, or 75 mg twice a day). For the relief of rheumatoid arthritis, the recommended dosage is 150 to 200 mg/day in divided doses (50 mg three times a day or four times a day, or 75 mg twice a day). For the relief of ankylosing spondylitis, the recommended dosage is 100 to 125 mg/day, administered as 25 mg four times a day, with an extra 25 mg dose at bedtime if necessary.
Different formulations of diclofenac (diclofenac sodium enteric-coated tablets; diclofenac sodium extended-release tablets; diclofenac potassium immediate-release tablets) are not necessarily bioequivalent even if the milligram strength is the same.
⛔ Contraindications ▾
CONTRAINDICATIONS Diclofenac sodium delayed-release tablets are contraindicated in the following patients. Known hypersensitivity (e.g., anaphylactic reactions and serious skin reactions) to diclofenac or any components of the drug product (see WARNINGS: Anaphylactic Reactions , Serious Skin Reactions ). History of asthma, urticaria, or other allergic-type reactions after taking aspirin or other NSAIDs.
Severe, sometimes fatal, anaphylactic reactions to NSAIDs have been reported in such patients (see WARNINGS: Anaphylactic Reaction , Exacerbation of Asthma Related to Aspirin Sensitivity ). In the setting of coronary artery bypass graft (CABG) surgery (see WARNINGS: Cardiovascular Thrombotic Events ).
⚠️ Warnings ▾
WARNINGS Cardiovascular Thrombotic Events Clinical trials of several COX-2 selective and nonselective NSAIDs of up to three years duration have shown an increased risk of serious cardiovascular (CV) thrombotic events, including myocardial infarction (MI), and stroke, which can be fatal. Based on available data, it is unclear that the risk for CV thrombotic events is similar for all NSAIDs. The relative increase in serious CV thrombotic events over baseline conferred by NSAID use appears to be similar in those with and without known CV disease or risk factors for CV disease.
However, patients with known CV disease or risk factors had a higher absolute incidence of excess serious CV thrombotic events, due to their increased baseline rate. Some observational studies found that this increased risk of serious CV thrombotic events began as early as the first weeks of treatment. The increase in CV thrombotic risk has been observed most consistently at higher doses.
To minimize the potential risk for an adverse CV event in NSAID-treated patients, use the lowest effective dose for the shortest duration possible. Physicians and patients should remain alert for the development of such events, throughout the entire treatment course, even in the absence of previous CV symptoms. Patients should be informed about the symptoms of serious CV events and the steps to take if they occur.
There is no consistent evidence that concurrent use of aspirin mitigates the increased risk of serious CV thrombotic events associated with NSAID use. The concurrent use of aspirin and an NSAID, such as diclofenac, increases the risk of serious gastrointestinal (GI) events (see WARNINGS: Gastrointestinal Bleeding, Ulceration, and Perforation ). Status Post Coronary Artery Bypass Graft (CABG) Surgery Two large, controlled clinical trials of a COX-2 selective NSAID for the treatment of pain in the first 10 to 14 days following CABG surgery found an increased incidence of myocardial infarction and stroke.
NSAIDs are contraindicated in the setting of CABG (see CONTRAINDICATIONS ). Post-MI Patients Observational studies conducted in the Danish National Registry have demonstrated that patients treated with NSAIDs in the post-MI period were at increased risk of reinfarction, CV-related death, and all-cause mortality beginning in the first week of treatment. In this same cohort, the incidence of death in the first year post MI was 20 per 100 person years in NSAID-treated patients compared to 12 per 100 person years in non-NSAID exposed patients.
Although the absolute rate of death declined somewhat after the first year post-MI, the increased relative risk of death in NSAID users persisted over at least the next four years of follow-up. Avoid the use of diclofenac in patients with a recent MI unless the benefits are expected to outweigh the risk of recurrent CV thrombotic events. If diclofenac is used in patients with a recent MI, monitor patients for signs of cardiac ischemia.
Gastrointestinal Bleeding, Ulceration, and Perforation NSAIDs, including diclofenac, cause serious gastrointestinal (GI) adverse events including inflammation, bleeding, ulceration, and perforation of the esophagus, stomach, small intestine, or large intestine, which can be fatal. These serious adverse events can occur at any time, with or without warning symptoms, in patients treated with NSAIDs. Only one in five patients, who develop a serious upper GI adverse event on NSAID therapy, is symptomatic.
Upper GI ulcers, gross bleeding, or perforation caused by NSAIDs occurred in approximately 1% of patients treated for 3 to 6 months, and in about 2% to 4% of patients treated for one year. However, even short-term therapy is not without risk. Risk Factors for GI Bleeding, Ulceration, and Perforation Patients with a prior history of peptic ulcer disease and/or GI bleeding who use NSAIDs had a greater than 10-fold increased risk for developing a GI bleed compared to patients without these risk factors.…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Cardiovascular Thrombotic Events (see WARNINGS ) GI Bleeding, Ulceration and Perforation (see WARNINGS ) Hepatotoxicity (see WARNINGS ) Hypertension (see WARNINGS ) Heart Failure and Edema (see WARNINGS ) Renal Toxicity and Hyperkalemia (see WARNINGS ) Anaphylactic Reactions (see WARNINGS ) Serious Skin Reactions (see WARNINGS ) Hematologic Toxicity (see WARNINGS ) Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
In patients taking diclofenac sodium delayed-release tablets, or other NSAIDs, the most frequently reported adverse experiences occurring in approximately 1% to 10% of patients are: Gastrointestinal experiences including: abdominal pain, constipation, diarrhea, dyspepsia, flatulence, gross bleeding/perforation, heartburn, nausea, GI ulcers (gastric/duodenal) and vomiting. Abnormal renal function, anemia, dizziness, edema, elevated liver enzymes, headaches, increased bleeding time, pruritus, reactions and tinnitus. Additional adverse experiences reported occasionally include: Body as a Whole fever, infection, sepsis Cardiovascular System congestive heart failure, hypertension, tachycardia, syncope Digestive System dry mouth, esophagitis, gastric/peptic ulcers, gastritis, gastrointestinal bleeding, glossitis, hematemesis, hepatitis, jaundice Hemic and Lymphatic System ecchymosis, eosinophilia, leukopenia, melena, purpura, rectal bleeding, stomatitis, thrombocytopenia Metabolic and Nutritional weight changes Nervous System anxiety, asthenia, confusion, depression, dream abnormalities, drowsiness, insomnia, malaise, nervousness, paresthesia, somnolence, tremors, vertigo Respiratory System asthma, dyspnea Skin and Appendages alopecia, photosensitivity, sweating increased Special Senses blurred vision Urogenital System cystitis, dysuria, hematuria, interstitial nephritis, oliguria/polyuria, proteinuria, renal failure Other adverse reactions, which occur rarely are: Body as a Whole anaphylactic reactions, appetite changes, death Cardiovascular System arrhythmia, hypotension, myocardial infarction, palpitations, vasculitis Digestive System colitis, eructation, fulminant hepatitis with and without jaundice, liver failure, liver necrosis, pancreatitis Hemic and Lymphatic System agranulocytosis, hemolytic anemia, aplastic anemia, lymphadenopathy, pancytopenia Metabolic and Nutritional hyperglycemia Nervous System convulsions, coma, hallucinations, meningitis Respiratory System respiratory depression, pneumonia Skin and Appendages angioedema, toxic epidermal necrolysis, erythema multiforme, exfoliative dermatitis, Stevens-Johnson syndrome, fixed drug eruption (FDE), urticaria Special Senses conjunctivitis, hearing impairment To report SUSPECTED ADVERSE REACTIONS , contact Rising Pharma Holdings, Inc. at 1-844-874-7464 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In patients taking diclofenac sodium delayed-release tablets, or other NSAIDs, the most frequently reported adverse experiences occurring in approximately 1% to 10% of patients are: Gastrointestinal experiences including: abdominal pain, constipation, diarrhea, dyspepsia, flatulence, gross bleeding/perforation, heartburn, nausea, GI ulcers (gastric/duodenal) and vomiting.
Abnormal renal function, anemia, dizziness, edema, elevated liver enzymes, headaches, increased bleeding time, pruritus, reactions and tinnitus. Additional adv…
🔄 Drug Interactions ▾
Drug Interactions See Table 2 for clinically significant drug interactions with diclofenac. Table 2. Clinically Significant Drug Interactions with Diclofenac Drugs That Interfere with Hemostasis Clinical Impact: Diclofenac and anticoagulants such as warfarin have a synergistic effect on bleeding.
The concomitant use of diclofenac and anticoagulants have an increased risk of serious bleeding compared to the use of either drug alone. Serotonin release by platelets plays an important role in hemostasis. Case-control and cohort epidemiological studies showed that concomitant use of drugs that interfere with serotonin reuptake and an NSAID may potentiate the risk of bleeding more than an NSAID alone.
Intervention: Monitor patients with concomitant use of diclofenac sodium delayed-release tablets with anticoagulants (e.g., warfarin), antiplatelet agents (e.g., aspirin), selective serotonin reuptake inhibitors (SSRIs), and serotonin norepinephrine reuptake inhibitors (SNRIs) for signs of bleeding (see WARNINGS: Hematologic Toxicity ). Aspirin Clinical Impact: Controlled clinical studies showed that the concomitant use of NSAIDs and analgesic doses of aspirin does not produce any greater therapeutic effect than the use of NSAIDs alone.
In a clinical study, the concomitant use of an NSAID and aspirin was associated with a significantly increased incidence of GI adverse reactions as compared to use of the NSAID alone (see WARNINGS: Gastrointestinal Bleeding, Ulceration, and Perforation ). Intervention: Concomitant use of diclofenac sodium delayed-release tablets and analgesic doses of aspirin is not generally recommended because of the increased risk of bleeding (see WARNINGS: Hematologic Toxicity ). Diclofenac sodium delayed-release tablets are not a substitute for low dose aspirin for cardiovascular protection.
ACE Inhibitors, Angiotensin Receptor Blockers, and Beta-Blockers Clinical Impact: NSAIDs may diminish the antihypertensive effect of angiotensin converting enzyme (ACE) inhibitors, angiotensin receptor blockers (ARBs), or beta-blockers (including propranolol). In patients who are elderly, volume-depleted (including those on diuretic therapy), or have renal impairment, co-administration of an NSAID with ACE inhibitors or ARBs may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible.
Intervention: During concomitant use of diclofenac sodium delayed-release tablets and ACE-inhibitors, ARBs, or beta- blockers, monitor blood pressure to ensure that the desired blood pressure is obtained. During concomitant use of diclofenac sodium delayed-release tablets and ACE-inhibitors or ARBs in patients who are elderly, volume-depleted, or have impaired renal function, monitor for signs of worsening renal function (see WARNINGS: Renal Toxicity and Hyperkalemia ). When these drugs are administered concomitantly, patients should be adequately hydrated.
Assess renal function at the beginning of the concomitant treatment and periodically thereafter. Diuretics Clinical Impact: Clinical studies, as well as post-marketing observations, showed that NSAIDs reduced the natriuretic effect of loop diuretics (e.g., furosemide) and thiazide diuretics in some patients. This effect has been attributed to the NSAID inhibition of renal prostaglandin synthesis.
Intervention: During concomitant use of diclofenac sodium delayed-release tablets with diuretics, observe patients for signs of worsening renal function, in addition to assuring diuretic efficacy including antihypertensive effects (see WARNINGS: Renal Toxicity and Hyperkalemia ). Digoxin Clinical Impact: The concomitant use of diclofenac with digoxin has been reported to increase the serum concentration and prolong the half-life of digoxin. Intervention: During concomitant use of diclofenac sodium delayed-release tablets and digoxin, monitor serum digoxin levels.
Lithium Clinical Impact: NSAIDs have produced elevations in plasma lithium le…
🆘 Overdosage ▾
OVERDOSAGE Symptoms following acute NSAID overdosages have been typically limited to lethargy, drowsiness, nausea, vomiting, and epigastric pain, which have been generally reversible with supportive care. Gastrointestinal bleeding has occurred. Hypertension, acute renal failure, respiratory depression and coma have occurred, but were rare (see WARNINGS: Cardiovascular Thrombotic Events , Gastrointestinal Bleeding, Ulceration, and Perforation , Hypertension , Renal Toxicity and Hyperkalemia ).
Manage patients with symptomatic and supportive care following an NSAID overdosage. There are no specific antidotes. Consider emesis and/or activated charcoal (60 to 100 grams in adults, 1 to 2 grams per kg of body weight in pediatric patients) and/or osmotic cathartic in symptomatic patients seen within four hours of ingestion or in patients with a large overdose (5 to 10 times the recommended dosage).
Forced diuresis, alkalinization of urine, hemodialysis, or hemoperfusion may not be useful due to high protein binding. For additional information about overdosage treatment contact a poison control center (1-800-222‑1222).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Diclofenac has analgesic, anti-inflammatory, and antipyretic properties. The mechanism of action of diclofenac sodium delayed-release tablets, like that of other NSAIDs, is not completely understood but involves inhibition of cyclooxygenase (COX-1 and COX-2). Diclofenac is a potent inhibitor of prostaglandin synthesis in vitro .
Diclofenac concentrations reached during therapy have produced in vivo effects. Prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain in animal models. Prostaglandins are mediators of inflammation.
Because diclofenac is an inhibitor of prostaglandin synthesis, its mode of action may be due to a decrease of prostaglandins in peripheral tissues. Pharmacokinetics Absorption Diclofenac is 100% absorbed after oral administration compared to IV administration as measured by urine recovery. However, due to first-pass metabolism, only about 50% of the absorbed dose is systemically available (see Table 1).
Food has no significant effect on the extent of diclofenac absorption. However, there is usually a delay in the onset of absorption of 1 to 4.5 hours and a reduction in peak plasma levels of <20%. Table 1.
Pharmacokinetic Parameters for Diclofenac Normal Healthy Adults (20-48 years) PK Parameter Mean Coefficient of Variation (%) Absolute Bioavailability (%) [N = 7] 55 40 Tmax (hr) [N = 56] 2.3 69 Oral Clearance (CL/F; mL/min) [N = 56] 582 23 Renal Clearance (% unchanged drug in urine)[N = 7] <1 – Apparent Volume of Distribution (V/F; L/kg) [N = 56] 1.4 58 Terminal Half-life (hr) [N = 56] 2.3 48 Distribution The apparent volume of distribution (V/F) of diclofenac sodium is
1.4L/kg. Diclofenac is more than 99% bound to human serum proteins, primarily to albumin. Serum protein binding is constant over the concentration range (0.15 to 105 mcg/mL) achieved with recommended doses.
Diclofenac diffuses into and out of the synovial fluid. Diffusion into the joint occurs when plasma levels are higher than those in the synovial fluid, after which the process reverses and synovial fluid levels are higher than plasma levels. It is not known whether diffusion into the joint plays a role in the effectiveness of diclofenac.
Elimination Metabolism Five diclofenac metabolites have been identified in human plasma and urine. The metabolites include 4’-hydroxy-, 5-hydroxy-,3’-hydroxy-, 4’,5-dihydroxy- and 3’-hydroxy-4’-methoxy diclofenac. The major diclofenac metabolite, 4’-hydroxy-diclofenac, has very weak pharmacologic activity.
The formation of 4’-hydroxy- diclofenac is primarily mediated by CYP2C9. Both diclofenac and its oxidative metabolites undergo glucuronidation or sulfation followed by biliary excretion. Acylglucuronidation mediated by UGT2B7 and oxidation mediated by CYP2C8 may also play a role in diclofenac metabolism.
CYP3A4 is responsible for the formation of minor metabolites, 5-hydroxy- and 3’-hydroxy-diclofenac. In patients with renal dysfunction, peak concentrations of metabolites 4’-hydroxy- and 5-hydroxy-diclofenac were approximately 50% and 4% of the parent compound after single oral dosing compared to 27% and 1% in normal healthy subjects. Excretion Diclofenac is eliminated through metabolism and subsequent urinary and biliary excretion of the glucuronide and the sulfate conjugates of the metabolites.
Little or no free unchanged diclofenac is excreted in the urine. Approximately 65% of the dose is excreted in the urine and approximately 35% in the bile as conjugates of unchanged diclofenac plus metabolites. Because renal elimination is not a significant pathway of elimination for unchanged diclofenac, dosing adjustment in patients with mild to moderate renal dysfunction is not necessary.
The terminal half-life of unchanged diclofenac is approximately 2 hours. Special Populations Pediatric The pharmacokinetics of diclofenac sodium delayed-release tablets has not been investigated in pediatric patients. Race Pharmacokinetic…
🧬 Mechanism of Action ▾
Mechanism of Action Diclofenac has analgesic, anti-inflammatory, and antipyretic properties. The mechanism of action of diclofenac sodium delayed-release tablets, like that of other NSAIDs, is not completely understood but involves inhibition of cyclooxygenase (COX-1 and COX-2). Diclofenac is a potent inhibitor of prostaglandin synthesis in vitro .
Diclofenac concentrations reached during therapy have produced in vivo effects. Prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain in animal models. Prostaglandins are mediators of inflammation.
Because diclofenac is an inhibitor of prostaglandin synthesis, its mode of action may be due to a decrease of prostaglandins in peripheral tissues.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Diclofenac sodium delayed-release tablets, USP, for oral administration, are available as: 25 mg: round, light brown, enteric-coated tablets "P;25" imprinted on one side in black ink and plain on the reverse side. NDC: 63629-3726-1: 60 Tablets in a Bottle. Store at 20° to 25°C (68° to 77°F) (see USP Controlled Room Temperature).
Protect from moisture. Dispense in a tight, light-resistant container. Repackaged/Relabeled by: Bryant Ranch Prepack, Inc.
Burbank, CA 91504
📋 Description ▾
DESCRIPTION Diclofenac sodium is a benzeneacetic acid derivative, designated chemically as 2-[(2,6-dichlorophenyl)amino] benzeneacetic acid, monosodium salt. The structural formula is: C 14 H 10 Cl 2 NNaO 2 M.W. 318.14 Diclofenac sodium is a white to off-white, hygroscopic crystalline powder.
It is freely soluble in methanol, soluble in ethanol, sparingly soluble in water and practically insoluble in chloroform and in dilute acid. The n-octanol/water partition coefficient is 13.4 at pH 7.4 and 1545 at pH 5.2. Diclofenac sodium has a dissociation constant (pKa) of 4.0 ± 0.2 at 25°C in water.
Each enteric-coated tablet for oral administration contains 25 mg, 50 mg, or 75 mg of diclofenac sodium. In addition, each tablet contains the following inactive ingredients. Inactive ingredients: lactose (monohydrate), microcrystalline cellulose, croscarmellose sodium, povidone, talc, magnesium stearate, methacrylic acid copolymer, polyethylene glycol, opadry brown (Titanium dioxide, hypromellose, polyethylene glycol, iron oxide red, iron oxide yellow).
💬 Patient Medication Information ▾
Diclofenac Sodium (dye kloe' fen ak soe' dee um) Delayed-release Tablets, USP Medication Guide for Nonsteroidal Anti-inflammatory Drugs (NSAIDs) What is the most important information I should know about medicines called Nonsteroidal Anti-inflammatory Drugs (NSAIDs)? NSAIDs can cause serious side effects, including: Increased risk of a heart attack or stroke that can lead to death. This risk may happen early in treatment and may increase: with increasing doses of NSAIDs with longer use of NSAIDs Do not take NSAIDs right before or after a heart surgery called a “coronary artery bypass graft (CABG).” Avoid taking NSAIDs after a recent heart attack, unless your healthcare provider tells you to.
You may have an increased risk of another heart attack if you take NSAIDs after a recent heart attack. Increased risk of bleeding, ulcers, and tears (perforation) of the esophagus (tube leading from the mouth to the stomach), stomach and intestines: anytime during use without warning symptoms that may cause death The risk of getting an ulcer or bleeding increases with: past history of stomach ulcers, or stomach or intestinal bleeding with use of NSAIDs taking medicines called “corticosteroids”, “anticoagulants”, “SSRIs”, or “SNRIs” increasing doses of NSAIDs longer use of NSAIDs smoking drinking alcohol older age poor health advanced liver disease bleeding problems NSAIDs should only be used: exactly as prescribed at the lowest dose possible for your treatment for the shortest time needed What are NSAIDs?
NSAIDs are used to treat pain and redness, swelling, and heat (inflammation) from medical conditions such as different types of arthritis, menstrual cramps, and other types of short-term pain. Who should not take NSAIDs? Do not take NSAIDs: if you had an asthma attack, hives, or other allergic reaction with aspirin or any other NSAIDs. right before or after heart bypass surgery.
Before taking NSAIDs, tell your healthcare provider about all of your medical conditions, including if you: have liver or kidney problems have high blood pressure have asthma are pregnant or plan to become pregnant. Taking NSAIDs at about 20 weeks of pregnancy or later may harm your unborn baby. If you need to take NSAIDs for more than 2 days when you are between 20 and 30 weeks of pregnancy, your healthcare provider may need to monitor the amount of fluid in your womb around your baby.
You should not take NSAIDs after about 30 weeks of pregnancy. are breastfeeding or plan to breastfeed. Tell your healthcare provider about all of the medicines you take, including prescription or over-the-counter medicines, vitamins or herbal supplements. NSAIDs and some other medicines can interact with each other and cause serious side effects.
Do not start taking any new medicine without talking to your healthcare provider first. What are the possible side effects of NSAIDs? NSAIDs can cause serious side effects, including: See “What is the most important information I should know about medicines called Nonsteroidal Anti-inflammatory Drugs (NSAIDs)?” new or worse high blood pressure heart failure liver problems including liver failure kidney problems including kidney failure low red blood cells (anemia) life-threatening skin reactions life-threatening allergic reactions Other side effects of NSAIDs include: stomach pain, constipation, diarrhea, gas, heartburn, nausea, vomiting, and dizziness.
Get emergency help right away if you have any of the following symptoms: shortness of breath or trouble breathing chest pain weakness in one part or side of your body slurred speech swelling of the face or throat Stop taking your NSAID and call your healthcare provider right away if you get any of the following symptoms: nausea more tired or weaker than usual diarrhea itching your skin or eyes look yellow indigestion or stomach pain flu-like symptoms vomit blood there is blood in your bowel movement or it is black and sticky like tar unusual weight gain skin reaction or blisters with fever…