
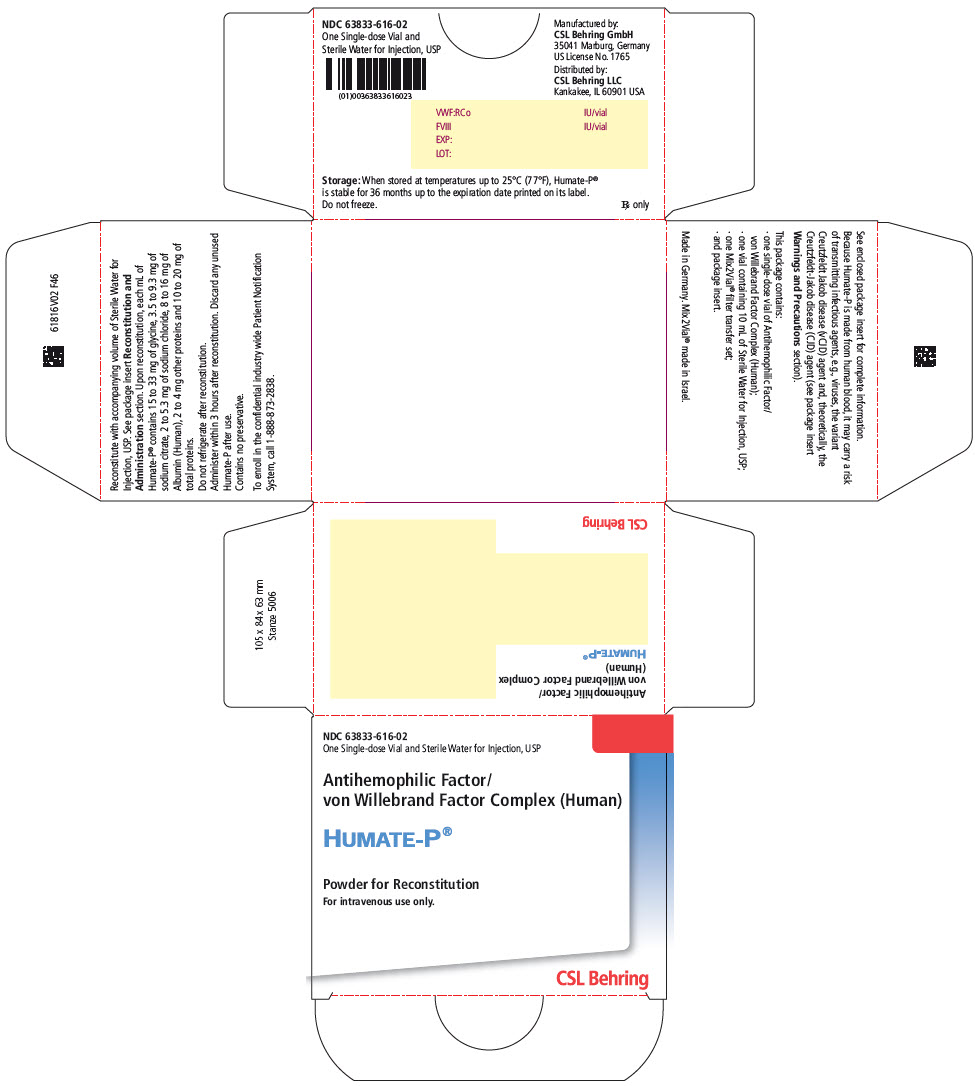
Humate-P antihemophilic factor/von willebrand factor complex (human) Kit — NDC 63833-616-02 (Billing 63833-0616-02)
This is a package of Humate-P antihemophilic factor/von willebrand factor complex (human) Kit from CSL Behring GmbH, marketed since May 1986 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 63833-616-02 alone.
- Record
- FDA NDC Directory package listing · Plasma derivative
- Code segments
- 63833 labeler · 616 product · 02 package
- Package marketed since
- May 1, 1986
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 6383361602 3
- Medicaid fills, this package
- 369 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 8, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 060325
- GCN: 26451
- GPI-14 (Medi-Span): 85100015102132
- HICL (First Databank): 017395
- AHFS class code: 20:28.16.00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 8, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $1.24 | — |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J7187 | $1.535 / J7187 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 63833-0616-02 You're viewing this Main listing | 1 KIT in 1 CARTON * 10 mL in 1 VIAL * 10 mL in 1 VIAL, SINGLE-DOSE | 1986-05-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Humate-P 63833-0615-02 | CSL | 1 kit | — | — | FDA listed | — |
| Humate-Pthis 63833-0616-02 | CSL | 1 kit | — | — | FDA listed | — |
| Humate-P 63833-0617-02 | CSL | 1 kit | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from CSL Behring GmbH labeler code 63833
- Kcentra PROTHROMBIN, COAGULATION FACTOR VII HUMAN, COAGULATION FACTOR IX HUMAN, COAGULATION FACTOR X HUMAN, Protein C, Protein S Human, and Water Kit NDC 63833-386-02
- Kcentra PROTHROMBIN, COAGULATION FACTOR VII HUMAN, COAGULATION FACTOR IX HUMAN, COAGULATION FACTOR X HUMAN, Protein C, Protein S Human, and Water Kit NDC 63833-387-02
- Corifact Factor XIII Concentrate (Human) Kit NDC 63833-518-02
- Humate-P antihemophilic factor/von willebrand factor complex (human) Kit NDC 63833-615-02
- Humate-P antihemophilic factor/von willebrand factor complex (human) Kit NDC 63833-617-02
- Berinert HUMAN C1-ESTERASE INHIBITOR Kit NDC 63833-825-02
- HAEGARDA C1 Esterase Inhibitor Subcutaneous (Human) Kit NDC 63833-828-02
- HAEGARDA C1 Esterase Inhibitor Subcutaneous (Human) Kit NDC 63833-829-02
- RiaSTAP FIBRINOGEN HUMAN 1300 mg/50mL Injection, Powder, Lyophilized, For Solution NDC 63833-891-51
- Riastap FIBRINOGEN HUMAN 2600 mg/100mL Injection, Solution NDC 63833-892-51
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full FDA label FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Humate-P is an Antihemophilic Factor/von Willebrand Factor (VWF) Complex (Human) indicated for: Hemophilia A – Treatment and prevention of bleeding in adults ( 1.1 ). Von Willebrand disease (VWD) – in adults and pediatric patients in the (1) Treatment of spontaneous and trauma-induced bleeding episodes, and (2) Prevention of excessive bleeding during and after surgery. This applies to patients with severe VWD as well as patients with mild to moderate VWD where the use of desmospressin is known or suspected to be inadequate ( 1.2 ).
Humate-P is not indicated for the prophylaxis of spontaneous bleeding episodes in VWD.
1.1Hemophilia A Humate-P, Antihemophilic Factor/von Willebrand Factor Complex (Human), is indicated for treatment and prevention of bleeding in adults with hemophilia A (classical hemophilia).
1.2Von Willebrand Disease (VWD) Humate-P is also indicated in adult and pediatric patients with von Willebrand disease (VWD) for: (1) treatment of spontaneous and trauma-induced bleeding episodes, and (2) prevention of excessive bleeding during and after surgery. This applies to patients with severe VWD as well as patients with mild to moderate VWD where use of desmopressin (DDAVP) is known or suspected to be inadequate. Controlled clinical trials to evaluate the safety and efficacy of prophylactic dosing with Humate-P to prevent spontaneous bleeding have not been conducted in VWD subjects (see Clinical Studies [14] ) .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For intravenous use only. Hemophilia A One IU of factor VIII (FVIII) activity per kg body weight increases the circulating FVIII level by approximately
2.0IU/dL. Individualize dosage based on the patient's weight, type and severity of hemorrhage, FVIII level, and presence of inhibitors (see Table 1 for dosing recommendations) ( 2.1 ). VWD Treatment of bleeding episodes – Administer 40-80 IU VWF:Ristocetin Cofactor (RCo) per kg body weight every 8-12 hours ( 2.2 ).
Prevention of excessive bleeding during and after surgery for all types of VWD ( 2.3 ). Type of Surgery (see Table 3 for complete surgical dosing) Calculation of Loading Dose Initial maintenance dose should be half the loading dose (see Table 4 for monitoring recommendations). IU = International Units.
BW = body weight. Major Surgery ( 2.3 ) Δ Δ = Target peak plasma VWF:RCo level – baseline plasma VWF:RCo level. VWF:RCo × BW (kg) IVR IVR = in vivo recovery as measured in the patient.
If the IVR is unknown, use
2.0IU/dL per IU/kg. = IU VWF:RCo required Minor/Oral Surgery Oral surgery is defined as extraction of fewer than three teeth, if the teeth are non-molars and have no bony involvement. ( 2.3 ) Δ VWF:RCo × BW (kg) IVR = IU VWF:RCo required Emergency Surgery ( 2.3 ) Administer a dose of 50-60 IU VWF:RCo/kg BW
2.1Therapy for Hemophilia A One IU of Factor VIII (FVIII) activity per kg body weight will increase the circulating FVIII level by approximately
2.0International Units (IU)/dL. Dosage must be individualized based on the patient's weight, type and severity of hemorrhage, FVIII level, and presence of inhibitors. Judge the adequacy of treatment by clinical effects and, in all cases, adjust doses as needed based on clinical judgment and on frequent monitoring of the patient's FVIII level.
Table 1 provides dosing recommendations for the treatment of hemophilia A in adults. Table 1: Dosing Recommendations for the Treatment of Hemophilia A in Adults 1 Hemorrhagic Event Dosage (IU FVIII:C/kg Body Weight) IU = International Units. Minor hemorrhage: Early joint or muscle bleed Severe epistaxis Loading dose 15 IU FVIII:C/kg to achieve a FVIII:C plasma level of approximately 30% of normal; one infusion may be sufficient.
If needed, half of the loading dose may be given once or twice daily for 1-2 days. Moderate hemorrhage: Advanced joint or muscle bleed Neck, tongue, or pharyngeal hematoma (without airway compromise) Tooth extraction Severe abdominal pain Loading dose 25 IU FVIII:C/kg to achieve a FVIII:C plasma level of approximately 50% of normal, followed by 15 IU FVIII:C/kg every 8-12 hours for the first 1-2 days to maintain the FVIII:C plasma level at 30% of normal. Continue the same dose once or twice daily for up to 7 days or until adequate wound healing is achieved.
Life-threatening hemorrhage: Major surgery Gastrointestinal bleeding Neck, tongue, or pharyngeal hematoma (with potential for airway compromise) Intracranial, intraabdominal, or intrathoracic bleeding Fractures Initially 40-50 IU FVIII:C/kg, followed by 20-25 IU FVIII:C/kg every 8 hours to maintain the FVIII:C plasma level at 80-100% of normal for 7 days. Continue the same dose once or twice daily for another 7 days to maintain the FVIII:C level at 30-50% of normal.
2.2Treatment of Bleeding Episodes in VWD Administer 40 to 80 International Units (IU) VWF:RCo (corresponding to 17 to 33 International Units (IU) FVIII in Humate-P) per kg body weight every 8 to 12 hours. Adjust the dosage based on the extent and location of bleeding. Administer repeat doses as long as needed based on monitoring of appropriate clinical and laboratory measures ( see Warnings and Precautions [5.2 and 5.3] ).
Expected levels of VWF:RCo are based on an expected in vivo recovery (IVR) of
2.0International Units (IU)/dL rise per International Unit (IU)/kg VWF:RCo administered. The administration of 1 International Unit (IU) of FVIII per kg body weight can be expected to lead to a rise in circulat… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Humate-P is a sterile, lyophilized powder for intravenous administration. Each vial of Humate-P contains the labeled amount of VWF:RCo and FVIII activity expressed in International Units (IU). The average ratio of VWF:RCo to FVIII is 2.4:1.
Approximate potencies are shown below; check each carton/vial for the actual potency prior to reconstitution: VWF:RCo/vial FVIII/vial Diluent * IU = International Units. 600 IU 250 IU 5 mL 1200 IU 500 IU 10 mL 2400 IU 1000 IU 15 mL Each vial of Humate-P lyophilized powder contains the labeled amount of VWF:RCo and FVIII activity expressed in IU IU = International Units. . The average ratio of VWF:RCo to FVIII is 2.4:1.
Approximate potencies are shown below; check each carton/vial for the actual potency prior to reconstitution ( 3 ): VWF:RCo/vial FVIII/vial Diluent * IU = International Units. 600 IU 250 IU 5 mL 1200 IU 500 IU 10 mL 2400 IU 1000 IU 15 mL
⛔ Contraindications ▾
4 CONTRAINDICATIONS Humate-P is contraindicated in individuals who have had an anaphylactic or severe systemic reaction to antihemophilic factor or von Willebrand factor preparations. Anaphylactic or severe systemic reaction to antihemophilic factor or VWF preparations ( 4 ).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS VWD patients receiving Humate-P may be at risk of developing thromboembolic events ( 5.1 ). Monitor for intravascular hemolysis and decreasing hematocrit values in patients with A, B, and AB blood groups who are receiving large or frequent doses ( 5.2 ). Monitor VWF:RCo and FVIII levels in VWD patients, especially those undergoing surgery ( 5.3 ).
Products made from human plasma may contain infectious agents (e.g., viruses, and, theoretically, the Creutzfeldt-Jakob disease (CJD) agent ( 5.4 ).
5.1Thromboembolic Events (VWD Patients) Thromboembolic events have been reported in VWD patients receiving Antihemophilic Factor/von Willebrand Factor Complex replacement therapy, especially in the setting of known risk factors for thrombosis. 3,4 Early reports indicate a higher incidence may occur in females. Endogenous high levels of FVIII have also been associated with thrombosis, but no causal relationship has been established.
Exercise caution and consider antithrombotic measures in all at-risk VWD patients who are receiving coagulation factor replacement therapy.
5.2Monitoring for Intravascular Hemolysis Humate-P contains blood group isoagglutinins (anti-A and anti-B). When doses are very large or need to be repeated frequently (for example, when inhibitors are present or when pre- and post-surgical care is involved), monitor patients of blood groups A, B, and AB for signs of intravascular hemolysis and decreasing hematocrit values and treat appropriately.
5.3Monitoring VWF:RCo and FVIII Levels Monitor the VWF:RCo and FVIII levels of VWD patients receiving Humate-P using standard coagulation tests, especially in cases of surgery. It is advisable to monitor trough VWF:RCo and FVIII:C levels at least once a day in order to adjust the dosage of Humate-P as needed to avoid excessive accumulation of coagulation factors (s ee Dosage and Administration [2.2 , 2.3] ).
5.4Transmission of Infectious Agents Humate-P is made from human plasma. Products made from human plasma may contain infectious agents (e.g., viruses and theoretically, the Creutzfeldt-Jakob disease [CJD] agent) that can cause disease ( see Description [11] and Patient Counseling Information [17.1] ). The risk that such products will transmit an infectious agent has been reduced by screening plasma donors for prior exposure to certain viruses, by testing for the presence of certain current virus infections, and by inactivating and/or removing certain viruses during manufacturing ( see Description [11.1] for virus reduction measures ).
Despite these measures, such products can still potentially transmit disease. There is also the possibility that unknown infectious agents may be present in such products. Thus the risk of transmission of infectious agents cannot be eliminated completely.
Report all infections thought by a physician possibly to have been transmitted by this product to CSL Behring Pharmacovigilance at 1-866-915-6958 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . Some viruses, such as Parvovirus B19 virus (B19V) or hepatitis A (HAV), are particularly difficult to remove or inactivate. B19V may most seriously affect pregnant women and immune-compromised individuals.
Although the overwhelming number of B19V and HAV cases are community acquired, reports of these infections have been associated with the use of some plasma-derived products. Therefore, physicians should be alert to the potential symptoms of B19V and HAV infections ( see Patient Counseling Information [17.1] ). Symptoms of B19V may include low-grade fever, rash, arthralgias, and transient symmetric, nondestructive arthritis.
Diagnosis is often established by measuring B19V-specific IgM and IgG antibodies. Symptoms of HAV include low-grade fever, anorexia, nausea, vomiting, fatigue, and jaundice. A diagnosis may be established by measuring specific IgM antibodies.
Physicians should strongly consider administration of hepatitis A and hepatitis B vaccines to individuals re… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most serious adverse reaction observed in patients receiving Humate-P is anaphylaxis. Thromboembolic events have also been observed in patients receiving Humate-P for the treatment of VWD ( see Warnings and Precautions [5.1] ). Reports of thromboembolic events in VWD patients with other thrombotic risk factors receiving coagulation factor replacement therapy have been obtained from spontaneous reports, published literature, and a European clinical study.
In some cases, inhibitors to coagulation factors may occur. However, no inhibitor formation was observed in any of the clinical studies. In patients receiving Humate-P in clinical studies for treatment of VWD, the most commonly reported adverse reactions observed by >5% of subjects are allergic-anaphylactic reactions (including urticaria, chest tightness, rash, pruritus, and edema).
For patients undergoing surgery, the most common adverse reactions are postoperative wound and injection-site bleeding, and epistaxis. Most common adverse reactions observed by >5% of subjects after receiving Humate-P are allergic-anaphylactic reactions (e.g., urticaria, chest tightness, rash, pruritus, edema) and, in patients undergoing surgery, postoperative wound and injection-site bleeding, and epistaxis ( 6 ). To report SUSPECTED ADVERSE REACTIONS, contact CSL Behring Pharmacovigilance at 1-866-915-6958 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Studies Experience Because clinical studies are conducted under widely varying conditions, the adverse reaction rates observed cannot be directly compared to rates in other clinical trials and may not reflect the rates observed in practice. Treatment of Bleeding Episodes in VWD Allergic symptoms, including allergic reaction, urticaria, chest tightness, rash, pruritus, and edema, were reported in 6 of 97 (6%) subjects in a Canadian retrospective study ( see Clinical Studies [14.1] ). Four of 97 (4%) subjects experienced seven adverse events that were considered to have a possible or probable relationship to Humate-P.
These included chills, phlebitis, vasodilation, paresthesia, pruritus, rash, and urticaria. All were mild in intensity with the exception of a moderate case of pruritus. In a prospective, open-label safety and efficacy study of Humate-P in VWD subjects with serious life- or limb-threatening bleeding or undergoing emergency surgery, seven of 71 (10%) subjects experienced nine adverse reactions.
These were one occurrence each of mild vasodilation and mild pruritis; two occurrences of mild paresthesia; and one occurrence each of moderate peripheral edema and extremity pain and severe pseudothrombocytopenia (platelet clumping with a false low reading). Humate-P was discontinued in the subject who experienced the peripheral edema and extremity pain. Prevention of Excessive Bleeding During and After Surgery in VWD Among the 63 VWD subjects who received Humate-P for prevention of excessive bleeding during and after surgery, including one subject who underwent colonoscopy without the planned polypectomy, the most common adverse events were postoperative hemorrhage (35 events in 19 subjects with five subjects experiencing bleeding at up to three different sites), postoperative nausea (15 subjects), and postoperative pain (11 subjects).
Table 5 presents the postoperative hemorrhagic adverse events. Table 5: Hemorrhagic Adverse Events in 63 Surgical Subjects Adverse Event Surgical Procedure Category Number of Subjects/Events Onset On = on-therapy; onset while receiving Humate-P or within 1 day of completing Humate-P administration. Post = post-therapy; onset at least one day after completing Humate-P administration.
(Number of Events) Severity (Number of Events) On Post Mild Mod Severe Wound/injection site bleeding Major 8/11 7 4 9 – 2 Minor 2/2 2 – 1 1 – Oral 2/6 – 6 3 3 – Epistaxis Major 4/4 2 2 3 1 – Minor 1/1 1 – 1 – – Cerebral hemorrhage/ subdural hematoma Major 1/2 2 Reported as serious adverse events… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS None reported.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: No human or animal data. Use only if clearly needed ( 8.1 ). The hemostatic efficacy of Humate-P has been studied in 34 pediatric subjects with VWD ( 8.4 ). Based on the data from a subset of these subjects, age had no effect on the pharmacokinetics of VWF:RCo ( 12.3 ).
8.1Pregnancy Pregnancy Category C. Animal reproduction studies have not been conducted with Humate-P. It is also not known whether Humate-P can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. Humate-P should be given to a pregnant woman only if clearly needed.
8.2Labor and Delivery It is not known whether Humate-P can cause harm to the mother or the fetus when administered during labor and delivery. Humate-P should be given during labor and delivery only if clearly needed.
8.3Nursing Mothers It is not know whether this drug is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when Humate-P is administered to a nursing woman.
8.4Pediatric Use Hemophilia A Adequate and well-controlled studies with long-term evaluation of joint damage have not been done in pediatric subjects. Joint damage may result from suboptimal treatment of hemarthroses. VWD The safety and effectiveness of Humate-P for the treatment of VWD was demonstrated in 26 pediatric subjects, including infants, children, and adolescents, but have not been evaluated in neonates.
The safety of Humate-P for the prevention of excessive bleeding during and after surgery was demonstrated in eight pediatric subjects (ages 3 to 15) with VWD. Of the 34 pediatric subjects studied for either treatment of bleeding episodes in VWD or prevention of excessive bleeding during and after surgery, four were infants (1 month to under 2 years of age), 23 were children (2 through 12 years), and seven were adolescents (13 through 15 years). As in adults, pediatric patients should be dosed based on body weight (kg) ( see Dosage and Administration [2.2 , 2.3] ).
8.5Geriatric Use Clinical studies of Humate-P did not include sufficient numbers of subjects 65 years of age and older to determine whether they respond differently from younger subjects. As for all patients, dosing for geriatric patients should be appropriate to their overall situation.
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category C. Animal reproduction studies have not been conducted with Humate-P. It is also not known whether Humate-P can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. Humate-P should be given to a pregnant woman only if clearly needed.
🧒 Pediatric Use ▾
8.4Pediatric Use Hemophilia A Adequate and well-controlled studies with long-term evaluation of joint damage have not been done in pediatric subjects. Joint damage may result from suboptimal treatment of hemarthroses. VWD The safety and effectiveness of Humate-P for the treatment of VWD was demonstrated in 26 pediatric subjects, including infants, children, and adolescents, but have not been evaluated in neonates.
The safety of Humate-P for the prevention of excessive bleeding during and after surgery was demonstrated in eight pediatric subjects (ages 3 to 15) with VWD. Of the 34 pediatric subjects studied for either treatment of bleeding episodes in VWD or prevention of excessive bleeding during and after surgery, four were infants (1 month to under 2 years of age), 23 were children (2 through 12 years), and seven were adolescents (13 through 15 years). As in adults, pediatric patients should be dosed based on body weight (kg) ( see Dosage and Administration [2.2 , 2.3] ).
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of Humate-P did not include sufficient numbers of subjects 65 years of age and older to determine whether they respond differently from younger subjects. As for all patients, dosing for geriatric patients should be appropriate to their overall situation.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The active components of Humate-P consist of two different noncovalently bound proteins (FVIII and VWF). FVIII is an essential cofactor in activation of factor X, leading ultimately to the formation of thrombin and, subsequently, fibrin. VWF promotes platelet aggregation and platelet adhesion on damaged vascular endothelium; activated platelets interact with clotting proteins to form a clot.
VWF also serves as a stabilizing carrier protein for the procoagulant protein FVIII. 7,8 The activity of VWF is measured as VWF:RCo.
12.3Pharmacokinetics Hemophilia A After infusion of Humate-P, a rapid increase of plasma FVIII:C is followed by a rapid decrease in activity and, subsequently, a slower rate of decrease in activity. Studies with Humate-P in subjects with hemophilia A have demonstrated a mean half-life of 12.2 (range: 8.4 to 17.4) hours. VWD The pharmacokinetics of Humate-P were studied in 41 subjects in a US study and in 28 subjects in a European study ( see Clinical Studies [14.2] ).
In both studies, subjects were evaluated in the nonbleeding state prior to a surgical procedure. Table 8 summarizes the pharmacokinetics of Humate-P based on these studies. Wide inter-subject variability was observed in pharmacokinetic values obtained from these studies.
Table 8: Pharmacokinetics of Humate-P in Two Studies of Subjects in the Non-Bleeding State Prior to Surgery US Study European Study IU = International Units. BW = body weight. Number of subjects Type 1 VWD Type 2A VWD Type 2B VWD Type 2M VWD Type 3 VWD 41 16 2 4 6 13 28 10 10 -- 1 7 Dosage of Humate-P 60 IU VWF:RCo/kg BW 80 IU VWF:RCo/kg BW Median terminal half-life of VWF:RCo (range) 11 hours Excluding 5 subjects with a half-life exceeding the blood sampling time of 24 or 48 hours.
(3.5-33.6) 10 hours Excluding 1 subject with a half-life exceeding the blood sampling time of 48 hours. (2.8-28.3) Median clearance (range) 3.1 mL/hr/kg (1-16.6) 4.8 mL/hr/kg (2.1-53) Volume of distribution at steady state (range) 53 mL/kg (29-141) 59 mL/kg (32-290) Median IVR for VWF:RCo activity (range)
2.4IU/dL per IU/kg (1.1-4.2)
1.9IU/dL per IU/kg (0.6-4.5) The multimeric patterns of Humate-P in the US study, were measured in 13 subjects with type 3 VWD; 11 had absent or barely detectable multimers at baseline. Of those 11 subjects, all had some high molecular weight multimers present 24 hours after infusion of Humate-P. In the European study, infusion of Humate-P corrected the defect of the multimer pattern in subjects with types 2A and 3 VWD.
High molecular weight multimers were detectable until at least 8 hours after infusion. Based on the small sample size evaluation, it appears that age, sex, and type of VWD have no impact on the pharmacokinetics of VWF:RCo.
🧬 Mechanism of Action ▾
12.1Mechanism of Action The active components of Humate-P consist of two different noncovalently bound proteins (FVIII and VWF). FVIII is an essential cofactor in activation of factor X, leading ultimately to the formation of thrombin and, subsequently, fibrin. VWF promotes platelet aggregation and platelet adhesion on damaged vascular endothelium; activated platelets interact with clotting proteins to form a clot.
VWF also serves as a stabilizing carrier protein for the procoagulant protein FVIII. 7,8 The activity of VWF is measured as VWF:RCo.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Humate-P is supplied in a single-dose vial containing the labeled amount of VWF:RCo and FVIII activity expressed in International Units (IU). Each package contains a vial of Humate-P, a vial of diluent containing sterile water (meets USP chemistry requirements Sterile Water for Injection, except for pH), a Mix2Vial filter transfer set, and two alcohol swabs. The components used in the packaging for Humate-P contain no latex.
Approximate potencies are shown below; check each carton/vial for the actual potency prior to reconstitution: NDC Number VWF:RCo/vial FVIII/vial Diluent IU = International Units. 63833-615-02 600 IU 250 IU 5 mL 63833-616-02 1200 IU 500 IU 10 mL 63833-617-02 2400 IU 1000 IU 15 mL When stored at temperatures up to 25°C (77°F), Humate-P is stable for 24 months up to the expiration date printed on its label. Do not freeze.
This product does not contain a preservative and should be used within 3 hours after reconstitution.
📦 Storage and Handling ▾
When stored at temperatures up to 25°C (77°F), Humate-P is stable for 24 months up to the expiration date printed on its label. Do not freeze. This product does not contain a preservative and should be used within 3 hours after reconstitution.
📋 Description ▾
11 DESCRIPTION Humate-P, Antihemophilic Factor/von Willebrand Factor Complex (Human), is a purified, sterile, lyophilized concentrate of Factor VIII (FVIII) and von Willebrand Factor (VWF) (Human) to be administered by the intravenous route in the treatment of patients with classical hemophilia (hemophilia A) and VWD ( see Clinical Pharmacology [12] ). Humate-P is purified from the cold insoluble fraction of pooled human plasma and contains purified and concentrated FVIII/VWF Complex (Human). Fibrinogen content is less than or equal to 0.2 mg/mL.
Each vial of Humate-P contains the labeled amount of von Willebrand Factor:Ristocetin Cofactor (VWF:RCo) and FVIII activity expressed in International Units (IU) ( see Dosage Forms and Strengths [3] ). An International Unit (IU) is defined by the current international standard established by the World Health Organization. One International Unit (IU) of VWF:RCo or FVIII is approximately equal to the amount of VWF:RCo or FVIII in 1.0 mL of fresh-pooled human plasma.
The average ratio of VWF:RCo to FVIII is 2.4:1. When reconstituted with the volume of diluent (sterile water) provided, each mL of Humate-P contains 72 to 224 International Units (IU) VWF:RCo activity This correlates to a VWF:RCo to FVIII activity average ratio of 2.4:1, which is used to calculate the nominal values of VWF:RCo activity and is the average VWF:RCo activity. , 40 to 80 International Units (IU) FVIII activity, 15 to 33 mg of glycine, 3.5 to 9.3 mg of sodium citrate, 2 to 5.3 mg of sodium chloride, 8 to 16 mg of Albumin (Human), 2 to 14 mg of other proteins, and 10 to 20 mg of total proteins.
Humate-P contains no preservative. Humate-P has been demonstrated in several studies to contain the high molecular weight multimers of VWF. This component is considered to be important for correcting the coagulation defect in patients with VWD.
5 When administered to patients with VWD (types 1, 2, or 3), bleeding time decreased. This outcome was correlated with the presence of a multimeric composition of VWF similar to that found in normal plasma. 6 Humate-P contains anti-A and anti-B blood group isoagglutinins ( see Warnings and Precautions [5.2] ).
The pooled human plasma used to produce Humate-P is collected from licensed facilities in the US. All source plasma used in the manufacture of Humate-P is tested by FDA-licensed Nucleic Acid Tests (NAT) for hepatitis C virus (HCV) and human immunodeficiency virus-1 (HIV-1) and found to be nonreactive (negative). The source plasma is also tested by an investigational NAT for hepatitis B virus (HBV) and found to be nonreactive (negative).
The purpose of the HBV test is to detect low levels of viral material; however, the significance of a nonreactive (negative) result has not been established.
11.1Virus Reduction Capacity The manufacturing procedure for Humate-P includes multiple processing steps that reduce the risk of virus transmission. The manufacturing process has been demonstrated to reduce the risk of virus transmission in an additive manner: 1) cryoprecipitation; 2) Al(OH) 3 adsorption, glycine precipitation, and NaCl precipitation, studied in combination; and 3) pasteurization in aqueous solution at 60°C for 10 hours. Total mean cumulative virus reductions ranged from 6.0 to ≥11.3 log 10 as shown in Table 7.
Table 7: Mean Virus Reduction Factors Virus Studied Cryoprecipitation Al(OH) 3 Adsorption / Glycine Precipitation / NaCl Precipitation Pasteurization Mean Cumulative Virus Reduction [log 10 ] [log 10 ] [log 10 ] [log 10 ] ND, not determined; NA, not applicable; HIV-1, human immunodeficiency virus type 1, model for HIV types 1 and 2; BVDV, bovine viral diarrhea virus, model for HCV and WNV; PRV, pseudorabies virus, model for large enveloped DNA viruses (e.g., herpes virus); WNV, West Nile virus; HAV, hepatitis A virus; and CPV, canine parvovirus, model for Parvovirus B19 virus (B19V).
Enveloped Viruses HIV-1 ND 3.6 ≥6.4 ≥10.0 BVDV ND 2.4 ≥8.9 ≥11.3 PRV 1.6 3.7 4.6 9.9… [Excerpted — this section continues on DailyMed.]
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Inform patients that Humate-P is made from human plasma (part of the blood) and may contain infectious agents that can cause disease (e.g., viruses and, theoretically, the CJD agent). Explain that the risk that Humate-P may transmit an infectious agent has been reduced by screening plasma donors, by testing the donated plasma for certain virus infections, and by inactivating and/or removing certain viruses during manufacturing ( see Warnings and Precautions [5.4] ). Inform patients that some viruses, such as B19V and HAV, may be particularly difficult to remove or inactivate.
Advise patients, especially pregnant women and immune-compromised individuals, to report low-grade fever, rash, joint pain, anorexia, nausea, vomiting, fatigue, and jaundice ( see Warnings and Precautions [5.4] ).
🍼 Nursing Mothers ▾
8.3Nursing Mothers It is not know whether this drug is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when Humate-P is administered to a nursing woman.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Hemophilia A After infusion of Humate-P, a rapid increase of plasma FVIII:C is followed by a rapid decrease in activity and, subsequently, a slower rate of decrease in activity. Studies with Humate-P in subjects with hemophilia A have demonstrated a mean half-life of 12.2 (range: 8.4 to 17.4) hours. VWD The pharmacokinetics of Humate-P were studied in 41 subjects in a US study and in 28 subjects in a European study ( see Clinical Studies [14.2] ).
In both studies, subjects were evaluated in the nonbleeding state prior to a surgical procedure. Table 8 summarizes the pharmacokinetics of Humate-P based on these studies. Wide inter-subject variability was observed in pharmacokinetic values obtained from these studies.
Table 8: Pharmacokinetics of Humate-P in Two Studies of Subjects in the Non-Bleeding State Prior to Surgery US Study European Study IU = International Units. BW = body weight. Number of subjects Type 1 VWD Type 2A VWD Type 2B VWD Type 2M VWD Type 3 VWD 41 16 2 4 6 13 28 10 10 -- 1 7 Dosage of Humate-P 60 IU VWF:RCo/kg BW 80 IU VWF:RCo/kg BW Median terminal half-life of VWF:RCo (range) 11 hours Excluding 5 subjects with a half-life exceeding the blood sampling time of 24 or 48 hours.
(3.5-33.6) 10 hours Excluding 1 subject with a half-life exceeding the blood sampling time of 48 hours. (2.8-28.3) Median clearance (range) 3.1 mL/hr/kg (1-16.6) 4.8 mL/hr/kg (2.1-53) Volume of distribution at steady state (range) 53 mL/kg (29-141) 59 mL/kg (32-290) Median IVR for VWF:RCo activity (range)
2.4IU/dL per IU/kg (1.1-4.2)
1.9IU/dL per IU/kg (0.6-4.5) The multimeric patterns of Humate-P in the US study, were measured in 13 subjects with type 3 VWD; 11 had absent or barely detectable multimers at baseline. Of those 11 subjects, all had some high molecular weight multimers present 24 hours after infusion of Humate-P. In the European study, infusion of Humate-P corrected the defect of the multimer pattern in subjects with types 2A and 3 VWD.
High molecular weight multimers were detectable until at least 8 hours after infusion. Based on the small sample size evaluation, it appears that age, sex, and type of VWD have no impact on the pharmacokinetics of VWF:RCo.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Controlled clinical studies to evaluate the safety and efficacy of prophylactic dosing with Humate-P to prevent spontaneous bleeding have not been conducted in VWD subjects. Adequate data are not presently available on which to evaluate or to base dosing recommendations in this setting.
14.1Treatment of Bleeding Episodes in VWD Clinical efficacy of Humate-P in the control of bleeding in subjects with VWD was determined by a retrospective review of clinical safety and efficacy data obtained from 97 Canadian VWD subjects who received product under an Emergency Drug Release Program. The dosage schedule and duration of therapy were determined by the medical practitioner. There were 514 requests for product use for surgery, bleeding, or prophylaxis in the 97 subjects.
Of these, Humate-P was not used in 151 cases, and follow-up safety and/or efficacy information was available for 303 (83%) of the remaining 363 requests. In many cases, Humate-P from a single request was used for several treatment courses in one subject. Therefore, there are more reported treatment courses than requests.
Humate-P was administered to 97 subjects in 530 treatment courses: 73 for surgery, 344 for treatment of bleeding, and 20 for prophylaxis of bleeding. The majority of the 93 "other" uses involved dental procedures, diagnostic procedures, prophylaxis prior to a procedure, or test doses. Table 9 summarizes the dosing information (all subjects) for bleeding episodes.
Table 9: Dosing Information for Bleeding Episodes in VWD Type/Location of Bleeding Episode Digestive System Nose+Mouth +Pharynx Integument System Female Genital System Musculo-skeletal SD, standard deviation. No. of Subjects 14 29 11 4 22 Loading Dose Mean Dose (SD) IU VWF:RCo/kg. 62.1 (31.1) 66.9 (24.3) 73.4 (37.7) 88.5 (28.3) 50.2 (24.9) No. of Infusions Number of infusions where the dose per kg body weight was available.
37 127 22 7 107 Maintenance Dose Mean Dose (SD) 61.5 (38.0) 67.5 (22.4) 56.5 (63.3) 74.5 (17.7) 63.8 (28.8) No. of Infusions 250 55 4 15 121 No. of Treatment Days per Bleeding Episode Mean (SD) No. of Events 4.6 (3.6) 49 1.4 (1.2) 130 1.1 (0.4) 22 2.8 (2.9) 9 2.0 (1.9) 108 No. of Infusions by Treatment Day No. of Subjects 14 29 11 4 22 Day 1 Day 1, first treatment day. Mean (SD) No. of Events 1.2 (0.4) 49 1.1 (0.2) 130 1.0 (0.2) 22 1.0 (0.0) 9 1.0 (0.1) 108 No. of Subjects 13 9 3 1 15 Day 2 Mean (SD) No. of Events 1.2 (0.6) 41 1.3 (0.5) 12 1.0 (0.0) 3 1.0 (-) 1 1.2 (0.5) 26 No. of Subjects 12 6 - 2 10 Day 3 Mean (SD) No. of Events 1.5 (0.8) 25 1.4 (0.7) 9 - - 1.0 (0.0) 3 1.2 (0.4) 18
14.2Prevention of Excessive Bleeding During and After Surgery in VWD Two prospective, open-label, non-controlled, multicenter clinical studies, one in the US and one in Europe, investigated the safety and hemostatic efficacy of Humate-P in subjects with VWD undergoing surgery. • US clinical study – The primary objective of this study was to demonstrate the safety and hemostatic efficacy of Humate-P in preventing excessive bleeding in adult and pediatric subjects with VWD undergoing surgery. The 35 subjects (21 female and 14 male) ranged in age from 3 to 75 years (mean 32.9); seven were age 15 or younger and two were age 65 or older.
Twelve subjects had type 1 VWD, two had type 2A, three had type 2B, five had type 2M, and 13 had type 3. Twenty-eight of the surgical procedures were classified as major (e.g., orthopedic joint replacement, intracranial surgery, multiple tooth extractions, laparoscopic cholecystectomy), four as minor (e.g., placement of intravenous access device), and three subjects had oral surgery Oral surgery is defined as extraction of fewer than three teeth, if the teeth are non-molars and have no bony involvement. Extraction of more than one impacted wisdom tooth is considered major surgery due to the expected difficulty of the surgery and the expected blood loss, particularly in subjects with type 2A or type 3 VWD.
Extraction of more than two teeth is c… [Excerpted — this section continues on DailyMed.]
📚 References ▾
15 REFERENCES Levine PH, Brettler DB. Clinical aspects and therapy for hemophilia A. In: Hoffman R, Benz JB, Shattil SJ, Furie B, Cohen HJ, eds.
Hematology: Basic Principles and Practice . New York: Churchill Livingstone Inc.; 1991:1296-1297. Scott JP, Montgomery RT.
Therapy of von Willebrand disease. Semin Thromb Hemost. 1993;19:37-47.
Mannucci, PM. Venous Thromboembolism in Von Willebrand Disease. Thromb Haemostas.
2002;88:378-379. Markis M, Colvin B, Gupta V, Shields ML, Smith MP. Venous thrombosis following the use of intermediate purity FVIII concentrate to treat patients with von Willebrand's disease.
Thromb Haemostas. 2002;88:387-388. Berntorp E, Nilsson IM.
Biochemical and in vivo properties of commercial virus-inactivated factor VIII concentrates . Eur J Haematol. 1988;40:205-214.
Berntorp E. Plasma product treatment in various types of von Willebrand's disease. Haemostasis.
1994;24:289-297. Hoyer LW. The factor VIII complex: structure and function.
Blood. 1981;58:1-13. Meyer D, Girma J-P. von Willebrand factor: structure and function.
Thromb Haemostas. 1993;70:99-104.
📄 Package Label / Principal Display Panel ▾
Principal Display Panel - 250 IU Carton NDC 63833-615-02 One Vial and Diluent Antihemophilic Factor/ von Willebrand Factor Complex (Human) HUMATE-P ® Powder for Reconstitution For intravenous use only. I.U. VWF:RCo/vial I.U. FVIII/vial Expires: Lot no.: CSL Behring Principal Display Panel - 250 IU Carton
Principal Display Panel - 500 IU Carton NDC 63833-616-02 One Vial and Diluent Antihemophilic Factor/ von Willebrand Factor Complex (Human) HUMATE-P ® Powder for Reconstitution For intravenous use only. I.U. VWF:RCo/vial I.U. FVIII/vial Expires: Lot no.: CSL Behring Principal Display Panel - 500 IU Carton
Principal Display Panel - 1000 IU Carton NDC 63833-617-02 One Vial and Diluent Antihemophilic Factor/ von Willebrand Factor Complex (Human) HUMATE-P ® Powder for Reconstitution For intravenous use only. I.U. VWF:RCo/vial I.U. FVIII/vial Expires: Lot no.: CSL Behring Principal Display Panel - 1000 IU Carton
Medicaid utilization & spend
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |