
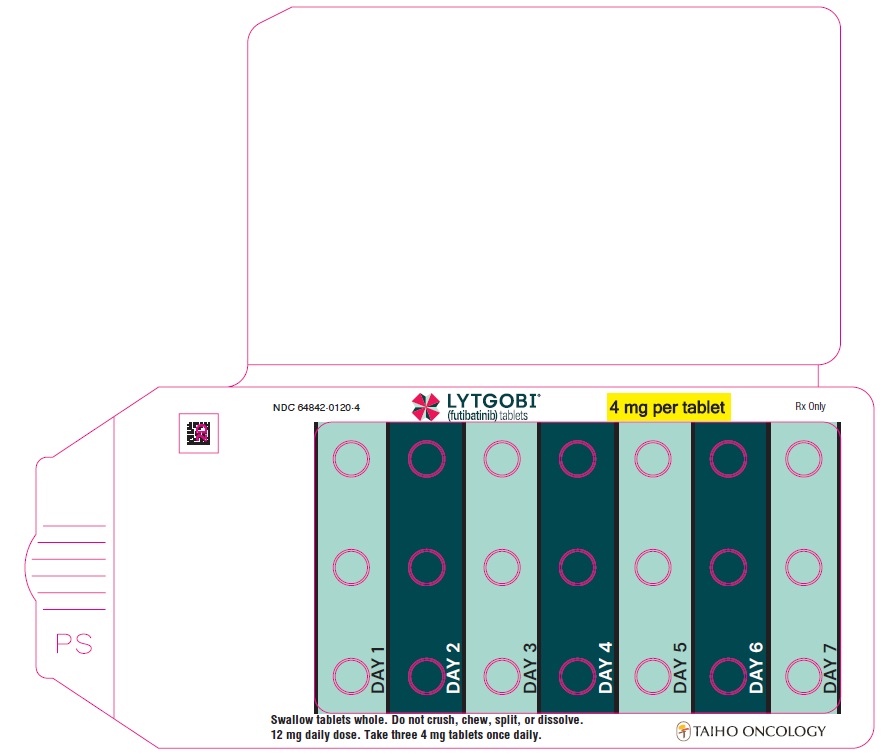
LYTGOBI FUTIBATINIB 4 mg Tablet, 21-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Futibatinib is used in adults who have received previous therapy to treat a certain type of cholangiocarcinoma (bile duct cancer) that has spread to nearby tissues or other parts of the body and cannot be removed by surgery. Futibatinib is in a class of medications called kinase inhibitors. It works by blocking the action of the abnormal protein that signals cancer cells to multiply. This helps slow or stop the spread of cancer cells.
Read the full MedlinePlus article ↗- Lytgobi is treating a specific type of bile duct cancer called intrahepatic cholangiocarcinoma — 'intrahepatic' means the cancer started inside the liver, in the bile ducts there....
- What exactly is Lytgobi treating — can you explain it in plain language?
- You can take Lytgobi with or without food, so meals don't need to be planned around it. What does matter is consistency — try to take it at roughly the same time each day. If you h...
- Do I have to take it at a specific time of day, and does it matter if I eat first?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Futibatinib — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 9XZ8H6N6OH
A plant-based cellulose derivative used as a binder to hold tablet ingredients together, a thickener in liquids, and a coating agent to control how fast the medicine dissolves.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $311.13 | $6,533.82 / 21 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lytgobi 4 mgthis 64842-0120-04 | TAIHO | 21 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9108973 ↗ | Drug substance | U-3456 | Feb 13, 2033 |
| US 9108973 ↗ | Drug substance | U-3456 | Feb 13, 2033 |
| US 11833151 ↗ | Drug product | — | Nov 5, 2039 |
| US 11833151 ↗ | Drug product | — | Nov 5, 2039 |
| US 10434103 ↗ | Drug substance | — | Mar 31, 2036 |
| US 10434103 ↗ | Drug substance | — | Mar 31, 2036 |
| Code | What it grants | Expires |
|---|---|---|
| NCE | New Chemical Entity (5-year) | Sep 30, 2027 |
| ODE-410 | Orphan Drug Exclusivity (7-year) | Sep 30, 2029 |
| NCE | New Chemical Entity (5-year) | Sep 30, 2027 |
| ODE* | Orphan Drug Exclusivity (7-year) | Sep 30, 2029 |
Is there a generic version of LYTGOBI 12 MG DOSE (3X 4MG TB)?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 64842-0120-04 You're viewing this | 1 BLISTER PACK in 1 CARTON (64842-0120-4) / 21 TABLET in 1 BLISTER PACK | 2023-02-03 | Active |
| 64842-0120-05 | 1 BLISTER PACK in 1 CARTON (64842-0120-5) / 28 TABLET in 1 BLISTER PACK | 2023-02-03 | Active |
| 64842-0120-06 | 1 BLISTER PACK in 1 CARTON (64842-0120-6) / 35 TABLET in 1 BLISTER PACK | 2023-02-03 | Active |
Pack size FAQ
What quantity is in NDC 64842-0120-04?
What is the difference between NDC 64842-0120-04 and NDC 64842-0120-05?
What NDC number is used to bill for this package of LYTGOBI FUTIBATINIB 4 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE LYTGOBI is indicated for the treatment of adult patients with previously treated, unresectable, locally advanced or metastatic intrahepatic cholangiocarcinoma harboring fibroblast growth factor receptor 2 (FGFR2) gene fusions or other rearrangements [see Dosage and Administration (2.1) ] . This indication is approved under accelerated approval based on overall response rate and duration of response [see Clinical Studies (14.1) ] . Continued approval for this indication may be contingent upon verification and description of clinical benefit in a confirmatory trial(s).
LYTGOBI is a kinase inhibitor indicated for the treatment of adult patients with previously treated, unresectable, locally advanced or metastatic intrahepatic cholangiocarcinoma harboring fibroblast growth factor receptor 2 (FGFR2) gene fusions or other rearrangements. ( 1 , 2.1 ) This indication is approved under accelerated approval based on overall response rate and duration of response. Continued approval for this indication may be contingent upon verification and description of clinical benefit in a confirmatory trial(s).
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Confirm the presence of an FGFR2 gene fusion or other rearrangement prior to initiation of treatment with LYTGOBI. ( 2.1 ) Recommended dose is 20 mg orally (five 4 mg tablets or one 16 mg tablet and one 4 mg tablet) once daily until disease progression or unacceptable toxicity occurs. ( 2.2 ) Swallow tablet whole, with or without food. ( 2.2 )
2.1Patient Selection Select patients for the treatment of unresectable, locally advanced or metastatic intrahepatic cholangiocarcinoma with LYTGOBI based on the presence of an FGFR2 gene fusion or rearrangement [see Clinical Studies (14.1) ]. An FDA-approved test for detection of FGFR2 gene fusions or other rearrangements in patients with unresectable, locally advanced, or metastatic intrahepatic cholangiocarcinoma for selecting patients for treatment with LYTGOBI is not available.
2.2Recommended Dosage The recommended dosage of LYTGOBI is 20 mg (five 4 mg tablets or one 16 mg and one 4 mg tablet) taken orally once daily until disease progression or unacceptable toxicity occurs. Take LYTGOBI with or without food at approximately the same time each day [see Clinical Pharmacology (12.3) ] . Swallow tablets whole.
Do not crush, chew, split, or dissolve tablets. If the patient misses a dose of LYTGOBI for more than 12 hours or if vomiting occurs, resume dosing with the next scheduled dose.
2.3Dosage Modification for Adverse Reactions The recommended dose reductions for adverse reactions are provided in Table 1 . Table 1: Recommended Dose Reductions for LYTGOBI for Adverse Reactions Dose Reduction Recommended Dosage First dose reduction 16 mg (four 4 mg tablets or one 16 mg tablet) orally once daily Second dose reduction Permanently discontinue LYTGOBI if unable to tolerate 12 mg orally once daily. 12 mg (three 4 mg tablets) orally once daily Recommended dosage modifications for adverse reactions are provided in Table 2 .
Table 2: Recommended Dosage Modifications for LYTGOBI Adverse Reactions Adverse Reaction Severity LYTGOBI Dosage Modifications a Severity as defined by National Cancer Institute Common Terminology Criteria for Adverse Events (NCI CTCAE version 4.03). Retinal Pigment Epithelial Detachment (RPED) [see Warnings and Precautions (5.1) ] Not applicable Continue LYTGOBI at the current dose and continue periodic ophthalmic evaluation: If resolving within 14 days, continue LYTGOBI at the current dose. If not resolving within 14 days, withhold LYTGOBI until resolving; then resume LYTGOBI at previous or a lower dose.
Hyperphosphatemia [see Warnings and Precautions (5.2) ] Serum phosphate ≥5.5 - ≤7 mg/dL Continue LYTGOBI at the current dose and initiate phosphate lowering therapy. Monitor serum phosphate weekly. Serum phosphate >7 - ≤10 mg/dL Initiate or adjust phosphate lowering therapy.
Monitor serum phosphate weekly and Dose reduce LYTGOBI to next lower dose - If the serum phosphate resolves to ≤7 mg/dL within 2 weeks after dose reduction, continue at this reduced dose. - If serum phosphate is not ≤7 mg/dL within 2 weeks, further reduce LYTGOBI to the next lower dose. - If serum phosphate is not ≤7 mg/dL within 2 weeks after the second dose reduction, withhold LYTGOBI until serum phosphate is ≤7 mg/dL and resume at the dose prior to suspending. Serum phosphate >10 mg/dL Initiate or adjust phosphate lowering therapy and monitor serum phosphate weekly and Withhold LYTGOBI until phosphate is ≤7 mg/dL and resume LYTGOBI at the next lower dose. - Permanently discontinue LYTGOBI if serum phosphate is not ≤7 mg/dL within 2 weeks following 2 dose interruptions and reductions.
Other Adverse Reactions Grade 3 a Withhold LYTGOBI until toxicity resolves to Grade 1 or baseline, then resume LYTGOBI - for hematological toxicities resolving within 1 week, at the dose prior to suspending. - for other adverse reactions, at next lower dose. Grade 4 a Permanently discontinue LYTGOBI
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 4 mg, round, white, film-coated tablets debossed with “4MG” on one side, and “FBN” on the other side. 16 mg, round, white, film-coated tablets debossed with “16MG” on one side and “FBN” on the other side. Tablets: 4 mg and 16 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Ocular Toxicity: LYTGOBI can cause retinal pigment epithelial detachment (RPED). Perform a comprehensive ophthalmological examination including optical coherence tomography (OCT) prior to initiation of therapy, every 2 months for the first 6 months, and every 3 months thereafter and urgently at any time for visual symptoms. ( 2.3 , 5.1 ) Hyperphosphatemia and Soft Tissue Mineralization: Increases in phosphate levels can cause hyperphosphatemia leading to soft tissue mineralization, calcinosis, nonuremic calciphylaxis and vascular calcification.
Monitor for hyperphosphatemia and withhold, reduce the dose, or permanently discontinue based on duration and severity of hyperphosphatemia. ( 2.3 , 5.2 ) Embryo-Fetal Toxicity: Can cause fetal harm. Advise patients of reproductive potential of the potential risk to the fetus and to use effective contraception.
( 5.3 , 8.1 , 8.3 )
5.1Ocular Toxicity Retinal Pigment Epithelial Detachment (RPED) LYTGOBI can cause RPED, which may cause symptoms such as blurred vision. Among 318 patients who received LYTGOBI across clinical trials [see Adverse Reactions (6.1) ] where ophthalmologic monitoring did not routinely include optical coherence tomography (OCT), RPED occurred in 9% of patients. The median time to first onset of RPED was 40 days.
RPED led to dose interruption of LYTGOBI in 1.3% of patients, dose reduction in 1.6% of patients, and permanent discontinuation in 0.3% of patients. Perform a comprehensive ophthalmological examination, including OCT of the macula, prior to initiation of therapy, every 2 months for the first 6 months, and every 3 months thereafter. For onset of visual symptoms, refer patients for ophthalmologic evaluation urgently, with follow-up every 3 weeks until resolution or discontinuation of LYTGOBI.
Withhold or reduce the dose of LYTGOBI as recommended [see Dosage and Administration (2.3) ]. Dry Eye/Corneal Keratitis Among 318 patients who received LYTGOBI across clinical trials [see Adverse Reactions (6.1) ] , dry eye occurred in 15% of patients. Treat patients with ocular demulcents as needed.
5.2Hyperphosphatemia and Soft Tissue Mineralization LYTGOBI can cause hyperphosphatemia leading to soft tissue mineralization, calcinosis, nonuremic calciphylaxis, and vascular calcification. Increases in phosphate levels are a pharmacodynamic effect of LYTGOBI [see Clinical Pharmacology (12.2) ] . Among 318 patients who received LYTGOBI across clinical trials [see Adverse Reactions (6.1) ] , hyperphosphatemia was reported in 88% of patients based on laboratory values above the upper limit of normal.
The median time to onset of hyperphosphatemia was 5 days (range 3-117). Phosphate binders were received by 77% of patients who received LYTGOBI. Monitor for hyperphosphatemia throughout treatment.
Initiate a low phosphate diet and phosphate lowering therapy when serum phosphate level is ≥5.5 mg/dL. For serum phosphate levels >7 mg/dL, initiate or intensify phosphate lowering therapy and dose reduce, withhold, or permanently discontinue LYTGOBI based on duration and severity of hyperphosphatemia [see Dosage and Administration (2.3) ] .
5.3Embryo-Fetal Toxicity Based on findings in an animal study and its mechanism of action, LYTGOBI can cause fetal harm when administered to a pregnant woman. Oral administration of futibatinib to pregnant rats during the period of organogenesis caused fetal malformations, fetal growth retardation, and embryo-fetal death at maternal exposures lower than the human exposure at the clinical dose of 20 mg based on area under the curve (AUC). Advise pregnant women of the potential risk to the fetus.
Advise female patients of reproductive potential to use effective contraception during treatment with LYTGOBI and for 1 week after the last dose of LYTGOBI. Advise males with female partners of reproductive potential to use effective contraception during treatment with LYTGOBI and for 1 week after the last dose [see Use in Specif…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed elsewhere in the labeling: Ocular Toxicity [see Warnings and Precautions (5.1) ] Hyperphosphatemia and Soft Tissue Mineralization [see Warnings and Precautions (5.2) ] Most common (≥20%) adverse reactions were nail toxicity, musculoskeletal pain, constipation, diarrhea, fatigue, dry mouth, alopecia, stomatitis, abdominal pain, dry skin, arthralgia, dysgeusia, dry eye, nausea, decreased appetite, urinary tract infection, palmar-plantar erythrodysesthesia syndrome, and vomiting.
( 6.1 ) Most common laboratory abnormalities (≥20%) were increased phosphate, increased creatinine, decreased hemoglobin, increased glucose, increased calcium, decreased sodium, decreased phosphate, increased alanine aminotransferase, increased alkaline phosphatase, decreased lymphocytes, increased aspartate aminotransferase, decreased platelets, increased activated partial thromboplastin time, decreased leukocytes, decreased albumin, decreased neutrophils, increased creatine kinase, increased bilirubin, decreased glucose, increased prothrombin international normalized ratio, and decreased potassium.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Taiho Oncology Inc. at 1-844-878-2446 or FDA at 1-800-FDA-1088 or http://www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The pooled safety population described in the WARNINGS AND PRECAUTIONS reflect exposure to LYTGOBI as a single agent at 20 mg orally once daily in 318 patients including 145 patients with cholangiocarcinoma and 173 patients with other advanced solid tumors.
Among 318 patients who received LYTGOBI, 37% were exposed for 6 months or longer and 13% were exposed for greater than 12 months. Previously Treated, Unresectable Locally Advanced or Metastatic Intrahepatic Cholangiocarcinoma The safety of LYTGOBI was evaluated in Study TAS-120-101, which included 103 patients with previously treated, unresectable locally advanced or metastatic intrahepatic cholangiocarcinoma harboring FGFR2 fusions or other gene rearrangements [see Clinical Studies (14.1) ] . Patients were treated with LYTGOBI 20 mg orally once daily until disease progression or unacceptable toxicity.
The median duration of treatment was 9 months (range: 0.5 - 25 months). Serious adverse reactions occurred in 39% of patients receiving LYTGOBI. Serious adverse reactions in ≥2% of patients who received LYTGOBI included pyrexia (3.9%), gastrointestinal hemorrhage (3.9%), ascites (2.9%), musculoskeletal pain (2.9%), and bile duct obstruction (2.9%).
Permanent discontinuation due to an adverse reaction occurred in 4.9% of patients who received LYTGOBI. Adverse reactions requiring permanent discontinuation of LYTGOBI in one patient each were esophagitis, oral dysesthesia, bile duct obstruction, dizziness, and anemia. Dosage interruptions due to an adverse reaction occurred in 66% of patients who received LYTGOBI.
Adverse reactions requiring dosage interruption in ≥5% of patients included hyperphosphatemia, palmar-plantar erythrodysesthesia syndrome, increased alanine aminotransferase, increased aspartate aminotransferase, and fatigue. Dose reductions due to an adverse reaction occurred in 58% of patients who received LYTGOBI. Adverse reactions requiring dosage reductions in ≥2% of patients who received LYTGOBI included hyperphosphatemia, palmar-plantar erythrodysesthesia syndrome, fatigue, increased alanine aminotransferase, increased aspartate aminotransferase, nail toxicity, and stomatitis.
The most common (≥20%) adverse reactions were nail toxicity, musculoskeletal pain, constipation, diarrhea, fatigue, dry mouth, alopecia, stomatitis, abdominal pain, dry skin, arthralgia, dysgeusia, dry eye, nausea, decr…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong CYP3A inhibitors : Avoid concomitant use. ( 7.1 ) Strong CYP3A inducers : Avoid concomitant use. ( 7.1 )
7.1Effect of Other Drugs on LYTGOBI Strong CYP3A Inhibitors Avoid concomitant use of strong CYP3A inhibitors with LYTGOBI. Futibatinib is a CYP3A substrate [see Clinical Pharmacology (12.3) ] . Concomitant use of a strong CYP3A inhibitor increases futibatinib exposure [see Clinical Pharmacology (12.3) ] , which may increase the risk of adverse reactions.
Strong CYP3A Inducers Avoid concomitant use of strong CYP3A inducers with LYTGOBI. Futibatinib is a CYP3A substrate [see Clinical Pharmacology (12.3) ] . Concomitant use of a strong CYP3A inducer decreases futibatinib exposure [see Clinical Pharmacology (12.3) ] , which may reduce the effectiveness of LYTGOBI.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings in an animal study and its mechanism of action, LYTGOBI can cause fetal harm or loss of pregnancy when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data on the use of LYTGOBI in pregnant women. Oral administration of futibatinib to pregnant rats during the period of organogenesis at maternal plasma exposures below the human exposure at the clinical dose of 20 mg resulted in fetal malformations, fetal growth retardation, and embryo-fetal death ( see Data ).
Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Once daily oral administration of futibatinib to pregnant rats during the period of organogenesis resulted in 100% embryofetal mortality due to post-implantation loss at doses ≥10 mg/kg (approximately 5 times the recommended clinical dose of 20 mg based on body surface area, BSA).
Fetal survival was unaffected at 0.5 mg/kg per day; however, once daily oral administration of futibatinib at the 0.5 mg/kg dose level (approximately 0.2 times the recommended clinical dose of 20 mg based on BSA) resulted in reduced mean fetal body weight and an increase in fetal skeletal and visceral malformations, major blood vessel variations, and reduced ossification.
8.2Lactation Risk Summary There are no data on the presence of futibatinib or its metabolites in human milk or their effects on either the breastfed child or on milk production. Because of the potential for serious adverse reactions from LYTGOBI in breastfed children, advise women not to breastfeed during treatment and for 1 week after the last dose.
8.3Females and Males of Reproductive Potential LYTGOBI can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Pregnancy Testing Verify pregnancy status of females of reproductive potential prior to initiating LYTGOBI [see Use in Specific Populations (8.1) ] . Contraception Females Advise females of reproductive potential to use effective contraception during treatment with LYTGOBI and for 1 week after the last dose.
Males Advise males with female partners of reproductive potential or who are pregnant to use effective contraception during treatment with LYTGOBI and for 1 week after the last dose.
8.4Pediatric Use The safety and effectiveness of LYTGOBI have not been established in pediatric patients. Animal Toxicity Data In 4- or 13-week repeat-dose toxicology studies in adult rats and dogs, findings included increased inorganic phosphorus and calcium in plasma, ectopic mineralization in various organs and tissues, and lesions in bone/cartilage at futibatinib exposures lower than the human exposure at the clinical dose of 20 mg. Findings in rats also included corneal lesions.
Evidence of recovery in rats and dogs was observed four weeks after cessation of dosing except for the ectopic mineralization.
8.5Geriatric Use Of the 103 patients treated with LYTGOBI in Study TAS-120-101, 22% were 65 years or older. Based on available data, no overall differences in safety or effectiveness of LYTGOBI have been observed between patients 65 years of age and older and younger adult patients.
8.7Hepatic Impairment There are limited data in patients treated with LYTGOBI with total bilirubin >1.5🞨 ULN, and patients with cholangiocarcinoma with total bilirubin >3🞨 ULN were excluded from enrollment in clinical trials. Patients with cirrhosis and total bilirubin >1.5🞨 ULN to 3🞨 ULN may have the potential for increased adverse reactions compared to patients with normal hepatic function due to higher unbound futibatinib exposure [see Clinical Pharmacology (12.3) ] .
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings in an animal study and its mechanism of action, LYTGOBI can cause fetal harm or loss of pregnancy when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data on the use of LYTGOBI in pregnant women. Oral administration of futibatinib to pregnant rats during the period of organogenesis at maternal plasma exposures below the human exposure at the clinical dose of 20 mg resulted in fetal malformations, fetal growth retardation, and embryo-fetal death ( see Data ).
Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Once daily oral administration of futibatinib to pregnant rats during the period of organogenesis resulted in 100% embryofetal mortality due to post-implantation loss at doses ≥10 mg/kg (approximately 5 times the recommended clinical dose of 20 mg based on body surface area, BSA).
Fetal survival was unaffected at 0.5 mg/kg per day; however, once daily oral administration of futibatinib at the 0.5 mg/kg dose level (approximately 0.2 times the recommended clinical dose of 20 mg based on BSA) resulted in reduced mean fetal body weight and an increase in fetal skeletal and visceral malformations, major blood vessel variations, and reduced ossification.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of LYTGOBI have not been established in pediatric patients. Animal Toxicity Data In 4- or 13-week repeat-dose toxicology studies in adult rats and dogs, findings included increased inorganic phosphorus and calcium in plasma, ectopic mineralization in various organs and tissues, and lesions in bone/cartilage at futibatinib exposures lower than the human exposure at the clinical dose of 20 mg. Findings in rats also included corneal lesions.
Evidence of recovery in rats and dogs was observed four weeks after cessation of dosing except for the ectopic mineralization.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 103 patients treated with LYTGOBI in Study TAS-120-101, 22% were 65 years or older. Based on available data, no overall differences in safety or effectiveness of LYTGOBI have been observed between patients 65 years of age and older and younger adult patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Futibatinib is a small molecule kinase inhibitor of FGFR 1, 2, 3, and 4 with IC 50 values of less than 4 nM. Futibatinib covalently binds FGFR. Constitutive FGFR signaling can support the proliferation and survival of malignant cells.
Futibatinib inhibited FGFR phosphorylation and downstream signaling and decreased cell viability in cancer cell lines with FGFR alterations including FGFR fusions/rearrangements, amplifications, and mutations. Futibatinib demonstrated anti-tumor activity in mouse and rat xenograft models of human tumors with activating FGFR genetic alterations.
12.2Pharmacodynamics Serum Phosphate Futibatinib increased serum phosphate levels due to FGFR inhibition. Serum phosphate increased with increasing futibatinib exposure across the dose range of 4 to 24 mg orally once daily (0.2 to 1.2 times the recommended dose), with increased risk of hyperphosphatemia at higher futibatinib exposure. Cardiac Electrophysiology At four times the approved recommended dose, LYTGOBI does not cause clinically significant QTc interval prolongation.
12.3Pharmacokinetics The pharmacokinetics of futibatinib were observed at steady state in patients with advanced solid tumors unless otherwise specified at the approved recommended dosage and are presented as mean (%CV) unless otherwise specified. Futibatinib maximum concentration (C max ) is 144 mg/mL (50%) and systemic exposure (AUC) is 790 ng∙hr/mL (45%). Futibatinib exposure (AUC) increased in dose proportional manner over the dose range from 4 to 24 mg orally once daily (0.2 to 1.2 times the approved recommended dosage).
No accumulation is observed at steady state. Absorption Futibatinib median (min, max) time to maximum plasma concentration (T max ) is 2 hours (1.2, 23 hours). Effect of Food Futibatinib C max decreased by 42% with no clinically significant differences in AUC in healthy subjects following administration of LYTGOBI with a high-fat and high-calorie meal (900 to 1000 calories with approximately 50% from fat).
Distribution The apparent (oral) volume of distribution is 66 L (18%). Futibatinib plasma protein binding is 95%, primarily to albumin and α1-acid glycoprotein. Elimination Futibatinib elimination half-life is 2.9 hours (27%) with an apparent (oral) clearance of 20 L/hr (23%).
Metabolism Futibatinib is primarily metabolized by CYP3A and to a lesser extent by CYP2C9 and CYP2D6. Unchanged futibatinib accounts for 59% of radioactivity in plasma in healthy subjects. Excretion Following a single oral dose of radiolabeled futibatinib 20 mg, approximately 91% of the dose was recovered in feces and 9% in urine.
Specific Populations No clinically significant differences in the pharmacokinetics of futibatinib were observed based on age (18 to 82 years), sex, race (White, Asian, and African American), body weight (36 to 152 kg), or creatinine clearance (CLcr) 30 to 89 mL/min (estimated by Cockcroft-Gault). The effect of CLcr of 15 to 29 mL/min or renal dialysis in end-stage renal disease (CLcr <15 mL/min) on futibatinib pharmacokinetics is unknown. Patients with Hepatic Impairment No clinically significant differences in the pharmacokinetics of futibatinib were observed in subjects with mild hepatic impairment (total bilirubin ≤ ULN and AST > ULN or total bilirubin >1 to 1.5🞨 ULN and any AST or Child-Pugh A) or moderate to severe hepatic impairment (Child-Pugh B to C) with total bilirubin < 1.5 🞨 ULN.
The effect of moderate to severe hepatic impairment without cirrhosis on futibatinib pharmacokinetics is unknown. In subjects with cirrhosis and total bilirubin >1 to 1.5🞨 ULN, mean unbound futibatinib AUC and C max increased by 1.7-fold relative to subjects with normal hepatic function. In subjects with cirrhosis and total bilirubin >1.5🞨 ULN, mean unbound futibatinib AUC and C max increased by 3.2-fold and 2.4-fold, respectively, compared to values in healthy subjects.
Drug Interaction Studies Clinical Studies Strong CYP3…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Futibatinib is a small molecule kinase inhibitor of FGFR 1, 2, 3, and 4 with IC 50 values of less than 4 nM. Futibatinib covalently binds FGFR. Constitutive FGFR signaling can support the proliferation and survival of malignant cells.
Futibatinib inhibited FGFR phosphorylation and downstream signaling and decreased cell viability in cancer cell lines with FGFR alterations including FGFR fusions/rearrangements, amplifications, and mutations. Futibatinib demonstrated anti-tumor activity in mouse and rat xenograft models of human tumors with activating FGFR genetic alterations.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING LYTGOBI tablets are round, white, and film-coated. The 4 mg tablets are debossed with “4MG” on one side, and “FBN” on the other side. The 16 mg tablets are debossed with “16MG” on one side, and “FBN” on the other.
Tablets are packaged in blister cards and supplied in child-resistant DosePak ® as follows: 20 mg daily dose: Each carton contains 1 blister card containing a 7-day supply (35 tablets; 4 mg futibatinib per tablet). [NDC-64842-0120-6] 20 mg daily dose: Each carton contains 1 blister card containing a 7-day supply (14 tablets; 7 tablets each of 4 mg and 16 mg futibatinib per tablet). [NDC-64842-0128-8] 16 mg daily dose: Each carton contains 1 blister card containing a 7-day supply (28 tablets; 4 mg futibatinib per tablet). [NDC-64842-0120-5] 16 mg daily dose: Each carton contains 1 blister card containing a 7-day supply (7 tablets; 16 mg futibatinib per tablet). [NDC-64842-0127-7] 12 mg daily dose: Each carton contains 1 blister card containing a 7-day supply (21 tablets; 4 mg futibatinib per tablet). [NDC-64842-0120-4] Store LYTGOBI tablets at room temperature 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F to 86°F).
([see USP Controlled Room Temperature]).
📋 Description ▾
11 DESCRIPTION Futibatinib is a kinase inhibitor with the chemical name 1-[(3 S )-3-{4-amino-3-[(3,5-dimethoxyphenyl)ethynyl]- 1 H -pyrazolo[3,4- d ]pyrimidin-1-yl}pyrrolidin-1-yl]prop-2-en-1-one. Futibatinib has a molecular formula of C 22 H 22 N 6 O 3 and molecular mass of 418.45 g/mole. Futibatinib has the following chemical structure: Futibatinib is a white crystalline powder.
The solubility of futibatinib is pH dependent with decreasing solubility with increasing pH, being practically insoluble at pH 3 or higher. Futibatinib is insoluble in water and poorly soluble in common solvents. LYTGOBI is supplied as 4 mg and 16 mg film-coated tablets for oral administration.
Each tablet contains inactive ingredients of corn starch, crospovidone, hydroxypropyl cellulose, lactose monohydrate, magnesium stearate, mannitol, microcrystalline cellulose, and sodium lauryl sulfate. The film coating material contains hypromellose, magnesium stearate, polyethylene glycol, and titanium dioxide. Futibatinib Str
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Ocular Toxicity Advise patients that LYTGOBI may cause ocular toxicity including RPED and to immediately inform their healthcare provider if they experience any visual changes [see Warnings and Precautions (5.1) ] . Advise patients to use artificial tears, or hydrating or lubricating eye gels to prevent or treat dry eyes [see Warnings and Precautions (5.1) ] .
Hyperphosphatemia and Soft Tissue Mineralization Inform patients that LYTGOBI may cause hyperphosphatemia and soft tissue mineralization and to immediately inform their healthcare provider of any symptoms related to acute change in phosphate levels such as muscle cramps, numbness, or tingling around the mouth [see Warnings and Precautions 5.2) ] . Nail Disorders Advise patients that LYTGOBI may cause nail disorders [see Adverse Reactions (6.1) ]. Embryo-Fetal Toxicity Advise females to inform their healthcare provider if they are pregnant or become pregnant.
Inform female patients of the risk to a fetus and potential loss of pregnancy [see Warnings and Precautions (5.3) and Use in Specific Populations (8.1) ]. Advise females of reproductive potential to use effective contraception while on LYTGOBI and for 1 week after the last dose [see Use in Specific Populations (8.3) ]. Advise males with female partners of reproductive potential or who are pregnant to use effective contraception during treatment and for 1 week after receiving the last dose of LYTGOBI [see Use in Specific Populations (8.3) ].
Lactation Advise patients not to breastfeed during treatment with LYTGOBI and for 1 week after the last dose [see Use in Specific Populations (8.2) ] . Administration Instruct patients to not crush, chew, split or dissolve tablets. Instruct patients if they miss a dose by 12 or more hours or if they vomit after taking a dose, resume dosing with the next scheduled dose.
Extra tablets should not be taken to make up for the missed dose [see Dosage and Administration (2.2) ]. Drug Interactions Advise patients to inform their healthcare providers of all concomitant medications, including prescription medicines, over-the-counter drugs, and herbal products. Advise patients to avoid grapefruit products during treatment with LYTGOBI [see Drug Interactions (7.1) ] .