
glyburide 5 mg Tablet, 1,000-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Sulfonylurea class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Great question. Diet and exercise are the foundation of managing type 2 diabetes, but sometimes they aren't enough on their own. Glyburide gives your pancreas a nudge to release mo...
- What exactly does glyburide do — and why do I need it if I'm already watching my diet?
- Low blood sugar — called hypoglycemia — is the main risk with glyburide. Watch for shakiness, sweating, sudden hunger, dizziness, confusion, or a fast heartbeat. If you catch it ea...
- How do I know if my blood sugar is going too low, and what should I do?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Glyburide — tap one for details:
Glyburide may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H0G9379FGK
Calcium carbonate is a white mineral powder used as a filler and buffering agent in medicines. It helps give tablets their bulk and size while neutralizing stomach acid in some formulations.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII O7TSZ97GEP
A mineral compound that serves as a filler and binding agent in tablets and capsules. It adds bulk to the medicine and helps hold ingredients together during manufacturing.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1224 | $122.40 / 1000 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Glyburide 5 mg 00093-8344-01 | Teva | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Glyburide 5 mg 00093-9364-01 | TEVA | 100 tablets | $0.064 | AB2 | Availability likely | — |
| Glyburide 5 mg 23155-0058-01 | Heritage | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Glyburide 5 mg 62135-0585-90 | Chartwell | 90 tablets | $0.064 | AB1 | Availability likely | — |
| Glyburide 5 mg 72241-0040-05 | Modavar | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Glyburide 5 mg 75834-0204-00 | Nivagen | 1000 tablets | $0.070 | AB1 | Discontinued | — |
| Glyburide 5 mg 50090-0495-00 | A-S | 30 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 50090-6196-00 | A-S | 30 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 50090-6607-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 50090-7859-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 51655-0492-25 | Northwind | 60 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 63187-0667-30 | Proficient | 30 tablets | — | AB1 | FDA listed | — |
| glyburide 5 mgthis 65841-0834-10 | Zydus | 1000 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 66267-0103-30 | NuCare | 30 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 68071-3452-03 | NuCare | 30 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 68071-3677-00 | NuCare | 100 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 68071-3702-06 | NuCare | 60 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 68071-4695-03 | NuCare | 30 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 68071-5030-00 | NuCare | 100 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 68071-5215-00 | NuCare | 100 tablets | — | AB1 | FDA listed | — |
| glyburide 5 mg 68382-0658-01 | Zydus | 100 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 68788-4073-01 | Preferred | 100 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 68788-8508-01 | Preferred | 100 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 70518-4035-00 | REMEDYREPACK | 30 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 71209-0011-05 | Cadila | 100 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 71335-0150-01 | Bryant | 30 tablets | — | AB1 | Discontinued | — |
| Glyburide 5 mg 71335-2771-01 | Bryant | 30 tablets | — | AB1 | FDA listed | — |
| Glyburide 5 mg 82804-0150-00 | Proficient | 100 tablets | — | AB1 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 65841-0834-01 | 100 TABLET in 1 BOTTLE (65841-834-01) | 2016-06-02 | Active |
| 65841-0834-05 | 500 TABLET in 1 BOTTLE (65841-834-05) | 2016-06-02 | Active |
| 65841-0834-06 | 30 TABLET in 1 BOTTLE (65841-834-06) | 2016-06-02 | Active |
| 65841-0834-10 You're viewing this | 1000 TABLET in 1 BOTTLE (65841-834-10) | 2016-06-02 | Active |
| 65841-0834-16 | 90 TABLET in 1 BOTTLE (65841-834-16) | 2016-06-02 | Active |
| 65841-0834-77 | 10 BLISTER PACK in 1 CARTON (65841-834-77) / 10 TABLET in 1 BLISTER PACK (65841-834-30) | 2016-06-02 | Active |
Pack size FAQ
What quantity is in NDC 65841-0834-10?
What is the difference between NDC 65841-0834-10 and NDC 65841-0834-06?
What NDC number is used to bill for this package of glyburide 5 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Glyburide tablets, USP are indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Patients should be retitrated when transferred from glyburide (micronized) tablets or other oral hypoglycemic agents (see PRECAUTIONS ). There is no fixed dosage regimen for the management of diabetes mellitus with glyburide tablets or any other hypoglycemic agent. In addition to the usual monitoring of urinary glucose, the patient's blood glucose must also be monitored periodically to determine the minimum effective dose for the patient; to detect primary failure, i.e. , inadequate lowering of blood glucose at the maximum recommended dose of medication; and to detect secondary failure, i.e. , loss of adequate blood glucose lowering response after an initial period of effectiveness.
Glycosylated hemoglobin levels may also be of value in monitoring the patient's response to therapy. Short-term administration of glyburide tablets may be sufficient during periods of transient loss of control in patients usually controlled well on diet. Usual Starting Dose The usual starting dose of glyburide tablets is 2.5 to 5 mg daily, administered with breakfast or the first main meal.
Those patients who may be more sensitive to hypoglycemic drugs should be started at 1.25 mg daily. (See PRECAUTIONS section for patients at increased risk.) Failure to follow an appropriate dosage regimen may precipitate hypoglycemia. Patients who do not adhere to their prescribed dietary and drug regimen are more prone to exhibit unsatisfactory response to therapy.
Transfer From Other Hypoglycemic Therapy Patients Receiving Other Oral Antidiabetic Therapy Transfer of patients from other oral antidiabetic regimens to glyburide tablets should be done conservatively and the initial daily dose should be 2.5 to 5 mg. When transferring patients from oral hypoglycemic agents other than chlorpropamide to glyburide tablets, no transition period and no initial or priming dose are necessary. When transferring patients from chlorpropamide, particular care should be exercised during the first two weeks because the prolonged retention of chlorpropamide in the body and subsequent overlapping drug effects may provoke hypoglycemia.
Patients Receiving Insulin Some Type II diabetic patients being treated with insulin may respond satisfactorily to glyburide tablets. If the insulin dose is less than 20 units daily, substitution of glyburide tablets 2.5 to 5 mg as a single daily dose may be tried. If the insulin dose is between 20 and 40 units daily, the patient may be placed directly on glyburide tablets 5 mg daily as a single dose.
If the insulin dose is more than 40 units daily, a transition period is required for conversion to glyburide tablets. In these patients, insulin dosage is decreased by 50% and glyburide tablets 5 mg daily is started. Please refer to Titration to Maintenance Dose for further explanation.
Patients Receiving Colesevelam When colesevelam is coadministered with glyburide, maximum plasma concentration and total exposure to glyburide is reduced. Therefore, glyburide tablets should be administered at least 4 hours prior to colesevelam. Titration to Maintenance Dose The usual maintenance dose is in the range of 1.25 to 20 mg daily, which may be given as a single dose or in divided doses (see Dosage Interval ).
Dosage increases should be made in increments of no more than 2.5 mg at weekly intervals based upon the patient's blood glucose response. No exact dosage relationship exists between glyburide tablets and the other oral hypoglycemic agents. Although patients may be transferred from the maximum dose of other sulfonylureas, the maximum starting dose of 5 mg of glyburide tablets should be observed.
A maintenance dose of 5 mg of glyburide tablets provides approximately the same degree of blood glucose control as 250 to 375 mg chlorpropamide, 250 to 375 mg tolazamide, 500 to 750 mg acetohexamide, or 1000 to 1500 mg tolbutamide. When transferring patients receiving more than 40 units of insulin daily, they may be started on a daily dose…
⛔ Contraindications ▾
CONTRAINDICATIONS Glyburide tablets are contraindicated in patients with: Known hypersensitivity or allergy to the drug. Diabetic ketoacidosis, with or without coma. This condition should be treated with insulin. Type I diabetes mellitus. Concomitant administration of bosentan.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Hypoglycemia: See PRECAUTIONS and OVERDOSAGE . Gastrointestinal Reactions: Cholestatic jaundice and hepatitis may occur rarely which may progress to liver failure; glyburide tablets should be discontinued if this occurs. Liver function abnormalities, including isolated transaminase elevations, have been reported.
Gastrointestinal disturbances, e.g. , nausea, epigastric fullness, and heartburn are the most common reactions, having occurred in 1.8% of treated patients during clinical trials. They tend to be dose related and may disappear when dosage is reduced. Dermatologic Reactions: Allergic skin reactions, e.g. , pruritus, erythema, urticaria, and morbilliform or maculopapular eruptions occurred in 1.5% of treated patients during clinical trials.
These may be transient and may disappear despite continued use of glyburide; if skin reactions persist, the drug should be discontinued. Porphyria cutanea tarda and photosensitivity reactions have been reported with sulfonylureas. Hematologic Reactions: Leukopenia, agranulocytosis, thrombocytopenia, hemolytic anemia (see PRECAUTIONS ), aplastic anemia, and pancytopenia have been reported with sulfonylureas.
Metabolic Reactions: Hepatic porphyria and disulfiram-like reactions have been reported with sulfonylureas; however, hepatic porphyria has not been reported with glyburide and disulfiram-like reactions have been reported very rarely. Cases of hyponatremia have been reported with glyburide and all other sulfonylureas, most often in patients who are on other medications or have medical conditions known to cause hyponatremia or increase release of antidiuretic hormone. The syndrome of inappropriate antidiuretic hormone (SIADH) secretion has been reported with certain other sulfonylureas, and it has been suggested that these sulfonylureas may augment the peripheral (antidiuretic) action of ADH and/or increase release of ADH.
Other Reactions: Changes in accommodation and/or blurred vision have been reported with glyburide and other sulfonylureas. These are thought to be related to fluctuation in glucose levels. In addition to dermatologic reactions, allergic reactions such as angioedema, arthralgia, myalgia and vasculitis have been reported.
🔄 Drug Interactions ▾
Drug Interactions The hypoglycemic action of sulfonylureas may be potentiated by certain drugs including non-steroidal anti-inflammatory agents and other drugs that are highly protein bound, salicylates, sulfonamides, chloramphenicol, probenecid, coumarins, monoamine oxidase inhibitors, and beta adrenergic blocking agents. When such drugs are administered to a patient receiving glyburide, the patient should be observed closely for hypoglycemia. When such drugs are withdrawn from a patient receiving glyburide, the patient should be observed closely for loss of control.
An increased risk of liver enzyme elevations was observed in patients receiving glyburide concomitantly with bosentan. Therefore concomitant administration of glyburide tablets and bosentan is contraindicated. Certain drugs tend to produce hyperglycemia and may lead to loss of control.
These drugs include the thiazides and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics, calcium channel blocking drugs, and isoniazid. When such drugs are administered to a patient receiving glyburide, the patient should be closely observed for loss of control. When such drugs are withdrawn from a patient receiving glyburide, the patient should be observed closely for hypoglycemia.
A possible interaction between glyburide and ciprofloxacin, a fluoroquinolone antibiotic, has been reported, resulting in a potentiation of the hypoglycemic action of glyburide. The mechanism for this interaction is not known. A potential interaction between oral miconazole and oral hypoglycemic agents leading to severe hypoglycemia has been reported.
Whether this interaction also occurs with the intravenous, topical or vaginal preparations of miconazole is not known. Metformin In a single-dose interaction study in NIDDM subjects, decreases in glyburide AUC and C max were observed, but were highly variable. The single-dose nature of this study and the lack of correlation between glyburide blood levels and pharmacodynamic effects, makes the clinical significance of this interaction uncertain.
Coadministration of glyburide and metformin did not result in any changes in either metformin pharmacokinetics or pharmacodynamics. Colesevelam Concomitant administration of colesevelam and glyburide resulted in reductions in glyburide AUC and C max of 32% and 47%, respectively. The reductions in glyburide AUC and C max were 20% and 15%, respectively when administered 1 hour before, and not significantly changed (-7% and 4%, respectively) when administered 4 hours before colesevelam.
Topiramate A drug-drug interaction study conducted in patients with type 2 diabetes evaluated the steady-state pharmacokinetics of glyburide (5 mg/day) alone and concomitantly with topiramate (150 mg/day). There was a 22% decrease in C max and a 25% reduction in AUC 24 for glyburide during topiramate administration. Systemic exposure (AUC) of the active metabolites, 4-trans-hydroxy-glyburide (M1) and 3-cishydroxyglyburide (M2), was also reduced by 13% and 15%, and C max was reduced by 18% and 25%, respectively.
The steady-state pharmacokinetics of topiramate were unaffected by concomitant administration of glyburide.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Pregnancy category B Reproduction studies have been performed in rats and rabbits at doses up to 500 times the human dose and have revealed no evidence of impaired fertility or harm to the fetus due to glyburide. There are, however, no adequate and well controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
Because recent information suggests that abnormal blood glucose levels during pregnancy are associated with a higher incidence of congenital abnormalities, many experts recommend that insulin be used during pregnancy to maintain blood glucose as close to normal as possible. Nonteratogenic Effects Prolonged severe hypoglycemia (4 to 10 days) has been reported in neonates born to mothers who were receiving a sulfonylurea drug at the time of delivery. This has been reported more frequently with the use of agents with prolonged half-lives.
If glyburide is used during pregnancy, it should be discontinued at least two weeks before the expected delivery date.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use Elderly patients are particularly susceptible to the hypoglycemic action of glucose lowering drugs. Hypoglycemia may be difficult to recognize in the elderly (see PRECAUTIONS ). The initial and maintenance dosing should be conservative to avoid hypoglycemic reactions (see DOSAGE AND ADMINISTRATION ).
Elderly patients are prone to develop renal insufficiency, which may put them at risk of hypoglycemia. Dose selection should include assessment of renal function.
🆘 Overdosage ▾
OVERDOSAGE Overdosage of sulfonylureas, including glyburide tablets, can produce hypoglycemia. Mild hypoglycemic symptoms, without loss of consciousness or neurological findings, should be treated aggressively with oral glucose and adjustments in drug dosage and/or meal patterns. Close monitoring should continue until the physician is assured that the patient is out of danger.
Severe hypoglycemic reactions with coma, seizure, or other neurological impairment occur infrequently, but constitute medical emergencies requiring immediate hospitalization. If hypoglycemic coma is diagnosed or suspected, the patient should be given a rapid intravenous injection of concentrated (50%) glucose solution. This should be followed by a continuous infusion of a more dilute (10%) glucose solution at a rate which will maintain the blood glucose at a level above 100 mg/dL.
Patients should be closely monitored for a minimum of 24 to 48 hours, since hypoglycemia may recur after apparent clinical recovery.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Actions Glyburide appears to lower the blood glucose acutely by stimulating the release of insulin from the pancreas, an effect dependent upon functioning beta cells in the pancreatic islets. The mechanism by which glyburide lowers blood glucose during long-term administration has not been clearly established. With chronic administration in Type II diabetic patients, the blood glucose lowering effect persists despite a gradual decline in the insulin secretory response to the drug.
Extrapancreatic effects may be involved in the mechanism of action of oral sulfonylurea hypoglycemic drugs. The combination of glyburide and metformin may have a synergistic effect, since both agents act to improve glucose tolerance by different but complementary mechanisms. Some patients who are initially responsive to oral hypoglycemic drugs, including glyburide, may become unresponsive or poorly responsive over time.
Alternatively, glyburide tablets may be effective in some patients who have become unresponsive to one or more other sulfonylurea drugs. In addition to its blood glucose lowering actions, glyburide produces a mild diuresis by enhancement of renal free water clearance. Disulfiram-like reactions have very rarely been reported in patients treated with glyburide tablets.
Pharmacokinetics Single dose studies with glyburide tablets in normal subjects demonstrate significant absorption of glyburide within one hour, peak drug levels at about four hours, and low but detectable levels at twenty-four hours. Mean serum levels of glyburide, as reflected by areas under the serum concentration-time curve, increase in proportion to corresponding increases in dose. Multiple dose studies with glyburide in diabetic patients demonstrate drug level concentration-time curves similar to single dose studies, indicating no buildup of drug in tissue depots.
The decrease of glyburide in the serum of normal healthy individuals is biphasic; the terminal half-life is about 10 hours. In single dose studies in fasting normal subjects, the degree and duration of blood glucose lowering is proportional to the dose administered and to the area under the drug level concentration-time curve. The blood glucose lowering effect persists for 24 hours following single morning doses in nonfasting diabetic patients.
Under conditions of repeated administration in diabetic patients, however, there is no reliable correlation between blood drug levels and fasting blood glucose levels. A one year study of diabetic patients treated with glyburide showed no reliable correlation between administered dose and serum drug level. The major metabolite of glyburide is the 4-trans-hydroxy derivative.
A second metabolite, the 3-cis-hydroxy derivative, also occurs. These metabolites probably contribute no significant hypoglycemic action in humans since they are only weakly active (1/400 th and 1/40 th as active, respectively, as glyburide) in rabbits. Glyburide is excreted as metabolites in the bile and urine, approximately 50% by each route.
This dual excretory pathway is qualitatively different from that of other sulfonylureas, which are excreted primarily in the urine. Sulfonylurea drugs are extensively bound to serum proteins. Displacement from protein binding sites by other drugs may lead to enhanced hypoglycemic action.
In vitro , the protein binding exhibited by glyburide is predominantly non-ionic, whereas that of other sulfonylureas (chlorpropamide, tolbutamide, tolazamide) is predominantly ionic. Acidic drugs such as phenylbutazone, warfarin, and salicylates displace the ionic-binding sulfonylureas from serum proteins to a far greater extent than the non-ionic binding glyburide. It has not been shown that this difference in protein binding will result in fewer drug-drug interactions with glyburide tablets in clinical use.
📦 How Supplied / Storage and Handling ▾
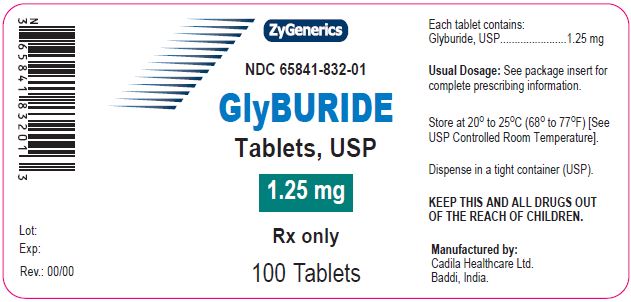
HOW SUPPLIED Glyburide Tablets USP, 1.25 mg are white to off-white colored, round shaped, biconvex, uncoated tablets debossed with '656' on one side and breakline on the other side and are supplied as follows: NDC 65841-832-06 in bottles of 30 tablets NDC 65841-832-16 in bottles of 90 tablets NDC 65841-832-01 in bottles of 100 tablets NDC 65841-832-05 in bottles of 500 tablets NDC 65841-832-10 in bottles of 1000 tablets NDC 65841-832-77 in unit-dose blister cartons of 100 (10 x 10) unit-dose tablets Glyburide Tablets USP, 2.5 mg are light yellow to yellow colored, may be spotted, round shaped, biconvex, uncoated tablets, debossed with "657" on one side and breakline on the other side and are supplied as follows: NDC 65841-833-06 in bottles of 30 tablets NDC 65841-833-16 in bottles of 90 tablets NDC 65841-833-01 in bottles of 100 tablets NDC 65841-833-05 in bottles of 500 tablets NDC 65841-833-10 in bottles of 1000 tablets NDC 65841-833-77 in unit-dose blister cartons of 100 (10 x 10) unit-dose tablets Glyburide Tablets USP, 5 mg are light green colored, may be spotted, round shaped, biconvex, uncoated tablets, debossed with "658" on one side and breakline on the other side and are supplied as follows: NDC 65841-834-06 in bottles of 30 tablets NDC 65841-834-16 in bottles of 90 tablets NDC 65841-834-01 in bottles of 100 tablets NDC 65841-834-05 in bottles of 500 tablets NDC 65841-834-10 in bottles of 1000 tablets NDC 65841-834-77 in unit-dose blister cartons of 100 (10 x 10) unit-dose tablets Storage Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature] .
Dispense in a tight container (USP). KEEP THIS AND ALL DRUGS OUT OF THE REACH OF CHILDREN. Call your doctor for medical advice about side effects.
You may report side effects to FDA at 1-800-FDA-1088. Manufactured by: Cadila Healthcare Ltd. Baddi, India
📋 Description ▾
DESCRIPTION Glyburide tablets USP contain glyburide, USP, which is an oral blood-glucose-lowering drug of the sulfonylurea class. Glyburide, USP is a white or almost white, crystalline powder. The chemical name for Glyburide, USP is 1-[[p-[2-(5-chloro-o-anisamido)ethyl]phenyl]-sulfonyl]-3-cyclohexylurea.
It has the following structural formula: C 23 H 28 ClN 3 O 5 S M.W. 494.0 Each glyburide tablet, USP intended for oral administration contains 1.25 mg or 2.5 mg or 5 mg of Glyburide, USP. In addition, each tablet contains the following inactive ingredients: calcium carbonate, dibasic calcium phosphate dihydrate, magnesium stearate, microcrystalline cellulose, povidone, pregelatinized starch and sodium starch glycolate.
Additionally each 2.5 mg tablet contains D&C yellow # 10 aluminum lake and FD & C yellow # 6 aluminum lake; each 5 mg tablet contains D&C yellow # 10 aluminum lake and FD & C blue # 1 aluminum lake. figure
💬 Information for Patients ▾
Information for Patients Patients should be informed of the potential risks and advantages of glyburide and of alternative modes of therapy. They also should be informed about the importance of adherence to dietary instructions, of a regular exercise program, and of regular testing of urine and/or blood glucose. The risks of hypoglycemia, its symptoms and treatment, and conditions that predispose to its development should be explained to patients and responsible family members.
Primary and secondary failure also should be explained.