
Cefprozil 125 mg/5mL Powder, For Suspension, 75 mL — NDC 65862-099-75 (Billing 65862-0099-75)
This is a package of 75 mL of Cefprozil 125 mg/5mL Powder, For Suspension from Aurobindo Pharma Limited, marketed since Jan 2007 and currently FDA-listed.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 016582
- GCN: 29291
- GPI-14 (Medi-Span): 02200062001910
- HICL (First Databank): 006316
- AHFS class code: 08:12.06.08
- RxCUI (RxNorm): 309080
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Cephalosporin Antibacterial class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It’s an antibiotic for mild to moderate bacterial infections of the throat, ears, sinuses, bronchitis and skin. It won’t help colds or flu, which are viral.
- Take it by mouth, as a tablet or a liquid, once or twice a day as prescribed. Most courses run about 10 days. Strep infections need at least 10 days. Food doesn’t change how much y...
- The most common are nausea, diarrhea, vomiting and belly pain. Most people tolerate it well.
- Call right away for signs of a severe allergic reaction, and stop the drug. Also call for severe or lasting diarrhea, even weeks after you finish.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cefprozil — tap one for details:
Cefprozil may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1951 | $14.63 / 75 ml |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 65862-0099-01 65862-099-01 Main listing | 100 mL in 1 BOTTLE | $0.1011 / mL | $10.11 | 2007-01-30 | — | Active |
| 65862-0099-50 65862-099-50 | 50 mL in 1 BOTTLE | — | — | 2007-01-30 | — | Active |
| 65862-0099-75 You're viewing this | 75 mL in 1 BOTTLE | — | — | 2007-01-30 | — | Active |
You're viewing one of 3 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 65862-0099-50?
What NDC number is used to bill for this package of Cefprozil 125 mg/5mL Powder, For Suspension?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cefprozil 125 mg/5mL 57237-0034-01 | Rising | 100 ml | $0.105 | AB | Availability likely | — |
| Cefprozil 125 mg/5mL 16714-0396-01 | NorthStar | 50 ml | $0.236 | AB | Discontinued | — |
| Cefprozil 125 mg/5mL 68180-0401-01 | Lupin | 50 ml | $0.236 | AB | Discontinued | — |
| Cefprozil 125 mg/5mLthis 65862-0099-75 | Aurobindo | 75 ml | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII Z0H242BBR1
Aspartame is an artificial sweetener made from amino acids. It's added to medicines to improve taste, making bitter or unpleasant-tasting drugs easier to take.
-
UNII K679OBS311
Carboxymethylcellulose sodium is a plant-derived thickening agent made from cellulose. In medicines, it acts as a binder to hold ingredients together, a disintegrant to help the tablet break apart, or a thickener in liquids.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII 92RU3N3Y1O
Dimethicone is a silicone-based oil that acts as an anti-foaming agent and lubricant in medicines. It reduces gas bubbles in liquid formulations and helps coat and protect the stomach lining when ingested.
-
UNII PN2ZH5LOQY
A synthetic red dye approved by the FDA for use in foods, medicines, and cosmetics. It serves as a colorant to make tablets, capsules, and liquids visually distinctive for product identification.
-
UNII TE7660XO1C
Glycine is an amino acid used in medicines as a buffer to help stabilize pH and improve taste. It may also serve as a filler or binder to give the product proper form and consistency.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII OJ245FE5EU
Sodium benzoate is a salt derived from benzoic acid, a preservative. It's added to medicines to prevent growth of bacteria, fungi, and other microorganisms that could spoil the product.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE To reduce the development of drug-resistant bacteria and maintain the effectiveness of cefprozil and other antibacterial drugs, cefprozil should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
Cefprozil for oral suspension is indicated for the treatment of patients with mild to moderate infections caused by susceptible strains of the designated microorganisms in the conditions listed below: UPPER RESPIRATORY TRACT Pharyngitis/tonsillitis caused by Streptococcus pyogenes . NOTE: The usual drug of choice in the treatment and prevention of streptococcal infections, including the prophylaxis of rheumatic fever, is penicillin given by the intramuscular route. Cefprozil is generally effective in the eradication of Streptococcus pyogenes from the nasopharynx; however, substantial data establishing the efficacy of cefprozil in the subsequent prevention of rheumatic fever are not available at present.
Otitis Media caused by Streptococcus pneumoniae , Haemophilus influenzae (including β-lactamase-producing strains), and Moraxella (Branhamella) catarrhalis (including β-lactamase-producing strains). (See CLINICAL STUDIES .) NOTE: In the treatment of otitis media due to β-lactamase producing organisms, cefprozil had bacteriologic eradication rates somewhat lower than those observed with a product containing a specific β-lactamase inhibitor. In considering the use of cefprozil, lower overall eradication rates should be balanced against the susceptibility patterns of the common microbes in a given geographic area and the increased potential for toxicity with products containing β-lactamase inhibitors.
Acute Sinusitis caused by Streptococcus pneumoniae , Haemophilus influenzae (including β-lactamase-producing strains), and Moraxella (Branhamella) catarrhalis (including β-lactamase-producing strains). LOWER RESPIRATORY TRACT Acute Bacterial Exacerbation of Chronic Bronchitis caused by Streptococcus pneumoniae , Haemophilus influenzae (including β-lactamase-producing strains), and Moraxella (Branhamella) catarrhalis (including β-lactamase-producing strains). SKIN AND SKIN STRUCTURE Uncomplicated Skin and Skin-Structure Infections caused by Staphylococcus aureus (including penicillinase-producing strains) and Streptococcus pyogenes .
Abscesses usually require surgical drainage.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Cefprozil for oral suspension is administered orally. Population/Infection Dosage (mg) Duration (days) a In the treatment of infections due to Streptococcus pyogenes , cefprozil should be administered for at least 10 days. b Not to exceed recommended adult doses. ADULTS (13 years and older) UPPER RESPIRATORY TRACT Pharyngitis/Tonsillitis 500 q24h 10 a Acute Sinusitis (For moderate to severe infections, the higher dose should be used) 250 q12h or 500 q12h 10 LOWER RESPIRATORY TRACT Acute Bacterial Exacerbation of Chronic Bronchitis 500 q12h 10 SKIN AND SKIN STRUCTURE Uncomplicated Skin and Skin Structure Infections 250 q12h or 500 q24h or 500 q12h 10 CHILDREN (2 years to 12 years) UPPER RESPIRATORY TRACT b Pharyngitis/Tonsillitis 7.5 mg/kg q12h 10 a SKIN AND SKIN STRUCTURE b Uncomplicated Skin and Skin Structure Infections 20 mg/kg q24h 10 INFANTS & CHILDREN (6 months to 12 years) UPPER RESPIRATORY TRACT b Otitis Media (See INDICATIONS AND USAGE and CLINICAL STUDIES ) 15 mg/kg q12h 10 Acute Sinusitis (For moderate to severe infections, the higher dose should be used) 7.5 mg/kg q12h or 15 mg/kg q12h 10 Renal Impairment Cefprozil may be administered to patients with impaired renal function.
The following dosage schedule should be used. Creatinine Clearance (mL/min) Dosage (mg) Dosing Interval * Cefprozil is in part removed by hemodialysis; therefore, cefprozil should be administered after the completion of hemodialysis. 30 to 120 0 to 29* standard 50% of standard standard standard Hepatic Impairment No dosage adjustment is necessary for patients with impaired hepatic function.
⛔ Contraindications ▾
CONTRAINDICATIONS Cefprozil for oral suspension is contraindicated in patients with known allergy to the cephalosporin class of antibiotics.
⚠️ Warnings ▾
WARNINGS BEFORE THERAPY WITH CEFPROZIL IS INSTITUTED, CAREFUL INQUIRY SHOULD BE MADE TO DETERMINE WHETHER THE PATIENT HAS HAD PREVIOUS HYPERSENSITIVITY REACTIONS TO CEFPROZIL, CEPHALOSPORINS, PENICILLINS, OR OTHER DRUGS. IF THIS PRODUCT IS TO BE GIVEN TO PENICILLIN-SENSITIVE PATIENTS, CAUTION SHOULD BE EXERCISED BECAUSE CROSS-SENSITIVITY AMONG β-LACTAM ANTIBIOTICS HAS BEEN CLEARLY DOCUMENTED AND MAY OCCUR IN UP TO 10% OF PATIENTS WITH A HISTORY OF PENICILLIN ALLERGY. IF AN ALLERGIC REACTION TO CEFPROZIL OCCURS, DISCONTINUE THE DRUG.
SERIOUS ACUTE HYPERSENSITIVITY REACTIONS MAY REQUIRE TREATMENT WITH EPINEPHRINE AND OTHER EMERGENCY MEASURES, INCLUDING OXYGEN, INTRAVENOUS FLUIDS, INTRAVENOUS ANTIHISTAMINES, CORTICOSTEROIDS, PRESSOR AMINES, AND AIRWAY MANAGEMENT, AS CLINICALLY INDICATED. Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including cefprozil, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile .
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin-producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibiotic use.
Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibiotic use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibiotic treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The adverse reactions to cefprozil are similar to those observed with other orally administered cephalosporins. Cefprozil was usually well tolerated in controlled clinical trials. Approximately 2% of patients discontinued cefprozil therapy due to adverse events.
The most common adverse effects observed in patients treated with cefprozil are: Gastrointestinal: Diarrhea (2.9%), nausea (3.5%), vomiting (1%), and abdominal pain (1%). Hepatobiliary: Elevations of AST (SGOT) (2%), ALT (SGPT) (2%), alkaline phosphatase (0.2%), and bilirubin values (<0.1%). As with some penicillins and some other cephalosporin antibiotics, cholestatic jaundice has been reported rarely.
Hypersensitivity: Rash (0.9%), urticaria (0.1%). Such reactions have been reported more frequently in children than in adults. Signs and symptoms usually occur a few days after initiation of therapy and subside within a few days after cessation of therapy.
CNS: Dizziness (1%), hyperactivity, headache, nervousness, insomnia, confusion, and somnolence have been reported rarely (<1%). All were reversible. Hematopoietic: Decreased leukocyte count (0.2%), eosinophilia (2.3%).
Renal: Elevated BUN (0.1%), serum creatinine (0.1%). Other: Diaper rash and superinfection (1.5%), genital pruritus and vaginitis (1.6%). The following adverse events, regardless of established causal relationship to cefprozil, have been rarely reported during postmarketing surveillance: anaphylaxis, angioedema, colitis (including pseudomembranous colitis), erythema multiforme, fever, serum-sickness like reactions, Stevens-Johnson syndrome, and thrombocytopenia.
Cephalosporin class paragraph In addition to the adverse reactions listed above which have been observed in patients treated with cefprozil, the following adverse reactions and altered laboratory tests have been reported for cephalosporin-class antibiotics: Aplastic anemia, hemolytic anemia, hemorrhage, renal dysfunction, toxic epidermal necrolysis, toxic nephropathy, prolonged prothrombin time, positive Coombs’ test, elevated LDH, pancytopenia, neutropenia, agranulocytosis. Several cephalosporins have been implicated in triggering seizures, particularly in patients with renal impairment, when the dosage was not reduced.
(See DOSAGE AND ADMINISTRATION and OVERDOSAGE .) If seizures associated with drug therapy occur, the drug should be discontinued. Anticonvulsant therapy can be given if clinically indicated.
🔄 Drug Interactions ▾
Drug Interactions Nephrotoxicity has been reported following concomitant administration of aminoglycoside antibiotics and cephalosporin antibiotics. Concomitant administration of probenecid doubled the AUC for cefprozil. The bioavailability of the capsule formulation of cefprozil was not affected when administered 5 minutes following an antacid.
🔄 Drug / Laboratory Test Interactions ▾
Drug/laboratory Test Interactions Cephalosporin antibiotics may produce a false positive reaction for glucose in the urine with copper reduction tests (Benedict’s or Fehling’s solution or with Clinitest ® tablets 1 ), but not with enzyme-based tests for glycosuria (e.g., Clinistix ® ). A false negative reaction may occur in the ferricyanide test for blood glucose. The presence of cefprozil in the blood does not interfere with the assay of plasma or urine creatinine by the alkaline picrate method.
1 Clinitest ® and Clinistix ® are registered trademarks of Bayer Healthcare LLC.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects: Pregnancy Category B Reproduction studies have been performed in rabbits, mice, and rats using oral doses of cefprozil of 0.8, 8.5, and 18.5 times the maximum daily human dose (1000 mg) based upon mg/m 2 , and have revealed no harm to the fetus. There are, however, no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use ( See INDICATIONS AND USAGE and DOSAGE AND ADMINISTRATION .) The safety and effectiveness of cefprozil in the treatment of otitis media have been established in the age groups 6 months to 12 years. Use of cefprozil for the treatment of otitis media is supported by evidence from adequate and well-controlled studies of cefprozil in pediatric patients. (See CLINICAL STUDIES .) The safety and effectiveness of cefprozil in the treatment of pharyngitis/tonsillitis or uncomplicated skin and skin-structure infections have been established in the age groups 2 to 12 years.
Use of cefprozil for the treatment of these infections is supported by evidence from adequate and well-controlled studies of cefprozil in pediatric patients. The safety and effectiveness of cefprozil in the treatment of acute sinusitis have been established in the age groups 6 months to 12 years. Use of cefprozil in these age groups is supported by evidence from adequate and well-controlled studies of cefprozil in adults.
Safety and effectiveness in pediatric patients below the age of 6 months have not been established for the treatment of otitis media or acute sinusitis, or below the age of 2 years for the treatment of pharyngitis/tonsillitis or uncomplicated skin and skin-structure infections. However, accumulation of other cephalosporin antibiotics in newborn infants (resulting from prolonged drug half-life in this age group) has been reported.
🧓 Geriatric Use ▾
Geriatric Use Of the more than 4500 adults treated with cefprozil in clinical studies, 14% were 65 years and older, while 5% were 75 years and older. When geriatric patients received the usual recommended adult doses, their clinical efficacy and safety were comparable to clinical efficacy and safety in nongeriatric adult patients. Other reported clinical experience has not identified differences in responses between elderly and younger patients, but greater sensitivity of some older individuals to the effects of cefprozil cannot be excluded (see CLINICAL PHARMACOLOGY ).
Cefprozil is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection and it may be useful to monitor renal function. See DOSAGE AND ADMINISTRATION for dosing recommendations for patients with impaired renal function.
🆘 Overdosage ▾
OVERDOSAGE Single 5000 mg/kg oral doses of cefprozil caused no mortality or signs of toxicity in adult, weanling, or neonatal rats, or adult mice. A single oral dose of 3000 mg/kg caused diarrhea and loss of appetite in cynomolgus monkeys, but no mortality. Cefprozil is eliminated primarily by the kidneys. In case of severe overdosage, especially in patients with compromised renal function, hemodialysis will aid in the removal of cefprozil from the body.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY The pharmacokinetic data were derived from the capsule formulation; however, bioequivalence has been demonstrated for the oral solution, capsule, tablet, and suspension formulations under fasting conditions. Following oral administration of cefprozil to fasting subjects, approximately 95% of the dose was absorbed. The average plasma half-life in normal subjects was 1.3 hours, while the steady-state volume of distribution was estimated to be
0.23L/kg. The total body clearance and renal clearance rates were approximately 3 mL/min/kg and 2.3 mL/min/kg, respectively. Average peak plasma concentrations after administration of 250 mg, 500 mg, or 1 g doses of cefprozil to fasting subjects were approximately 6.1, 10.5, and 18.3 mcg/mL, respectively, and were obtained within 1.5 hours after dosing.
Urinary recovery accounted for approximately 60% of the administered dose. (See Table.) *Data represent mean values of 12 healthy volunteers. Dosage (mg) Mean Plasma Cefprozil Concentrations (mcg/mL)* 8-hour Urinary Excretion (%) Peak appx.
1.5h 4 h 8 h 250 mg 6.1 1.7 0.2 60% 500 mg 10.5 3.2 0.4 62% 1000 mg 18.3 8.4 1 54% During the first 4-hour period after drug administration, the average urine concentrations following 250 mg, 500 mg, and 1 g doses were approximately 700 mcg/mL, 1000 mcg/mL, and 2900 mcg/mL, respectively. Administration of cefprozil tablet or suspension formulations with food did not affect the extent of absorption (AUC) or the peak plasma concentration (C max ) of cefprozil. However, there was an increase of 0.25 to 0.75 hours in the time to maximum plasma concentration of cefprozil (T max ).
Plasma protein binding is approximately 36% and is independent of concentration in the range of 2 mcg/mL to 20 mcg/mL. There was no evidence of accumulation of cefprozil in the plasma in individuals with normal renal function following multiple oral doses of up to 1000 mg every 8 hours for 10 days. In patients with reduced renal function, the plasma half-life may be prolonged up to 5.2 hours depending on the degree of the renal dysfunction.
In patients with complete absence of renal function, the plasma half-life of cefprozil has been shown to be as long as 5.9 hours. The half-life is shortened during hemodialysis. Excretion pathways in patients with markedly impaired renal function have not been determined.
(See PRECAUTIONS and DOSAGE AND ADMINISTRATION .) In patients with impaired hepatic function, the half-life increases to approximately 2 hours. The magnitude of the changes does not warrant a dosage adjustment for patients with impaired hepatic function. Healthy geriatric volunteers (≥65 years old) who received a single 1-g dose of cefprozil had 35% to 60% higher AUC and 40% lower renal clearance values compared with healthy adult volunteers 20 to 40 years of age.
The average AUC in young and elderly female subjects was approximately 15 to 20% higher than in young and elderly male subjects. The magnitude of these age- and gender-related changes in the pharmacokinetics of cefprozil is not sufficient to necessitate dosage adjustments. Adequate data on CSF levels of cefprozil are not available.
Comparable pharmacokinetic parameters of cefprozil are observed between pediatric patients (6 months to 12 years) and adults following oral administration of selected matched doses. The maximum concentrations are achieved at 1 to 2 hours after dosing. The plasma elimination half-life is approximately 1.5 hours.
In general, the observed plasma concentrations of cefprozil in pediatric patients at the 7.5, 15, and 30 mg/kg doses are similar to those observed within the same time frame in normal adult subjects at the 250, 500, and 1000 mg doses, respectively. The comparative plasma concentrations of cefprozil in pediatric patients and adult subjects at the equivalent dose level are presented in the table below. a n=11; b n=5; c n=9; d n=11. Mean (SD) Plasma Cefprozil Concentrations (mcg/mL) Population Dose 1 h 2 h 4 h 6 h… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Cefprozil for Oral Suspension, USP 125 mg/5 mL: Each 5 mL of reconstituted suspension contains cefprozil USP equivalent to anhydrous cefprozil 125 mg. 50 mL Bottle NDC 65862-099-50 75 mL Bottle NDC 65862-099-75 100 mL Bottle NDC 65862-099-01 Cefprozil for Oral Suspension, USP 250 mg/5 mL: Each 5 mL of reconstituted suspension contains cefprozil USP equivalent to anhydrous cefprozil 250 mg. 50 mL Bottle NDC 65862-100-50 75 mL Bottle NDC 65862-100-75 100 mL Bottle NDC 65862-100-01 All powder formulations for oral suspension contain cefprozil in light pink granular powder with bubble-gum flavored mixture.
Reconstitution Directions for Oral Suspension Prepare the suspension at the time of dispensing; for ease in preparation, add water in two portions and shake well after each aliquot. Total Amount of Water Required for Reconstitution Bottle Size Final Concentration 125 mg/5 mL Final Concentration 250 mg/5 mL 50 mL 35 mL 35 mL 75 mL 52 mL 52 mL 100 mL 70 mL 70 mL After mixing, store at 2° to 8°C [36° to 46° F] in a refrigerator and discard unused portion after 14 days. Store dry powder at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature] prior to constitution.
📋 Description ▾
DESCRIPTION Cefprozil is a semi-synthetic broad-spectrum cephalosporin antibiotic. Cefprozil is a cis and trans isomeric mixture (≥90% cis). The chemical name for the monohydrate is (6 R, 7 R )-7-[( R )-2-Amino-2-( p -hydroxyphenyl)acetamido]-8-oxo-3-propenyl-5-thia-1-azabicyclo[4.2.0]oct-2-ene-2-carboxylic acid monohydrate, and the structural formula is: Cefprozil, USP is a white to yellowish powder with a molecular formula for the monohydrate of C 18 H 19 N 3 O 5 S•H 2 O and a molecular weight of 407.45.
Cefprozil for oral suspension, USP is intended for oral administration. Cefprozil for oral suspension, USP contains cefprozil USP equivalent to 125 mg or 250 mg anhydrous cefprozil per 5 mL constituted suspension. In addition, the oral suspension contains the following inactive ingredients: aspartame, microcrystalline cellulose, carboxymethylcellulose sodium, citric acid monohydrate, colloidal silicon dioxide, FD&C Red No.3, glycine, polysorbate 80, simethicone emulsion, sodium benzoate, sodium chloride, bubble gum flavor and sucrose.
Chemical Structure
💬 Information for Patients ▾
Information for Patients Phenylketonurics: Cefprozil for oral suspension contains 8.4 mg of phenylalanine per 5 mL (1 teaspoonful) constituted suspension for both the 125 mg/5 mL and 250 mg/5 mL dosage forms. Patients should be counseled that antibacterial drugs including cefprozil should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold).
When cefprozil is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by cefprozil or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued.
Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic. If this occurs, patients should contact their physician as soon as possible.
⚠️ Precautions ▾
PRECAUTIONS General Prescribing cefprozil in the absence of proven or strongly suspected bacterial infection or a prophylactic indication is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria. In patients with known or suspected renal impairment (see DOSAGE AND ADMINISTRATION ), careful clinical observation and appropriate laboratory studies should be done prior to and during therapy. The total daily dose of cefprozil should be reduced in these patients because high and/or prolonged plasma antibiotic concentrations can occur in such individuals from usual doses.
Cephalosporins, including cefprozil, should be given with caution to patients receiving concurrent treatment with potent diuretics since these agents are suspected of adversely affecting renal function. Prolonged use of cefprozil may result in the overgrowth of nonsusceptible organisms. Careful observation of the patient is essential.
If superinfection occurs during therapy, appropriate measures should be taken. Cefprozil should be prescribed with caution in individuals with a history of gastrointestinal disease particularly colitis. Positive direct Coombs’ tests have been reported during treatment with cephalosporin antibiotics.
Information for Patients Phenylketonurics: Cefprozil for oral suspension contains 8.4 mg of phenylalanine per 5 mL (1 teaspoonful) constituted suspension for both the 125 mg/5 mL and 250 mg/5 mL dosage forms. Patients should be counseled that antibacterial drugs including cefprozil should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold).
When cefprozil is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by cefprozil or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued.
Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic. If this occurs, patients should contact their physician as soon as possible. Drug Interactions Nephrotoxicity has been reported following concomitant administration of aminoglycoside antibiotics and cephalosporin antibiotics.
Concomitant administration of probenecid doubled the AUC for cefprozil. The bioavailability of the capsule formulation of cefprozil was not affected when administered 5 minutes following an antacid. Drug/laboratory Test Interactions Cephalosporin antibiotics may produce a false positive reaction for glucose in the urine with copper reduction tests (Benedict’s or Fehling’s solution or with Clinitest ® tablets 1 ), but not with enzyme-based tests for glycosuria (e.g., Clinistix ® ).
A false negative reaction may occur in the ferricyanide test for blood glucose. The presence of cefprozil in the blood does not interfere with the assay of plasma or urine creatinine by the alkaline picrate method. 1 Clinitest ® and Clinistix ® are registered trademarks of Bayer Healthcare LLC.
Carcinogenesis, Mutagenesis, Impairment of Fertility Long term in vivo studies have not been performed to evaluate the carcinogenic potential of cefprozil. Cefprozil was not found to be mutagenic in either the Ames Salmonella or E. coli WP2 urvA reversion assays or the Chinese hamster ovary cell HGPRT forward gene mutation assay and it did not induce chromosomal abnormalities in Chinese hamster ovary cells or unscheduled DNA synthesis in rat hepatocytes in vitro . Chromosomal aberrations were not observ… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Small amounts of cefprozil (<0.3% of dose) have been detected in human milk following administration of a single 1 gram dose to lactating women. The average levels over 24 hours ranged from 0.25 to 3.3 mcg/mL. Caution should be exercised when cefprozil is administered to a nursing woman, since the effect of cefprozil on nursing infants is unknown.
🔬 Clinical Studies ▾
CLINICAL STUDIES Study One: In a controlled clinical study of acute otitis media performed in the United States where significant rates of β-lactamase-producing organisms were found, cefprozil was compared to an oral antimicrobial agent that contained a specific β-lactamase inhibitor. In this study, using very strict evaluability criteria and microbiologic and clinical response criteria at the 10 to 16 days post-therapy follow-up, the following presumptive bacterial eradication/clinical cure outcomes (i.e., clinical success) and safety results were obtained: U.S.
Acute Otitis Media Study Cefprozil vs β-lactamase inhibitor-containing control drug EFFICACY: Pathogen % of Cases with Pathogen (n=155) Outcome S. pneumoniae 48.4% cefprozil success rate 5% better than control H. influenzae 35.5% cefprozil success rate 17% less than control M. catarrhalis 13.5% cefprozil success rate 12% less than control S. pyogenes 2.6% cefprozil equivalent to control Overall 100% cefprozil success rate 5% less than control SAFETY: The incidences of adverse events, primarily diarrhea and rash*, were clinically and statistically significantly higher in the control arm versus the cefprozil arm.
Age Group Cefprozil Control * The majority of these involved the diaper area in young children. 6 months to 2 years 21% 41% 3 to 12 years 10% 19% Study Two: In a controlled clinical study of acute otitis media performed in Europe, cefprozil was compared to an oral antimicrobial agent that contained a specific β-lactamase inhibitor. As expected in a European population, this study population had a lower incidence of β-lactamase-producing organisms than usually seen in U.S. trials.
In this study, using very strict evaluability criteria and microbiologic and clinical response criteria at the 10 to 16 days post-therapy follow-up, the following presumptive bacterial eradication/clinical cure outcomes (i.e., clinical success) were obtained: European Acute Otitis Media Study Cefprozil Vs β-lactamase inhibitor-containing control drug EFFICACY: Pathogen % of Cases with Pathogen (n=47) Outcome S. pneumoniae 51% cefprozil equivalent to control H. influenzae 29.8% cefprozil equivalent to control M. catarrhalis 6.4% cefprozil equivalent to control S. pyogenes 12.8% cefprozil equivalent to control Overall 100% cefprozil equivalent to control SAFETY: The incidence of adverse events in the cefprozil arm was comparable to the incidence of adverse events in the control arm (agent that contained a specific β-lactamase inhibitor).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Long term in vivo studies have not been performed to evaluate the carcinogenic potential of cefprozil. Cefprozil was not found to be mutagenic in either the Ames Salmonella or E. coli WP2 urvA reversion assays or the Chinese hamster ovary cell HGPRT forward gene mutation assay and it did not induce chromosomal abnormalities in Chinese hamster ovary cells or unscheduled DNA synthesis in rat hepatocytes in vitro . Chromosomal aberrations were not observed in bone marrow cells from rats dosed orally with over 30 times the highest recommended human dose based upon mg/m 2 .
Impairment of fertility was not observed in male or female rats given oral doses of cefprozil up to 18.5 times the highest recommended human dose based upon mg/m 2 .
📚 References ▾
Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 12/2021
📄 Package Label / Principal Display Panel ▾
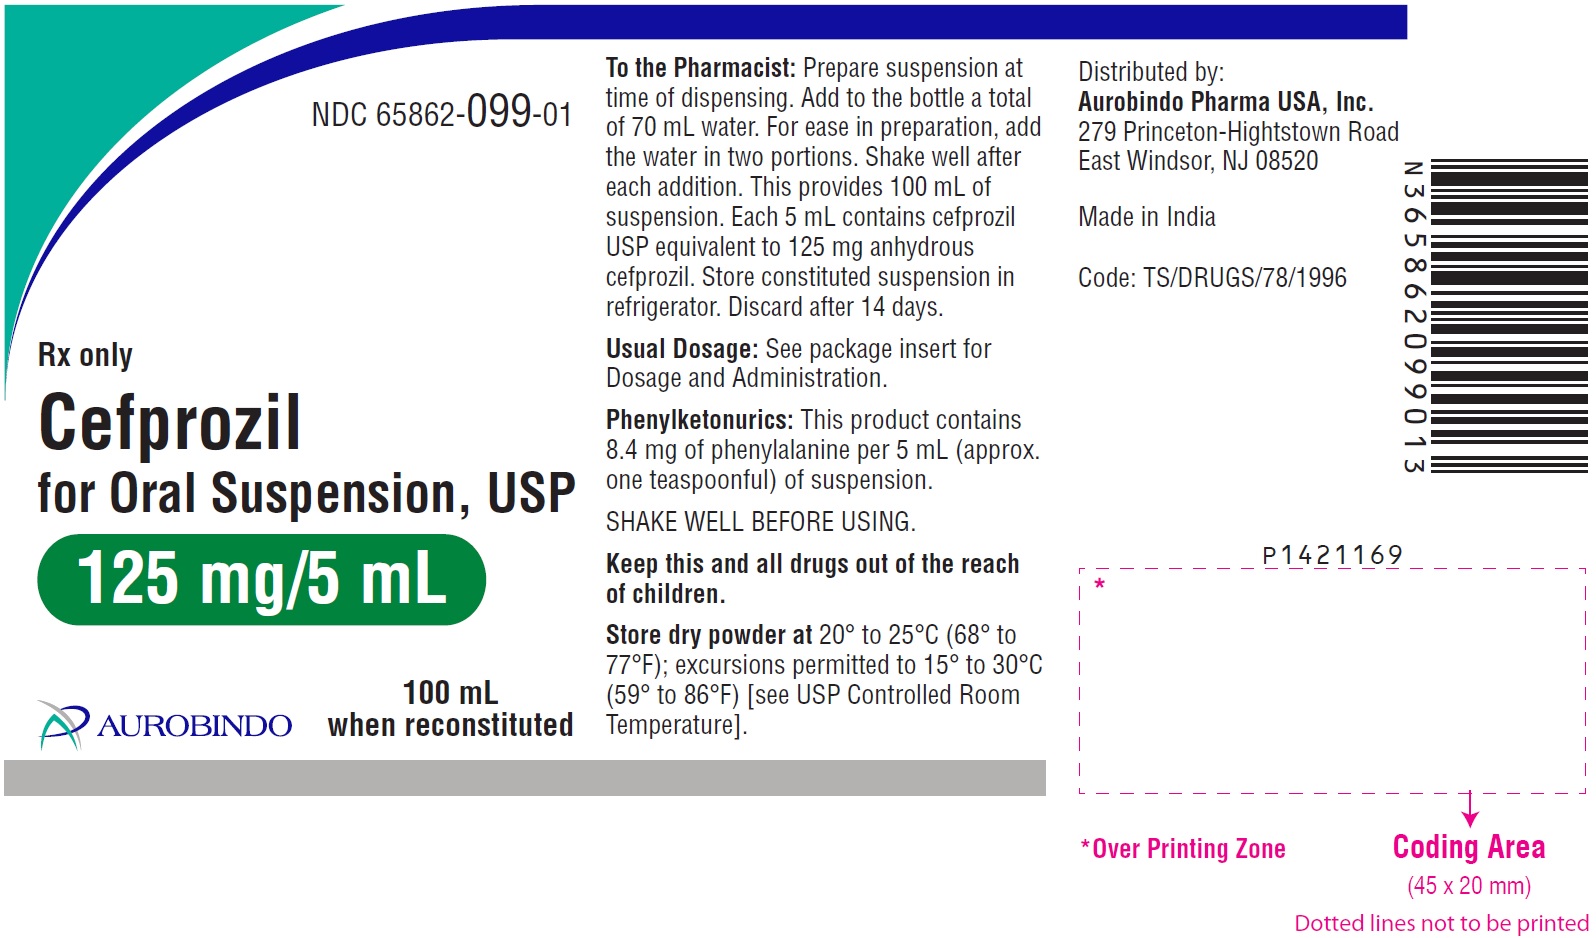
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 125 mg/5 mL (100 mL Bottle) NDC 65862-099-01 Rx only Cefprozil for Oral Suspension, USP 125 mg/5 mL 100 mL when reconstituted AUROBINDO PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 125 mg/5 mL (100 mL Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg/5 mL (100 mL Bottle) NDC 65862-100-01 Rx only Cefprozil for Oral Suspension, USP 250 mg/5 mL 100 mL when reconstituted AUROBINDO PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg/5 mL (100 mL Bottle)
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |