
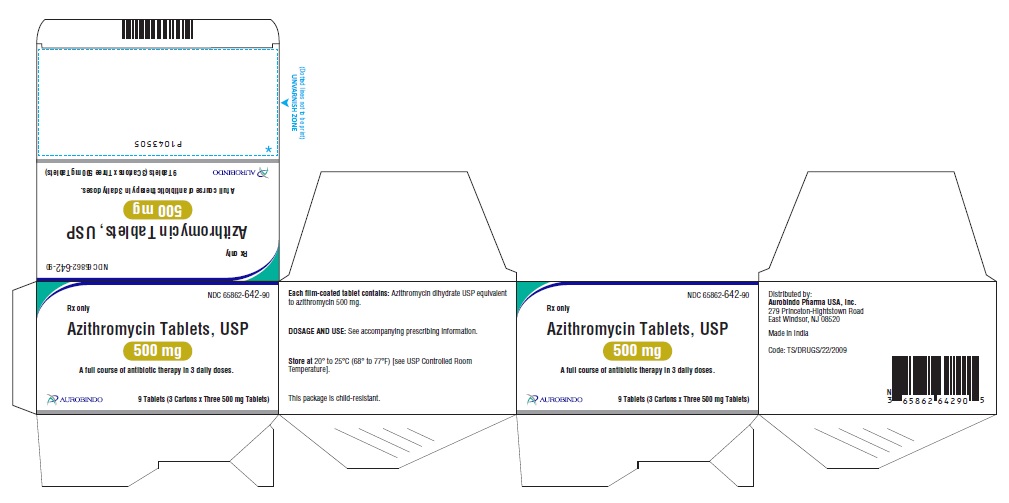
Azithromycin 500 mg Tablet, Film Coated — NDC 65862-642-90 (Billing 65862-0642-90)
This is a package of Azithromycin 500 mg Tablet, Film Coated from Aurobindo Pharma Limited, marketed since Jul 2018 and currently FDA-listed; retail pharmacies pay about $0.5409 per unit (NADAC).
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 022624
- GCN: 61198
- HICL (First Databank): 006334
- AHFS class code: 08:12.12.08
- RxCUI (RxNorm): 248656
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Macrolide Antimicrobial class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats certain mild to moderate bacterial infections, like sinus, throat, ear, lung, skin and some genital infections. The IV form is for pneumonia and pelvic inflammatory disea...
- Tablets can be taken with or without food. If it upsets your stomach, taking it with food may help. Take it exactly as your prescriber and label direct, and finish the course.
- The most common are diarrhea, nausea, stomach pain and vomiting. They are usually mild. Call your doctor if they are severe or don't settle.
- Get emergency help for facial or throat swelling, trouble breathing, or a severe blistering rash. Call promptly for yellow skin or eyes, a racing or irregular heartbeat, fainting,...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Azithromycin — tap one for details:
Azithromycin may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.541 | $4.87 / 9 tablets |
| Medicaid paysCMS SDUD · 12 mo | $2.17 | $19.55 / 9 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.5357 | $4.82 / 9 tablets |
| Medicare Part B allowsASP · Q0144 | No ASP payment limit on file for Q0144 this quarter. | |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 65862-0642-30 65862-642-30 Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | $0.5409 / ea | $16.23 | 2018-07-05 | — | Active |
| 65862-0642-64 65862-642-64 | 1 BLISTER PACK in 1 CARTON / 3 TABLET, FILM COATED in 1 BLISTER PACK | $0.5409 / ea | $1.62 | 2018-07-05 | — | Active |
| 65862-0642-90 You're viewing this | 3 BLISTER PACK in 1 CARTON / 3 TABLET, FILM COATED in 1 BLISTER PACK | $0.5409 / ea | $4.87 | 2018-07-05 | — | Active |
| 65862-0642-12 65862-642-12 | 12500 TABLET, FILM COATED in 1 BAG | — | — | — | — | Active |
| 65862-0642-55 65862-642-55 | 15000 TABLET, FILM COATED in 1 BAG | — | — | — | — | Active |
This pack effectively ties for the lowest per-ea cost of the 3 priced pack sizes ($0.5409 NADAC).
This pack accounts for about 5.8% of this product's recent Medicaid fills; most go to the 30 tablets pack. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Azithromycin 500 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| azithromycin 500 mg 00527-2395-32 | Lannett | 30 tablets | $0.541 | AB | Availability likely | — |
| Azithromycin 500 mg 00781-8090-03 | Sandoz | 3 tablets | $0.541 | AB | Availability likely | — |
| azithromycin 500 mg 00904-7351-04 | Major | 30 tablets | $0.541 | AB | Availability likely | — |
| Azithromycin 500 mg 50111-0788-10 | Teva | 30 tablets | $0.541 | AB | Availability likely | — |
| Azithromycin 500 mg 60687-0753-21 | American | 30 tablets | $0.541 | AB | Availability likely | — |
| Azithromycin 500 mgthis 65862-0642-90 | Aurobindo | 3 tablets | $0.541 | AB | Availability likely | — |
| Azithromycin Dihydrate 500 mg 68094-0799-03 | Precision | 3 tablets | $0.541 | AB | Availability likely | — |
| azithromycin 500 mg 68180-0862-06 | Lupin | 30 tablets | $0.541 | AB | Availability likely | — |
| Azithromycin 500 mg 69452-0172-13 | Bionpharma | 30 tablets | $0.541 | AB | Availability likely | — |
| Azithromycin Dihydrate 500 mg 51224-0122-03 | TAGI | 3 tablets | $0.676 | AB | Discontinued | +25% |
| Zithromax 500 mg 00069-3070-30 | Pfizer | 30 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 42291-0083-03 | AvKARE | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 46708-0058-03 | Alembic | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 50090-5366-00 | A-S | 5 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 50090-5376-00 | A-S | 2 tablets | — | AB | FDA listed | — |
| Azithromycin Dihydrate 500 mg 50090-7298-00 | A-S | 5 tablets | — | AB | FDA listed | — |
| Azithromycin Dihydrate 500 mg 50090-7299-00 | A-S | 2 tablets | — | AB | FDA listed | — |
| Azithromycin Dihydrate 500 mg 50090-7506-00 | A-S | 1 tablet | — | AB | FDA listed | — |
| Azithromycin 500 mg 54348-0857-00 | PharmPak, | 1 tablet | — | AB | FDA listed | — |
| Azithromycin 500 mg 62332-0252-03 | Alembic | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 63187-0189-03 | Proficient | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 63629-8251-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| azithromycin 500 mg 64980-0726-03 | Rising | 30 tablets | — | AB | FDA listed | — |
| Azithromycin Dihydrate 500 mg 67046-1607-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 68071-2297-02 | NuCare | 2 tablets | — | AB | FDA listed | — |
| Azithromycin Dihydrate 500 mg 68071-3661-02 | NuCare | 2 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 68071-5058-03 | NuCare | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 68071-5082-05 | NuCare | 5 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 68788-7598-03 | Preferred | 3 tablets | — | AB | FDA listed | — |
| Azithromycin Dihydrate 500 mg 68788-8773-03 | Preferred | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 70518-0599-00 | REMEDYREPACK | 1 tablet | — | AB | FDA listed | — |
| Azithromycin Dihydrate 500 mg 70518-3168-00 | REMEDYREPACK | 1 tablet | — | AB | Discontinued | — |
| Azithromycin 500 mg 70518-3254-00 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| Azithromycin Dihydrate 500 mg 70518-4105-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| azithromycin 500 mg 70518-4367-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Azithromycin Dihydrate 500 mg 71093-0175-01 | ACI | 30 tablets | — | — | Discontinued | — |
| Azithromycin 500 mg 71205-0503-03 | Proficient | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 71205-0519-03 | Proficient | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 71335-1755-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Azithromycin Dihydrate 500 mg 71335-2581-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 72162-2669-03 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 72189-0015-02 | Direct_Rx | 2 tablets | — | AB | FDA listed | — |
| Azithromycin Dihydrate 500 mg 72789-0445-02 | PD-Rx | 2 tablets | — | AB | FDA listed | — |
| Azithromycin Dihydrate 500 mg 82804-0153-04 | Proficient | 4 tablets | — | AB | FDA listed | — |
| Azithromycin Dihydrate 500 mg 83112-0501-00 | Health | 2 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 85766-0077-03 | Sportpharm | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 68071-4976-03 | NuCare | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 71205-0674-03 | Proficient | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 72189-0088-03 | DIRECT | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 67296-1945-05 | Redpharm | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 68788-8125-03 | Preferred | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 50090-8013-00 | A-S | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 50090-8017-00 | A-S | 3 tablets | — | AB | FDA listed | — |
| Azithromycin 500 mg 70518-3508-00 | REMEDYREPACK | 1 tablet | — | AB | Discontinued | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L11K75P92J
A mineral salt made from calcium and phosphate. It acts as a filler and binder in tablets to add bulk and help hold the medicine together in solid form.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 36SFW2JZ0W
Hypromellose 2910 is a plant-based thickening agent derived from cellulose. In medicines, it forms a protective coating on tablets or capsules and controls how quickly the drug dissolves and releases into your body.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Azithromycin tablets are a macrolide antibacterial drug indicated for treatment of patients with mild to moderate infections caused by susceptible strains of the designated microorganisms in the specific conditions listed below: Acute bacterial exacerbations of chronic bronchitis in adults ( 1.1 ) Acute bacterial sinusitis in adults ( 1.1 ) Uncomplicated skin and skin structure infections in adults ( 1.1 ) Urethritis and cervicitis in adults ( 1.1 ) Genital ulcer disease in men ( 1.1 ) Acute otitis media in pediatric patients (6 months of age and older) ( 1.2 ) Community-acquired pneumonia in adults and pediatric patients (6 months of age and older) ( 1.1 , 1.2 ) Pharyngitis/tonsillitis in adults and pediatric patients (2 years of age and older) ( 1.1 , 1.2 ) Limitation of Use: Azithromycin tablets are not recommended in patients with pneumonia who are judged to be inappropriate for oral therapy because of moderate to severe illness or risk factors.
( 1.3 ) To reduce the development of drug-resistant bacteria and maintain the effectiveness of azithromycin tablets and other antibacterial drugs, azithromycin tablets should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. ( 1.4 )
1.1Indications in Adult Patients Azithromycin tablets are indicated in adult patients for the treatment of mild to moderate infections caused by susceptible strains of the designated microorganisms in the specific conditions listed below: Acute bacterial exacerbations of chronic bronchitis due to Haemophilus influenzae , Moraxella catarrhalis, or Streptococcus pneumoniae . Acute bacterial sinusitis due to Haemophilus influenzae , Moraxella catarrhalis. or Streptococcus pneumoniae . Community-acquired pneumonia due to Chlamydophila pneumoniae , Haemophilus influenzae , Mycoplasma pneumoniae, or Streptococcus pneumoniae in patients appropriate for oral therapy.
Pharyngitis/tonsillitis caused by Streptococcus pyogenes as an alternative to first-line therapy in individuals who cannot use first-line therapy. Uncomplicated skin and skin structure infections due to Staphylococcus aureus , Streptococcus pyogenes , or Streptococcus agalactiae . Urethritis and cervicitis due to Chlamydia trachomatis or Neisseria gonorrhoeae .
Genital ulcer disease in men due to Haemophilus ducreyi (chancroid). Due to the small number of women included in clinical trials, the efficacy of azithromycin in the treatment of chancroid in women has not been established.
1.2Indications in Pediatric Patients Azithromycin tablets are indicated in pediatric patients for the treatment of mild to moderate infections caused by susceptible strains of the designated microorganisms in the specific conditions listed below: [see Use in Specific Populations (8.4) and Clinical Studies (14.2) ]. Acute otitis media caused by Haemophilus influenzae , Moraxella catarrhalis, or Streptococcus pneumoniae, in pediatric patients 6 months of age and older . Community-acquired pneumonia due to Chlamydophila pneumoniae , Haemophilus influenzae , Mycoplasma pneumoniae , or Streptococcus pneumoniae in pediatric patients 6 months of age and older appropriate for oral therapy.
Pharyngitis/tonsillitis caused by Streptococcus pyogenes as an alternative to first-line therapy in individuals who cannot use first-line therapy in pediatric patients 2 years of age and older.
1.3Limitations of Use Azithromycin is not recommended in patients with pneumonia who are judged to be inappropriate for oral therapy because of moderate to severe illness or risk factors such as any of the following: patients with cystic fibrosis, patients with nosocomial infections, patients with known or suspected bacteremia, patients requiring hospitalization, elderly or debilitated patients, or patients with significant underlying health problems that may compromise their ability to respond to their illness (including immunodeficiency or functional asple… [Excerpted — this section continues on DailyMed.]
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended Dosage for Adult Patients ( 2.1 ) Infection Recommended Dose/Duration of Therapy Community-acquired pneumonia (mild severity) Pharyngitis/tonsillitis (second-line therapy) Skin/skin structure (uncomplicated) 500 mg as a single dose on Day 1, followed by 250 mg once daily on Days 2 through 5. Acute bacterial exacerbations of chronic bronchitis (mild to moderate) 500 mg as a single dose on Day 1, followed by 250 mg once daily on Days 2 through 5 or 500 mg once daily for 3 days. Acute bacterial sinusitis 500 mg once daily for 3 days.
Genital ulcer disease (chancroid) Non-gonococcal urethritis and cervicitis One single 1 gram dose. Gonococcal urethritis and cervicitis One single 2 gram dose. Recommended Dosage for Pediatric Patients ( 2.2 ) Infection Recommended Dose/Duration of Therapy Acute otitis media (6 months of age and older) 30 mg/kg as a single dose or 10 mg/kg once daily for 3 days or 10 mg/kg as a single dose on Day 1 followed by 5 mg/kg/day on Days 2 through 5.
Acute bacterial sinusitis (6 months of age and older) 10 mg/kg once daily for 3 days. Community-acquired pneumonia (6 months of age and older) 10 mg/kg as a single dose on Day 1 followed by 5 mg/kg once daily on Days 2 through 5. Pharyngitis/tonsillitis (2 years of age and older) 12 mg/kg once daily for 5 days.
2.1Recommended Dosage for Adult Patients Recommended dosages and durations of therapy in adult patient populations vary by indications [see Indications and Usage (1.1) and Clinical Pharmacology (12.3) ]. Azithromycin tablets can be taken with or without food. Table 1.
Recommended dosage for Adult Patients by Indication Infection* Recommended Dose/Duration of Therapy Community-acquired pneumonia Pharyngitis/tonsillitis (second-line therapy) Skin/skin structure (uncomplicated) 500 mg as a single dose on Day 1, followed by 250 mg once daily on Days 2 through 5 Acute bacterial exacerbations of chronic obstructive pulmonary disease 500 mg once daily for 3 days OR 500 mg as a single dose on Day 1, followed by 250 mg once daily on Days 2 through 5 Acute bacterial sinusitis 500 mg once daily for 3 days Genital ulcer disease (chancroid) One single 1 gram dose Non-gonococcal urethritis and cervicitis One single 1 gram dose Gonococcal urethritis and cervicitis One single 2 gram dose * Due to the indicated microorganisms [see Indications and Usage (1.1) ].
2.2Recommended Dosage for Pediatric Patients Recommended dosages and durations of therapy in pediatric patient populations vary by indications [see Indications and Usage (1.2) and Clinical Pharmacology (12.3) ]. Azithromycin for oral suspension can be taken with or without food. Table 2.
Recommended dose for Pediatric Patients by Indication Infection* Recommended Dose/Duration of Therapy 1 Acute otitis media 30 mg/kg as a single dose or 10 mg/kg once daily for 3 days or 10 mg/kg as a single dose on Day 1 followed by 5 mg/kg/day on Days 2 through 5. Acute bacterial sinusitis 10 mg/kg once daily for 3 days. Community-acquired pneumonia 10 mg/kg as a single dose on Day 1 followed by 5 mg/kg once daily on Days 2 through 5.
Pharyngitis/tonsillitis 12 mg/kg once daily for 5 days. * Due to the indicated microorganisms [see Indications and Usage (1.2) and Use in Specific Populations (8.4) ]. 1 see dosing tables below for maximum doses evaluated by indication. PEDIATRIC DOSAGE GUIDELINES FOR OTITIS MEDIA, ACUTE BACTERIAL SINUSITIS, AND COMMUNITY-ACQUIRED PNEUMONIA (Age 6 months and above, [see Use in Specific Populations (8.4) ] ) Based on Body Weight Table 3.
Otitis Media and Community-Acquired Pneumonia: (5-Day Regimen)* Dosing Calculated on 10 mg/kg/day Day 1 and 5 mg/kg/day Days 2 to 5. Weight 100 mg/5 mL 200 mg/5 mL Total mL per Treatment Course Total mg per Treatment Course Kg Day 1 Days 2 to 5 Day 1 Days 2 to 5 5 2.5 mL; (½ tsp) 1.25 mL; (¼ tsp) 7.5 mL 150 mg 10 5 mL; (1tsp) 2.5 mL; (½ tsp) 15 mL 300 mg 20 5 mL; (1 tsp) 2.5 mL; (½ tsp) 15 mL 600 mg 30 7.5 mL; (1½ tsp) 3.75 mL… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Azithromycin Tablets USP, 250 mg are white to off-white, modified capsule shaped, film-coated biconvex tablets, debossed with “66” on one side and “D” on other side. These are packaged in bottles and blister packs. Azithromycin Tablets USP, 500 mg are white to off-white, oval shaped, film-coated biconvex tablets, debossed with “67” on one side and “D” on other side.
These are packaged in bottles and blister packs. Azithromycin tablets USP 250 mg and 500 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Patients with known hypersensitivity to azithromycin, erythromycin, any macrolide or ketolide drug. ( 4.1 ) Patients with a history of cholestatic jaundice/hepatic dysfunction associated with prior use of azithromycin. ( 4.2 )
4.1Hypersensitivity Azithromycin tablets are contraindicated in patients with known hypersensitivity to azithromycin, erythromycin, any macrolide or ketolide drug.
4.2Hepatic Dysfunction Azithromycin tablets are contraindicated in patients with a history of cholestatic jaundice/hepatic dysfunction associated with prior use of azithromycin.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Serious (including fatal) allergic and skin reactions: Discontinue azithromycin if reaction occurs. ( 5.1 ) Hepatotoxicity: Severe, and sometimes fatal, hepatotoxicity has been reported. Discontinue azithromycin immediately if signs and symptoms of hepatitis occur.
( 5.2 ) Infantile Hypertrophic Pyloric Stenosis (IHPS): Following the use of azithromycin in neonates (treatment up to 42 days of life), IHPS has been reported. Direct parents and caregivers to contact their physician if vomiting or irritability with feeding occurs. ( 5.3 ) Prolongation of QT interval and cases of torsades de pointes have been reported.
This risk which can be fatal should be considered in patients with certain cardiovascular disorders including known QT prolongation or history torsades de pointes, those with proarrhythmic conditions, and with other drugs that prolong the QT interval. ( 5.4 ) Cardiovascular Death: Some observational studies have shown an approximately two-fold increased short-term potential risk of acute cardiovascular death in adults exposed to azithromycin relative to other antibacterial drugs, including amoxicillin. Consider balancing this potential risk with treatment benefits when prescribing azithromycin.
( 5.5 ) Clostridioides difficile -Associated Diarrhea: Evaluate patients if diarrhea occurs. ( 5.6 ) Azithromycin may exacerbate muscle weakness in persons with myasthenia gravis. ( 5.7 )
5.1Hypersensitivity Serious allergic reactions, including angioedema, anaphylaxis, and dermatologic reactions including Acute Generalized Exanthematous Pustulosis (AGEP), Stevens-Johnson syndrome, and toxic epidermal necrolysis have been reported in patients on azithromycin therapy. [see Contraindications (4.1) ] Fatalities have been reported. Cases of Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) have also been reported. Despite initially successful symptomatic treatment of the allergic symptoms, when symptomatic therapy was discontinued, the allergic symptoms recurred soon thereafter in some patients without further azithromycin exposure.
These patients required prolonged periods of observation and symptomatic treatment. The relationship of these episodes to the long tissue half-life of azithromycin and subsequent prolonged exposure to antigen is presently unknown. If an allergic reaction occurs, the drug should be discontinued and appropriate therapy should be instituted.
Physicians should be aware that allergic symptoms may reappear when symptomatic therapy has been discontinued.
5.2Hepatotoxicity Abnormal liver function, hepatitis, cholestatic jaundice, hepatic necrosis, and hepatic failure have been reported, some of which have resulted in death. Discontinue azithromycin immediately if signs and symptoms of hepatitis occur.
5.3Infantile Hypertrophic Pyloric Stenosis (IHPS) Following the use of azithromycin in neonates (treatment up to 42 days of life), IHPS has been reported. Direct parents and caregivers to contact their physician if vomiting or irritability with feeding occurs.
5.4QT Prolongation Prolonged cardiac repolarization and QT interval, imparting a risk of developing cardiac arrhythmia and torsades de pointes, have been seen with treatment with macrolides, including azithromycin. Cases of torsades de pointes have been spontaneously reported during postmarketing surveillance in patients receiving azithromycin. Providers should consider the risk of QT prolongation which can be fatal when weighing the risks and benefits of azithromycin for at-risk groups including: patients with known prolongation of the QT interval, a history of torsades de pointes, congenital long QT syndrome, bradyarrhythmias or uncompensated heart failure patients on drugs known to prolong the QT interval patients with ongoing proarrhythmic conditions such as uncorrected hypokalemia or hypomagnesemia, clinically significant bradycardia, and in patients receiving Class IA (quinidine, procainamide) or Class III (d… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in labeling: Hypersensitivity [see Warnings and Precautions (5.1) ] Hepatotoxicity [see Warnings and Precautions (5.2) ] Infantile Hypertrophic Pyloric Stenosis (IHPS) [see Warnings and Precautions (5.3) ] QT Prolongation [see Warnings and Precautions (5.4) ] Cardiovascular Death [see Warnings and Precautions (5.5) ] Clostridioides difficile- Associated Diarrhea (CDAD) [see Warnings and Precautions (5.6) ] Exacerbation of Myasthenia Gravis [see Warnings and Precautions (5.7) ] Most common adverse reactions are diarrhea (5 to 14%), nausea (3 to 18%), abdominal pain (3 to 7%), or vomiting (2 to 7%).
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In clinical trials, most of the reported side effects were mild to moderate in severity and were reversible upon discontinuation of the drug. Potentially serious adverse reactions of angioedema and cholestatic jaundice were reported.
Approximately 0.7% of the patients (adults and pediatric patients) from the 5-day multiple-dose clinical trials discontinued azithromycin therapy because of treatment-related adverse reactions. In adults given 500 mg/day for 3 days, the discontinuation rate due to treatment-related adverse reactions was 0.6%. In clinical trials in pediatric patients given 30 mg/kg, either as a single dose or over 3 days, discontinuation from the trials due to treatment-related adverse reactions was approximately 1%.
Most of the adverse reactions leading to discontinuation were related to the gastrointestinal tract, e.g., nausea, vomiting, diarrhea, or abdominal pain. [see Clinical Studies (14.2) ] Clinical Trials Experience in Adults Multiple-dose regimens: Overall, the most common treatment-related adverse reactions in adult patients receiving multiple-dose regimens of azithromycin were related to the gastrointestinal system with diarrhea/loose stools (4 to 5%), nausea (3%), and abdominal pain (2 to 3%) being the most frequently reported.
No other adverse reactions occurred in patients on the multiple-dose regimens of azithromycin with a frequency greater than 1%. Adverse reactions that occurred with a frequency of 1% or less included the following: Cardiovascular: Palpitations, chest pain. Gastrointestinal: Dyspepsia, flatulence, vomiting, melena, and cholestatic jaundice.
Genitourinary: Monilia, vaginitis, and nephritis. Nervous System: Dizziness, headache, vertigo, and somnolence. General: Fatigue.
Allergic: Rash, pruritus, photosensitivity, and angioedema. Single 1 gram dose regimen: Overall, the most common adverse reactions in patients receiving a single-dose regimen of 1 gram of azithromycin were related to the gastrointestinal system and were more frequently reported than in patients receiving the multiple-dose regimen. Adverse reactions that occurred in patients on the single 1 gram dosing regimen of azithromycin with a frequency of 1% or greater included diarrhea/loose stools (7%), nausea (5%), abdominal pain (5%), vomiting (2%), dyspepsia (1%), and vaginitis (1%).
Single 2 gram dose regimen: Overall, the most common adverse reactions in patients receiving a single 2 gram dose of azithromycin were related to the gastrointestinal system. Adverse reactions that occurred in patients in this study with a frequency of 1% or greater included nausea (18%), diarrhea/loose stools (14%), vomiting (7%), abdominal pain (7%), vaginitis (2%), dyspepsia (1%), and dizziness (1%). The majority of these complaints were mild in nature.
Clinical Trials Experience in Pediatric Patients Single and… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Nelfinavir: Close monitoring for known adverse reactions of azithromycin, such as liver enzyme abnormalities and hearing impairment, is warranted. ( 7.1 ) Warfarin: Use with azithromycin may increase coagulation times; monitor prothrombin time. ( 7.2 )
7.1Nelfinavir Co-administration of nelfinavir at steady-state with a single oral dose of azithromycin resulted in increased azithromycin serum concentrations. Although a dose adjustment of azithromycin is not recommended when administered in combination with nelfinavir, close monitoring for known adverse reactions of azithromycin, such as liver enzyme abnormalities and hearing impairment, is warranted. [see Adverse Reactions (6) ]
7.2Warfarin Spontaneous postmarketing reports suggest that concomitant administration of azithromycin may potentiate the effects of oral anticoagulants such as warfarin, although the prothrombin time was not affected in the dedicated drug interaction study with azithromycin and warfarin. Prothrombin times should be carefully monitored while patients are receiving azithromycin and oral anticoagulants concomitantly.
7.3Potential Drug-Drug Interaction with Macrolides Interactions with digoxin, colchicine or phenytoin have not been reported in clinical trials with azithromycin. No specific drug interaction studies have been performed to evaluate potential drug-drug interaction. However, drug interactions have been observed with other macrolide products.
Until further data are developed regarding drug interactions when digoxin, colchicine or phenytoin are used with azithromycin careful monitoring of patients is advised.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatric use: Elderly patients may be more susceptible to development of torsades de pointes arrhythmias. ( 8.5 )
8.1Pregnancy Risk Summary Available data from published literature and postmarketing experience over several decades with azithromycin use in pregnant women have not identified any drug-associated risks for major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data) . Developmental toxicity studies with azithromycin in rats, mice, and rabbits showed no drug-induced fetal malformations at doses up to 4, 2, and 2 times, respectively, an adult human daily dose of 500 mg based on body surface area.
Decreased viability and delayed development were observed in the offspring of pregnant rats administered azithromycin from day 6 of pregnancy through weaning at a dose equivalent to 4 times an adult human daily dose of 500 mg based on body surface area (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data Available data from published observational studies, case series, and case reports over several decades do not suggest an increased risk for major birth defects, miscarriage, or adverse maternal or fetal outcomes with azithromycin use in pregnant women. Limitations of these data include the lack of randomization and inability to control for confounders such as underlying maternal disease and maternal use of concomitant medications.
Animal Data Azithromycin administered during the period of organogenesis did not cause fetal malformations in rats and mice at oral doses up to 200 mg/kg/day (moderately maternally toxic). Based on body surface area, this dose is approximately 4 (rats) and 2 (mice) times an adult human daily dose of 500 mg. In rabbits administered azithromycin at oral doses of 10, 20, and 40 mg/kg/day during organogenesis, reduced maternal body weight and food consumption were observed in all groups; no evidence of fetotoxicity or teratogenicity was observed at these doses, the highest of which is estimated to be 2 times an adult human daily dose of 500 mg based on body surface area.
In a pre- and postnatal development study, azithromycin was administered orally to pregnant rats from day 6 of pregnancy until weaning at doses of 50 or 200 mg/kg/day. Maternal toxicity (reduced food consumption and body weight gain; increased stress at parturition) was observed at the higher dose. Effects in the offspring were noted at 200 mg/kg/day during the postnatal development period (decreased viability, delayed developmental landmarks).
These effects were not observed in a pre- and postnatal rat study when up to 200 mg/kg/day of azithromycin was given orally beginning on day 15 of pregnancy until weaning.
8.2Lactation Risk Summary Azithromycin is present in human milk (see Data) . Non-serious adverse reactions have been reported in breastfed infants after maternal administration of azithromycin (see Clinical Considerations) . There are no available data on the effects of azithromycin on milk production.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for azithromycin and any potential adverse effects on the breastfed infant from azithromycin or from the underlying maternal condition. Clinical Considerations Advise women to monitor the breastfed infant for diarrhea, vomiting, or rash. Data Azithromycin breastmilk concentrations were measured in 20 women after receiving a single 2 g oral dose of azithromycin during labor.
Breastmilk samples collected on days 3 and 6 postpartum as well as 2 and 4 weeks postpartum revealed the presence of azithromycin in breastmil… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from published literature and postmarketing experience over several decades with azithromycin use in pregnant women have not identified any drug-associated risks for major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data) . Developmental toxicity studies with azithromycin in rats, mice, and rabbits showed no drug-induced fetal malformations at doses up to 4, 2, and 2 times, respectively, an adult human daily dose of 500 mg based on body surface area.
Decreased viability and delayed development were observed in the offspring of pregnant rats administered azithromycin from day 6 of pregnancy through weaning at a dose equivalent to 4 times an adult human daily dose of 500 mg based on body surface area (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data Available data from published observational studies, case series, and case reports over several decades do not suggest an increased risk for major birth defects, miscarriage, or adverse maternal or fetal outcomes with azithromycin use in pregnant women. Limitations of these data include the lack of randomization and inability to control for confounders such as underlying maternal disease and maternal use of concomitant medications.
Animal Data Azithromycin administered during the period of organogenesis did not cause fetal malformations in rats and mice at oral doses up to 200 mg/kg/day (moderately maternally toxic). Based on body surface area, this dose is approximately 4 (rats) and 2 (mice) times an adult human daily dose of 500 mg. In rabbits administered azithromycin at oral doses of 10, 20, and 40 mg/kg/day during organogenesis, reduced maternal body weight and food consumption were observed in all groups; no evidence of fetotoxicity or teratogenicity was observed at these doses, the highest of which is estimated to be 2 times an adult human daily dose of 500 mg based on body surface area.
In a pre- and postnatal development study, azithromycin was administered orally to pregnant rats from day 6 of pregnancy until weaning at doses of 50 or 200 mg/kg/day. Maternal toxicity (reduced food consumption and body weight gain; increased stress at parturition) was observed at the higher dose. Effects in the offspring were noted at 200 mg/kg/day during the postnatal development period (decreased viability, delayed developmental landmarks).
These effects were not observed in a pre- and postnatal rat study when up to 200 mg/kg/day of azithromycin was given orally beginning on day 15 of pregnancy until weaning.
🧒 Pediatric Use ▾
8.4Pediatric Use [see Clinical Pharmacology (12.3) , Indications and Usage (1.2) , and Dosage and Administration (2.2) ] Safety and effectiveness in the treatment of pediatric patients with acute otitis media, acute bacterial sinusitis and community-acquired pneumonia under 6 months of age have not been established. Use of azithromycin for the treatment of acute bacterial sinusitis and community-acquired pneumonia in pediatric patients (6 months of age or greater) is supported by adequate and well-controlled trials in adults.
Pharyngitis/Tonsillitis: Safety and effectiveness in the treatment of pediatric patients with pharyngitis/tonsillitis under 2 years of age have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In multiple-dose clinical trials of oral azithromycin, 9% of patients were at least 65 years of age (458/4949) and 3% of patients (144/4949) were at least 75 years of age. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in response between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Elderly patients may be more susceptible to development of torsades de pointes arrhythmias than younger patients. [see Warnings and Precautions (5.4) ]
🆘 Overdosage ▾
10 OVERDOSAGE Adverse reactions experienced at higher than recommended doses were similar to those seen at normal doses particularly nausea, diarrhea, and vomiting. In the event of overdosage, general symptomatic and supportive measures are indicated as required.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Azithromycin is a macrolide antibacterial drug. [see Microbiology (12.4) ]
12.2Pharmacodynamics Based on animal models of infection, the antibacterial activity of azithromycin appears to correlate with the ratio of area under the concentration-time curve to minimum inhibitory concentration (AUC/MIC) for certain pathogens ( S. pneumoniae and S. aureus ). The principal pharmacokinetic/pharmacodynamic parameter best associated with clinical and microbiological cure has not been elucidated in clinical trials with azithromycin. Cardiac Electrophysiology QTc interval prolongation was studied in a randomized, placebo-controlled parallel trial in 116 healthy subjects who received either chloroquine (1000 mg) alone or in combination with oral azithromycin (500 mg, 1000 mg, and 1500 mg once daily).
Co-administration of azithromycin increased the QTc interval in a dose- and concentration-dependent manner. In comparison to chloroquine alone, the maximum mean (95% upper confidence bound) increases in QTcF were 5 (10) ms, 7 (12) ms and 9 (14) ms with the co-administration of 500 mg, 1000 mg and 1500 mg azithromycin, respectively.
12.3Pharmacokinetics Following oral administration of a single 500 mg dose (two 250 mg tablets) to 36 fasted healthy male volunteers, the mean (SD) pharmacokinetic parameters were AUC 0-72 =4.3 (1.2) mcg·hr/mL; C max =0.5 (0.2) mcg/mL; T max =2.2 (0.9) hours. Two azithromycin 250 mg tablets are bioequivalent to a single 500 mg tablet. In a two-way crossover study, 12 adult healthy volunteers (6 males, 6 females) received 1500 mg of azithromycin administered in single daily doses over either 5 days (two 250 mg tablets on day 1, followed by one 250 mg tablet on days 2 to 5) or 3 days (500 mg per day for days 1 to 3).
Due to limited serum samples on day 2 (3-day regimen) and days 2 to 4 (5-day regimen), the serum concentration-time profile of each subject was fit to a 3-compartment model and the AUC 0-∞ for the fitted concentration profile was comparable between the 5-day and 3-day regimens. Table 11. Pharmacokinetic Parameters for Adult Patients Receiving a 3‑Day and 5‑Day Oral Regimen 3-Day Regimen 5-Day Regimen Pharmacokinetic Parameter [mean (SD)] Day 1 Day 3 Day 1 Day 5 C max (serum, mcg/mL) 0.44 (0.22) 0.54 (0.25) 0.43 (0.20) 0.24 (0.06) Serum AUC 0-∞ (mcg·hr/mL) 17.4 (6.2)* 14.9 (3.1)* Serum T 1/2 71.8 hr 68.9 hr *Total AUC for the entire 3-day and 5-day regimens.
Absorption The absolute bioavailability of azithromycin 250 mg capsules is 38%. In a two-way crossover study in which 12 healthy subjects received a single 500 mg dose of azithromycin (two 250 mg tablets) with or without a high fat meal, food was shown to increase C max by 23% but had no effect on AUC. When azithromycin oral suspension was administered with food to 28 adult healthy male subjects, C max increased by 56% and AUC was unchanged.
Distribution The serum protein binding of azithromycin is variable in the concentration range approximating human exposure, decreasing from 51% at 0.02 mcg/mL to 7% at 2 mcg/mL. The antibacterial activity of azithromycin is pH related and appears to be reduced with decreasing pH, However, the extensive distribution of drug to tissues may be relevant to clinical activity. Azithromycin has been shown to penetrate into human tissues, including skin, lung, tonsil, and cervix.
Extensive tissue distribution was confirmed by examination of additional tissues and fluids (bone, ejaculum, prostate, ovary, uterus, salpinx, stomach, liver, and gallbladder). As there are no data from adequate and well-controlled studies of azithromycin treatment of infections in these additional body sites, the clinical significance of these tissue concentration data is unknown. Following a regimen of 500 mg on the first day and 250 mg daily for 4 days, very low concentrations were noted in cerebrospinal fluid (less than 0.01 mcg/mL) in the presence of noninflamed meninges.
Elimination Metabo… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Azithromycin is a macrolide antibacterial drug. [see Microbiology (12.4) ]
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Azithromycin tablets, USP are supplied in the following strengths and package configurations: Azithromycin Tablets USP, 250 mg are white to off-white, modified capsule shaped, film-coated biconvex tablets, debossed with “66” on one side and “D” on other side. Bottles of 30 NDC 65862-641-30 Bottles of 50 NDC 65862-641-50 Bottles of 100 NDC 65862-641-01 Bottles of 500 NDC 65862-641-05 Carton of 6 (1X 6) Unit-dose Tablets NDC 65862-641-69 Carton of 18 (3X 6) Unit-dose Tablets NDC 65862-641-63 Azithromycin Tablets USP, 500 mg are white to off-white, oval shaped, film-coated biconvex tablets, debossed with “67” on one side and “D” on other side.
Bottles of 30 NDC 65862-642-30 Carton of 3 (1X 3) Unit-dose Tablets NDC 65862-642-64 Carton of 9 (3X 3) Unit-dose Tablets NDC 65862-642-90 Storage and Handling Store azithromycin tablets, USP at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Azithromycin tablets USP contain the active ingredient azithromycin, a macrolide antibacterial drug, for oral administration. Azithromycin has the chemical name (2R,3S,4R,5R,8R,10R,11R,12S,13S,14R)-13-[(2,6-dideoxy-3-C-methyl-3-O-methyl-α-L-ribo-hexopyranosyl)oxy]-2-ethyl-3,4,10-trihydroxy-3,5,6,8,10,12,14-heptamethyl-11-[[3,4,6-trideoxy-3-(dimethylamino)-β-D-xylo-hexopyranosyl]oxy]-1-oxa-6-azacyclopentadecan-15-one. Azithromycin is derived from erythromycin; however, it differs chemically from erythromycin in that a -methyl substituted-nitrogen atom is incorporated into the lactone ring.
Its molecular formula is C 38 H 72 N 2 O 12 , and its molecular weight is 749.00. Azithromycin has the following structural formula: Azithromycin, as the dihydrate, is a white or almost white powder with a molecular formula of C 38 H 72 N 2 O 12• 2H 2 O and a molecular weight of 785.0. Azithromycin is supplied as tablets containing azithromycin dihydrate USP equivalent to either 250 mg or 500 mg azithromycin and the following inactive ingredients: croscarmellose sodium, dibasic calcium phosphate anhydrous, hypromellose, lactose monohydrate, pregelatinized starch (maize), magnesium stearate, sodium lauryl sulfate, titanium dioxide and triacetin.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Important Administration Instructions Azithromycin tablets can be taken with or without food. Concomitant Administration with Aluminum and Magnesium Containing Antacids Advise patients not to take aluminum and magnesium containing antacids and azithromycin simultaneously.
Allergic Reactions Direct patients to discontinue azithromycin immediately and contact a physician if any signs of an allergic reaction occur [see warnings and Precautions (5.1) ]. Vomiting, Irritability, Diarrhea or Rash with Feeding in Infants Direct parents or caregivers to contact their physician if vomiting, irritability, diarrhea or rash with feeding occurs in the infant [see Warnings and Precautions (5.3) and Use in Specific Population (8.2) ]. Antibacterial Resistance Patients should be counseled that antibacterial drugs including azithromycin should only be used to treat bacterial infections.
They do not treat viral infections (e.g., the common cold). When azithromycin is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of the therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by azithromycin or other antibacterial drugs in the future.
Diarrhea Diarrhea is a common problem caused by antibacterials, including azithromycin which usually ends when the antibacterial is discontinued. Sometimes after starting treatment with antibacterials patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibacterial drug. If this occurs, patients should contact their physician as soon as possible [see Warnings and Precautions (5.6) ].
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following oral administration of a single 500 mg dose (two 250 mg tablets) to 36 fasted healthy male volunteers, the mean (SD) pharmacokinetic parameters were AUC 0-72 =4.3 (1.2) mcg·hr/mL; C max =0.5 (0.2) mcg/mL; T max =2.2 (0.9) hours. Two azithromycin 250 mg tablets are bioequivalent to a single 500 mg tablet. In a two-way crossover study, 12 adult healthy volunteers (6 males, 6 females) received 1500 mg of azithromycin administered in single daily doses over either 5 days (two 250 mg tablets on day 1, followed by one 250 mg tablet on days 2 to 5) or 3 days (500 mg per day for days 1 to 3).
Due to limited serum samples on day 2 (3-day regimen) and days 2 to 4 (5-day regimen), the serum concentration-time profile of each subject was fit to a 3-compartment model and the AUC 0-∞ for the fitted concentration profile was comparable between the 5-day and 3-day regimens. Table 11. Pharmacokinetic Parameters for Adult Patients Receiving a 3‑Day and 5‑Day Oral Regimen 3-Day Regimen 5-Day Regimen Pharmacokinetic Parameter [mean (SD)] Day 1 Day 3 Day 1 Day 5 C max (serum, mcg/mL) 0.44 (0.22) 0.54 (0.25) 0.43 (0.20) 0.24 (0.06) Serum AUC 0-∞ (mcg·hr/mL) 17.4 (6.2)* 14.9 (3.1)* Serum T 1/2 71.8 hr 68.9 hr *Total AUC for the entire 3-day and 5-day regimens.
Absorption The absolute bioavailability of azithromycin 250 mg capsules is 38%. In a two-way crossover study in which 12 healthy subjects received a single 500 mg dose of azithromycin (two 250 mg tablets) with or without a high fat meal, food was shown to increase C max by 23% but had no effect on AUC. When azithromycin oral suspension was administered with food to 28 adult healthy male subjects, C max increased by 56% and AUC was unchanged.
Distribution The serum protein binding of azithromycin is variable in the concentration range approximating human exposure, decreasing from 51% at 0.02 mcg/mL to 7% at 2 mcg/mL. The antibacterial activity of azithromycin is pH related and appears to be reduced with decreasing pH, However, the extensive distribution of drug to tissues may be relevant to clinical activity. Azithromycin has been shown to penetrate into human tissues, including skin, lung, tonsil, and cervix.
Extensive tissue distribution was confirmed by examination of additional tissues and fluids (bone, ejaculum, prostate, ovary, uterus, salpinx, stomach, liver, and gallbladder). As there are no data from adequate and well-controlled studies of azithromycin treatment of infections in these additional body sites, the clinical significance of these tissue concentration data is unknown. Following a regimen of 500 mg on the first day and 250 mg daily for 4 days, very low concentrations were noted in cerebrospinal fluid (less than 0.01 mcg/mL) in the presence of noninflamed meninges.
Elimination Metabolism In vitro and in vivo studies to assess the metabolism of azithromycin have not been performed. Excretion Plasma concentrations of azithromycin following single 500 mg oral and IV doses declined in a polyphasic pattern resulting in a mean apparent plasma clearance of 630 mL/min and terminal elimination half-life of 68 hr. The prolonged terminal half-life is thought to be due to extensive uptake and subsequent release of drug from tissues.
Biliary excretion of azithromycin, predominantly as unchanged drug, is a major route of elimination. Over the course of a week, approximately 6% of the administered dose appears as unchanged drug in urine. Specific Populations Patients with Renal Impairment Azithromycin pharmacokinetics was investigated in 42 adults (21 to 85 years of age) with varying degrees of renal impairment.
Following the oral administration of a single 1 g dose of azithromycin (4 x 250 mg capsules), mean C max and AUC 0-120 increased by 5.1% and 4.2%, respectively, in subjects with GFR 10 to 80 mL/min compared to subjects with GFR >80 mL/min. The mean C max and AUC 0-120 increased 61% and 35%, respectively, in subjects with GFR <10 mL/min compared to subj… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Based on animal models of infection, the antibacterial activity of azithromycin appears to correlate with the ratio of area under the concentration-time curve to minimum inhibitory concentration (AUC/MIC) for certain pathogens ( S. pneumoniae and S. aureus ). The principal pharmacokinetic/pharmacodynamic parameter best associated with clinical and microbiological cure has not been elucidated in clinical trials with azithromycin. Cardiac Electrophysiology QTc interval prolongation was studied in a randomized, placebo-controlled parallel trial in 116 healthy subjects who received either chloroquine (1000 mg) alone or in combination with oral azithromycin (500 mg, 1000 mg, and 1500 mg once daily).
Co-administration of azithromycin increased the QTc interval in a dose- and concentration-dependent manner. In comparison to chloroquine alone, the maximum mean (95% upper confidence bound) increases in QTcF were 5 (10) ms, 7 (12) ms and 9 (14) ms with the co-administration of 500 mg, 1000 mg and 1500 mg azithromycin, respectively.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Adult Patients
14.1Acute Bacterial Exacerbations of Chronic Bronchitis in Adult Patients In a randomized, double-blind controlled clinical trial of acute exacerbation of chronic bronchitis (AECB), azithromycin (500 mg once daily for 3 days) was compared with clarithromycin (500 mg twice daily for 10 days). The primary endpoint of this trial was the clinical cure rate at Days 21 to 24. For the 304 patients analyzed in the modified intent-to-treat analysis at the Days 21 to 24 visit, the clinical cure rate for 3 days of azithromycin was 85% (125/147) compared to 82% (129/157) for 10 days of clarithromycin.
Clinical Cure Rates at Days 21 to 24 Bacteriologically Evaluable Patients by Pathogen: Table 15. Clinical Cure Rates at Days 21 to 24 in Adult Patients with AECB by Pathogen Pathogen Azithromycin (3 Days) Clarithromycin (10 Days) S. pneumoniae 29/32 (91%) 21/27 (78%) H. influenzae 12/14 (86%) 14/16 (88%) M. catarrhalis 11/12 (92%) 12/15 (80%)
14.2Acute Bacterial Sinusitis in Adult Patients In a randomized, double-blind, double-dummy controlled clinical trial of acute bacterial sinusitis, azithromycin (500 mg once daily for 3 days) was compared with amoxicillin/clavulanate (500/125 mg three times a day for 10 days). Clinical response assessments were made at Day 10 and Day 28. The primary endpoint of this trial was prospectively defined as the clinical cure rate at Day 28.
For the 594 patients analyzed in the modified intent to treat analysis at the Day 10 visit, the clinical cure rate for 3 days of azithromycin was 88% (268/303) compared to 85% (248/291) for 10 days of amoxicillin/clavulanate. For the 586 patients analyzed in the modified intent to treat analysis at the Day 28 visit, the clinical cure rate for 3 days of azithromycin was 71.5% (213/298) compared to 71.5% (206/288), with a 97.5% confidence interval of –8.4 to 8.3, for 10 days of amoxicillin/clavulanate. In an open label, non-comparative study requiring baseline transantral sinus punctures, the following outcomes were the clinical success rates at the Day 7 and Day 28 visits for the modified intent to treat patients administered 500 mg of azithromycin once daily for 3 days with the following pathogens: Table 16.
Clinical Success Rates of Azithromycin (500 mg per day for 3 Days) on Days 7 and 10 in Adult Patients with Acute Bacterial Sinusitis by Pathogen Pathogen Day 7 Day 28 S. pneumoniae 23/26 (88%) 21/25 (84%) H. influenzae 28/32 (87%) 24/32 (75%) M. catarrhalis 14/15 (93%) 13/15 (87%) Pediatric Patients From the perspective of evaluating pediatric clinical trials, Days 11 to 14 were considered on-therapy evaluations because of the extended half-life of azithromycin. Days 11 to 14 data are provided for clinical guidance.
Days 24 to 32 evaluations were considered the primary test of cure endpoint.
14.3Pharyngitis/Tonsillitis in Pediatric Patients In three double-blind controlled studies, conducted in the United States, azithromycin (12 mg/kg once a day for 5 days) was compared to penicillin V (250 mg three times a day for 10 days) in the treatment of pharyngitis due to documented Group A β-hemolytic streptococci (GABHS or S. pyogenes ). Azithromycin was clinically and microbiologically statistically superior to penicillin at Day 14 and Day 30 with the following clinical success (i.e., cure and improvement) and bacteriologic efficacy rates (for the combined evaluable patient with documented GABHS): Table 17.
Summary of Three U.S. Studies of Azithromycin vs. Penicillin V and Clinical Success and Bacteriological Efficacy Rates at Days 14 and 30 in evaluable Pediatric Patients with Pharyngitis/Tonsilitis Day 14 Day 30 Bacteriologic Eradication: Azithromycin 323/340 (95%) 255/330 (77%) Penicillin V 242/332 (73%) 206/325 (63%) Clinical Success (cure plus improvement): Azithromycin 336/343 (98%) 310/330 (94%) Penicillin V 284/338 (84%) 241/325 (74%) Approximately 1% of azithromycin-susceptible S. pyogenes isolates were resistant to azithromycin… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long term studies in animals have not been performed to evaluate carcinogenic potential. Mutagenesis Azithromycin has shown no mutagenic potential in standard laboratory tests: mouse lymphoma assay, human lymphocyte clastogenic assay, and mouse bone marrow clastogenic assay. Impairment of Fertility In fertility studies conducted in male and female rats, oral administration of azithromycin for 64 to 66 days (males) or 15 days (females) prior to and during cohabitation resulted in decreased pregnancy rate at 20 and 30 mg/kg/day when both males and females were treated with azithromycin.
This minimal effect on pregnancy rate (approximately 12% reduction compared to concurrent controls) did not become more pronounced when the dose was increased from 20 to 30 mg/kg/day (approximately 0.4 to 0.6 times the adult daily dose of 500 mg based on body surface area) and it was not observed when only one animal in the mated pair was treated. There were no effects on any other reproductive parameters, and there were no effects on fertility at 10 mg/kg/day. The relevance of these findings to patients being treated with azithromycin at the doses and durations recommended in the prescribing information is uncertain.
13.2Animal Toxicology and/or Pharmacology Phospholipidosis (intracellular phospholipid accumulation) has been observed in some tissues of mice, rats, and dogs given multiple doses of azithromycin. It has been demonstrated in numerous organ systems (e.g., eye, dorsal root ganglia, liver, gallbladder, kidney, spleen, and/or pancreas) in dogs and rats treated with azithromycin at doses which, expressed on the basis of body surface area, are similar to or less than the highest recommended adult human dose. This effect has been shown to be reversible after cessation of azithromycin treatment.
Based on the pharmacokinetic data, phospholipidosis has been seen in the rat (50 mg/kg/day dose) at the observed maximal plasma concentration of 1.3 mcg/mL (1.6 times the observed C max of 0.821 mcg/mL at the adult dose of 2 g). Similarly, it has been shown in the dog (10 mg/kg/day dose) at the observed maximal serum concentration of 1 mcg/mL (1.2 times the observed C max of 0.821 mcg/mL at the adult dose of 2 g). Phospholipidosis was also observed in neonatal rats dosed for 18 days at 30 mg/kg/day, which is less than the pediatric dose of 60 mg/kg based on the surface area.
It was not observed in neonatal rats treated for 10 days at 40 mg/kg/day with mean maximal serum concentrations of 1.86 mcg/mL, approximately 1.5 times the C max of 1.27 mcg/mL at the pediatric dose. Phospholipidosis has been observed in neonatal dogs (10 mg/kg/day) at maximum mean whole blood concentrations of 3.54 mcg/mL, approximately 3 times the pediatric dose C max . The significance of these findings for animals and for humans is unknown.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long term studies in animals have not been performed to evaluate carcinogenic potential. Mutagenesis Azithromycin has shown no mutagenic potential in standard laboratory tests: mouse lymphoma assay, human lymphocyte clastogenic assay, and mouse bone marrow clastogenic assay. Impairment of Fertility In fertility studies conducted in male and female rats, oral administration of azithromycin for 64 to 66 days (males) or 15 days (females) prior to and during cohabitation resulted in decreased pregnancy rate at 20 and 30 mg/kg/day when both males and females were treated with azithromycin.
This minimal effect on pregnancy rate (approximately 12% reduction compared to concurrent controls) did not become more pronounced when the dose was increased from 20 to 30 mg/kg/day (approximately 0.4 to 0.6 times the adult daily dose of 500 mg based on body surface area) and it was not observed when only one animal in the mated pair was treated. There were no effects on any other reproductive parameters, and there were no effects on fertility at 10 mg/kg/day. The relevance of these findings to patients being treated with azithromycin at the doses and durations recommended in the prescribing information is uncertain.
📄 Patient Package Insert ▾
Patient Information Azithromycin (ay zith'' roe mye' sin) Tablets, USP Read this Patient Information leaflet before you start taking azithromycin tablets and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or your treatment.
What are azithromycin tablets? Azithromycin tablets are macrolide antibiotic prescription medicine used in adults 18 years of age or older to treat certain infections caused by certain germs called bacteria. These bacterial infections include: acute worsening of chronic bronchitis acute sinus infection community-acquired pneumonia infected throat or tonsils skin infections infections of the urethra or cervix genital ulcers in men Azithromycin tablets are used in children 6 months of age and older to treat: ear infections community-acquired pneumonia Azithromycin tablets are used in children 2 years of age and older to treat: infected throat or tonsils Azithromycin tablets are not recommended for use in people who cannot tolerate oral medicines because they are very ill or have certain other risk factors including: have cystic fibrosis have hospital acquired infections have known or suspected bacteria in the blood (bacterial infection in the blood) need to be in the hospital are elderly have any medical problems that can lower the ability of the immune system to fight infections Azithromycin tablets are not for viral infections such as the common cold.
It is not known if azithromycin tablets are safe and effective for genital ulcers in women. It is not known if azithromycin tablets are safe and effective for ear infections, sinus infections and community-acquired pneumonia in children under 6 months of age. It is not known if azithromycin tablets are safe and effective for infected throat or tonsils in children under 2 years of age.
Who should not take azithromycin tablets? Do not take azithromycin tablets if you: have had a severe allergic reaction to certain antibiotics known as macrolides or ketolides including azithromycin and erythromycin. have a history of cholestatic jaundice or hepatic dysfunction that happened with the use of azithromycin. What should I tell my healthcare provider before taking azithromycin tablets?
Before you take azithromycin tablets, tell your healthcare provider about all your medical conditions including if you: have pneumonia. have cystic fibrosis. have known or suspected bacteremia (bacterial infection in the blood). have liver or kidney problems. have heart problems, including a slow or irregular heartbeat, a heart problem called “QT prolongation”, or heart failure. have a problem that causes muscle weakness (myasthenia gravis). are pregnant or plan to become pregnant. It is not known if azithromycin tablets will harm your unborn baby. are breastfeeding or plan to breastfeed.
Azithromycin can pass into breast milk. Talk to your healthcare provider about the best way to feed your baby while you take azithromycin tablets. Contact your healthcare provider immediately if you are breastfeeding a young child (less than 6 weeks of age) and he or she vomits, has diarrhea, develops a rash, or becomes irritable when fed.
Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. Azithromycin tablets and other medicines may affect each other causing side effects. Azithromycin tablets may affect the way other medicines work, and other medicines may affect how azithromycin tablets work.
Especially tell your healthcare provider if you take: nelfinavir a blood thinner (warfarin) digoxin colchicine phenytoin an antacid that contains aluminum or magnesium Know the medicines you take. Keep a list of your medicines and show it to your healthcare provider and pharmacist when you get a new medicine. How should I take azithromycin tablets?
Take azithromycin tablets exactly as your healt… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg (30 Tablets Bottle) NDC 65862-641-30 Rx only Azithromycin Tablets, USP 250 mg AUROBINDO 30 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg (30 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg (1 x 6) Unit-dose Tablets NDC 65862-641-69 Rx only Azithromycin Tablets, USP 250 mg A full course of antibiotic therapy in 5 daily doses AUROBINDO 6 Tablets (1 Blister x Six 250 mg Tablets ) PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg (1 x 6) Unit-dose Tablets
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg (3 x 6) Unit-dose Tablets NDC 65862-641-63 Rx only Azithromycin Tablets, USP 250 mg A full course of antibiotic therapy in 5 daily doses AUROBINDO 18 Tablets (3 Cartons x Six 250 mg Tablets) PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg (3 x 6) Unit-dose Tablets
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 500 mg (30 Tablets Bottle) NDC 65862-642-30 Rx only Azithromycin Tablets, USP 500 mg AUROBINDO 30 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 500 mg (30 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 500 mg 3 Tablets (1 Blister x Three 500 mg Tablets) NDC 65862-642-64 Rx only Azithromycin Tablets, USP 500 mg A full course of antibiotic therapy in 3 daily doses. AUROBINDO 3 Tablets (1 Blister x Three 500 mg Tablets) PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 500 mg 3 Tablets (1 Blister x Three 500 mg Tablets)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 500 mg 9 Tablets (3 Cartons x Three 500 mg Tablets) NDC 65862-642-90 Rx only Azithromycin Tablets, USP 500 mg A full course of antibiotic therapy in 3 daily doses. AUROBINDO 9 Tablets (3 Cartons x Three 500 mg Tablets ) PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 500 mg 9 Tablets (3 Cartons x Three 500 mg Tablets)