
Cefixime 100 mg/5mL Powder, For Suspension, 100 mL — NDC 65862-751-01 (Billing 65862-0751-01)
This is a package of 100 mL of Cefixime 100 mg/5mL Powder, For Suspension from Aurobindo Pharma Limited, marketed since Apr 2015 and currently FDA-listed.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 009182
- GCN: 33120
- GPI-14 (Medi-Span): 02300060001910
- HICL (First Databank): 003999
- AHFS class code: 08:12.06.12
- RxCUI (RxNorm): 309058
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Cephalosporin Antibacterial class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Cefixime is used to treat certain infections caused by bacteria. Cefixime is in a class of medications called cephalosporin antibiotics. It works by killing bacteria. Antibiotics such as cefixime will not work for colds, flu, or other viral infections. Using antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- It is an antibiotic for certain bacterial infections: urinary tract infections, throat and tonsil infections, flare-ups of chronic bronchitis, and uncomplicated gonorrhea. Capsules...
- Take it by mouth, usually once a day or split into two doses, exactly as prescribed. Tablets and capsules can be taken with or without food. Finish the full course, which is at lea...
- Stomach upset is the most common: diarrhea, nausea, loose stools, belly pain, and gas. Call your doctor if diarrhea is severe or lasts, since it can sometimes signal a C. difficile...
- Tell me and your prescriber before starting. Cross-allergy between penicillins and cephalosporins can happen in up to 10% of people with a penicillin allergy. Don't take cefixime i...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cefixime — tap one for details:
Cefixime may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $2.24 | $224.35 / 100 ml |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 65862-0751-01 You're viewing this | 100 mL in 1 BOTTLE | — | — | 2015-04-14 | — | Active |
| 65862-0751-50 65862-751-50 Main listing | 50 mL in 1 BOTTLE | $2.44 / mL | $122.15 | 2015-04-14 | — | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack shows little to no recent Medicaid volume — the 50 ml pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 65862-0751-50?
What NDC number is used to bill for this package of Cefixime 100 mg/5mL Powder, For Suspension?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cefixime 100 mg/5mLthis 65862-0751-01 | Aurobindo | 100 ml | — | AB | FDA listed | — |
| Cefixime 100 mg/5mL 68180-0405-01 | Lupin | 50 ml | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 4J2TY8Y81V
A natural flavoring derived from strawberries that gives the medicine its strawberry taste and smell. It helps make the medicine more pleasant to take, especially for children.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII TTV12P4NEE
Xanthan gum is a thickening and stabilizing ingredient made from fermented corn or other sugars. It's added to medicines to improve texture, prevent separation of liquids and solids, and help the product stay consistent.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Cefixime for oral suspension is a cephalosporin antibacterial drug indicated in the treatment of adults and pediatric patients six months and older with the following infections: Uncomplicated Urinary Tract Infections (1.1) Otitis Media (1.2) Pharyngitis and Tonsillitis (1.3) Acute Exacerbations of Chronic Bronchitis (1.4) Uncomplicated Gonorrhea (cervical/urethral) (1.5) To reduce the development of drug-resistant bacteria and maintain the effectiveness of cefixime for oral suspension and other antibacterial drugs, cefixime for oral suspension should be used only to treat infections that are proven or strongly suspected to be caused by bacteria.
(1.6)
1.1Uncomplicated Urinary Tract Infections Cefixime for oral suspension is indicated in the treatment of adults and pediatric patients six months of age or older with uncomplicated urinary tract infections caused by susceptible isolates of Escherichia coli and Proteus mirabilis .
1.2Otitis Media Cefixime for oral suspension is indicated in the treatment of adults and pediatric patients six months of age or older with otitis media caused by susceptible isolates of Haemophilus influenzae , Moraxella catarrhalis , and Streptococcus pyogenes. (Efficacy for Streptococcus pyogenes in this organ system was studied in fewer than 10 infections.) Note: For patients with otitis media caused by Streptococcus pneumoniae , overall response was approximately 10% lower for cefixime than for the comparator [see Clinical Studies (14) ].
1.3Pharyngitis and Tonsillitis Cefixime for oral suspension is indicated in the treatment of adults and pediatric patients six months of age or older with pharyngitis and tonsillitis caused by susceptible isolates of Streptococcus pyogenes. (Note: Penicillin is the usual drug of choice in the treatment of Streptococcus pyogenes infections. Cefixime for oral suspension is generally effective in the eradication of Streptococcus pyogenes from the nasopharynx; however, data establishing the efficacy of cefixime for oral suspension in the subsequent prevention of rheumatic fever is not available.)
1.4Acute Exacerbations of Chronic Bronchitis Cefixime for oral suspension is indicated in the treatment of adults and pediatric patients six months of age or older with acute exacerbations of chronic bronchitis caused by susceptible isolates of Streptococcus pneumoniae and Haemophilus influenzae.
1.5Uncomplicated Gonorrhea (cervical/urethral) Cefixime for oral suspension is indicated in the treatment of adults and pediatric patients six months of age or older with uncomplicated gonorrhea (cervical/urethral) caused by susceptible isolates of Neisseria gonorrhoeae (penicillinase-and non-penicillinase-producing isolates).
1.6Usage To reduce the development of drug resistant bacteria and maintain the effectiveness of cefixime for oral suspension and other antibacterial drugs, cefixime for oral suspension should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antimicrobial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adults: 400 mg daily (2.1) Pediatric patients (6 months and older): 8 mg/kg/day (2.2)
2.1Adults The recommended dose of cefixime is 400 mg daily. This may be given as a 400 mg tablet or capsule daily or the 400 mg tablet may be split and given as one half tablet every 12 hours. For the treatment of uncomplicated cervical/urethral gonococcal infections, a single oral dose of 400 mg is recommended.
The capsule and tablet may be administered without regard to food. In the treatment of infections due to Streptococcus pyogenes , a therapeutic dosage of cefixime should be administered for at least 10 days.
2.2Pediatric Patients (6 months or older) The recommended dose is 8 mg/kg/day of the suspension. This may be administered as a single daily dose or may be given in two divided doses, as 4 mg/kg every 12 hours. Note: A suggested dose has been determined for each pediatric weight range.
Refer to Table 1. Ensure all orders that specify a dose in milliliters include a concentration, because cefixime for oral suspension is available in three different concentrations (100 mg/5 mL, 200 mg/5 mL, and 500 mg/5 mL). Table 1.
Suggested doses for pediatric patients * The preferred concentrations of oral suspension to use are 100 mg/5 mL or 200 mg/5 mL for pediatric patients in these weight ranges. PEDIATRIC DOSAGE CHART Doses are suggested for each weight range and rounded for ease of administration Cefixime for oral suspension Cefixime chewable tablet 100 mg/5 mL 200 mg/5 mL 500 mg/5 mL Patient Weight (kg) Dose/Day (mg) Dose/Day (mL) Dose/Day (mL) Dose/Day (mL) Dose 5 to 7.5* 50 2.5 -- -- -- 7.6 to 10* 80 4 2 -- -- 10.1 to 12.5 100 5 2.5 1 1 tablet of 100 mg 12.6 to 20.5 150 7.5 4 1.5 1 tablet of 150 mg 20.6 to 28 200 10 5 2 1 tablet of 200 mg 28.1 to 33 250 12.5 6 2.5 1 tablet of 100 mg and 1 tablet of 150 mg 33.1 to 40 300 15 7.5 3 2 tablets of 150 mg 40.1 to 45 350 17.5 9 3.5 1 tablet of 150 mg and 1 tablet of 200 mg 45.1 or greater 400 20 10 4 2 tablets of 200 mg Children weighing more than 45 kg or older than 12 years should be treated with the recommended adult dose.
Cefixime chewable tablets must be chewed or crushed before swallowing. Otitis media should be treated with the chewable tablets or suspension. Clinical trials of otitis media were conducted with the chewable tablets or suspension, and the chewable tablets or suspension results in higher peak blood levels than the tablet when administered at the same dose.
Therefore, the tablet or capsule should not be substituted for the chewable tablets or suspension in the treatment of otitis media [see Clinical Pharmacology (12.3) ]. In the treatment of infections due to Streptococcus pyogenes , a therapeutic dosage of cefixime should be administered for at least 10 days.
2.3Renal Impairment Cefixime for oral suspension may be administered in the presence of impaired renal function. Normal dose and schedule may be employed in patients with creatinine clearances of 60 mL/min or greater. Refer to Table 2 for dose adjustments for adults with renal impairment.
Neither hemodialysis nor peritoneal dialysis removes significant amounts of drug from the body. Table 2. Doses for Adults with Renal Impairment * The preferred concentrations of oral suspension to use are 200 mg/5 mL or 500 mg/5 mL for patients with this renal dysfunction Renal Dysfunction Cefixime for oral suspension Tablet Chewable Tablet Creatinine Clearance (mL/min) 100 mg/5 mL 200 mg/5 mL 500 mg/5 mL 400 mg 200 mg Dose/Day (mL) Dose/Day (mL) Dose/Day (mL) Dose/Day Dose/Day 60 or greater Normal dose Normal dose Normal dose Normal dose Normal dose 21 to 59* OR renal hemodialysis* 13 6.5
2.6Not Appropriate Not Appropriate 20 or less OR continuous peritoneal dialysis 8.6 4.4 1.8 0.5 tablet 1 tablet
2.4Reconstitution Directions for Oral Suspension Strength Bottle Size Reconstitution Directions 100 mg/5 mL 100 mL To reconstitute, suspend with 70 mL water . Method: Tap the bottle several times to loosen p… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Cefixime is available for oral administration in the following strengths: Powder for oral suspension, when reconstituted, provides either 100 mg/5 mL or 200 mg/5 mL of cefixime as trihydrate. The powder has an off-white to pale yellow color and is strawberry flavored. Oral Suspension: 100 mg/5 mL and 200 mg/5 mL (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Cefixime for oral suspension is contraindicated in patients with known allergy to cefixime or other cephalosporins. Contraindicated in patients with known allergy to cefixime or other cephalosporins. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity reactions including shock and fatalities have been reported with cefixime. Discontinue use if a reaction occurs. (5.1) Clostridium difficile associated diarrhea: Evaluate if diarrhea occurs. (5.2)
5.1Hypersensitivity Reactions Anaphylactic/anaphylactoid reactions (including shock and fatalities) have been reported with the use of cefixime. Before therapy with cefixime is instituted, careful inquiry should be made to determine whether the patient has had previous hypersensitivity reactions to cephalosporins, penicillins, or other drugs. If this product is to be given to penicillin-sensitive patients, caution should be exercised because cross hypersensitivity among beta-lactam antibacterial drugs has been clearly documented and may occur in up to 10% of patients with a history of penicillin allergy.
If an allergic reaction to cefixime occurs, discontinue the drug.
5.2Clostridium difficile -Associated Diarrhea Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including cefixime, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile. C. difficile produces toxins A and B which contribute to the development of CDAD.
Hypertoxin producing isolates of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibacterial drug use. Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents.
If CDAD is suspected or confirmed, ongoing antibacterial drug use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibacterial drug treatment of C. difficile, and surgical evaluation should be instituted as clinically indicated.
5.3Dose Adjustment in Renal Impairment The dose of cefixime should be adjusted in patients with renal impairment as well as those undergoing continuous ambulatory peritoneal dialysis (CAPD) and hemodialysis (HD). Patients on dialysis should be monitored carefully [see Dosage and Administration (2) ] .
5.4Coagulation Effects Cephalosporins, including cefixime, may be associated with a fall in prothrombin activity. Those at risk include patients with renal or hepatic impairment, or poor nutritional state, as well as patients receiving a protracted course of antimicrobial therapy, and patients previously stabilized on anticoagulant therapy. Prothrombin time should be monitored in patients at risk and exogenous vitamin K administered as indicated.
5.5Development of Drug-Resistant Bacteria Prescribing cefixime in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions are gastrointestinal such as diarrhea (16%), nausea (7%), loose stools (6%), abdominal pain (3%), dyspepsia (3%), and vomiting. (6) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/m edwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The most commonly seen adverse reactions in U.S. trials of the tablet formulation were gastrointestinal events, which were reported in 30% of adult patients on either the twice daily or the once daily regimen. Five percent (5%) of patients in the U.S. clinical trials discontinued therapy because of drug-related adverse reactions.
Individual adverse reactions included diarrhea 16%, loose or frequent stools 6%, abdominal pain 3%, nausea 7%, dyspepsia 3%, and flatulence 4%. The incidence of gastrointestinal adverse reactions, including diarrhea and loose stools, in pediatric patients receiving the suspension was comparable to the incidence seen in adult patients receiving tablets.
6.2Post-marketing Experience The following adverse reactions have been reported following the post-approval use of cefixime. Incidence rates were less than 1 in 50 (less than 2%). Gastrointestinal Several cases of documented pseudomembranous colitis were identified in clinical trials.
The onset of pseudomembranous colitis symptoms may occur during or after therapy. Hypersensitivity Reactions Anaphylactic/anaphylactoid reactions (including shock and fatalities), skin rashes, urticaria, drug fever, pruritus, angioedema, and facial edema. Erythema multiforme, Stevens-Johnson syndrome, and serum sickness-like reactions have been reported.
Hepatic Transient elevations in SGPT, SGOT, alkaline phosphatase, hepatitis, jaundice. Renal Transient elevations in BUN or creatinine, acute renal failure. Central Nervous System Headaches, dizziness, seizures.
Hemic and Lymphatic System Transient thrombocytopenia, leukopenia, neutropenia, prolongation in prothrombin time, elevated LDH, pancytopenia, agranulocytosis, and eosinophilia. Abnormal Laboratory Tests Hyperbilirubinemia. Other Adverse Reactions Genital pruritus, vaginitis, candidiasis, toxic epidermal necrolysis.
Adverse Reactions Reported for Cephalosporin-class Drugs Allergic reactions, superinfection, renal dysfunction, toxic nephropathy, hepatic dysfunction including cholestasis, aplastic anemia, hemolytic anemia, hemorrhage, and colitis. Several cephalosporins have been implicated in triggering seizures, particularly in patients with renal impairment when the dosage was not reduced [see Dosage and Administration (2) and Overdosage (10) ] . If seizures associated with drug therapy occur, the drug should be discontinued.
Anticonvulsant therapy can be given if clinically indicated.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Elevated carbamazepine levels have been reported in postmarketing experience when cefixime is administered concomitantly. (7.1) Increased prothrombin time, with or without clinical bleeding, has been reported when cefixime is administered concomitantly with warfarin and anticoagulants. (7.2)
7.1Carbamazepine Elevated carbamazepine levels have been reported in postmarketing experience when cefixime is administered concomitantly. Drug monitoring may be of assistance in detecting alterations in carbamazepine plasma concentrations.
7.2Warfarin and Anticoagulants Increased prothrombin time, with or without clinical bleeding, has been reported when cefixime is administered concomitantly.
7.3Drug/Laboratory Test Interactions A false-positive reaction for ketones in the urine may occur with tests using nitroprusside but not with those using nitroferricyanide. The administration of cefixime may result in a false-positive reaction for glucose in the urine using Clinitest ®** , Benedict’s solution, or Fehling’s solution. It is recommended that glucose tests based on enzymatic glucose oxidase reactions (such as Clinistix ®** or TesTape ®** ) be used.
A false-positive direct Coombs test has been reported during treatment with other cephalosporins; therefore, it should be recognized that a positive Coombs test may be due to the drug. ** Clinitest ® and Clinistix ® are registered trademarks of Ames Division, Miles Laboratories, Inc. Tes-Tape ® is a registered trademark of Eli Lilly and Company.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pediatric Use: Efficacy and safety in infants younger than 6 months of age have not been established. ( 8.4 ) Geriatric Use: Clinical studies did not include sufficient numbers of subjects aged 65 and older to determine whether they respond differently than younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
( 8.5 ) Renal Impairment: Cefixime may be administered in the presence of impaired renal function. Dose adjustment is required in patients whose creatinine clearance is less than 60 mL/min. ( 8.6 )
8.1Pregnancy Risk Summary Available data from published observational studies, case series, and case reports over several decades with cephalosporin use, including cefixime, in pregnant women have not established drug-associated risks of major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data) . Reproduction studies have been performed in mice and rats at doses equivalent to 40 and 80 times, respectively, the adult human recommended dose and have revealed no evidence of harm to the fetus due to cefixime (see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Maternal gonorrhea may be associated with preterm birth, low neonatal birth weight, chorioamnionitis, intrauterine growth restriction, small for gestational age and premature rupture of membranes. Perinatal transmission of gonorrhea to the offspring can result in infant blindness, joint infections, and bloodstream infections. Data Human Data While available studies cannot definitively establish the absence of risk, published data from prospective cohort studies, case series, and case reports over several decades have not identified a consistent association with cephalosporin use, including cefixime, during pregnancy, and major birth defects, miscarriage, or other adverse maternal or fetal outcomes.
Available studies have methodological limitations, including small sample size, retrospective data collection, and inconsistent comparator groups. Animal data The results of embryo-fetal development studies in mice and rats show that cefixime, at doses up to 3200 mg/kg/day administered during the period of organogenesis did not adversely affect development. In these studies, in mice and rats, cefixime did not affect postnatal development or reproductive capacity of the F 1 generation or fetal development of the F 2 generation.
In an embryo-fetal development study in rabbits, cefixime at doses of 3.2, 10 or 32 mg/kg given daily during the period of organogenesis (gestation days 6 through 18) resulted in abortions and/or maternal deaths at doses > 10 mg/kg (typically associated with the administration of antibiotics in this species), but no malformations were reported at lower doses. A pre- and post-natal development study of cefixime at oral doses up to 3200 mg/kg/day in rats demonstrated no effect on the duration of pregnancy, process of parturition, development and viability of offspring, or reproductive capacity of the F 1 generation and development of their fetuses (F 2 ).
8.2Lactation Risk Summary There are no available data on the presence of cefixime in human milk, the effects on the breastfed infant, or the effects on milk production. Cefixime is present in animal milk (see Data) . When a drug is present in animal milk, it is likely the drug will be present in human milk.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for cefixime and any potential adverse effec… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from published observational studies, case series, and case reports over several decades with cephalosporin use, including cefixime, in pregnant women have not established drug-associated risks of major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data) . Reproduction studies have been performed in mice and rats at doses equivalent to 40 and 80 times, respectively, the adult human recommended dose and have revealed no evidence of harm to the fetus due to cefixime (see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Maternal gonorrhea may be associated with preterm birth, low neonatal birth weight, chorioamnionitis, intrauterine growth restriction, small for gestational age and premature rupture of membranes. Perinatal transmission of gonorrhea to the offspring can result in infant blindness, joint infections, and bloodstream infections. Data Human Data While available studies cannot definitively establish the absence of risk, published data from prospective cohort studies, case series, and case reports over several decades have not identified a consistent association with cephalosporin use, including cefixime, during pregnancy, and major birth defects, miscarriage, or other adverse maternal or fetal outcomes.
Available studies have methodological limitations, including small sample size, retrospective data collection, and inconsistent comparator groups. Animal data The results of embryo-fetal development studies in mice and rats show that cefixime, at doses up to 3200 mg/kg/day administered during the period of organogenesis did not adversely affect development. In these studies, in mice and rats, cefixime did not affect postnatal development or reproductive capacity of the F 1 generation or fetal development of the F 2 generation.
In an embryo-fetal development study in rabbits, cefixime at doses of 3.2, 10 or 32 mg/kg given daily during the period of organogenesis (gestation days 6 through 18) resulted in abortions and/or maternal deaths at doses > 10 mg/kg (typically associated with the administration of antibiotics in this species), but no malformations were reported at lower doses. A pre- and post-natal development study of cefixime at oral doses up to 3200 mg/kg/day in rats demonstrated no effect on the duration of pregnancy, process of parturition, development and viability of offspring, or reproductive capacity of the F 1 generation and development of their fetuses (F 2 ).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of cefixime in pediatric patients younger than 6 months of age have not been established. The incidence of gastrointestinal adverse reactions, including diarrhea and loose stools, in the pediatric patients receiving the suspension, was comparable to the incidence seen in adult patients receiving tablets.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies did not include sufficient numbers of subjects aged 65 and older to determine whether they respond differently than younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. A pharmacokinetic study in the elderly detected differences in pharmacokinetic parameters [see Clinical Pharmacology (12.3) ] .
These differences were small and do not indicate a need for dosage adjustment of the drug in the elderly.
🆘 Overdosage ▾
10 OVERDOSAGE Gastric lavage may be indicated; otherwise, no specific antidote exists. Cefixime is not removed in significant quantities from the circulation by hemodialysis or peritoneal dialysis. Adverse reactions in small numbers of healthy adult volunteers receiving single doses up to 2 g of cefixime did not differ from the profile seen in patients treated at the recommended doses.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Cefixime is a semisynthetic cephalosporin antibacterial drug [see Microbiology (12.4) ].
12.3Pharmacokinetics Cefixime chewable tablets are bioequivalent to oral suspension. Cefixime tablets and suspension, given orally, are about 40% to 50% absorbed whether administered with or without food; however, time to maximal absorption is increased approximately 0.8 hours when administered with food. A single 200 mg tablet of cefixime produces an average peak serum concentration of approximately 2 mcg/mL (range 1 to 4 mcg/mL); a single 400 mg tablet produces an average peak concentration of approximately 3.7 mcg/mL (range 1.3 to 7.7 mcg/mL).
The oral suspension produces average peak concentrations approximately 25% to 50% higher than the tablets, when tested in normal adult volunteers. Two hundred and 400 mg doses of oral suspension produce average peak concentrations of 3 mcg/mL (range 1 to 4.5 mcg/mL) and 4.6 mcg/mL (range 1.9 to 7.7 mcg/mL), respectively, when tested in normal adult volunteers. The area under the time versus concentration curve (AUC) is greater by approximately 10% to 25% with the oral suspension than with the tablet after doses of 100 to 400 mg, when tested in normal adult volunteers.
This increased absorption should be taken into consideration if the oral suspension is to be substituted for the tablet. Because of the lack of bioequivalence, tablets should not be substituted for oral suspension in the treatment of otitis media [see Dosage and Administration (2) ]. Cross-over studies of tablet versus suspension have not been performed in children.
The 400 mg capsule is bioequivalent to the 400 mg tablet under fasting conditions. However, food reduces the absorption following administration of the capsule by approximately 15% based on AUC and 25% based on C max . Peak serum concentrations occur between 2 and 6 hours following oral administration of a single 200 mg tablet, a single 400 mg tablet or 400 mg of cefixime suspension.
Peak serum concentrations occur between 2 and 5 hours following a single administration of 200 mg of suspension. Peak serum concentrations occur between 3 and 8 hours following oral administration of a single 400 mg capsule. Distribution Serum protein binding is concentration independent with a bound fraction of approximately 65%.
In a multiple dose study conducted with a research formulation which is less bioavailable than the tablet or suspension, there was little accumulation of drug in serum or urine after dosing for 14 days. Adequate data on CSF levels of cefixime are not available. Metabolism and Excretion There is no evidence of metabolism of cefixime in vivo.
Approximately 50% of the absorbed dose is excreted unchanged in the urine in 24 hours. In animal studies, it was noted that cefixime is also excreted in the bile in excess of 10% of the administered dose. The serum half-life of cefixime in healthy subjects is independent of dosage form and averages 3 to 4 hours but may range up to 9 hours in some normal volunteers.
Special Populations Geriatrics : Average AUCs at steady state in elderly patients are approximately 40% higher than average AUCs in other healthy adults. Differences in the pharmacokinetic parameters between 12 young and 12 elderly subjects who received 400 mg of cefixime once daily for 5 days are summarized as follows: * Difference between age groups was significant. (p<0.05) Pharmacokinetic Parameters (mean ± SD) for Cefixime in Both Young & Elderly Subjects Pharmacokinetic parameter Young Elderly C max (mg/L) 4.74 ± 1.43 5.68 ±
1.83T max (h)* 3.9 ± 0.3 4.3 ±
0.6AUC (mg.h/L)* 34.9 ± 12.2 49.5 ±
19.1T ½ (h)* 3.5 ± 0.6 4.2 ±
0.4C ave (mg/L)* 1.42 ± 0.5 1.99 ±
0.75However, these increases were not clinically significant [see Dosage and Administration (2) ]. Renal Impairment: In subjects with moderate impairment of renal function (20 to 40 mL/min creatinine clearance), the average serum half-life of cefixime is prol… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Cefixime is a semisynthetic cephalosporin antibacterial drug [see Microbiology (12.4) ].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Cefixime for oral suspension USP 100 mg/5 mL is off-white to pale yellow colored powder - Each 5 mL of reconstituted off-white to pale yellow, strawberry flavored suspension contains cefixime trihydrate equivalent to 100 mg cefixime. 50 mL Bottles NDC 65862-751-50 100 mL Bottles NDC 65862-751-01 Cefixime for oral suspension USP 200 mg/5 mL is off-white to pale yellow colored powder - Each 5 mL of reconstituted off-white to pale yellow, strawberry flavored suspension contains cefixime trihydrate equivalent to 200 mg cefixime.
50 mL Bottles NDC 65862-752-50 75 mL Bottles NDC 65862-752-75 Storage Prior to Reconstitution : Store drug powder at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. After Reconstitution : Store at room temperature or under refrigeration. Shake well before using.
Discard unused portion after 14 days. Keep tightly closed.
📋 Description ▾
11 DESCRIPTION Cefixime is a semisynthetic, cephalosporin antibacterial for oral administration. Chemically, it is ( 6R,7R )-7-[2-(2-Amino-4-thiazolyl)glyoxylamido]-8-oxo-3-vinyl-5-thia-1-azabicyclo [4.2.0] oct-2-ene-2-carboxylic acid, 7 2 -( Z )-[ O -(carboxy methyl) oxime] trihydrate. Molecular weight = 507.50 as the trihydrate.
Chemical Formula is C 16 H 15 N 5 O 7 S 2 .3H 2 O. The structural formula for cefixime is: Inactive ingredients contained in cefixime powder for oral suspension USP are: colloidal silicon dioxide, strawberry guarana flavor, sucrose, and xanthan gum. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Drug Resistance Patients should be counseled that antibacterial drugs, including cefixime, should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When cefixime is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may: (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by cefixime for oral suspension or other antibacterial drugs in the future. Diarrhea Advise patients that diarrhea is a common problem caused by antibacterial drugs which usually ends when the antibacterial drug is discontinued. Sometimes after starting treatment with antibacterial drugs, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibacterial drug.
If this occurs, patients should contact their physician as soon as possible. Distributed by: Aurobindo Pharma USA, Inc . 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 10/2021
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Cefixime chewable tablets are bioequivalent to oral suspension. Cefixime tablets and suspension, given orally, are about 40% to 50% absorbed whether administered with or without food; however, time to maximal absorption is increased approximately 0.8 hours when administered with food. A single 200 mg tablet of cefixime produces an average peak serum concentration of approximately 2 mcg/mL (range 1 to 4 mcg/mL); a single 400 mg tablet produces an average peak concentration of approximately 3.7 mcg/mL (range 1.3 to 7.7 mcg/mL).
The oral suspension produces average peak concentrations approximately 25% to 50% higher than the tablets, when tested in normal adult volunteers. Two hundred and 400 mg doses of oral suspension produce average peak concentrations of 3 mcg/mL (range 1 to 4.5 mcg/mL) and 4.6 mcg/mL (range 1.9 to 7.7 mcg/mL), respectively, when tested in normal adult volunteers. The area under the time versus concentration curve (AUC) is greater by approximately 10% to 25% with the oral suspension than with the tablet after doses of 100 to 400 mg, when tested in normal adult volunteers.
This increased absorption should be taken into consideration if the oral suspension is to be substituted for the tablet. Because of the lack of bioequivalence, tablets should not be substituted for oral suspension in the treatment of otitis media [see Dosage and Administration (2) ]. Cross-over studies of tablet versus suspension have not been performed in children.
The 400 mg capsule is bioequivalent to the 400 mg tablet under fasting conditions. However, food reduces the absorption following administration of the capsule by approximately 15% based on AUC and 25% based on C max . Peak serum concentrations occur between 2 and 6 hours following oral administration of a single 200 mg tablet, a single 400 mg tablet or 400 mg of cefixime suspension.
Peak serum concentrations occur between 2 and 5 hours following a single administration of 200 mg of suspension. Peak serum concentrations occur between 3 and 8 hours following oral administration of a single 400 mg capsule. Distribution Serum protein binding is concentration independent with a bound fraction of approximately 65%.
In a multiple dose study conducted with a research formulation which is less bioavailable than the tablet or suspension, there was little accumulation of drug in serum or urine after dosing for 14 days. Adequate data on CSF levels of cefixime are not available. Metabolism and Excretion There is no evidence of metabolism of cefixime in vivo.
Approximately 50% of the absorbed dose is excreted unchanged in the urine in 24 hours. In animal studies, it was noted that cefixime is also excreted in the bile in excess of 10% of the administered dose. The serum half-life of cefixime in healthy subjects is independent of dosage form and averages 3 to 4 hours but may range up to 9 hours in some normal volunteers.
Special Populations Geriatrics : Average AUCs at steady state in elderly patients are approximately 40% higher than average AUCs in other healthy adults. Differences in the pharmacokinetic parameters between 12 young and 12 elderly subjects who received 400 mg of cefixime once daily for 5 days are summarized as follows: * Difference between age groups was significant. (p<0.05) Pharmacokinetic Parameters (mean ± SD) for Cefixime in Both Young & Elderly Subjects Pharmacokinetic parameter Young Elderly C max (mg/L) 4.74 ± 1.43 5.68 ±
1.83T max (h)* 3.9 ± 0.3 4.3 ±
0.6AUC (mg.h/L)* 34.9 ± 12.2 49.5 ±
19.1T ½ (h)* 3.5 ± 0.6 4.2 ±
0.4C ave (mg/L)* 1.42 ± 0.5 1.99 ±
0.75However, these increases were not clinically significant [see Dosage and Administration (2) ]. Renal Impairment: In subjects with moderate impairment of renal function (20 to 40 mL/min creatinine clearance), the average serum half-life of cefixime is prolonged to 6.4 hours. In severe renal impairment (5 to 20 mL/min creatinine clearance), the half-life increased to an average of 11.5 hours.… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Comparative clinical trials of otitis media were conducted in nearly 400 children between the ages of 6 months to 10 years. Streptococcus pneumoniae was isolated from 47% of the patients, Haemophilus influenzae from 34%, Moraxella catarrhalis from 15% and S. pyogenes from 4%. The overall response rate of Streptococcus pneumoniae to cefixime was approximately 10% lower and that of Haemophilus influenzae or Moraxella catarrhalis approximately 7% higher (12% when beta-lactamase positive isolates of H. influenzae are included) than the response rates of these organisms to the active control drugs.
In these studies, patients were randomized and treated with either cefixime at dose regimens of 4 mg/kg twice a day or 8 mg/kg once a day, or with a comparator. Sixty-nine to 70% of the patients in each group had resolution of signs and symptoms of otitis media when evaluated 2 to 4 weeks post-treatment, but persistent effusion was found in 15% of the patients. When evaluated at the completion of therapy, 17% of patients receiving cefixime and 14% of patients receiving effective comparative drugs (18% including those patients who had Haemophilus influenzae resistant to the control drug and who received the control antibacterial drug) were considered to be treatment failures.
By the 2 to 4 week follow-up, a total of 30% to 31% of patients had evidence of either treatment failure or recurrent disease. (a) Number eradicated/number isolated. (b) An additional 20 beta-lactamase positive isolates of Haemophilus influenzae were isolated, but were excluded from this analysis because they were resistant to the control antibacterial drug.
In nineteen of these, the clinical course could be assessed and a favorable outcome occurred in 10. When these cases are included in the overall bacteriological evaluation of therapy with the control drugs, 140/185 (76%) of pathogens were considered to be eradicated. Bacteriological Outcome of Otitis Media at Two to Four Weeks Post-Therapy Based on Repeat Middle Ear Fluid Culture or Extrapolation from Clinical Outcome Organism Cefixime(a) 4 mg/kg BID Cefixime(a) 8 mg/kg QD Control(a) drugs Streptococcus pneumoniae 48/70 (69%) 18/22 (82%) 82/100 (82%) Haemophilus influenzae beta-lactamase negative 24/34 (71%) 13/17 (76%) 23/34 (68%) Haemophilus influenzae beta-lactamase positive 17/22 (77%) 9/12 (75%) 1/1 (b) Moraxella catarrhalis 26/31 (84%) 5/5 18/24 (75%) S. pyogenes 5/5 3/3 6/7 All Isolates 120/162 (74%) 48/59 (81%) 130/166 (78%)
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Lifetime studies in animals to evaluate carcinogenic potential have not been conducted. Cefixime did not cause point mutations in bacteria or mammalian cells, DNA damage, or chromosome damage in vitro and did not exhibit clastogenic potential in vivo in the mouse micronucleus test. In the fertility and reproductive performance study in rats, no difference between control and drug-treated animals was detected in mating behavior, pregnancy rate, or litter parameters (determined at sacrifice on day 13 of pregnancy) at oral doses up to 1000 mg/kg/day (25 times the adult therapeutic dose) administered to males (for 68 days prior to pairing and during the cohabitation period) and females (for 14 days before pairing to weaning).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Lifetime studies in animals to evaluate carcinogenic potential have not been conducted. Cefixime did not cause point mutations in bacteria or mammalian cells, DNA damage, or chromosome damage in vitro and did not exhibit clastogenic potential in vivo in the mouse micronucleus test. In the fertility and reproductive performance study in rats, no difference between control and drug-treated animals was detected in mating behavior, pregnancy rate, or litter parameters (determined at sacrifice on day 13 of pregnancy) at oral doses up to 1000 mg/kg/day (25 times the adult therapeutic dose) administered to males (for 68 days prior to pairing and during the cohabitation period) and females (for 14 days before pairing to weaning).
📚 References ▾
15 REFERENCES Halperin-Walega, E. Batra VK, Tonelli AP, Barr A, Yacobi A. ‘Disposition of Cefixime in the Pregnant and Lactating Rat. Transfer to the Fetus and Nursing Pup’. Drug Metabolism and Disposition . 1988:16(1):pp130–134.
📄 Package Label / Principal Display Panel ▾
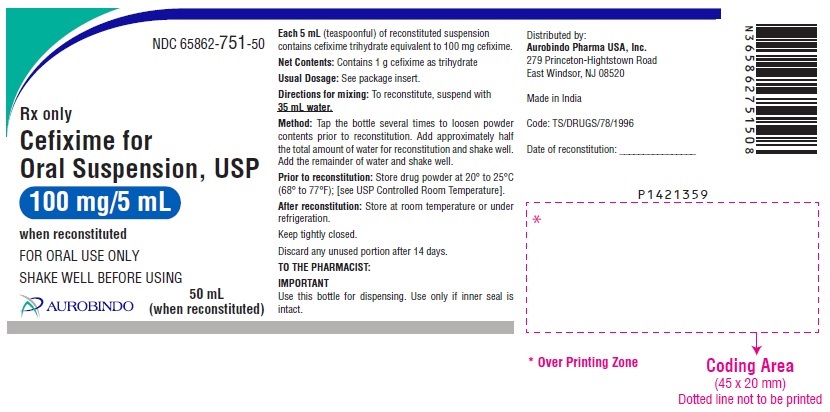
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 100 mg/5 mL (50 mL Bottle) NDC 65862-751-50 Rx only Cefixime for Oral Suspension, USP 100 mg/5 mL when reconstituted FOR ORAL USE ONLY SHAKE WELL BEFORE USING AUROBINDO 50 mL (when reconstituted) PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 100 mg/5 mL (50 mL Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 200 mg/5 mL (50 mL Bottle) NDC 65862-752-50 Rx only Cefixime for Oral Suspension, USP 200 mg/5 mL when reconstituted FOR ORAL USE ONLY SHAKE WELL BEFORE USING AUROBINDO 50 mL (when reconstituted) PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 200 mg/5 mL (50 mL Bottle)
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |