
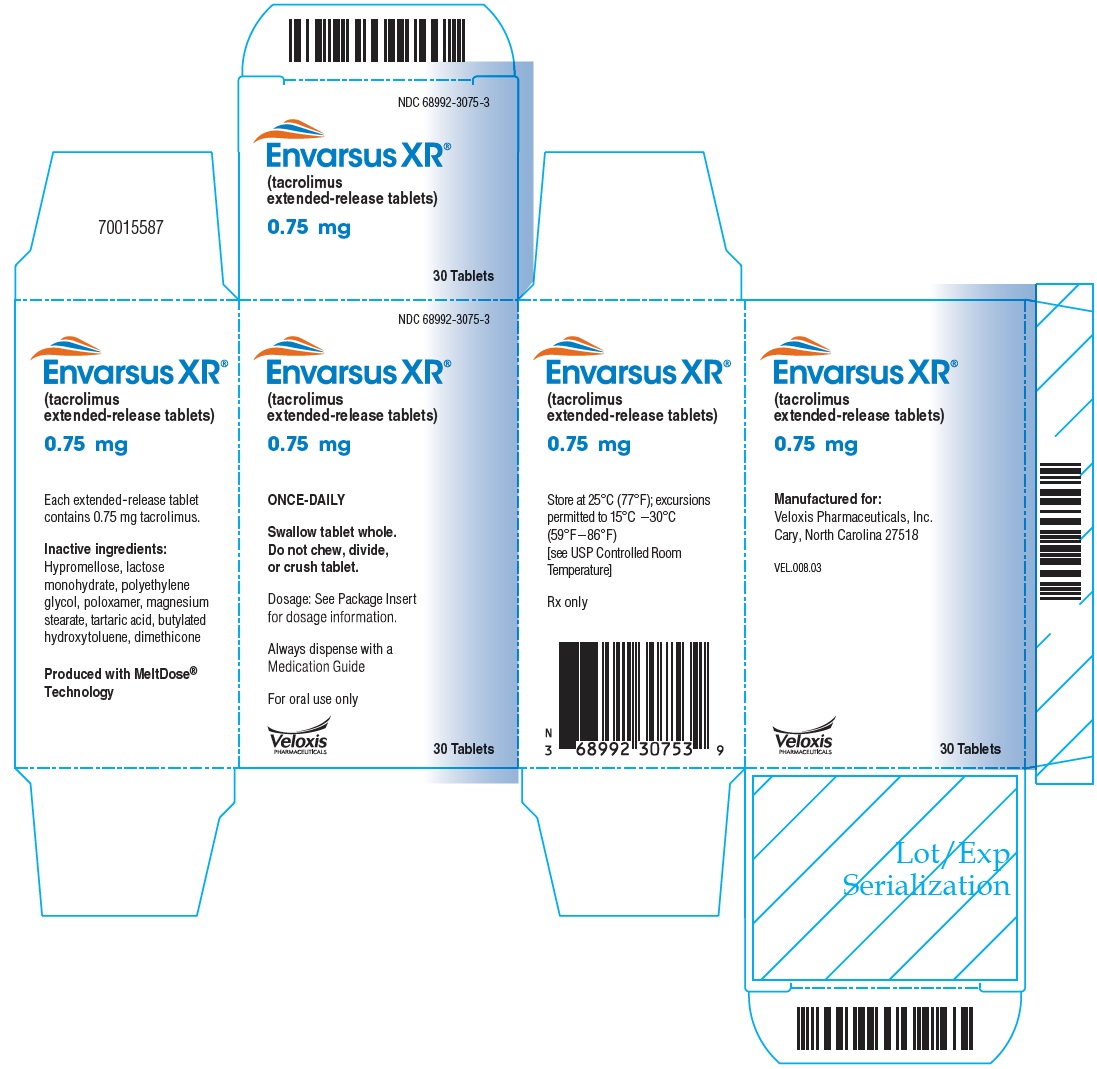
Envarsus XR Tacrolimus .75 mg Tablet, Extended Release, 30-count
Other active recalls for Tacrolimus (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Calcineurin Inhibitor Immunosuppressant class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Tacrolimus (Astagraf XL, Envarsus XR, Prograf) is used along with other medications to prevent rejection (attack of a transplanted organ by the immune system of a person receiving the organ) in people who have received a kidney transplant. Tacrolimus (Prograf) is also used along with other medications to prevent rejection in people who have received a liver, lung, or heart transplant. Tacrolimus is in a class of medications called immunosupressants. It works by decreasing the activity of the immune system to prevent it from attacking the transplanted organ.
Read the full MedlinePlus article ↗- That's a great question, and it's one of the most important things to understand. Your body's immune system doesn't just stop trying to attack the new organ once you leave the hosp...
- Why do I have to take tacrolimus even when I feel completely fine?
- It actually does matter — but the key is being consistent, not choosing one over the other. Food can change how much tacrolimus your body absorbs, so if you always take it the same...
- Does it matter if I take tacrolimus with food or on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tacrolimus — tap one for details:
Tacrolimus may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 1P9D0Z171K
BHT is a synthetic antioxidant that prevents fats and oils in medicines from breaking down and becoming rancid. It helps keep the product stable and effective during storage.
-
UNII 92RU3N3Y1O
Dimethicone is a silicone-based oil that acts as an anti-foaming agent and lubricant in medicines. It reduces gas bubbles in liquid formulations and helps coat and protect the stomach lining when ingested.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII 30IQX730WE
Polyethylene glycol 6000 is a synthetic polymer made from ethylene glycol units. It acts as a binder, filler, and solubilizer in medicines to help hold ingredients together, add bulk, and improve how well active drugs dissolve and absorb.
-
UNII W4888I119H
Tartaric acid is a natural organic acid found in grapes and tamarinds. In medicines, it works as a buffer to control acidity, an antioxidant to prevent spoilage, and sometimes a flavoring or binding agent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $5.16 | $154.71 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $6.86 | $205.94 / 30 tablets |
| Medicare Part B allowsASP · J7503 | $1.863 / J7503 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Envarsus XR .75 mgthis 68992-3075-03 | Veloxis | 30 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8664239 ↗ | Method of use | U-1752 | Aug 30, 2028 |
| US 8685998 ↗ | Method of use | U-1752 | Aug 30, 2028 |
| US 8685998 ↗ | Method of use | U-1752 | Aug 30, 2028 |
| US 8664239 ↗ | Method of use | U-1752 | Aug 30, 2028 |
| US 8685998 ↗ | Method of use | U-1752 | Aug 30, 2028 |
| US 8664239 ↗ | Method of use | U-1752 | Aug 30, 2028 |
| US 8685998 ↗ | Method of use | U-2678 | Aug 30, 2028 |
| US 8685998 ↗ | Method of use | U-2677 | Aug 30, 2028 |
| US 8685998 ↗ | Method of use | U-2678 | Aug 30, 2028 |
| US 8685998 ↗ | Method of use | U-2677 | Aug 30, 2028 |
| US 8685998 ↗ | Method of use | U-2677 | Aug 30, 2028 |
| US 8685998 ↗ | Method of use | U-2678 | Aug 30, 2028 |
| US 11123331 ↗ | Method of use | U-2677 | May 30, 2028 |
| US 11123331 ↗ | Method of use | U-2677 | May 30, 2028 |
| US 11123331 ↗ | Method of use | U-2677 | May 30, 2028 |
| US 8664239 ↗ | Method of use | U-2677 | Aug 30, 2028 |
| US 8664239 ↗ | Method of use | U-2677 | Aug 30, 2028 |
| US 8664239 ↗ | Method of use | U-2677 | Aug 30, 2028 |
| US 11110081 ↗ | Method of use | U-2678 | May 30, 2028 |
| US 11110081 ↗ | Method of use | U-2678 | May 30, 2028 |
| US 11110081 ↗ | Method of use | U-2678 | May 30, 2028 |
| US 12083103 ↗ | Method of use | U-2678 | May 30, 2028 |
| US 12083103 ↗ | Method of use | U-2678 | May 30, 2028 |
| US 12083103 ↗ | Method of use | U-2678 | May 30, 2028 |
| US 8664239 ↗ | Method of use | U-2678 | Aug 30, 2028 |
| US 8664239 ↗ | Method of use | U-2678 | Aug 30, 2028 |
| US 8664239 ↗ | Method of use | U-2678 | Aug 30, 2028 |
| US 10864199 ↗ | Method of use | U-2678 | May 30, 2028 |
| US 10864199 ↗ | Method of use | U-2677 | May 30, 2028 |
| US 10864199 ↗ | Method of use | U-2677 | May 30, 2028 |
| US 10864199 ↗ | Method of use | U-2678 | May 30, 2028 |
| US 10864199 ↗ | Method of use | U-2677 | May 30, 2028 |
| US 10864199 ↗ | Method of use | U-2678 | May 30, 2028 |
| US 10166190 ↗ | Drug product | — | May 30, 2028 |
| US 11419823 ↗ | Drug product | — | May 30, 2028 |
| US 9549918 ↗ | Drug product | — | May 30, 2028 |
| US 11419823 ↗ | Drug product | — | May 30, 2028 |
| US 9549918 ↗ | Drug product | — | May 30, 2028 |
| US 9549918 ↗ | Drug product | — | May 30, 2028 |
| US 12403095 ↗ | Drug product | — | May 30, 2028 |
| US 11419823 ↗ | Drug product | — | May 30, 2028 |
| US 12403095 ↗ | Drug product | — | May 30, 2028 |
| US 10166190 ↗ | Drug product | — | May 30, 2028 |
| US 12403095 ↗ | Drug product | — | May 30, 2028 |
| US 10166190 ↗ | Drug product | — | May 30, 2028 |
Is there a generic version of ENVARSUS XR 0.75 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 68992-3075-01 | 1 POUCH in 1 CARTON (68992-3075-1) / 1 BOTTLE in 1 POUCH / 100 TABLET, EXTENDED RELEASE in 1 BOTTLE | 2015-09-01 | Active |
| 68992-3075-03 You're viewing this | 1 POUCH in 1 CARTON (68992-3075-3) / 1 BOTTLE, PLASTIC in 1 POUCH / 30 TABLET, EXTENDED RELEASE in 1 BOTTLE, PLASTIC | 2015-09-01 | Active |
This pack accounts for about 41% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 68992-3075-03?
What is the difference between NDC 68992-3075-03 and NDC 68992-3075-01?
What NDC number is used to bill for this package of Envarsus XR Tacrolimus .75 mg Tablet, Extended Release?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: MALIGNANCIES AND SERIOUS INFECTIONS Increased risk for developing serious infections and malignancies with ENVARSUS XR or other immunosuppressants that may lead to hospitalization or death [see Warnings and Precautions (5.1 , 5.2 )]. WARNING: MALIGNANCIES AND SERIOUS INFECTIONS See full prescribing information for complete boxed warning. Increased risk for developing serious infections and malignancies with ENVARSUS XR or other immunosuppressants that may lead to hospitalization or death.
( 5.1 , 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ENVARSUS XR is a calcineurin-inhibitor immunosuppressant indicated for: The prophylaxis of organ rejection in de novo kidney transplant patients in combination with other immunosuppressants ( 1.1 ) The prophylaxis of organ rejection in kidney transplant patients converted from tacrolimus immediate-release formulations in combination with other immunosuppressants ( 1.2 )
1.1Prophylaxis of Organ Rejection in De Novo Kidney Transplant Patients ENVARSUS XR is indicated for the prophylaxis of organ rejection in kidney transplant patients in combination with other immunosuppressants [see Clinical Studies (14.1) ].
1.2Prophylaxis of Organ Rejection in Stable Kidney Transplant Patients Converting from Immediate-Release Formulations ENVARSUS XR is indicated for the prophylaxis of organ rejection in kidney transplant patients converted from tacrolimus immediate-release formulations, in combination with other immunosuppressants [see Clinical Studies (14.2) ].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Take once daily on empty stomach at the same time of the day, preferably in the morning. ( 2.1 ) Avoid eating grapefruit or drinking grapefruit juice or alcohol. ( 2.1 ) African-American patients may need to be titrated to higher dosages to achieve the target tacrolimus concentrations.
( 2.4 ) Patients with severe hepatic impairment may require a lower starting dose. ( 2.4 ) Frequent monitoring of trough concentrations is recommended. ( 2.5 ) Recommended ENVARSUS XR Initial Dosage Initial Oral Dosage Whole Blood Trough Concentration Range De novo kidney transplantation with antibody induction 0.14 mg/kg/day Month 1: 6-11 ng/mL >Month 1: 4-11 ng/mL Conversion from tacrolimus immediate-release formulations 80% of the pre-conversion dose of tacrolimus immediate-release Titrate to 4-11 ng/mL
2.1Important Administration Instructions ENVARSUS XR (tacrolimus extended-release tablets) is not interchangeable or substitutable with tacrolimus extended-release capsules, tacrolimus capsules, and tacrolimus for oral suspension. Under or overexposure to tacrolimus may result in graft rejection or other serious adverse reactions [see Warnings and Precautions (5.3) ]. ENVARSUS XR should not be used without the supervision of a physician with experience in immunosuppressive therapy.
ENVARSUS XR should be taken on an empty stomach consistently at the same time of the day, preferably in the morning to ensure consistent and maximum possible drug exposure, at least 1 hour before a meal or at least 2 hours after a meal [see Clinical Pharmacology (12.3) ]. Advise patients to swallow ENVARSUS XR tablets whole with fluid (preferably water); patients must not chew, divide, crush or dissovle the tablets. If a dose is missed, instruct the patient to take it as soon as possible within 15 hours after missing the dose.
Beyond the 15-hour time frame, instruct the patient to wait until the usual scheduled time to take the next regular daily dose. Instruct the patient not to double the next dose. Patients should avoid eating grapefruit or drinking grapefruit juice or alcoholic beverage while taking ENVARSUS XR [see Drug Interactions (7.2) ].
2.2Dosing in De Novo Kidney Transplant Patients The recommended starting dose of ENVARSUS XR in de novo kidney transplant patients is 0.14 mg/kg/day. Titrate ENVARSUS XR dosage based on clinical assessments of rejection and tolerability and to achieve whole blood trough concentration ranges (see Table 1 ). Table 1.
Recommended Tacrolimus Whole Blood Trough Concentration Ranges in Kidney Transplant Patients with Antibody Induction Time Period Post Transplant Target Tacrolimus Whole Blood Trough Concentration Ranges During Month 1 6 to 11 ng/mL > Month 1 4 to 11 ng/mL
2.3Dosing for Conversion from Tacrolimus Immediate-Release Formulations To convert from a tacrolimus immediate-release product to ENVARSUS XR, administer ENVARSUS XR once daily at a dose that is 80% of the total daily dose of the tacrolimus immediate-release product. Monitor tacrolimus whole blood trough concentrations and titrate ENVARSUS XR dosage to achieve whole blood trough concentration ranges of 4 to 11 ng/mL.
2.4Dosing Adjustments in African-American Patients, Patients with Hepatic Impairment, Drug Interactions African-American patients, compared to Caucasian patients, may need to be titrated to higher ENVARSUS XR dosages to attain comparable trough concentrations [see Use in Specific Populations (8.8) , Clinical Pharmacology (12.3) ]. Due to reduced clearance and prolonged half-life seen in patients with severe hepatic impairment (Child-Pugh ≥10) these patients may require a lower starting dosage of ENVARSUS XR [see Clinical Pharmacology (12.3) ].
Dose adjustments of ENVARSUS XR may be necessary when administered concomitantly with CYP3A inducers or CYP3A inhibitors or cannabidiol [see Warnings and Precautions (5.9 , 5.13) , Drug Interactions (7.2 , 7.3) ].
2.5 Therapeutic Drug Monitoring Measure tacrolimus whole blood tr…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Oval, white to off-white uncoated extended-release tablets debossed with “TCS” on one side: 0.75 mg extended-release tablet: debossed with “0.75” on the other side. 1 mg extended-release tablet: debossed with “1” on the other side. 4 mg extended-release tablet: debossed with “4” on the other side. Extended-release tablets: 0.75 mg, 1 mg, 4 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ENVARSUS XR is contraindicated in patients with known hypersensitivity to tacrolimus or to any of the ingredients in ENVARSUS XR. Known hypersensitivity to tacrolimus or any of the ingredients ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Not Interchangeable with Other Tacrolimus Products: Instruct patients or caregivers to recognize appearance of ENVARSUS XR tablets. ( 5.3 ) New Onset Diabetes after Transplant: Monitor blood glucose. ( 5.4 ) Nephrotoxicity (acute and/or chronic): May occur due to ENVARSUS XR, drug interactions or concomitant nephrotoxic drugs.
Monitor renal function and tacrolimus blood concentrations; consider dosage reduction or temporary interruption of ENVARSUS. ( 5.5 ) Neurotoxicity: Including risk of posterior reversible encephalopathy syndrome (PRES); monitor for neurologic abnormalities; reduce dosage or discontinue ENVARSUS XR. ( 5.6 ) Hyperkalemia: Risk may be increased with other agents associated with hyperkalemia; monitor serum potassium levels.
( 5.7 ) Hypertension: May require antihypertensive therapy; monitor relevant drug interactions. ( 5.8 ) QT Prolongation: Consider obtaining electrocardiograms and monitoring electrolytes in patients at high risk. ( 5.10 ) Immunizations: Avoid live vaccines.
( 5.11 ) Pure Red Cell Aplasia: Consider discontinuation. ( 5.12 ) Thrombotic Microangiopathy, Including Hemolytic Uremic Syndrome and Thrombotic Thrombocytopenic Purpura: May occur, especially in patients with infections and certain concomitant medications. ( 5.14 )
5.1Lymphoma and Other Malignancies Immunosuppressants, including ENVARSUS XR, increase the risk of developing lymphomas and other malignancies, particularly of the skin. The risk appears to be related to the intensity and duration of immunosuppression rather than to the use of any specific agent. Examine patients for skin changes and advise to avoid or limit exposure to sunlight and UV light by wearing protective clothing and using a sunscreen with a high protection factor.
Post-transplant lymphoproliferative disorder (PTLD), associated with Epstein-Barr Virus (EBV), has been reported in immunosuppressed organ transplant patients. The risk of PTLD appears greatest in those individuals who are EBV seronegative. Monitor EBV serology during treatment.
5.2Serious Infections Immunosuppressants, including ENVARSUS XR, increase the risk of developing bacterial, viral, fungal, and protozoal infections, including opportunistic infections. These infections may lead to serious, including fatal, outcomes. Serious viral infections reported include: Polyomavirus-associated nephropathy (especially due to BK virus infection), JC virus-associated progressive multifocal leukoencephalopathy (PML), and Cytomegalovirus (CMV) infections: CMV seronegative transplant patients who receive an organ from a CMV seropositive donor are at highest risk of CMV viremia and CMV disease.
Monitor for the development of infection and adjust the immunosuppressive regimen to balance the risk of rejection with the risk of infection [see Adverse Reactions (6.1) ] .
5.3Not Interchangeable with Other Tacrolimus Products-Medication Errors Medication errors, including substitution and dispensing errors, between tacrolimus capsules and tacrolimus extended-release capsules were reported outside the U.S. This led to serious adverse reactions, including graft rejection, or other adverse reactions due to under- or over-exposure to tacrolimus. ENVARSUS XR is not interchangeable or substitutable with tacrolimus extended-release capsules, tacrolimus capsules or tacrolimus for oral suspension.
Instruct patients and caregivers to recognize the appearance of ENVARSUS XR tablet [see Dosage Forms and Strengths (3) ] and to confirm with their healthcare provider if a different product is dispensed or if dosing instructions have changed.
5.4New Onset Diabetes after Transplant ENVARSUS XR caused new onset diabetes after transplant (NODAT) in kidney transplant patients, which may be reversible in some patients. African-American and Hispanic kidney transplant patients are at an increased risk. Monitor blood glucose concentrations and treat appropriately [see Adverse Reactions (6.1) and Use in Specific Pop…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse drug reactions are discussed in greater detail in other sections of the labeling: Lymphoma and Other Malignancies [see Boxed Warning, Warnings and Precautions (5.1) ] Serious Infections [see Boxed Warning, Warnings and Precautions (5.2) ] New Onset Diabetes after Transplant [see Warnings and Precautions (5.4) ] Nephrotoxicity due to ENVARSUS XR and Drug Interactions [see Warnings and Precautions (5.5) ] Neurotoxicity [see Warnings and Precautions (5.6) ] Hyperkalemia [see Warnings and Precautions (5.7) ] Hypertension [see Warnings and Precautions (5.8) ] QT Prolongation [see Warnings and Precautions (5.10) ] Pure Red Cell Aplasia [see Warnings and Precautions (5.12) ] Thrombotic Microangiopathy, Including Hemolytic Uremic Syndrome and Thrombotic Thrombocytopenic Purpura [see Warnings and Precautions (5.13) ] De novo kidney transplant patients: Most common adverse reactions (incidence ≥15%) include: diarrhea, anemia, urinary tract infection, hypertension, tremor, constipation, diabetes mellitus, peripheral edema, hyperkalemia and headache.
( 6.1 ) Conversion of kidney transplant patients from immediate-release to extended-release tacrolimus: Most common adverse reactions (incidence ≥10%) include: diarrhea and blood creatinine increased. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Veloxis Pharmaceuticals, Inc. at 1-844-VELOXIS (1-844-835-6947) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Studies Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. In addition, the clinical studies were not designed to establish comparative differences across study arms with regards to the adverse reactions discussed below. Study 1- Phase 3 Clinical Study in De Novo Kidney Transplant Recipients Study 1 (NCT 01187953), was a Phase 3 randomized study in de novo kidney transplant patients that were treated with ENVARSUS XR (N=268) or tacrolimus [immediate-release] capsules (N=275) and concomitant immunosuppressants in a double-blind, randomized, multinational study [see Clinical Studies (14.1) ].
The proportion of patients who discontinued treatment due to adverse reactions was 8.6% and 9.8% in the ENVARSUS XR and tacrolimus capsules treatment groups, respectively, through 12 months of treatment. The most common adverse reactions leading to discontinuation of study drug in the ENVARSUS XR treatment group were esophagitis, polyomavirus-associated nephropathy, graft dysfunction, complications of transplanted kidney, and diabetes mellitus, each resulting in 0.7% discontinuations among ENVARSUS XR treatment patients.
In Study 1, de novo kidney transplant patients who received a starting dose of 0.17 mg/kg/day, which is higher than the recommended ENVARSUS XR starting dose of 0.14 mg/kg/day, exceeded the recommended target tacrolimus trough concentrations as high as 57 ng/mL during the first 1 to 2 weeks post-transplant [see Dosage and Administration (2.2) ]. Infections The overall incidence of infections, serious infections, and infections with identified etiology reported in de novo kidney transplant recipients treated with ENVARSUS XR or tacrolimus [immediate-release] capsules in Study 1 are shown in Table 2 .
Table 2 Percentage of Patients with Infections Through 1 Year Post-Kidney Transplant in Study 1 a MMF/MPS- Mycophenolate mofetil/mycophenolate sodium; AZA-azathioprine a Study 1 was not designed to support comparative claims of ENVARSUS XR compared to tacrolimus [immediate-release] capsules for the adverse reactions reported in this table. b BK virus-associated nephropathy (BKVAN) occurred in 1.5% (4/268) and 0.7% (2/275) in the ENVARSUS XR and tacrolimus capsules treatment groups, respectively. ENVARSUS XR ± steroids, IL-2 recepto…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Risk of rejection with strong CYP3A inducers and risk of serious adverse reactions with strong CYP3A inhibitors: Adjust dose and monitor tacrolimus concentrations. ( 2.4 , 5.9 , 7.2 ) Therapeutic drug monitoring and dose reduction for ENVARSUS XR should be considered when ENVARSUS XR is co-administered with cannabidiol ( 2.5 , 5.13 , 7.3 ). See Full Prescribing Information for clinically significant drug interactions. ( 7.1 , 7.2 )
7.1Mycophenolic Acid When ENVARSUS XR is prescribed with a given dose of mycophenolic acid (MPA) product, exposure to MPA is higher with ENVARSUS XR co-administration than with cyclosporine co-administration with MPA, because cyclosporine interrupts the enterohepatic recirculation of MPA while tacrolimus does not. Monitor for MPA associated adverse reactions and reduce the dose of concomitantly administered MPA products as needed.
7.2Effects of Other Drugs/Substances on ENVARSUS XR Table 7. Effects of Other Drugs/Substances on ENVARSUS XR a, d a ENVARSUS XR dosage adjustment recommendation based on observed effect of co-administered drug on tacrolimus exposures [see Clinical Pharmacology (12.3) ] , literature reports of altered tacrolimus exposures, or the other drug’s known CYP3A inhibitor/inducer status b High dose or double strength grapefruit juice is a strong CYP3A inhibitor; low dose or single strength grapefruit juice is a moderate CYP3A inhibitor c Strong CYP3A inhibitor/inducer, based on reported effect on exposures to immediate-release tacrolimus along with supporting in vitro CYP3A inhibitor/inducer data, or based on drug-drug interaction studies with midazolam (sensitive CYP3A probe substrate) d A drug interaction study with voriconazole was conducted for ENVARSUS XR [see Clinical Pharmacology (12.3) ] .
No other drug-drug interaction studies were conducted with ENVARSUS XR. Drug/Substance Class or Name Drug Interaction Effect Recommendations Grapefruit or grapefruit juice b May increase tacrolimus whole blood trough concentrations and increase the risk of serious adverse reactions (e.g., neurotoxicity, QT prolongation) [see Warnings and Precautions (5.6 , 5.9 , 5.10) ]. Avoid grapefruit or grapefruit juice.
Alcohol May modify the rate of tacrolimus release. Avoid alcoholic beverages. Strong CYP3A Inducers c, such as: Antimycobacterials (e.g., rifampin, rifabutin), anticonvulsants (e.g., phenytoin, carbamazepine and phenobarbital), St John’s Wort May decrease tacrolimus whole blood trough concentrations and increase the risk of rejection [see Warnings and Precautions (5.9) ].
Increase ENVARSUS XR dose and monitor tacrolimus whole blood trough concentrations [see Dosage and Administration (2.5) and Clinical Pharmacology (12.3) ]. Strong CYP3A Inhibitors c, , such as: Protease inhibitors (e.g., nelfinavir, telaprevir, boceprevir, ritonavir or ritonavir containing products), azole antifungals (e.g., voriconazole, posaconazole, itraconazole, ketoconazole), antibiotics (e.g., clarithromycin, troleandomycin, chloramphenicol), nefazodone, Schisandra sphenanthera extracts, cobicistat May increase tacrolimus whole blood trough concentrations and increase the risk of serious adverse reactions (e.g., neurotoxicity, QT prolongation).
A rapid, sharp rise in tacrolimus levels may occur early, despite an immediate reduction of tacrolimus dose [see Warnings and Precautions (5.6, 5.9, 5.10) ]. Reduce ENVARSUS XR dose (for voriconazole and posaconazole, give one-third of the original dose) and adjust dose based on tacrolimus whole blood trough concentrations [see Dosage and Administration (2.5) and Clinical Pharmacology (12.3) ]. Early and frequent monitoring of tacrolimus whole blood trough levels should start within 1-3 days and continue monitoring as necessary [see Warnings and Precautions (5.9)] .
Mild or Moderate CYP3A Inhibitors, such as: antibiotics (e.g., erythromycin), calcium channel blockers (e.g., verapamil, diltiazem, nifedipine, nicardipine), amiodarone, danazol, ethiny…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Can cause fetal harm. Advise pregnant women of the potential risk to the fetus. ( 8.1 , 8.3 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy registry that monitors pregnancy outcomes in women exposed to ENVARSUS XR during pregnancy. The Transplantation Pregnancy Registry International (TPRI) is a voluntary pregnancy exposure registry that monitors outcomes of pregnancy in female transplant recipients and those fathered by male transplant recipients exposed to immunosuppressants including tacrolimus. Healthcare providers are encouraged to advise their patients to register by contacting the Transplantation Pregnancy Registry International at 1-877-955-6877 or https://www.transplantpregnancyregistry.org.
Risk Summary Tacrolimus can cause fetal harm when administered to a pregnant woman. Data from postmarketing surveillance and TPRI suggest that infants exposed to tacrolimus in utero are at a risk of prematurity, birth defects/congenital anomalies, low birth weight, and fetal distress [see Human Data]. Advise pregnant women of the potential risk to the fetus.
Administration of oral tacrolimus to pregnant rabbits and rats throughout the period of organogenesis was associated with maternal toxicity/lethality, and an increased incidence of abortion, malformation and embryofetal death at clinically relevant doses (0.7 to 3.7 times the recommended clinical dose [0.14 mg/kg/day], on a mg/m² basis). Administration of oral tacrolimus to pregnant rats after organogenesis and throughout lactation produced maternal toxicity, effects on parturition, reduced pup viability and reduced pup weight at clinically relevant doses (1.2 to 3.7 times the recommended clinical dose, on a mg/m² basis).
Administration of oral tacrolimus to rats prior to mating, and throughout gestation and lactation produced maternal toxicity/lethality, marked effects on parturition, embryofetal loss, malformations, and reduced pup viability at clinically relevant doses (1.2 to 3.7 times the recommended clinical dose, on a mg/m² basis). Interventricular septal defects, hydronephrosis, craniofacial malformations and skeletal effects were observed in offspring that died [see Animal Data]. The background risk of major birth defects and miscarriage in the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4 % and 15 to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo-Fetal Risk Risks during pregnancy are increased in organ transplant recipients. The risk of premature delivery following transplantation is increased.
Pre-existing hypertension and diabetes confer additional risk to the pregnancy of an organ transplant recipient. Pre-gestational and gestational diabetes are associated with birth defects/congenital anomalies, hypertension, low birth weight and fetal death. Cholestasis of pregnancy (COP) was reported in 7% of liver or liver-kidney (LK) transplant recipients, compared with approximately 1% of pregnancies in the general population.
However, COP symptoms resolved postpartum and no long-term effects on the offspring were reported. Maternal Adverse Reactions ENVARSUS XR may increase hyperglycemia in pregnant women with diabetes (including gestational diabetes). Monitor maternal blood glucose levels regularly [see Warnings and Precautions (5.4) ].
ENVARSUS XR may exacerbate hypertension in pregnant women and increase pre-eclampsia. Monitor and control blood pressure [see Warnings and Precautions (5.7 , 5.8) ]. Fetal/Neonatal Adverse Reactions Renal dysfunction, transient neonatal hyperkalemia and low birth weight have been reported at the time of delivery in infants of mothers taking ENVARSUS XR.
Labor or Delivery There is an increased risk for premature delivery (<37 weeks) following transplantation and maternal exposure to ENVARSUS XR. Data Human Data T…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy registry that monitors pregnancy outcomes in women exposed to ENVARSUS XR during pregnancy. The Transplantation Pregnancy Registry International (TPRI) is a voluntary pregnancy exposure registry that monitors outcomes of pregnancy in female transplant recipients and those fathered by male transplant recipients exposed to immunosuppressants including tacrolimus. Healthcare providers are encouraged to advise their patients to register by contacting the Transplantation Pregnancy Registry International at 1-877-955-6877 or https://www.transplantpregnancyregistry.org.
Risk Summary Tacrolimus can cause fetal harm when administered to a pregnant woman. Data from postmarketing surveillance and TPRI suggest that infants exposed to tacrolimus in utero are at a risk of prematurity, birth defects/congenital anomalies, low birth weight, and fetal distress [see Human Data]. Advise pregnant women of the potential risk to the fetus.
Administration of oral tacrolimus to pregnant rabbits and rats throughout the period of organogenesis was associated with maternal toxicity/lethality, and an increased incidence of abortion, malformation and embryofetal death at clinically relevant doses (0.7 to 3.7 times the recommended clinical dose [0.14 mg/kg/day], on a mg/m² basis). Administration of oral tacrolimus to pregnant rats after organogenesis and throughout lactation produced maternal toxicity, effects on parturition, reduced pup viability and reduced pup weight at clinically relevant doses (1.2 to 3.7 times the recommended clinical dose, on a mg/m² basis).
Administration of oral tacrolimus to rats prior to mating, and throughout gestation and lactation produced maternal toxicity/lethality, marked effects on parturition, embryofetal loss, malformations, and reduced pup viability at clinically relevant doses (1.2 to 3.7 times the recommended clinical dose, on a mg/m² basis). Interventricular septal defects, hydronephrosis, craniofacial malformations and skeletal effects were observed in offspring that died [see Animal Data]. The background risk of major birth defects and miscarriage in the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4 % and 15 to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo-Fetal Risk Risks during pregnancy are increased in organ transplant recipients. The risk of premature delivery following transplantation is increased.
Pre-existing hypertension and diabetes confer additional risk to the pregnancy of an organ transplant recipient. Pre-gestational and gestational diabetes are associated with birth defects/congenital anomalies, hypertension, low birth weight and fetal death. Cholestasis of pregnancy (COP) was reported in 7% of liver or liver-kidney (LK) transplant recipients, compared with approximately 1% of pregnancies in the general population.
However, COP symptoms resolved postpartum and no long-term effects on the offspring were reported. Maternal Adverse Reactions ENVARSUS XR may increase hyperglycemia in pregnant women with diabetes (including gestational diabetes). Monitor maternal blood glucose levels regularly [see Warnings and Precautions (5.4) ].
ENVARSUS XR may exacerbate hypertension in pregnant women and increase pre-eclampsia. Monitor and control blood pressure [see Warnings and Precautions (5.7 , 5.8) ]. Fetal/Neonatal Adverse Reactions Renal dysfunction, transient neonatal hyperkalemia and low birth weight have been reported at the time of delivery in infants of mothers taking ENVARSUS XR.
Labor or Delivery There is an increased risk for premature delivery (<37 weeks) following transplantation and maternal exposure to ENVARSUS XR. Data Human Data There are no adequate and well controlled studies on the effects of tacrolimus in human pregnancy. Safety data from the TPRI and postmark…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ENVARSUS XR in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of ENVARSUS XR did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients. In Studies 1, 2 and 3, there were 37 patients 65 years of age and older, and no patients were over 75 years [see Clinical Studies (14) ] . Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Postmarketing cases of overdose with tacrolimus have been reported. Overdosage adverse reactions included: nervous system disorders (tremor, headache, confusional state, balance disorders, encephalopathy, lethargy and somnolence) gastrointestinal disturbances (nausea, vomiting, and diarrhea) abnormal renal function (increased blood urea nitrogen and elevated serum creatinine) urticaria hypertension peripheral edema, and infections (one fatal postmarketing case of bilateral pneumopathy and CMV infection was attributed to tacrolimus extended-release capsules overdose).
Based on the poor aqueous solubility and extensive erythrocyte and plasma protein binding, it is anticipated that tacrolimus is not dialyzable to any significant extent; there is no experience with charcoal hemoperfusion. The oral use of activated charcoal has been reported in treating acute overdoses, but experience has not been sufficient to warrant recommending its use. General supportive measures and treatment of specific symptoms should be followed in all cases of overdosage.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tacrolimus binds to an intracellular protein, FKBP-12. A complex of tacrolimus-FKBP-12, calcium, calmodulin, and calcineurin (an ubiquitous mammalian intracellular enzyme) is then formed and the phosphatase activity of calcineurin inhibited. Such inhibition prevents the dephosphorylation and translocation of various factors such as the nuclear factor of activated T-cells (NF-AT) and nuclear factor kappa-light-chain-enhancer of activated B-cells (NF-κB).
Tacrolimus inhibits the expression and/or production of several cytokines that include interleukin (IL)-1 beta, IL-2, IL-3, IL-4, IL-5, IL-6, IL-8, IL-10, gamma interferon, tumor necrosis factor-alpha, and granulocyte macrophage colony stimulating factor. Tacrolimus also inhibits IL-2 receptor expression and nitric oxide release, induces apoptosis and production of transforming growth factor-beta that can lead to immunosuppressive activity. The net result is the inhibition of T-lymphocyte activation and proliferation as well as T-helper-cell-dependent B-cell response (i.e., immunosuppression).
12.3Pharmacokinetics Table 9 summarizes the pharmacokinetic (PK) parameters of tacrolimus following oral administration of once-daily ENVARSUS XR in healthy subjects and in kidney transplant patients, under fasted conditions. Whole blood tacrolimus concentrations in the pharmacokinetic studies were measured using validated HPLC/MS/MS assays. Table 9.
Pharmacokinetic Parameters of ENVARSUS XR by Study Day in Healthy Subjects and Kidney Transplant Patients Under Fasted Conditions a) Healthy adult subjects (administered mg/day dose); Adult de novo kidney transplant patients (group average of administered mg/day dose); Adult kidney ≥ 6 months post-transplant (group average of administered mg/day dose of ENVARSUS XR, following conversion to 67% to 80% of the daily tacrolimus immediate -release capsules dose) b) Day of ENVARSUS XR dosing and PK profiling c) Arithmetic means ± S.D. d) Median [range] e) “ De novo ” refers to immunosuppression starting at the time of transplantation f) Starting ENVARSUS XR dose = 0.14 mg/kg/day g) Starting ENVARSUS XR dose = 0.17 mg/kg/day.
De novo kidney transplant patients who received ENVARSUS XR starting dose of 0.17 mg/kg/day achieved higher than recommended target tacrolimus trough concentrations, as high as 57 ng/mL during the first 1 to 2 weeks post-transplant. h) Tacrolimus trough concentration before the next dose i) After 7 days of stable dosing with ENVARSUS XR j) AUC 0-24 –to- C 24 correlation coefficient (r) at steady state was 0.80 or higher k) Conversion to ENVARSUS XR at a mean dose of 80% of the total daily dose of tacrolimus immediate-release resulted in equivalent exposure with a 30% reduction in C max .
Population ENVARSUS XR Dose Day b Pharmacokinetic Parameters of ENVARSUS XR C max c (ng/mL) T max d (hr) AUC 24 c (ng•hr/mL) C 24 h (ng/mL) Healthy Subjects a (n=19) 2 mg 2 mg Day 1 Day 10 11.9 ± 3.8 8.3 ± 2.9 14.0 [6 - 28] 8.0 [1.0-12.0] 50 ± 14 140 ± 50 1.8 ± 0.6 4.6 ±
1.7Adult Kidney a De novo e (n=21) 11.8 mg f 10 mg 9.5 mg Day 1 Day 7 Day 14 11.8 ± 7.2 25.1 ± 16.3 27.1 ± 13.4 8.0 [4-24] 6.0 [2-12] 4.0 [1-8] 138 ± 80 335 ± 129 371 ± 104 5.2 ± 2.7 9.9 ± 4.4 11.4 ± 4.1 j Adult Kidney a De novo (n=10) 15.5 mg g 11.4 mg 11.1 mg Day 1 Day 14 Day 28 33.6 ± 21.8 31.1 ± 14.6 35.9± 18.7 6.0 [4-24] 4.0 [1-18] 4.0 [1-14] 377 ± 257 376 ± 140 396 ± 150 11.0 ± 6.1 9.1 ± 3.0 10.5 ±
3.2Adult Kidney a (≥ 6 months post- transplant) (n=47) 5.3 mg Day 7 i 13.5 ± 4.8 6.0 [1 - 16] 216 ± 63 7.0 ± 2.3 j Adult African- American Kidney k (≥ 6 months post-transplant) (n=46) 7.8 mg Day 7 i 18.4 ± 7.2 5.0 [1 - 16] 272 ± 97 7.8 ± 2.9 j In de novo adult kidney transplant patients, the administration of ENVARSUS XR once daily at a starting dose of 0.14 mg/kg/day results in a tacrolimus systemic exposure (AUC 24 ) on Day 1 post-transplant that is up to 10% lower than that of tacrolimus immediate-release capsules twice da…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tacrolimus binds to an intracellular protein, FKBP-12. A complex of tacrolimus-FKBP-12, calcium, calmodulin, and calcineurin (an ubiquitous mammalian intracellular enzyme) is then formed and the phosphatase activity of calcineurin inhibited. Such inhibition prevents the dephosphorylation and translocation of various factors such as the nuclear factor of activated T-cells (NF-AT) and nuclear factor kappa-light-chain-enhancer of activated B-cells (NF-κB).
Tacrolimus inhibits the expression and/or production of several cytokines that include interleukin (IL)-1 beta, IL-2, IL-3, IL-4, IL-5, IL-6, IL-8, IL-10, gamma interferon, tumor necrosis factor-alpha, and granulocyte macrophage colony stimulating factor. Tacrolimus also inhibits IL-2 receptor expression and nitric oxide release, induces apoptosis and production of transforming growth factor-beta that can lead to immunosuppressive activity. The net result is the inhibition of T-lymphocyte activation and proliferation as well as T-helper-cell-dependent B-cell response (i.e., immunosuppression).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ENVARSUS XR is supplied in round HDPE bottles with twist-off caps (see Table 12 ); the statement ‘ONCE-DAILY’ appears on its labels. Table 12. Strengths of ENVARSUS XR Strength Description NDC 0.75 mg Oval, white to off-white uncoated extended-release tablet, debossed with “0.75” on one side and “TCS” on the other side.
30-count (NDC 68992-3075-3) 100-count (NDC 68992-3075-1) 1 mg Oval, white to off-white uncoated extended-release tablet, debossed with “1” on one side and “TCS” on the other side. 30-count (NDC 68992-3010-3) 100-count (NDC 68992-3010-1) 4 mg Oval, white to off-white uncoated extended-release tablet, debossed with “4” on one side and “TCS” on the other side. 30-count (NDC 68992-3040-3) 100-count (NDC 68992-3040-1) Store and Dispense Store at 25 °C (77 °F); excursions permitted to 15 °C to 30 °C (59 °F to 86 °F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Tacrolimus is the active ingredient in ENVARSUS XR. Tacrolimus is a calcineurin-inhibitor immunosuppressant produced by Streptomyces tsukubaensis. Chemically, tacrolimus is designated as [3 S -[3 R *[ E (1 S *,3 S *,4 S *)],4 S *,5 R *,8 S *,9 E ,12 R *,14 R *,15 S *,16 R *,18 S *,19 S *,26a R *]]-5,6,8,11,12,13,14,15,16,17,18,19,24,25,26,26a-hexadecahydro-5,19-dihydroxy-3-[2-(4-hydroxy-3-methoxycyclo-hexyl)-1-methylethenyl]-14,16-dimethoxy-4,10,12,18-tetramethyl-8-(2-propenyl)-15,19-epoxy-3H-pyrido[2,1- c ][1,4]oxaazacyclotricosine-1,7,20,21(4H,23H)-tetrone, monohydrate.
The chemical structure of tacrolimus is: Tacrolimus has an empirical formula of C 44 H 69 NO 12 •H 2 O and a formula weight of 822.03. Tacrolimus appears as white crystals or crystalline powder. It is practically insoluble in water, freely soluble in ethanol, and very soluble in methanol and chloroform.
ENVARSUS XR is available for oral administration as extended-release tablets containing the equivalent of 0.75 mg, 1 mg, or 4 mg of anhydrous tacrolimus USP. Inactive ingredients include hypromellose USP, lactose monohydrate NF, polyethylene glycol NF, poloxamer NF, magnesium stearate NF, tartaric acid NF, butylated hydroxytoluene NF, and dimethicone NF. chemical-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide).
17.1Administration Advise patients to: Inspect their ENVARSUS XR medicine when they receive a new prescription and before taking it. If the appearance of the tablet is not the same as usual, or if dosage instructions have changed, advise patients to contact their healthcare provider as soon as possible to make sure that you have the right medicine. Other tacrolimus products cannot be substituted for ENVARSUS XR [see Warnings and Precautions (5.3) ] .
Take once-daily ENVARSUS XR at the same time every day (preferably in the morning) on an empty stomach. at least 1 hour before or at least 2 hours after a meal to ensure consistent and maximum possible drug concentrations in the blood. Swallow tablet whole with liquid, preferably water. Do not chew, divide or crush tablet.
Avoid alcoholic beverages, grapefruit, and grapefruit juice while on ENVARSUS XR [see Dosage and Administration (2.1) and Drug Interactions (7.2) ] . Take a missed dose as soon as possible but not more than 15 hours after the scheduled time (i.e., for a missed 8 AM dose, take it no later than 10 PM). Beyond the 15-hour timeframe, instruct the patient to wait until the usual scheduled time the following morning to take the next regularly scheduled dose.
Do not take two doses at the same time [see Dosage and Administration (2.1) ] .
17.2Development of Lymphoma and Other Malignancies Inform patients that they are at an increased risk of developing lymphomas and other malignancies, particularly of the skin, due to immunosuppression. Advise patients to limit exposure to sunlight and ultraviolet (UV) light by wearing protective clothing and use a sunscreen with a high protection factor [see Boxed Warning and Warnings and Precautions (5.1) ] .
17.3Increased Risk of Infection Inform patients that they are at an increased risk of developing a variety of infections, including opportunistic infections, due to immunosuppression and to contact their physician if they develop any symptoms of infection such as fever, sweats or chills, cough or flu-like symptoms, muscle aches, or warm, red, painful areas on the skin [see Boxed Warning and Warnings and Precautions (5.2) ] .
17.4New Onset Diabetes After Transplant Inform patients that ENVARSUS XR can cause diabetes mellitus and should be advised to contact their physician if they develop frequent urination, increased thirst or hunger [see Warnings and Precautions (5.4) ] .
17.5Nephrotoxicity Inform patients that ENVARSUS XR can have toxic effects on the kidney that should be monitored. Advise patients to attend all visits and complete all blood tests ordered by their medical team [see Warnings and Precautions (5.5) ] .
17.6Neurotoxicity Inform patients that they are at risk of developing adverse neurologic effects including seizure, altered mental status, and tremor. Advise patients to contact their physician should they develop vision changes, delirium, or tremors [see Warnings and Precautions (5.6) ] .
17.7Hyperkalemia Inform patients that ENVARSUS XR can cause hyperkalemia. Monitoring of potassium levels may be necessary, especially with concomitant use of other drugs known to cause hyperkalemia [see Warnings and Precautions (5.7) ] .
17.8Hypertension Inform patients that ENVARSUS XR can cause high blood pressure which may require treatment with anti-hypertensive therapy. Advise patients to monitor their blood pressure [see Warnings and Precautions (5.8) ] .
17.9Thrombotic Microangiopathy Inform patients that ENVARSUS XR can cause blood clotting problems. The risk of this occurring increases when patients take ENVARSUS XR and sirolimus or everolimus concomitantly, or when patients develop certain infections. Advise them to seek medical attention promptly if they develop fever, petequiae or bruises, fatigue, confusion, jaundice, oliguria [see Warnings and Precautions (5.13) ].
17.10 Drug Interactions Instr…
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 4/2024 MEDICATION GUIDE ENVARSUS XR® (En var' sus XR) (tacrolimus extended-release tablets) for oral use Read this Medication Guide before you start taking ENVARSUS XR and each time you get a refill.
There may be new information. This information does not take the place of talking with your healthcare provider about your medical condition or your treatment. If you have any questions about ENVARSUS XR, ask your healthcare provider or pharmacist.
What is the most important information I should know about ENVARSUS XR? ENVARSUS XR can cause serious side effects, including: Increased risk of cancer. People who take ENVARSUS XR have an increased risk of getting some kinds of cancer, including skin and lymph gland cancer (lymphoma).
Increased risk of infection. ENVARSUS XR is a medicine that affects your immune system. ENVARSUS XR can lower the ability of your immune system to fight infections.
Serious infections can happen in people receiving ENVARSUS XR that can cause death. Call your healthcare provider right away if you have symptoms of an infection such as: fever sweats or chills cough or flu-like symptoms muscle aches warm, red, or painful areas on your skin What is ENVARSUS XR? ENVARSUS XR is a prescription medicine used with other medicines to help prevent organ rejection in people who have had a kidney transplant.
ENVARSUS XR is an extended-release tablet and is not the same as tacrolimus extended-release capsules, tacrolimus immediate-release capsules or tacrolimus for oral suspension. Your healthcare provider should decide what medicine is right for you. It is not known if Envarsus XR is safe and effective in children.
Who should not take ENVARSUS XR? Do not take ENVARSUS XR if you: are allergic to tacrolimus or any of the ingredients in ENVARSUS XR. See the end of this Medication Guide for a complete list of ingredients in ENVARSUS XR.
What should I tell my doctor before taking ENVARSUS XR? Before you take ENVARSUS XR, tell your healthcare provider about all your medication conditions, including if you: plan to receive any live vaccines. Ask your healthcare provider if you are not sure if your vaccine is a live vaccine. have or have had liver, kidney or heart problems. are pregnant or plan to become pregnant.
ENVARSUS XR may harm your unborn baby. If you are able to become pregnant, you should use effective birth control before and during treatment with ENVARSUS XR. Talk to your healthcare provider about birth control methods that may be right for you.
Males who have female partners that are able to become pregnant should also use effective birth control before and during treatment with ENVARSUS XR. Talk to your healthcare provider before starting treatment with ENVARSUS XR about birth control methods that may be right for you. There is a pregnancy registry for females who become pregnant and males who have fathered a pregnancy during treatment with ENVARSUS XR.
The purpose of this registry is to collect information about your health and of your baby. To enroll in this voluntary registry, call 1-877- 955-6877 or register at https://www.transplantpregnancyregistry.org . are breastfeeding or plan to breastfeed. ENVARSUS XR passes into your breast milk.
You and your healthcare provider should decide if you will breastfeed while taking ENVARSUS XR Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, natural, herbal or nutritional supplements. ENVARSUS XR may affect the way other medicines work, and other medicines may affect how ENVARSUS XR works. Especially tell your healthcare provider if you take: sirolimus (RAPAMUNE): everolimus cyclosporine (GENGRAF, NEORAL, and SANDIMMUNE) medicines called aminoglycosides that are used to treat bacterial infections ganciclovir (CYTOVENE IV, VALCYTE) amphotericin B (ABELCET, AMBISOME) cisplatin antiviral medicines called nu…