
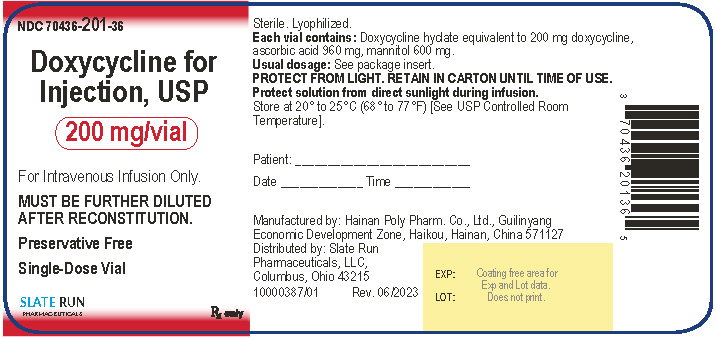
NDC 70436-0201-82: doxycycline hyclate 200 mg/20mL Powder, For Solution
This is a package of doxycycline hyclate 200 mg/20mL Powder, For Solution from Slate Run Pharmaceuticals, LLC, first listed with the FDA Jul 2024 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 70436-201-82 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 70436 labeler · 201 product · 82 package
- Package marketed since
- Jul 22, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 7043620182 2
- FDA record last changed
- Nov 12, 2026
Other active recalls for Doxycycline Hyclate (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Where does this data come from?
- FDA openFDA NDC Directory · synced Nov 19, 2026
- FDA label on DailyMed · label index refreshed Nov 21, 2026
- RxNorm (NLM RxNav) · catalog refreshed Nov 19, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Nov 19, 2026
Clinical
- It treats serious bacterial infections, such as Rocky Mountain spotted fever and other tick-borne infections, certain pneumonia-type infections, plague, cholera, and trachoma. It i...
- A healthcare professional gives it as a slow infusion into a vein, usually over one to four hours. It should never go into a muscle or under the skin. Your team will switch you to...
- Nausea, vomiting, diarrhea, and loss of appetite are common. You may also get a rash or burn more easily in the sun, so protect your skin. Irritation of the vein can happen if the...
- What side effects should I expect with Doxycycline Injection?
Patient education
Drug interactions
Supplement & herbal interactions
Some supplements/herbs that may interact with Doxycycline Hyclate — tap one for details:
Doxycycline Hyclate may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Nov 19, 2026
- FDA label on DailyMed · label index refreshed Nov 21, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Nov 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Nov 19, 2026
- CMS Part D plan pricing files · refreshed Oct 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 70436-0201-82 You're viewing this Main listing | 10 VIAL, SINGLE-DOSE in 1 CARTON / 20 mL in 1 VIAL, SINGLE-DOSE Inner NDC 70436-201-36 · each single-dose vial (20 mL) | 2024-07-22 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| doxycycline hyclate 200 mg/20mLthis 70436-0201-82 | Slate | 10 vials | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Nov 19, 2026
- FDA Orange Book · refreshed Nov 6, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Nov 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Doxycycline Injection inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII PQ6CK8PD0R
Ascorbic acid, also known as vitamin C, is a white crystalline powder. It serves as an antioxidant to prevent degradation of other ingredients and may also function as a preservative in the formulation.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Nov 21, 2026
- FDA openFDA NDC Directory · synced Nov 19, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Slate Run Pharmaceuticals, LLC labeler code 70436
- Diltiazem Hydrochloride 120 mg Tablet, Extended Release NDC 70436-195-04
- Diltiazem Hydrochloride 180 mg Tablet, Extended Release NDC 70436-196-04
- Diltiazem Hydrochloride 240 mg Tablet, Extended Release NDC 70436-197-04
- Diltiazem Hydrochloride 300 mg Tablet, Extended Release NDC 70436-198-04
- Diltiazem Hydrochloride 360 mg Tablet, Extended Release NDC 70436-199-04
- Diltiazem Hydrochloride 420 mg Tablet, Extended Release NDC 70436-200-04
- Metoprolol succinate 25 mg Tablet, Extended Release NDC 70436-202-01
- Dobutamine 250 mg/20mL Injection NDC 70436-203-80
- sodium nitroprusside in 0.9% sodium chloride .2 mg/mL Injection NDC 70436-205-80
- sodium nitroprusside in 0.9% sodium chloride .2 mg/mL Injection NDC 70436-206-80
- sodium nitroprusside in 0.9% sodium chloride .5 mg/mL Injection NDC 70436-207-80
- LEVOLEUCOVORIN CALCIUM levoleucovorin injection 10 mg/mL Injection, Solution NDC 70436-209-80
Where does this data come from?
- FDA openFDA NDC Directory · synced Nov 19, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE To reduce the development of drug-resistant bacteria and maintain the effectiveness of Doxycycline for Injection, USP and other antibacterial drugs, Doxycycline for Injection, USP should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
Doxycycline for Injection, USP is indicated in infections caused by the following microorganisms: Rickettsiae (Rocky Mountain spotted fever, typhus fever, and the typhus group, Q fever, rickettsial pox and tick fevers). Mycoplasma pneumoniae (PPLO, Eaton Agent). Agents of psittacosis and ornithosis.
Agents of lymphogranuloma venereum and granuloma inguinale. The spirochetal agent of relapsing fever ( Borrelia recurrentis ). The following gram-negative microorganisms: Haemophilus ducreyi (chancroid).
Yersinia pestis. Francisella tularensis . Bartonella bacilliformis .
Bacteroides species. Vibrio cholerae. Campylobacter fetus .
Brucella species (in conjunction with streptomycin). Because many strains of the following groups of microorganisms have been shown to be resistant to tetracyclines, culture and susceptibility testing are recommended. Doxycycline is indicated for treatment of infections caused by the following gram-negative microorganisms when bacteriologic testing indicates appropriate susceptibility to the drug: Escherichia coli .
Enterobacter aerogenes Shigella species. Acinetobacter species. Haemophilus influenzae (respiratory infections).
Klebsiella species (respiratory and urinary infections). Doxycycline is indicated for treatment of infections caused by the following gram-positive microorganisms when bacteriologic testing indicates appropriate susceptibility to the drug: Streptococcus species Up to 44 percent of strains of Streptococcus pyogenes and 74 percent of Enterococcus faecalis have been found to be resistant to tetracycline drugs. Therefore, tetracyclines should not be used for streptococcal disease unless the organism has been demonstrated to be sensitive.
For upper respiratory infections due to group A beta-hemolytic streptococci, penicillin is the usual drug of choice, including prophylaxis of rheumatic fever. Streptococcus pneumoniae . Staphylococcus aureus , respiratory, skin and soft tissue infections.
Tetracyclines are not the drugs of choice in the treatment of any type of staphylococcal infections. Anthrax due to Bacillus anthracis , including inhalational anthrax (post-exposure): to reduce the incidence or progression of disease following exposure to aerosolized Bacillus anthracis . When penicillin is contraindicated, doxycycline is an alternative drug in the treatment of infections due to: Neisseria gonorrhoeae and N. meningitidis .
Treponema pallidum and Treponema pertenue (syphilis and yaws). Listeria monocytogenes. Clostridium species.
Fusobacterium fusiforme (Vincent's infection). Actinomyces species. In acute intestinal amebiasis, doxycycline may be a useful adjunct to amebicides.
Doxycycline is indicated in the treatment of trachoma, although the infectious agent is not always eliminated, as judged by immunofluorescence.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION NOTE: Rapid administration is to be avoided. Parenteral therapy is indicated only when oral therapy is not indicated. Oral therapy should be instituted as soon as possible.
If intravenous therapy is given over prolonged periods of time, thrombophlebitis may result. The usual dosage and frequency of administration of Doxycycline for Injection (100 to 200 mg/day) differs from that of the other tetracyclines (1 to 2 g/day). Exceeding the recommended dosage may result in an increased incidence of side effects.
Studies to date have indicated that doxycycline hyclate at the usual recommended doses does not lead to excessive accumulation of doxycycline in patients with renal impairment. Adults The usual dosage of doxycycline for injection is 200 mg on the first day of treatment administered in one or two infusions. Subsequent daily dosage is 100 to 200 mg depending upon the severity of infection, with 200 mg administered in one or two infusions.
In the treatment of primary and secondary syphilis, the recommended dosage is 300 mg daily for at least 10 days. In the treatment of inhalational anthrax (post-exposure) the recommended dose is 100 mg of doxycycline, twice a day. Parenteral therapy is only indicated when oral therapy is not indicated and should not be continued over a prolonged period of time.
Oral therapy should be instituted as soon as possible. Therapy must continue for a total of 60 days. Pediatric Patients For all pediatric patients weighing less than 45 kg with severe or life-threatening infections (e.g., anthrax, Rocky Mountain spotted fever), the recommended dosage is 2.2 mg/kg of body weight administered every 12 hours.
Children weighing 45 kg or more should receive the adult dose (see WARNINGS and PRECAUTIONS ). For pediatric patients with less severe disease (greater than 8 years of age and weighing less than 45 kg), the recommended dosage schedule is 4.4 mg/kg of body weight divided into two doses on the first day of treatment, followed by a maintenance dose of 2.2 mg/kg of body weight (given as a single daily dose or divided into twice daily doses). For pediatric patients weighing over 45 kg, the usual adult dose should be used.
In the treatment of inhalational anthrax (post-exposure) the recommended dose is 2.2 mg/kg of body weight, twice a day in children weighing less than 45 kg. Parenteral therapy is only indicated when oral therapy is not indicated and should not be continued over a prolonged period of time. Oral therapy should be instituted as soon as possible.
Therapy must continue for a total of 60 days. General The duration of infusion may vary with the dose (100 to 200 mg/day), but is usually one to four hours. A recommended minimum infusion time for 100 mg of a 0.5 mg/mL solution is one hour.
Therapy should be continued for at least 24 to 48 hours after symptoms and fever have subsided. The therapeutic antibacterial serum activity will usually persist for 24 hours following recommended dosage. Intravenous solutions should not be injected intramuscularly or subcutaneously.
Caution should be taken to avoid the inadvertent introduction of the intravenous solution into the adjacent soft tissue. Preparation of Solution To prepare a solution containing 10 mg/mL, the contents of the vial should be reconstituted with 10 mL (for the 100 mg/vial container) or 20 mL (for the 200 mg/vial container) of Sterile Water for Injection or any of the 10 intravenous infusion solutions listed below. Each 100 mg of doxycycline for injection (i.e., withdraw entire solution from the 100 mg vial) is further diluted with 100 mL to 1,000 mL of the intravenous solutions listed below.
Each 200 mg of doxycycline for injection (i.e., withdraw entire solution from the 200 mg vial) is further diluted with 200 mL to 2,000 mL of the following intravenous solutions: Sodium Chloride Injection, USP 5% Dextrose Injection, USP Ringer's Injection, USP Invert Sugar, 10% in Water Lactated Ringer's Injection, USP Dextros… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS This drug is contraindicated in persons who have shown hypersensitivity to any of the tetracyclines.
⚠️ Warnings ▾
WARNINGS The use of drugs of the tetracycline class during tooth development (last half of pregnancy, infancy and childhood to the age of 8 years) may cause permanent discoloration of the teeth (yellow-gray-brown). This adverse reaction is more common during long-term use of the drugs but has been observed following repeated short-term courses. Enamel hypoplasia has also been reported.
Use doxycycline in pediatric patients 8 years of age or less only when the potential benefits are expected to outweigh the risks in severe or life-threatening conditions (e.g., anthrax, Rocky Mountain spotted fever), particularly when there are no alternative therapies. Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including doxycycline for injection, USP, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile .
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibiotic use.
Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing use of antibacterial drugs not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibiotic treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
Severe skin reactions, such as exfoliative dermatitis, erythema multiforme, Stevens-Johnson syndrome, toxic epidermal necrolysis, and drug reaction with eosinophilia and systemic symptoms (DRESS) have been reported in patients receiving doxycycline. Fixed drug eruptions have occurred with doxycycline and have been associated with worsening severity upon subsequent administrations, including generalized bullous fixed drug eruption (see ADVERSE REACTIONS ). If severe skin reactions occur, discontinue doxycycline for injection, USP immediately and institute appropriate therapy.
Intracranial hypertension (IH, pseudotumor cerebri) has been associated with the use of tetracyclines including doxycycline. Clinical manifestations of IH include headache, blurred vision, diplopia, and vision loss; papilledema can be found on fundoscopy. Women of childbearing age who are overweight or have a history of IH are at greater risk for developing tetracycline associated IH.
Concomitant use of isotretinoin and doxycycline should be avoided because isotretinoin is also known to cause pseudotumor cerebri. Although IH typically resolves after discontinuation of treatment, the possibility for permanent visual loss exists. If visual disturbance occurs during treatment, prompt ophthalmologic evaluation is warranted.
Since intracranial pressure can remain elevated for weeks after drug cessation patients should be monitored until they stabilize. Photosensitivity manifested by an exaggerated sunburn reaction has been observed in some individuals taking tetracyclines. Patients apt to be exposed to direct sunlight or ultraviolet light, should be advised that this reaction can occur with tetracycline drugs, and treatment should be discontinued at the first evidence of skin erythema.
The anti-anabolic action of the tetracyclines may cause an increase in BUN. Studies to date indicate that this does not occur with the use of doxycycline in patients with impaired renal function.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Gastrointestinal Anorexia, nausea, vomiting, diarrhea, glossitis, dysphagia, enterocolitis and inflammatory lesions (with monilial overgrowth) in the anogenital region, and pancreatitis. Hepatotoxicity has been reported rarely. These reactions have been caused by both the oral and parenteral administration of tetracyclines.
Superficial discoloration of the adult permanent dentition, reversible upon drug discontinuation and professional dental cleaning has been reported. Permanent tooth discoloration and enamel hypoplasia may occur with drugs of the tetracycline class when used during tooth development (see WARNINGS ). Skin Maculopapular and erythematous rashes, Stevens-Johnson syndrome, toxic epidermal necrolysis, and erythema multiforme, and fixed drug eruption have been reported.
Exfoliative dermatitis has been reported but is uncommon. Photosensitivity is discussed above (see WARNINGS ). Renal Toxicity Rise in BUN has been reported and is apparently dose related (see WARNINGS ).
Immune Hypersensitivity reactions including urticaria, angioneurotic edema, anaphylaxis, anaphylactoid purpura, pericarditis and exacerbation of systemic lupus erythematosus, and drug reaction with eosinophilia and systemic symptoms (DRESS). Other Bulging fontanels in infants and intracranial hypertension in adults (see WARNINGS ). Blood Hemolytic anemia, thrombocytopenia, neutropenia and eosinophilia have been reported.
When given over prolonged periods, tetracyclines have been reported to produce brown-black microscopic discoloration of thyroid glands. No abnormalities of thyroid function studies are known to occur. Psychiatric Depression, anxiety, suicidal ideation, insomnia, abnormal dreams, hallucination.
To report SUSPECTED ADVERSE REACTIONS, contact Slate Run Pharmaceuticals, LLC at 1-888-341-9214 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
Drug Interactions Because tetracyclines have been shown to depress plasma prothrombin activity, patients who are on anticoagulant therapy may require downward adjustment of their anticoagulant dosage. Since bacteriostatic drugs may interfere with the bactericidal action of penicillin, it is advisable to avoid giving tetracycline in conjunction with penicillin. Barbiturates, carbamazepine, and phenytoin decrease the half-life of doxycycline.
The concurrent use of tetracycline and Penthrane ® (methoxyflurane) has been reported to result in fatal renal toxicity. Concurrent use of tetracycline may render oral contraceptives less effective.
🤰 Pregnancy ▾
Usage in Pregnancy (See WARNINGS about use during tooth development.) Doxycycline for Injection has not been studied in pregnant patients. It should not be used in pregnant women unless, in the judgment of the physician, it is essential for the welfare of the patient. Results of animal studies indicate that tetracycline cross the placenta, are found in fetal tissues and can have toxic effects on the developing fetus (often related to retardation of skeletal development).
Evidence of embryotoxicity has also been noted in animals treated early in pregnancy.
🧒 Pediatric Use ▾
Usage in Children The use of Doxycycline for Injection in children under 8 years is not recommended because safe conditions for its use have not been established. Because of the effects of drugs of the tetracycline-class on tooth development and growth, use of doxycycline in pediatric patients 8 years of age or less only when the potential benefits are expected to outweigh the risks in severe or life-threatening conditions (e.g., anthrax, Rocky Mountain spotted fever), particularly when there are no alternative therapies (see WARNINGS and DOSAGE AND ADMINISTRATION ).
As with other tetracyclines, doxycycline forms a stable calcium complex in any bone-forming tissue. A decrease in the fibula growth rate has been observed in prematures given oral tetracycline in doses of 25 mg/kg every 6 hours. This reaction was shown to be reversible when the drug was discontinued.
Tetracyclines are present in the milk of lactating women who are taking a drug in this class.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Tetracyclines are readily absorbed and are bound to plasma proteins in varying degree. They are concentrated by the liver in the bile, and excreted in the urine and feces at high concentrations and in a biologically active form. Following a single 100 mg dose administered in a concentration of 0.4 mg/mL in a one-hour infusion, normal adult volunteers averaged a peak of 2.5 mcg/mL, while 200 mg of a concentration of 0.4 mg/mL administered over two hours averaged a peak of 3.6 mcg/mL.
Excretion of doxycycline by the kidney is about 40 percent/72 hours in individuals with normal function (creatinine clearance about 75 mL/min). This percentage of excretion may fall as low as 1 to 5 percent/72 hours in individuals with severe renal insufficiency (creatinine clearance below 10 mL/min). Studies have shown no significant difference in serum half-life of doxycycline (range 18 to 22 hours) in individuals with normal and severely impaired renal function.
Hemodialysis does not alter this serum half-life of doxycycline. Population pharmacokinetic analysis of sparse concentration-time data of doxycycline following standard of care intravenous and oral dosing in 44 pediatric patients (2-18 years of age) showed that allometrically-scaled clearance (CL) of doxycycline in pediatric patients ≥2 to ≤8 years of age (median [range] 3.58 [2.27-10.82] L/h/70 kg, N=11) did not differ significantly from pediatric patients ˃8 to 18 years of age (3.27 [1.11-8.12] L/h/70 kg, N=33). For pediatric patients weighing ≤45 kg, body weight normalized doxycycline CL in those ≥2 to ≤8 years of age (median [range] 0.071 [0.041-0.202] L/kg/h, N=10) did not differ significantly from those ˃8 to 18 years of age (0.081 [0.035-0.126] L/kg/h, N=8).
In pediatric patients weighing ˃45 kg, no clinically significant differences in body weight normalized doxycycline CL were observed between those ≥2 to ≤8 years of age (0.050 L/kg/h, N=1) and those ˃8 to 18 years of age (0.044 [0.014-0.121] L/kg/h, N=25). No clinically significant difference in CL between oral and IV dosing was observed in the small cohort of pediatric patients who received the oral (N=19) or IV (N=21) formulation alone. Microbiology Mechanism of Action Doxycycline inhibits bacterial protein synthesis by binding to the 30S ribosomal subunit.
Doxycycline has bacteriostatic activity against a broad range of Gram-positive and Gram-negative bacteria. Resistance Cross resistance with other tetracyclines is common. Antimicrobial Activity Doxycycline has been shown to be active against most isolates of the following microorganisms, both in vitro and in clinical infections (see INDICATIONS AND USAGE ).
Gram-Negative Bacteria Acinetobacter species Bartonella bacilliformis Brucella species Enterobacter aerogenes Escherichia coli Francisella tularensis Haemophilus ducreyi Haemophilus influenzae Klebsiella granulomatis Klebsiella species Neisseria gonorrhoeae Shigella species Vibrio cholerae Campylobacter fetus Yersinia pestis Gram-Positive Bacteria Bacillus anthracis Listeria monocytogenes Streptococcus pneumoniae Anaerobic Bacteria Clostridium species Fusobacterium fusiforme Propionibacterium acnes Other Bacteria Nocardiae and other aerobic Actinomyces species Borrelia recurrentis Chlamydophila psittaci Chlamydia trachomatis Mycoplasma pneumoniae Rickettsiae Treponema pallidum Treponema pallidum subspecies pertenue Ureaplasma urealyticum Parasites Balantidium coli Entamoeba species Plasmodium falciparum * *Doxycycline has been found to be active against the asexual erythrocytic forms of Plasmodium falciparum but not against the gametocytes of P. falciparum .
The precise mechanism of action of the drug is not known. Susceptibility Testing For specific information regarding susceptibility test interpretive criteria and associated test methods and quality control standards recognized by FDA for this drug, please see: https://www.fda.gov/STIC.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Doxycycline for Injection, USP, sterile powder, is supplied as follows: Unit of Sale Units per Carton Strength Each 70436-032-82 10 vials per carton Doxycycline hyclate equivalent to 100 mg doxycycline per vial NDC 70436-032-35 10 mL single dose vial 70436-201-82 10 vials per carton Doxycycline hyclate equivalent to 200 mg doxycycline per vial NDC 70436-201-36 10 mL single dose vial Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. PROTECT FROM LIGHT. Retain in carton until time of use.
Manufactured by: Hainan Poly Pharm. Co., Ltd., Guilinyang Economic Development Zone, Haikou, Hainan, China 571127 Distributed by: Slate Run Pharmaceuticals, LLC, Columbus, Ohio 43215 10000069/02 Revised 06/2025
📋 Description ▾
DESCRIPTION Doxycycline for Injection, USP is an antibacterial drug synthetically derived from oxytetracycline, and is available as Doxycycline Hyclate (doxycycline hydrochloride hemiethanolate hemihydrate). The chemical designation of this light-yellow crystalline powder is alpha-6-deoxy-5-oxytetracycline. Doxycycline has a high degree of lipoid solubility and a low affinity for calcium binding.
It is highly stable in normal human serum. Each 100 mg vial contains: Doxycycline hyclate equivalent to 100 mg doxycycline; ascorbic acid 480 mg; mannitol 300 mg. pH of the reconstituted solution (10 mg/mL) is between 1.8 and 3.3. Each 200 mg vial contains: Doxycycline hyclate equivalent to 200 mg doxycycline; ascorbic acid 960 mg; mannitol 600 mg. pH of the reconstituted solution (10 mg/mL) is between 1.8 and 3.3.
💬 Information for Patients ▾
Information for Patients Patients taking doxycycline should be advised: to avoid excessive sunlight or artificial ultraviolet light while receiving doxycycline and to discontinue therapy if phototoxicity (e.g., skin eruption, etc.) occurs. Sunscreen or sunblock should be considered. (See WARNINGS .) that the use of doxycycline might increase the incidence of vaginal candidiasis.
Patients should be counseled that antibacterial drugs, including doxycycline should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When doxycycline is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by doxycycline or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibacterial drugs, which usually ends when the antibacterials are discontinued. Sometimes after starting treatment with antibacterial drugs, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibacterial drug.
If this occurs, patients should contact their physician as soon as possible.
⚠️ Precautions ▾
PRECAUTIONS General As with other antibacterial drugs, use of doxycycline may result in overgrowth of nonsusceptible organisms, including fungi. If superinfection occurs, doxycycline should be discontinued and appropriate therapy instituted. Incision and drainage or other surgical procedures should be performed in conjunction with antibacterial therapy, when indicated.
Prescribing doxycycline in the absence of proven or strongly suspected bacterial infection or a prophylactic indication is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria. All infections due to group A beta-hemolytic streptococci should be treated for at least 10 days. Information for Patients Patients taking doxycycline should be advised: to avoid excessive sunlight or artificial ultraviolet light while receiving doxycycline and to discontinue therapy if phototoxicity (e.g., skin eruption, etc.) occurs.
Sunscreen or sunblock should be considered. (See WARNINGS .) that the use of doxycycline might increase the incidence of vaginal candidiasis. Patients should be counseled that antibacterial drugs, including doxycycline should only be used to treat bacterial infections.
They do not treat viral infections (e.g., the common cold). When doxycycline is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by doxycycline or other antibacterial drugs in the future.
Diarrhea is a common problem caused by antibacterial drugs, which usually ends when the antibacterials are discontinued. Sometimes after starting treatment with antibacterial drugs, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibacterial drug. If this occurs, patients should contact their physician as soon as possible.
Laboratory Tests In venereal diseases when coexistent syphilis is suspected, a dark field examination should be done before treatment is started and the blood serology repeated monthly for at least 4 months. In long-term therapy, periodic laboratory evaluation of organ systems, including hematopoietic, renal, and hepatic studies should be performed. Drug Interactions Because tetracyclines have been shown to depress plasma prothrombin activity, patients who are on anticoagulant therapy may require downward adjustment of their anticoagulant dosage.
Since bacteriostatic drugs may interfere with the bactericidal action of penicillin, it is advisable to avoid giving tetracycline in conjunction with penicillin. Barbiturates, carbamazepine, and phenytoin decrease the half-life of doxycycline. The concurrent use of tetracycline and Penthrane ® (methoxyflurane) has been reported to result in fatal renal toxicity.
Concurrent use of tetracycline may render oral contraceptives less effective. Usage in Pregnancy (See WARNINGS about use during tooth development.) Doxycycline for Injection has not been studied in pregnant patients. It should not be used in pregnant women unless, in the judgment of the physician, it is essential for the welfare of the patient.
Results of animal studies indicate that tetracycline cross the placenta, are found in fetal tissues and can have toxic effects on the developing fetus (often related to retardation of skeletal development). Evidence of embryotoxicity has also been noted in animals treated early in pregnancy. Usage in Children The use of Doxycycline for Injection in children under 8 years is not recommended because safe conditions for its use have not been established.
Because of the effects of drugs of the tetracycline-class on tooth dev… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL NDC 70436-032-35 Doxycycline for Injection, USP, 100 mg per vial 10000068_01_v01.2
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL NDC 70436-201-36 Doxycycline for Injection, USP, 200 mg per vial 10000387_01_v01.2
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |