
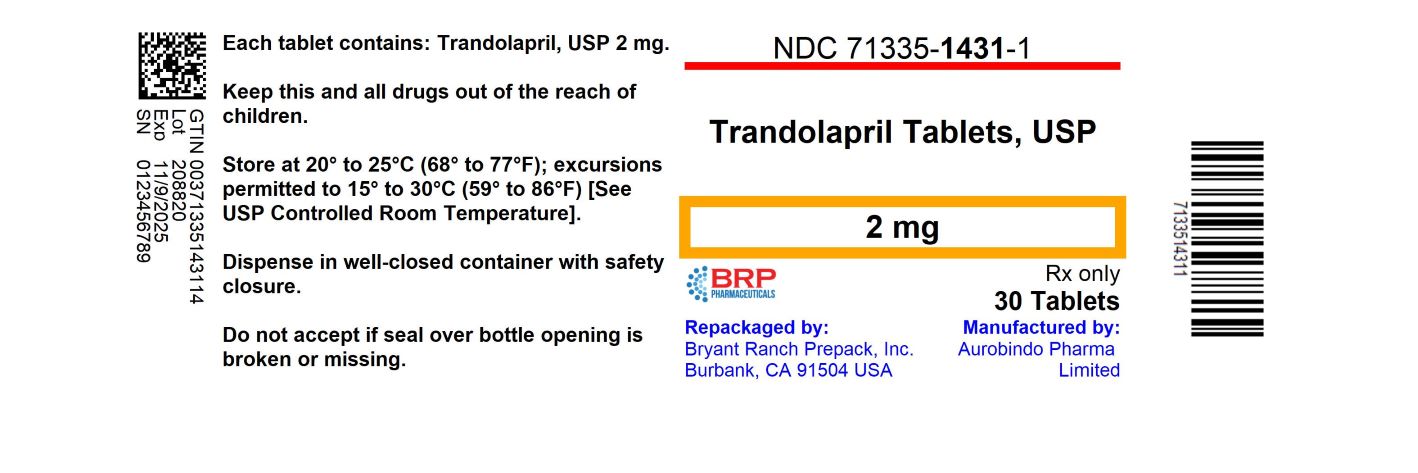
Trandolapril 2 mg Tablet, 90-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Angiotensin Converting Enzyme Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Trandolapril is used alone or in combination with other medications to treat high blood pressure. It is also used to improve survival in patients with heart failure after a heart attack. Trandolapril is in a class of medications called angiotensin-converting enzyme (ACE) inhibitors. It works by decreasing certain chemicals that tighten the blood vessels, so blood flows more smoothly and the heart can pump blood more efficiently. High blood pressure is a common condition and when not treated, can cause damage to the brain, heart, blood vessels, kidneys, and other parts of the body. Damage to th...
Read the full MedlinePlus article ↗- Trandolapril is used for two main things. First, it treats high blood pressure — it can be used on its own or paired with other blood pressure medicines. Second, it's used after a...
- Yes, a dry, persistent cough is the most commonly reported side effect of trandolapril — it showed up in about 1 in 5 patients in heart failure trials. It's a known quirk of the wh...
- I've heard ACE inhibitors cause a cough. Is that true with this one?
- No — trandolapril is not safe during pregnancy and carries a serious boxed warning because of it. Using it during the second or third trimester can damage the baby's kidneys, cause...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Trandolapril — tap one for details:
Trandolapril may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2799 | $25.19 / 90 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Trandolapril 2 mg 57237-0090-01 | Rising | 100 tablets | $0.182 | AB | Availability likely | — |
| Trandolapril 2 mg 68180-0567-01 | Lupin | 100 tablets | $0.182 | AB | Availability likely | — |
| Trandolapril 2 mg 42806-0053-01 | Epic | 100 tablets | — | AB | FDA listed | — |
| Trandolapril 2 mg 63629-8003-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Trandolapril 2 mg 65862-0165-01 | Aurobindo | 100 tablets | — | AB | FDA listed | — |
| Trandolapril 2 mgthis 71335-1431-02 | Bryant | 90 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1431-01 | 30 TABLET in 1 BOTTLE (71335-1431-1) | 2019-12-12 | Active |
| 71335-1431-02 You're viewing this | 90 TABLET in 1 BOTTLE (71335-1431-2) | 2019-12-12 | Active |
You're viewing the largest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1431-02?
What is the difference between NDC 71335-1431-02 and NDC 71335-1431-01?
What NDC number is used to bill for this package of Trandolapril 2 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue trandolapril as soon as possible. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. (See WARNINGS: Fetal Toxicity .)
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Hypertension Trandolapril tablets USP are indicated for the treatment of hypertension. They may be used alone or in combination with other antihypertensive medication such as hydrochlorothiazide. Heart Failure Post Myocardial Infarction or Left-Ventricular Dysfunction Post Myocardial Infarction Trandolapril tablets USP are indicated in stable patients who have evidence of left-ventricular systolic dysfunction (identified by wall motion abnormalities) or who are symptomatic from congestive heart failure within the first few days after sustaining acute myocardial infarction.
Administration of trandolapril to Caucasian patients has been shown to decrease the risk of death (principally cardiovascular death) and to decrease the risk of heart failure-related hospitalization (see CLINICAL PHARMACOLOGY -Heart Failure or Left-Ventricular Dysfunction Post Myocardial Infarction for details of the survival trial).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Hypertension The recommended initial dosage of trandolapril tablets for patients not receiving a diuretic is 1 mg once daily in non-black patients and 2 mg in black patients. Dosage should be adjusted according to the blood pressure response. Generally, dosage adjustments should be made at intervals of at least 1 week.
Most patients have required dosages of 2 to 4 mg once daily. There is little clinical experience with doses above 8 mg. Patients inadequately treated with once-daily dosing at 4 mg may be treated with twice-daily dosing.
If blood pressure is not adequately controlled with trandolapril tablets monotherapy, a diuretic may be added. In patients who are currently being treated with a diuretic, symptomatic hypotension occasionally can occur following the initial dose of trandolapril tablets. To reduce the likelihood of hypotension, the diuretic should, if possible, be discontinued two to three days prior to beginning therapy with trandolapril tablets.
(See WARNINGS . ) Then, if blood pressure is not controlled with trandolapril tablets alone, diuretic therapy should be resumed. If the diuretic cannot be discontinued, an initial dose of 0.5 mg trandolapril tablets should be used with careful medical supervision for several hours until blood pressure has stabilized. The dosage should subsequently be titrated (as described above) to the optimal response.
(See WARNINGS , PRECAUTIONS and Drug Interactions . ) Concomitant administration of trandolapril tablets with potassium supplements, potassium salt substitutes, or potassium sparing diuretics can lead to increases of serum potassium. (See PRECAUTIONS . ) Heart Failure Post Myocardial Infarction or Left-Ventricular Dysfunction Post Myocardial Infarction The recommended starting dose is 1 mg, once daily. Following the initial dose, all patients should be titrated (as tolerated) toward a target dose of 4 mg, once daily.
If a 4 mg dose is not tolerated, patients can continue therapy with the greatest tolerated dose. Dosage Adjustment in Renal Impairment or Hepatic Cirrhosis For patients with a creatinine clearance <30 mL/min. or with hepatic cirrhosis, the recommended starting dose, based on clinical and pharmacokinetic data, is 0.5 mg daily. Patients should subsequently have their dosage titrated (as described above) to the optimal response.
⛔ Contraindications ▾
CONTRAINDICATIONS Trandolapril tablets are contraindicated in patients who are hypersensitive to this product, in patients with hereditary/idiopathic angioedema and in patients with a history of angioedema related to previous treatment with an ACE inhibitor. Do not co-administer aliskiren with trandolapril in patients with diabetes (see PRECAUTIONS, Drug Interactions ). Trandolapril tablets are contraindicated in combination with a neprilysin inhibitor (e.g., sacubitril).
Do not administer trandolapril tablets within 36 hours of switching to or from sacubitril/valsartan, a neprilysin inhibitor (see WARNINGS ).
⚠️ Warnings ▾
WARNINGS Anaphylactoid and Possibly Related Reactions Presumably because angiotensin converting enzyme inhibitors affect the metabolism of eicosanoids and polypeptides, including endogenous bradykinin, patients receiving ACE inhibitors, including trandolapril, may be subject to a variety of adverse reactions, some of them serious. Anaphylactoid Reactions During Desensitization Two patients undergoing desensitizing treatment with hymenoptera venom while receiving ACE inhibitors sustained life-threatening anaphylactoid reactions.
In the same patients, these reactions did not occur when ACE inhibitors were temporarily withheld, but they reappeared when the ACE inhibitors were inadvertently readministered. Anaphylactoid Reactions During Membrane Exposure Anaphylactoid reactions have been reported in patients dialyzed with high-flux membranes and treated concomitantly with an ACE inhibitor. Anaphylactoid reactions have also been reported in patients undergoing low-density lipoprotein apheresis with dextran sulfate absorption.
Head and Neck Angioedema In controlled trials ACE inhibitors (for which adequate data are available) cause a higher rate of angioedema in black than in non-black patients. Angioedema of the face, extremities, lips, tongue, glottis, and larynx has been reported in patients treated with ACE inhibitors including trandolapril. Symptoms suggestive of angioedema or facial edema occurred in 0.13% of trandolapril-treated patients.
Two of the four cases were life-threatening and resolved without treatment or with medication (corticosteroids). Angioedema associated with laryngeal edema can be fatal. If laryngeal stridor or angioedema of the face, tongue or glottis occurs, treatment with trandolapril should be discontinued immediately, the patient treated in accordance with accepted medical care and carefully observed until the swelling disappears.
In instances where swelling is confined to the face and lips, the condition generally resolves without treatment; antihistamines may be useful in relieving symptoms. Where there is involvement of the tongue, glottis, or larynx, likely to cause airway obstruction, emergency therapy, including but not limited to subcutaneous epinephrine solution 1:1,000 (0.3 to 0.5 mL) should be promptly administered. (See PRECAUTIONS - Information for Patients and ADVERSE REACTIONS . ) Patients receiving coadministration of an ACE inhibitor with an mTOR (mammalian target of rapamycin) inhibitor (e.g., temsirolimus, sirolimus, everolimus) or a neprilysin inhibitor (e.g., sacubitril) may be at increased risk for angioedema.
Intestinal Angioedema Intestinal angioedema has been reported in patients treated with ACE inhibitors. These patients presented with abdominal pain (with or without nausea or vomiting); in some cases there was no prior history of facial angioedema and C-1 esterase levels were normal. The angioedema was diagnosed by procedures including abdominal CT scan or ultrasound, or at surgery, and symptoms resolved after stopping the ACE inhibitor.
Intestinal angioedema should be included in the differential diagnosis of patients on ACE inhibitors presenting with abdominal pain. Hypotension Trandolapril can cause symptomatic hypotension. Like other ACE inhibitors, trandolapril has only rarely been associated with symptomatic hypotension in uncomplicated hypertensive patients.
Symptomatic hypotension is most likely to occur in patients who have been salt- or volume-depleted as a result of prolonged treatment with diuretics, dietary salt restriction, dialysis, diarrhea, or vomiting. Volume and/or salt depletion should be corrected before initiating treatment with trandolapril. (See PRECAUTIONS - Drug Interactions and ADVERSE REACTIONS .) In controlled and uncontrolled studies, hypotension was reported as an adverse event in 0.6% of patients and led to discontinuations in 0.1% of patients.
In patients with concomitant congestive heart failure, with or without associated renal insufficiency…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The safety experience in U.S. placebo-controlled trials included 1069 hypertensive patients, of whom 832 received trandolapril. Nearly 200 hypertensive patients received trandolapril for over one year in open-label trials. In controlled trials, withdrawals for adverse events were 2.1% on placebo and 1.4% on trandolapril.
Adverse events considered at least possibly related to treatment occurring in 1% of trandolapril-treated patients and more common on trandolapril than placebo, pooled for all doses, are shown below, together with the frequency of discontinuation of treatment because of these events. ADVERSE EVENTS IN PLACEBO-CONTROLLED HYPERTENSION TRIALS Occurring at 1% or greater TRANDOLAPRIL (N=832) % Incidence (% Discontinuance) PLACEBO (N=237) % Incidence (% Discontinuance) Cough 1.9 (0.1) 0.4 (0.4) Dizziness 1.3 (0.2) 0.4 (0.4) Diarrhea 1 (0) 0.4 (0) Headache and fatigue were all seen in more than 1% of trandolapril-treated patients but were more frequently seen on placebo.
Adverse events were not usually persistent or difficult to manage. Left Ventricular Dysfunction Post Myocardial Infarction Adverse reactions related to trandolapril occurring at a rate greater than that observed in placebo-treated patients with left ventricular dysfunction, are shown below. The incidences represent the experiences from the TRACE study.
The follow-up time was between 24 and 50 months for this study. Percentage of Patients with Adverse Events Greater Than Placebo Placebo-Controlled (TRACE) Mortality Study Adverse Event Trandolapril N=876 Placebo N=873 Cough 35 22 Dizziness 23 17 Hypotension 11
6.8 Elevated serum uric acid 15 13 Elevated BUN 9
7.6PICA or CABG 7.3
6.1Dyspepsia 6.4 6 Syncope 5.9
3.3Hyperkalemia 5.3
2.8Bradycardia 4.7
4.4Hypocalcemia 4.7
3.9Myalgia 4.7
3.1Elevated creatinine 4.7
2.4Gastritis 4.2
3.6Cardiogenic shock 3.8 < 2 Intermittent claudication 3.8 < 2 Stroke 3.3
3.2Asthenia 3.3
2.6Clinical adverse experiences possibly or probably related or of uncertain relationship to therapy occurring in 0.3% to 1% (except as noted) of the patients treated with trandolapril (with or without concomitant calcium ion antagonist or diuretic) in controlled or uncontrolled trials (N=1134) and less frequent, clinically significant events seen in clinical trials or post-marketing experience include (listed by body system): General Body Function Chest pain. Cardiovascular AV first degree block, bradycardia, edema, flushing, and palpitations.
Central Nervous System Drowsiness, insomnia, paresthesia, vertigo. Dermatologic Pruritus, rash, pemphigus. Eye, Ear, Nose, Throat Epistaxis, throat inflammation, upper respiratory tract infection.
Emotional, Mental, Sexual States Anxiety, impotence, decreased libido. Gastrointestinal Abdominal distention, abdominal pain/cramps, constipation, dyspepsia, diarrhea, vomiting, nausea. Hemopoietic Decreased leukocytes, decreased neutrophils.
Metabolism and Endocrine Increased liver enzymes including SGPT (ALT). Musculoskeletal System Extremity pain, muscle cramps, gout. Pulmonary Dyspnea.
Postmarketing The following adverse reactions were identified during post approval use of trandolapril. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. General Body Function Malaise, fever.
Cardiovascular Myocardial infarction, myocardial ischemia, angina pectoris, cardiac failure, ventricular tachycardia, tachycardia, transient ischemic attack, arrhythmia. Central Nervous System Cerebral hemorrhage. Dermatologic Alopecia, sweating, Stevens-Johnson syndrome and toxic epidermal necrolysis.
Emotional, Mental, Sexual States Hallucination, depression. Gastrointestinal Dry mouth, pancreatitis, jaundice and hepatitis. Hemopoietic Agranulocytosis, pancytopenia.
Metabolism and Endocrine Increased SGOT (AST). Pulmonary Bronchitis. Renal and Urinary Renal…
🔄 Drug Interactions ▾
Drug Interactions Dual Blockade of the Renin-Angiotensin System (RAS) Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. Most patients receiving the combination of two RAS inhibitors do not obtain any additional benefit compared to monotherapy. In general, avoid combined use of RAS inhibitors.
Closely monitor blood pressure, renal function and electrolytes in patients on trandolapril and other agents that affect the RAS. Do not co-administer aliskiren with trandolapril in patients with diabetes. Avoid use of aliskiren with trandolapril in patients with renal impairment (GFR <60 mL/min).
Concomitant Diuretic Therapy As with other ACE inhibitors, patients on diuretics, especially those on recently instituted diuretic therapy, may experience an excessive reduction of blood pressure after initiation of therapy with trandolapril. The possibility of exacerbation of hypotensive effects with trandolapril may be minimized by either discontinuing the diuretic or cautiously increasing salt intake prior to initiation of treatment with trandolapril. If it is not possible to discontinue the diuretic, the starting dose of trandolapril should be reduced.
(See DOSAGE AND ADMINISTRATION . ) Agents Increasing Serum Potassium Trandolapril can attenuate potassium loss caused by thiazide diuretics and increase serum potassium when used alone. Use of potassium-sparing diuretics (spironolactone, triamterene, or amiloride), potassium supplements, or potassium-containing salt substitutes concomitantly with ACE inhibitors can increase the risk of hyperkalemia. If concomitant use of such agents is indicated, they should be used with caution and with appropriate monitoring of serum potassium.
(See PRECAUTIONS . ) Antidiabetic Agents Concomitant use of ACE inhibitors and antidiabetic medicines (insulin or oral hypoglycemic agents) may cause an increased blood glucose lowering effect with greater risk of hypoglycemia. Lithium Increased serum lithium levels and symptoms of lithium toxicity have been reported in patients receiving concomitant lithium and ACE inhibitor therapy. These drugs should be coadministered with caution, and frequent monitoring of serum lithium levels is recommended.
If a diuretic is also used, the risk of lithium toxicity may be increased. Non-Steroidal Anti-Inflammatory Agents including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors) In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, co-administration of NSAIDs, including selective COX-2 inhibitors, with ACE inhibitors, including trandolapril, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible.
Monitor renal function periodically in patients receiving trandolapril and NSAID therapy. The antihypertensive effect of ACE inhibitors, including trandolapril may be attenuated by NSAIDs. Gold Nitritoid reactions (symptoms include facial flushing, nausea, vomiting and hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy including trandolapril.
Mammalian Target of Rapamycin (mTOR) Inhibitors Patients taking concomitant mTOR inhibitor (e.g., temsirolimus, sirolimus, everolimus) therapy may be at increased risk for angioedema (see Warnings – Head and Neck Angioedema). Neprilysin Inhibitor Patients taking concomitant neprilysin inhibitors (e.g., sacubitril) may be at increased risk for angioedema (see WARNINGS ). Other No clinically significant pharmacokinetic interaction has been found between trandolaprilat and food, cimetidine, digoxin, or furosemide.
The anticoagulant effect of warfarin was not significantly changed by trandolapril. The hypotensive effect of certain i…
🧒 Pediatric Use ▾
Pediatric Use Neonates with a history of in utero exposure to trandolapril If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function. The safety and effectiveness of trandolapril in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use In placebo-controlled studies of trandolapril, 31.1% of patients were 60 years and older, 20.1% were 65 years and older, and 2.3% were 75 years and older. No overall differences in effectiveness or safety were observed between these patients and younger patients. (Greater sensitivity of some older individual patients cannot be ruled out.)
🆘 Overdosage ▾
OVERDOSAGE No data are available with respect to overdosage in humans. The oral LD 50 of trandolapril in mice was 4875 mg/Kg in males and 3990 mg/Kg in females. In rats, an oral dose of 5000 mg/Kg caused low mortality (1 male out of 5; 0 females).
In dogs, an oral dose of 1000 mg/Kg did not cause mortality and abnormal clinical signs were not observed. In humans, the most likely clinical manifestation would be symptoms attributable to severe hypotension. Symptoms also expected with ACE inhibitors are hypotension, hyperkalemia, and renal failure.
Laboratory determinations of serum levels of trandolapril and its metabolites are not widely available, and such determinations have, in any event, no established role in the management of trandolapril overdose. No data are available to suggest that physiological maneuvers (e.g., maneuvers to change the pH of the urine) might accelerate elimination of trandolapril and its metabolites. Trandolaprilat is removed by hemodialysis.
Angiotensin II could presumably serve as a specific antagonist antidote in the setting of trandolapril overdose, but angiotensin II is essentially unavailable outside of scattered research facilities. Because the hypotensive effect of trandolapril is achieved through vasodilation and effective hypovolemia, it is reasonable to treat trandolapril overdose by infusion of normal saline solution.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Trandolapril is deesterified to the diacid metabolite, trandolaprilat, which is approximately eight times more active as an inhibitor of ACE activity. ACE is a peptidyl dipeptidase that catalyzes the conversion of angiotensin I to the vasoconstrictor, angiotensin II. Angiotensin II is a potent peripheral vasoconstrictor that also stimulates secretion of aldosterone by the adrenal cortex and provides negative feedback for renin secretion.
The effect of trandolapril in hypertension appears to result primarily from the inhibition of circulating and tissue ACE activity thereby reducing angiotensin II formation, decreasing vasoconstriction, decreasing aldosterone secretion, and increasing plasma renin. Decreased aldosterone secretion leads to diuresis, natriuresis, and a small increase of serum potassium. In controlled clinical trials, treatment with trandolapril alone resulted in mean increases in potassium of 0.1 mEq/L.
(See PRECAUTIONS .) ACE is identical to kininase II, an enzyme that degrades bradykinin, a potent peptide vasodilator; whether increased levels of bradykinin play a role in the therapeutic effect of trandolapril remains to be elucidated. While the principal mechanism of antihypertensive effect is thought to be through the renin-angiotensin-aldosterone system, trandolapril exerts antihypertensive actions even in patients with low-renin hypertension. Trandolapril was an effective antihypertensive in all races studied.
Both black patients (usually a predominantly low-renin group) and non-black patients responded to 2 to 4 mg of trandolapril. Pharmacokinetics and Metabolism Pharmacokinetics Trandolapril’s ACE-inhibiting activity is primarily due to its diacid metabolite, trandolaprilat. Cleavage of the ester group of trandolapril, primarily in the liver, is responsible for conversion.
Absolute bioavailability after oral administration of trandolapril is about 10% as trandolapril and 70% as trandolaprilat. After oral trandolapril under fasting conditions, peak trandolapril levels occur at about one hour and peak trandolaprilat levels occur between 4 and 10 hours. The elimination half-life of trandolapril is about 6 hours.
At steady state, the effective half-life of trandolaprilat is 22.5 hours. Like all ACE inhibitors, trandolaprilat also has a prolonged terminal elimination phase, involving a small fraction of administered drug, probably representing binding to plasma and tissue ACE. During multiple dosing of trandolapril, there is no significant accumulation of trandolaprilat.
Food slows absorption of trandolapril, but does not affect AUC or C max of trandolaprilat or C max of trandolapril. Metabolism and Excretion After oral administration of trandolapril, about 33% of parent drug and metabolites are recovered in urine, mostly as trandolaprilat, with about 66% in feces. The extent of the absorbed dose which is biliary excreted has not been determined.
Plasma concentrations (C max and AUC of trandolapril and C max of trandolaprilat) are dose proportional over the 1 to 4 mg range, but the AUC of trandolaprilat is somewhat less than dose proportional. In addition to trandolaprilat, at least 7 other metabolites have been found, principally glucuronides or deesterification products. Serum protein binding of trandolapril is about 80%, and is independent of concentration.
Binding of trandolaprilat is concentration-dependent, varying from 65% at 1000 ng/mL to 94% at 0.1 ng/mL, indicating saturation of binding with increasing concentration. The volume of distribution of trandolapril is about 18 liters. Total plasma clearances of trandolapril and trandolaprilat after approximately 2 mg IV doses are about 52 liters/hour and 7 liters/hour respectively.
Renal clearance of trandolaprilat varies from 1 to 4 liters/hour, depending on dose. Special Populations Pediatric Trandolapril pharmacokinetics have not been evaluated in patients <18 years of age. Geriatric and Gender Trandolapril pharm…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Trandolapril Tablets USP 2 mg are yellow colored, round, biconvex, uncoated tablets debossed with ‘E’ on one side and ‘36’ on the other side. NDC: 71335-1431-1: 30 Tablets in a BOTTLE NDC: 71335-1431-2: 90 Tablets in a BOTTLE Dispense in well-closed container with safety closure. Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
DESCRIPTION Trandolapril is the ethyl ester prodrug of a nonsulfhydryl angiotensin converting enzyme (ACE) inhibitor, trandolaprilat. Trandolapril is chemically described as (2S,3aR,7aS)-1-[(S)-N-[(S)-1-Carboxy-3-phenylpropyl]alanyl] hexahydro-2-indolinecarboxylic acid, 1-ethyl ester. Its molecular formula is C 24 H 34 N 2 O 5 and its structural formula is M.W. = 430.54 Melting Point = 125°C Trandolapril USP is a white or almost white powder that is soluble (>100 mg/mL) in chloroform, dichloromethane, and methanol.
Trandolapril tablets USP contain 1 mg, 2 mg, or 4 mg of trandolapril USP for oral administration. Each tablet also contains lactose monohydrate, corn starch, croscarmellose sodium, hypromellose, povidone, and sodium stearyl fumarate. In addition 1 mg and 4 mg tablet also contains ferric oxide red and 2 mg tablet contains ferric oxide yellow.
💬 Information for Patients ▾
Information for Patients Angioedema Angioedema, including laryngeal edema, may occur at any time during treatment with ACE inhibitors, including trandolapril. Patients should be so advised and told to report immediately any signs or symptoms suggesting angioedema (swelling of face, extremities, eyes, lips, tongue, difficulty in swallowing or breathing) and to stop taking the drug until they have consulted with their physician. (See WARNINGS and ADVERSE REACTIONS . ) Symptomatic Hypotension Patients should be cautioned that light-headedness can occur, especially during the first days of trandolapril therapy, and should be reported to a physician.
If actual syncope occurs, patients should be told to stop taking the drug until they have consulted with their physician. (See WARNINGS .) All patients should be cautioned that inadequate fluid intake, excessive perspiration, diarrhea, or vomiting, resulting in reduced fluid volume, may precipitate an excessive fall in blood pressure with the same consequences of light-headedness and possible syncope. Patients planning to undergo any surgery and/or anesthesia should be told to inform their physician that they are taking an ACE inhibitor that has a long duration of action.
Hyperkalemia Patients should be told not to use potassium supplements or salt substitutes containing potassium without consulting their physician. (See PRECAUTIONS . ) Neutropenia Patients should be told to report promptly any indication of infection (e.g., sore throat, fever) which could be a sign of neutropenia. Pregnancy Female patients of childbearing age should be told about the consequences of exposure to trandolapril during pregnancy.
Discuss treatment options with women planning to become pregnant. Patients should be asked to report pregnancies to their physicians as soon as possible. NOTE: As with many other drugs, certain advice to patients being treated with trandolapril is warranted.
This information is intended to aid in the safe and effective use of this medication. It is not a disclosure of all possible adverse or intended effects.