
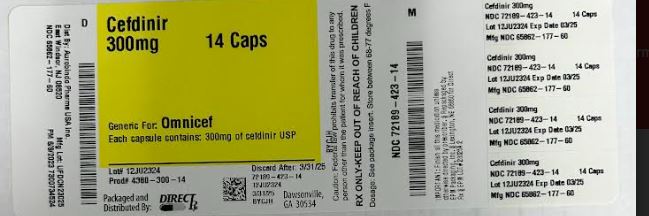
Cefdinir 300 mg Capsule, 14-count — NDC 72189-423-14 (Billing 72189-0423-14)
This is a package of 14 capsules of Cefdinir 300 mg Capsule from Direct_Rx, marketed since Feb 2023 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 040257
- GCN: 32231
- HICL (First Databank): 018548
- AHFS class code: 08:12.06.12
- RxCUI (RxNorm): 200346
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Cephalosporin Antibacterial class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Cefdinir is used to treat certain infections caused by bacteria. Cefdinir is in a class of medications called cephalosporin antibiotics. It works by killing bacteria. Antibiotics such as cefdinir will not work for colds, flu, or other viral infections. Using antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- It treats mild to moderate bacterial infections such as pneumonia, sinus infections, strep throat, skin infections and, in children, ear infections. It will not help colds or the f...
- No. You can take it with or without food. Try to take it at about the same times each day, and finish the full course even if you feel better.
- It can be. Aluminum or magnesium antacids and iron supplements can lower how much cefdinir your body absorbs. Take cefdinir at least 2 hours before or after them.
- I take an antacid or iron. Is that a problem?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cefdinir — tap one for details:
Cefdinir may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.7631 | $10.68 / 14 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 72189-0423-14 You're viewing this Main listing | 14 CAPSULE in 1 BOTTLE | 2023-02-08 | — | Active |
| 72189-0423-20 72189-423-20 | 20 CAPSULE in 1 BOTTLE | 2023-02-08 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 72189-0423-20?
What NDC number is used to bill for this package of Cefdinir 300 mg Capsule?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cefdinir 300 mg 00093-3160-06 | Teva | 60 capsules | $0.458 | AB | Availability likely | — |
| Cefdinir 300 mg 00904-7563-04 | Major | 30 capsules | $0.458 | AB | Availability likely | — |
| Cefdinir 300 mg 57237-0099-60 | Rising | 60 capsules | $0.458 | AB | Availability likely | — |
| Cefdinir 300 mg 60687-0699-21 | American | 30 capsules | $0.458 | AB | Availability likely | — |
| Cefdinir 300 mg 68001-0362-06 | BluePoint | 60 capsules | $0.458 | AB | Availability likely | — |
| Cefdinir 300 mg 68180-0711-60 | Lupin | 60 capsules | $0.458 | AB | Availability likely | — |
| Cefdinir 300 mg 00781-2176-01 | Sandoz | 100 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 42291-0043-60 | AvKARE | 60 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 43063-0959-20 | PD-Rx | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 43063-0964-14 | PD-Rx | 14 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 50090-1033-00 | A-S | 10 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 50090-2719-00 | A-S | 10 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 50090-6041-00 | A-S | 10 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 50090-6042-00 | A-S | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 63187-0989-14 | Proficient | 14 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 63629-5101-01 | Bryant | 10 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 63629-8968-01 | Bryant | 20 capsules | — | AB | FDA listed | — |
| cefdinir 300 mg 65862-0177-05 | Aurobindo | 500 capsules | — | — | FDA listed | — |
| Cefdinir 300 mg 67296-1448-07 | Redpharm | 14 capsules | — | AB | Discontinued | — |
| Cefdinir 300 mg 67877-0543-01 | Ascend | 100 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 68071-2401-02 | NuCare | 2 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 68071-2503-02 | NuCare | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 68071-3998-02 | NuCare | 2 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 68071-4007-02 | NuCare | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 68071-4856-02 | NuCare | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 68071-4946-02 | NuCare | 2 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 68071-5145-02 | NuCare | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 68788-7339-02 | Preferred | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 68788-7987-02 | Preferred | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 68788-8323-02 | Preferred | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 68788-8404-02 | Preferred | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 70518-1880-00 | REMEDYREPACK | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 70518-4169-00 | REMEDYREPACK | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 71205-0224-14 | Proficient | 14 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 71205-0576-06 | Proficient | 6 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 72189-0308-14 | DirectRx | 14 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mgthis 72189-0423-14 | Direct_Rx | 14 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 72789-0054-14 | PD-Rx | 14 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 72789-0061-20 | PD-Rx | 20 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 72789-0550-10 | PD-Rx | 10 capsules | — | AB | FDA listed | — |
| Cefdinir 300 mg 82868-0059-20 | Northwind | 20 capsules | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII UTY7PDF93L
A plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 767IP0Y5NH
A synthetic red colorant used to give medicines their color. It helps patients identify their medication and makes the product visually appealing.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
To reduce the development of drug-resistant bacteria and maintain the effectiveness of cefdinir and other antibacterial drugs, cefdinir should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
Cefdinir capsules, USP are indicated for the treatment of patients with mild to moderate infections caused by susceptible strains of the designated microorganisms in the conditions listed below. Adults and Adolescents Community-Acquired Pneumonia caused by Haemophilus influenzae (including β-lactamase producing strains), Haemophilus parainfluenzae (including β-lactamase producing strains), Streptococcus pneumoniae (penicillin-susceptible strains only), and Moraxella catarrhalis (including β-lactamase producing strains) (see CLINICAL STUDIES).
Acute Exacerbations of Chronic Bronchitis caused by Haemophilus influenzae (including β-lactamase producing strains), Haemophilus parainfluenzae (including β-lactamase producing strains), Streptococcus pneumoniae (penicillin-susceptible strains only), and Moraxella catarrhalis (including β-lactamase producing strains). Acute Maxillary Sinusitis caused by Haemophilus influenzae (including β-lactamase producing strains), Streptococcus pneumoniae (penicillin-susceptible strains only), and Moraxella catarrhalis (including β-lactamase producing strains).
NOTE: For information on use in pediatric patients, see PEDIATRIC USE and DOSAGE AND ADMINISTRATION. Pharyngitis/Tonsillitis caused by Streptococcus pyogenes (see CLINICAL STUDIES). NOTE: Cefdinir is effective in the eradication of S. pyogenes from the oropharynx.
Cefdinir has not, however, been studied for the prevention of rheumatic fever following S. pyogenes pharyngitis/tonsillitis. Only intramuscular penicillin has been demonstrated to be effective for the prevention of rheumatic fever. Uncomplicated Skin and Skin Structure Infections caused by Staphylococcus aureus (including β-lactamase producing strains) and Streptococcus pyogenes.
Pediatric Patients Acute Bacterial Otitis Media caused by Haemophilus influenzae (including β-lactamase producing strains), Streptococcus pneumoniae (penicillin-susceptible strains only), and Moraxella catarrhalis (including β-lactamase producing strains). Pharyngitis/Tonsillitis caused by Streptococcus pyogenes (see CLINICAL STUDIES). NOTE: Cefdinir is effective in the eradication of S. pyogenes from the oropharynx.
Cefdinir has not, however, been studied for the prevention of rheumatic fever following S. pyogenes pharyngitis/tonsillitis. Only intramuscular penicillin has been demonstrated to be effective for the prevention of rheumatic fever. Uncomplicated Skin and Skin Structure Infections caused by Staphylococcus aureus (including β-lactamase producing strains) and Streptococcus pyogenes.
⏱️ Dosage and Administration ▾
(see INDICATIONS AND USAGE for Indicated Pathogens) The recommended dosage and duration of treatment for infections in adults and adolescents are described in the following chart; the total daily dose for all infections is 600 mg. Once-daily dosing for 10 days is as effective as BID dosing. Once-daily dosing has not been studied in pneumonia or skin infections; therefore, cefdinir capsules should be administered twice daily in these infections.
Cefdinir capsules may be taken without regard to meals. Adults and Adolescents (Age 13 Years and Older) Type of Infection Dosage Duration Community-Acquired Pneumonia 300 mg q12h 10 days Acute Exacerbations of Chronic Bronchitis 300 mg q12h or 600 mg q24h 5 to 10 days 10 days Acute Maxillary Sinusitis 300 mg q12h or 600 mg q24h 10 days 10 days Pharyngitis/Tonsillitis 300 mg q12h or 600 mg q24h 5 to 10 days 10 days Uncomplicated Skin and Skin Structure Infections 300 mg q12h 10 days Patients With Renal Insufficiency For adult patients with creatinine clearance <30 mL/min, the dose of cefdinir should be 300 mg given once daily.
Creatinine clearance is difficult to measure in outpatients. However, the following formula may be used to estimate creatinine clearance (CLcr) in adult patients. For estimates to be valid, serum creatinine levels should reflect steady-state levels of renal function.
Males: CLcr = (weight) (140 – age) (72) (serum creatinine) Females: CLcr = 0.85 x above value where creatinine clearance is in mL/min, age is in years, weight is in kilograms, and serum creatinine is in mg/dL.1 The following formula may be used to estimate creatinine clearance in pediatric patients: CLcr = K x body length or height serum creatinine where K=0.55 for pediatric patients older than 1 year2 and 0.45 for infants (up to 1 year)3. In the above equation, creatinine clearance is in mL/min/1.73 m2, body length or height is in centimeters, and serum creatinine is in mg/dL.
For pediatric patients with a creatinine clearance of <30 mL/min/1.73 m2, the dose of cefdinir should be 7 mg/kg (up to 300 mg) given once daily. Patients on Hemodialysis Hemodialysis removes cefdinir from the body. In patients maintained on chronic hemodialysis, the recommended initial dosage regimen is a 300 mg or 7 mg/kg dose every other day.
At the conclusion of each hemodialysis session, 300 mg (or 7 mg/kg) should be given. Subsequent doses (300 mg or 7 mg/kg) are then administered every other day.
⛔ Contraindications ▾
Cefdinir capsules are contraindicated in patients with known allergy to the cephalosporin class of antibiotics.
⚠️ Warnings ▾
BEFORE THERAPY WITH CEFDINIR IS INSTITUTED, CAREFUL INQUIRY SHOULD BE MADE TO DETERMINE WHETHER THE PATIENT HAS HAD PREVIOUS HYPERSENSITIVITY REACTIONS TO CEFDINIR, OTHER CEPHALOSPORINS, PENICILLINS, OR OTHER DRUGS. IF CEFDINIR IS TO BE GIVEN TO PENICILLIN-SENSITIVE PATIENTS, CAUTION SHOULD BE EXERCISED BECAUSE CROSS-HYPERSENSITIVITY AMONG β-LACTAM ANTIBIOTICS HAS BEEN CLEARLY DOCUMENTED AND MAY OCCUR IN UP TO 10% OF PATIENTS WITH A HISTORY OF PENICILLIN ALLERGY. IF AN ALLERGIC REACTION TO CEFDINIR OCCURS, THE DRUG SHOULD BE DISCONTINUED.
SERIOUS ACUTE HYPERSENSITIVITY REACTIONS MAY REQUIRE TREATMENT WITH EPINEPHRINE AND OTHER EMERGENCY MEASURES, INCLUDING OXYGEN, INTRAVENOUS FLUIDS, INTRAVENOUS ANTIHISTAMINES, CORTICOSTEROIDS, PRESSOR AMINES, AND AIRWAY MANAGEMENT, AS CLINICALLY INDICATED. Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including cefdinir, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile.
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibacterial use.
Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibacterial use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibacterial treatment of C. difficile, and surgical evaluation should be instituted as clinically indicated.
🤒 Adverse Reactions ▾
Clinical Trials - Cefdinir Capsules (Adult and Adolescent Patients) In clinical trials, 5093 adult and adolescent patients (3841 U.S. and 1252 non-U.S.) were treated with the recommended dose of cefdinir capsules (600 mg/day). Most adverse events were mild and self-limiting. No deaths or permanent disabilities were attributed to cefdinir.
One hundred forty-seven of 5093 (3%) patients discontinued medication due to adverse events thought by the investigators to be possibly, probably, or definitely associated with cefdinir therapy. The discontinuations were primarily for gastrointestinal disturbances, usually diarrhea or nausea. Nineteen of 5093 (0.4%) patients were discontinued due to rash thought related to cefdinir administration.
In the U.S., the following adverse events were thought by investigators to be possibly, probably, or definitely related to cefdinir capsules in multiple-dose clinical trials (N = 3841 cefdinir-treated patients): ADVERSE EVENTS ASSOCIATED WITH CEFDINIR CAPSULES U.S. TRIALS IN ADULT AND ADOLESCENT PATIENTS (N = 3841)a Incidence ≥1% Diarrhea 15% Vaginal moniliasis 4% of women Nausea 3% Headache 2% Abdominal pain 1% Vaginitis 1% of women Incidence <1% but >0.1% Rash 0.9% Dyspepsia 0.7% Flatulence 0.7% Vomiting 0.7% Abnormal stools 0.3% Anorexia 0.3% Constipation 0.3% Dizziness 0.3% Dry mouth 0.3% Asthenia 0.2% Insomnia 0.2% Leukorrhea 0.2% of women Moniliasis 0.2% Pruritus 0.2% Somnolence 0.2% a 1733 males, 2108 females The following laboratory value changes of possible clinical significance, irrespective of relationship to therapy with cefdinir, were seen during clinical trials conducted in the U.S.: LABORATORY VALUE CHANGES OBSERVED WITH CEFDINIR CAPSULES U.S.
TRIALS IN ADULT AND ADOLESCENT PATIENTS (N = 3841) Incidence ≥1% ↑Urine leukocytes 2% ↑Urine protein 2% ↑Gamma-glutamyltransferasea 1% ↓Lymphocytes, ↑Lymphocytes 1%, 0.2% ↑Microhematuria 1% Incidence <1% but >0.1% ↑Glucosea 0.9% ↑Urine glucose 0.9% ↑White blood cells, ↓White blood cells 0.9%, 0.7% ↑Alanine aminotransferase (ALT) 0.7% ↑Eosinophils 0.7% ↑Urine specific gravity, ↓Urine specific gravitya 0.6%, 0.2% ↓Bicarbonatea 0.6% ↑Phosphorus, ↓Phosphorusa 0.6%, 0.3% ↑Aspartate aminotransferase (AST) 0.4% ↑Alkaline phosphatase 0.3% ↑Blood urea nitrogen (BUN) 0.3% ↓Hemoglobin 0.3% ↑Polymorphonuclear neutrophils (PMNs), ↓PMNs 0.3%, 0.2% ↑Bilirubin 0.2% ↑Lactate dehydrogenasea 0.2% ↑Platelets 0.2% ↑Potassiuma 0.2% ↑Urine pHa 0.2% a N <3841 for these parameters Clinical Trials - Cefdinir for Oral Suspension (Pediatric Patients) In clinical trials, 2289 pediatric patients (1783 U.S. and 506 non-U.S.) were treated with the recommended dose of cefdinir suspension (14 mg/kg/day).
Most adverse events were mild and self-limiting. No deaths or permanent disabilities were attributed to cefdinir. Forty of 2289 (2%) patients discontinued medication due to adverse events considered by the investigators to be possibly, probably, or definitely associated with cefdinir therapy.
Discontinuations were primarily for gastrointestinal disturbances, usually diarrhea. Five of 2289 (0.2%) patients were discontinued due to rash thought related to cefdinir administration. In the U.S., the following adverse events were thought by investigators to be possibly, probably, or definitely related to cefdinir suspension in multiple-dose clinical trials (N = 1783 cefdinir-treated patients): a 977 males, 806 females b Laboratory changes were occasionally reported as adverse events.
ADVERSE EVENTS ASSOCIATED WITH CEFDINIR SUSPENSION U.S. TRIALS IN PEDIATRIC PATIENTS (N = 1783)a Incidence ≥1% Diarrhea 8% Rash 3% Vomiting 1% Incidence <1% but >0.1% Cutaneous moniliasis 0.9% Abdominal pain 0.8% Leukopeniab 0.3% Vaginal moniliasis 0.3% of girls Vaginitis 0.3% of girls Abnormal stools 0.2% Dyspepsia 0.2% Hyperkinesia 0.2% Increased ASTb 0.2% Maculopapular rash 0.2% Nausea 0.2% NOTE: In both cefdinir- and control-treated patients, rates of diarrhea and rash were higher in the youngest pedia… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
Information on cefdinir overdosage in humans is not available. In acute rodent toxicity studies, a single oral 5600 mg/kg dose produced no adverse effects. Toxic signs and symptoms following overdosage with other β-lactam antibiotics have included nausea, vomiting, epigastric distress, diarrhea, and convulsions.
Hemodialysis removes cefdinir from the body. This may be useful in the event of a serious toxic reaction from overdosage, particularly if renal function is compromised.
🧬 Clinical Pharmacology ▾
Pharmacokinetics and Drug Metabolism Absorption Oral Bioavailability Maximal plasma cefdinir concentrations occur 2 to 4 hours postdose following capsule or suspension administration. Plasma cefdinir concentrations increase with dose, but the increases are less than dose-proportional from 300 mg (7 mg/kg) to 600 mg (14 mg/kg). Following administration of suspension to healthy adults, cefdinir bioavailability is 120% relative to capsules.
Estimated bioavailability of cefdinir capsules is 21% following administration of a 300 mg capsule dose, and 16% following administration of a 600 mg capsule dose. Estimated absolute bioavailability of cefdinir suspension is 25%. Cefdinir oral suspension of 250 mg/5 mL strength was shown to be bioequivalent to the 125 mg/5 mL strength in healthy adults under fasting conditions.
Effect of Food The Cmax and AUC of cefdinir from the capsules are reduced by 16% and 10%, respectively, when given with a high-fat meal. In adults given the 250 mg/5 mL oral suspension with a high-fat meal, the Cmax and AUC of cefdinir are reduced by 44% and 33%, respectively. The magnitude of these reductions is not likely to be clinically significant because the safety and efficacy studies of oral suspension in pediatric patients were conducted without regard to food intake.
Therefore, cefdinir may be taken without regard to food. Cefdinir Capsules Cefdinir plasma concentrations and pharmacokinetic parameter values following administration of single 300 and 600 mg oral doses of cefdinir to adult subjects are presented in the following table: Mean (±SD) Plasma Cefdinir Pharmacokinetic Parameter Values Following Administration of Capsules to Adult Subjects Dose Cmax (mcg/mL) tmax (hr) AUC (mcg•hr/mL) 300 mg 1.6 (0.55) 2.9 (0.89) 7.05 (2.17) 600 mg 2.87 (1.01) 3 (0.66) 11.1 (3.87) Cefdinir Suspension Cefdinir plasma concentrations and pharmacokinetic parameter values following administration of single 7 and 14 mg/kg oral doses of cefdinir to pediatric subjects (age 6 months to 12 years) are presented in the following table: Mean (±SD) Plasma Cefdinir Pharmacokinetic Parameter Values Following Administration of Suspension to Pediatric Subjects Dose Cmax (mcg/mL) tmax (hr) AUC (mcg•hr/mL) 7 mg/kg 2.3 (0.65) 2.2 (0.6) 8.31 (2.5) 14 mg/kg 3.86 (0.62) 1.8 (0.4) 13.4 (2.64) Multiple Dosing Cefdinir does not accumulate in plasma following once- or twice-daily administration to subjects with normal renal function.
Distribution The mean volume of distribution (Vdarea) of cefdinir in adult subjects is
0.35L/kg (±0.29); in pediatric subjects (age 6 months to 12 years), cefdinir Vdarea is
0.67L/kg (±0.38). Cefdinir is 60% to 70% bound to plasma proteins in both adult and pediatric subjects; binding is independent of concentration. Skin Blister In adult subjects, median (range) maximal blister fluid cefdinir concentrations of 0.65 (0.33 to 1.1) and 1.1 (0.49 to 1.9) mcg/mL were observed 4 to 5 hours following administration of 300 and 600 mg doses, respectively.
Mean (±SD) blister Cmax and AUC(0-∞) values were 48% (±13) and 91% (±18) of corresponding plasma values. Tonsil Tissue In adult patients undergoing elective tonsillectomy, respective median tonsil tissue cefdinir concentrations 4 hours after administration of single 300 and 600 mg doses were 0.25 (0.22 to 0.46) and 0.36 (0.22 to 0.8) mcg/g. Mean tonsil tissue concentrations were 24% (±8) of corresponding plasma concentrations.
Sinus Tissue In adult patients undergoing elective maxillary and ethmoid sinus surgery, respective median sinus tissue cefdinir concentrations 4 hours after administration of single 300 and 600 mg doses were <0.12 (<0.12 to 0.46) and 0.21 (<0.12 to 2) mcg/g. Mean sinus tissue concentrations were 16% (±20) of corresponding plasma concentrations. Lung Tissue In adult patients undergoing diagnostic bronchoscopy, respective median bronchial mucosa cefdinir concentrations 4 hours after administration of single 300 and 600 mg doses were 0.78 (<0.06 to 1.33)… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
Cefdinir Capsules USP, 300 mg are lavender opaque/turquoise opaque size ‘0’ hard gelatin capsule filled with off-white to yellow powder and imprinted with ‘E99’ on turquoise opaque body with black ink. Bottles of 30 NDC 65862-177-30 Bottles of 60 NDC 65862-177-60 Bottles of 500 NDC 65862-177-05 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature]. Preserve in tight, light-resistant containers.
📋 Description ▾
Cefdinir capsules, USP contain the active ingredient cefdinir, an extended-spectrum, semisynthetic cephalosporin, for oral administration. Chemically, cefdinir is [6R-[6α, 7β (Z)]]-7-[[(2-amino-4-thiazolyl)(hydroxyimino)acetyl]amino]-3-ethenyl-8-oxo-5-thia-1-azabicyclo[4.2.0]oct-2-ene-2-carboxylic acid. Cefdinir USP is a white to slightly brownish-yellow solid. It is slightly soluble in dilute hydrochloric acid and sparingly soluble in
0.1M pH 7.0 phosphate buffer. The molecular formula is C14H13N5O5S2 and the molecular weight is 395.42. Cefdinir has the structural formula shown below: [Chemical Structure] Cefdinir capsules, USP contain 300 mg cefdinir USP and the following inactive ingredients: carboxymethylcellulose calcium, colloidal silicon dioxide and magnesium stearate.
The empty hard gelatin capsule shells contain FD&C Blue #1, D&C Red #28, titanium dioxide, gelatin and sodium lauryl sulphate. The capsules are printed with edible ink containing black iron oxide and shellac.
⚠️ Precautions ▾
General Prescribing cefdinir in the absence of a proven or strongly suspected bacterial infection or a prophylactic indication is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria. As with other broad-spectrum antibiotics, prolonged treatment may result in the possible emergence and overgrowth of resistant organisms. Careful observation of the patient is essential.
If superinfection occurs during therapy, appropriate alternative therapy should be administered. Cefdinir, as with other broad-spectrum antimicrobials (antibiotics), should be prescribed with caution in individuals with a history of colitis. In patients with transient or persistent renal insufficiency (creatinine clearance <30 mL/min), the total daily dose of cefdinir should be reduced because high and prolonged plasma concentrations of cefdinir can result following recommended doses (see DOSAGE AND ADMINISTRATION).
Information for Patients Patients should be counseled that antibacterial drugs including cefdinir should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When cefdinir is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by cefdinir or other antibacterial drugs in the future. Antacids containing magnesium or aluminum interfere with the absorption of cefdinir. If this type of antacid is required during cefdinir therapy, cefdinir should be taken at least 2 hours before or after the antacid.
Iron supplements, including multivitamins that contain iron, interfere with the absorption of cefdinir. If iron supplements are required during cefdinir therapy, cefdinir should be taken at least 2 hours before or after the supplement. Iron-fortified infant formula does not significantly interfere with the absorption of cefdinir.
Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued. Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic. If this occurs, patients should contact their physician as soon as possible.
Drug Interactions Antacids (aluminum- or magnesium-containing) Concomitant administration of 300 mg cefdinir capsules with 30 mL Maalox® TC suspension reduces the rate (Cmax) and extent (AUC) of absorption by approximately 40%. Time to reach Cmax is also prolonged by 1 hour. There are no significant effects on cefdinir pharmacokinetics if the antacid is administered 2 hours before or 2 hours after cefdinir.
If antacids are required during cefdinir therapy, cefdinir should be taken at least 2 hours before or after the antacid. Probenecid As with other β-lactam antibiotics, probenecid inhibits the renal excretion of cefdinir, resulting in an approximate doubling in AUC, a 54% increase in peak cefdinir plasma levels, and a 50% prolongation in the apparent elimination t½. Iron Supplements and Foods Fortified With Iron Concomitant administration of cefdinir with a therapeutic iron supplement containing 60 mg of elemental iron (as FeSO4) or vitamins supplemented with 10 mg of elemental iron reduced extent of absorption by 80% and 31%, respectively.
If iron supplements are required during cefdinir therapy, cefdinir should be taken at least 2 hours before or after the supplement. The effect of foods highly fortified with elemental iron (primarily iron-fortified breakfast cereals) on cefdinir absorption has not been studied. Concomitantly administered iron-fortified infant formul… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
Community-Acquired Bacterial Pneumonia In a controlled, double-blind study in adults and adolescents conducted in the U.S., cefdinir BID was compared with cefaclor 500 mg TID. Using strict evaluability and microbiologic/clinical response criteria 6 to 14 days posttherapy, the following clinical cure rates, presumptive microbiologic eradication rates, and statistical outcomes were obtained: U.S. Community-Acquired Pneumonia Study Cefdinir vs Cefaclor Cefdinir BID Cefaclor TID Outcome Clinical Cure Rates 150/187 (80%) 147/186 (79%) Cefdinir equivalent to control Eradication Rates Overall 177/195 (91%) 184/200 (92%) Cefdinir equivalent to control S. pneumoniae 31/31 (100%) 35/35 (100%) H. influenzae 55/65 (85%) 60/72 (83%) M. catarrhalis 10/10 (100%) 11/11 (100%) H. parainfluenzae 81/89 (91%) 78/82 (95%) In a second controlled, investigator-blind study in adults and adolescents conducted primarily in Europe, cefdinir BID was compared with amoxicillin/clavulanate 500/125 mg TID.
Using strict evaluability and clinical response criteria 6 to 14 days posttherapy, the following clinical cure rates, presumptive microbiologic eradication rates, and statistical outcomes were obtained: European Community-Acquired Pneumonia Study Cefdinir vs Amoxicillin/Clavulanate Cefdinir BID Amoxicillin/ Clavulanate TID Outcome Clinical Cure Rates 83/104 (80%) 86/97(89%) Cefdinir not equivalent to control Eradication Rates Overall 85/96 (89%) 84/90 (93%) Cefdinir equivalent to control S. pneumoniae 42/44 (95%) 43/44 (98%) H. influenzae 26/35 (74%) 21/26 (81%) M. catarrhalis 6/6 (100%) 8/8 (100%) H. parainfluenzae 11/11 (100%) 12/12 (100%) Streptococcal Pharyngitis/Tonsillitis In four controlled studies conducted in the United States, cefdinir was compared with 10 days of penicillin in adult, adolescent, and pediatric patients.
Two studies (one in adults and adolescents, the other in pediatric patients) compared 10 days of cefdinir QD or BID to penicillin 250 mg or 10 mg/kg QID. Using strict evaluability and microbiologic/clinical response criteria 5 to 10 days posttherapy, the following clinical cure rates, microbiologic eradication rates, and statistical outcomes were obtained: Pharyngitis/Tonsillitis Studies Cefdinir (10 days) vs Penicillin (10 days) Study Efficacy Parameter Cefdinir QD Cefdinir BID Penicillin QID Outcome Adults/ Adolescents Eradication of S. pyogenes 192/210 (91%) 199/217 (92%) 181/217 (83%) Cefdinir superior to control Clinical Cure Rates 199/210 (95%) 209/217 (96%) 193/217 (89%) Cefdinir superior to control Pediatric Patients Eradication of S. pyogenes 215/228 (94%) 214/227 (94%) 159/227 (70%) Cefdinir superior to control Clinical Cure Rates 222/228 (97%) 218/227 (96%) 196/227 (86%) Cefdinir superior to control Two studies (one in adults and adolescents, the other in pediatric patients) compared 5 days of cefdinir BID to 10 days of penicillin 250 mg or 10 mg/kg QID.
Using strict evaluability and microbiologic/clinical response criteria 4 to 10 days posttherapy, the following clinical cure rates, microbiologic eradication rates, and statistical outcomes were obtained: Pharyngitis/Tonsillitis Studies Cefdinir (5 days) vs Penicillin (10 days) Study Efficacy Parameter Cefdinir BID Penicillin QID Outcome Adults/ Adolescents Eradication of S. pyogenes 193/218 (89%) 176/214 (82%) Cefdinir equivalent to control Clinical Cure Rates 194/218 (89%) 181/214 (85%) Cefdinir equivalent to control Pediatric Patients Eradication of S. pyogenes 176/196 (90%) 135/193 (70%) Cefdinir superior to control Clinical Cure Rates 179/196 (91%) 173/193 (90%) Cefdinir equivalent to control
📚 References ▾
Cockcroft DW, Gault MH. Prediction of creatinine clearance from serum creatinine. Nephron 1976;16:31-41.
Schwartz GJ, Haycock GB, Edelmann CM, Spitzer A. A simple estimate of glomerular filtration rate in children derived from body length and plasma creatinine. Pediatrics 1976;58:259-63.
Schwartz GJ, Feld LG, Langford DJ. A simple estimate of glomerular filtration rate in full-term infants during the first year of life. J Pediatrics 1984;104:849-54.
Maalox® TC is a registered trademark of Novartis Consumer Health, Inc. Clinitest® is a registered trademark of Miles, Inc. Clinistix® is a registered trademark of Bayer Corporation.
Tes-Tape® is a registered trademark of Lilly Inc. Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 10/2021
📄 Package Label / Principal Display Panel ▾
72189-423-20
72189-423-14
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |