
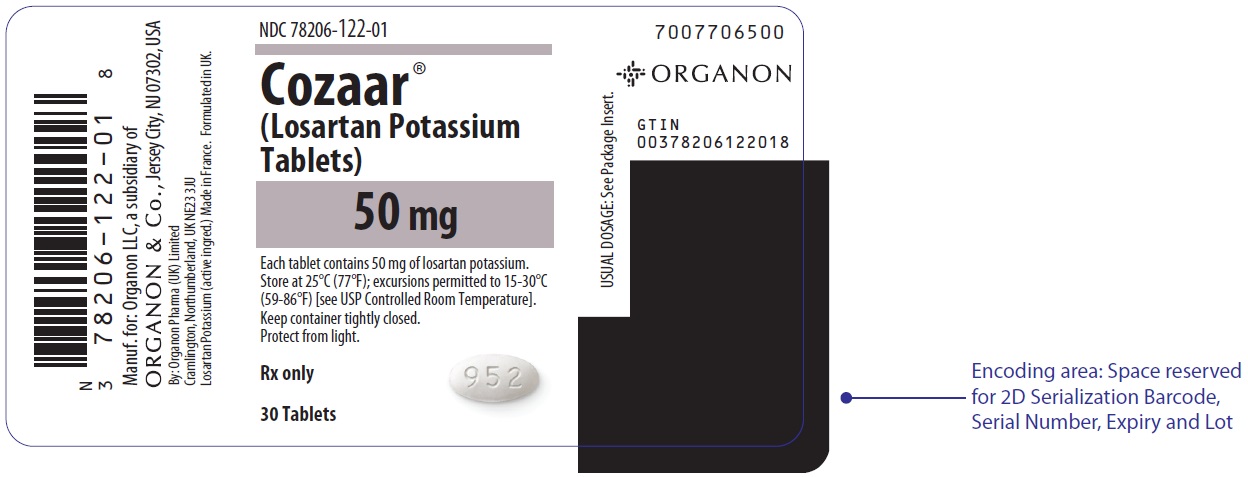
COZAAR losartan potassium 50 mg Tablet, Film Coated, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Angiotensin 2 Receptor Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Losartan is used alone or in combination with other medications to treat high blood pressure. Losartan is also used to decrease the risk of stroke in people who have high blood pressure and a heart condition called left ventricular hypertrophy (enlargement of the walls of the left side of the heart). Losartan may not decrease the risk of stroke in African Americans who have these conditions. This medication is also used to treat kidney disease in people who have type 2 diabetes (condition in which the body does not use insulin normally and therefore cannot control the amount of sugar in the bl...
Read the full MedlinePlus article ↗- Losartan is mainly used to lower high blood pressure, which protects you from strokes and heart attacks over time. Depending on your situation, your doctor may also have prescribed...
- What exactly is losartan supposed to do for me?
- You can take losartan at any time of day that works for you, as long as you're consistent. Taking it with or without food is both fine — eating may slow things down a tiny bit, but...
- Does it matter what time of day I take it, and can I take it with food?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Losartan Potassium — tap one for details:
Losartan Potassium may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $4.494 | $134.83 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $4.55 | $136.43 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $4.61 | $138.22 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Losartan Potassium 50 mg 00904-7048-61 | Major | 1 tablet | $0.032 | AB | Availability likely | save 99% |
| Losartan Potassium 50 mg 11788-0101-10 | AiPing | 1000 tablets | $0.032 | AB | Availability likely | save 99% |
| Losartan potassium 50 mg 33342-0045-07 | Macleods | 30 tablets | $0.032 | AB | Availability likely | save 99% |
| Losartan Potassium 50 mg 43547-0361-03 | Solco | 30 tablets | $0.032 | AB | Availability likely | save 99% |
| Losortan Potassium 50 mg 50268-0505-15 | AvPAK | 1 tablet | $0.032 | AB | Availability likely | save 99% |
| Losartan Potassium 50 mg 62332-0028-30 | Alembic | 30 tablets | $0.032 | AB | Availability likely | save 99% |
| Losartan Potassium 50 mg 65862-0202-30 | Aurobindo | 30 tablets | $0.032 | — | Availability likely | save 99% |
| Losartan Potassium 50 mg 68084-0347-01 | American | 1 tablet | $0.032 | AB | Availability likely | save 99% |
| Losartan Potassium 50 mg 70010-0742-03 | Granules | 30 tablets | $0.032 | AB | Availability likely | save 99% |
| Losartan potassium 50 mg 72205-0142-30 | Novadoz | 30 tablets | $0.032 | AB | Availability likely | save 99% |
| Losartan Potassium 50 mg 72603-0341-01 | NorthStar | 90 tablets | $0.032 | AB | Availability likely | save 99% |
| Losartan Potassium 50 mg 82009-0043-10 | Quallent | 1000 tablets | $0.032 | AB | Availability likely | save 99% |
| LOSARTAN POTASSIUM 50 mg 64380-0934-04 | Strides | 30 tablets | $0.034 | AB | Availability likely | save 99% |
| Losartan Potassium 50 mg 42571-0111-10 | Micro | 1000 tablets | $0.038 | AB | Discontinued | save 99% |
| Cozaar 50 mgthis 78206-0122-01 | Organon | 30 tablets | $4.494 | AB | Availability likely | — |
| Losartan Potassium 50 mg 00615-7959-05 | NCS | 15 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 29300-0145-01 | Unichem | 100 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 31722-0701-05 | Camber | 500 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 42708-0055-30 | QPharma, | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 42708-0113-30 | QPharma, | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 42708-0152-30 | QPharma, | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 43063-0854-60 | PD-Rx | 60 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 43063-0955-90 | PD-Rx | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 46708-0446-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 50090-4489-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 50090-4910-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 50090-5480-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 50090-7945-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 50090-7946-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| LOSARTAN POTASSIUM 50 mg 51655-0418-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 51655-0795-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 55154-2089-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 55154-2327-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Losartan potassium Tablets, 50 mg 59746-0334-01 | Jubilant | 100 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 60760-0786-30 | St. | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 62207-0742-49 | Granules | 1000 tablets | — | AB | FDA listed | — |
| Losortan Potassium 50 mg 63187-0071-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 63187-0296-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 63187-0830-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Losartan potassium Tablets, 50 mg 63629-9192-01 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 65841-0730-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Losartan potassium 50 mg 67046-1510-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 67296-2225-01 | Redpharm | 7 tablets | — | AB | Discontinued | — |
| Losartan Potassium 50 mg 68071-1517-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 68071-2690-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 68071-4471-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 68071-4943-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 68071-5040-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 68071-5175-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 68071-5209-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 68071-5212-01 | NuCare | 120 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 68180-0377-01 | Lupin | 100 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 68382-0136-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Losartan potassium 50 mg 68788-4127-03 | Preferred | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 68788-7665-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 68788-8189-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 70518-0245-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 70518-2316-01 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 71205-0281-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| LOSARTAN POTASSIUM 50 mg 71205-0598-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 71335-0262-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 71335-1102-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 71335-1221-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Losartan potassium Tablets, 50 mg 71335-1817-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 71610-0207-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 71610-0440-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 71610-0466-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Losartan potassium Tablets, 50 mg 72162-1697-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 72162-2507-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 72189-0096-30 | DIRECT | 30 tablets | — | AB | FDA listed | — |
| LOSARTAN POTASSIUM 50 mg 72789-0164-90 | PD-Rx | 90 tablets | — | AB | FDA listed | — |
| LOSARTAN POTASSIUM 50 mg 72789-0179-90 | PD-Rx | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 72865-0142-10 | XLCare | 1000 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 87441-0053-01 | Unit | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 50 mg 70518-3282-02 | REMEDYREPACK | 90 tablets | — | AB | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 78206-0122-01 You're viewing this | 30 TABLET, FILM COATED in 1 BOTTLE (78206-122-01) | $4.49 / ea | $134.83 | 2021-06-01 | Active |
| 78206-0122-02 | 90 TABLET, FILM COATED in 1 BOTTLE (78206-122-02) | $4.49 / ea | $404.48 | 2021-06-01 | Active |
You're viewing the smallest of 2 pack sizes for this product.
This pack has the lowest per-ea cost of the 2 priced pack sizes ($4.49 NADAC).
Pack size FAQ
What quantity is in NDC 78206-0122-01?
What is the difference between NDC 78206-0122-01 and NDC 78206-0122-02?
What NDC number is used to bill for this package of COZAAR losartan potassium 50 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue COZAAR as soon as possible. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [see Warnings and Precautions (5.1) ] . WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning.
When pregnancy is detected, discontinue COZAAR as soon as possible. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE COZAAR is an angiotensin II receptor blocker (ARB) indicated for: Treatment of hypertension, to lower blood pressure in adults and children greater than 6 years old. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. ( 1.1 ) Reduction of the risk of stroke in patients with hypertension and left ventricular hypertrophy.
There is evidence that this benefit does not apply to Black patients. ( 1.2 ) Treatment of diabetic nephropathy with an elevated serum creatinine and proteinuria in patients with type 2 diabetes and a history of hypertension. ( 1.3 )
1.1Hypertension COZAAR ® is indicated for the treatment of hypertension in adults and pediatric patients 6 years of age and older, to lower blood pressure. Lowering blood pressure lowers the risk of fatal and nonfatal cardiovascular (CV) events, primarily strokes and myocardial infarction. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including losartan.
Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than 1 drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program's Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC).
Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits. The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly.
Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in Black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. COZAAR may be administered with other antihypertensive agents.
1.2Hypertensive Patients with Left Ventricular Hypertrophy COZAAR is indicated to reduce the risk of stroke in patients with hypertension and left ventricular hypertrophy, but there is evidence that this benefit does not apply to Black patients [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3) ] .
1.3Nephropathy in Type 2 Diabetic Patients COZAAR is indicated for the treatment of diabetic nephropathy with an elevated serum creatinine and proteinuria (urinary albumin to creatinine ratio ≥300 mg/g) in patients with type 2 diabetes and a history of hypertension. In this population, COZAAR reduces the rate of progression of nephropathy as measured by the occurrence of doubling of serum creatinine or end stage renal disease (need for dialysis or…
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Hypertension Usual adult dose: 50 mg once daily. ( 2.1 ) Usual pediatric starting dose: 0.7 mg per kg once daily (up to 50 mg). ( 2.1 ) Hypertensive Patients with Left Ventricular Hypertrophy Usual starting dose: 50 mg once daily.
( 2.2 ) Add hydrochlorothiazide 12.5 mg and/or increase COZAAR to 100 mg followed by an increase to hydrochlorothiazide 25 mg if further blood pressure response is needed. ( 2.2 , 14.2 ) Nephropathy in Type 2 Diabetic Patients Usual dose: 50 mg once daily. ( 2.3 ) Increase dose to 100 mg once daily if further blood pressure response is needed.
( 2.3 )
2.1Hypertension Adult Hypertension The usual starting dose of COZAAR is 50 mg once daily. The dosage can be increased to a maximum dose of 100 mg once daily as needed to control blood pressure [see Clinical Studies (14.1) ] . A starting dose of 25 mg is recommended for patients with possible intravascular depletion (e.g., on diuretic therapy).
Pediatric Hypertension The usual recommended starting dose is 0.7 mg per kg once daily (up to 50 mg total) administered as a tablet or a suspension [see Dosage and Administration (2.5) ] . Dosage should be adjusted according to blood pressure response. Doses above 1.4 mg per kg (or in excess of 100 mg) daily have not been studied in pediatric patients [see Clinical Pharmacology (12.3) , Clinical Studies (14.1) , and Warnings and Precautions (5.2) ] .
COZAAR is not recommended in pediatric patients less than 6 years of age or in pediatric patients with estimated glomerular filtration rate less than 30 mL/min/1.73 m 2 [see Use in Specific Populations (8.4) , Clinical Pharmacology (12.3) , and Clinical Studies (14) ] .
2.2Hypertensive Patients with Left Ventricular Hypertrophy The usual starting dose is 50 mg of COZAAR once daily. Hydrochlorothiazide 12.5 mg daily should be added and/or the dose of COZAAR should be increased to 100 mg once daily followed by an increase in hydrochlorothiazide to 25 mg once daily based on blood pressure response [see Clinical Studies (14.2) ] .
2.3Nephropathy in Type 2 Diabetic Patients The usual starting dose is 50 mg once daily. The dose should be increased to 100 mg once daily based on blood pressure response [see Clinical Studies (14.3) ] .
2.4Dosage Modifications in Patients with Hepatic Impairment In patients with mild-to-moderate hepatic impairment the recommended starting dose of COZAAR is 25 mg once daily. COZAAR has not been studied in patients with severe hepatic impairment [see Use in Specific Populations (8.8) and Clinical Pharmacology (12.3) ] .
2.5Preparation of Suspension (for 200 mL of a 2.5 mg/mL suspension) Add 10 mL of Purified Water USP to an 8 ounce (240 mL) amber polyethylene terephthalate (PET) bottle containing ten 50 mg COZAAR tablets. Immediately shake for at least 2 minutes. Let the concentrate stand for 1 hour and then shake for 1 minute to disperse the tablet contents.
Separately prepare a 50/50 volumetric mixture of Ora-Plus ™ and Ora-Sweet SF ™ . Add 190 mL of the 50/50 Ora-Plus ™ /Ora-Sweet SF ™ mixture to the tablet and water slurry in the PET bottle and shake for 1 minute to disperse the ingredients. The suspension should be refrigerated at 2-8°C (36-46°F) and can be stored for up to 4 weeks.
Shake the suspension prior to each use and return promptly to the refrigerator.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS COZAAR, 25 mg, are white, oval, film-coated tablets with code 951 on one side. COZAAR, 50 mg, are white, oval, film-coated tablets with code 952 on one side and scored on the other. COZAAR, 100 mg, are white, teardrop-shaped, film-coated tablets with code 960 on one side. Tablets: 25 mg; 50 mg; and 100 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS COZAAR is contraindicated: In patients who are hypersensitive to any component of this product. For coadministration with aliskiren in patients with diabetes. Hypersensitivity to any component. ( 4 ) Coadministration with aliskiren in patients with diabetes. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypotension: Correct volume or salt depletion prior to administration of COZAAR. ( 5.2 ) Monitor renal function and potassium in susceptible patients. ( 5.3 , 5.4 )
5.1Fetal Toxicity COZAAR can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue COZAAR as soon as possible [see Use in Specific Populations (8.1) ] .
5.2Hypotension in Volume- or Salt-Depleted Patients In patients with an activated renin-angiotensin system, such as volume- or salt-depleted patients (e.g., those being treated with high doses of diuretics), symptomatic hypotension may occur after initiation of treatment with COZAAR. Correct volume or salt depletion prior to administration of COZAAR [see Dosage and Administration (2.1) ] .
5.3Renal Function Deterioration Changes in renal function including acute renal failure can be caused by drugs that inhibit the renin-angiotensin system and by diuretics. Patients whose renal function may depend in part on the activity of the renin-angiotensin system (e.g., patients with renal artery stenosis, chronic kidney disease, severe congestive heart failure, or volume depletion) may be at particular risk of developing acute renal failure on COZAAR. Monitor renal function periodically in these patients.
Consider withholding or discontinuing therapy in patients who develop a clinically significant decrease in renal function on COZAAR [see Drug Interactions (7.3) and Use in Specific Populations (8.7) ] .
5.4Hyperkalemia Monitor serum potassium periodically and treat appropriately. Dosage reduction or discontinuation of COZAAR may be required [see Adverse Reactions (6.1) ] . Concomitant use of other drugs that may increase serum potassium may lead to hyperkalemia [see Drug Interactions (7.1) ] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence ≥2% and greater than placebo) are: dizziness, upper respiratory infection, nasal congestion, and back pain. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Organon LLC, a subsidiary of Organon & Co., at 1-844-674-3200 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Hypertension COZAAR has been evaluated for safety in more than 3300 adult patients treated for essential hypertension and 4058 patients/subjects overall. Over 1200 patients were treated for over 6 months and more than 800 for over one year.
Treatment with COZAAR was well-tolerated with an overall incidence of adverse events similar to that of placebo. In controlled clinical trials, discontinuation of therapy for adverse events occurred in 2.3% of patients treated with COZAAR and 3.7% of patients given placebo. In 4 clinical trials involving over 1000 patients on various doses (10-150 mg) of losartan potassium and over 300 patients given placebo, the adverse events that occurred in ≥2% of patients treated with COZAAR and more commonly than placebo were: dizziness (3% vs.
2%), upper respiratory infection (8% vs. 7%), nasal congestion (2% vs. 1%), and back pain (2% vs.
1%). The following less common adverse reactions have been reported: Blood and lymphatic system disorders: Anemia. Psychiatric disorders: Depression.
Nervous system disorders: Somnolence, headache, sleep disorders, paresthesia, migraine. Ear and labyrinth disorders: Vertigo, tinnitus. Cardiac disorders: Palpitations, syncope, atrial fibrillation, CVA.
Respiratory, thoracic and mediastinal disorders: Dyspnea. Gastrointestinal disorders: Abdominal pain, constipation, nausea, vomiting. Skin and subcutaneous tissue disorders: Urticaria, pruritus, rash, photosensitivity.
Musculoskeletal and connective tissue disorders: Myalgia, arthralgia. Reproductive system and breast disorders: Impotence. General disorders and administration site conditions: Edema.
Cough Persistent dry cough (with an incidence of a few percent) has been associated with ACE-inhibitor use and in practice can be a cause of discontinuation of ACE-inhibitor therapy. Two prospective, parallel-group, double-blind, randomized, controlled trials were conducted to assess the effects of losartan on the incidence of cough in hypertensive patients who had experienced cough while receiving ACE-inhibitor therapy. Patients who had typical ACE-inhibitor cough when challenged with lisinopril, whose cough disappeared on placebo, were randomized to losartan 50 mg, lisinopril 20 mg, or either placebo (one study, n=97) or 25 mg hydrochlorothiazide (n=135).
The double-blind treatment period lasted up to 8 weeks. The incidence of cough is shown in Table 1 below. Table 1 Study 1 Demographics = (89% Caucasian, 64% female) HCTZ Losartan Lisinopril Cough 25% 17% 69% Study 2 Demographics = (90% Caucasian, 51% female) Placebo Losartan Lisinopril Cough 35% 29% 62% These studies demonstrate that the incidence of cough associated with losartan therapy, in a population that all had cough associated with ACE-inhibitor therapy, is similar to that associated with hydrochlorothiazide or placebo therapy.
Cases of cough, including positive re-challenges, have been reported with the use of losartan in postmarketing experience. Hypertensive Patients with Left Ventricular Hypertrophy In the Losartan Intervention for Endpoint (LIFE) study, adverse reactions with COZAAR were similar to those reported previously for patients with hypertension. Nephropathy in Type 2 Diabetic Patients In the Reduction of Endpoints in NIDDM with the Angiotensin II Receptor Antagonist Losartan (RENAAL) study involving 1513 patients treated with CO…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Agents Increasing Serum Potassium: Risk of hyperkalemia. ( 7.1 ) Lithium: Risk of lithium toxicity. ( 7.2 ) NSAIDs: Increased risk of renal impairment and reduced diuretic, natriuretic, and antihypertensive effects. ( 7.3 ) Dual Inhibition of the Renin-Angiotensin System: Increased risk of renal impairment, hypotension, syncope, and hyperkalemia. ( 7.4 )
7.1Agents Increasing Serum Potassium Coadministration of losartan with other drugs that raise serum potassium levels may result in hyperkalemia. Monitor serum potassium in such patients.
7.2Lithium Increases in serum lithium concentrations and lithium toxicity have been reported during concomitant administration of lithium with angiotensin II receptor antagonists. Monitor serum lithium levels during concomitant use.
7.3Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) Including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors) In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists (including losartan) may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving losartan and NSAID therapy.
The antihypertensive effect of angiotensin II receptor antagonists, including losartan, may be attenuated by NSAIDs, including selective COX-2 inhibitors.
7.4Dual Blockade of the Renin-Angiotensin System (RAS) Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, syncope, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. The Veterans Affairs Nephropathy in Diabetes (VA NEPHRON-D) trial enrolled 1448 patients with type 2 diabetes, elevated urinary-albumin-to-creatinine ratio, and decreased estimated glomerular filtration rate (GFR 30 to 89.9 mL/min), randomized them to lisinopril or placebo on a background of losartan therapy and followed them for a median of 2.2 years.
Patients receiving the combination of losartan and lisinopril did not obtain any additional benefit compared to monotherapy for the combined endpoint of decline in GFR, end stage renal disease, or death, but experienced an increased incidence of hyperkalemia and acute kidney injury compared with the monotherapy group. In most patients no benefit has been associated with using two RAS inhibitors concomitantly. In general, avoid combined use of RAS inhibitors.
Closely monitor blood pressure, renal function, and electrolytes in patients on COZAAR and other agents that affect the RAS. Do not coadminister aliskiren with COZAAR in patients with diabetes. Avoid use of aliskiren with COZAAR in patients with renal impairment (GFR <60 mL/min).
Drug Interactions No clinically significant drug interactions have been found in studies of losartan potassium with hydrochlorothiazide, digoxin, warfarin, cimetidine and phenobarbital. However, rifampin has been shown to decrease the AUC of losartan and its active metabolite by 30% and 40%, respectively. Fluconazole, an inhibitor of cytochrome P450 2C9, decreased the AUC of the active metabolite by approximately 40%, but increased the AUC of losartan by approximately 70% following multiple doses.
Conversion of losartan to its active metabolite after intravenous administration is not affected by ketoconazole, an inhibitor of P450 3A4. The AUC of active metabolite following oral losartan was not affected by erythromycin, an inhibitor of P450 3A4, but the AUC of losartan was increased by 30%. The pharmacodynamic consequences of concomitant use of losartan and inhibitors of P450 2C9 have not been examined.
Subjects who do not metabolize losartan to active metabolite have been shown to have a specific, rare defect in cytochrome P450 2C9. These data s…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS COZAAR is not recommended in pediatric patients less than 6 years of age or in pediatric patients with glomerular filtration rate less than 30 mL/min/1.73 m 2 . ( 2.1 , 8.4 ) Hepatic Impairment: Recommended starting dose 25 mg once daily. ( 2.4 , 8.8 , 12.3 )
8.1Pregnancy Risk Summary COZAAR can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue COZAAR as soon as possible (see Clinical Considerations ). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death.
Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
In patients taking COZAAR during pregnancy, perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. If oligohydramnios is observed, discontinue COZAAR, unless it is considered lifesaving for the mother.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe neonates with histories of in utero exposure to COZAAR for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to COZAAR, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Data Animal Data Losartan potassium was administered orally to rats during the period of late gestation through lactation (Gestation Day 15 through Lactation Day 20) at doses of 10, 25, and 100 mg/kg/day. Losartan potassium has been shown to produce adverse effects in rat fetuses and neonates, including decreased body weight, delayed physical and behavioral development, mortality and renal toxicity.
With the exception of neonatal weight gain (which was affected at doses as low as 10 mg/kg/day), doses associated with these effects exceeded 25 mg/kg/day (approximately three times the maximum recommended human dose of 100 mg on a mg/m 2 basis). These findings are attributed to drug exposure in late gestation and during lactation. Significant levels of losartan and its active metabolite were shown to be present in rat fetal plasma during late gestation and in rat milk.
8.2 Lactation…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary COZAAR can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue COZAAR as soon as possible (see Clinical Considerations ). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death.
Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
In patients taking COZAAR during pregnancy, perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. If oligohydramnios is observed, discontinue COZAAR, unless it is considered lifesaving for the mother.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe neonates with histories of in utero exposure to COZAAR for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to COZAAR, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Data Animal Data Losartan potassium was administered orally to rats during the period of late gestation through lactation (Gestation Day 15 through Lactation Day 20) at doses of 10, 25, and 100 mg/kg/day. Losartan potassium has been shown to produce adverse effects in rat fetuses and neonates, including decreased body weight, delayed physical and behavioral development, mortality and renal toxicity.
With the exception of neonatal weight gain (which was affected at doses as low as 10 mg/kg/day), doses associated with these effects exceeded 25 mg/kg/day (approximately three times the maximum recommended human dose of 100 mg on a mg/m 2 basis). These findings are attributed to drug exposure in late gestation and during lactation. Significant levels of losartan and its active metabolite were shown to be present in rat fetal plasma during late gestation and in rat milk.
🧒 Pediatric Use ▾
8.4Pediatric Use Antihypertensive effects of COZAAR have been established in hypertensive pediatric patients aged 6 to 16 years. Safety and effectiveness have not been established in pediatric patients under the age of 6 or in pediatric patients with glomerular filtration rate <30 mL/min/1.73 m 2 [see Dosage and Administration (2.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14.1) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of patients receiving COZAAR in controlled clinical studies for hypertension, 391 patients (19%) were 65 years and over, while 37 patients (2%) were 75 years and over. In a controlled clinical study for renal protection in type 2 diabetic patients with proteinuria, 248 patients (33%) were 65 years and over. In a controlled clinical study for the reduction in the combined risk of cardiovascular death, stroke and myocardial infarction in hypertensive patients with left ventricular hypertrophy, 2857 patients (62%) were 65 years and over, while 808 patients (18%) were 75 years and over.
No overall differences in effectiveness or safety were observed between these patients and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Significant lethality was observed in mice and rats after oral administration of 1000 mg/kg and 2000 mg/kg, respectively, about 44 and 170 times the maximum recommended human dose on a mg/m 2 basis. Limited data are available in regard to overdosage in humans. The most likely manifestation of overdosage would be hypotension and tachycardia; bradycardia could occur from parasympathetic (vagal) stimulation.
If symptomatic hypotension should occur, supportive treatment should be instituted. Neither losartan nor its active metabolite can be removed by hemodialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Angiotensin II [formed from angiotensin I in a reaction catalyzed by angiotensin converting enzyme (ACE, kininase II)] is a potent vasoconstrictor, the primary vasoactive hormone of the renin-angiotensin system, and an important component in the pathophysiology of hypertension. It also stimulates aldosterone secretion by the adrenal cortex. Losartan and its principal active metabolite block the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor found in many tissues, (e.g., vascular smooth muscle, adrenal gland).
There is also an AT 2 receptor found in many tissues but it is not known to be associated with cardiovascular homeostasis. Neither losartan nor its principal active metabolite exhibits any partial agonist activity at the AT 1 receptor, and both have much greater affinity (about 1000-fold) for the AT 1 receptor than for the AT 2 receptor. In vitro binding studies indicate that losartan is a reversible, competitive inhibitor of the AT 1 receptor.
The active metabolite is 10 to 40 times more potent by weight than losartan and appears to be a reversible, non-competitive inhibitor of the AT 1 receptor. Neither losartan nor its active metabolite inhibits ACE (kininase II, the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin), nor do they bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation.
12.2Pharmacodynamics Losartan inhibits the pressor effect of angiotensin II (as well as angiotensin I) infusions. A dose of 100 mg inhibits the pressor effect by about 85% at peak with 25-40% inhibition persisting for 24 hours. Removal of the negative feedback of angiotensin II causes a doubling to tripling in plasma renin activity and consequent rise in angiotensin II plasma concentration in hypertensive patients.
Losartan does not affect the response to bradykinin, whereas ACE inhibitors increase the response to bradykinin. Aldosterone plasma concentrations fall following losartan administration. In spite of the effect of losartan on aldosterone secretion, very little effect on serum potassium was observed.
The effect of losartan is substantially present within one week but in some studies the maximal effect occurred in 3-6 weeks. In long-term follow-up studies (without placebo control) the effect of losartan appeared to be maintained for up to a year. There is no apparent rebound effect after abrupt withdrawal of losartan.
There was essentially no change in average heart rate in losartan-treated patients in controlled trials.
12.3Pharmacokinetics Absorption: Following oral administration, losartan is well absorbed and undergoes substantial first-pass metabolism. The systemic bioavailability of losartan is approximately 33%. Mean peak concentrations of losartan and its active metabolite are reached in 1 hour and in 3-4 hours, respectively.
While maximum plasma concentrations of losartan and its active metabolite are approximately equal, the AUC (area under the curve) of the metabolite is about 4 times as great as that of losartan. A meal slows absorption of losartan and decreases its C max but has only minor effects on losartan AUC or on the AUC of the metabolite (~10% decrease). The pharmacokinetics of losartan and its active metabolite are linear with oral losartan doses up to 200 mg and do not change over time.
Distribution: The volume of distribution of losartan and the active metabolite is about 34 liters and 12 liters, respectively. Both losartan and its active metabolite are highly bound to plasma proteins, primarily albumin, with plasma free fractions of 1.3% and 0.2%, respectively. Plasma protein binding is constant over the concentration range achieved with recommended doses.
Studies in rats indicate that losartan crosses the blood-brain barrier poorly, if at all. Metabolism: Losartan is an orally activ…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Angiotensin II [formed from angiotensin I in a reaction catalyzed by angiotensin converting enzyme (ACE, kininase II)] is a potent vasoconstrictor, the primary vasoactive hormone of the renin-angiotensin system, and an important component in the pathophysiology of hypertension. It also stimulates aldosterone secretion by the adrenal cortex. Losartan and its principal active metabolite block the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor found in many tissues, (e.g., vascular smooth muscle, adrenal gland).
There is also an AT 2 receptor found in many tissues but it is not known to be associated with cardiovascular homeostasis. Neither losartan nor its principal active metabolite exhibits any partial agonist activity at the AT 1 receptor, and both have much greater affinity (about 1000-fold) for the AT 1 receptor than for the AT 2 receptor. In vitro binding studies indicate that losartan is a reversible, competitive inhibitor of the AT 1 receptor.
The active metabolite is 10 to 40 times more potent by weight than losartan and appears to be a reversible, non-competitive inhibitor of the AT 1 receptor. Neither losartan nor its active metabolite inhibits ACE (kininase II, the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin), nor do they bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING COZAAR is a white film-coated tablet supplied as follows: Losartan Shape Engraving (reverse) NDC 78206-xxx-xx Bottle/30 Bottle/90 25 mg oval 951 n/a 121-01 50 mg oval 952 (scored) 122-01 122-02 100 mg teardrop 960 123-01 123-02 Store at 25°C (77°F); excursions permitted to 15-30°C (59-86°F) [see USP Controlled Room Temperature]. Keep container tightly closed. Protect from light.
📦 Storage and Handling ▾
Store at 25°C (77°F); excursions permitted to 15-30°C (59-86°F) [see USP Controlled Room Temperature]. Keep container tightly closed. Protect from light.
📋 Description ▾
11 DESCRIPTION COZAAR (losartan potassium) is an angiotensin II receptor blocker acting on the AT 1 receptor subtype. Losartan potassium, a non-peptide molecule, is chemically described as 2-butyl-4-chloro-1-[ p -( o -1 H -tetrazol-5-ylphenyl)benzyl]imidazole-5-methanol monopotassium salt. Its empirical formula is C 22 H 22 ClKN 6 O, and its structural formula is: Losartan potassium is a white to off-white free-flowing crystalline powder with a molecular weight of 461.01.
It is freely soluble in water, soluble in alcohols, and slightly soluble in common organic solvents, such as acetonitrile and methyl ethyl ketone. Oxidation of the 5-hydroxymethyl group on the imidazole ring results in the active metabolite of losartan. COZAAR is available as tablets for oral administration containing either 25 mg, 50 mg or 100 mg of losartan potassium and the following inactive ingredients: microcrystalline cellulose, lactose hydrous, pregelatinized starch, magnesium stearate, hydroxypropyl cellulose, hypromellose, and titanium dioxide.
COZAAR 25 mg, 50 mg and 100 mg tablets contain potassium in the following amounts: 2.12 mg (0.054 mEq), 4.24 mg (0.108 mEq) and 8.48 mg (0.216 mEq), respectively. COZAAR 25 mg, COZAAR 50 mg, and COZAAR 100 mg may also contain carnauba wax. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Pregnancy Advise female patients of childbearing age about the consequences of exposure to COZAAR during pregnancy. Discuss treatment options with women planning to become pregnant.
Tell patients to report pregnancies to their physicians as soon as possible [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1) ] . Potassium Supplements Advise patients receiving COZAAR not to use potassium supplements or salt substitutes containing potassium without consulting their healthcare provider [see Drug Interactions (7.1) ] .