
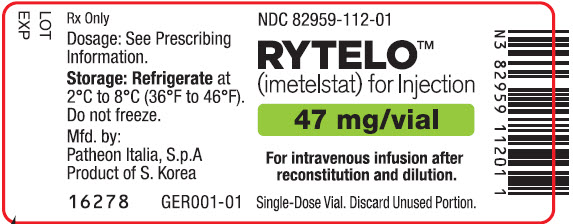
Rytelo imetelstat sodium 47 mg Injection, Powder, Lyophilized, For Solution, 1 vial — NDC 82959-112-01 (Billing 82959-0112-01)
This is a package of 1 vial of Rytelo imetelstat sodium 47 mg Injection, Powder, Lyophilized, For Solution from Geron Corporation, marketed since Jun 2024 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 82959-112-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 82959 labeler · 112 product · 01 package
- Package marketed since
- Jun 6, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 1 EA per package
- Barcode (UPC-A, from the NDC)
- 3 8295911201 1
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 086177
- GCN: 55852
- GPI-14 (Medi-Span): 21535325602120
- HICL (First Databank): 049663
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 2685241
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Oligonucleotide Telomerase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Imetelstat injection is used to treat certain types of myelodysplastic syndrome (MDS) with transfusion-dependent anemia that have not responded to or cannot receive other therapies used for MDS. Imetelstat is in a class of medications called telomerase inhibitors. It works by stopping the production of unhealthy red blood cells.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0870 | $59.531 / J0870 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 82959-0112-01 You're viewing this Main listing | 1 VIAL, SINGLE-DOSE in 1 CARTON / 1 INJECTION, POWDER, LYOPHILIZED, FOR SOLUTION in 1 VIAL, SINGLE-DOSE | 2024-06-06 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Rytelo 47 mgthis 82959-0112-01 | Geron | 1 vial | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12442000 ↗ | Method of use | U-3956 | Mar 15, 2033 |
| US 12442000 ↗ | Method of use | U-3956 | Mar 15, 2033 |
| US 9388416 ↗ | Method of use | U-3956 | Sep 9, 2026 |
| US 9388416 ↗ | Method of use | U-3956 | Sep 9, 2026 |
| US 9388415 ↗ | Method of use | U-3956 | Sep 9, 2026 |
| US 9388415 ↗ | Method of use | U-3956 | Sep 9, 2026 |
| US 9375485 ↗ | Method of use | U-3956 | Mar 15, 2033 |
| US 9375485 ↗ | Method of use | U-3956 | Mar 15, 2033 |
| US 12171778 ↗ | Method of use | U-3956 | Jun 16, 2039 |
| US 12171778 ↗ | Method of use | U-3956 | Jun 16, 2039 |
| US 7494982 ↗ | Drug substance | — | Dec 27, 2026 |
| US 7494982 ↗ | Drug substance | — | Dec 27, 2026 |
| Code | What it grants | Expires |
|---|---|---|
| ODE-482 | Orphan Drug Exclusivity (7-year) | Jun 6, 2031 |
| ODE-482 | Orphan Drug Exclusivity (7-year) | Jun 6, 2031 |
Is there a generic version of RYTELO 47 MG VIAL?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 45P3261C7T
Sodium carbonate is an alkaline mineral salt commonly used in medications as a buffer to help maintain pH balance and improve stability. It may also function as a disintegrant to help tablets break apart in the digestive system.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Geron Corporation labeler code 82959
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1. INDICATIONS AND USAGE RYTELO is indicated for the treatment of adult patients with low- to intermediate-1 risk myelodysplastic syndromes (MDS) with transfusion-dependent anemia requiring 4 or more red blood cell units over 8 weeks who have not responded to or have lost response to or are ineligible for erythropoiesis-stimulating agents (ESA). RYTELO is an oligonucleotide telomerase inhibitor indicated for the treatment of adult patients with low- to intermediate-1 risk myelodysplastic syndromes (MDS) with transfusion-dependent anemia requiring 4 or more red blood cell units over 8 weeks who have not responded to or have lost response to or are ineligible for erythropoiesis-stimulating agents (ESA).
( 1 )
⏱️ Dosage and Administration ▾
2. DOSAGE AND ADMINISTRATION The recommended dosage of RYTELO is 7.1 mg/kg administered as an intravenous infusion over 2 hours every 4 weeks. ( 2.1 ) Premedicate prior to dosing with RYTELO for potential infusion-related reactions.
( 2.2 ) See full prescribing information for preparation and administration instructions. ( 2.4 ) 2.1. Recommended Dosage The recommended dosage of RYTELO is 7.1 mg/kg administered as an intravenous infusion over 2 hours every 4 weeks.
Discontinue RYTELO if a patient does not experience a decrease in red blood cell (RBC) transfusion burden after 24 weeks of treatment (administration of 6 doses) or if unacceptable toxicity occurs at any time [see Dosage and Administration (2.3) ] . 2.2. Recommended Premedications Administer the following pre-treatment medications at least 30 minutes prior to dosing to prevent or reduce potential infusion-related reactions: diphenhydramine (or equivalent) 25 mg to 50 mg, intravenously or orally hydrocortisone (or equivalent) 100 mg to 200 mg, intravenously or orally Monitor patients for adverse reactions for at least one hour after the infusion has been completed [see Warnings and Precautions (5.3) and Adverse Reactions (6.1) ] .
2.3. Dosage Modifications for Adverse Reactions Recommended dose reductions for Grade 3 and Grade 4 adverse reactions are found in Table 1. The management of Grade 3 and Grade 4 adverse reactions may require temporary dose delay, dose reduction, or treatment discontinuation and are presented in Table 2 and Table 3.
RYTELO treatment should be permanently discontinued if the patient cannot tolerate the lowest dose level of 4.4 mg/kg. Table 1: Recommended Dose Reduction for RYTELO for Grade 3 and Grade 4 Adverse Reactions Dose Reduction Dose Every 4 Weeks First dose reduction 5.6 mg/kg Second dose reduction 4.4 mg/kg Dosage Modifications for Hematologic (Grade 3 and Grade 4) Adverse Reactions Monitor complete blood cell counts prior to administration of RYTELO, weekly for the first two cycles, prior to each cycle thereafter, and as clinically indicated.
Delay the next cycle if absolute neutrophil count is less than 1 × 10 9 /L or platelets are less than 50 × 10 9 /L. Modify dose as described in Table 2. Table 2: Dosage Modifications for Patients with Hematologic Adverse Reactions (Grade 3 and Grade 4) Adverse Reaction Severity Grade Severity based on National Cancer Institute Common Terminology Criteria for Adverse Events Version 4.03.
Occurrence Treatment Modification Abbreviation: ANC = absolute neutrophil count Thrombocytopenia [see Warnings and Precautions (5.1) ] Grade 3 First Delay RYTELO until recovery of platelets to 50 × 10 9 /L; restart at same dose level. Second and Third Delay RYTELO until recovery of platelets to 50 × 10 9 /L; restart at one dose level lower. Fourth Discontinue RYTELO.
Grade 4 First and Second Delay RYTELO until recovery of platelets to 50 × 10 9 /L; restart at one dose level lower. Third Discontinue RYTELO. Neutropenia [see Warnings and Precautions (5.2) ] Grade 3 First Delay RYTELO until recovery of ANC to 1 × 10 9 /L; restart at same dose level.
Second and Third Delay RYTELO until recovery of ANC to 1 × 10 9 /L; restart at one dose level lower. Fourth Discontinue RYTELO. Grade 4 First and Second Delay RYTELO until recovery of ANC to 1 × 10 9 /L; restart at one dose level lower.
Third Discontinue RYTELO. Dosage Modifications for Non-hematologic Adverse Reactions Dosage modifications for infusion-related reactions and other adverse drug reactions, including elevated liver function tests (LFTs), are described in Table 3. Monitor liver function tests prior to administration of RYTELO, weekly for the first cycle, prior to each cycle thereafter, and as clinically indicated.
Table 3: Dosage Modifications for Patients with Non-hematologic Adverse Reactions Adverse Reaction Severity Grade Severity based on National Cancer Institute Common Terminology Criteria for Adverse Events Version 4.03. Occurrence Treatment Modifica… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3. DOSAGE FORMS AND STRENGTHS For injection: 47 mg of imetelstat supplied as a white to off-white or slightly yellow lyophilized powder in a single-dose vial for reconstitution. For injection: 188 mg of imetelstat supplied as a white to off-white or slightly yellow lyophilized powder in a single-dose vial for reconstitution.
For injection: 47 mg powder in a single-dose vial for reconstitution. ( 3 ) For injection: 188 mg powder in a single-dose vial for reconstitution. ( 3 )
⛔ Contraindications ▾
4. CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5. WARNINGS AND PRECAUTIONS Thrombocytopenia : Grade 3 and Grade 4 thrombocytopenia occurred; obtain complete blood cell counts prior to initiation of RYTELO, weekly for the first two cycles, and prior to each cycle thereafter to monitor. Delay or dose reduce as recommended.
( 2.3 , 5.1 ) Neutropenia : Grade 3 and Grade 4 neutropenia occurred; obtain complete blood cell counts prior to initiation of RYTELO, weekly for the first two cycles, and prior to each cycle thereafter to monitor. Delay or dose reduce as recommended. ( 2.3 , 5.2 ) Infusion-Related Reactions : Premedicate before infusion.
Interrupt, decrease the rate of infusion, or permanently discontinue RYTELO based on severity. ( 2.2 , 2.3 , 5.3 ) Embryo-Fetal Toxicity : Can cause embryo-fetal harm. Advise females of reproductive potential of potential risk to a fetus and to use effective contraception.
( 5.4 , 8.1 , 8.3 ) 5.1. Thrombocytopenia RYTELO can cause thrombocytopenia based on laboratory values. In the clinical trial, new or worsening Grade 3 or 4 decreased platelets occurred in 65% of patients with MDS treated with RYTELO [see Adverse Reactions (6.1) ] .
Median time to onset of first occurrence of Grade 3 or 4 decreased platelets was 6 weeks (range: 2 to 88 weeks) and median time to recovery from each occurrence of Grade 3 or 4 decreased platelets to Grade 2 or lower, or last value available, was 1.3 weeks (range: 0.1 to 13 weeks). Grade 3 or 4 decreased platelets occurred throughout treatment with RYTELO, with 48% of patients experiencing Grade 3 or Grade 4 thrombocytopenia during cycles 1-3, 31% during cycles 4-6, 33% during cycles 7-12, and 24% during cycles 13 and beyond.
Grade 3 or 4 bleeding was seen in 2.5% of patients, including gastrointestinal bleeding (1.7%) and hematuria (0.8%). Monitor patients with thrombocytopenia for bleeding. Monitor complete blood cell counts prior to initiation of RYTELO, weekly for the first two cycles, prior to each cycle thereafter, and as clinically indicated.
Administer platelet transfusions as appropriate. Delay the next cycle and resume at the same or reduced dose, or discontinue as recommended [see Dosage and Administration (2.3) ] . 5.2.
Neutropenia RYTELO can cause neutropenia based on laboratory values. In the clinical trial, new or worsening Grade 3 or 4 decreased neutrophils occurred in 72% of patients with MDS treated with RYTELO [see Adverse Reactions (6.1) ] . Median time to onset of first occurrence of Grade 3 or 4 decreased neutrophils was 4.6 weeks (range: 1 to 81 weeks) and median time to recovery from each occurrence of Grade 3 or 4 decreased neutrophils to Grade 2 or lower, or last value available, was 1.9 weeks (range: 0 to 16 weeks).
Grade 3 or 4 decreased neutrophils occurred throughout treatment with RYTELO, with 65% of patients experiencing Grade 3 or Grade 4 neutropenia during cycles 1-3, 35% during cycles 4-6, 32% during cycles 7-12, and 39% during cycles 13 and beyond. Febrile neutropenia occurred in 0.8% and sepsis in 4.2%. Monitor patients with Grade 3 or 4 neutropenia for infections, including sepsis.
Monitor complete blood cell counts prior to initiation of RYTELO, weekly for the first two cycles, prior to each cycle thereafter, and as clinically indicated. Administer growth factors and anti-infective therapies for treatment or prophylaxis as appropriate. Delay the next cycle and resume at the same or reduced dose, or discontinue as recommended [see Dosage and Administration (2.3) ] .
5.3. Infusion-Related Reactions RYTELO can cause infusion-related reactions. In the clinical trial, infusion-related reactions occurred in 8% of patients with MDS treated with RYTELO; Grade 3 or 4 infusion-related reactions occurred in 1.7%, including hypertensive crisis (0.8%).
The most common infusion-related reaction was headache (4.2%). Infusion-related reactions usually occur during or shortly after the end of the infusion. Premedicate patients at least 30 minutes prior to infusion with diphenhydramine a… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6. ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Thrombocytopenia [see Warnings and Precautions (5.1) ] Neutropenia [see Warnings and Precautions (5.2) ] Infusion-Related Reactions [see Warnings and Precautions (5.3) ] Most common adverse reactions (incidence ≥10% with a difference between arms of >5% compared to placebo), including laboratory abnormalities are decreased platelets, decreased white blood cells, decreased neutrophils, increased AST, increased alkaline phosphatase, increased ALT, fatigue, prolonged partial thromboplastin time, arthralgia/myalgia, COVID-19 infections, and headache.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Geron Corporation at 1-855-437-6664 (1-855-GERONMI) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . 6.1. Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
Low- to Intermediate-Risk Myelodysplastic Syndromes The safety of RYTELO was evaluated in a randomized, double-blind, placebo-controlled, multicenter trial (IMerge) in 177 adult patients with International Prognostic Scoring System (IPSS) low- to intermediate-1 risk MDS who were transfusion-dependent and relapsed or refractory to or ineligible for ESA treatment [see Clinical Studies (14) ] . The safety population included patients who received at least one dose of either RYTELO (n=118) or placebo (n=59) at 7.1 mg/kg as an intravenous infusion administered over two hours every 4 weeks.
The median time on treatment with RYTELO was 8 months (range, 0 to 38 months); 69% of patients were exposed to RYTELO for 24 weeks or longer and 45% were exposed for 48 weeks or longer. The median age of patients who received at least one dose of RYTELO was 72 years (range: 44 to 87 years) with 77% of patients 65 years of age and older and 30% of patients 75 years of age and older. Participants were 60% male, 81% White, 7% Asian, and 0.8% Black.
Serious adverse reactions occurred in 32% of patients who received RYTELO. Serious adverse reactions in > 2% of patients included sepsis (4.2%), fracture (3.4%), cardiac failure (2.5%), and hemorrhage (2.5%). Fatal adverse reactions occurred in 0.8% of patients who received RYTELO, including sepsis (0.8%).
Permanent discontinuation of RYTELO due to an adverse reaction occurred in 15% of patients. Adverse reactions which resulted in permanent discontinuation of RYTELO in > 2% of patients included neutropenia and thrombocytopenia. Dosage interruptions of RYTELO due to an adverse reaction occurred in 80% of patients.
Adverse reactions which required dosage interruption in > 5% of patients included neutropenia, thrombocytopenia and infections. Dose reductions of RYTELO due to an adverse reaction occurred in 49% of patients. Adverse reactions which required dose reductions in > 2% of patients included neutropenia and thrombocytopenia.
The most common (≥10% with a difference between arms of >5% compared to placebo) adverse reactions, including laboratory abnormalities, were decreased platelets, decreased white blood cells, decreased neutrophils, increased AST, increased alkaline phosphatase, increased ALT, fatigue, prolonged partial thromboplastin time, arthralgia/myalgia, COVID-19 infections, and headache. Table 5 summarizes the adverse reactions in IMerge. Table 5: Adverse Reactions (≥5%) in Patients with MDS Who Received RYTELO with a Difference Between Arms of >2% Compared to Placebo in IMerge Adverse Reaction RYTELO (N=118) Placebo (N=59) All Grades % Grades 3 or 4 % All Grades % Grades 3 or 4 % Graded according to National Cancer Institute Common Terminology Criteria for Adverse Events Version 4.03.
General disorders and administrative site conditions Fatigue Fatigue: asthenia, fatigue, and malaise. 29… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8. USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 ) 8.1.
Pregnancy Risk Summary Based on findings in animal studies, RYTELO can cause embryo-fetal harm when administered to a pregnant woman. There are no available data on RYTELO use in pregnant women to evaluate for drug-associated risk. In embryo-fetal developmental toxicity studies, administration of imetelstat to pregnant mice and rabbits during the period of organogenesis resulted in embryo-fetal mortality, which in mice occurred at maternal exposures approximately 2.5 times the human exposure at the recommended clinical dose.
Advise pregnant women of the potential risk to a fetus [see Data ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In embryo-fetal developmental toxicity studies, imetelstat was administered by IV bolus injection at doses of 4.7, 9.4, 14.1 or 28.2 mg/kg/day on gestation days 6, 9, and 12 in mice, or by 2-hour intravenous infusion at doses of 4.7, 14.1, or 28.2 mg/kg on gestation days 6 and 13 in rabbits.
In rabbits, the dose of 28.2 mg/kg was maternally toxic. Increased post-implantation loss due to an increase in early resorptions, resulting in a decrease in viable fetuses and litter was noted in mice at 28.2 mg/kg and in rabbits starting at 14.1 mg/kg; corresponding to exposures (based on AUC) that are approximately 2.5-times (mice) or 9.3-times (rabbits) the human exposure at the recommended clinical dose. 8.2.
Lactation Risk Summary There is no data on the presence of imetelstat in human milk, or the effects RYTELO on the breastfed child, or milk production. Because of the potential for adverse reactions in breastfed children, advise women not to breastfeed during treatment with RYTELO and for 1 week after the last dose. 8.3.
Females and Males of Reproductive Potential Based on findings from animal studies, RYTELO can cause embryo-fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Pregnancy Testing Verify the pregnancy status of females of reproductive potential prior to initiating treatment with RYTELO. Contraception Females Advise females of reproductive potential to use effective contraception during treatment with RYTELO and for 1 week after the last dose [see Use in Specific Populations (8.1) ] .
Infertility Females Based on findings in animals, RYTELO may impair fertility in females of reproductive potential. The effect on fertility is reversible [see Nonclinical Toxicology (13.1) ] . 8.4.
Pediatric Use Safety and effectiveness of RYTELO in pediatric patients have not been established. 8.5. Geriatric Use Of the 118 patients with low- to intermediate-1 risk myelodysplastic syndromes (MDS) in the clinical trial who received RYTELO, 91 (77.1%) patients were 65 years of age and older and 35 (29.7%) patients 75 years of age and older.
No differences in safety or efficacy were observed between older (≥ 65 years) and younger patients.
🤰 Pregnancy ▾
8.1. Pregnancy Risk Summary Based on findings in animal studies, RYTELO can cause embryo-fetal harm when administered to a pregnant woman. There are no available data on RYTELO use in pregnant women to evaluate for drug-associated risk.
In embryo-fetal developmental toxicity studies, administration of imetelstat to pregnant mice and rabbits during the period of organogenesis resulted in embryo-fetal mortality, which in mice occurred at maternal exposures approximately 2.5 times the human exposure at the recommended clinical dose. Advise pregnant women of the potential risk to a fetus [see Data ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data In embryo-fetal developmental toxicity studies, imetelstat was administered by IV bolus injection at doses of 4.7, 9.4, 14.1 or 28.2 mg/kg/day on gestation days 6, 9, and 12 in mice, or by 2-hour intravenous infusion at doses of 4.7, 14.1, or 28.2 mg/kg on gestation days 6 and 13 in rabbits. In rabbits, the dose of 28.2 mg/kg was maternally toxic. Increased post-implantation loss due to an increase in early resorptions, resulting in a decrease in viable fetuses and litter was noted in mice at 28.2 mg/kg and in rabbits starting at 14.1 mg/kg; corresponding to exposures (based on AUC) that are approximately 2.5-times (mice) or 9.3-times (rabbits) the human exposure at the recommended clinical dose.
🧒 Pediatric Use ▾
8.4. Pediatric Use Safety and effectiveness of RYTELO in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5. Geriatric Use Of the 118 patients with low- to intermediate-1 risk myelodysplastic syndromes (MDS) in the clinical trial who received RYTELO, 91 (77.1%) patients were 65 years of age and older and 35 (29.7%) patients 75 years of age and older. No differences in safety or efficacy were observed between older (≥ 65 years) and younger patients.
🧬 Clinical Pharmacology ▾
12. CLINICAL PHARMACOLOGY 12.1. Mechanism of Action Imetelstat is an oligonucleotide human telomerase inhibitor that binds to the template region of the RNA component of human telomerase (hTR), inhibits telomerase enzymatic activity and prevents telomere binding.
Increased telomerase activity and human telomerase reverse transcriptase (hTERT) RNA expression have been reported in MDS and malignant stem and progenitor cells. Nonclinical studies showed imetelstat treatment led to reduction of telomere length, reduction of malignant stem and progenitor cell proliferation, and induction of apoptotic cell death. 12.2.
Pharmacodynamics Grade 3 and 4 Thrombocytopenia Higher imetelstat exposure is associated with higher incidence of Grade 3 and 4 thrombocytopenia in patients with MDS. Cardiac Electrophysiology At the maximum recommended dose, clinically significant QTc interval prolongation was not observed. 12.3.
Pharmacokinetics Imetelstat plasma geometric mean (coefficient of variation [CV] %) maximum concentration (C max ) is 18.3 µM (27.3%) and the area under the concentration-time curve from time 0 to 28 days (AUC 0-28 ) was 114.2 h*µM (43.2%). Imetelstat does not accumulate between treatment cycles. Distribution Following a single intravenous dose of 7.1 mg/kg of RYTELO administered over 2 hours in patients with MDS, the geometric mean (CV%) volume of distribution is approximately
14.1L (27.2%). In vitro human plasma protein binding is greater than 94%. Elimination The imetelstat geometric mean (CV%) apparent plasma half-life is approximately 4.9 hours (43.2%) at the approved recommended dosage.
Metabolism Imetelstat is expected to be metabolized by nucleases to nucleotides of various lengths. Specific populations No clinically significant differences in the pharmacokinetics of imetelstat were observed based on age (21 to 87 years), sex, race (81% White, 4% Asian, 7% Black, 8% other/unknown), mild to moderate renal impairment (CL cr 30 to < 90 mL/min), mild hepatic impairment (total bilirubin ≤ ULN and AST > ULN, or total bilirubin > 1× to 1.5× ULN and any AST), or moderate hepatic impairment (total bilirubin > 1.5× to 3× ULN and any AST).
The effect of severe renal impairment (CL cr 15 to < 30 mL/min), end-stage renal disease, or severe hepatic impairment (total bilirubin > 3× ULN and any AST) has not been established. Drug Interaction Studies In Vitro Studies CYP Enzymes : Imetelstat is not an inhibitor or inducer of CYP450 enzymes. Transporter systems : Imetelstat is an inhibitor of OATP1B1 and OATP1B3.
12.6. Immunogenicity The observed incidence of anti-drug antibodies (ADA) is highly dependent on the sensitivity and specificity of the assay. Differences in assay methods preclude meaningful comparisons of the incidence of anti-drug antibodies in the studies described below with the incidence of anti-drug antibodies in other studies, including those of RYTELO.
Seventeen percent (28/166) of evaluable patients with low- or intermediate-1 risk MDS tested positive for imetelstat anti-drug antibodies, with a median onset of 38 weeks following the study drug dosage of RYTELO for a median duration of treatment of 35 weeks in Phase 2 and Phase 3 of the IMerge study. There was no clinically significant effect of ADA on the PK, safety, or efficacy of RYTELO among the study participants who developed anti-drug antibodies.
🧬 Mechanism of Action ▾
12.1. Mechanism of Action Imetelstat is an oligonucleotide human telomerase inhibitor that binds to the template region of the RNA component of human telomerase (hTR), inhibits telomerase enzymatic activity and prevents telomere binding. Increased telomerase activity and human telomerase reverse transcriptase (hTERT) RNA expression have been reported in MDS and malignant stem and progenitor cells.
Nonclinical studies showed imetelstat treatment led to reduction of telomere length, reduction of malignant stem and progenitor cell proliferation, and induction of apoptotic cell death.
📦 How Supplied / Storage and Handling ▾
16. HOW SUPPLIED/STORAGE AND HANDLING How Supplied RYTELO (imetelstat) for injection is a preservative free, white to off-white or slightly yellow, lyophilized powder available as: Carton Contents NDC One RYTELO 47 mg single-dose vial 82959-112-01 One RYTELO 188 mg single-dose vial 82959-111-01 Storage Store vials refrigerated at 2°C to 8°C (36°F to 46°F) in original carton. Do not freeze.
📦 Storage and Handling ▾
Storage Store vials refrigerated at 2°C to 8°C (36°F to 46°F) in original carton. Do not freeze.
📋 Description ▾
11. DESCRIPTION RYTELO for injection contains imetelstat, an oligonucleotide telomerase inhibitor for intravenous use. Imetelstat sodium is a white to off-white or slightly yellow, amorphous, solid powder.
It is highly soluble in aqueous solutions, including in 0.9% Sodium Chloride Injection, at both refrigerated and room temperatures. Imetelstat sodium is hygroscopic. The chemical name for the imetelstat sodium drug substance is DNA, d(3'-amino-3'-deoxy-P-thio) (T-A-G-G-G-T-T-A-G-A-C-A-A), 5'-[ O -[2-hydroxy-3-(hexadecanoylamino)propyl] phosphorothioate], sodium salt (1:13).
The molecular formula is C 148 H 198 N 68 O 53 P 13 S 13 Na 13 (as sodium salt), which equates to a formula weight of 4896 g/mol. The molecular formula for the free acid form is C 148 H 211 N 68 O 53 P 13 S 13 which equates to a formula weight of 4610 g/mol. The structural formula for imetelstat sodium is: RYTELO (imetelstat) for injection is a sterile, preservative-free, white to off-white or slightly yellow lyophilized powder for intravenous infusion after reconstitution and dilution.
Each single-dose vial provides either 47 mg of imetelstat (equivalent to 50 mg imetelstat sodium) or 188 mg of imetelstat (equivalent to 200 mg imetelstat sodium). The following inactive ingredients may be added during manufacturing: sodium carbonate anhydrous (for the 47 mg preparation) / sodium carbonate monohydrate (for the 188 mg preparation) or hydrochloric acid (to adjust to pH of 7.0 to 8.5). Chemical Structure
💬 Information for Patients ▾
17. PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Discuss the following with patients prior to and during treatment with RYTELO.
Thrombocytopenia Advise patients of the risk of thrombocytopenia with RYTELO, and that their blood counts will be monitored routinely while on treatment and dose of RYTELO delayed or reduced as needed. Instruct patients to notify a healthcare provider immediately if they show signs or symptoms of thrombocytopenia such as unusual bleeding or bruising [see Warnings and Precautions (5.1) ] . Neutropenia Advise patients of the risk of neutropenia with RYTELO and that their blood counts will be monitored routinely while on treatment and the dose of RYTELO may be delayed or reduced as needed.
Instruct patients to notify a healthcare provider immediately if they show signs or symptoms of neutropenia, such as fever or infection [see Warnings and Precautions (5.2) ] . Infusion-Related Reactions Inform patients that infusion-related reactions can occur during treatment with RYTELO and premedications will be given prior to each infusion. Patients will be monitored by their healthcare provider for at least an hour after the infusion [see Dosage and Administration (2.2) and Warnings and Precautions (5.3) ] .
Advise patients that their healthcare provider may decide to give RYTELO more slowly or stop the infusion if an infusion-related reaction occurs [see Adverse Reactions (6.1) ] Embryo-Fetal Toxicity Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females of reproductive potential to inform their healthcare provider if they are pregnant or become pregnant [see Warnings and Precautions (5.4) and Use in Specific Populations (8.1) ] . Advise females of reproductive potential to use effective contraception during treatment with RYTELO and for 1 week after the last dose [see Use in Specific Populations (8.3) ] .
Lactation Advise women not to breastfeed during treatment with RYTELO and for 1 week after the last dose [see Use in Specific Populations (8.2) ] .
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Issued: 6/2024 MEDICATION GUIDE RYTELO™ (ri-TEL-o) (imetelstat) for injection, for intravenous use What is the most important information I should know about RYTELO?
RYTELO may cause serious side effects, including: Low platelet counts (thrombocytopenia). Low platelet counts are common during treatment with RYTELO and can also be severe. Low platelet counts can increase your risk for bleeding.
Your healthcare provider may give you platelet transfusions to reduce the risk of bleeding if you develop a low platelet count during treatment with RYTELO. Tell your healthcare provider right away if you develop any signs or symptoms of bleeding, including: unusual bleeding or bruising bleeding that lasts a long time nosebleeds vomiting blood blood in your stool or black tarry stool Low neutrophil counts (neutropenia). Low counts of a type of white blood cell called neutrophils are common during treatment with RYTELO and can also be severe.
Low neutrophil counts can increase your risk for infections, including serious infections and sepsis. Your healthcare provider may give you medicines before you start treatment to help prevent neutropenia and infections and may treat you with medicines if you develop these problems during treatment with RYTELO. Tell your healthcare provider right away if you develop any signs or symptoms of infection during treatment with RYTELO, including: fever shortness of breath or trouble breathing cough chills pain or burning when you urinate Your healthcare provider will do blood tests to check your platelet and neutrophil counts before starting treatment with RYTELO, weekly for the first 2 cycles of treatment, before you receive each additional cycle, and as needed during your treatment.
Your healthcare provider may delay your next treatment, decrease your dose, or stop treatment with RYTELO if you develop thrombocytopenia or neutropenia during treatment. See " What are the possible side effects of RYTELO? " for more information about side effects. What is RYTELO?
RYTELO is a prescription medicine used to treat a condition called low- to intermediate-1 risk myelodysplastic syndromes (MDS) in adults: with anemia (low red blood cell counts) who need blood transfusions of 4 or more red blood cell units over 8 weeks and who have not responded to, have stopped responding to, or cannot be treated with other medicines called erythropoiesis-stimulating agents (ESAs). It is not known if RYTELO is safe and effective in children. Before receiving RYTELO, tell your healthcare provider about all of your medical conditions, including if you: are pregnant or plan to become pregnant.
RYTELO may harm your unborn baby and may cause loss of pregnancy (miscarriage). Tell your healthcare provider right away if you become pregnant or think you may be pregnant during treatment with RYTELO. Females who are able to become pregnant: Your healthcare provider will perform a pregnancy test before you are given RYTELO.
You should use effective birth control (contraception) during treatment with RYTELO and for 1 week after your last dose. are breastfeeding or plan to breastfeed. It is not known if RYTELO passes into your breastmilk. Do not breastfeed during treatment with RYTELO and for 1 week after your last dose.
Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. Know the medicines you take. Keep a list of them to show your healthcare provider and pharmacist when you get a new medicine.
How will I receive RYTELO? RYTELO will be given as an intravenous infusion into your vein over a period of 2 hours by your healthcare provider. RYTELO is usually given every 4 weeks.
Your healthcare provider will prescribe RYTELO in a dose that is right for you and may change your dose, change your dosing schedule, or stop treatment depending on how you respond to RYTELO. Yo… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3. Pharmacokinetics Imetelstat plasma geometric mean (coefficient of variation [CV] %) maximum concentration (C max ) is 18.3 µM (27.3%) and the area under the concentration-time curve from time 0 to 28 days (AUC 0-28 ) was 114.2 h*µM (43.2%). Imetelstat does not accumulate between treatment cycles.
Distribution Following a single intravenous dose of 7.1 mg/kg of RYTELO administered over 2 hours in patients with MDS, the geometric mean (CV%) volume of distribution is approximately
14.1L (27.2%). In vitro human plasma protein binding is greater than 94%. Elimination The imetelstat geometric mean (CV%) apparent plasma half-life is approximately 4.9 hours (43.2%) at the approved recommended dosage.
Metabolism Imetelstat is expected to be metabolized by nucleases to nucleotides of various lengths. Specific populations No clinically significant differences in the pharmacokinetics of imetelstat were observed based on age (21 to 87 years), sex, race (81% White, 4% Asian, 7% Black, 8% other/unknown), mild to moderate renal impairment (CL cr 30 to < 90 mL/min), mild hepatic impairment (total bilirubin ≤ ULN and AST > ULN, or total bilirubin > 1× to 1.5× ULN and any AST), or moderate hepatic impairment (total bilirubin > 1.5× to 3× ULN and any AST).
The effect of severe renal impairment (CL cr 15 to < 30 mL/min), end-stage renal disease, or severe hepatic impairment (total bilirubin > 3× ULN and any AST) has not been established. Drug Interaction Studies In Vitro Studies CYP Enzymes : Imetelstat is not an inhibitor or inducer of CYP450 enzymes. Transporter systems : Imetelstat is an inhibitor of OATP1B1 and OATP1B3.
🧬 Pharmacodynamics ▾
12.2. Pharmacodynamics Grade 3 and 4 Thrombocytopenia Higher imetelstat exposure is associated with higher incidence of Grade 3 and 4 thrombocytopenia in patients with MDS. Cardiac Electrophysiology At the maximum recommended dose, clinically significant QTc interval prolongation was not observed.
🔬 Clinical Studies ▾
14. CLINICAL STUDIES 14.1. Myelodysplastic Syndromes (MDS) The efficacy of RYTELO was evaluated in a randomized, double-blind, placebo-controlled, multicenter trial (IMerge; NCT02598661) in 178 patients enrolled with International Prognostic Scoring System (IPSS) low- or intermediate-1 risk MDS who were transfusion-dependent (requiring ≥ 4 red blood cell (RBC) units over an 8-week period during the 16 weeks prior to randomization).
Eligible patients were required to have failed to respond or have lost response or be ineligible for erythropoiesis-stimulating agents (ESAs); and had an absolute neutrophil count of 1.5 × 10 9 /L or greater and platelets 75 × 10 9 /L or greater. Patients were ineligible if they had del(5q) cytogenetic abnormality or had received prior treatment with lenalidomide or hypomethylating agents. Participants were randomized in a 2:1 ratio to receive an intravenous infusion of RYTELO (n=118) 7.1 mg/kg or placebo (n=60) in 28-day treatment cycles until disease progression, unacceptable toxicity, or withdrawal from the study.
Randomization was stratified by prior RBC transfusion burden and by IPSS risk group. All patients received supportive care, which included RBC transfusions. Of the 178 patients enrolled, the median age was 72 years (range: 39 to 87 years), with 62% male, and 80% White, 6% Asian, 1.7% Black, 12% other or not reported.
The key baseline disease characteristics of the efficacy population are shown in Table 7. Table 7: Baseline Disease Characteristics of Patients with MDS in IMerge Disease Characteristic RYTELO (N=118) Placebo (N=60) Abbreviations: ECOG = Eastern Cooperative Oncology Group; ESA = erythropoietin stimulating agents; IPSS = International Prognostic Scoring System; RBC = Red Blood Cell; MDS = myelodysplastic syndromes; sEPO = serum erythropoietin; WHO = World Health Organization Time since original diagnosis Median years (range) 3.5 (0.1, 26.7) 2.8 (0.2, 25.7) ECOG Score (0, 1, 2), n (%) 0: Asymptomatic 42 (35.6) 21 (35) 1: Symptomatic fully ambulatory 70 (59.3) 39 (65) 2: Symptomatic in bed less than 50% of the day 6 (5.1) 0 IPSS Risk Classification, n (%) Low 80 (67.8) 39 (65) Intermediate-1 38 (32.2) 21 (35) Prior RBC transfusion burden Prior RBC transfusion burden is defined as the maximum number of RBC units transfused over an 8-week period during the 16 weeks prior to randomization. , n (%) 4 to 6 units 62 (52.5) 33 (55) > 6 units 56 (47.5) 27 (45) WHO Classification (2008), n (%) RS+ RS+ includes refractory anemia with ring sideroblasts (RARS)/refractory cytopenia with multilineage dysplasia and ≥ 15% ringed sideroblasts (RCMD-RS).
73 (61.9) 37 (61.7) RS˗ RS˗ includes others. 44 (37.3) 23 (38.3) Missing 1 (0.8) 0 Baseline sEPO, n (%) ≤ 500 mU/mL 87 (73.7) 36 (60) > 500 mU/mL 26 (22) 22 (36.7) Missing 5 (4.2) 2 (3.3) Prior ESA Use, n (%) Yes 108 (91.5) 52 (86.7) No 10 (8.5) 8 (13.3) Baseline blood counts, median Neutrophils (cells/L) 2.6 × 10 9 2.7 × 10 9 Hemoglobin (g/dL) 7.9
7.8Platelets (cells/L) 230 × 10 9 230 × 10 9 Efficacy was established after a median follow up time of 19.5 months (range: 1.4 to 36.2) in the imetelstat group and 17.5 months (range: 0.7 to 34.3) in the placebo group based upon the proportion of patients who achieved ≥ 8-week and ≥ 24-week RBC-TI, defined as the absence of RBC transfusion(s) during any consecutive 8-week (56-day) period, and during any consecutive 24-week (168-day) period, respectively, from randomization until the start of subsequent anti-cancer therapy (if any).
The efficacy results are summarized in Table 8. Table 8: Efficacy Results of RYTELO in IMerge RYTELO (N=118) Placebo (N=60) % Difference (95% CI) 95% CI based on Wilson Score method. p -value p- value is based on Cochran-Mantel-Haenszel (CMH) controlling for prior RBC transfusion burden (≤ 6 versus >6 units RBC) and IPSS risk group (low versus intermediate-1) applied to randomization. Abbreviations: CI = Confidence Interval; RBC = Red Blood Cell; TI = Transfusion Independ… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13. NONCLINICAL TOXICOLOGY 13.1. Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies have not been conducted with imetelstat.
In vitro, imetelstat was not mutagenic in the bacterial mutagenicity assay (Ames test) or clastogenic in the chromosomal aberrations assay using cultured human peripheral blood lymphocytes. Imetelstat was not genotoxic in an in vivo mouse micronucleus assay at intravenous dose levels up to approximately 104 mg/kg. Fertility studies have not been conducted with imetelstat.
Female monkeys given 14.1 mg/kg once weekly for 9 months exhibited uterine endometrial atrophy in a general toxicology study. This effect was observed at a mean exposure (based on AUC) that is approximately 14.4-times the human exposure at the recommended clinical dose. This finding was not present in animals following a 14-week recovery period.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1. Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies have not been conducted with imetelstat. In vitro, imetelstat was not mutagenic in the bacterial mutagenicity assay (Ames test) or clastogenic in the chromosomal aberrations assay using cultured human peripheral blood lymphocytes.
Imetelstat was not genotoxic in an in vivo mouse micronucleus assay at intravenous dose levels up to approximately 104 mg/kg. Fertility studies have not been conducted with imetelstat. Female monkeys given 14.1 mg/kg once weekly for 9 months exhibited uterine endometrial atrophy in a general toxicology study.
This effect was observed at a mean exposure (based on AUC) that is approximately 14.4-times the human exposure at the recommended clinical dose. This finding was not present in animals following a 14-week recovery period.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 47 mg Vial Label NDC 82959-112-01 RYTELO™ (imetelstat) for Injection 47 mg/vial For intravenous infusion after reconstitution and dilution. Single-Dose Vial. Discard Unused Portion. PRINCIPAL DISPLAY PANEL - 47 mg Vial Label
PRINCIPAL DISPLAY PANEL - 47 mg Vial Carton NDC 82959-112-01 Rx Only RYTELO™ (imetelstat) for Injection 47 mg/vial For intravenous infusion after reconstitution and dilution. Dispense the enclosed Medication Guide to each patient. Single-Dose Vial. Discard Unused Portion. 1 Vial geron ® PRINCIPAL DISPLAY PANEL - 47 mg Vial Carton
PRINCIPAL DISPLAY PANEL - 188 mg Vial Label NDC 82959-111-01 RYTELO™ (imetelstat) for Injection 188 mg/vial For intravenous infusion after reconstitution and dilution. Single-Dose Vial. Discard Unused Portion. PRINCIPAL DISPLAY PANEL - 188 mg Vial Label
PRINCIPAL DISPLAY PANEL - 188 mg Vial Carton NDC 82959-111-01 Rx Only RYTELO™ (imetelstat) for Injection 188 mg/vial For intravenous infusion after reconstitution and dilution. Dispense the enclosed Medication Guide to each patient. Single-Dose Vial. Discard Unused Portion. 1 Vial geron ® PRINCIPAL DISPLAY PANEL - 188 mg Vial Carton
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |