
Hear Loss Formula Ingredients & Drug Interactions
by SuperSmart
What is this page for?
First and foremost: checking Hear Loss Formula against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Hear Loss Formula is a dietary supplement by SuperSmart with 12 active ingredients. Its ingredients are commonly taken for common cold and immune support, antioxidant support, skin health and collagen formation.Based on those ingredients, 1,686 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Ginkgo biloba, Quercetin, Vitamin E. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Hear Loss Formula by SuperSmart
Ask about any prescription or over-the-counter medication and we check it for interactions with Hear Loss Formula by SuperSmart — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Hear Loss Formula by SuperSmart
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
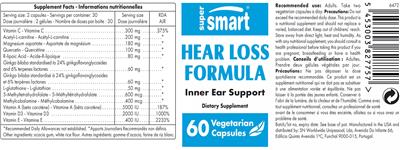
Hear Loss Formula contains 12 active ingredients including vitamins (C, A, E, D3, and B12 in methylcobalamin form), minerals (magnesium aspartate), plant extracts (ginkgo biloba, quercetin, R-lipoic acid), amino acid derivatives (acetyl-L-carnitine), and two ingredients we cannot evaluate: L-glutathione and 5-methyltetrahydrofolate. The product also contains two inactive ingredients — acacia gum and white rice flour — used as binders and flow agents.
These ingredients are combined to support hearing health, with ginkgo and magnesium having documented effects on blood flow and nerve function, and various antioxidants (vitamins C and E, R-lipoic acid, quercetin) intended to protect cells from oxidative stress.
Does it work?
Moderate evidence
The individual ingredients have varying levels of evidence for hearing-related benefits. Ginkgo biloba is rated Possibly Effective for hearing loss.
Vitamin B12 (methylcobalamin) is Effective for B12 deficiency and Possibly Effective for conditions like postherpetic neuralgia that can affect nerves. Acetyl-L-Carnitine is Possibly Effective for age-related cognitive decline and diabetic nerve damage.
The other ingredients — Vitamin C, A, E, D3, Magnesium, R-Lipoic Acid, and Quercetin — either show Possibly Effective or Insufficient Reliable Evidence for hearing loss specifically; we hold no effectiveness data for L-Glutathione and 5-Methyltetrahydrofolate.
How safe is it?
Well-documented data
Most ingredients are generally well tolerated at recommended doses. Vitamin C can cause stomach upset, heartburn, and kidney stones at very high doses (above 2 grams daily).
Vitamin A and Vitamin E can build up in your body with long-term high-dose use and carry toxicity risks; pregnancy safety data advises against high-dose vitamin A supplements. Magnesium commonly causes diarrhea and gastrointestinal irritation.
Quercetin safety during pregnancy and breastfeeding is not well established — avoid supplemental doses. R-Lipoic Acid can lower blood sugar and lacks reliable pregnancy and breastfeeding data.
Ginkgo may increase bleeding risk and should be avoided in pregnancy; safety while breastfeeding is not established. Acetyl-L-Carnitine pregnancy and breastfeeding safety is not well established.
We have no safety data on file for L-Glutathione and 5-Methyltetrahydrofolate.
Meds to double-check
Major interaction found
Before taking this product, double-check the following medication types: retinoid drugs for acne or skin conditions (Major interaction with Vitamin A), talinolol or other blood pressure medications (Major interaction with ginkgo), blood thinners and anticoagulants like warfarin, birth control or hormone therapy, levodopa/carbidopa for Parkinson's disease, diabetes medications, heart rhythm drugs, chemotherapy agents, antibiotics (especially quinolones), and bone medications. No interactions are documented for L-Glutathione and 5-Methyltetrahydrofolate in our data.
The bottom line
Scorecard at a glanceFully disclosed formula with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
This formula combines multiple antioxidants and nutrients with some evidence for supporting cellular health. If you take any prescription medications — especially blood thinners like warfarin, birth control, diabetes drugs, heart rhythm medications, or antibiotics — check with your pharmacist before starting.
Avoid if you're pregnant or breastfeeding unless your doctor advises otherwise, particularly due to Vitamin A and other ingredients with limited pregnancy data.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 10 of 12 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jun 25, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Hear Loss Formula, straight from the product label.
| Brand | SuperSmart |
|---|---|
| Barcode (UPC) | 5453003827757 |
| Net contents | 60 Vegetarian Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Jun 25, 2025 |
| DSLD ID | 332375 |
| Product type | Other Combinations |
| Supplement form | Capsule |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Hear Loss Formula by SuperSmart, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin C | 300 mg | 375% |
| Vitamin A | 5000 IU | 187% |
| Vitamin E | 400 IU | 2233% |
| Vitamin D3 | 2000 IU | 1000% |
| Quercetin | 100 mg | -- |
| L-Glutathione | 50 mg | -- |
| Magnesium Aspartate | 180 mg | -- |
| R-Lipoic Acid | 80 mg | -- |
| 5-Methyltetrahydrofolate | 600 mcg | -- |
| Acetyl-L-Carnitine | 200 mg | -- |
| Ginkgo biloba | 60 mg | -- |
| Methylcobalamin | 400 mcg | -- |
Other ingredients: Acacia Gum, White Rice Flour
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
Inner Ear Support
FDA Statement of Identity
Dietary Supplement
Suggested/Recommended/Usage/Directions
Recommended use: Adults. Take two vegetarian capsules a day.
Precautions
Precautions: Do not exceed the recommended daily dose. This product is a nutritional supplement and should not replace a varied, balanced diet.
Keep out of childrens' reach.
As with any nutritional supplement, you should consult a health professional before taking this product if you are pregnant, breastfeeding or have a health problem.
Storage
Store away from direct light, heat and humidity.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Hear Loss Formula by SuperSmart label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Hear Loss Formula by SuperSmart
These are the 12 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Capsule(s) Dosage formCapsule Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsVitamin A
Interacts with387 drugs
Vitamin A is an essential nutrient important for vision, skin, immune function, and growth. Most people get enough from a balanced diet, and supplemen...
Vitamin A monograph & interactionsVitamin E
Interacts with764 drugs
Vitamin E is an essential fat-soluble vitamin and antioxidant that most people get in adequate amounts from a normal diet. Supplements can help correc...
Vitamin E monograph & interactionsVitamin D3
Interacts with715 drugs
Vitamin D is a fat-soluble vitamin that helps your body absorb calcium and is important for healthy bones, muscles, and immune function. Many people,...
Vitamin D3 monograph & interactionsQuercetin
Interacts with1,169 drugs
Quercetin is a plant flavonoid with antioxidant and anti-inflammatory properties found in many common foods and sold as a supplement. While early rese...
Quercetin monograph & interactionsL-Glutathione
Magnesium Aspartate
Interacts with295 drugs
Magnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preven...
Magnesium Aspartate monograph & interactionsR-Lipoic Acid
Interacts with263 drugs
Alpha-lipoic acid (ALA) is an antioxidant made naturally by the body and found in small amounts in foods. It is most studied for diabetic nerve pain,...
R-Lipoic Acid monograph & interactions5-Methyltetrahydrofolate
Acetyl-L-Carnitine
Interacts with203 drugs
Acetyl-L-carnitine is a form of the amino acid carnitine that the body uses to help produce energy in cells. It is most studied for nerve pain and mem...
Acetyl-L-Carnitine monograph & interactionsGinkgo biloba
Interacts with1,266 drugs
Ginkgo is one of the world's most popular herbal supplements, mostly taken to support memory and circulation. The evidence for these uses is mixed and...
Ginkgo biloba monograph & interactionsMethylcobalamin
Interacts with20 drugs
Vitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very h...
Methylcobalamin monograph & interactionsOther (inactive) ingredients: Acacia Gum, White Rice Flour. These complete the product’s ingredient list but are not active constituents.
Hear Loss Formula by SuperSmart Drug Interactions
HelloPharmacist Interaction Report
Hear Loss Formula by SuperSmart contains multiple ingredients with documented interactions affecting a large number of medications.
The most serious interaction is Vitamin A with retinoids (a Major severity interaction) — taking retinoid drugs like isotretinoin (Accutane) or tretinoin alongside this product could produce dangerously high vitamin A levels and additive toxic effects.
Read the full breakdown — every affected drug type, severity by severity
Vitamin C interacts with estrogens (including birth control and hormone replacement therapy), potentially increasing estrogen levels by up to 55%, and with blood thinners like warfarin, where high-dose vitamin C may reduce warfarin's effectiveness. Magnesium interacts with levodopa/carbidopa (a Major interaction), reducing levodopa absorption by 35%, and with several other drug categories including skeletal muscle relaxants, blood pressure medications, diabetes drugs, antibiotics, and bone medications.
Ginkgo biloba carries a Major interaction with talinolol, a blood pressure medication, increasing its levels by 36%.
Additionally, Vitamin E interacts with blood thinners and anticoagulants at doses above 400 IU daily, increasing bleeding risk, and with several chemotherapy drugs. Vitamin D interacts with thiazide diuretics and heart rhythm medications, potentially causing dangerously high calcium levels.
Quercetin interacts with blood pressure drugs, cholesterol medications, blood thinners, antibiotics, and immunosuppressants. R-Lipoic Acid interacts with blood thinners and diabetes medications.
Acetyl-L-Carnitine interacts with blood thinners and antidepressants. Altogether, these interactions span 1,662 individual medications.
We could not check L-Glutathione and 5-Methyltetrahydrofolate — no interaction data is on file for them. Check your exact medications with the tool on this page before starting this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Hear Loss Formula?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Hear Loss Formula interact with 1,686 drugs. Click any drug to see the details.
10 of the 12 ingredients in Hear Loss Formula interact with drugs. Each result below shows which ingredient is responsible. Ginkgo biloba Quercetin Vitamin E Vitamin D3 Vitamin A Magnesium Aspartate R-Lipoic Acid Vitamin C Acetyl-L-Carnitine Methylcobalamin
6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Hear Loss Formula — through 1 ingredient. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Hear Loss Formula — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Ado-trastuzumab Emtansine interactionGinkgo BilobaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba + Ado-trastuzumab Emtansine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Ado-trastuzumab Emtansine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with Hear Loss Formula — through 1 ingredient. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with Hear Loss Formula — through 1 ingredient. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Abacavir, Lamivudine interactionAbciximabReoPro
How Abciximab interacts with Hear Loss Formula — through 4 ingredients. Tap an ingredient for the detail:
Vitamin EAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Read the full Vitamin E + Abciximab interactionR-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full R-lipoic Acid + Abciximab interactionGinkgo BilobaAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Read the full Ginkgo Biloba + Abciximab interactionMagnesium AspartateAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium Aspartate + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Hear Loss Formula — through 4 ingredients. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Abemaciclib interactionQuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Abemaciclib interactionGinkgo BilobaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba + Abemaciclib interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Hear Loss Formula — through 5 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Abiraterone interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Abiraterone interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Abiraterone interactionGinkgo BilobaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba + Abiraterone interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Hear Loss Formula — through 5 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Abiraterone Acetate interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Abiraterone Acetate interactionGinkgo BilobaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba + Abiraterone Acetate interactionQuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Abiraterone Acetate interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Hear Loss Formula — through 5 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2C9 substrates.
Read the full Quercetin + Abrocitinib interactionVitamin EAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Read the full Vitamin E + Abrocitinib interactionR-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full R-lipoic Acid + Abrocitinib interactionGinkgo BilobaAnticoagulant/antiplatelet Drugs, Cytochrome P450 2c9 (cyp2c9) Substrates +1 Moderate
Interaction Summary
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Read the full Ginkgo Biloba + Abrocitinib interactionMagnesium AspartateAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium Aspartate + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Hear Loss Formula — through 4 ingredients. Tap an ingredient for the detail:
Ginkgo BilobaCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba + Acalabrutinib interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acalabrutinib interactionQuercetinP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of P-glycoprotein substrates.
Read the full Quercetin + Acalabrutinib interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Hear Loss Formula — through 4 ingredients. Tap an ingredient for the detail:
Ginkgo BilobaAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking ginkgo with antidiabetes drugs might alter the response to antidiabetes drugs.
Read the full Ginkgo Biloba + Acarbose interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acarbose interactionQuercetinAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use of quercetin and antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Quercetin + Acarbose interactionR-lipoic AcidAntidiabetes Drugs Minor
Interaction Summary
Theoretically, taking alpha-lipoic acid with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full R-lipoic Acid + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Hear Loss Formula — through 2 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acebutolol interactionQuercetinAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking quercetin with antihypertensive drugs might increase the risk of hypotension.
Read the full Quercetin + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Hear Loss Formula — through 5 ingredients. Tap an ingredient for the detail:
R-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full R-lipoic Acid + Acenocoumarol interactionGinkgo BilobaAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Read the full Ginkgo Biloba + Acenocoumarol interactionAcetyl-l-carnitineAcenocoumarol (sintrom) Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the anticoagulant effects of acenocoumarol.
Read the full Acetyl-l-carnitine + Acenocoumarol interactionVitamin EAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Read the full Vitamin E + Acenocoumarol interactionMagnesium AspartateAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium Aspartate + Acenocoumarol interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with Hear Loss Formula — through 3 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen interactionGinkgo BilobaCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba + Acetaminophen interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Hear Loss Formula — through 7 ingredients. Tap an ingredient for the detail:
Ginkgo BilobaCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba + Acetaminophen, Aspirin interactionVitamin EAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Read the full Vitamin E + Acetaminophen, Aspirin interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Aspirin interactionQuercetinOrganic Anion Transporter 3 (oat3) Substrates, Organic Anion Transporter 1 (oat1) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the effects and adverse effects of OAT3 substrates.
Read the full Quercetin + Acetaminophen, Aspirin interactionR-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full R-lipoic Acid + Acetaminophen, Aspirin interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin interactionMagnesium AspartateAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium Aspartate + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Hear Loss Formula — through 8 ingredients. Tap an ingredient for the detail:
R-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full R-lipoic Acid + Acetaminophen, Aspirin, Caffeine interactionGinkgo BilobaAnticoagulant/antiplatelet Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Read the full Ginkgo Biloba + Acetaminophen, Aspirin, Caffeine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Aspirin, Caffeine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Aspirin, Caffeine interactionQuercetinOrganic Anion Transporter 1 (oat1) Substrates, Organic Anion Transporter 3 (oat3) Substrates +1 Moderate
Interaction Summary
Theoretically, concomitant use might increase the effects and adverse effects of OAT1 substrates.
Read the full Quercetin + Acetaminophen, Aspirin, Caffeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Aspirin, Caffeine interactionMagnesium AspartateAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium Aspartate + Acetaminophen, Aspirin, Caffeine interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with Hear Loss Formula — through 3 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionGinkgo BilobaCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with Hear Loss Formula — through 3 ingredients. Tap an ingredient for the detail:
Ginkgo BilobaCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba + Acetaminophen, Butalbital interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Butalbital interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with Hear Loss Formula — through 6 ingredients. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Butalbital, Caffeine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Butalbital, Caffeine interactionQuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Butalbital, Caffeine interactionGinkgo BilobaCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba + Acetaminophen, Butalbital, Caffeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Hear Loss Formula — through 6 ingredients. Tap an ingredient for the detail:
Ginkgo BilobaCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs +1 Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba + Acetaminophen, Butalbital, Caffeine, Codeine interactionQuercetinCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Hear Loss Formula — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Butalbital, Codeine interactionGinkgo BilobaCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba + Acetaminophen, Butalbital, Codeine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Butalbital, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Hear Loss Formula — through 4 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Butalbital, Codeine Phosphate interactionQuercetinCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Butalbital, Codeine Phosphate interactionGinkgo BilobaSeizure Threshold Lowering Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba + Acetaminophen, Butalbital, Codeine Phosphate interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Hear Loss Formula — through 6 ingredients. Tap an ingredient for the detail:
Ginkgo BilobaCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionQuercetinCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Hear Loss Formula — through 6 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Caffeine, Codeine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Caffeine, Codeine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Caffeine, Codeine interactionGinkgo BilobaSeizure Threshold Lowering Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba + Acetaminophen, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with Hear Loss Formula — through 6 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Caffeine, Codeine, Salicylamide interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Caffeine, Codeine, Salicylamide interactionQuercetinCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Caffeine, Codeine, Salicylamide interactionGinkgo BilobaSeizure Threshold Lowering Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba + Acetaminophen, Caffeine, Codeine, Salicylamide interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Codeine, Salicylamide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with Hear Loss Formula — through 6 ingredients. Tap an ingredient for the detail:
Ginkgo BilobaCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs +1 Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Caffeine, Dihydrocodeine interactionQuercetinCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with Hear Loss Formula — through 6 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Caffeine, Isometheptene interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Caffeine, Isometheptene interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Caffeine, Isometheptene interactionGinkgo BilobaCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba + Acetaminophen, Caffeine, Isometheptene interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Isometheptene interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Caffeine, PyrilamineMidol Max Strength Menstrual
How Acetaminophen, Caffeine, Pyrilamine interacts with Hear Loss Formula — through 6 ingredients. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Caffeine, Pyrilamine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Caffeine, Pyrilamine interactionQuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Caffeine, Pyrilamine interactionGinkgo BilobaCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba + Acetaminophen, Caffeine, Pyrilamine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Pyrilamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Pyrilamine interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with Hear Loss Formula — through 7 ingredients. Tap an ingredient for the detail:
Ginkgo BilobaCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs +1 Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetyl-l-carnitineSerotonergic Drugs Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Read the full Acetyl-l-carnitine + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionQuercetinCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with Hear Loss Formula — through 7 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionGinkgo BilobaCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs +1 Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetyl-l-carnitineSerotonergic Drugs Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Read the full Acetyl-l-carnitine + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Hear Loss Formula with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Ginkgo biloba
Talinolol
Taking ginkgo with talinolol seems to increase blood levels of talinolol.
There is some evidence that using ginkgo leaf extract 120 mg orally three times daily for 14 days can increase levels of talinolol by 36% in healthy male individuals. However, single doses of ginkgo do not seem to affect talinolol pharmacokinetics.
Alprazolam (Xanax)
Theoretically, ginkgo might decrease the levels and clinical effects of alprazolam.
In clinical research, ginkgo extract (Ginkgold) 120 mg twice daily seems to decrease alprazolam levels by about 17%. However, ginkgo does not appear to decrease the elimination half-life of alprazolam. This suggests that ginkgo is more likely to decrease absorption of alprazolam rather than induce hepatic metabolism of alprazolam.
Anticoagulant/Antiplatelet Drugs
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin. Theoretically, ginkgo might increase the risk of bleeding if used with other anticoagulant or antiplatelet drugs.
Several pharmacodynamic studies suggest that ginkgo inhibits platelet aggregation. It is thought that the ginkgo constituent, ginkgolide B, displaces platelet-activating factor (PAF) from its binding sites, decreasing blood coagulation. Several case reports have documented serious bleeding events in patients taking ginkgo. However, population and clinical studies have produced mixed results. Some evidence shows that short-term use of ginkgo leaf does not significantly reduce platelet aggregation and blood clotting. A study in healthy males who took a specific ginkgo leaf extract (EGb 761) 160 mg twice daily for 7 days found no change in prothrombin time. An analysis of a large medical record database suggests that ginkgo increases the risk of a bleeding adverse event by 38% when taken concurrently with warfarin. It has been suggested that ginkgo has to be taken for at least 2-3 weeks to have a significant effect on platelet aggregation. However, a meta-analysis of 18 studies using standardized ginkgo extracts, 80-480 mg daily for up to 32 weeks, did not find a significant effect on platelet aggregation, fibrinogen concentration, or PT/aPTT. In addition, a single dose of ginkgo plus clopidogrel or ticlopidine does not seem to significantly increase bleeding time or platelet aggregation. Also, taking ginkgo leaf extract daily for 8 days in conjunction with rivaroxaban does not affect anti-factor Xa activity; however, this study did not evaluate bleeding time.
Anticonvulsants
Theoretically, ginkgo might reduce the effectiveness of anticonvulsants.
Ginkgo seeds contain ginkgotoxin. Large amounts of ginkgotoxin can cause neurotoxicity and seizure. Ginkgotoxin is present in much larger amounts in ginkgo seeds than leaves. Ginkgo leaf extract contains trace amounts of ginkgotoxin. The amount of ginkgotoxin in ginkgo leaf and leaf extract seems unlikely to cause toxicity. However, there are anecdotal reports of seizure occurring after use of ginkgo leaf both in patients without a history of seizure disorder and in those with previously well-controlled epilepsy.
Antidiabetes Drugs
Theoretically, taking ginkgo with antidiabetes drugs might alter the response to antidiabetes drugs.
Ginkgo leaf extract seems to alter insulin secretion and metabolism, and might affect blood glucose levels in people with type 2 diabetes. The effect of ginkgo seems to differ depending on the insulin and treatment status of the patient. In diet-controlled diabetes patients with hyperinsulinemia, taking ginkgo does not seem to significantly affect insulin or blood glucose levels. In patients with hyperinsulinemia who are treated with oral hypoglycemic agents, taking ginkgo seems to decrease insulin levels and increase blood glucose following an oral glucose tolerance test. Researchers speculate that this could be due to ginkgo-enhanced hepatic metabolism of insulin. In patients with pancreatic exhaustion, taking ginkgo seems to stimulate pancreatic beta-cells, resulting in increased insulin and C-peptide levels, but with no significant change in blood glucose levels in response to an oral glucose tolerance test.
Atorvastatin (Lipitor)
Theoretically, ginkgo might decrease the levels and clinical effects of atorvastatin.
In humans, intake of ginkgo extract appears to increase atorvastatin clearance, reducing the area under the curve of atorvastatin by 10% to 14% and the maximum concentration by 29%. However, this interaction does not appear to affect cholesterol synthesis and absorption. Further, a model in rats with hyperlipidemia suggests that administering ginkgo extract does not impact blood levels of atorvastatin and leads to lower total cholesterol, low-density lipoprotein cholesterol, and triglycerides when compared with rats given atorvastatin alone.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Laboratory research suggests that ginkgo leaf extract can mildly inhibit CYP1A2 enzymes. However, clinical research suggests ginkgo might not affect CYP1A2. Until more is known, use ginkgo cautiously in patients taking drugs metabolized by these enzymes.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP2C19.
Some clinical research shows that a specific ginkgo leaf extract (Remembrance, Herbs Product LTD) 140 mg twice daily can induce CYP2C19 enzymes and potentially decrease levels of drugs metabolized by these enzymes. However, other clinical research shows that taking ginkgo 120 mg twice daily for 12 days has no effect on levels of drugs metabolized by CYP2C19.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, ginkgo might increase levels of drugs metabolized by CYP2C9.
In vitro, a specific standardized extract of ginkgo leaf (EGb 761) inhibits CYP2C9 activity . The terpenoid (ginkgolides) and flavonoid (quercetin, kaempferol, etc.) constituents seem to be responsible for this effect. Most ginkgo extracts contain some amount of these constituents. Therefore, other ginkgo leaf extracts might also inhibit the CYP2C9 enzyme. However, clinical research suggests that ginkgo might not have a significant effect on CYP2C9 in humans. Ginkgo does not seem to significantly affect the pharmacokinetics of CYP2C9 substrates diclofenac or tolbutamide.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
There is conflicting evidence about whether ginkgo induces or inhibits CYP3A4. Ginkgo does not appear to affect hepatic CYP3A4. However, it is not known if ginkgo affects intestinal CYP3A4. Preliminary clinical research suggests that taking ginkgo does not significantly affect levels of donepezil, lopinavir, or ritonavir, which are all CYP3A4 substrates. Other clinical research also suggests ginkgo does not significantly affect CYP3A4 activity. However, there are two case reports of decreased efavirenz concentrations and increased viral load in patients taking ginkgo. It is suspected that terpenoids from the ginkgo extract reduced drug levels by inducing cytochrome P450 3A4 (CYP3A4).
Efavirenz (Sustiva)
Theoretically, ginkgo might decrease the levels and clinical effects of efavirenz.
There are two case reports of decreased efavirenz concentrations and increased viral load in patients taking ginkgo. In one case, an HIV-positive male experienced over a 50% decrease in efavirenz levels over the course of 14 months while taking ginkgo extract. HIV-1 RNA copies also increased substantially, from less than 50 to more than 1500. It is suspected that terpenoids from the ginkgo extract reduced drug levels by inducing cytochrome P450 3A4 (CYP3A4). In another case report, a patient stable on antiviral therapy including efavirenz for 10 years, had an increase in viral load from <50 copies/mL to 1350 copies/mL after 2 months of taking a combination of supplements including ginkgo. After stopping ginkgo, the viral load was again controlled with the same antiviral therapy regimen.
Ibuprofen (Advil, Others)
Theoretically, ginkgo might increase the risk of bleeding when used with ibuprofen.
Ginkgo might have antiplatelet effects and has been associated with several case reports of spontaneous bleeding. In one case, a 71-year-old male had taken a specific ginkgo extract (Gingium, Biocur) 40 mg twice daily for 2.5 years. About 4 weeks after starting ibuprofen 600 mg daily he experienced a fatal intracerebral hemorrhage. However, the antiplatelet effects of ginkgo have been questioned. A meta-analysis and other studies have not found a significant antiplatelet effect with standardized ginkgo extracts, 80 mg to 480 mg taken daily for up to 32 weeks.
P-Glycoprotein Substrates
Theoretically, taking ginkgo with P-glycoprotein substrates might increase the levels and adverse effects of these substrates.
A small clinical study in healthy volunteers shows that using ginkgo leaf extract 120 mg orally three times daily for 14 days can increase levels of the P-glycoprotein substrate, talinolol, by 36% in healthy male individuals. However, single doses of ginkgo do not have the same effect.
Risperidone (Risperdal)
Theoretically, taking ginkgo with risperidone might increase the levels and adverse effects of risperidone.
A single case of priapism has been reported for a 26-year-old male with schizophrenia who used risperidone 3 mg daily along with ginkgo extract 160 mg daily. Risperidone is metabolized by cytochrome P450 (CYP) 2D6 and CYP3A4. CYP3A4 activity might be affected by ginkgo. Theoretically, ginkgo may inhibit the metabolism of risperidone and increase the risk of adverse effects.
Rosiglitazone (Avandia)
Theoretically, ginkgo might decrease the levels and clinical effects of rosiglitazone.
Animal research shows that ginkgo leaf extract orally 100 or 200 mg/kg daily for 10 days alters the pharmacodynamics of rosiglitazone in a dose-dependent manner. The 100 mg/kg and 200 mg/kg doses reduce the area under the concentration time curve (AUC) of rosiglitazone by 39% and 52%, respectively, and the half-life by 28% and 39%, respectively. It is hypothesized that these changes may be due to induction of cytochrome P450 2C8 by ginkgo.
Seizure Threshold Lowering Drugs
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Ginkgo seeds contain ginkgotoxin. Large amounts of ginkgotoxin can cause neurotoxicity and seizure. Ginkgotoxin is present in much larger amounts in ginkgo seeds than leaves. Ginkgo leaf extract contains trace amounts of ginkgotoxin. The amount of ginkgotoxin in ginkgo leaf and leaf extract seems unlikely to cause toxicity. However, there are anecdotal reports of seizure occurring after use of ginkgo leaf both in patients without a history of seizure disorder and in those with previously well-controlled epilepsy.
Simvastatin (Zocor)
Theoretically, ginkgo might decrease the levels and clinical effects of simvastatin.
Clinical research shows that taking ginkgo extract can reduce the area under the curve and maximum concentration of simvastatin by 32% to 39%. However, ginkgo extract does not seem to affect the cholesterol-lowering ability of simvastatin.
Sofosbuvir (Sovaldi)
Theoretically, ginkgo might increase the levels and clinical effects of sofosbuvir.
Animal research in rats shows that giving a ginkgo extract 25 mg/kg orally daily for 14 days increases the area under the concentration time curve (AUC) after a single sofosbuvir dose of 40 mg/kg by 11%, increases the half-life by 60%, and increases the plasma concentration at 4 hours by 38%. This interaction appears to be related to the inhibition of intestinal P-glycoprotein by ginkgo.
Tacrolimus (Prograf)
Theoretically, ginkgo might increase the blood levels of tacrolimus.
In vitro evidence suggests that certain biflavonoids in ginkgo leaves (i.e. amentoflavone, ginkgetin, bilobetin) may inhibit the metabolism of tacrolimus by up to 50%. This interaction appears to be time-dependent and due to inhibition of cytochrome P450 (CYP) 3A4 by these bioflavonoids. In rats given tacrolimus 1 mg/kg orally, amentoflavone was shown to increase the area under the concentration time curve (AUC) of tacrolimus by 3.8-fold.
Trazodone (Desyrel)
Theoretically, ginkgo might increase the levels and clinical effects of trazodone.
In a case report, an Alzheimer patient taking trazodone 20 mg twice daily and ginkgo leaf extract 80 mg twice daily for four doses became comatose. The coma was reversed by administration of flumazenil (Romazicon). Coma might have been induced by excessive GABA-ergic activity. Ginkgo flavonoids are thought to have GABA-ergic activity and act directly on benzodiazepine receptors. Ginkgo might also increase metabolism of trazodone to active GABA-ergic metabolites, possibly by inducing cytochrome P450 3A4 (CYP3A4) metabolism.
Warfarin (Coumadin)
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Several pharmacodynamic studies suggest that ginkgo inhibits platelet aggregation. It is thought that the ginkgo constituent, ginkgolide B, displaces platelet-activating factor (PAF) from its binding sites, decreasing blood coagulation. Several case reports have documented serious bleeding events in patients taking ginkgo. Information from a medical database suggests that when taken concurrently with warfarin, ginkgo increases the risk of a bleeding adverse event by 38%. There is also some evidence that ginkgo leaf extract can inhibit cytochrome P450 2C9, an enzyme that metabolizes warfarin. This could result in increased warfarin levels. However, population and clinical research has produced mixed results. Clinical research in healthy people suggests that ginkgo has no effect on INR, or the pharmacokinetics or pharmacodynamics of warfarin. A meta-analysis of 18 studies using standardized ginkgo extracts, 80 mg to 480 mg daily for up to 32 weeks, did not find a significant effect on platelet aggregation, fibrinogen concentration, or PT/aPTT. There is also some preliminary clinical research that suggests ginkgo might not significantly increase the effects of warfarin in patients that have a stable INR.
Nifedipine (Procardia)
Theoretically, taking ginkgo with oral, but not intravenous, nifedipine might increase levels and adverse effects of nifedipine.
Animal research and some clinical evidence suggests that taking ginkgo leaf extract orally in combination with oral nifedipine might increase nifedipine levels and cause increased side effects, such as headaches, dizziness, and hot flushes. However, taking ginkgo orally does not seem to affect the pharmacokinetics of intravenous nifedipine.
Omeprazole (Prilosec)
Theoretically, taking ginkgo with omeprazole might decrease the levels and clinical effects of omeprazole.
Clinical research shows that a specific ginkgo leaf extract (Remembrance, Herbs Product LTD) 140 mg twice daily can induce cytochrome P450 (CYP) 2C19 enzymes and decrease levels of omeprazole by about 27% to 42%.
Quercetin
Antidiabetes Drugs
Theoretically, concomitant use of quercetin and antidiabetes drugs might increase the risk of hypoglycemia.
Clinical research suggests that a combination of quercetin, myricetin, and chlorogenic acid reduce levels of fasting glucose in patients with type 2 diabetes, including those already taking antidiabetes agents. The effect of quercetin alone is unknown.
Antihypertensive Drugs
Theoretically, taking quercetin with antihypertensive drugs might increase the risk of hypotension.
Quercetin can modestly decrease blood pressure in people with mild hypertension. Theoretically, it might have additive blood pressure lowering effects when used with antihypertensive drugs.
Cyclosporine (Neoral, Sandimmune)
Theoretically, concomitant use might increase the levels and adverse effects of cyclosporine.
A small study in healthy volunteers shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of a single dose of cyclosporine, possibly due to inhibition of p-glycoprotein or cytochrome P450 3A4 (CYP3A4), which metabolizes cyclosporin.
Cytochrome P450 2C8 (Cyp2C8) Substrates
Theoretically, concomitant use might increase the levels and adverse effects of CYP2C8 substrates.
In vitro research shows that quercetin inhibits CYP2C8. Inhibition of paclitaxel (Taxol) metabolism via CYP2C8 has been reported in vitro. However, a small study in humans found no effect of quercetin on rosiglitazone (Avandia), which is also a CYP2C8 substrate.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, concomitant use might increase the levels and adverse effects of CYP2C9 substrates.
A small clinical study in healthy volunteers shows that taking quercetin 500 mg twice daily for 10 days prior to taking diclofenac, a CYP2C9 substrate, increases diclofenac plasma levels by 75% and prolongs the half-life by 32.5%. Animal research also shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of losartan (Cozaar), a substrate of CYP2C9. Furthermore, laboratory research shows that quercetin inhibits CYP2C9.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
In vitro research show that quercetin inhibits CYP2D6. This effect has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
A small clinical study in healthy volunteers shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of a single dose of cyclosporine (Neoral, Sandimmune), a substrate of CYP3A4. Animal research also shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of losartan (Cozaar) and quetiapine (Seroquel), substrates of CYP3A4. Other laboratory research also shows that quercetin inhibits CYP3A4. However, one clinical study shows that quercetin can increase the metabolism of midazolam, a substrate of CYP3A4, and decrease serum concentrations of midazolam by about 24% in some healthy individuals, suggesting possible induction of CYP3A4.
Diclofenac (Voltaren, Others)
Theoretically, concomitant use might increase the levels and adverse effects of diclofenac.
A small clinical study in healthy volunteers shows that taking quercetin 500 mg twice daily for 10 days prior to taking diclofenac increases diclofenac plasma levels by 75% and prolongs the half-life by 32.5%. This is thought to be due to inhibition of CYP2C9 by quercetin.
Losartan (Cozaar)
Theoretically, concomitant use might increase the effects and adverse effects of losartan and decrease the effects of its active metabolite.
Animal research shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of losartan (Cozaar) while decreasing plasma levels of losartan's active metabolite. This metabolite, which is around 10-fold more potent than losartan, is the result of cytochrome P450 (CYP) 2C9- and CYP3A4-mediated transformation of losartan. Additionally, in vitro research shows that quercetin may inhibit P-glycoprotein-mediated efflux of losartan from the intestines, resulting in increased absorption of losartan. These results suggest that concomitant use of quercetin and losartan might increase systemic exposure to losartan while also decreasing plasma concentrations of losartan's active and more potent metabolite.
Midazolam (Versed)
Theoretically, concomitant use might decrease the levels and effects of midazolam.
A small clinical study in healthy volunteers shows that quercetin can increase the metabolism of midazolam, with a decrease in AUC of about 24%.
Mitoxantrone
Theoretically, quercetin might increase the effects and adverse effects of mitoxantrone.
In vitro research shows that quercetin increases the intracellular accumulation and cytotoxicity of mitoxantrone, possibly through inhibition of breast cancer resistance protein (BCRP), of which mitoxantrone is a substrate. So far, this interaction has not been reported in humans.
Organic Anion Transporter 1 (Oat1) Substrates
Theoretically, concomitant use might increase the effects and adverse effects of OAT1 substrates.
In vitro research shows that quercetin is a strong non-competitive inhibitor of OAT1, with half-maximal inhibitory concentration (IC50) values less than 10 mcM. So far, this interaction has not been reported in humans.
Organic Anion Transporter 3 (Oat3) Substrates
Theoretically, concomitant use might increase the effects and adverse effects of OAT3 substrates.
In vitro research shows that quercetin is a strong non-competitive inhibitor of OAT3, with half-maximal inhibitory concentration (IC50) values as low as 0.75 mcM. So far, this interaction has not been reported in humans.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Theoretically, concomitant use might increase the effects and adverse effects of OATP substrates.
In vitro evidence shows that quercetin can inhibit organic anion-transporting peptide (OATP) 1B1-mediated uptake of estrone-3-sulfate and pravastatin. Furthermore, clinical research in healthy males shows that intake of quercetin along with pravastatin increases the AUC of pravastatin by 24%, prolongs its half-life by 14%, and decreases its apparent clearance by 18%, suggesting that quercetin modestly inhibits the uptake of pravastatin in hepatic cells.
P-Glycoprotein Substrates
Theoretically, concomitant use might alter the effects and adverse effects of P-glycoprotein substrates.
There is preliminary evidence that quercetin inhibits the gastrointestinal P-glycoprotein efflux pump, which might increase the bioavailability and serum levels of drugs transported by the pump. A small study in healthy volunteers reported that pretreatment with quercetin increased bioavailability and plasma levels after a single dose of cyclosporine (Neoral, Sandimmune). Also, two small studies have shown that quercetin might decrease the absorption of talinolol, a substrate transported by the gastrointestinal P-glycoprotein efflux pump. However, in another small study, several days of quercetin treatment did not significantly affect the pharmacokinetics of saquinavir (Invirase). The reason for these discrepancies is not entirely clear. Until more is known, use quercetin cautiously in combination with P-glycoprotein substrates.
Pravastatin (Pravachol)
Theoretically, concomitant use might increase the effects and adverse effects of pravastatin.
In vitro evidence shows that quercetin can inhibit OATP 1B1-mediated uptake of pravastatin. Also, preliminary clinical research in healthy males shows that intake of quercetin along with pravastatin increases the maximum concentration of pravastatin by 24%, prolongs its half-life by 14%, and decreases its apparent clearance by 18%, suggesting that quercetin modestly inhibits the uptake of pravastatin in hepatic cells.
Prazosin (Minipress)
Theoretically, quercetin might increase the effects and adverse effects of prazosin.
In vitro research shows that quercetin inhibits the transcellular efflux of prazosin, possibly through inhibition of breast cancer resistance protein (BCRP), of which prazosin is a substrate. BCRP is an ATP-binding cassette efflux transporter in the intestines, kidneys, and liver. So far, this interaction has not been reported in humans.
Quetiapine (Seroquel)
Theoretically, concomitant use might increase the effects and adverse effects of quetiapine.
Animal research shows that pretreatment with quercetin can increase plasma levels of quetiapine and prolong its clearance, possibly due to inhibition of cytochrome P450 3A4 (CYP3A4) by quercetin. Additionally, the brain-to-plasma ratio of quetiapine concentrations increased, possibly due to inhibition of P-glycoprotein at the blood-brain barrier. This interaction has not been reported in humans.
Quinolone Antibiotics
Theoretically, concomitant use might inhibit the effects of quinolone antibiotics.
In vitro, quercetin binds to the DNA gyrase site on bacteria, which may interfere with the activity of quinolone antibiotics.
Sulfasalazine (Azulfidine)
Theoretically, quercetin might increase the effects and adverse effects of sulfasalazine.
Animal research shows that quercetin increases the maximum serum concentration (Cmax) and area under the curve (AUC) of sulfasalazine, possibly through inhibition of breast cancer resistance protein (BCRP), of which sulfasalazine is a substrate. So far, this interaction has not been reported in humans.
Warfarin (Coumadin)
Theoretically, quercetin may increase the risk of bleeding if used with warfarin.
Animal and in vitro studies show that quercetin might increase serum levels of warfarin. Quercetin and warfarin have the same human serum albumin (HSA) binding site, and in vitro research shows that quercetin has stronger affinity for the HSA binding site and can theoretically displace warfarin, causing higher serum levels of warfarin. Animal research shows that taking quercetin for 2 weeks before initiating warfarin increases the maximum serum level of warfarin by 30%, the half-life by 10%, and the overall exposure by 63% when compared with control. Concomitant administration of quercetin and warfarin, without quercetin pre-treatment, also increased these measures, but to a lesser degree. Researchers theorize that inhibition of CYP3A4 by quercetin may explain these effects. So far, this interaction has not been reported in humans.
Vitamin E
Alkylating Agents
Theoretically, antioxidant effects of vitamin E might reduce the effectiveness of alkylating agents.
There's concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin E have on chemotherapy. Advise patients to consult their oncologist before using vitamin E supplements, especially in high doses.
Anticoagulant/Antiplatelet Drugs
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Vitamin E seems to inhibit of platelet aggregation and antagonize the effects of vitamin K-dependent clotting factors. These effects appear to be dose-dependent, and are probably only likely to be clinically significant with doses of at least 800 units daily. Mixed tocopherols, such as those found in food, might have a greater antiplatelet effect than alpha-tocopherol. RRR alpha-tocopherol (natural vitamin E) 1000 IU daily antagonizes vitamin K-dependent clotting factors. Advise patients to avoid high doses of vitamin E, especially in people with low vitamin K intake or other risk factors for bleeding.
Antitumor Antibiotics
Theoretically, antioxidant effects of vitamin E might reduce the effectiveness of antitumor antibiotics.
There's concern that antioxidants could reduce the activity of antitumor antibiotic drugs such as doxorubicin, which generate free radicals. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin E have on chemotherapy involving antitumor antibiotics. Advise patients to consult their oncologist before using vitamin E supplements, especially in high doses.
Cyclosporine (Neoral, Sandimmune)
A specific form of vitamin E might increase absorption and levels of cyclosporine.
There is some evidence that one specific formulation of vitamin E (D-alpha-tocopheryl-polyethylene glycol-1000 succinate, TPGS, tocophersolan, Liqui-E) might increase absorption of cyclosporine. This vitamin E formulation forms micelles which seems to increase absorption of cyclosporine by 40% to 72% in some patients. However, this interaction is unlikely to occur with the usual forms of vitamin E.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Vitamin E appears to bind with the nuclear receptor, pregnane X receptor (PXR), which results in increased expression of CYP3A4. Although the clinical significance of this is not known, use caution when considering concomitant use of vitamin E and other drugs affected by these enzymes.
Selumetinib (Koselugo)
Taking selumetinib with vitamin E can result in a total daily dose of vitamin E that exceeds safe limits and therefore might increase the risk of bleeding.
Selumetinib contains 48-54 IU vitamin E per capsule. The increased risk of bleeding with vitamin E appears to be dose-dependent. Be cautious when using selumetinib in combination with supplemental vitamin E, especially in patients at higher risk of bleed, such as those with chronic conditions and those taking antiplatelet drugs.
Warfarin (Coumadin)
Using vitamin E with warfarin might increase the risk of bleeding.
Due to interference with production of vitamin K-dependent clotting factors, use of more than 400 IU of vitamin E daily with warfarin might increase prothrombin time (PT), INR, and the risk of bleeding,. At a dose of 1000 IU per day, vitamin E can antagonize vitamin K-dependent clotting factors even in people not taking warfarin. Limited clinical evidence suggests that doses up to 1200 IU daily may be used safely by patients taking warfarin, but this may not be applicable in all patient populations.
Niacin
Vitamin E might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises high-density lipoprotein (HDL) cholesterol levels in people with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50%. Vitamin E alone combined with a statin does not seem to decrease HDL levels. It is not known whether the adverse effect on HDL is due to one of the other antioxidants or to the combination. It also is not known whether it will occur in other patient populations.
Vitamin D3
Aluminum
Vitamin D might increase aluminum absorption and toxicity, but this has only been reported in people with renal failure.
The protein that transports calcium across the intestinal wall can also bind and transport aluminum. This protein is stimulated by vitamin D, which may therefore increase aluminum absorption. This mechanism may contribute to increased aluminum levels and toxicity in people with renal failure, when they take vitamin D and aluminum-containing phosphate binders chronically.
Atorvastatin (Lipitor)
Vitamin D might reduce absorption of atorvastatin.
A small, low-quality clinical study shows that taking vitamin D reduces levels of atorvastatin and its active metabolites by up to 55%. However, while atorvastatin levels decreased, total cholesterol, low-density lipoprotein (LDL) cholesterol, and high-density lipoprotein (HDL) cholesterol levels did not substantially change. Atorvastatin is metabolized in the gut by CYP3A4 enzymes, and researchers theorized that vitamin D might induce CYP3A4, causing reduced levels of atorvastatin. However, this proposed mechanism was not specifically studied.
Calcipotriene (Dovonex)
Taking calcipotriene with vitamin D increases the risk for hypercalcemia.
Calcipotriene is a vitamin D analog used topically for psoriasis. It can be absorbed in sufficient amounts to cause systemic effects, including hypercalcemia. Theoretically, combining calcipotriene with vitamin D supplements might increase the risk of hypercalcemia.
Digoxin (Lanoxin)
Theoretically, hypercalcemia induced by high-dose vitamin D can increase the risk of arrhythmia from digoxin.
High doses of vitamin D can cause hypercalcemia. Hypercalcemia increases the risk of fatal cardiac arrhythmias with digoxin. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and digoxin concurrently.
Diltiazem (Cardizem, Others)
Theoretically, hypercalcemia induced by high-dose vitamin D can reduce the therapeutic effects of diltiazem for arrhythmia.
High doses of vitamin D can cause hypercalcemia. Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically this could also occur with diltiazem. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and diltiazem concurrently.
Thiazide Diuretics
Theoretically, taking thiazide diuretics and high-dose vitamin D can increase the risk of hypercalcemia.
Thiazide diuretics decrease urinary calcium excretion, which could lead to hypercalcemia if vitamin D supplements are taken concurrently. This has been reported in people being treated with vitamin D for hypoparathyroidism, and also in elderly people with normal parathyroid function who were taking a thiazide, vitamin D, and calcium-containing antacids daily.
Verapamil (Calan, Others)
Hypercalcemia induced by high-dose vitamin D can reduce the therapeutic effects of verapamil for arrhythmia.
Hypercalcemia due to high doses of vitamin D can reduce the effectiveness of verapamil in atrial fibrillation. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and verapamil concurrently.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
There is some concern that vitamin D might induce CYP3A4. In vitro research suggests that vitamin D induces CYP3A4 transcription. Additionally, observational research has found that increased UV light exposure and serum vitamin D levels are associated with decreased serum levels of CYP3A4 substrates such as tacrolimus and sirolimus, while no association between UV light exposure or vitamin D levels and levels of mycophenolic acid, a non-CYP3A4 substrate, was found. A small, low-quality clinical study shows that taking vitamin D reduces levels of the CYP3A4 substrate atorvastatin and its active metabolites by up to 55%; however, the clinical effects of atorvastatin were not reduced. While researchers theorized that vitamin D might induce CYP3A4, this proposed mechanism was not specifically studied.
Vitamin A
Retinoids
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Retinoids, which are vitamin A derivatives, could have additive toxic effects when taken with vitamin A supplements.
Hepatotoxic Drugs
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
The tolerable upper intake level (UL) is the highest level of intake that is likely to pose no risk of adverse effects. Doses of vitamin A above the UL can cause hepatotoxicity, ranging from elevated liver enzymes to liver failure.
Tetracycline Antibiotics
Theoretically, taking tetracycline antibiotics with high doses of vitamin A can increase the risk of pseudotumor cerebri.
Benign intracranial hypertension (pseudotumor cerebri) can occur with tetracyclines and with acute or chronic vitamin A toxicity. Case reports suggest that taking tetracyclines and vitamin A concurrently can increase the risk of this condition. Avoid high doses of vitamin A in people taking tetracyclines chronically.
Warfarin (Coumadin)
Theoretically, high doses of vitamin A could increase the risk of bleeding with warfarin.
Vitamin A toxicity is associated with hemorrhage and hypoprothrombinemia, possibly due to vitamin K antagonism. Advise patients taking warfarin to avoid doses of vitamin A above the tolerable upper intake level of 10,000 IU/day for adults.
Magnesium Aspartate
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
R-Lipoic Acid
Alkylating Agents
Theoretically, the antioxidant effects of alpha-lipoic acid might alter the effectiveness of alkylating agents.
The use of antioxidants like alpha-lipoic acid during chemotherapy is controversial. There are concerns that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as alpha-lipoic acid have on chemotherapy. Advise patients to consult their oncologist before using alpha-lipoic acid.
Anticoagulant/Antiplatelet Drugs
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro, alpha-lipoic acid inhibits platelet aggregation.
Antitumor Antibiotics
Theoretically, the antioxidant effects of alpha-lipoic acid might alter the effectiveness of antitumor antibiotics.
The use of antioxidants like alpha-lipoic acid during chemotherapy is controversial. There are concerns that antioxidants could reduce the activity of antitumor antibiotic drugs, which work by generating free radicals. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as alpha-lipoic acid have on chemotherapy involving antitumor antibiotics. Advise patients to consult their oncologist before using alpha-lipoic acid.
Thyroid Hormone
Theoretically, alpha-lipoic acid might decrease the effects of thyroid hormone drugs.
Animal research suggests that co-administration of thyroxine with alpha-lipoic acid reduces conversion into the active T3 form.
Antidiabetes Drugs
Theoretically, taking alpha-lipoic acid with antidiabetes drugs might increase the risk of hypoglycemia.
Although some small clinical studies have suggested that alpha-lipoic acid can lower blood glucose levels, larger clinical studies in patients with diabetes have shown no clinically meaningful effect. Additionally, co-administration of single doses of alpha-lipoic acid and glyburide or acarbose did not cause detectable drug interactions in healthy volunteers.
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Acetyl-L-Carnitine
Acenocoumarol (Sintrom)
Theoretically, acetyl-L-carnitine might increase the anticoagulant effects of acenocoumarol.
L-carnitine, the parent compound of acetyl-L-carnitine, might enhance the anticoagulant effects of acenocoumarol, an oral anticoagulant that is similar to warfarin, but shorter-acting. There are at least two case reports of INR elevation when L-carnitine was taken with acenocoumarol. In one case, a 33-year-old male with a previously stable INR had an elevated INR of 4.65 after L-carnitine was started and continued for 10 weeks. INR normalized after discontinuation of the L-carnitine-containing product. It is unclear if such an interaction would also occur with acetyl-L-carnitine.
Serotonergic Drugs
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Animal research shows that acetyl-L-carnitine can increase levels of serotonin in the brain.
Thyroid Hormone
Theoretically, acetyl-L-carnitine might decrease the effectiveness of thyroid hormone replacement.
L-carnitine appears to act as a peripheral thyroid hormone antagonist by inhibiting entry of thyroid hormone into the nucleus of cells. Taking L-carnitine also seems to diminish some of the symptoms of hyperthyroidism. It is unclear if such an interaction would occur with acetyl-L-carnitine.
Warfarin (Coumadin)
Theoretically, acetyl-L-carnitine might increase the anticoagulant effects of warfarin.
L-carnitine, the parent compound of acetyl-L-carnitine, might increase the anticoagulant effects of acenocoumarol, a shorter-acting oral anticoagulant similar to warfarin. There is not enough information to know whether this interaction occurs with acetyl-L-carnitine and warfarin.
Methylcobalamin
Metformin (Glucophage)
Metformin, a common medication used to manage type 2 diabetes, has been associated with lower vitamin B12 levels in some individuals. Prolonged use of metformin can interfere with the absorption of B12 in the digestive system, potentially leading to a deficiency in this essential vitamin.
Brand information
Manufacturer and brand details for Hear Loss Formula, from the product label.
SuperSmart
See all SuperSmart products- Name
- SN Worldwide Unipessoal, LDA
- Street Address
- Avenida Do Infante 66 Edificio Quinta Avenida 1 C
- City
- Funchal
- ZipCode
- 9000-015
Hear Loss Formula by SuperSmart: Common Questions
Does Hear Loss Formula by SuperSmart interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take this if I'm on warfarin or another blood thinner?
Is it safe to take while pregnant or breastfeeding?
What's ginkgo biloba in here for?
Does this actually work for hearing loss?
Will this cause diarrhea or stomach upset?
Can I take this with my diabetes medication?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Hear Loss Formula is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Hear Loss Formula’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographVitamin A
Interacts with 387 drugsVitamin A is an essential nutrient important for vision, skin, immune function, and growth. Most people get enough from a balanced diet, and supplements are mainly useful for correcting a tr...
Read the full Vitamin A monograph → Herb & supplement monographVitamin E
Interacts with 764 drugsVitamin E is an essential fat-soluble vitamin and antioxidant that most people get in adequate amounts from a normal diet. Supplements can help correct a true deficiency, but high-dose vitam...
Read the full Vitamin E monograph → Herb & supplement monographVitamin D
Interacts with 715 drugsVitamin D is a fat-soluble vitamin that helps your body absorb calcium and is important for healthy bones, muscles, and immune function. Many people, especially those with low sun exposure,...
Read the full Vitamin D monograph → Herb & supplement monographQuercetin
Interacts with 1,169 drugsQuercetin is a plant flavonoid with antioxidant and anti-inflammatory properties found in many common foods and sold as a supplement. While early research is interesting for allergies, blood...
Read the full Quercetin monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographAlpha-lipoic Acid
Interacts with 263 drugsAlpha-lipoic acid (ALA) is an antioxidant made naturally by the body and found in small amounts in foods. It is most studied for diabetic nerve pain, where some evidence suggests it may help...
Read the full Alpha-lipoic Acid monograph → Herb & supplement monographAcetyl-l-carnitine
Interacts with 203 drugsAcetyl-L-carnitine is a form of the amino acid carnitine that the body uses to help produce energy in cells. It is most studied for nerve pain and memory-related conditions, though the evide...
Read the full Acetyl-l-carnitine monograph → Herb & supplement monographGinkgo
Interacts with 1,266 drugsGinkgo is one of the world's most popular herbal supplements, mostly taken to support memory and circulation. The evidence for these uses is mixed and generally weak, and it is not proven to...
Read the full Ginkgo monograph → Herb & supplement monographVitamin B12
Interacts with 20 drugsVitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very helpful for people who are deficient — su...
Read the full Vitamin B12 monograph →Sources & How We Checked
Hear Loss Formula's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 477 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Vitamin A 31 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Griffiths JK. The vitamin A paradox. J Pediatr 2000;137:604-7.. PubMed
- Hardman JG, Limbird LL, Molinoff PB, eds. Goodman and Gillman's The Pharmacological Basis of Therapeutics, 9th ed. New York, NY: McGraw-Hill, 1996.
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- FDA Talk Paper. Vitamin A and birth defects (T95-56). Food and Drug Administration, U.S. Department of Health and Human Services, Rockville, MD. October 6, 1995.
- Russell RM. The vitamin A spectrum: from deficiency to toxicity. Am J Clin Nutr 2000;71:878-84. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Feskanich D, Singh V, Willett WC, Colditz GA. Vitamin A intake and hip fractures among postmenopausal women. JAMA 2002;287:47-54. PubMed
- Melhus H, Michaelsson K, Kindmark A, et al. Excessive dietary intake of vitamin A is associated with reduced bone mineral density and increased risk for hip fracture. Ann Intern Med 1998;129:770-8. PubMed
- Michaelsson K, Lithell H, Vessby B, Melhus H. Serum retinol levels and the risk of fracture. N Engl J Med 2003;348:287-94.. PubMed
- Botterweck AA, van den Brandt PA, Goldbohm RA. Vitamins, carotenoids, dietary fiber, and the risk of gastric carcinoma: results from a prospective study after 6.3 years of follow-up. Cancer 2000;88:737-48.. DOI
- Meyskens FL Jr, Graham V, Chvapil M, et al. A phase I trial of beta-all-trans-retinoic acid delivered via a collagen sponge and a cervical cap for mild or moderate intraepithelial cervical neoplasia. J Natl Cancer Inst 1983;71:921-5..
- Hathcock JN, Hattan DG, Jenkins MY, et al. Evaluation of vitamin A toxicity. Am J Clin Nutr 1990;52:183-202.. PubMed
- Walters BN, Gubbay SS. Tetracycline and benign intracranial hypertension: report of five cases. Br Med J 1981;282:19-20.. PubMed
- Pearson MG, Littlewood SM, Bowden AN. Tetracycline and benign intracranial hypertension (letter). Br Med J 1981;282:568-9.. PubMed
- Azais-Braesco V, Pascal G. Vitamin A in pregnancy: requirements and safety limits. Am J Clin Nutr 2000;71:1325S-33S. PubMed
- Smedts HP, de Vries JH, Rakhshandehroo M, et al. High maternal vitamin E intake by diet or supplements is associated with congenital heart defects in the offspring. BJOG 2009;116:416-23. PubMed
- Grotto, I., Mimouni, M., Gdalevich, M., and Mimouni, D. Vitamin A supplementation and childhood morbidity from diarrhea and respiratory infections: a meta-analysis. J Pediatr 2003;142(3):297-304. PubMed
- Mahalanabis, D., Lahiri, M., Paul, D., Gupta, S., Gupta, A., Wahed, M. A., and Khaled, M. A. Randomized, double-blind, placebo-controlled clinical trial of the efficacy of treatment with zinc or vitamin A in infants and young children with severe acute l
- Long, K. Z., Montoya, Y., Hertzmark, E., Santos, J. I., and Rosado, J. L. A double-blind, randomized, clinical trial of the effect of vitamin A and zinc supplementation on diarrheal disease and respiratory tract infections in children in Mexico City, Mex
- Fritz, H., Kennedy, D., Fergusson, D., Fernandes, R., Doucette, S., Cooley, K., Seely, A., Sagar, S., Wong, R., and Seely, D. Vitamin A and retinoid derivatives for lung cancer: a systematic review and meta analysis. PLoS.One. 2011;6(6):e21107. PubMed
- Mayo-Wilson, E., Imdad, A., Herzer, K., Yakoob, M. Y., and Bhutta, Z. A. Vitamin A supplements for preventing mortality, illness, and blindness in children aged under 5: systematic review and meta-analysis. BMJ 2011;343:d5094. PubMed
- Mazumder S, Taneja S, Bhatia K, Yoshida S, Kaur J, Dube B, Toteja GS, Bahl R, Fontaine O, Martines J, Bhandari N; Neovita India Study Group. Efficacy of early neonatal supplementation with vitamin A to reduce mortality in infancy in Haryana, India (Neovit
- Baineni R, Gulati R, Delhi CK. Vitamin A toxicity presenting as bone pain. Arch Dis Child. 2017;102(6):556-8. PubMed
- Darlow BA, Graham PJ, Rojas-Reyes MX. Vitamin A supplementation to prevent mortality and short- and long-term morbidity in very low birth weight infants. Cochrane Database Syst Rev. 2016;(8):CD000501. PubMed
- Haider BA, Sharma R, Bhutta ZA. Neonatal vitamin A supplementation for the prevention of mortality and morbidity in term neonates in low and middle income countries. Cochrane Database Syst Rev. 2017;2:CD006980. PubMed
- Mohammad YM, Raslan IR, Al-Hussain FA. Idiopathic Intracranial Hypertension Induced by Topical Application of Vitamin A. J Neuroophthalmol. 2016;36(4):412-3. PubMed
- Masnadi Shirazi K, Nikniaz Z, Masnadi Shirazi A, Rohani M. Vitamin A supplementation decreases disease activity index in patients with ulcerative colitis: A randomized controlled clinical trial. Complement Ther Med. 2018 Dec;41:215-219. PubMed
- Ding Y, Hu P, Yang Y, et al. Impact of maternal daily oral low-dose vitamin A supplementation on the mother-infant pair: a randomised placebo-controlled trial in China. Nutrients 2021;13(7):2370. PubMed
- Knapik JJ, Hoedebecke SS. Vitamin A and bone fractures: systematic review and meta-analysis. J Spec Oper Med 2021;21(2):100-7. PubMed
- Imdad A, Mayo-Wilson E, Haykal MR, et al. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev 2022;3(3):CD008524. PubMed
Vitamin E 64 references
- Kim JM, White RH. Effect of vitamin E on the anticoagulant response to warfarin. Am J Cardiol 1996;77:545-6. PubMed
- Corrigan JJ Jr. The effect of vitamin E on warfarin-induced vitamin K deficiency. Ann N Y Acad Sci 1982;393:361-8. PubMed
- Corrigan JJ Jr. Coagulation problems relating to vitamin E. Am J Pediatr Hematol Oncol 1979;1:169-73.
- Corrigan JJ Jr, Marcus FI. Coagulopathy associated with vitamin E ingestion. JAMA 1974;230:1300-1. DOI
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Chang T, Benet LZ, Hebert MF. The effect of water-soluble vitamin E on cyclosporine pharmacokinetics in healthy volunteers. Clin Pharmacol Ther 1996;59:297-303. PubMed
- Pan SH, Lopez RR Jr, Sher LS, et al. Enhanced oral cyclosporine absorption with water-soluble vitamin E early after liver transplantation. Pharmacother 1996;16:59-65. DOI
- Anon. Dietary supplementation with n-3 polyunsaturated fatty acids and vitamin E after myocardial infarction: results of the GISSI-Prevenzione trial. Gruppo Italiano per lo Studio della Soprawivenza nell'Infarto miocardico. Lancet 1999;354:447-55. DOI
- Chappell LC, Seed PT, Briley AL, et al. Effect of antioxidants on the occurrence of pre-eclampsia in women at increased risk: a randomised trial. Lancet 1999;354:810-6. DOI
- Yusuf S, Dagenais G, Pogue J, et al. Vitamin E supplementation and cardiovascular events in high-risk patients. The heart outcomes prevention evaluation study investigators. N Engl J Med 2000;342:154-60. PubMed
- Stephens NG, Parsons A, Schofield PM, et al. Randomised controlled trial of vitamin E in patients with coronary disease: Cambridge Heart Antioxidant Study. Lancet 1996;347:781-6.
- The Alpha-Tocopherol, Beta Carotene Cancer Prevention Study Group. The effect of vitamin E and beta carotene on the incidence of lung cancer and other cancers in male smokers. N Engl J Med 1994;330:1029-35. PubMed
- Takahashi O. Haemorrhagic toxicity of a large dose of alpha-, beta-, gamma- and delta-tocopherols, ubiquinone, beta-carotene, retinol acetate and L-ascorbic acid in the rat. Food Chem Toxicol 1995;33:121-8.
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Sano M, Ernesto C, Thomas RG, et al. A controlled trial of selegiline, alpha-tocopherol, or both as treatment for Alzheimer's disease. The Alzheimer's Disease Cooperative Study. N Engl J Med 1997;336:1216-22. PubMed
- Liede KE, Haukka JK, Saxen LM, Heinonen OP. Increased tendency towards gingival bleeding caused by joint effect of alpha-tocopherol supplementation and acetylsalicylic acid. Ann Med 1998;30:542-6.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Liu M, Wallmon A, Olsson-Mortlock C, et al. Mixed tocopherols inhibit platelet aggregation in humans: potential mechanisms. Am J Clin Nutr 2003;77:700-6. PubMed
- Sokol RJ, Johnson KE, Karrer FM, et al. Improvement of cyclosporin absorption in children after liver transplantation by means of water-soluble vitamin E. Lancet 1991;338:212-4.. PubMed
- Stein JH, Carlsson CM, Papcke-Benson K, et al. The effects of lipid-lowering and antioxidant vitamin therapies on flow-mediated vasodilation of the brachial artery in older adults with hypercholesterolemia. J Am Coll Cardiol 2001;38:1806-13.. PubMed
- Carlsson CM, Papcke-Benson K, Carnes M, et al. Health-related quality of life and long-term therapy with pravastatin and tocopherol (vitamin E) in older adults. Drugs Aging 2002;19:793-805. . PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Schrogie JJ. Coagulopathy and fat-soluble vitamins (letter). JAMA 1975;232:19. DOI
- Celestini A, Pulcinelli FM, Pignatelli P, et al. Vitamin E potentiates the antiplatelet activity of aspirin in collagen-stimulated platelets. Haematologica 2002;87:420-6.
- Stampfer MJ, Jakubowski JA, Faigel D, et al. Vitamin E supplementation effect on human platelet function, arachidonic acid metabolism, and plasma prostacyclin levels. Am J Clin Nutr 1988;47:700-6. PubMed
- Jandak J, Steiner M, Richardson PD. Alpha-tocopherol, an effective inhibitor of platelet adhesion. Blood 1989;73:141-9. DOI
- Freedman JE, Farhat JH, Loscalzo J, Keaney JF. Alpha-tocopherol inhibits aggregation of human platelets by a protein kinase C-dependent mechanism. Circulation 1996;94:2434-40. PubMed
- Steiner M. Vitamin E, a modifier of platelet function: rationale and use in cardiovascular and cerebrovascular disease. Nutr Rev 1999;57:306-9. PubMed
- Brodkin RH, Bleiberg J. Sensitivity to topically applied vitamin E. Arch Dermatol 1965;92:76-7. DOI
- Booth SL, Golly I, Sacheck JM, et al. Effect of vitamin E supplementation on vitamin K status in adults with normal coagulation status. Am J Clin Nutr 2004;80:143-8. PubMed
- Miller ER 3rd, Pastor-Barriuso R, Dalal D, et al. Meta-analysis: High-dosage vitamin E supplementation may increase all-cause mortality. Ann Intern Med 2005;142:60520-53. PubMed
- Lonn E, Bosch J, Yusuf S, et al. HOPE and HOPE-TOO Trial Investigators. Effects of long-term vitamin E supplementation on cardiovascular events and cancer: a randomized controlled trial. JAMA 2005;293:1338-47. PubMed
- Landes N, Pfluger P, Kluth D, et al. Vitamin E activates gene expression via the pregnane X receptor. Biochem Pharmacol 2003;65:269-73. . PubMed
- Brigelius-Flohe R. Vitamin E and drug metabolism. Biochem Biophys Res Commun 2003;305:737-40. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Schurks M, Glynn RJ, Rist PM, et al. Effects of vitamin E on stroke subtypes: meta-analysis of randomized controlled trials. BMJ 2010;341: c5702. doi: 10.1136/bmj.c5702.
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Gaziano JM, Glynn RJ, Christen WG, et al. Vitamins E and C in the prevention of prostate total cancer in men: the physicians' health study II randomised controlled trial. JAMA 2009;301:52-62.
- Hayden KM, Welsh-Bohmer KA, Wengreen HJ, et al; Cache County Investigators. Risk of mortality with vitamin E supplements: the Cache County study. Am L Med 2007;120:180-4. PubMed
- Smedts HP, de Vries JH, Rakhshandehroo M, et al. High maternal vitamin E intake by diet or supplements is associated with congenital heart defects in the offspring. BJOG 2009;116:416-23. PubMed
- Klein EA, Thompson IM Jr, Tangen CM, et al. Vitamin E and the risk of prostate cancer: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA 2011;306:1549-56. PubMed
- Huang, H. Y., Caballero, B., Chang, S., Alberg, A. J., Semba, R. D., Schneyer, C. R., Wilson, R. F., Cheng, T. Y., Vassy, J., Prokopowicz, G., Barnes, G. J., and Bass, E. B. The efficacy and safety of multivitamin and mineral supplement use to prevent ca
- Sesso, H. D., Buring, J. E., Christen, W. G., Kurth, T., Belanger, C., MacFadyen, J., Bubes, V., Manson, J. E., Glynn, R. J., and Gaziano, J. M. Vitamins E and C in the prevention of cardiovascular disease in men: the Physicians' Health Study II randomiz
- Papaioannou, D., Cooper, K. L., Carroll, C., Hind, D., Squires, H., Tappenden, P., and Logan, R. F. Antioxidants in the chemoprevention of colorectal cancer and colorectal adenomas in the general population: a systematic review and meta-analysis. Colorec PubMed
- Cooper, K., Squires, H., Carroll, C., Papaioannou, D., Booth, A., Logan, R. F., Maguire, C., Hind, D., and Tappenden, P. Chemoprevention of colorectal cancer: systematic review and economic evaluation. Health Technol.Assess. 2010;14(32):1-206. PubMed
- Mathew, M. C., Ervin, A. M., Tao, J., and Davis, R. M. Antioxidant vitamin supplementation for preventing and slowing the progression of age-related cataract. Cochrane.Database.Syst.Rev. 2012;6:CD004567. PubMed
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Soares, K. V. and McGrath, J. J. Vitamin E for neuroleptic-induced tardive dyskinesia. Cochrane.Database.Syst.Rev. 2001;(4):CD000209. DOI
- Roed-Petersen, J. and Hjorth, N. Contact dermatitis from antioxidants. Br.J.Dermatol. 1976;94(3):233-241. PubMed
- Brion, L. P., Bell, E. F., Raghuveer, T. S., and Soghier, L. What is the appropriate intravenous dose of vitamin E for very-low-birth-weight infants? J.Perinatol. 2004;24(4):205-207. PubMed
- Manny, T., Pettus, J., Hemal, A., Marks, M., and Mirzazadeh, M. Penile sclerosing lipogranulomas and disfigurement from use of "1Super Extenze" among Laotian immigrants. J.Sex Med. 2011;8(12):3505-3510. PubMed
- Musso, G., Cassader, M., Rosina, F., and Gambino, R. Impact of current treatments on liver disease, glucose metabolism and cardiovascular risk in non-alcoholic fatty liver disease (NAFLD): a systematic review and meta-analysis of randomised trials. Diabe PubMed
- Bell, E. F. Upper limit of vitamin E in infant formulas. J.Nutr. 1989;119(12 Suppl):1829-1831. PubMed
- Manzano, D., Aguirre, A., Gardeazabal, J., Eizaguirre, X., and Diaz Perez, J. L. Allergic contact dermatitis from tocopheryl acetate (vitamin E) and retinol palmitate (vitamin A) in a moisturizing cream. Contact Dermatitis 1994;31(5):324.
- Barak, Y., Swartz, M., Shamir, E., Stein, D., and Weizman, A. Vitamin E (alpha-tocopherol) in the treatment of tardive dyskinesia: a statistical meta-analysis. Ann.Clin.Psychiatry 1998;10(3):101-105.
- Chae CU, Albert CM, Moorthy MV, et al. Vitamin E supplementation and the risk of heart failure in women. Circ Heart Fail. 2012;5(2):176-82. PubMed
- Rumbold A, Ota E, Hori H, Miyazaki C, Crowther CA. Vitamin E supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004069. PubMed
- Prescribing information: KOSELUGO (selumetinib) capsules. U.S. Food and Drug Administration. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2020/213756s000lbl.pdf.
- Warshaw EM, Ruggiero JL, DeKoven JG, et al. Patch testing with tocopherol and tocopherol acetate: the North American Contact Dermatitis Group experience, 2001 to 2016. Dermatitis. 2021;32(5):308-18. PubMed
- US Preventive Services Task Force, Mangione CM, Barry MJ, et al. Vitamin, Mineral, and Multivitamin Supplementation to Prevent Cardiovascular Disease and Cancer: US Preventive Services Task Force Recommendation Statement. JAMA 2022;327(23):2326-2333. PubMed
- Abrol R, Kaushik R, Goel D, Sama S, Kaushik RM, Kala M. Vitamin E-induced coagulopathy in a young patient: a case report. J Med Case Rep 2023;17(1):107. PubMed
- Abtahi-Naeini B, Rastegarnasab F, Saffaei A. Liquid vitamin E injection for cosmetic facial rejuvenation: A disaster report of lipogranuloma. J Cosmet Dermatol 2022;21(11):5549-5554. PubMed
Vitamin D 26 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Tatro DS, ed. Drug Interactions Facts. Facts and Comparisons Inc., St. Louis, MO. 1999.
- Koutkia P, Chen TC, Holick MF. Vitamin D intoxication associated with an over-the-counter supplement. N Engl J Med 2001;345:66-7. PubMed
- Bar-Or D, Yoel G. Calcium and calciferol antagonize effect of verapamil in atrial fibrillation. Br Med J 1981;282:1585-6.
- Demontis R, Leflon A, Fournier A, et al. 1 alpha(OH) vitamin D3 increases plasma aluminum in hemodialyzed patients taking AI(OH)3. Clin Nephrol 1986;26:146-9.
- Crowe M, Wollner L, Griffiths RA. Hypercalcemia following vitamin D and thiazide therapy in the elderly. Practitioner 1984;228:312-3.
- Parfitt AM. Thiazide-induced hypercalcemia in vitamin D-treated hypoparathyroidism. Ann Intern Med 1972;77:557-63. PubMed
- Thiazide diuretics and the risk of osteoporosis. Pharmacist's Letter/Prescriber's Letter 2003;19(11):191105.
- Moon J. The role of vitamin D in toxic metal absorption. J Am Coll Nutr 1994;13:559-64.
- Demontis R, Reissi D, Noel C, et al. Indirect clinical evidence that 1alphaOH vitamin D<SUB>3</SUB> increases the intestinal absorption of aluminum. Clin Nephrol 1989;31:123-7.
- Adler AJ, Berlyne GM. Duodenal aluminum absorption in the rat: effect of vitamin D. Am J Physiol 1985;249:G209-13. PubMed
- Schwartz JB. Effects of vitamin D supplementation in atorvastatin-treated patients: A new drug interaction with an unexpected consequence. Clin Pharmacol Ther 2009;85:198-203. PubMed
- Dietary reference intakes for calcium and vitamin D. Institute of Medicine, November 30, 2010. Available at: http://www.iom.edu/~/media/Files/Report%20Files/2010/Dietary-Reference-Intakes-for-Calcium-and-Vitamin-D/Vitamin%20D%20and%20Calcium%202010%20Repo
- Cox KA, Dunn MA. Aluminum toxicity alters the regulation of calbindin-D28k protein and mRNA expression in chick intestine. J Nutr 2001;131:2007-13. PubMed
- Escribano, J., Balaguer, A., Pagone, F., Feliu, A., and Roque, I. Figuls. Pharmacological interventions for preventing complications in idiopathic hypercalciuria. Cochrane.Database.Syst.Rev. 2009;(1):CD004754. PubMed
- Carlton, S., Clopton, D., and Cappuzzo, K. A. Vitamin D deficiency: appropriate replenishment therapies and the effects of vitamin D toxicity. Consult Pharm 2010;25(3):171-177. PubMed
- Wang, H., Xia, N., Yang, Y., and Peng, D. Q. Influence of vitamin D supplementation on plasma lipid profiles: a meta-analysis of randomized controlled trials. Lipids Health Dis. 2012;11:42. PubMed
- Turner AN, Carr Reese P, Fields KS, Anderson J, Ervin M, Davis JA, Fichorova RN, Roberts MW, Klebanoff MA, Jackson RD. A blinded, randomized controlled trial of high-dose vitamin D supplementation to reduce recurrence of bacterial vaginosis. Am J Obstet G PubMed
- Weiner M, Epstein FH. Signs and symptoms of electrolyte disorders. Yale J Biol Med. 1970;43(2):76-109.
- Lappe J, Watson P, Travers-Gustafson D, Recker R, Garland C, Gorham E, Baggerly K, McDonnell SL. Effect of Vitamin D and Calcium Supplementation on Cancer Incidence in Older Women: A Randomized Clinical Trial. JAMA. 2017 Mar 28;317(12):1234-1243. PubMed
- Roth DE, Leung M, Mesfin E, Qamar H, Watterworth J, Papp E. Vitamin D supplementation during pregnancy: state of the evidence from a systematic review of randomised trials. BMJ. 2017;359:j5237. PubMed
- Murai IH, Fernandes AL, Sales LP, et al. Effect of a single high dose of vitamin D3 on hospital length of stay in patients with moderate to severe COVID-19: A randomized clinical trial. JAMA. 2021.
- Wang Z, Schuetz EG, Xu Y, Thummel KE. Interplay between vitamin D and the drug metabolizing enzyme CYP3A4. J Steroid Biochem Mol Biol 2013;136:54-8. PubMed
- Doyle D, Browne U, Brickley A, Murphy D. Vitamin D-induced hypercalcaemia and acute kidney injury in sarcoidosis. BMJ Case Rep 2023;16(1):e250580. PubMed
- Williamson A, Martineau AR, Sheikh A, Jolliffe D, Griffiths CJ. Vitamin D for the management of asthma. Cochrane Database Syst Rev 2023;2(2):CD011511. PubMed
- Kinesya E, Santoso D, Gde Arya N, et al. Vitamin D as adjuvant therapy for diabetic foot ulcers: Systematic review and meta-analysis approach. Clin Nutr ESPEN 2023;54:137-143. PubMed
Quercetin 26 references
- Shoskes DA, Zeitlin SI, Shahed A, Rajfer J. Quercetin in men with category III chronic prostatitis: A preliminary prospective, double-blind, placebo-controlled trial. Urol 1999;54:960-3. PubMed
- Starvic B. Quercetin in our diet: from potent mutagen to probable anticarcinogen. Clin Biochem 1994;27:245-8. PubMed
- Ferry DR, Smith A, Malkhandi J, et al. Phase I clinical trial of the flavonoid quercetin: Pharmacokinetics and evidence for in vivo tyrosine kinase inhibition. Clin Cancer Res 1996;2:659-67..
- Obach RS. Inhibition of human cytochrome P450 enzymes by constituents of St. John's wort, an herbal preparation used in the treatment of depression. J Pharmacol Exp Ther 2000;294:88-95. DOI
- Edwards RL, Lyon T, Litwin SE, et al. Quercetin reduces blood pressure in hypertensive subjects. J Nutr 2007;137:2405-11.
- Kim KA, Park PW, Kim HK, et al. Effect of quercetin on the pharmacokinetics of rosiglitazone, a CYP2C8 substrate, in healthy subjects. J Clin Pharmacol 2005;45:941-6. PubMed
- DiCenzo R, Frerichs V, Larppanichpoonphol P, et al. Effect of quercetin on the plasma and intracellular concentrations of saquinavir in healthy adults. Pharmacotherapy 2006;26:1255-61. PubMed
- Choi JS, Choi BC, Choi KE. Effect of quercetin on the pharmacokinetics of oral cyclosporine. Am J Health Syst Pharm 2004;61:2406-9. PubMed
- Choi JS, Jo BW, Kim YC. Enhanced paclitaxel bioavailability after oral administration of paclitaxel or prodrug to rats pretreated with quercetin. Eur J Pharm Biopharm 2004;57:313-8. PubMed
- Vaclavikova R, Horsky S, Simek P, Gut I. Paclitaxel metabolism in rat and human liver microsomes is inhibited by phenolic antioxidants. Naunyn Schmiedebergs Arch Pharmacol 2003;368:200-9. PubMed
- Di Bari L, Ripoli S, Pradhan S, Salvadori P. Interactions between quercetin and warfarin for albumin binding: A new eye on food/drug interference. Chirality 2010;22:593-6. PubMed
- Lamson, D. W. and Brignall, M. S. Antioxidants and cancer, part 3: quercetin. Altern.Med.Rev. 2000;5(3):196-208.
- Duan KM, Wang SY, Ouyang W, Mao YM, Yang LJ. Effect of quercetin on CYP3A activity in Chinese healthy participants. J Clin Pharmacol 2012;52(6):940-6. PubMed
- Wang SY, Duan KM, Li Y, et al. Effect of quercetin on P-glycoprotein transport ability in Chinese healthy subjects. Eur J Clin Nutr 2013;67(4):390-4. PubMed
- Nguyen MA, Staubach P, Wolffram S, Langguth P. Effect of single-dose and short-term administration of quercetin on the pharmacokinetics of talinolol in humans - Implications for the evaluation of transporter-mediated flavonoid-drug interactions. Eur J Pha PubMed
- Wu LX, Guo CX, Chen WQ, et al. Inhibition of the organic anion-transporting polypeptide 1B1 by quercetin: an in vitro and in vivo assessment. Br J Clin Pharmacol 2012;73(5):750-7.
- Ahrens MJ, Thompson DL. Effect of emulin on blood glucose in type 2 diabetics. J Med Food. 2013;16(3):211-5. PubMed
- Larson A, Witman MA, Guo Y, et al. Acute, quercetin-induced reductions in blood pressure in hypertensive individuals are not secondary to lower plasma angiotensin-converting enzyme activity or endothelin-1: nitric oxide. Nutr Res. 2012;32(8):557-64. PubMed
- Bedada SK, Neerati P. Evaluation of the effect of quercetin treatment on CYP2C9 enzyme activity of diclofenac in healthy human volunteers. Phytother Res. 2018 Feb;32(2):305-311. doi: 10.1002/ptr.5978. PubMed
- Zhao Q, Wei J, Zhang H. Effects of quercetin on the pharmacokinetics of losartan and its metabolite EXP3174 in rats. Xenobiotica 2019;49(5):563-8. PubMed
- Bhutani P, Rajanna PK, Paul AT. Impact of quercetin on pharmacokinetics of quetiapine: insights from in-vivo studies in wistar rats. Xenobiotica. 2020:1-7.
- Li C, Wang X, Bi Y, et al. Potent Inhibitors of Organic Anion Transporters 1 and 3 From Natural Compounds and Their Protective Effect on Aristolochic Acid Nephropathy. Toxicol Sci. 2020;175(2):279-291. PubMed
- Ni Y, Duan Z, Zhou D, et al. Identification of Structural Features for the Inhibition of OAT3-Mediated Uptake of Enalaprilat by Selected Drugs and Flavonoids. Front Pharmacol. 2020;11:802. PubMed
- Song YK, Yoon JH, Woo JK, et al. Quercetin is a flavonoid breast cancer resistance protein inhibitor with an impact on the oral pharmacokinetics of sulfasalazine in rats. Pharmaceutics 2020;12(5):397. PubMed
- Ahmad E, Jahangir M, Ismail MA, et al. Influence of quercetin pretreatment on pharmacokinetics of warfarin in rats. Curr Drug Saf 2022. PubMed
- Nambiar A, Kellogg D 3rd, Justice J, et al. Senolytics dasatinib and quercetin in idiopathic pulmonary fibrosis: results of a phase I, single-blind, single-center, randomized, placebo-controlled pilot trial on feasibility and tolerability. EBioMedicine 20 PubMed
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Alpha-lipoic Acid 48 references
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Anon. Alpha-lipoic acid. Altern Med Rev 1998;3:308-10.
- Konrad T, Vicini P, Kusterer K, et al. Alpha-lipoic acid treatment decreases serum lactate and pyruvate concentrations and improves glucose effectiveness in lean and obese patients with Type 2 diabetes. Diabetes Care 1999;22:280-7. PubMed
- Ziegler D, Hanefeld M, Ruhnau KJ, et al. Treatment of symptomatic diabetic peripheral neuropathy with the antioxidant alpha-lipoic acid: A 3-week, multicentre randomized controlled trial (ALADIN Study). Diabetologia 1995;38:1425-33.
- Gleiter CH, Schreeb KH, Freudenthaler S, et al. Lack of interaction between thioctic acid, glibenclamide and acarbose. Br J Clin Pharmacol 1999;48:819-25. PubMed
- Jacob S, Henriksen EJ, Tritschler HJ, et al. Improvement of insulin-stimulated glucose-disposal in type 2 diabetes after repeated parenteral administration of thioctic acid. Exp Clin Endocrinol Diabet 1996;104:284-8. PubMed
- Jacob S, Henriksen EJ, Schiemann AL, et al. Enhancement of glucose disposal in patients with type 2 diabetes by alpha-lipoic acid. Arzneimittelforschung 1995;45:872-4.
- Jacob S, Ruus P, Hermann R, et al. Oral administration of RAC-alpha-lipoic acid modulates insulin sensitivity in patients with type-2 diabetes mellitus: a placebo-controlled, pilot trial. Free Rad Biol Med 1999;27:309-14.
- Segermann J, Hotze A, Ulrich H, Rao GS. Effect of alpha-lipoic acid on the peripheral conversion of thyroxine to triiodothyronine and on serum lipid-, protein- and glucose levels. Arzneimittelforschung 1991;41:1294-8.
- Beitner H. Randomized, placebo controlled, double-blind study on the clinical efficacy of a cream containing 5% alpha-lipoic acid related to photoaging of facial skin. Br J Dermatol 2003;149:841-9.
- Ziegler D, Nowak H, Kempler P, et al. Treatment of symptomatic diabetic polyneuropathy with the antioxidant alpha-lipoic acid: A meta-analysis. Diabet Med 2004;21:114-21.
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Vincent HK, Bourguignon CM, Vincent KR, Taylor AG. Effects of alpha-lipoic acid supplementation in peripheral arterial disease: a pilot study. J Alt Complement Med 2007;13:577-84. PubMed
- Furukawa N, Miyamura N, Nishida K, et al. Possible relevance of alpha lipoic acid contained in a health supplement in a case of insulin autoimmune syndrome. Diabetes Res Clin Pract 2007;75:366-7. PubMed
- Ziegler D., Ametov A., Barinov A., Dyck P. J., Gurieva I., Low P. A., Munzel U., Yakhno N., Raz I., Novosadova M., Maus J., Samigullin, R. Oral treatment with alpha-lipoic acid improves symptomatic diabetic polyneuropathy: the SYDNEY 2 trial. Diabetes Car
- Gu X. M., Zhang S. S., Wu J. C., Tang Z. Y., Lu Z. Q., Li H., Liu C., Chen L., Ning, G. [Efficacy and safety of high-dose a-lipoic acid in the treatment of diabetic polyneuropathy]. Zhonghua Yi Xue Za Zhi 2010;90(35):2473-2476.
- Porasuphatana S., Suddee S., Nartnampong A., Konsil J., Harnwong B., Santaweesuk A. Glycemic and oxidative status of patients with type 2 diabetes mellitus following oral administration of alpha-lipoic acid: a randomized double-blinded placebo-controlled
- Ansar H., Mazloom Z., Kazemi F., Hejazi N. Effect of alpha-lipoic acid on blood glucose, insulin resistance and glutathione peroxidase of type 2 diabetic patients. Saudi Med J 2011;32(6):584-588. DOI
- de Oliveira A. M., Rondó P. H., Luzia L. A., D'Abronzo F. H., Illison V. K. The effects of lipoic acid and a-tocopherol supplementation on the lipid profile and insulin sensitivity of patients with type 2 diabetes mellitus: a randomized, double-blind, pla
- Mazloom Z., Ansar H. The Effect of Alpha-Lipoic Acid on Blood Pressure in Type 2 Diabetics. Iranian Journal of Endocrinology and Metabolism 2009;11(3):245-250.
- Volchegorskii I. A., Rassokhina L. M., Koliadich M. I., Alekseev M. I. [Comparative study of alpha-lipoic acid and mexidol effects on affective status, cognitive functions and quality of life in diabetes mellitus patients]. Eksp Klin Farmakol 2011;74(11):
- Cavalcanti D. R., da Silveira F. R. Alpha lipoic acid in burning mouth syndrome--a randomized double-blind placebo-controlled trial. J Oral Pathol Med 2009;38(3):254-261. PubMed
- Koh E. H., Lee W. J., Lee S. A., Kim E. H., Cho E. H., Jeong E., Kim D. W., Kim M. S., Park J. Y., Park K. G., Lee H. J., Lee I. K., Lim S., Jang H. C., Lee K. H., Lee K. U. Effects of alpha-lipoic Acid on body weight in obese subjects. Am J Med 2011;124( PubMed
- Bergqvist-Karlsson, A., Thelin, I., and Bergendorff, O. Contact dermatitis to alpha-lipoic acid in an anti-wrinkle cream. Contact Dermatitis 2006;55(1):56-57.
- Tang, J., Wingerchuk, D. M., Crum, B. A., Rubin, D. I., and Demaerschalk, B. M. Alpha-lipoic acid may improve symptomatic diabetic polyneuropathy. Neurologist. 2007;13(3):164-167. PubMed
- Hegazy SK, Tolba OA, Mostafa TM, Eid MA, El-Afify DR. Alpha-lipoic acid improves subclinical left ventricular dysfunction in asymptomatic patients with type 1 diabetes. Rev Diabet Stud 2013;10(1):58-67. PubMed
- Huang Z, Wan X, Liu J, et al. Short-term continuous subcutaneous insulin infusion combined with insulin sensitizers rosiglitazone, metformin, or antioxidant a-lipoic acid in patients with newly diagnosed type 2 diabetes mellitus. Diabetes Technol Ther 201
- Sarezky D, Raquib AR, Dunaief JL, Kim BJ. Tolerability in the elderly population of high-dose alpha lipoic acid: a potential antioxidant therapy for the eye. Clin Ophthalmol. 2016 Sep 29;10:1899-1903. PubMed
- Boriani F, Granchi D, Roatti G, Merlini L, Sabattini T, Baldini N. Alpha-lipoic acid after median nerve decompression at the carpal tunnel: a randomized controlled trial. J Hand Surg Am. 2017 Apr;42(4):236-42. PubMed
- Karkabounas S, Papadopoulos N, Anastasiadou C, et al. Effects of a-lipoic Acid, carnosine, and thiamine supplementation in obese patients with type 2 diabetes mellitus: A randomized, double-blind study. J Med Food. 2018;21(12):1197-1203.
- Murray GL, Colombo J. (r)Alpha lipoic acid is a safe, effective pharmacologic therapy of chronic orthostatic hypotension associated with low sympathetic tone. Int J Angiol. 2019;28(3):188-193. PubMed
- Bobe G, Michels AJ, Zhang WJ, et al. A randomized controlled trial of long-term (R)-α-lipoic acid supplementation promotes weight loss in overweight or obese adults without altering baseline elevated plasma triglyceride concentrations. J Nutr. 2020:
- Passiatore M, Perna A, De-Vitis R, Taccardo G. The use of alfa-lipoic acid-R (ALA-R) in patients with mild-moderate carpal tunnel syndrome: A randomised controlled open label prospective study. Malays Orthop J. 2020;14(1):1-6. PubMed
- El-Nahas MR, Elkannishy G, Abdelhafez H, Elkhamisy ET, El-Sehrawy AA. Oral alpha lipoic acid treatment for symptomatic diabetic peripheral neuropathy: A randomized double-blinded placebo-controlled study. Endocr Metab Immune Disord Drug Targets. 2020. PubMed
- Kim BJ, Hunter A, Brucker AJ, et al. Orally administered alpha lipoic acid as a treatment for geographic atrophy: A randomized clinical trial. Ophthalmol Retina. 2020;4(9):889-898. PubMed
- Derosa G, D'Angelo A, Preti P, Maffioli P. Safety and efficacy of alpha lipoic acid during 4 years of observation: A retrospective, clinical trial in healthy subjects in primary prevention. Drug Des Devel Ther. 2020;14:5367-5374.
- Sun Y, Guan X, Wang H, et al. Randomized clinical trial of combined therapy with oral a-lipoic acid and NB-UVB for nonsegmental stable vitiligo. Dermatol Ther. 2021;34(1):e14610.
- Gilron I, Robb S, Tu D, et al. Double-blind, randomized, placebo-controlled crossover trial of alpha-lipoic acid for the treatment of fibromyalgia pain: the IMPALA trial. Pain. 2021;162(2):561-568. PubMed
- Gullo D, Evans JL, Sortino G, Goldfine ID, Vigneri R. Insulin autoimmune syndrome (Hirata Disease) in European Caucasians taking a-lipoic acid. Clin Endocrinol (Oxf). 2014;81(2):204-9.
- Yukina M, Nuralieva N, Solovyev M, Troshina E, Vasilyev E. Insulin autoimmune syndrome. Endocrinol Diabetes Metab Case Rep. 2020;2020:19-0159. PubMed
- Moffa S, Improta I, Rocchetti S, Mezza T, Giaccari A. Potential cause-effect relationship between insulin autoimmune syndrome and alpha lipoic acid: Two case reports. Nutrition. 2019;57:1-4. PubMed
- Izzo V, Greco C, Corradini D, et al. Insulin autoimmune syndrome in an Argentine woman taking a-lipoic acid: A case report and review of the literature. SAGE Open Med Case Rep. 2018;6:2050313X18819601.
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA), Turck D, et al. Scientific opinion on the relationship between intake of alpha-lipoic acid (thioctic acid) and the risk of insulin autoimmune syndrome. EFSA J 2021;19(6):e06577. PubMed
- Jibril AT, Jayedi A, Shab-Bidar S. Efficacy and safety of oral alpha-lipoic acid supplementation for type 2 diabetes management: a systematic review and dose-response meta-analysis of randomized trials. Endocr Connect 2022;11(10):e220322. PubMed
- Corazza M, Arlotti E, Schettini N, Pacetti L, Bianchi A, Borghi A. Allergic contact dermatitis due to a-lipoic acid in a topical over-the-counter product: A case report. Contact Dermatitis 2023.
- Velasco-Amador JP, Prados-Carmona Á, Navarro-Triviño FJ. Contact urticaria syndrome caused by alpha-lipoic acid in a master formula for vulvar lichen sclerosus. Contact Dermatitis 2023;89(2):136-137. PubMed
- Sehgal T, Ohri U, Mittal N, Attri P, Dishant F. A Case of Insulin Autoimmune Syndrome in an Indian Male Taking Alpha-Lipoic Acid. Cureus 2023;15(8):e43743. PubMed
Acetyl-l-carnitine 22 references
- Thal LJ, Carta A, Clarke WR, et al. A 1-year multicenter placebo-controlled study of acetyl-L-carnitine in patients with Alzheimer's Disease. Neurology 1996;47:705-11. PubMed
- Sano M, Bell K, Cote L, et al. Double-blind parallel design pilot study of acetyl levocarnitine in patients with Alzheimer's Disease. Arch Neurol 1992;49:1137-41. PubMed
- Spagnoli A, Lucca U, Menasce G, et al. Long-term acetyl-L-carnitine treatment in Alzheimer's Disease. Neurology 1991;41:1726-32. PubMed
- Brooks JO 3rd, Yesavage JA, Carta A, Bravi D. Acetyl L-carnitine slows decline in younger patients with Alzheimer's disease: a reanalysis of a double-blind, placebo-controlled study using the trilinear approach. Int Psychoger 1998;10:193-203. PubMed
- Pettegrew JW, Klunk WE, Panchalingam K, et al. Clinical and neurochemical effects of acetyl-L-carnitine in Alzheimer's disease. Neurobiol Aging 1995;16:1-4. PubMed
- Rai G, Wright G, Scott L, et al. Double-blind, placebo controlled study of acetyl-l-carnitine in patients with Alzheimer's dementia. Curr Med Res Opin 1990;11:638-47. PubMed
- Benvenga S, Ruggeri RM, Russo A, et al. Usefulness of L-carnitine, a naturally occurring peripheral antagonist of thyroid hormone action, in iatrogenic hyperthyroidism: a randomized, double-blind, placebo-controlled clinical trial. J Clin Endocrinol Meta
- Montgomery SA, Thal LJ, Amrein R. Meta-analysis of double blind randomized controlled clinical trials of acetyl-L-carnitine versus placebo in the treatment of mild cognitive impairment and mild Alzheimer's disease. Int Clin Psychopharmacol 2003;18:61-71.. PubMed
- Martinez E, Domingo P, Roca-Cusachs A. Potentiation of acenocoumarol action by L-carnitine. J Intern Med 1993;233:94.
- Hudson S, Tabet N. Acetyl-L-carnitine for dementia. Cochrane Database Syst Rev 2003;2:CD003158.. PubMed
- Bachmann HU, Hoffmann A. Interaction of food supplement L-carnitine with oral anticoagulant acenocoumarol. Swiss Med Wkly 2004;134:385. PubMed
- De Grandis D, Minardi C. Acetyl-L-carnitine (levacecarnine) in the treatment of diabetic neuropathy. A long-term, randomised, double-blind, placebo-controlled study. Drugs R D 2002;3:223-31. PubMed
- 12761 Benvenga S, Amato A, Calvani M, Trimarchi F. Effects of carnitine on thyroid hormone action. Ann N Y Acad Sci 2004;1033:158-67. PubMed
- Sima AAF, Calvani M, Mehra M, et al. Acetyl-L-carnitine improves pain, nerve regeneration, and vibratory perception in patients with chronic diabetic neuropathy: An analysis of two randomized, placebo-controlled trials. Diabetes Care 2005;28:89-94.
- Youle, M. and Osio, M. A double-blind, parallel-group, placebo-controlled, multicentre study of acetyl L-carnitine in the symptomatic treatment of antiretroviral toxic neuropathy in patients with HIV-1 infection. HIV.Med. 2007;8(4):241-250.
- Brennan BP, Jensen JE, Hudson JI, Coit CE, Beaulieu A, Pope HG Jr, Renshaw PF, Cohen BM. A placebo-controlled trial of acetyl-L-carnitine and a-lipoic acid in the treatment of bipolar depression. J Clin Psychopharmacol. 2013 Oct;33(5):627-35.
- Ledinek AH, Sajko MC, Rot U. Evaluating the effects of amantadin, modafinil and acetyl-L-carnitine on fatigue in multiple sclerosis--result of a pilot randomized, blind study. Clin Neurol Neurosurg. 2013 Dec;115 Suppl 1:S86-9. PubMed
- Martinotti G, Andreoli S, Reina D, Di Nicola M, Ortolani I, Tedeschi D, Fanella F, Pozzi G, Iannoni E, D'Iddio S, Prof LJ. Acetyl-l-Carnitine in the treatment of anhedonia, melancholic and negative symptoms in alcohol dependent subjects. Prog Neuropsychop PubMed
- Baek SM, Zheng R, Seo EJ, Hwang DY, Kim BH. Pharmacokinetic comparisons of two acetyl-L-carnitine formulations in healthy Korean volunteers. Int J Clin Pharmacol Ther. 2015;53(11):980-6. PubMed
- Goodison G, Overeem K, de Monte V, Siskind D. Mania associated with self-prescribed acetyl-l-carnitine in a man with bipolar I disorder. Australas Psychiatry. 2017;25(1):13-4.
- Bruno A, Pandolfo G, Crucitti M, Lorusso S, Zoccali RA, Muscatello MR. Acetyl-L-Carnitine Augmentation of Clozapine in Partial-Responder Schizophrenia: A 12-Week, Open-Label Uncontrolled Preliminary Study. Clin Neuropharmacol. 2016;39(6):277-80. PubMed
- Veronese N, Stubbs B, Solmi M, Ajnakina O, Carvalho AF, Maggi S. Acetyl-L-Carnitine Supplementation and the Treatment of Depressive Symptoms: A Systematic Review and Meta-Analysis. Psychosom Med. 2018;80(2):154-9. PubMed
Ginkgo 97 references
- Davydov L, Stirling AL. Stevens-Johnson syndrome with Ginkgo biloba. J Herb Pharmacother 2001;1:65-9. DOI
- Benjamin J, Muir T, Briggs K, Pentland B. A case of cerebral haemorrhage-can Ginkgo biloba be implicated? Postgrad Med J 2001;77:112-3.
- Matthews, MK. Association of Ginkgo biloba with intracerebral hemorrhage. Neurology 1998;50:1934.
- Rowin J, Lewis SL. Spontaneous bilateral subdural hemotomas with chronic Ginkgo biloba ingestion. Neurology 1996;46:1775-6.
- Rosenblatt M, Mindel T. Spontaneous hyphema associated with ingestion of Ginkgo biloba extract. N Engl J Med 1997;336:1108.
- Fessenden JM, Wittenborn W, Clarke L. Gingko biloba: a case report of herbal medicine and bleeding postoperatively from a laparoscopic cholecystectomy. Am Surg 2001;67:33-5. DOI
- Gurley BJ, Gardner SF, Hubbard MA. Clinical assessment of potential cytochrome P450-mediated herb-drug interactions. AAPS Ann Mtg & Expo Indianapolis, IN: 2000; Oct 29 - Nov 2:presentation #3460.
- Cohen AJ, Bartlik B. Ginkgo biloba for antidepressant-induced sexual dysfunction. J Sex Marital Ther 1998;24:139-43. PubMed
- Kudolo GB. The effect of 3-month ingestion of Ginkgo biloba extract on pancreatic beta-cell function in response to glucose loading in normal glucose tolerant individuals. J Clin Pharmacol 2000;40:647-54.
- Heck AM, DeWitt BA, Lukes AL. Potential interactions between alternative therapies and warfarin. Am J Health Syst Pharm 2000;57:1221-7. DOI
- Cesarani A, Meloni F, Alpini D, et al. Ginkgo biloba (EGb 761) in the treatment of equilibrium disorders. Adv Ther 1998;15:291-304.
- Galluzzi S, Zanetti O, Binetti G, et al. Coma in a patient with Alzheimer's disease taking low dose trazodone and Ginkgo biloba. J Neurol Neurosurg Psychiatry 2000;68:679-80. DOI
- Budzinski JW, Foster BC, Vandenhoek S, Arnason JT. An in vitro evaluation of human cytochrome P450 3A4 inhibition by selected commercial herbal extracts and tinctures. Phytomedicine 2000;7:273-82. PubMed
- Gregory PJ. Seizure associated with Ginkgo biloba? Ann Intern Med 2001;134:344.
- Granger AS. Ginkgo biloba precipitating epileptic seizures. Age Ageing 2001;30:523-5. PubMed
- Kajiyama Y, Fujii K, Takeuchi H, Manabe Y. Ginkgo seed poisoning. Pediatrics 2002;109:325-7. PubMed
- Miwa H, Iijima M, Tanaka S, Mizuno Y. Generalized convulsions after consuming a large amount of gingko nuts. Epilepsia 2001;42:280-1. DOI
- Burschka MA, Hassan HA, Reineke T, et al. Effect of treatment with Ginkgo biloba extract EGb 761 (oral) on unilateral idiopathic sudden hearing loss in a prospective randomized double-blind study of 106 outpatients. Eur Arch Otorhinolaryngol 2001;258:213- PubMed
- Miller LG, Freeman B. Possible subdural hematoma associated with Ginkgo biloba. J Herb Pharmacother 2002;2:57-63.
- Kudolo GB, Dorsey S, Blodgett J. Effect of the ingestion of Ginkgo biloba extract on platelet aggregation and urinary prostanoid excretion in healthy and Type 2 diabetic subjects. Thromb Res 2002;108:151-60.. PubMed
- Fong KC, Kinnear PE. Retrobulbar haemorrhage associated with chronic Ginkgo biloba ingestion. Postgrad Med J 2003;79:531-2..
- Gurley BJ, Gardner SF, Hubbard MA, et al. Cytochrome P450 phenotypic ratios for predicting herb-drug interactions in humans. Clin Pharmacol Ther 2002;72:276-87.. PubMed
- Kang BJ, Lee SJ, Kim MD, Cho MJ. A placebo-controlled, double-blind trial of Ginkgo biloba for antidepressant-induced sexual dysfunction. Hum Psychopharmacol 2002;17:279-84.
- Yale SH, Glurich I. Analysis of the inhibitory potential of Ginkgo biloba, Echinacea purpurea, and Serenoa repens on the metabolic activity of cytochrome P450 3A4, 2D6, and 2C9. J Altern Complement Med 2005;11:433-9.
- Yasui-Furukori N, Furukori H, Kaneda A, et al. The effects of Ginkgo biloba extracts on the pharmacokinetics and pharmacodynamics of donepezil. J Clin Pharmacol 2004;44:538-42.
- Markowitz JS, Donovan JL, Lindsay DeVane C, et al. Multiple-dose administration of Ginkgo biloba did not affect cytochrome P-450 2D6 or 3A4 activity in normal volunteers. J Clin Psychopharmacol 2003;23:576-81. PubMed
- Arenz A, Kelin M, Flehe K, et al. Occurrence of neurotoxic 4'-O-methylpyridoxine in ginkgo biloba leaves, ginkgo medications and Japanese ginkgo food. Planta Med 1996;62:548-51.
- Engelsen J, Nielsen JD, Winther K. Effect of coenzyme Q10 and Ginkgo biloba on warfarin dosage in stable, long-term warfarin treated outpatients. A randomised, double blind, placebo-crossover trial. Thromb Haemost 2002;87:1075-6. DOI
- Gaudineau C, Beckerman R, Welbourn S, Auclair K. Inhibition of human P450 enzymes by multiple constituents of the Ginkgo biloba extract. Biochem Biophys Res Comm 2004;318:1072–8. PubMed
- Kohler S, Funk P, Kieser M. Influence of a 7-day treatment with Ginkgo biloba special extract EGb 761 on bleeding time and coagulation: a randomized, placebo-controlled, double-blind study in healthy volunteers. Blood Coagul Fibrinolysis 2004;15:303–9. PubMed
- Jiang X, Williams KM, Liauw WS, et al. Effect of ginkgo and ginger on the pharmacokinetics and pharmacodynamics of warfarin in healthy subjects. Br J Clin Pharmacol 2005;59:425-32. PubMed
- Destro MW, Speranzini MB, Cavalheiro Filho C, et al. Bilateral haematoma after rhytidoplasty and blepharoplasty following chronic use of Ginkgo biloba. Br J Plast Surg 2005;58:100-1. PubMed
- Yin OQ, Tomlinson B, Waye MM, et al. Pharmacogenetics and herb-drug interactions: experience with Ginkgo biloba and omeprazole. Pharmacogenetics 2004;14:841-50. PubMed
- Bent S, Goldberg H, Padula A, Avins AL. Spontaneous bleeding associated with Ginkgo biloba: a case report and systematic review of the literature. J Gen Intern Med 2005;20;657-61. DOI
- Meisel C, Johne A, Roots I. Fatal intracerebral mass bleeding associated with Ginkgo biloba and ibuprofen. Atherosclerosis 2003;167:367. PubMed
- Bebbington A, Kulkarni R, Roberts P. Ginkgo biloba: Persistent bleeding after total hip arthroplasty caused by herbal self-medication. J Arthroplasty 2005;20:125-6. .
- Kupiec T, Raj V. Fatal seizures due to potential herb-drug interactions with Ginkgo biloba. J Anal Toxicol 2005:755-8. PubMed
- Hauser D, Gayowski T, Singh N. Bleeding complications precipitated by unrecognized Gingko biloba use after liver transplantation. Transpl Int 2002;15:377-9. DOI
- Mohutsky MA, Anderson GD, Miller JW, Elmer GW. Ginkgo biloba: evaluation of CYP2C9 drug interactions in vitro and in vivo. Am J Ther 2006;13:24-31. PubMed
- Kudolo GB. The effect of 3-month ingestion of Ginkgo biloba extract (EGb 761) on pancreatic beta-cell function in response to glucose loading in individuals with non-insulin-dependent diabetes mellitus. J Clin Pharmacol 2001;41:600-11.
- Pennisi RS. Acute generalised exanthematous pustulosis induced by the herbal remedy Ginkgo biloba. Med J Aust 2006;184:583-4. PubMed
- Yagmur E, Piatkowski A, Groger A, et al. Bleeding complication under Gingko biloba medication. Am J Hematol 2005;79:343-4. PubMed
- Vale S. Subarachnoid haemorrhage associated with Ginkgo biloba. Lancet 1998;352:36. PubMed
- Aruna D, Naidu MU. Pharmacodynamic interaction studies of Ginkgo biloba with cilostazol and clopidogrel in healthy human subjects. Br J Clin Pharmacol 2007;63:333-8.
- Dugoua JJ, Mills E, Perri D, Koren G. Safety and efficacy of ginkgo (Ginkgo biloba) during pregnancy and lactation. Can J Clin Pharmacol 2006;13:e277-84.
- Jiang X, Blair EY, McLachlan AJ. Investigation of the effects of herbal medicines on warfarin response in healthy subjects: a population pharmacokinetic-pharmacodynamic modeling approach. J Clin Pharmacol 2006;46:1370-8. PubMed
- Woelk H, Arnoldt KH, Kieser M, Hoerr R. Ginkgo biloba special extract EGb 761 in generalized anxiety disorder and adjustment disorder with anxious mood: a randomized, double-blind, placebo-controlled trial. J Psychiatr Res 2007;41:472-80. PubMed
- DeKosky ST, Williamson JD, Fitzpatrick AL, et al. Ginkgo biloba for prevention of dementia. JAMA 2008;300:2253-62.
- Dodge HH, Zitzelberger T, Oken BS, et al. A randomized placebo-controlled trial of ginkgo biloba for the prevention of cognitive decline. Neurology 2008;70(19 Pt 2):1809-17. PubMed
- Wiegman DJ, Brinkman K, Franssen EJ. Interaction of Ginkgo biloba with efavirenz. AIDS 2009;23:1184-5. PubMed
- Kim BH, Kim KP, Lim KS, et al. Influence of Ginkgo biloba extract on the pharmacodynamic effects and pharmacokinetic properties of ticlopidine: An open-label, randomized, two-period, two-treatment, two-sequence, single-dose crossover study in healthy Kor
- Salehi B, Imani R, Mohammadi MR, et al. Ginkgo biloba for attention-deficit/hyperactivity disorder in children and adolescents: a double blind, randomized controlled trial. Prog Neuropsychopharmacol Biol Psychiatry 2010;34:76-80. PubMed
- Kellermann AJ, Kloft C. Is there a risk of bleeding associated with standardized ginkgo biloba extract therapy? A systematic review and meta-analysis. Pharmacotherapy 2011;31:490-502.
- Kuller LH, Ives DG, Fitzpatrick AL, et al. Does Ginkgo biloba reduce the risk of cardiovascular events? Circ Cardiovasc Qual Outcomes 2010;3:41-7.
- Naccarato M, Yoong D, Gough K. A potential drug-herbal interaction between Ginkgo biloba and efavirenz. J Int Assoc Physicians AIDS Care (Chic). 2012;11(2):98-100. doi: 10.1177/1545109711435364. Epub 2012 Feb 9.
- Engelsen, J., Nielsen, J. D., and Hansen, K. F. [Effect of Coenzyme Q10 and Ginkgo biloba on warfarin dosage in patients on long-term warfarin treatment. A randomized, double-blind, placebo-controlled cross-over trial]. Ugeskr.Laeger 4-28-2003;165(18):18
- Parsad, D., Pandhi, R., and Juneja, A. Effectiveness of oral Ginkgo biloba in treating limited, slowly spreading vitiligo. Clin Exp.Dermatol. 2003;28(3):285-287.
- Bal Dit, Sollier C., Caplain, H., and Drouet, L. No alteration in platelet function or coagulation induced by EGb761 in a controlled study. Clin Lab Haematol. 2003;25(4):251-253. PubMed
- Yoshioka, M., Ohnishi, N., Koishi, T., Obata, Y., Nakagawa, M., Matsumoto, T., Tagagi, K., Takara, K., Ohkuni, T., Yokoyama, T., and Kuroda, K. Studies on interactions between functional foods or dietary supplements and medicines. IV. Effects of ginkgo b
- Yoshioka, M., Ohnishi, N., Sone, N., Egami, S., Takara, K., Yokoyama, T., and Kuroda, K. Studies on interactions between functional foods or dietary supplements and medicines. III. Effects of ginkgo biloba leaf extract on the pharmacokinetics of nifedipi
- Lovera, J., Bagert, B., Smoot, K., Morris, C. D., Frank, R., Bogardus, K., Wild, K., Oken, B., Whitham, R., and Bourdette, D. Ginkgo biloba for the improvement of cognitive performance in multiple sclerosis: a randomized, placebo-controlled trial. Mult.S PubMed
- Lin, Y. Y., Chu, S. J., and Tsai, S. H. Association between priapism and concurrent use of risperidone and Ginkgo biloba. Mayo Clin Proc 2007;82(10):1289-1290.
- Robertson, S. M., Davey, R. T., Voell, J., Formentini, E., Alfaro, R. M., and Penzak, S. R. Effect of Ginkgo biloba extract on lopinavir, midazolam and fexofenadine pharmacokinetics in healthy subjects. Curr Med Res Opin 2008;24(2):591-599. PubMed
- Penzak, S. R., Busse, K. H., Robertson, S. M., Formentini, E., Alfaro, R. M., and Davey, R. T., Jr. Limitations of using a single postdose midazolam concentration to predict CYP3A-mediated drug interactions. J Clin Pharmacol 2008;48(6):671-680. PubMed
- May, B. H., Yang, A. W., Zhang, A. L., Owens, M. D., Bennett, L., Head, R., Cobiac, L., Li, C. G., Hugel, H., Story, D. F., and Xue, C. C. Chinese herbal medicine for Mild Cognitive Impairment and Age Associated Memory Impairment: a review of randomised
- Choi, W. S., Choi, C. J., Kim, K. S., Lee, J. H., Song, C. H., Chung, J. H., Ock, S. M., Lee, J. B., and Kim, C. M. To compare the efficacy and safety of nifedipine sustained release with Ginkgo biloba extract to treat patients with primary Raynaud's phe
- Lei, H. P., Wang, G., Wang, L. S., Ou-yang, D. S., Chen, H., Li, Q., Zhang, W., Tan, Z. R., Fan, L., He, Y. J., and Zhou, H. H. Lack of effect of Ginkgo biloba on voriconazole pharmacokinetics in Chinese volunteers identified as CYP2C19 poor and extensiv
- Russo, V., Stella, A., Appezzati, L., Barone, A., Stagni, E., Roszkowska, A., and Delle, Noci N. Clinical efficacy of a Ginkgo biloba extract in the topical treatment of allergic conjunctivitis. Eur J Ophthalmol. 2009;19(3):331-336. PubMed
- Fan, L., Tao, G. Y., Wang, G., Chen, Y., Zhang, W., He, Y. J., Li, Q., Lei, H. P., Jiang, F., Hu, D. L., Huang, Y. F., and Zhou, H. H. Effects of Ginkgo biloba extract ingestion on the pharmacokinetics of talinolol in healthy Chinese volunteers. Ann Phar PubMed
- Ozgoli, G., Selselei, E. A., Mojab, F., and Majd, H. A. A randomized, placebo-controlled trial of Ginkgo biloba L. in treatment of premenstrual syndrome. J Altern.Complement Med 2009;15(8):845-851.
- Singh, V., Singh, S. P., and Chan, K. Review and meta-analysis of usage of ginkgo as an adjunct therapy in chronic schizophrenia. Int J Neuropsychopharmacol. 2010;13(2):257-271.
- Kim, T. E., Kim, B. H., Kim, J., Kim, K. P., Yi, S., Shin, H. S., Lee, Y. O., Lee, K. H., Shin, S. G., Jang, I. J., and Yu, K. S. Comparison of the pharmacokinetics of ticlopidine between administration of a combined fixed-dose tablet formulation of ticl
- Nicolai, S. P., Gerardu, V. C., Kruidenier, L. M., Prins, M. H., and Teijink, J. A. From the Cochrane library: Ginkgo biloba for intermittent claudication. Vasa 2010;39(2):153-158. PubMed
- Patel, N. Herbal remedies. Br.Dent.J 8-28-2010;209(4):153.
- Pedroso, J. L., Henriques Aquino, C. C., Escorcio Bezerra, M. L., Baiense, R. F., Suarez, M. M., Dutra, L. A., Braga-Neto, P., and Povoas Barsottini, O. G. Ginkgo biloba and cerebral bleeding: a case report and critical review. Neurologist. 2011;17(2):89 PubMed
- Russo, V., Rago, A., Russo, G. M., Calabro, R., and Nigro, G. Ginkgo biloba: an ancient tree with new arrhythmic side effects. J Postgrad.Med 2011;57(3):221.
- Zhou, Y. and Zeng, R. [Effects of Ginkgo biloba extract on anticoagulation and blood drug level of warfarin in healthy wolunteers]. Zhongguo Zhong Yao Za Zhi 2011;36(16):2290-2293. DOI
- Skogh, M. Extracts of Ginkgo biloba and bleeding or haemorrhage. Lancet 10-3-1998;352(9134):1145-1146. PubMed
- Fessenden JM, Wittenborn W, and Clarke L. Ginkgo biloba: a case report of herbal medicine and bleeding postoperatively from a laparoscopic cholecystectomy. Am Surg 2001;67(1):33-35.
- Burkard G. [The efficacy and safety of ginkgo biloba extract in dementia]. Fortschr Med [Supp] 1991;109(107):6-8.
- Dai LL, Fan L, Wu HZ, Tan ZR, Chen Y, Peng XD, Shen MX, Yang GP, Zhou HH. Assessment of a pharmacokinetic and pharmacodynamic interaction between simvastatin and Ginkgo biloba extracts in healthy subjects. Xenobiotica 2013;43(10):862-7.
- Guo CX, Pei Q, Yin JY, Peng XD, Zhou BT, Zhao YC, Wu LX, Meng XG, Wang G, Li Q, Ouyang DS, Liu ZQ, Zhang W, Zhou HH. Effects of Ginkgo biloba extracts on pharmacokinetics and efficacy of atorvastatin based on plasma indices. Xenobiotica 2012;42(8):784-90.
- Stoddard GJ, Archer M, Shane-McWhorter L, Bray BE, Redd DF, Proulx J, Zeng-Treitler Q. Ginkgo and Warfarin Interaction in a Large Veterans Administration Population. AMIA Annu Symp Proc. 2015 Nov 5;2015:1174-83.
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Carlile PV. Unexplained alveolar hemorrhage associated with ginkgo and ginseng use. J Bronchology Interv Pulmonol. 2015;22(2):170-2. doi: 10.1097/LBR.0000000000000150. PubMed
- Han EJ, Park HL, Kim SH. Allergic Reaction to Ginkgo Nut on FDG PET/CT. Clin Nucl Med. 2016 Sep;41(9):716-7. doi: 10.1097/RLU.0000000000001276. PubMed
- Rho SS, Woo YS, Bahk WM. Ginkgo biloba induced mood dysregulation: a case report. BMC Complement Altern Med. 2018 Jan 15;18(1):14. PubMed
- Aziz TA, Hussain SA, Mahwi TO, Ahmed ZA, Rahman HS, Rasedee A. The efficacy and safety of Ginkgo biloba extract as an adjuvant in type 2 diabetes mellitus patients ineffectively managed with metformin: a double-blind, randomized, placebo-controlled trial.
- World Health Organization. WHO pharmaceuticals newsletter: 2020, No. 3. Available at: https://www.who.int/medicines/publications/WHO_Pharmaceuticals_Newslet3_20.pdf?ua=1. Accessed June 23, 2021.
- Health Canada. Ginkgo biloba-containing products and the risk of cardiac arrhythmias. Health Product InfoWatch. February 2021. Available at: https://www.canada.ca/en/health-canada/services/drugs-health-products/medeffect-canada/health-product-infowatch/fe
- Wasef AK, Wahdan SA, Saeed NM, El-Demerdash E. Effects of aged garlic and ginkgo biloba extracts on the pharmacokinetics of sofosbuvir in rats. Biopharm Drug Dispos. 2022;43(4):152-62. PubMed
- Xing X, Kong M, Hou Q, Li J, Qian W, Chen X, Li H, Yang C. Effects of ginkgo leaf tablet on the pharmacokinetics of rosiglitazone in rats and its potential mechanism. Pharm Biol. 2022;60(1):1190-7. PubMed
- Hoerr R, Zimmermann A, Seitz F, Dienel A. Single and repeated doses of EGb 761® do not affect pharmacokinetics or pharmacodynamics of rivaroxaban in healthy subjects. Front Pharmacol. 2022 Apr 20;13:868843. PubMed
- Bai J, Zhang C. Metabolic interaction between biflavonoids in Ginkgo biloba leaves and tacrolimus. Biopharm Drug Dispos 2023;44(2):157-164.
- Wang Q, Liu Z, Wang R, et al. Effect of Ginkgo biloba extract on pharmacology and pharmacokinetics of atorvastatin in rats with hyperlipidaemia. Food Funct 2023;14(7):3051-3066.
- Burnett CL, Bergfeld WF, Belsito DV, et al. Safety Assessment of Ginkgo biloba-Derived Ingredients as Used in Cosmetics. Int J Toxicol. 2023 Nov 6:10915818231210792.
- Yao Y, Zhao J, Li C, et al. Ginkgo biloba extract safety: Insights from a real-world pharmacovigilance study of FDA adverse event reporting system (FAERS) events. J Ethnopharmacol 2025;337(Pt 3):119010. PubMed
Vitamin B12 30 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Hartman TJ, Woodson K, Stolzenberg-Solomon R, et al. Association of the B-vitamins pyridoxal 5'-phosphate (B6), B12, and folate with lung cancer risk in older men. Am J Epidemiol 2001;153:688-94.. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Geissbuhler, P., Mermillod, B., and Rapin, C. H. Elevated serum vitamin B12 levels associated with CRP as a predictive factor of mortality in palliative care cancer patients: a prospective study over five years. J.Pain Symptom.Manage. 2000;20(2):93-103. PubMed
- Salles, N., Herrmann, F., Sakbani, K., Rapin, C. H., and Sieber, C. High vitamin B12 level: a strong predictor of mortality in elderly inpatients. J Am Geriatr.Soc 2005;53(5):917-918.
- Looker, H. C., Fagot-Campagna, A., Gunter, E. W., Pfeiffer, C. M., Sievers, M. L., Bennett, P. H., Nelson, R. G., Hanson, R. L., and Knowler, W. C. Homocysteine and vitamin B(12) concentrations and mortality rates in type 2 diabetes. Diabetes Metab Res R
- Uhl, W., Nolting, A., Golor, G., Rost, K. L., and Kovar, A. Safety of hydroxocobalamin in healthy volunteers in a randomized, placebo-controlled study. Clin Toxicol (Phila) 2006;44 Suppl 1:17-28. PubMed
- Borron, S. W., Baud, F. J., Barriot, P., Imbert, M., and Bismuth, C. Prospective study of hydroxocobalamin for acute cyanide poisoning in smoke inhalation. Ann Emerg.Med 2007;49(6):794-801, 801. PubMed
- Borron, S. W., Baud, F. J., Megarbane, B., and Bismuth, C. Hydroxocobalamin for severe acute cyanide poisoning by ingestion or inhalation. Am J Emerg.Med 2007;25(5):551-558. PubMed
- Lewis, J. G. Gout, Steatorrhoea, and Megaloblastic Anaemia. Ann Rheum.Dis 1962;21(3):284-286. PubMed
- Tal, S., Shavit, Y., Stern, F., and Malnick, S. Association between vitamin B12 levels and mortality in hospitalized older adults. J Am Geriatr.Soc 2010;58(3):523-526. PubMed
- Baztan, J. J., Gavidia, J. J., Gomez-Pavon, J., Esteve, A., and Ruiperez, I. High vitamin B12 levels and in-hospital mortality. J Am Geriatr.Soc 2010;58(11):2237-2238. PubMed
- Omboni, E., Checchini, M., and Longoni, F. [Hypopotassemia and megaloblastic anemia. Presentation of a case]. Minerva Med 8-31-1987;78(16):1255-1257.
- Aalfs As, Scholvinck LH, Horvath B. Acneiform eruption in a 5-year old due to vitamin B12 supplementation. Eur J Dermatol 2013;23(5):726-7. PubMed
- Balta I, Ozuguz P. Vitamin B12-induced acneiform eruption. Cutan Ocul Toxicol 2014;33(2):94-5. PubMed
- Carman KB, Belgemen T, Yis U. Involuntary movements misdiagnosed as seizure during vitamin B12 treatment. Pediatr Emerg Care 2013;29(11):1223-4. PubMed
- Djuric V, Bogic M, Popadic AP, et al. Anaphylactic reaction to hydroxycobalamin with tolerance to cyanocobalamin. Ann Allergy Asthma Immunol 2012;108(3):207-8. PubMed
- Kartel O, Gulec M, Demirel F, et al. Vitamin B12 allergy and successful desensitization with cyanocobalamin: A case report. Allergol Immunopath (Madr) 2012;40(5):324-5.
- Patiroglu T, Unal E, Yildirim S. Infantile tremor syndrome associated with cobalamin therapy: A case report. Clin Neurol Neurosurg 2013;115(9):1903-5. PubMed
- Schulte S, Barkema LW, Kardaun SH. Long-lasting atypical acneiform eruption with prominent comedones induced by hydroxocobalamin (vitamin B12). J Dtsch Dermatol Ges 2014;12(6):502-3.
- Zanus C, Alberini E, Costa P, et al. Involuntary movements after correction of vitamin B12 deficiency: A video-case report. Epileptic Disord 2012;14(2):174-80. PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Fujita Y, Mizukami T, Maya Y, et al. Vitamin B12 allergy manifesting as lymphomatoid contact dermatitis. Eur J Dermatol. 2020;30(3):304-305. PubMed
- Dépret F, Hoffmann C, Daoud L, et al. Association between hydroxocobalamin administration and acute kidney injury after smoke inhalation: a multicenter retrospective study. Crit Care. 2019;23(1):421. PubMed
- Khairan P, Sobue T, Eshak ES, et al. Association of dietary intakes of vitamin B12, vitamin B6, folate, and methionine with the risk of esophageal cancer: the Japan Public Health Center-based (JPHC) prospective study. BMC Cancer 2021;21(1):982. PubMed
- Evans J, Pandya A, Ding Y, Qunibi WY. Hydroxocobalamin-Induced Oxalate Nephropathy in a Patient With Smoke Inhalation. Kidney Int Rep 2021;6(8):2228-2231. PubMed
- Lacombe V, Chabrun F, Lacout C, et al. Persistent elevation of plasma vitamin B12 is strongly associated with solid cancer. Sci Rep 2021;11(1):13361. PubMed
- Pegalajar-García MD, Cebolla-Verdugo M, Prados-Carmona Á, Llamas-Segura C, Navarro-Triviño FJ. Systemic allergic dermatitis to cobalt present in cyanocobalamin supplementation. Contact Dermatitis 2023;89(3):203-205. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC