
Magnesium Taurate + Ingredients & Drug Interactions
by KAL
What is this page for?
First and foremost: checking Magnesium Taurate + against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Magnesium Taurate + is a dietary supplement by KAL with 8 active ingredients. Its ingredients are commonly taken for constipation, diarrhea, high cholesterol.Based on those ingredients, 2,230 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Dietary Fiber, Turmeric Root Extract, BioPerine. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Magnesium Taurate + by KAL
Ask about any prescription or over-the-counter medication and we check it for interactions with Magnesium Taurate + by KAL — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Magnesium Taurate + by KAL
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
This product contains 7 active ingredients. Magnesium is included for heart and bone health and to support normal nerve and muscle function.
Cayenne pepper extract, ginger root extract, turmeric root extract, and rosemary leaf extract are herbal constituents traditionally used for inflammation and pain relief. Vitamin B6 (as pyridoxine) supports nerve and energy metabolism.
BioPerine is black pepper extract, added to enhance absorption of the other ingredients. The product also contains inactive ingredients—cellulose, magnesium stearate, croscarmellose sodium, and silica—which serve as binders and flow agents in the tablet.
Does it work?
Strong evidence
The evidence for this product's ingredients is mixed. Magnesium is effective for constipation and heartburn, and likely effective for preventing pre-eclampsia in pregnancy.
Cayenne pepper extract is likely effective for nerve pain after shingles and diabetic nerve pain, and possibly effective for cluster headaches and back pain. Ginger is possibly effective for pregnancy-related nausea and period cramps, and possibly effective for osteoarthritis.
Vitamin B6 is effective for certain types of anemia and B6 deficiency. Turmeric is possibly effective for depression, high cholesterol, and seasonal allergies.
Rosemary and black pepper have insufficient evidence or insufficient reliable evidence to establish their benefits for the conditions listed in our data. None of the ingredients' effectiveness ratings match a single labeled use of the product (which would typically appear on the label), so check your bottle for what health goals the maker claims.
How safe is it?
Well-documented data
Most of these ingredients are generally well tolerated at typical doses. Magnesium commonly causes diarrhea, nausea, or gastrointestinal irritation—especially at higher doses.
Cayenne pepper extract often causes burning, bloating, and gas; food amounts are fine, but concentrated medicinal doses haven't been well studied. Ginger is generally well tolerated but doses above 5 grams daily increase side effects; it may cause heartburn, diarrhea, or a burning sensation in the mouth.
Vitamin B6 is safe below 100 mg daily, but high doses over time can cause nerve damage (sensory neuropathy). Turmeric is generally well tolerated as a food but concentrated supplements have been associated with liver damage in rare cases—over 70 reports exist of liver injury with supplement use lasting 2 weeks to 14 months, though most resolved when the supplement was stopped.
Rosemary in normal food amounts is safe; concentrated extracts require caution. Black pepper is well tolerated as a spice and in single doses.
For pregnancy and breastfeeding, magnesium is needed in pregnancy but use supplements only under a doctor's guidance; ginger and rosemary are used for morning sickness but require doctor approval; turmeric and cayenne pepper safety data in pregnancy is insufficient, so discuss with your doctor first; we have no pregnancy/breastfeeding data on file for vitamin B6 or ginger in this product's facts.
Meds to double-check
Major interaction found
Before taking this, double-check with your pharmacist if you're on blood thinners (anticoagulants) or antiplatelet drugs such as warfarin—multiple ingredients including cayenne, ginger, and rosemary may increase bleeding risk. If you take Parkinson's medication (levodopa/carbidopa), this product's magnesium will reduce its effectiveness.
Check for interactions if you're on diabetes medications, seizure drugs (phenytoin, phenobarbital), blood pressure medications, heart medications like propranolol or nifedipine, cancer drugs, or theophylline. Black pepper in this product may increase levels of several medications including phenytoin, rifampin, and propranolol.
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with strong clinical evidence behind its ingredients' uses. Major medication interactions have been identified, and safety information is well characterized.
This is a multi-ingredient supplement with herbal and micronutrient components. If you take any medications—especially blood thinners, diabetes drugs, seizure medications, heart medications, or Parkinson's disease treatment—check your specific drugs with the tool on this page before starting.
Anyone with a history of liver problems should talk to their pharmacist before using, given turmeric's rare association with liver injury. Pregnant or breastfeeding?
Discuss this product with your doctor or pharmacist first.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 8 of 8 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Nov 22, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Magnesium Taurate +, straight from the product label.
| Brand | KAL |
|---|---|
| Barcode (UPC) | 021245618324 |
| Net contents | 180 Tablet(s) |
| Market status | On market |
| Date entered into DSLD | Nov 22, 2024 |
| DSLD ID | 322920 |
| Product type | Botanical With Nutrients |
| Supplement form | Tablet Or Pill |
| Dietary claims / uses | Nutrient, All Other, Structure/Function |
| Intended target group(s) | Vegan, Vegetarian, Adult (18 - 50 Years), Gluten Free, Dairy Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Magnesium Taurate + by KAL, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Total Carbohydrates | 1 Gram(s) | 1% |
| Dietary Fiber | 1 Gram(s) | 4% |
| Cayenne Pepper extract | 0 NP | -- |
| Vitamin B6 | 25 mg | 1471% |
| Ginger Root Extract | 0 NP | -- |
| Turmeric Root Extract | 0 NP | -- |
| Rosemary Leaf Extract | 0 NP | -- |
| Magnesium | 400 mg | 95% |
| ActiSorb Base | 10 mg | -- |
| BioPerine | 0 NP | -- |
Other ingredients: Cellulose, Magnesium Stearate, Croscarmellose Sodium, Silica
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
General Statements
2 Daily PCR Bottle
Brand IP Statement(s)
KAL Trust Quality Since 1932
Bioperine is a registered trademark of Sabinsa Corp.
Formula
400 mg Magnesium with Coenzyme B-6
Discussion: KAL Magnesium Taurate+ combines the mineral Magnesium with a free-form amino acid, Taurine.
Formulation
Gluten free Non GMO
Magnesium Taurate is intended to provide nutritive support for normal muscle function, healthy nerve and muscle function.
Gluten free, made without soy, made without dairy, Vegan, Non-GMO
Gluten free, made without soy, made without dairy, Vegan, Non-GMO
FDA Statement of Identity
Dietary Supplement
Precautions
Warning: Do not use if safety seal is broken or missing. Keep your licensed health care practitioner informed when using this product.
Keep out of reach of children.
Suggested/Recommended/Usage/Directions
Directions: Take 2 tablets daily with a meal or glass of water. Use only as directed.
Storage
Store in a cool, dry place.
FDA Disclaimer Statement
These statements have not been evaluated by the FDA. This product is not intended to diagnose, treat, cure or prevent any disease.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
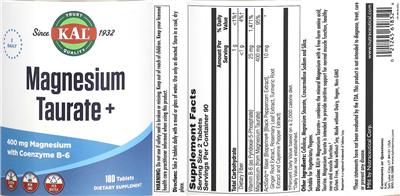
Magnesium Taurate + by KAL label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Magnesium Taurate + by KAL
These are the 8 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Tablet(s) Dosage formTablet Or Pill Servings per container90 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Dietary Fiber
Interacts with2,025 drugs
Black psyllium is a soluble-fiber supplement made from the seeds of a Plantago plant, used mostly to ease constipation and support digestive health. I...
Dietary Fiber monograph & interactionsVitamin B6
Interacts with210 drugs
Vitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is b...
Vitamin B6 monograph & interactionsMagnesium
Interacts with295 drugs
Magnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preven...
Magnesium monograph & interactionsActiSorb Base
Other (inactive) ingredients: Cellulose, Magnesium Stearate, Croscarmellose Sodium, Silica. These complete the product’s ingredient list but are not active constituents.
Magnesium Taurate + by KAL Drug Interactions
HelloPharmacist Interaction Report
Magnesium Taurate + by KAL contains multiple active ingredients that interact with medications.
The single most serious interaction is magnesium with levodopa/carbidopa (Sinemet): magnesium can reduce levodopa's blood levels by 35% and carbidopa's by 81%, potentially weakening treatment for Parkinson's disease.
Read the full breakdown — every affected drug type, severity by severity
The remaining ingredients carry Moderate-severity interactions with several drug types. Cayenne pepper extract may increase bleeding risk with blood thinners and antiplatelet drugs, raise low blood sugar risk with diabetes medications, and affect theophylline levels.
Vitamin B6 can reduce blood pressure medication effects, worsen amiodarone-induced light sensitivity, and reduce seizure medication levels at high doses. Ginger root extract may increase bleeding risk with anticoagulants and antiplatelet drugs, affect diabetes and blood pressure medications, and interact with cancer drugs and P-glycoprotein substrates.
Turmeric root extract interacts with cancer medications, immunosuppressants, and methotrexate. Rosemary leaf extract may increase bleeding risk and affect blood sugar control.
Black pepper (BioPerine) increases levels of propranolol, phenytoin, rifampin, nevirapine, theophylline, and other medications.
We could not check ActiSorb Base because the product facts describe it as a blend container.
Altogether, these interactions span 1,403 individual medications. Use the medication checker on this page to verify your exact drugs before starting.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Magnesium Taurate +?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Magnesium Taurate + interact with 2,230 drugs. Click any drug to see the details.
8 of the 8 ingredients in Magnesium Taurate + interact with drugs. Each result below shows which ingredient is responsible. Dietary Fiber Turmeric Root Extract BioPerine Ginger Root Extract Rosemary Leaf Extract Magnesium Cayenne Pepper extract Vitamin B6
6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Magnesium Taurate + — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + 6-mercaptopurine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Magnesium Taurate + — through 3 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Ado-trastuzumab Emtansine interactionGinger Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger Root Extract + Ado-trastuzumab Emtansine interactionTurmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with Magnesium Taurate + — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Abacavir Sulfate, Dolutegravir, Lamivudine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with Magnesium Taurate + — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Abacavir, Lamivudine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Abacavir, Lamivudine interactionAbciximabReoPro
How Abciximab interacts with Magnesium Taurate + — through 7 ingredients. Tap an ingredient for the detail:
Rosemary Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, rosemary may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Rosemary Leaf Extract + Abciximab interactionGinger Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Ginger Root Extract + Abciximab interactionCayenne Pepper ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, capsicum may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Cayenne Pepper Extract + Abciximab interactionBioperineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Bioperine + Abciximab interactionTurmeric Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Abciximab interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Abciximab interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Magnesium Taurate + — through 4 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Abemaciclib interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Abemaciclib interactionGinger Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger Root Extract + Abemaciclib interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Magnesium Taurate + — through 4 ingredients. Tap an ingredient for the detail:
Ginger Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger Root Extract + Abiraterone interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Abiraterone interactionTurmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Abiraterone interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Magnesium Taurate + — through 4 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Abiraterone Acetate interactionGinger Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger Root Extract + Abiraterone Acetate interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Abiraterone Acetate interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Magnesium Taurate + — through 7 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Abrocitinib interactionGinger Root ExtractCytochrome P450 2c9 (cyp2c9) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP2C9 substrates.
Read the full Ginger Root Extract + Abrocitinib interactionRosemary Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, rosemary may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Rosemary Leaf Extract + Abrocitinib interactionBioperineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Bioperine + Abrocitinib interactionCayenne Pepper ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, capsicum may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Cayenne Pepper Extract + Abrocitinib interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Abrocitinib interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Magnesium Taurate + — through 4 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acalabrutinib interactionGinger Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger Root Extract + Acalabrutinib interactionTurmeric Root ExtractP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
Read the full Turmeric Root Extract + Acalabrutinib interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Magnesium Taurate + — through 6 ingredients. Tap an ingredient for the detail:
Rosemary Leaf ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking rosemary with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Rosemary Leaf Extract + Acarbose interactionTurmeric Root ExtractHepatotoxic Drugs, Antidiabetes Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acarbose interactionGinger Root ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking ginger with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Ginger Root Extract + Acarbose interactionCayenne Pepper ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking capsicum with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Cayenne Pepper Extract + Acarbose interactionBioperineAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Bioperine + Acarbose interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Magnesium Taurate + — through 3 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acebutolol interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Acebutolol interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Magnesium Taurate + — through 7 ingredients. Tap an ingredient for the detail:
Cayenne Pepper ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, capsicum may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Cayenne Pepper Extract + Acenocoumarol interactionBioperineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Bioperine + Acenocoumarol interactionGinger Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Ginger Root Extract + Acenocoumarol interactionTurmeric Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Acenocoumarol interactionRosemary Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, rosemary may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Rosemary Leaf Extract + Acenocoumarol interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acenocoumarol interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Acenocoumarol interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen interactionGinger Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger Root Extract + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Magnesium Taurate + — through 7 ingredients. Tap an ingredient for the detail:
Ginger Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger Root Extract + Acetaminophen, Aspirin interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Aspirin interactionCayenne Pepper ExtractAspirin, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking capsicum with aspirin might reduce the bioavailability of aspirin.
Read the full Cayenne Pepper Extract + Acetaminophen, Aspirin interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Aspirin interactionTurmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Aspirin interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Acetaminophen, Aspirin interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Magnesium Taurate + — through 7 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractAnticoagulant/antiplatelet Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Acetaminophen, Aspirin, Caffeine interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Aspirin, Caffeine interactionGinger Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger Root Extract + Acetaminophen, Aspirin, Caffeine interactionCayenne Pepper ExtractAnticoagulant/antiplatelet Drugs, Aspirin Moderate
Interaction Summary
Theoretically, capsicum may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Cayenne Pepper Extract + Acetaminophen, Aspirin, Caffeine interactionRosemary Leaf ExtractAspirin, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, rosemary might have additive effects with salicylate-containing drugs such as aspirin.
Read the full Rosemary Leaf Extract + Acetaminophen, Aspirin, Caffeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Aspirin, Caffeine interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionGinger Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger Root Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Butalbital interactionGinger Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger Root Extract + Acetaminophen, Butalbital interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Butalbital interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
Ginger Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger Root Extract + Acetaminophen, Butalbital, Caffeine interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Butalbital, Caffeine interactionTurmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital, Caffeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Butalbital, Caffeine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionBioperineCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Bioperine + Acetaminophen, Butalbital, Caffeine, Codeine interactionGinger Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger Root Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Butalbital, Codeine interactionTurmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital, Codeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Butalbital, Codeine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Butalbital, Codeine interactionGinger Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger Root Extract + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Butalbital, Codeine Phosphate interactionGinger Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger Root Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Bioperine + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionGinger Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger Root Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionTurmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
Ginger Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger Root Extract + Acetaminophen, Caffeine, Codeine interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Caffeine, Codeine interactionTurmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Codeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Codeine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionBioperineCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Bioperine + Acetaminophen, Caffeine, Codeine, Salicylamide interactionGinger Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger Root Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Caffeine, Dihydrocodeine interactionTurmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionGinger Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger Root Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Dihydrocodeine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
Ginger Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger Root Extract + Acetaminophen, Caffeine, Isometheptene interactionTurmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Isometheptene interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Caffeine, Isometheptene interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Caffeine, Isometheptene interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Caffeine, PyrilamineMidol Max Strength Menstrual
How Acetaminophen, Caffeine, Pyrilamine interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Caffeine, Pyrilamine interactionGinger Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger Root Extract + Acetaminophen, Caffeine, Pyrilamine interactionTurmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Pyrilamine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Caffeine, Pyrilamine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Pyrilamine interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
Ginger Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger Root Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionTurmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionBioperineCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Bioperine + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with Magnesium Taurate + — through 5 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionGinger Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger Root Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Magnesium Taurate + with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Dietary Fiber
Carbamazepine (Tegretol)
Theoretically, black psyllium might reduce the effects of carbamazepine and increase the risk for convulsions.
Theoretically, black psyllium might reduce carbamazepine absorption. A preliminary study using blond psyllium reported decreased carbamazepine bioavailability due to binding of the drug to psyllium, as well as reduction of available fluid in the gut for dissolution of the drug. This interaction may also occur with black psyllium.
Lithium
Theoretically, taking black psyllium at the same time as lithium might reduce lithium absorption.
The fiber in black psyllium might reduce lithium absorption and plasma levels. Some case reports describe a reduction in plasma lithium levels with concomitant administration of blond psyllium. This was reversed when psyllium was stopped. This interaction may also occur with black psyllium.
Metformin (Glucophage)
Theoretically, black psyllium might increase the therapeutic and adverse effects of metformin.
Animal research shows that concurrent consumption of blond psyllium with metformin slows and increases the absorption of metformin. This interaction may also occur with black psyllium. To avoid changes in absorption, take psyllium 30-60 minutes after metformin.
Olanzapine (Zyprexa)
Theoretically, taking black psyllium at the same time as olanzapine might reduce olanzapine absorption.
The fiber in black psyllium might decrease the absorption of olanzapine. A single case report describes a reduction in the effectiveness of olanzapine when it was concomitantly administered with an unspecified type of psyllium 3 grams orally twice daily. This effect was reversed when psyllium was stopped.
Digoxin (Lanoxin)
Theoretically, taking black psyllium at the same time as digoxin might reduce digoxin absorption and decrease digoxin levels.
Psyllium might bind digoxin in the gut. However, some clinical evidence suggests that psyllium does not impact digoxin absorption.
Ethinyl Estradiol
Theoretically, taking black psyllium at the same time as ethinyl estradiol might alter levels of estradiol.
Concurrent use of blond psyllium with ethinyl estradiol results in a slight increase in the extent of ethinyl estradiol absorption and a slower rate of absorption. This is unlikely to be clinically significant.
Oral Drugs
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Psyllium seems to have variable effects on drug absorption. To avoid changes in absorption, take psyllium 30-60 minutes after oral medications. Animal research shows that blond psyllium delays and increases the absorption of metformin and ethinyl estradiol. Case reports and animal research suggest that blond psyllium might reduce absorption of lithium, digoxin, olanzapine, and carbamazepine. Finally, some pharmacokinetic studies show that psyllium does not affect the absorption of levothyroxine or warfarin. Although many of these studies evaluated blond psyllium, the fiber content in black psyllium may have similar effects.
Turmeric Root Extract
Alkylating Agents
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research suggests that curcumin, a constituent of turmeric, inhibits mechlorethamine-induced apoptosis of breast cancer cells by up to 70%. Also, animal research shows that curcumin inhibits cyclophosphamide-induced tumor regression. However, some in vitro research shows that curcumin does not affect the apoptosis capacity of etoposide. Also, other laboratory research suggests that curcumin might augment the cytotoxic effects of alkylating agents. Reasons for the discrepancies may relate to the dose of curcumin and the specific chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have on alkylating agents.
Amlodipine (Norvasc)
Taking turmeric with amlodipine may increase levels of amlodipine.
Animal research shows that giving amlodipine 1 mg/kg as a single dose following the use of turmeric extract 200 mg/kg daily for 2 weeks increases the maximum concentration and area under the curve by 53% and 56%, respectively, when compared with amlodipine alone. Additional animal research shows that taking amlodipine 1 mg/kg with a curcumin 2 mg/kg pretreatment for 10 days increases the maximum concentration and area under the curve by about 2-fold when compared with amlodipine alone.
Anticoagulant/Antiplatelet Drugs
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs. However, research is conflicting.
Curcumin, a constituent of turmeric, has demonstrated antiplatelet effects in vitro. Furthermore, two case reports have found that taking turmeric along with warfarin or fluindione was associated with an increased international normalized ratio (INR). However, one clinical study in healthy volunteers shows that taking curcumin 500 mg daily for 3 weeks, alone or with aspirin 100 mg, does not increase antiplatelet effects or bleeding risk. It is possible that the dose of turmeric used in this study was too low to produce a notable effect.
Antidiabetes Drugs
Theoretically, taking turmeric with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research and case reports suggest that curcumin, a turmeric constituent, can reduce blood glucose levels in patients with diabetes. Furthermore, clinical research in adults with type 2 diabetes shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg decreased postprandial glucose levels for up to 24 hours when compared with glyburide alone, despite the lack of a significant pharmacokinetic interaction. Other clinical studies in patients with diabetes show that taking curcumin daily can reduce blood glucose levels when compared with placebo.
Antitumor Antibiotics
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro and animal research shows that curcumin, a constituent of turmeric, inhibits doxorubicin-induced apoptosis of breast cancer cells by up to 65%. However, curcumin does not seem to affect the apoptosis capacity of daunorubicin. In fact, some research shows that curcumin might augment the cytotoxic effects of antitumor antibiotics, increasing their effectiveness. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effects, if any, antioxidants such as turmeric have on antitumor antibiotics.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
In vitro and animal research show that turmeric and its constituents curcumin and curcuminoids inhibit CYP3A4. Also, 8 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking turmeric and cancer medications that are CYP3A4 substrates, including everolimus, ruxolitinib, ibrutinib, and palbociclib, and bortezomib. In another case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels after consuming turmeric powder at a dose of 15 or more spoonfuls daily for ten days prior. It was thought that turmeric increased levels of tacrolimus due to CYP3A4 inhibition.
Conversely, other in vitro research suggests that turmeric induces CYP3A4 activity, leading to reduced levels of CYP3A4 substrates. An animal model suggests that induction of CYP3A4 occurs after daily curcumin use for 1 week. However, the induction of CYP3A4 by turmeric has not been reported in humans.
Hepatotoxic Drugs
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
There is concern that turmeric might cause hepatotoxicity, especially when highly bioavailable formulations are used in high doses.
Methotrexate (Trexall, Others)
Theoretically, turmeric might have additive effects when used with hepatotoxic drugs such as methotrexate.
In one case report, a 39-year-old female taking methotrexate, turmeric, and linseed oil developed hepatotoxicity.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Theoretically, turmeric might increase blood levels of OATP4C1 substrates.
In vitro research shows that the turmeric constituent curcumin competitively inhibits OATP4C1 transport. This transporter is expressed in the kidney and facilitates the renal excretion of certain drugs. Theoretically, taking turmeric might decrease renal excretion of OATP substrates.
Sulfasalazine (Azulfidine)
Turmeric might increase the effects and adverse effects of sulfasalazine.
Clinical research shows that taking the turmeric constituent, curcumin, can increase blood levels of sulfasalazine by 3.2-fold.
Tacrolimus (Prograf)
Turmeric might increase the effects and adverse effects of tacrolimus.
In one case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels of 29 ng/mL. The patient previously had tacrolimus levels within the therapeutic range at 9.7 ng/mL. Ten days prior to presenting at the emergency room the patient started consumption of turmeric powder at a dose of 15 or more spoonfuls daily. It was thought that turmeric increased levels of tacrolimus due to cytochrome P450 3A4 (CYP3A4) inhibition. In vitro and animal research show that turmeric and its constituent curcumin inhibit CYP3A4.
Talinolol
Turmeric may reduce the absorption of talinolol in some situations.
Clinical research shows that taking curcumin for 6 days decreases the bioavailability of talinolol when taken together on the seventh day. The clinical significance of this effect is unclear.
Tamoxifen (Nolvadex)
Theoretically, turmeric might reduce the levels and clinical effects of tamoxifen.
In a small clinical trial in patients with breast cancer taking tamoxifen 20-30 mg daily, adding curcumin 1200 mg plus piperine 10 mg three times daily reduces the 24-hour area under the curve of tamoxifen and the active metabolite endoxifen by 12.8% and 12.4%, respectively, as well as the maximum concentrations of tamoxifen, when compared with tamoxifen alone. However, in the absence of piperine, the area under the curve for endoxifen and the maximum concentration of tamoxifen were not significantly reduced. Effects were most pronounced in patients who were extensive cytochrome P450 (CYP) 2D6 metabolizers.
Topoisomerase I Inhibitors
Turmeric has antioxidant effects. There is some concern that this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research shows that curcumin, a constituent of turmeric, inhibits camptothecin-induced apoptosis of breast cancer cells by up to 71%. However, other in vitro research shows that curcumin augments the cytotoxic effects of camptothecin. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agents. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have.
Tramadol (Ultram)
Theoretically, turmeric might increase or decrease levels of tramadol.
Animal research suggests that a single dose of curcumin, a constituent of turmeric, may increase tramadol's maximum concentration (Cmax) by inhibiting metabolism, while continued daily use for 7 days may reduce the area under the curve (AUC) due to the induction of drug-metabolizing enzymes such as cytochrome P450 3A4 (CYP3A4). However, this interaction has not been reported in humans.
Warfarin (Coumadin)
Turmeric might increase the risk of bleeding with warfarin.
One case of increased international normalized ratio (INR) has been reported for a patient taking warfarin who began taking turmeric. Prior to taking turmeric, the patient had stable INR measurements. Within a few weeks of starting turmeric supplementation, the patient's INR increased to 10. Additionally, curcumin, the active constituent in turmeric, has demonstrated antiplatelet effects in vitro, which may produce additive effects when taken with warfarin.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2. However, research is conflicting.
In vitro and animal research show that the turmeric constituent, curcumin, inhibits CYP1A2. However, other in vitro research suggests that curcumin does not significantly affect CYP1A2.
Docetaxel (Taxotere)
Theoretically, turmeric might increase blood levels of oral docetaxel.
Animal research suggests that the turmeric constituent, curcumin, enhances the oral bioavailability of docetaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
Estrogens
Theoretically, large amounts of turmeric might interfere with hormone replacement therapy through competition for estrogen receptors.
In vitro research shows that curcumin, a constituent of turmeric, displaces the binding of estrogen to its receptors.
Glyburide (Diabeta, Others)
Theoretically, taking turmeric and glyburide in combination might increase the risk of hypoglycemia.
Clinical research shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg increases blood levels of glyburide by 12% at 2 hours after the dose in patients with type 2 diabetes. While maximal blood concentrations of glyburide were not affected, turmeric modestly decreased postprandial glucose levels for up to 24 hours when compared to glyburide alone, possibly due to the hypoglycemic effect of turmeric demonstrated in animal research.
Losartan (Cozaar)
Theoretically, turmeric might increase the effects of losartan.
Research in hypertensive rats shows that taking turmeric can increase the hypotensive effects of losartan.
Norfloxacin (Noroxin)
Theoretically, turmeric might increase the effects and adverse effects of norfloxacin.
Animal research shows that taking curcumin, a turmeric constituent, can increase blood levels of orally administered norfloxacin.
P-Glycoprotein Substrates
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
In vitro and animal research shows that curcuminoids and other constituents found in turmeric can inhibit P-glycoprotein expression and activity.
Paclitaxel (Abraxane, Onxol)
Theoretically, turmeric might alter blood levels of paclitaxel, although any effect may not be clinically relevant.
Clinical research in adults with breast cancer receiving intravenous paclitaxel suggests that taking turmeric may modestly alter paclitaxel pharmacokinetics. Patients received paclitaxel on day 1, followed by either no treatment or turmeric 2 grams daily from days 2-22. Pharmacokinetic modeling suggests that turmeric reduces the maximum concentration and area under the curve of paclitaxel by 12.1% and 7.7%, respectively. However, these changes are not likely to be considered clinically relevant. Conversely, animal research suggests that curcumin, a constituent of turmeric, enhances the oral bioavailability of paclitaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
BioPerine
Anticoagulant/Antiplatelet Drugs
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
In vitro research shows that piperine, a constituent of black pepper, seems to inhibit platelet aggregation. This has not been reported in humans.
Antidiabetes Drugs
Theoretically, black pepper might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Animal research shows that piperine, a constituent of black pepper, can reduce blood glucose levels. Monitor blood glucose levels closely. Dose adjustments might be necessary.
Atorvastatin (Lipitor)
Theoretically, black pepper might increase blood levels of atorvastatin.
Animal research shows that taking piperine, a constituent of black pepper, 35 mg/kg can increase the maximum serum concentration of atorvastatin three-fold. This has not been reported in humans.
Cyclosporine (Neoral, Sandimmune)
Theoretically, black pepper might increase the effects and side effects of cyclosporine.
In vitro research shows that piperine, a constituent of black pepper, increases the bioavailability of cyclosporine. This has not been reported in humans.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
In vitro research suggests that some constituents of black pepper inhibit CYP2D6. This has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
In vitro research and pharmacokinetic simulation data suggest that piperine, a constituent of black pepper, as well as the pepper fruit seem to inhibit CYP3A4. This has not been reported in humans.
Lithium
Theoretically, black pepper might increase blood levels of lithium due to its diuretic effects. The dose of lithium might need to be reduced.
Black pepper is thought to have diuretic properties.
Nevirapine (Viramune)
Black pepper might increase blood levels of nevirapine.
Clinical research shows that piperine, a constituent of black pepper, increases the plasma concentration of nevirapine. However, no adverse effects were observed in this study.
P-Glycoprotein Substrates
Theoretically, black pepper might increase levels of P-glycoprotein substrates.
In vitro research shows that piperine, a constituent of black pepper, seems to inhibit P-glycoprotein.
Pentobarbital (Nembutal)
Theoretically, black pepper might increase the sedative effects of pentobarbital.
Animal research shows that piperine, a constituent of black pepper, increases pentobarbital-induced sleeping time.
Phenytoin (Dilantin)
Black pepper might increase blood levels of phenytoin.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption, slow elimination, and increase levels of phenytoin. Taking a single dose of black pepper 1 gram along with phenytoin seems to double the serum concentration of phenytoin. Consuming a soup with black pepper providing piperine 44 mg/200 mL of soup along with phenytoin also seems to increase phenytoin levels when compared with consuming the same soup without black pepper.
Propranolol (Inderal)
Black pepper might increase blood levels of propranolol.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and slow elimination of propranolol.
Rifampin (Rifadin)
Black pepper might increase blood levels of rifampin.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and serum levels of rifampin.
Theophylline
Black pepper might increase blood levels of theophylline.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and slow elimination of theophylline.
Amoxicillin (Amoxil, Trimox)
Theoretically, black pepper might increase the effects and side effects of amoxicillin.
Animal research shows that taking piperine, a constituent of black pepper, with amoxicillin increases plasma levels of amoxicillin. This has not been reported in humans.
Carbamazepine (Tegretol)
Theoretically, black pepper might increase blood levels of carbamazepine, potentially increasing the effects and side effects of carbamazepine.
One clinical study in patients taking carbamazepine 300 mg or 500 mg twice daily shows that taking a single 20 mg dose of purified piperine, a constituent of black pepper, increases carbamazepine levels. Piperine may increase carbamazepine absorption by increasing blood flow to the GI tract, increasing the surface area of the small intestine, or inhibiting cytochrome P450 3A4 (CYP3A4) in the gut wall. Absorption was significantly increased by 7-10 mcg/mL/hour. The time to eliminate carbamazepine was also increased by 4-8 hours. Although carbamazepine levels were increased, this did not appear to increase side effects. In vitro research also shows that piperine can increase carbamazepine levels by 11% in a time-dependent manner.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
In vitro research suggests that black pepper induces CYP1A2. This has not been reported in humans.
Ginger Root Extract
Anticoagulant/Antiplatelet Drugs
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs. However, research is conflicting.
Laboratory research suggests that ginger inhibits thromboxane synthetase and decreases platelet aggregation. However, this has not been demonstrated unequivocally in humans, with mixed results from clinical trials. Theoretically, excessive amounts of ginger might increase the risk of bleeding when used with anticoagulant/antiplatelet drugs.
Antidiabetes Drugs
Theoretically, taking ginger with antidiabetes drugs might increase the risk of hypoglycemia.
Animal and human research suggests that ginger might increase insulin levels and/or decrease blood glucose levels.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Ginger might increase or decrease the levels of CYP3A4 substrates.
In vitro research and some case reports suggest that ginger inhibits CYP3A4 activity. Three case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking ginger and cancer medications that are CYP3A4 substrates (imatinib, dabrafenib, and crizotinib). However, the causality of this interaction is unclear due to the presence of multiple interacting drugs and routes of administration.
Conversely, other in vitro research suggests that ginger induces CYP3A4 activity, leading to reduced levels of CYP3A4 substrates. However, this interaction has not been reported in humans.
Losartan (Cozaar)
Theoretically, ginger might increase levels of losartan and the risk of hypotension.
In animal research, ginger increased the levels and hypotensive effects of a single dose of losartan. It is not clear if ginger alters the concentration or effects of losartan when taken continuously. Additionally, this interaction has not been shown in humans.
Nifedipine (Procardia)
Ginger may have antiplatelet effects and increase the risk of bleeding if used with nifedipine.
Clinical research shows that combined treatment with ginger 1 gram plus nifedipine 10 mg significantly inhibits platelet aggregation when compared to nifedipine or ginger alone.
P-Glycoprotein Substrates
Ginger might increase the absorption and blood levels of P-glycoprotein (P-gp) substrates.
In vitro research and case reports suggest that ginger inhibits drug efflux by P-gp, potentially increasing absorption and serum levels of P-gp substrates. Two case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking ginger and cancer medications that are P-gp substrates (trametinib, crizotinib). However, the causality of this interaction is unclear due to the presence of multiple interacting drugs and routes of administration.
Phenprocoumon (Marcoumar, Others)
Ginger might increase the risk of bleeding with phenprocoumon.
Phenprocoumon, a warfarin-related anticoagulant, might increase the international normalized ratio (INR) when taken with ginger. There is one case report of a 76-year-old woman with a stable INR on phenprocoumon that increased to greater than 10 when she began consuming dried ginger and ginger tea.
Warfarin (Coumadin)
Ginger might increase the risk of bleeding with warfarin.
Laboratory research suggests that ginger might inhibit thromboxane synthetase and decrease platelet aggregation. In one case report, ginger increased the INR when taken with phenprocoumon, which has similar pharmacological effects as warfarin. In another case report, ginger increased the INR when taken with a combination of warfarin, hydrochlorothiazide, and acetaminophen. A longitudinal analysis suggests that taking ginger increases the risk of bleeding in patients taking warfarin for at least 4 months. However, research in healthy people suggests that ginger has no effect on INR, or the pharmacokinetics or pharmacodynamics of warfarin. Until more is known, monitor INRs closely in patients taking large amounts of ginger.
Calcium Channel Blockers
Theoretically, taking ginger with calcium channel blockers might increase the risk of hypotension.
Some animal and in vitro research suggests that ginger has hypotensive and calcium channel-blocking effects. Another animal study shows that concomitant administration of ginger and the calcium channel blocker amlodipine leads to greater reductions in blood pressure when compared with amlodipine alone.
Cyclosporine (Neoral, Sandimmune)
Theoretically, when taken prior to cyclosporine, ginger might decrease cyclosporine levels.
In an animal model, ginger juice taken 2 hours prior to cyclosporine administration reduced the maximum concentration and area under the curve of cyclosporine by 51% and 40%, respectively. This effect was not observed when ginger juice and cyclosporine were administered at the same time.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ginger might increase the levels of CYP1A2 substrates.
In vitro research shows that ginger inhibits CYP1A2 activity. However, this interaction has not been reported in humans.
Cytochrome P450 2B6 (Cyp2B6) Substrates
Theoretically, ginger might increase the levels of CYP2B6 substrates.
In vitro research shows that ginger inhibits CYP2B6 activity. However, this interaction has not been reported in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, ginger might increase the levels of CYP2C9 substrates.
In vitro research shows that ginger inhibits CYP2C9 activity. However, this interaction has not been reported in humans.
Metronidazole (Flagyl)
Theoretically, ginger might increase levels of metronidazole.
In an animal model, ginger increased the absorption and plasma half-life of metronidazole. In addition, the elimination rate and clearance of metronidazole was significantly reduced.
Rosemary Leaf Extract
Anticoagulant/Antiplatelet Drugs
Theoretically, rosemary may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro and animal research suggests that rosemary inhibits platelet aggregation.
Antidiabetes Drugs
Theoretically, taking rosemary with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research shows that rosemary extract can decrease blood glucose levels in diabetic models. However, research in humans is conflicting. Although rosemary powder decreased blood glucose levels in healthy adults, no change in blood glucose levels was seen in adults with type 2 diabetes, most of whom were taking antidiabetes drugs.
Aspirin
Theoretically, rosemary might have additive effects with salicylate-containing drugs such as aspirin.
Rosemary is reported to contain salicylates.
Choline Magnesium Trisalicylate (Trilisate)
Theoretically, rosemary might have additive effects with salicylate-containing drugs such as choline magnesium trisalicylate.
Rosemary is reported to contain salicylate.
Salsalate (Disalcid)
Theoretically, rosemary might have additive effects with salicylate-containing drugs such as salsalate.
Rosemary is reported to contain salicylate.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
In vitro research shows that rosemary induces CYP1A2 enzymes. This effect has not been reported in humans.
Magnesium
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
Cayenne Pepper extract
Anticoagulant/Antiplatelet Drugs
Theoretically, capsicum may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro research shows that capsicum might increase the effects of antiplatelet drugs. Also, population research shows that capsicum is associated with an increased risk of self-reported bleeding in patients taking warfarin. However, clinical research shows that taking a single dose of capsaicin (Asian Herbex Ltd.), the active ingredient in capsicum, 400-800 mcg orally in combination with aspirin 500 mg does not decrease platelet aggregation when compared with taking aspirin 500 mg alone. Also, there was no notable effect on measures of platelet aggregation with capsaicin. It is unclear whether capsaicin must be used in more than a single dose to affect platelet aggregation.
Antidiabetes Drugs
Theoretically, taking capsicum with antidiabetes drugs might increase the risk of hypoglycemia.
Preliminary clinical research shows that consuming capsicum 5 grams along with a glucose drink attenuates the rise in plasma glucose after 30 minutes by 21%, decreases the 2-hour postprandial area under the curve of plasma glucose by 11%, and increases the 2-hour postprandial area under the curve of plasma insulin by 58% in healthy individuals when compared with placebo. Other clinical research shows that taking capsicum 5 mg daily for 28 days significantly reduces postprandial blood glucose and insulin levels, but not fasting blood glucose and insulin levels, in patients with gestational diabetes.
Aspirin
Theoretically, taking capsicum with aspirin might reduce the bioavailability of aspirin.
Animal research shows that acute or chronic intake of capsicum pepper reduces oral aspirin bioavailability. This has not been shown in humans.
Theophylline
Theoretically, taking capsicum with theophylline might increase the levels and adverse effects of theophylline.
In animal research, oral administration of capsicum reduced excretion of theophylline. However, capsicum does not seem to affect the pharmacokinetics of theophylline when administered intravenously.
Ace Inhibitors (Aceis)
Theoretically, using topical capsaicin may increase the risk of ACE inhibitor-induced cough.
There is one case report of a topically applied capsaicin cream contributing to the cough reflex in a patient using an ACEI. However, it is unclear if this interaction is clinically significant.
Ciprofloxacin (Cipro)
Theoretically, taking capsicum with ciprofloxacin might increase levels and adverse effects of ciprofloxacin.
Animal research shows that concomitant use of capsaicin, the active constituent of capsicum, and ciprofloxacin increases the bioavailability of ciprofloxacin by up to 70%.
Vitamin B6
Amiodarone (Cordarone)
Theoretically, vitamin B6 might increase the photosensitivity caused by amiodarone.
Despite initial case reports suggesting that pyridoxine may have a protective effect against amiodarone-induced photosensitivity, preliminary clinical research suggests that pyridoxine may actually exacerbate this adverse effect.
Antihypertensive Drugs
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Research in hypertensive rats shows that vitamin B6 can decrease systolic blood pressure. Similarly, clinical research in patients with hypertension shows that taking high doses of vitamin B6 may reduce systolic and diastolic blood pressure, possibly by reducing plasma levels of epinephrine and norepinephrine.
Phenobarbital (Luminal)
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenobarbital, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenobarbital to avoid high doses of vitamin B6.
Phenytoin (Dilantin)
High doses of vitamin B6 may reduce the levels and clinical effects of phenytoin.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenytoin, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenytoin to avoid high doses of vitamin B6.
Levodopa
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Vitamin B6 (pyridoxine) enhances the metabolism of levodopa, reducing its clinical effects. However, this interaction does not occur when carbidopa is used concurrently with levodopa (Sinemet). Therefore, it is not likely to be a problem in most people.
Brand information
Manufacturer and brand details for Magnesium Taurate +, from the product label.
Magnesium Taurate + by KAL: Common Questions
Does Magnesium Taurate + by KAL interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take this if I'm on blood thinners like warfarin?
Will this affect my diabetes medication?
What's the black pepper (BioPerine) in here for?
Can I take this during pregnancy?
Is turmeric in this product safe for my liver?
Can this cause side effects from the magnesium alone?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Magnesium Taurate + is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Magnesium Taurate +’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Black Psyllium
Interacts with 2,025 drugsBlack psyllium is a soluble-fiber supplement made from the seeds of a Plantago plant, used mostly to ease constipation and support digestive health. It is best known and most studied for rel...
Read the full Black Psyllium monograph → Herb & supplement monographVitamin B6
Interacts with 210 drugsVitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is best known for helping with pregnancy-rel...
Read the full Vitamin B6 monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographCapsicum
Interacts with 239 drugsCapsicum (chili pepper) contains capsaicin, which is best known and best studied as a topical treatment for certain types of pain. Topical capsaicin products are supported by reasonable evid...
Read the full Capsicum monograph → Herb & supplement monographGinger
Interacts with 1,007 drugsGinger is a widely used culinary spice with a long history in traditional medicine, and it has the strongest evidence for helping with nausea and vomiting, including from motion sickness, pr...
Read the full Ginger monograph → Herb & supplement monographTurmeric
Interacts with 1,133 drugsTurmeric is a popular spice whose main active compounds, curcuminoids, are studied mostly for inflammation and joint pain. Some research is promising, but quality is mixed and curcumin is po...
Read the full Turmeric monograph → Herb & supplement monographRosemary
Interacts with 372 drugsRosemary is a fragrant Mediterranean herb that is safe and flavorful in normal food amounts. Some early research suggests possible benefits for memory, mood, and hair growth, but the evidenc...
Read the full Rosemary monograph → Herb & supplement monographBlack Pepper
Interacts with 1,019 drugsBlack pepper is a common kitchen spice that is generally safe in the amounts used in food. Its extract, piperine, is mostly added to supplements to help the body absorb other ingredients (li...
Read the full Black Pepper monograph →Sources & How We Checked
Magnesium Taurate +'s label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 436 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Black Psyllium 18 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Etman M. Effect of a bulk forming laxative on the bioavailablility of carbamazepine in man. Drug Dev Ind Pharm 1995;21:1901-6.
- Perlman BB. Interaction between lithium salts and ispaghula husk. Lancet 1990;335:416.
- Vaswani SK, Hamilton RG, Valentine MD, Adkinson NF. Psyllium laxative-induced anaphylaxis, asthma, and rhinitis. Allergy 1996;51:266-8. PubMed
- Lantner RR, Espiritu BR, Zumerchik P, Tobin MC. Anaphylaxis following ingestion of a psyllium-containing cereal. JAMA 1990;264:2534-6. DOI
- Kaplan MJ. Anaphylactic reaction to "Heartwise." N Engl J Med 1990;323:1072-3. DOI
- Nordstrom M, Melander A, Robertsson E, Steen B. Influence of wheat bran and of a bulk-forming ispaghula cathartic on the bioavailability of digoxin in geriatric in-patients. Drug Nutr Interact 1987;5:67-9..
- Robinson DS, Benjamin DM, McCormack JJ. Interaction of warfarin and nonsystemic gastrointestinal drugs. Clin Pharmacol Ther 1971;12:491-5. PubMed
- Garcia JJ, Fernandez N, Diez MJ, et al. Influence of two dietary fibers in the oral bioavailability and other pharmacokinetic parameters of ethinyloestradiol. Contraception 2000;62:253-7. PubMed
- Fernandez N, Lopez C, Díez R, et al. Drug interactions with the dietary fiber Plantago ovata husk. Expert Opin Drug Metab Toxicol 2012;8(11):1377-86.
- Semen plantaginis in: WHO Monographs on Selected Medicinal Plants, volume 1. World Health Organization, Geneva, 1999. Available at http://apps.who.int/medicinedocs/en/d/Js2200e/. Accessed November 26, 1026.
- Code of Federal Regulations, Title 21 (21CFR 101.17). Food labeling warning, notice, and safe handling statements. Available at www.ecfr.gov/cgi-bin/text-idx?SID=20f647d3b74161501f46564b915b4048&mc=true&node=se21.2.101_117&rgn=div8. Accessed December 3, 2
- Code of Federal Regulations, Title 21 (21CFR 201.319). Specific labeling requirements - water-soluble gums, hydrophilic gums, and hydrophilic mucilloids. Available at www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfcfr/CFRSearch.cfm?fr=201.319. Accessed Dece
- Diez R, Garcia JJ, Diez MJ, Sierra M, Sahagun AM, Fernandez N. Influence of Plantago ovata husk (dietary fiber) on the bioavailability and other pharmacokinetic parameters of metformin in diabetic rabbits. BMC Complement Altern Med. 2017 Jun 7;17(1):298. PubMed
- Chiu AC, Sherman SI. Effects of pharmacological fiber supplements on levothyroxine absorption. Thyroid. 1998;8(8):667-71. PubMed
- Merrick C, Madden CA, Capurso NA. A Case of Blunted Orally Disintegrating Olanzapine Effect Due to Coadministered Psyllium. J Clin Psychiatry 2021;82(2):20cr13633. PubMed
Capsicum 89 references
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Cooper RL, Cooper MM. Red pepper-induced dermatitis in breast-fed infants. Dermatol 1996;93:61-2. PubMed
- Millqvist E. Cough provocation with capsaicin is an objective way to test sensory hyperreactivity in patients with asthma-like symptoms. Allergy 2000;55:546-50. DOI
- Locock RA. Capsicum. Can Pharm J 1985;118:517-9.
- Mason L, Moore RA, Derry S, et al. Systematic review of topical capsaicin for the treatment of chronic pain. BMJ 2004;328:991. PubMed
- Schmulson MJ, Valdovinos MA, Milke P. Chili pepper and rectal hyperalgesia in irritable bowel syndrome. Am J Gastroenterol 2003;98:1214-5. PubMed
- Surh YJ, Lee SS. Capsaicin in hot chili pepper: carcinogen, co-carcinogen or anticarcinogen? Food Chem Toxicol 1996;34:313-6. PubMed
- Bouraoui A, Brazier JL, Zouaghi H, Rousseau M. Theophylline pharmacokinetics and metabolism in rabbits following single and repeated administration of Capsicum fruit. Eur J Drug Metab Pharmacokinet 1995;20:173-8.
- Hogaboam CM, Wallace JL. Inhibition of platelet aggregation by capsaicin. An effect unrelated to actions on sensory afferent neurons. Eur J Pharmacol 1991;202:129-31. PubMed
- Wang JP, Hsu MF, Teng CM. Antiplatelet effect of capsaicin. Thromb Res 1984;36:497-507. PubMed
- Williams SR, Clark RF, Dunford JV. Contact dermatitis associated with capsaicin: Hunan hand syndrome. Ann Emerg Med 1995;25:713-5. PubMed
- Zollman TM, Bragg RM, Harrison DA. Clinical effects of oleoresin capsicum (pepper spray) on the human cornea and conjunctiva. Ophthalmology 2000;107:2186-9. PubMed
- Bortolotti M, Coccia G, Grossi G, Miglioli M. The treatment of functional dyspepsia with red pepper. Aliment Pharmacol Ther 2002;16:1075-82. PubMed
- Hakas JF Jr. Topical capsaicin induces cough in patient receiving ACE inhibitor. Ann Allergy 1990;65:322-3.
- Rapoport AM, Bigal ME, Tepper SJ, Sheftell FD. Intranasal medications for the treatment of migraine and cluster headache. CNS Drugs 2004;18:671-85. PubMed
- Stjarne P, Rinder J, Heden-Blomquist E, et al. Capsaicin desensitization of the nasal mucosa reduces symptoms upon allergen challenge in patients with allergic rhinitis. Acta Otolaryngol 1998;118:235-9. PubMed
- Levy RL. Intranasal capsaicin for acute abortive treatment of migraine without aura. Headache 1995;35:277.
- Fusco BM, Marabini S, Maggi CA, et al. Preventative effect of repeated nasal applications of capsaicin in cluster headache. Pain 1994;59:321-5. PubMed
- Sicuteri F, Fusco BM, Marabini S, et al. Beneficial effect of capsaicin application to the nasal mucosa in cluster headache. Clin J Pain 1989;5:49-53. PubMed
- Marabini S, Ciabatti PG, Polli G, et al. Beneficial effects of intranasal applications of capsaicin in patients with vasomotor rhinitis. Eur Arch Otorhinolaryngol 1991;248:191-4. PubMed
- Frerick H, Keitel W, Kuhn U, et al. Topical treatment of chronic low back pain with a capsicum plaster. Pain 2003;106:59-64. PubMed
- Keitel W, Frerick H, Kuhn U, et al. Capsicum pain plaster in chronic non-specific low back pain. Arzneimittelforschung 2001;51:896-903. PubMed
- Shalansky S, Lynd L, Richardson K, et al. Risk of warfarin-related bleeding events and supratherapeutic international normalized ratios associated with complementary and alternative medicine: a longitudinal analysis. Pharmacotherapy. 2007;27:1237-47. PubMed
- Sumano-López H, Gutiérrez-Olvera L, Aguilera-Jiménez R, et al. Administration of ciprofloxacin and capsaicin in rats to achieve higher maximal serum concentrations. Arzneimittelforschung. 2007;57(5):286-90. PubMed
- Wanwimolruk S, Nyika S, Kepple M, et al. Effects of capsaicin on the pharmacokinetics of antipyrine, theophylline and quinine in rats. J Pharm Pharmacol. 1993;45(7):618-21. PubMed
- Cruz L, Castañeda-Hernández G, Navarrete A. Ingestion of chilli pepper (Capsicum annuum) reduces salicylate bioavailability after oral asprin administration in the rat. Can J Physiol Pharmacol.
- Rodriguez-Stanley, S., Collings, K. L., Robinson, M., Owen, W., and Miner, P. B., Jr. The effects of capsaicin on reflux, gastric emptying and dyspepsia. Aliment.Pharmacol.Ther. 2000;14(1):129-134. PubMed
- Brown, L., Takeuchi, D., and Challoner, K. Corneal abrasions associated with pepper spray exposure. Am.J.Emerg.Med. 2000;18(3):271-272. PubMed
- Vesaluoma, M., Muller, L., Gallar, J., Lambiase, A., Moilanen, J., Hack, T., Belmonte, C., and Tervo, T. Effects of oleoresin capsicum pepper spray on human corneal morphology and sensitivity. Invest Ophthalmol.Vis.Sci. 2000;41(8):2138-2147.
- Stam, C., Bonnet, M. S., and van Haselen, R. A. The efficacy and safety of a homeopathic gel in the treatment of acute low back pain: a multi-centre, randomised, double-blind comparative clinical trial. Br Homeopath J 2001;90(1):21-28. PubMed
- Olajos, E. J. and Salem, H. Riot control agents: pharmacology, toxicology, biochemistry and chemistry. J.Appl.Toxicol. 2001;21(5):355-391. PubMed
- Fett, D. D. Botanical briefs: Capsicum peppers. Cutis 2003;72(1):21-23.
- McCarthy, G. M. and McCarty, D. J. Effect of topical capsaicin in the therapy of painful osteoarthritis of the hands. J.Rheumatol. 1992;19(4):604-607.
- Chaiyata, P., Puttadechakum, S., and Komindr, S. Effect of chili pepper (Capsicum frutescens) ingestion on plasma glucose response and metabolic rate in Thai women. J.Med.Assoc.Thai. 2003;86(9):854-860.
- Petruzzi, M., Lauritano, D., De Benedittis, M., Baldoni, M., and Serpico, R. Systemic capsaicin for burning mouth syndrome: short-term results of a pilot study. J.Oral Pathol.Med. 2004;33(2):111-114. PubMed
- Misra, M. N., Pullani, A. J., and Mohamed, Z. U. Prevention of PONV by acustimulation with capsicum plaster is comparable to ondansetron after middle ear surgery: [La prevention des NVPO par acustimulation avec un emplatre de Capsicum est comparable a ce PubMed
- Milke, P., Diaz, A., Valdovinos, M. A., and Moran, S. Gastroesophageal reflux in healthy subjects induced by two different species of chilli (Capsicum annum). Dig.Dis. 2006;24(1-2):184-188.
- de Jong, N. W., van der Steen, J. J., Smeekens, C. C., Blacquiere, T., Mulder, P. G., van Wijk, R. G., and de Groot, H. Honeybee interference as a novel aid to reduce pollen exposure and nasal symptoms among greenhouse workers allergic to sweet bell pepp
- Final report on the safety assessment of capsicum annuum extract, capsicum annuum fruit extract, capsicum annuum resin, capsicum annuum fruit powder, capsicum frutescens fruit, capsicum frutescens fruit extract, capsicum frutescens resin, and capsaicin.
- Tandan, R., Lewis, G. A., Krusinski, P. B., Badger, G. B., and Fries, T. J. Topical capsaicin in painful diabetic neuropathy. Controlled study with long-term follow-up. Diabetes Care 1992;15(1):8-14. PubMed
- Gupta, P. J. Red hot chilli consumption is harmful in patients operated for anal fissure - a randomized, double-blind, controlled study. Dig.Surg. 2007;24(5):354-357. PubMed
- Patane, S., Marte, F., Di Bella, G., Cerrito, M., and Coglitore, S. Capsaicin, arterial hypertensive crisis and acute myocardial infarction associated with high levels of thyroid stimulating hormone. Int.J Cardiol. 5-1-2009;134(1):130-132. PubMed
- Gupta, P. J. Consumption of red-hot chili pepper increases symptoms in patients with acute anal fissures. A prospective, randomized, placebo-controlled, double blind, crossover trial. Arq Gastroenterol. 2008;45(2):124-127. PubMed
- Gupta, P. J. Consumption of red-hot chili pepper increases symptoms in patients with acute anal fissures. Ann.Ital.Chir 2008;79(5):347-351.
- Patane, S., Marte, F., La Rosa, F. C., and La, Rocca R. Capsaicin and arterial hypertensive crisis. Int J Cardiol. 10-8-2010;144(2):e26-e27. PubMed
- Chaiyasit, K., Khovidhunkit, W., and Wittayalertpanya, S. Pharmacokinetic and the effect of capsaicin in Capsicum frutescens on decreasing plasma glucose level. J Med.Assoc.Thai. 2009;92(1):108-113.
- Blanc, P., Liu, D., Juarez, C., and Boushey, H. A. Cough in hot pepper workers. Chest 1991;99(1):27-32. PubMed
- Akcay, A. B., Ozcan, T., Seyis, S., and Acele, A. Coronary vasospasm and acute myocardial infarction induced by a topical capsaicin patch. Turk.Kardiyol.Dern.Ars 2009;37(7):497-500.
- van Boxel, O. S., ter Linde, J. J., Siersema, P. D., and Smout, A. J. Role of chemical stimulation of the duodenum in dyspeptic symptom generation. Am J Gastroenterol. 2010;105(4):803-811. PubMed
- Niemcunowicz-Janica, A., Ptaszynska-Sarosiek, I., and Wardaszka, Z. [Sudden death caused by an oleoresin capsicum spray]. Arch.Med.Sadowej.Kryminol. 2009;59(3):252-254.
- Reuter, J., Merfort, I., and Schempp, C. M. Botanicals in dermatology: an evidence-based review. Am J Clin Dermatol 2010;11(4):247-267. PubMed
- McCormack, P. L. Capsaicin dermal patch: in non-diabetic peripheral neuropathic pain. Drugs 10-1-2010;70(14):1831-1842. PubMed
- Bortolotti, M. and Porta, S. Effect of red pepper on symptoms of irritable bowel syndrome: preliminary study. Dig.Dis.Sci 2011;56(11):3288-3295. PubMed
- Webster, L. R., Peppin, J. F., Murphy, F. T., Lu, B., Tobias, J. K., and Vanhove, G. F. Efficacy, safety, and tolerability of NGX-4010, capsaicin 8% patch, in an open-label study of patients with peripheral neuropathic pain. Diabetes Res Clin Pract. 2011 PubMed
- Gerber, S., Frueh, B. E., and Tappeiner, C. Conjunctival proliferation after a mild pepper spray injury in a young child. Cornea 2011;30(9):1042-1044. PubMed
- Lim, L. G., Tay, H., and Ho, K. Y. Curry induces acid reflux and symptoms in gastroesophageal reflux disease. Dig.Dis.Sci 2011;56(12):3546-3550. PubMed
- Ludy, M. J., Moore, G. E., and Mattes, R. D. The effects of capsaicin and capsiate on energy balance: critical review and meta-analyses of studies in humans. Chem Senses 2012;37(2):103-121. PubMed
- Sayin, M. R., Karabag, T., Dogan, S. M., Akpinar, I., and Aydin, M. A case of acute myocardial infarction due to the use of cayenne pepper pills. Wien.Klin.Wochenschr. 2012;124(7-8):285-287. PubMed
- Bley, K., Boorman, G., Mohammad, B., McKenzie, D., and Babbar, S. A comprehensive review of the carcinogenic and anticarcinogenic potential of capsaicin. Toxicol.Pathol. 2012;40(6):847-873. PubMed
- Derry, S. and Moore, R. A. Topical capsaicin (low concentration) for chronic neuropathic pain in adults. Cochrane.Database.Syst.Rev. 2012;9:CD010111. PubMed
- Tominack, R. L. and Spyker, D. A. Capsicum and capsaicin--a review: case report of the use of hot peppers in child abuse. J.Toxicol.Clin.Toxicol. 1987;25(7):591-601. PubMed
- Schuurs, A. H., Abraham-Inpijn, L., van Straalen, J. P., and Sastrowijoto, S. H. An unusual case of black teeth. Oral Surg.Oral Med.Oral Pathol. 1987;64(4):427-431. PubMed
- Kumar, N., Vij, J. C., Sarin, S. K., and Anand, B. S. Do chillies influence healing of duodenal ulcer? Br.Med.J.(Clin.Res.Ed) 6-16-1984;288(6433):1803-1804. PubMed
- Steffee, C. H., Lantz, P. E., Flannagan, L. M., Thompson, R. L., and Jason, D. R. Oleoresin capsicum (pepper) spray and "in-custody deaths". Am.J.Forensic Med.Pathol. 1995;16(3):185-192. PubMed
- Knight, T. E. and Hayashi, T. Solar (brachioradial) pruritus--response to capsaicin cream. Int.J.Dermatol. 1994;33(3):206-209. DOI
- Watson, W. A., Stremel, K. R., and Westdorp, E. J. Oleoresin capsicum (Cap-Stun) toxicity from aerosol exposure. Ann.Pharmacother. 1996;30(7-8):733-735. PubMed
- Busker, R. W. and van Helden, H. P. Toxicologic evaluation of pepper spray as a possible weapon for the Dutch police force: risk assessment and efficacy. Am.J.Forensic Med.Pathol. 1998;19(4):309-316. PubMed
- Sausenthaler, S., Koletzko, S., Schaaf, B., Lehmann, I., Borte, M., Herbarth, O., von Berg, A., Wichmann, H. E., and Heinrich, J. Maternal diet during pregnancy in relation to eczema and allergic sensitization in the offspring at 2 y of age. Am J Clin Nu PubMed
- Bleuel I, Zinkernagel M, Tschopp M, Tappeiner C. Association of bilateral acute anterior uveitis with a capsaicin patch. Ocul Immunol Inflamm 2013;21(5):394-5. PubMed
- Casanueva B, Rodero B, Quintial C, Llorca J, González-Gay MA. Short-term efficacy of topical capsaicin therapy in severely affected fibromyalgia patients. Rheumatol Int 2013;33(10):2665-70. PubMed
- Copeland S, Nugent K. Persistent respiratory symptoms following prolonged capsaicin exposure. Int J Occup Environ Med. 2013;4(4):211-5.
- García-Menaya JM, Cordobés -Durán C, Bobadilla-González P, et al. Anaphylactic reaction to bell pepper (Capsicum annuum) in a patient with a latex-fruit syndrome. Allergol Immunopathol (Madr). 2014;42(3):263-5. PubMed
- Kim DH, Yoon KB, Park S, et al. Comparison of NSAID patch given as monotherapy and NSAID patch in combination with transcutaneous electric nerve stimulation, a heating pad, or topical capsaicin in the treatment of patients with myofascial pain syndrome o
- Kulkantrakorn K, Lorsuwansiri C, Meesawatsom P. 0.025% capsaicin gel for the treatment of painful diabetic neuropathy: a randomized, double-blind, crossover, placebo-controlled trial. Pain Pract. 2013;13(6):497-503. PubMed
- Pabalan N, Jarjanazi H, Ozcelik H. The impact of capsaicin intake on risk of developing gastric cancers: a meta-analysis. J Gastrointest Cancer. 2014;45(3):334-41. PubMed
- Sandor B, Papp J, Mozsik G, et al. Orally given gastroprotective capsaicin does not modify aspirin-induced platelet aggregation in healthy male volunteers (human phase I examination). Acta Physiol Hung. 2014 Dec;101(4):429-37. PubMed
- Van Nooten F, Treur M, Pantiri K, Stoker M, Charokopou M. Capsaicin 8% patch versus oral neuropathic pain medications for the treatment of painful diabetic peripheral neuropathy: a systematic literature review and network meta-analysis. Clin Ther. 2017 Ap PubMed
- Simpson DM, Robinson-Papp J, Van J, et al. Capsaicin 8% patch in painful diabetic peripheral neuropathy: a randomized, double-blind, placebo-controlled study. J Pain. 2017 Jan;18(1):42-53. PubMed
- Campbell CM, Diamond E, Schmidt WK, et al. A randomized, double-blind, placebo-controlled trial of injected capsaicin for pain in Morton's neuroma. Pain. 2016 Jun;157(6):1297-304. PubMed
- Jorgensen MR, Pedersen AM. Analgesic effect of topical oral capsaicin gel in burning mouth syndrome. Acta Odontol Scand. 2017 Mar;75(2):130-6.
- Yuan LJ, Qin Y, Wang L, et al. Capsaicin-containing chili improved postprandial hyperglycemia, hyperinsulinemia, and fasting lipid disorders in women with gestational diabetes mellitus and lowered the incidence of large-for-gestational-age newborns. Clin PubMed
- Dean DJ, Sabagha N, Rose K, et al. A pilot trial of topical capsaicin cream for treatment of cannabinoid hyperemesis syndrome. Acad Emerg Med. 2020;27(11):1166-1172. PubMed
- Jang HH, Lee J, Lee SH, Lee YM. Effects of Capsicum annuum supplementation on the components of metabolic syndrome: a systematic review and meta-analysis. Sci Rep. 2020;10(1):20912. PubMed
- Joseph MSc A, John PhD F, Thomas MSc JV, Sivadasan SDP, Maliakel PhD B, Mohan PhD R, I M K. Influence of a novel food-grade formulation of red chili extract (Capsicum annum) on overweight subjects: Randomized, double-blinded, placebo-controlled study. J D
- Kocak AO, Dogruyol S, Akbas I, et al. Comparison of topical capsaicin and topical piroxicam in the treatment of acute trauma-induced pain: A randomized double-blind trial. Am J Emerg Med. 2020;38(9):1767-1771. PubMed
- Lassen CL, Meyer K, Bredthauer A, Klier TW. Facial and oral cross-contamination of a 3-year-old child with high concentration capsaicin: A case report. A A Pract. 2020;14(9):e01258. PubMed
- Predel HG, Ebel-Bitoun C, Peil B, Weiser TW, Lange R. Efficacy and safety of diclofenac?+?capsaicin gel in patients with acute back/neck pain: A multicenter randomized controlled study. Pain Ther. 2020;9(1):279-296. PubMed
- Umigai N, Kozai Y, Saito T, Takara T. Effects of paprika carotenoid supplementation on bone turnover in postmenopausal women: a randomized, double-blind, placebo-controlled, parallel-group comparison study. Food Nutr Res. 2020;64. PubMed
- Trin K, Perino J, Allouchery M, Géniaux H, Miremont G, Salvo F. Second-degree burn induced by high-concentration topical capsaicin with mobility sequelae: A case report. Pain Pract 2023;23(2):216-219. PubMed
Vitamin B6 32 references
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Geerling BJ, Dagnelie PC, Badart-Smook A, et al. Diet as a risk factor for the development of ulcerative colitis. Am J Gastroenterol 2000;95:1008-13. PubMed
- South M. Neonatal seizures after pyridoxine use -- reply. Lancet 1999;354:2083. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Baxter P, Aicardi J. Neonatal seizures after pyridoxine use. Lancet 1999;354:2082-3. PubMed
- Bendich A, Cohen M. Vitamin B6 safety issues. Ann N Y Acad Sci 1990;585:321-30.
- Schaumburg H, Kaplan J, Windebank A. Sensory neuropathy from pyridoxine abuse. A new megavitamin syndrome. N Engl J Med 1983;309:445-8. PubMed
- Gordon N. Pyridoxine dependency: an update. Dev Med Child Neurol 1997;39:63-5. PubMed
- Lewis PJ. Pain in the hand and wrist. Pyridoxine supplements may help patients with carpal tunnel syndrome. BMJ 1995;310:1534. PubMed
- Kaufman G. Pyridoxine against amiodarone-induced photosensitivity (letter). Lancet 1984;1:51-2. PubMed
- Mulrow JP, Mulrow CD, McKenna WJ. Pyridoxine and amiodarone-induced photosensitivity. Ann Intern Med 1985;103:68-9. PubMed
- Kawada A, Kashima A, Shiraishi H, et al. Pyridoxine-induced photosensitivity and hypophosphatasia. Dermatology 2000;201:356-60.. PubMed
- Vasile A, Goldberg R, Kornberg B. Pyridoxine toxicity: report of a case. J Am Osteopath Assoc 1984;83:790-1. DOI
- Hansson O, Sillanpaa M. Pyridoxine and serum concentration of phenytoin and phenobarbitone. Lancet 1976;1:256. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Hatzitolios, A., Iliadis, F., Katsiki, N., and Baltatzi, M. Is the anti-hypertensive effect of dietary supplements via aldehydes reduction evidence based? A systematic review. Clin Exp.Hypertens. 2008;30(7):628-639. PubMed
- Vasdev, S., Ford, C. A., Parai, S., Longerich, L., and Gadag, V. Dietary vitamin B6 supplementation attenuates hypertension in spontaneously hypertensive rats. Mol.Cell Biochem. 1999;200(1-2):155-162.
- de, Vogel S., Dindore, V., van, Engeland M., Goldbohm, R. A., van den Brandt, P. A., and Weijenberg, M. P. Dietary folate, methionine, riboflavin, and vitamin B-6 and risk of sporadic colorectal cancer. J Nutr 2008;138(12):2372-2378. PubMed
- Hagen, I., Nesheim, B. I., and Tuntland, T. No effect of vitamin B-6 against premenstrual tension. A controlled clinical study. Acta Obstet.Gynecol.Scand. 1985;64(8):667-670. PubMed
- Aybak, M., Sermet, A., Ayyildiz, M. O., and Karakilcik, A. Z. Effect of oral pyridoxine hydrochloride supplementation on arterial blood pressure in patients with essential hypertension. Arzneimittelforschung. 1995;45(12):1271-1273.
- Lal, K. J., Dakshinamurti, K., and Thliveris, J. The effect of vitamin B6 on the systolic blood pressure of rats in various animal models of hypertension. J Hypertens. 1996;14(3):355-363. PubMed
- Lauritzen CH, Reuter HD, Repges R, Bohnert K, and Schmidt U. Treatment of premenstrual tension syndrome with Vitex agnus castus. Controlled, double-blind study versus pyridoxine. Phytomed 1997;4(3):183-189. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Hoyer-Kuhn H, Kohbrok S, Volland R, Franklin J, Hero B, Beck BB, Hoppe B. Vitamin B6 in primary hyperoxaluria I: first prospective trial after 40 years of practice. Clin J Am Soc Nephrol. 2014 Mar;9(3):468-77. PubMed
- Mahmoud A, Tabassum S, Al Enazi S, et al. Amelioration of levetiracetam-induced behavioral side effects by pyridoxine. A randomized double blind controlled study. Pediatr Neurol 2021;119:15-21. PubMed
- Gupta M, Gallante B, Bamberger JN, et al. Prospective randomized evaluation of idiopathic hyperoxaluria treatments. J Endourol 2021;35(12):1844-1851. PubMed
- Li H, Chen M, Liang S, et al. Excessive vitamin B6 during treatment is related to poor prognosis of patients with nasopharyngeal carcinoma: A U-shaped distribution suggests low dose supplement. Clin Nutr 2021;40(4):2293-2300. PubMed
- Tanigawa J, Nabatame S, Tominaga K, et al. High-dose pyridoxine treatment for inherited glycosylphosphatidylinositol deficiency. Brain Dev 2021;43(6):680-687. PubMed
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
Ginger 64 references
- Fischer-Rasmussen W, Kjaer SK, Dahl C, Asping U. Ginger treatment of hyperemesis gravidarum. Eur J Obstet Gynecol Reprod Biol 1991;38:19-24. PubMed
- Jewell D, Young G. Interventions for nausea and vomiting in early pregnancy. Cochrane Database Syst Rev 2000;(2):CD000145. PubMed
- Vutyavanich T, Kraisarin T, Ruangsri R. Ginger for nausea and vomiting in pregnancy: randomized, double-masked, placebo-controlled trial. Obstet Gynecol 2001;97:577-82. DOI
- Backon J. Ginger in preventing nausea and vomiting of pregnancy; a caveat due to its thromboxane synthetase activity and effect on testosterone binding. Eur J Obstet Gynecol Reprod Biol 1991;42:163-4. PubMed
- Srivastava KC. Effect of onion and ginger consumption on platelet thromboxane production in humans. Prostaglandins Leukot Essent Fatty Acids 1989;35:183-5. PubMed
- Stewart JJ, Wood MJ, Wood CD, Mims ME. Effects of ginger on motion sickness susceptibility and gastric function. Pharmacology 1991;42:111-20. PubMed
- Smith C, Crowther C, Willson K, et al. A randomized controlled trial of ginger to treat nausea and vomiting in pregnancy. Obstet Gynecol 2004;103:639-45. PubMed
- Portnoi G, Chng LA, Karimi-Tabesh L, et al. Prospective comparative study of the safety and effectiveness of ginger for the treatment of nausea and vomiting in pregnancy. Am J Obstet Gynecol 2003;189:1374-7.. PubMed
- Wigler I, Grotto I, Caspi D, Yaron M. The effects of Zintona EC (a ginger extract) on symptomatic gonarthritis. Osteoarthritis Cartilage 2003;11:783-9. PubMed
- Ghayur MN, Gilani AH. Ginger lowers blood pressure through blockade of voltage-dependent calcium channels. J Cardiovasc Pharmacol 2005;45:74-80. PubMed
- Thomson M, Al-Qattan KK, Al-Sawan SM, et al. The use of ginger (Zingiber officinale Rosc.) as a potential anti-inflammatory and antithrombotic agent. Prostaglandins Leukot Essent Fatty Acids 2002;67:475-8. PubMed
- Kanerva L, Estlander T, Jolanki R. Occupational allergic contact dermatitis from spices. Contact Dermatitis 1996;35:157-62. PubMed
- Akhani SP, Vishwakarma SL, Goyal RK. Anti-diabetic activity of Zingiber officinale in streptozotocin-induced type I diabetic rats. J Pharm Pharmacol 2004;56:101-5.
- Kruth P, Brosi E, Fux R, et al. Ginger-associated overanticoagulation by phenprocoumon. Ann Pharmacother 2004;38:257-60. PubMed
- Jiang X, Williams KM, Liauw WS, et al. Effect of ginkgo and ginger on the pharmacokinetics and pharmacodynamics of warfarin in healthy subjects. Br J Clin Pharmacol 2005;59:425-32. PubMed
- Borrelli F, Capasso R, Aviello G, et al. Effectiveness and safety of ginger in the treatment of pregnancy-induced nausea and vomiting. Obstet Gynecol 2005;105:849-56. PubMed
- Smith C, Crowther C, Wilson K et al. A randomized controlled trial of ginger to treat nausea and vomiting in pregnancy. Obstet Gynecol 2004;103:639-45. PubMed
- Jiang X, Blair EY, McLachlan AJ. Investigation of the effects of herbal medicines on warfarin response in healthy subjects: a population pharmacokinetic-pharmacodynamic modeling approach. J Clin Pharmacol 2006;46:1370-8. PubMed
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Ozgoli G, Goli M, Moattar F. Comparison of effects of ginger, mefenamic acid, and ibuprofen on pain in women with primary dysmenorrhea. J Altern Complement Med 2009;15:129-32. PubMed
- Black CD, Herring MP, Hurley DJ, O'Connor PJ. Ginger (Zingiber officinale) reduces muscle pain caused by eccentric exercise. J Pain 2010;11:894-903. PubMed
- Heitmann K, Nordeng H, Holst L. Safety of ginger use in pregnancy: results from a large population-based cohort study. Eur J Clin Pharmacol 2012 Jun 17. PubMed
- Ryan JL, Heckler CE, Roscoe JA, et al. Ginger (Zingiber officinale) reduces acute chemotherapy-induced nausea: a URCC CCOP study of 576 patients. Support Care Cancer. 2012;20:1479-89. PubMed
- Backon J. Ginger as an antiemetic: possible side effects due to its thromboxane synthetase activity. Anaesthesia. 1991;46(8):705-6.. PubMed
- Abebe W. Herbal medication: potential for adverse interactions with analgesic drugs. J Clin Pharm Ther. 2002;27:391-401. PubMed
- Argento A, Tiraferri E, Marzaloni M. [Oral anticoagulants and medicinal plants. An emerging interaction]. Ann Ital Med Int. 2000;15:139-43.
- Young HY, Liao JC, Chang YS, et al. Synergistic effect of ginger and nifedipine on human platelet aggregation: a study in hypertensive patients and normal volunteers. Am J Chin Med. 2006;34:545-51. PubMed
- Greenway FL, Liu Z, Martin CK, et al. Safety and efficacy of NT, an herbal supplement, in treating human obesity. Int J Obes (Lond). 2006;30:1737-41. PubMed
- Shalansky S, Lynd L, Richardson K, et al. Risk of warfarin-related bleeding events and supratherapeutic international normalized ratios associated with complementary and alternative medicine: a longitudinal analysis. Pharmacotherapy. 2007;27:1237-47. PubMed
- Lesho EP, Saullo L, Udvari-Nagy S. A 76-year-old woman with erratic anticoagulation. Cleve Clin J Med. 2004;71:651-6. PubMed
- Okonta JM, Uboh M, Obonga WO. Herb-Drug Interaction: A Case Study of Effect of Ginger on the Pharmacokinetic of Metronidazole in Rabbit. Indian Journal of Pharmaceutical Sciences (India) 2008;70(230):232. PubMed
- Chiang HM, Chao PD, Hsiu SL, et al. Ginger significantly decreased the oral bioavailability of cyclosporine in rats. Am J Chin Med. 2006;34:845-55. PubMed
- Bhandari U, Kanojia R, Pillai KK. Effect of ethanolic extract of Zingiber officinale on dyslipidaemia in diabetic rats. J Ethnopharmacol. 2005;97:227-30. PubMed
- Ojewole JA. Analgesic, antiinflammatory and hypoglycaemic effects of ethanol extract of Zingiber officinale (Roscoe) rhizomes (Zingiberaceae) in mice and rats. Phytother Res. 2006;20:764-72.
- Al-Amin ZM, Thomson M, Al-Qattan KK, et al. Anti-diabetic and hypolipidaemic properties of ginger (Zingiber officinale) in streptozotocin-induced diabetic rats. Br J Nutr. 2006;96:660-6.
- Islam MS, Choi H. Comparative effects of dietary ginger (Zingiber officinale) and garlic (Allium sativum) investigated in a type 2 diabetes model of rats. J Med Food. 2008;11:152-9.
- Cady RK, Goldstein J, Nett R, et al. A double-blind placebo-controlled pilot study of sublingual feverfew and ginger (LipiGesic M) in the treatment of migraine. Headache 2011;51:1078-86.
- Futrell, J. M. and Rietschel, R. L. Spice allergy evaluated by results of patch tests. Cutis 1993;52(5):288-290.
- Sripramote, M. and Lekhyananda, N. A randomized comparison of ginger and vitamin B6 in the treatment of nausea and vomiting of pregnancy. J Med Assoc.Thai. 2003;86(9):846-853.
- Lohsiriwat, S., Rukkiat, M., Chaikomin, R., and Leelakusolvong, S. Effect of ginger on lower esophageal sphincter pressure. J.Med.Assoc.Thai. 2010;93(3):366-372.
- Liu, P. H. and Ho, H. L. Ginger and drug bezoar induced small bowel obstruction. J R.Coll.Surg.Edinb. 1983;28(6):397-398.
- Maghbooli M, Golipour F, Moghimi Esfandabadi A, Yousefi M. Comparison between the efficacy of ginger and sumatriptan in the ablative treatment of the common migraine. Phytother Res 2014;28(3):412-5. PubMed
- Mahluji S, Attari VE, Mobasseri M, Payahoo L, Ostadrahimi A, Golzari SE. Effects of ginger (Zingiber officinale) on plasma glucose level, HbA1c and insulin sensitivity in type 2 diabetic patients. Int J Food Sci Nutr 2013;64(6):682-6.
- Mozaffari-Khosravi H, Talaei B, Jalali BA, Najarzadeh A, Mozayan MR. The effect of ginger powder supplementation on insulin resistance and glycemic indices in patients with type 2 diabetes: a randomized, double-blind, placebo-controlled trial. Complement PubMed
- Paramdeep G. Efficacy and tolerability of ginger (Zingiber officinale) in patients of osteoarthritis of knee. Indian J Physiol Pharmacol 2013;57(2):177-83.
- Rahnama P, Montazeri A, Huseini HF, Kianbakht S, Naseri M. Effect of Zingiber officinale R. rhizomes (ginger) on pain relief in primary dysmenorrhea: a placebo randomized trial. BMC Complement Altern Med 2012;12:92. PubMed
- Viljoen E, Visser J, Koen N, Musekiwa A. A systematic review and meta-analysis of the effect and safety of ginger in the treatment of pregnancy-associated nausea and vomiting. Nutr J 2014;13:20. PubMed
- Bartels EM, Folmer VN, Bliddal H, et al. Efficacy and safety of ginger in osteoarthritis patients: a meta-analysis of randomized placebo-controlled trials. Osteoarthritis Cartilage. 2015;23(1):13-21. PubMed
- Choi JS, Han JY, Ahn HK, et al. Assessment of fetal and neonatal outcomes in the offspring of women who had been treated with dried ginger (Zingiberis rhizoma siccus) for a variety of illnesses during pregnancy. J Obstet Gynaecol. 2015;35(2):125-30.
- Marx W, McKavanagh D, McCarthy AL, Bird R, Ried K, Chan A, Isenring L. The effect of ginger (Zingiber officinale) on platelet aggregation: A systematic literature review. PLoS One. 2015;10(10):e0141119. PubMed
- Crichton M, Marshall S, Marx W, McCarthy AL, Isenring E. Efficacy of ginger (Zingiber officinale) in ameliorating chemotherapy-induced nausea and vomiting and chemotherapy-related outcomes: A systematic review update and meta-analysis. J Acad Nutr Diet. 2 PubMed
- Martins LB, Rodrigues AMDS, Monteze NM, et al. Double-blind placebo-controlled randomized clinical trial of ginger (Zingiber officinale Rosc.) in the prophylactic treatment of migraine. Cephalalgia. 2020;40(1):88-95.
- Martins LB, Rodrigues AMDS, Rodrigues DF, Dos Santos LC, Teixeira AL, Ferreira AVM. Double-blind placebo-controlled randomized clinical trial of ginger (Zingiber officinale Rosc.) addition in migraine acute treatment. Cephalalgia. 2019;39(1):68-76.
- Ahad A, Raish M, Bin Jardan YA, Alam MA, Al-Mohizea AM, Al-Jenoobi FI. Effect of Hibiscus sabdariffa and Zingiber officinale on the antihypertensive activity and pharmacokinetic of losartan in hypertensive rats. Xenobiotica. 2020:1-11.
- Okuhira H, Nakatani Y, Furukawa F, Kanazawa N. Anaphylaxis to ginger induced by herbal medicine. Allergol Int. 2020;69(1):159-160. PubMed
- Yamprasert R, Chanvimalueng W, Mukkasombut N, Itharat A. Ginger extract versus Loratadine in the treatment of allergic rhinitis: a randomized controlled trial. BMC Complement Med Ther. 2020;20(1):116. PubMed
- Ebrahimzadeh A, Ebrahimzadeh A, Mirghazanfari SM, Hazrati E, Hadi S, Milajerdi A. The effect of ginger supplementation on metabolic profiles in patients with type 2 diabetes mellitus: a systematic review and meta-analysis of randomized controlled trials. PubMed
- Alam MA, Bin Jardan YA, Alzenaidy B, et al. Effect of Hibiscus sabdariffa and Zingiber officinale on pharmacokinetics and pharmacodynamics of amlodipine. J Pharm Pharmacol 2021;73(9):1151-60.
- Akbarzadeh E, Heydari M, Atarzadeh F, Jaladat AM. Chronic dysuria following ginger (Zingiber officinale) use: a case report. Galen Med J 2018;7:e1086. DOI
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Rostamkhani H, Veisi P, Niknafs B, Jafarabadi MA, Ghoreishi Z. The effect of zingiber officinale on prooxidant-antioxidant balance and glycemic control in diabetic patients with ESRD undergoing hemodialysis: a double-blind randomized control trial. BMC Co PubMed
- Husain I, Dale OR, Idrisi M, et al. Evaluation of the Herb-Drug Interaction (HDI) Potential of Zingiber officinale and Its Major Phytoconstituents. J Agric Food Chem. 2023;71(19):7521-7534.
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
Turmeric 102 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Sharma RA, McLelland HR, Hill KA, et al. Pharmacodynamic and pharmacokinetic study of oral Curcuma extract in patients with colorectal cancer. Clin Cancer Res 2001;7:1894-900..
- Shah BH, Nawaz Z, Pertani SA. Inhibitory effect of curcumin, a food spice from turmeric, on platelet-activating factor- and arachidonic acid-mediated platelet aggregation through inhibition of thromboxane formation and Ca2+ signaling. Biochem Pharmacol 1 PubMed
- Hata M, Sasaki E, Ota M, et al . Allergic contact dermatitis from curcumin (turmeric). Contact Dermatitis 1997;36:107-8. PubMed
- Kuttan R, Sudheeran PC, Josph CD. Turmeric and curcumin as topical agents in cancer therapy. Tumori 1987;73:29-31.. PubMed
- Thapliyal R, Deshpande SS, Maru GB. Mechanism(s) of turmeric-mediated protective effects against benzo(a)pyrene-derived DNA adducts. Cancer Lett 2002;175:79-88. PubMed
- Lee SW, Nah SS, Byon JS, et al. Transient complete atrioventricular block associated with curcumin intake. Int J Cardiol 2011;150:e50-2. PubMed
- Kuptniratsaikul V, Thanakhumtorn S, Chinswangwatanakul P, et al. Efficacy and safety of Curcuma domestica extracts in patients with knee osteoarthritis. J Altern Complement Med 2009;15:891-7.
- Carroll RE, Benya RV, Turgeon DK, et al. Phase IIa clinical trial of curcumin for the prevention of colorectal neoplasia. Cancer Prev Res (Phila) 2011;4:354-64. PubMed
- Junyaprasert, V. B., Soonthornchareonnon, N., Thongpraditchote, S., Murakami, T., and Takano, M. Inhibitory effect of Thai plant extracts on P-glycoprotein mediated efflux. Phytother.Res 2006;20(1):79-81. PubMed
- Ampasavate, C., Sotanaphun, U., Phattanawasin, P., and Piyapolrungroj, N. Effects of Curcuma spp. on P-glycoprotein function. Phytomedicine. 2010;17(7):506-512. PubMed
- Hou, X. L., Takahashi, K., Tanaka, K., Tougou, K., Qiu, F., Komatsu, K., Takahashi, K., and Azuma, J. Curcuma drugs and curcumin regulate the expression and function of P-gp in Caco-2 cells in completely opposite ways. Int.J Pharm 6-24-2008;358(1-2):224-2 PubMed
- Choi, B. H., Kim, C. G., Lim, Y., Shin, S. Y., and Lee, Y. H. Curcumin down-regulates the multidrug-resistance mdr1b gene by inhibiting the PI3K/Akt/NF kappa B pathway. Cancer Lett. 1-18-2008;259(1):111-118.
- Zhang, W., Tan, T. M., and Lim, L. Y. Impact of curcumin-induced changes in P-glycoprotein and CYP3A expression on the pharmacokinetics of peroral celiprolol and midazolam in rats. Drug Metab Dispos. 2007;35(1):110-115. PubMed
- Limtrakul, P., Chearwae, W., Shukla, S., Phisalphong, C., and Ambudkar, S. V. Modulation of function of three ABC drug transporters, P-glycoprotein (ABCB1), mitoxantrone resistance protein (ABCG2) and multidrug resistance protein 1 (ABCC1) by tetrahydrocu
- Holland, M. L., Panetta, J. A., Hoskins, J. M., Bebawy, M., Roufogalis, B. D., Allen, J. D., and Arnold, J. C. The effects of cannabinoids on P-glycoprotein transport and expression in multidrug resistant cells. Biochem.Pharmacol 4-14-2006;71(8):1146-1154 PubMed
- Tang, X. Q., Bi, H., Feng, J. Q., and Cao, J. G. Effect of curcumin on multidrug resistance in resistant human gastric carcinoma cell line SGC7901/VCR. Acta Pharmacol Sin. 2005;26(8):1009-1016. PubMed
- Nabekura, T., Kamiyama, S., and Kitagawa, S. Effects of dietary chemopreventive phytochemicals on P-glycoprotein function. Biochem.Biophys.Res Commun. 2-18-2005;327(3):866-870. PubMed
- Romiti, N., Tongiani, R., Cervelli, F., and Chieli, E. Effects of curcumin on P-glycoprotein in primary cultures of rat hepatocytes. Life Sci. 1998;62(25):2349-2358. PubMed
- Yue, G. G., Cheng, S. W., Yu, H., Xu, Z. S., Lee, J. K., Hon, P. M., Lee, M. Y., Kennelly, E. J., Deng, G., Yeung, S. K., Cassileth, B. R., Fung, K. P., Leung, P. C., and Lau, C. B. The role of turmerones on curcumin transportation and P-glycoprotein acti
- Shenouda, N. S., Zhou, C., Browning, J. D., Ansell, P. J., Sakla, M. S., Lubahn, D. B., and MacDonald, R. S. Phytoestrogens in common herbs regulate prostate cancer cell growth in vitro. Nutr.Cancer 2004;49(2):200-208. PubMed
- Appiah-Opong, R., Commandeur, J. N., Vugt-Lussenburg, B., and Vermeulen, N. P. Inhibition of human recombinant cytochrome P450s by curcumin and curcumin decomposition products. Toxicology 6-3-2007;235(1-2):83-91. PubMed
- Hou, X. L., Takahashi, K., Kinoshita, N., Qiu, F., Tanaka, K., Komatsu, K., Takahashi, K., and Azuma, J. Possible inhibitory mechanism of Curcuma drugs on CYP3A4 in 1alpha,25 dihydroxyvitamin D3 treated Caco-2 cells. Int.J Pharm 6-7-2007;337(1-2):169-177.
- Valentine, S. P., Le Nedelec, M. J., Menzies, A. R., Scandlyn, M. J., Goodin, M. G., and Rosengren, R. J. Curcumin modulates drug metabolizing enzymes in the female Swiss Webster mouse. Life Sci. 4-11-2006;78(20):2391-2398. PubMed
- Price, R. J., Scott, M. P., Giddings, A. M., Walters, D. G., Stierum, R. H., Meredith, C., and Lake, B. G. Effect of butylated hydroxytoluene, curcumin, propyl gallate and thiabendazole on cytochrome P450 forms in cultured human hepatocytes. Xenobiotica 2 PubMed
- Ganta, S., Devalapally, H., and Amiji, M. Curcumin enhances oral bioavailability and anti-tumor therapeutic efficacy of paclitaxel upon administration in nanoemulsion formulation. J Pharm Sci 2010;99(11):4630-4641. PubMed
- Lamb, S. R. and Wilkinson, S. M. Contact allergy to tetrahydrocurcumin. Contact Dermatitis 2003;48(4):227. PubMed
- Joshi, J., Ghaisas, S., Vaidya, A., Vaidya, R., Kamat, D. V., Bhagwat, A. N., and Bhide, S. Early human safety study of turmeric oil (Curcuma longa oil) administered orally in healthy volunteers. J Assoc.Physicians India 2003;51:1055-1060.
- Mahesh, T., Balasubashini, M. S., and Menon, V. P. Effect of photo-irradiated curcumin treatment against oxidative stress in streptozotocin-induced diabetic rats. J Med.Food 2005;8(2):251-255. PubMed
- Thompson, D. A. and Tan, B. B. Tetrahydracurcumin-related allergic contact dermatitis. Contact Dermatitis 2006;55(4):254-255. PubMed
- Patumraj, S., Wongeakin, N., Sridulyakul, P., Jariyapongskul, A., Futrakul, N., and Bunnag, S. Combined effects of curcumin and vitamin C to protect endothelial dysfunction in the iris tissue of STZ-induced diabetic rats. Clin Hemorheol.Microcirc. 2006;3
- Liddle, M., Hull, C., Liu, C., and Powell, D. Contact urticaria from curcumin. Dermatitis 2006;17(4):196-197. PubMed
- Juan, H., Terhaag, B., Cong, Z., Bi-Kui, Z., Rong-Hua, Z., Feng, W., Fen-Li, S., Juan, S., Jing, T., and Wen-Xing, P. Unexpected effect of concomitantly administered curcumin on the pharmacokinetics of talinolol in healthy Chinese volunteers. Eur.J Clin PubMed
- Murugan, P. and Pari, L. Influence of tetrahydrocurcumin on erythrocyte membrane bound enzymes and antioxidant status in experimental type 2 diabetic rats. J Ethnopharmacol. 9-25-2007;113(3):479-486. PubMed
- Seo, K. I., Choi, M. S., Jung, U. J., Kim, H. J., Yeo, J., Jeon, S. M., and Lee, M. K. Effect of curcumin supplementation on blood glucose, plasma insulin, and glucose homeostasis related enzyme activities in diabetic db/db mice. Mol.Nutr.Food Res 2008;5
- Weisberg, S. P., Leibel, R., and Tortoriello, D. V. Dietary curcumin significantly improves obesity-associated inflammation and diabetes in mouse models of diabesity. Endocrinology 2008;149(7):3549-3558. PubMed
- Jain, S. K., Rains, J., Croad, J., Larson, B., and Jones, K. Curcumin supplementation lowers TNF-alpha, IL-6, IL-8, and MCP-1 secretion in high glucose-treated cultured monocytes and blood levels of TNF-alpha, IL-6, MCP-1, glucose, and glycosylated hemog
- Yu, Y., Hu, S. K., and Yan, H. [The study of insulin resistance and leptin resistance on the model of simplicity obesity rats by curcumin]. Zhonghua Yu Fang Yi.Xue.Za Zhi. 2008;42(11):818-822.
- Pavithra, B. H., Prakash, N., and Jayakumar, K. Modification of pharmacokinetics of norfloxacin following oral administration of curcumin in rabbits. J Vet.Sci. 2009;10(4):293-297. PubMed
- Yan, Y. D., Kim, D. H., Sung, J. H., Yong, C. S., and Choi, H. G. Enhanced oral bioavailability of docetaxel in rats by four consecutive days of pre-treatment with curcumin. Int J Pharm 10-31-2010;399(1-2):116-120. PubMed
- Epelbaum, R., Schaffer, M., Vizel, B., Badmaev, V., and Bar-Sela, G. Curcumin and gemcitabine in patients with advanced pancreatic cancer. Nutr Cancer 2010;62(8):1137-1141. PubMed
- Madkor, H. R., Mansour, S. W., and Ramadan, G. Modulatory effects of garlic, ginger, turmeric and their mixture on hyperglycaemia, dyslipidaemia and oxidative stress in streptozotocin-nicotinamide diabetic rats. Br J Nutr 2011;105(8):1210-1217. PubMed
- Pungcharoenkul, K. and Thongnopnua, P. Effect of different curcuminoid supplement dosages on total in vivo antioxidant capacity and cholesterol levels of healthy human subjects. Phytother Res 2011;25(11):1721-1726.
- Kusuhara, H., Furuie, H., Inano, A., Sunagawa, A., Yamada, S., Wu, C., Fukizawa, S., Morimoto, N., Ieiri, I., Morishita, M., Sumita, K., Mayahara, H., Fujita, T., Maeda, K., and Sugiyama, Y. Pharmacokinetic interaction study of sulphasalazine in healthy
- Mohammadi, A., Sahebkar, A., Iranshahi, M., Amini, M., Khojasteh, R., Ghayour-Mobarhan, M., and Ferns, G. A. Effects of supplementation with curcuminoids on dyslipidemia in obese patients: a randomized crossover trial. Phytother Res 2013;27(3):374-379. PubMed
- Chuengsamarn, S., Rattanamongkolgul, S., Luechapudiporn, R., Phisalaphong, C., and Jirawatnotai, S. Curcumin extract for prevention of type 2 diabetes. Diabetes Care 2012;35(11):2121-2127. PubMed
- Goh, C. L. and Ng, S. K. Allergic contact dermatitis to Curcuma longa (turmeric). Contact Dermatitis 1987;17(3):186. PubMed
- Srivastava, R., Puri, V., Srimal, R. C., and Dhawan, B. N. Effect of curcumin on platelet aggregation and vascular prostacyclin synthesis. Arzneimittelforschung. 1986;36(4):715-717.
- Srinivasan, M. Effect of curcumin on blood sugar as seen in a diabetic subject. Indian J Med Sci 1972;26(4):269-270.
- Srivastava, K. C., Bordia, A., and Verma, S. K. Curcumin, a major component of food spice turmeric (Curcuma longa) inhibits aggregation and alters eicosanoid metabolism in human blood platelets. Prostaglandins Leukot.Essent.Fatty Acids 1995;52(4):223-227 PubMed
- Oetari, S., Sudibyo, M., Commandeur, J. N., Samhoedi, R., and Vermeulen, N. P. Effects of curcumin on cytochrome P450 and glutathione S-transferase activities in rat liver. Biochem Pharmacol 1-12-1996;51(1):39-45. PubMed
- Kiec-Swierczynska, M. and Krecisz, B. Occupational allergic contact dermatitis due to curcumin food colour in a pasta factory worker. Contact Dermatitis 1998;39(1):30-31. PubMed
- Van Dau N, Ngoc Ham N, Huy Khac D, and et al. The effects of a traditional drug, tumeric (Curcuma longa), and placebo on the healing of duodenal ulcer. Phytomed 1998;5(1):29-34.
- Daveluy A, Géniaux H, Thibaud L, Mallaret M, Miremont-Salamé G, Haramburu F. Probable interaction between an oral vitamin K antagonist and turmeric (Curcuma longa). Therapie. 2014 Nov-Dec;69(6):519-20. PubMed
- Kuptniratsaikul V, Dajpratham P, Taechaarpornkul W, Buntragulpoontawee M, Lukkanapichonchut P, Chootip C, Saengsuwan J, Tantayakom K, Laongpech S. Efficacy and safety of Curcuma domestica extracts compared with ibuprofen in patients with knee osteoarthrit
- Madhu K, Chanda K, Saji MJ. Safety and efficacy of Curcuma longa extract in the treatment of painful knee osteoarthritis: a randomized placebo-controlled trial. Inflammopharmacology 2013;21(2):129-36. PubMed
- Mali AM, Behal R, Gilda SS. Comparative evaluation of 0.1% turmeric mouthwash with 0.2% chlorhexidine gluconate in prevention of plaque and gingivitis: A clinical and microbiological study. J Indian Soc Periodontol 2012;16(3):386-91. PubMed
- Sanmukhani J, Satodia V, Trivedi J, Patel T, Tiwari D, Panchal B, Goel A, Tripathi CB. Efficacy and safety of curcumin in major depressive disorder: a randomized controlled trial. Phytother Res 2014;28(4):579-85. PubMed
- Nayeri A, Wu S, Adams E, et al. Acute Calcineurin Inhibitor Nephrotoxicity Secondary to Turmeric Intake: A Case Report. Transplant Proc. 2017;49(1):198-200. PubMed
- Mitchell TM. Correspondence re: Somasundaram et al., Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2003;63(16):5165-6; author reply 5166-7.
- Somasundaram S, Edmund NA, Moore DT, Small GW, Shi YY, Orlowski RZ. Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2002;62(13):3868-75.
- Haroyan A, Mukuchyan V, Mkrtchyan N, et al. Efficacy and safety of curcumin and its combination with boswellic acid in osteoarthritis: a comparative, randomized, double-blind, placebo-controlled study. BMC Complement Altern Med. 2018;18(1):7. PubMed
- Al-Karawi D, Al Mamoori DA, Tayyar Y. The role of curcumin administration in patients with major depressive disorder: Mini meta-analysis of clinical trials. Phytother Res. 2016;30(2):175-83. PubMed
- Neerati P, Devde R, Gangi AK. Evaluation of the effect of curcumin capsules on glyburide therapy in patients with type-2 diabetes mellitus. Phytother Res. 2014;28(12):1796-800. PubMed
- Simental-Mendía LE, Pirro M, Gotto AM Jr, et al. Lipid-modifying activity of curcuminoids: A systematic review and meta-analysis of randomized controlled trials. Crit Rev Food Sci Nutr. 2017:1-10. PubMed
- Fung FY, Wong WH, Ang SK, et al. A randomized, double-blind, placebo- controlled study on the anti-haemostatic effects of Curcuma longa, Angelica sinensis and Panax ginseng. Phytomedicine. 2017;32:88-96. PubMed
- Small GW, Siddarth P, Li Z, et al. Memory and brain amyloid and tau effects of a bioavailable form of curcumin in non-demented adults: A double-blind, placebo-controlled 18-month trial. Am J Geriatr Psychiatry. 2018;26(3):266-277.
- Cruz-Correa M, Hylind LM, Marrero JH, et al. Efficacy and safety of curcumin in treatment of intestinal adenomas in patients with familial adenomatous polyposis. Gastroenterology. 2018 May 23. Pii:S0016-5085(18)34564-5. [Epub ahead of print] PubMed
- Rahmani S, Asgary S, Askari G, et al. Treatment of non-alcoholic fatty liver disease with curcumin: a randomized placebo-controlled trial. Phytother Res. 2016 Sep;30(9):1540-8. PubMed
- Lopez-Villafuerte L, CLores KH. Contact dermatitis caused by turmeric in a massage oil. Contact Dermatitis. 2016 Jul;75(1):52-3. PubMed
- Lukefahr AL, McEvoy S, Alfafara C, Funk JL. Drug-induced autoimmune hepatitis associated with turmeric dietary supplement use. BMJ Case Rep. 2018. pii: bcr-2018-224611. PubMed
- Medsafe Safety Communication- Turmeric/Curcumin Interaction with Warfarin. April 30, 2018. Accessed at: https://medsafe.govt.nz/safety/EWS/2018/Turmeric.asp.
- Imam Z, Khasawneh M, Jomaa D, Iftikhar H, Sayedahmad Z. Drug induced liver injury attributed to a curcumin supplement. Case Rep Gastrointest Med 2019 Oct 20;2019:6029403. doi: 10.1155/2019/6029403. PubMed
- Chand S, Hair C, Beswick L. A rare case of turmeric-induced hepatotoxicity. Intern Med J. 2020;50(2):258-259. PubMed
- Jiang N, Zhang M, Meng X, Sun B. Effects of Curcumin on the Pharmacokinetics of Amlodipine in Rats and Its Potential Mechanism. Pharm Biol. 2020;58(1):465-468. PubMed
- Lee BS, Bhatia T, Chaya CT, Wen R, Taira MT, Lim BS. Autoimmune Hepatitis Associated With Turmeric Consumption. ACG Case Rep J. 2020;7(3):e00320. PubMed
- Lombardi N, Crescioli G, Maggini V, et al. Acute liver injury following turmeric use in Tuscany: an analysis of the Italian Phytovigilance database and systematic review of case reports. Br J Clin Pharmacol. 2020. PubMed
- Suhail FK, Masood U, Sharma A, John S, Dhamoon A. Turmeric supplement induced hepatotoxicity: a rare complication of a poorly regulated substance. Clin Toxicol (Phila). 2020;58(3):216-217. PubMed
- Nakagawa Y, Mukai S, Yamada S, et al. The efficacy and safety of highly-bioavailable curcumin for treating knee osteoarthritis: a 6-month open-labeled prospective study. Clin Med Insights Arthritis Musculoskelet Disord. 2020;13:1179544120948471. PubMed
- Shafabakhsh R, Asemi Z, Reiner Z, Soleimani A, Aghadavod E, Bahmani F. The effects of nano-curcumin on metabolic status in patients with diabetes on hemodialysis, a randomized, double blind, placebo-controlled trial. Iran J Kidney Dis. 2020;14(4):290-9.
- Allegri P, Rosa R, Masala A, et al. Clinical effectiveness of a new oral curcumin formulation in acute non-infectious uveitic macular edema: a 12-month observational study. Eur Rev Med Pharmacol Sci 2022;26(1):46-53.
- Tsai IC, Hsu CW, Chang CH, Tseng PT, Chang KV. The effect of curcumin differs on individual cognitive domains across different patient populations: A systematic review and meta-analysis. Pharmaceuticals (Basel) 2021;14(12):1235. PubMed
- Alam MA, Bin Jardan YA, Raish M, Al-Mohizea AM, Ahad A, Al-Jenoobi FI. Herb-drug interaction: Pharmacokinetics and pharmacodynamics of anti-hypertensive drug amlodipine besylate in presence of lepidium sativum and curcuma longa. Xenobiotica 2022;1-9.
- Sohal A, Alhankawi D, Sandhu S, Chintanaboina J. Turmeric-induced hepatotoxicity: Report of 2 cases. Int Med Case Rep J 2021;14:849-852. PubMed
- Hussaarts KGAM, Hurkmans DP, Oomen-de Hoop E, et al. Impact of curcumin (with or without piperine) on the pharmacokinetics of tamoxifen. Cancers (Basel). 2019;11(3):403. PubMed
- Kalluru H, Mallayasamy SR, Kondaveeti SS, Chandrasekhar V, Kalachaveedu M. Effect of turmeric supplementation on the pharmacokinetics of paclitaxel in breast cancer patients: A study with population pharmacokinetics approach. Phytother Res 2022;36(4):1761 PubMed
- 109288 Halegoua-DeMarzio D, Navarro V, Ahmad J, et al. Liver injury associated with turmeric-A growing problem: Ten cases from the drug-induced liver injury network [DILIN]. Am J Med. 2022:S0002-9343(22)00740-9. PubMed
- Arzallus T, Izagirre A, Castiella A, Torrente S, Garmendia M, Zapata EM. Drug induced autoimmune hepatitis after turmeric intake. Gastroenterol Hepatol 2023. PubMed
- Gilad O, Rosner G, Ivancovsky-Wajcman D, et al. Efficacy of wholistic turmeric supplement on adenomatous polyps in patients with familial adenomatous polyposis-A randomized, double-blinded, placebo-controlled study. Genes (Basel) 2022;13(12):2182. PubMed
- Ahad A, Raish M, Abdelrahman IA, et al. Changes in pharmacokinetics and pharmacodynamics of losartan in experimental diseased rats treated with Curcuma longa and Lepidium sativum. Pharmaceuticals (Basel) 2022;16(1):33. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
- Kou H, Huang L, Jin M, He Q, Zhang R, Ma J. Effect of curcumin on rheumatoid arthritis: a systematic review and meta-analysis. Front Immunol 2023;14:1121655. PubMed
- Qiu L, Gao C, Wang H, et al. Effects of dietary polyphenol curcumin supplementation on metabolic, inflammatory, and oxidative stress indices in patients with metabolic syndrome: a systematic review and meta-analysis of randomized controlled trials. Front PubMed
- Sato T, Yagi A, Yamauchi M, et al. The use of an antioxidant enables accurate evaluation of the interaction of curcumin on organic anion-transporting polypeptides 4C1 by preventing auto-oxidation. Int J Mol Sci 2024;25(2):991. PubMed
- Washington O, Robinson E, Simh D, et al. Oxalate nephropathy and chronic turmeric supplementation: a case report. J Bras Nefrol 2024;46(1):99-106. PubMed
- Munshi R, Karande-Patil S, Kumbhar D, Deshmukh A, Hingorani L. A randomized, controlled, comparative, proof-of-concept study to evaluate the efficacy and safety of Nisha-Amalaki capsules in prediabetic patients for preventing progression to diabetes. J Ay PubMed
- Sharifi Razavi A, Mohajerani F, Niksolat F, Karimi N. Efficacy of topical curcumin on mild to moderate carpal tunnel syndrome: a randomized double-blind, placebo-controlled clinical trial. Pain Med 2024;25(5):327-333. PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. Curcumin Reduces Depression in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2414. PubMed
- Tehrani SD, Hosseini A, Shahzamani M, et al. Evaluation of the effectiveness of curcumin and piperine co-supplementation on inflammatory factors, cardiac biomarkers, atrial fibrillation, and clinical outcomes after coronary artery bypass graft surgery. Cl PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. The Effect of Curcumin on Reducing Atherogenic Risks in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2441. PubMed
- Dibaei M, Hosseini A, Lavasani H, Kiani-Dehkordi B, Rouini M. Assessment of metabolic interaction between curcumin and tramadol using the isolated perfused rat liver. Heliyon 2024;10(15):e35070. PubMed
Rosemary 20 references
- Newall CA, Anderson LA, Philpson JD. Herbal Medicine: A Guide for Healthcare Professionals. London, UK: The Pharmaceutical Press, 1996.
- Foster S, Tyler VE. Tyler's Honest Herbal: A Sensible Guide to the Use of Herbs and Related Remedies. 3rd ed., Binghamton, NY: Haworth Herbal Press, 1993.
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Cartier LC, Lehrer A, Malo JL. Occupational asthma caused by aromatic herbs. Allergy 1996;51:647-9. DOI
- Burkhard PR, Burkhardt K, Haenggeli CA, Landis T. Plant-induced seizures: reappearance of an old problem. J Neurol 1999;246:667-70. PubMed
- Swain AR, Dutton SP, Truswell AS. Salicylates in foods. J Am Diet.Assoc 1985;85(8):950-60. DOI
- Zhu BT, Loder DP, Cai MX, et al. Dietary administration of an extract from rosemary leaves enhances the liver microsomal metabolism of endogenous estrogens and decreases their uterotropic action in CD-1 mice. Carcinogenesis 1998;19(10):1821-7. PubMed
- Debersac P, Heydel JM, Amiot MJ, et al. Induction of cytochrome P450 and/or detoxication enzymes by various extracts of rosemary: description of specific patterns. Food Chem Toxicol 2001;39(9):907-18. PubMed
- Debersac P, Vernevaut MF, Amiot MJ, et al. Effects of a water-soluble extract of rosemary and its purified component rosmarinic acid on xenobiotic-metabolizing enzymes in rat liver. Food Chem Toxicol 2001;39(2):109-17. PubMed
- Lee JJ, Jin YR, Lee JH, et al. Antiplatelet activity of carnosic acid, a phenolic diterpene from Rosmarinus officinalis. Planta Med 2007;73(2):121-7.
- Yamamoto J, Yamada K, Naemura A, et al. Testing various herbs for antithrombotic effect. Nutrition 2005;21(5):580-7. PubMed
- Naemura A, Ura M, Yamashita T, et al. Long-term intake of rosemary and common thyme herbs inhibits experimental thrombosis without prolongation of bleeding time. Thromb Res 2008;122(4):517-22. PubMed
- Lee JJ, Jin YR, Lim Y, et al. Antiplatelet activity of carnosol is mediated by the inhibition of TXA2 receptor and cytosolic calcium mobilization. Vascul Pharmacol 2006;45:148-53. PubMed
- Bakirel, T., Bakirel, U., Keles, O. U., Ulgen, S. G., and Yardibi, H. In vivo assessment of antidiabetic and antioxidant activities of rosemary (Rosmarinus officinalis) in alloxan-diabetic rabbits. J Ethnopharmacol 2-28-2008;116(1):64-73. PubMed
- Erenmemisoglu, A., Saraymen, R., and Ustun, S. Effect of a Rosmarinus officinalis leave extract on plasma glucose levels in normoglycaemic and diabetic mice. Pharmazie 1997;52(8):645-646.
- Valones MAA, Silva ICG, Gueiros LAM, Leão JC, Caldas AF Jr, Carvalho AAT. Clinical assessment of rosemary-based toothpaste (Rosmarinus officinalis Linn.): A randomized controlled double-blind study. Braz Dent J. 2019;30(2):146-151. PubMed
- Quirarte-Báez SM, Zamora-Perez AL, Reyes-Estrada CA, et al. A shortened treatment with rosemary tea (rosmarinus officinalis) instead of glucose in patients with diabetes mellitus type 2 (TSD). J Popul Ther Clin Pharmacol. 2019;26(4):e18-e28.
- Al Jamal A. Effect of rosemary (Rosmarinus officinalis) on lipid profiles and blood glucose in human diabetic patients (type-2). African J. Biochem. Res. 2014;8(8):147-50. DOI
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Black Pepper 29 references
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Bano G, Amla V, Raina RK, et al. The effect of piperine on pharmacokinetics of phenytoin in healthy volunteers. Planta Med 1987;53:568-9. PubMed
- Bano G, et al. Effect of piperine on bioavailability and pharmacokinetics of propranolol and theophylline in healthy volunteers. Eur J Clin Pharmacol 1991;41;615-7. PubMed
- Cohle SD, Trestrail JD III, Graham MA, et al. Fatal pepper aspiration. Am J Dis Child 1988;142:633-6. PubMed
- Bhardwaj RK, Glaeser H, Becquemont L, et al. Piperine, a major constituent of black pepper, inhibits human P-glycoprotein and CYP3A4. J Pharmacol Exp Ther 2002;302:645-50. PubMed
- Velpandian T, Jasuja R, Bhardwaj RK, et al. Piperine in food: interference in the pharmacokinetics of phenytoin. Eur J Drug Metab Pharmacokinet 2001;26:241-7. PubMed
- Pattanaik S, Hota D, Prabhakar S, et al. Pharmacokinetic interaction of a single dose of piperine with steady-state carbamazepine in epilepsy patients. Phytother Res 2009;23:1281-6.
- Munakata, M., Kobayashi, K., Niisato-Nezu, J., Tanaka, S., Kakisaka, Y., Ebihara, T., Ebihara, S., Haginoya, K., Tsuchiya, S., and Onuma, A. Olfactory stimulation using black pepper oil facilitates oral feeding in pediatric patients receiving long-term en
- Myers, B. M., Smith, J. L., and Graham, D. Y. Effect of red pepper and black pepper on the stomach. Am J Gastroenterol 1987;82(3):211-214.
- Raghavendra, R. H. and Naidu, K. A. Spice active principles as the inhibitors of human platelet aggregation and thromboxane biosynthesis. Prostaglandins Leukot.Essent.Fatty Acids 2009;81(1):73-78. PubMed
- Subehan, Usia, T., Kadota, S., and Tezuka, Y. Mechanism-based inhibition of human liver microsomal cytochrome P450 2D6 (CYP2D6) by alkamides of Piper nigrum. Planta Med 2006;72(6):527-532.
- Kasibhatta, R. and Naidu, M. U. Influence of piperine on the pharmacokinetics of nevirapine under fasting conditions: a randomised, crossover, placebo-controlled study. Drugs R.D. 2007;8(6):383-391. PubMed
- Usia, T., Iwata, H., Hiratsuka, A., Watabe, T., Kadota, S., and Tezuka, Y. CYP3A4 and CYP2D6 inhibitory activities of Indonesian medicinal plants. Phytomedicine. 2006;13(1-2):67-73. PubMed
- Mujumdar, A. M., Dhuley, J. N., Deshmukh, V. K., Raman, P. H., Thorat, S. L., and Naik, S. R. Effect of piperine on pentobarbitone induced hypnosis in rats. Indian J Exp.Biol. 1990;28(5):486-487.
- Panda, S. and Kar, A. Piperine lowers the serum concentrations of thyroid hormones, glucose and hepatic 5'D activity in adult male mice. Horm.Metab Res. 2003;35(9):523-526. PubMed
- Lawless, H. and Stevens, D. A. Effects of oral chemical irritation on taste. Physiol Behav. 1984;32(6):995-998. PubMed
- Hiwale, A. R., Dhuley, J. N., and Naik, S. R. Effect of co-administration of piperine on pharmacokinetics of beta-lactam antibiotics in rats. Indian J Exp.Biol. 2002;40(3):277-281.
- Han, Y., Chin Tan, T. M., and Lim, L. Y. In vitro and in vivo evaluation of the effects of piperine on P-gp function and expression. Toxicol.Appl.Pharmacol. 8-1-2008;230(3):283-289. PubMed
- Sharma, P., Varma, M. V., Chawla, H. P., and Panchagnula, R. In situ and in vivo efficacy of peroral absorption enhancers in rats and correlation to in vitro mechanistic studies. Farmaco 2005;60(11-12):874-883. PubMed
- Aher, S., Biradar, S., Gopu, C. L., and Paradkar, A. Novel pepper extract for enhanced P-glycoprotein inhibition. J Pharm.Pharmacol. 2009;61(9):1179-1186. PubMed
- Zutshi, R. K., Singh, R., Zutshi, U., Johri, R. K., and Atal, C. K. Influence of piperine on rifampicin blood levels in patients of pulmonary tuberculosis. J Assoc.Physicians India 1985;33(3):223-224.
- Marotta, R. B. and Floch, M. H. Diet and nutrition in ulcer disease. Med Clin North Am 1991;75(4):967-979. PubMed
- Subehan, Usia, T., Iwata, H., Kadota, S., and Tezuka, Y. Mechanism-based inhibition of CYP3A4 and CYP2D6 by Indonesian medicinal plants. J Ethnopharmacol. 5-24-2006;105(3):449-455. PubMed
- Gimenez L, Zacharisen M. Severe pepper allergy in a young child. WMJ. 2011 Jun;110(3):138-9.
- Ren T, Yang M, Xiao M, Zhu J, Xie W, Zuo Z. Time-dependent inhibition of carbamazepine metabolism by piperine in anti-epileptic treatment. Life Sci. 2019;218:314-323. PubMed
- Thomas AB, Choudhary DC, Raje A, Nagrik SS. Pharmacokinetics and pharmacodynamic herb-drug interaction of piperine with atorvastatin in rats. J Chromatogr Sci 2021;59(4):371-80. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Lin F, Hu Y, Zhang Y, Zhao L, Zhong D, Liu J. Predicting Food-Drug Interactions between Piperine and CYP3A4 Substrate Drugs Using PBPK Modeling. Int J Mol Sci 2024;25(20):10955. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC