
Multimineral Ingredients & Drug Interactions
What is this page for?
First and foremost: checking Multimineral against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Multimineral is a dietary supplement by Clean Nutraceuticals with 15 active ingredients. Its ingredients are commonly taken for common cold and immune support, antioxidant support, skin health and collagen formation.Based on those ingredients, 1,579 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Ashwagandha Herb Extract, Turmeric Root Extract, Black Seed Extract. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Multimineral by Clean Nutraceuticals
Ask about any prescription or over-the-counter medication and we check it for interactions with Multimineral by Clean Nutraceuticals — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Multimineral by Clean Nutraceuticals
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Partial disclosure
This multimineral formula contains 15 active ingredients spanning vitamins, herbal extracts, and botanical powders. The vitamin components — vitamin C and vitamin D3 — support immune function and bone health respectively.
The herbal and plant-based actives include dandelion root extract, turmeric root extract, sea moss whole plant extract, elderberry fruit extract, manuka honey powder, burdock root extract, ashwagandha herb extract, black seed extract, apple cider vinegar powder, yellow dock powder, and two others we cannot fully assess due to limited data (bladderwrack and kelp herb extract). The product also contains sodium copper chlorophyllin, which provides mineral support.
Inactive ingredients — microcrystalline cellulose, magnesium stearate, rice flour, and a vegetarian capsule — are excipients that help form and deliver the active components.
Does it work?
Moderate evidence
Vitamin C is effective for vitamin C deficiency and possibly effective for anemia of chronic disease, atrial fibrillation, cataracts, and exercise-induced respiratory infections. Vitamin D3 is effective for familial hypophosphatemia, osteomalacia (soft bones from vitamin D deficiency), renal osteodystrophy, rickets, and hypoparathyroidism.
For the remaining ingredients in this formula — dandelion, turmeric, sea moss, elderberry, honey, burdock, ashwagandha, black seed, apple cider vinegar, and yellow dock — the evidence we hold either rates them as possibly effective for specific conditions (turmeric for depression and hay fever; ashwagandha for anxiety and stress; black seed for asthma and allergic rhinitis; honey for cough and cold sores) or as having insufficient evidence to rate. We cannot establish effectiveness for bladderwrack or kelp from the data available.
How safe is it?
Well-documented data
Vitamin C is generally well tolerated at normal doses but can cause stomach upset, diarrhea, and kidney stones at high doses above 2 grams daily. In pregnancy and breastfeeding, normal dietary amounts are fine; avoid high-dose supplements unless directed by your doctor.
Vitamin D3 is generally safe at recommended doses; very high doses over time risk toxicity with symptoms of high blood calcium. Pregnancy and breastfeeding data for vitamin D3 are not on file.
Dandelion, turmeric, sea moss, and ashwagandha are generally well tolerated but carry cautions in pregnancy and breastfeeding due to limited safety data — avoid medicinal or supplement doses during these periods. Elderberry and burdock should be avoided during pregnancy and breastfeeding.
Yellow dock can cause laxative effects and contains oxalates; avoid during pregnancy and breastfeeding. Black seed, apple cider vinegar, honey, and sodium are generally safe in food amounts at typical doses.
Bladderwrack and kelp herb extract safety data are not on file.
Meds to double-check
Major interaction found
Before taking this product, check with your pharmacist if you take diuretics or digoxin (both Major risk with yellow dock), warfarin or other blood thinners, heart rhythm medications like verapamil or diltiazem, diabetes or blood pressure drugs, thyroid hormones, chemotherapy agents, immunosuppressants, or lithium. Minor interactions are documented with some antidiabetes drugs and antiplatelet medications.
The bottom line
Scorecard at a glancePartially disclosed formula with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
This multimineral is suited for people looking to supplement basic vitamins and minerals with herbal support, but it's not for everyone. If you take any blood thinners, heart medications, diabetes drugs, thyroid hormones, antidepressants, or blood pressure medications — or if you're pregnant or breastfeeding — talk to your pharmacist or doctor before starting.
Yellow dock and several other ingredients carry serious interaction risks with common medications.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 15 of 15 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jun 25, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Multimineral, straight from the product label.
| Brand | Clean Nutraceuticals |
|---|---|
| Barcode (UPC) | X003EQ6LI3 |
| Net contents | 60 Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Jun 25, 2025 |
| DSLD ID | 332695 |
| Product type | Other Combinations |
| Supplement form | Capsule |
| Dietary claims / uses | Nutrient, All Other |
| Intended target group(s) | Adult (18 - 50 Years) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
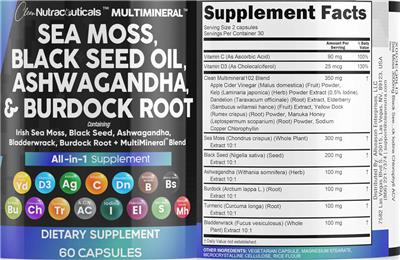
Supplement Facts
The label details for Multimineral by Clean Nutraceuticals, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin C | 90 mg | 100% |
| Vitamin D3 | 25 mcg | 130% |
| Dandelion Root Extract | 0 NP | -- |
| Turmeric Root Extract | 100 mg | -- |
| Sodium Copper Chlorophyllin | 0 NP | -- |
| Sea Moss Whole Plant Extract | 300 mg | -- |
| Elderberry Fruit Extract | 0 NP | -- |
| Manuka Honey, Powder | 0 NP | -- |
| Burdock Root Extract | 100 mg | -- |
| Ashwagandha Herb Extract | 100 mg | -- |
| Bladderwrack Whole Plant Extract | 100 mg | -- |
| Black Seed Extract | 200 mg | -- |
| Apple Cider Vinegar, Powder | 0 NP | -- |
| Yellow Dock, Powder | 0 NP | -- |
| Clean Multimineral 102 Blend | 350 mg | -- |
| Kelp Herb Extract, Powder | 0 NP | -- |
Other ingredients: Vegetarian Capsule, Magnesium Stearate, Microcrystalline Cellulose, Rice Flour
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formula
Sea Moss, Black Seed Oil, Ashwagandha, & Burdock Root Containing: Irish Sea Moss, Black Seed, Ashwagandha, Bladderwrack, Burdock Root + Multimineral blend
Yellow Dock Yd Vitamin D3 Ashwa AG Vitamin C Dandelion Dn Bladderwrack B Black Seed Bs Burdock Bu Chlorophyll Ch Turmeric Tr A.C.V. Ac Iodine I Elderberry El Sea Moss S Manuka honey Mh
Sea Moss 3000 mg Black see...ck Iodine Chlorophyll ACV
Formulation
All-in-1 Supplement
FDA Statement of Identity
Dietary Supplement
General Statements
New
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Multimineral by Clean Nutraceuticals label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Multimineral by Clean Nutraceuticals
These are the 15 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Capsule(s) Dosage formCapsule Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsVitamin D3
Interacts with715 drugs
Vitamin D is a fat-soluble vitamin that helps your body absorb calcium and is important for healthy bones, muscles, and immune function. Many people,...
Vitamin D3 monograph & interactionsTurmeric Root Extract
Interacts with1,133 drugs
Turmeric is a popular spice whose main active compounds, curcuminoids, are studied mostly for inflammation and joint pain. Some research is promising,...
Turmeric Root Extract monograph & interactionsSea Moss Whole Plant Extract
Interacts with22 drugs
Sea moss is a type of red seaweed that is naturally rich in iodine and several minerals, and it is popular as a 'whole-food' supplement. Strong human...
Sea Moss Whole Plant Extract monograph & interactionsBurdock Root Extract
Interacts with122 drugs
Burdock is a traditional herb most often used for skin problems and as a so-called 'blood purifier,' but high-quality human studies are lacking and mo...
Burdock Root Extract monograph & interactionsAshwagandha Herb Extract
Interacts with1,372 drugs
Ashwagandha is an Ayurvedic herb most often taken to help with stress, anxiety, and sleep, and some small studies suggest it may help, though the evid...
Ashwagandha Herb Extract monograph & interactionsBladderwrack Whole Plant Extract
Interacts with891 drugs
Fucus vesiculosus (bladderwrack) is a brown seaweed rich in iodine that has been used traditionally for thyroid concerns, weight, and skin. There is l...
Bladderwrack Whole Plant Extract monograph & interactionsBlack Seed Extract
Interacts with912 drugs
Black seed (Nigella sativa) is a traditional spice and remedy that has been studied for asthma, blood sugar, cholesterol, and blood pressure, with ear...
Black Seed Extract monograph & interactionsClean Multimineral 102 Blend
Other (inactive) ingredients: Vegetarian Capsule, Magnesium Stearate, Microcrystalline Cellulose, Rice Flour. These complete the product’s ingredient list but are not active constituents.
Multimineral by Clean Nutraceuticals Drug Interactions
HelloPharmacist Interaction Report
Clean Nutraceuticals Multimineral contains 15 ingredients, several of which interact with medications.
The most serious interactions involve yellow dock, which carries Major severity warnings for diuretic drugs and digoxin — both can lead to dangerous potassium loss or life-threatening heart rhythm problems if combined.
Read the full breakdown — every affected drug type, severity by severity
Vitamin C (at high doses), vitamin D3, dandelion root, turmeric, sodium copper chlorophyllin, sea moss, elderberry, manuka honey, burdock, ashwagandha, and black seed each carry Moderate severity interactions across multiple drug types. Vitamin C affects estrogens, chemotherapy drugs (alkylating agents and antitumor antibiotics), aluminum absorption, warfarin, and several others.
Vitamin D3 interacts with thiazide diuretics, heart rhythm medications (verapamil, diltiazem, digoxin), and statins. Dandelion root affects blood thinners, diabetes medications, lithium, and antibiotics.
Turmeric interacts with immunosuppressants, cancer drugs, and methotrexate. Sodium from the chlorophyllin affects blood pressure medications and lithium.
Sea moss, due to iodine content, alters thyroid medications and amiodarone. Ashwagandha and black seed both interact with blood pressure drugs, blood thinners, diabetes medications, and immunosuppressants, among others.
We could not check bladderwrack and kelp herb extract — no interaction data is on file for these ingredients. Altogether, these interactions span 1,538 individual medications.
Use the medication checker on this page to search your exact prescriptions before starting this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Multimineral?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Multimineral interact with 1,579 drugs. Click any drug to see the details.
14 of the 15 ingredients in Multimineral interact with drugs. Each result below shows which ingredient is responsible. Ashwagandha Herb Extract Turmeric Root Extract Black Seed Extract Bladderwrack Whole Plant Extract Manuka Honey, Powder Vitamin D3 Dandelion Root Extract Vitamin C Sodium Copper Chlorophyllin Apple Cider Vinegar, Powder Burdock Root Extract Elderberry Fruit Extract Yellow Dock, Powder Sea Moss Whole Plant Extract
6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Multimineral — through 4 ingredients. Tap an ingredient for the detail:
Ashwagandha Herb ExtractHepatotoxic Drugs, Immunosuppressants Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha Herb Extract + 6-mercaptopurine interactionBlack Seed ExtractImmunosuppressants Moderate
Interaction Summary
Theoretically, black seed might interfere with immunosuppressive therapy.
Read the full Black Seed Extract + 6-mercaptopurine interactionTurmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + 6-mercaptopurine interactionElderberry Fruit ExtractImmunosuppressants Moderate
Interaction Summary
Theoretically, elderberry might interfere with immunosuppressant therapy due to its immunostimulant activity.
Read the full Elderberry Fruit Extract + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Multimineral — through 5 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Ado-trastuzumab Emtansine interactionAshwagandha Herb ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha Herb Extract + Ado-trastuzumab Emtansine interactionKelp Herb Extract, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP3A4 substrates might increase the risk for adverse effects.
Read the full Kelp Herb Extract, Powder + Ado-trastuzumab Emtansine interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Ado-trastuzumab Emtansine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with Multimineral — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAshwagandha Herb ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha Herb Extract + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with Multimineral — through 2 ingredients. Tap an ingredient for the detail:
Ashwagandha Herb ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha Herb Extract + Abacavir, Lamivudine interactionTurmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Abacavir, Lamivudine interactionAbciximabReoPro
How Abciximab interacts with Multimineral — through 6 ingredients. Tap an ingredient for the detail:
Black Seed ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black seed may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Black Seed Extract + Abciximab interactionDandelion Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion Root Extract + Abciximab interactionTurmeric Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Abciximab interactionBurdock Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking burdock with anticoagulant or antiplatelet drugs might increase the risk of bleeding.
Read the full Burdock Root Extract + Abciximab interactionManuka Honey, PowderAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, honey may increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Manuka Honey, Powder + Abciximab interactionKelp Herb Extract, PowderAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, taking Fucus vesiculosus with antiplatelet or anticoagulant drugs might increase the risk of bruising and bleeding.
Read the full Kelp Herb Extract, Powder + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Multimineral — through 5 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Abemaciclib interactionKelp Herb Extract, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP3A4 substrates might increase the risk for adverse effects.
Read the full Kelp Herb Extract, Powder + Abemaciclib interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Abemaciclib interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Abemaciclib interactionAshwagandha Herb ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha Herb Extract + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Multimineral — through 5 ingredients. Tap an ingredient for the detail:
Ashwagandha Herb ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha Herb Extract + Abiraterone interactionTurmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Abiraterone interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Abiraterone interactionKelp Herb Extract, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP3A4 substrates might increase the risk for adverse effects.
Read the full Kelp Herb Extract, Powder + Abiraterone interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Multimineral — through 5 ingredients. Tap an ingredient for the detail:
Ashwagandha Herb ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha Herb Extract + Abiraterone Acetate interactionTurmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Abiraterone Acetate interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Abiraterone Acetate interactionKelp Herb Extract, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP3A4 substrates might increase the risk for adverse effects.
Read the full Kelp Herb Extract, Powder + Abiraterone Acetate interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Multimineral — through 8 ingredients. Tap an ingredient for the detail:
Ashwagandha Herb ExtractImmunosuppressants Moderate
Interaction Summary
Theoretically, taking ashwagandha might decrease the effects of immunosuppressants.
Read the full Ashwagandha Herb Extract + Abrocitinib interactionTurmeric Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Abrocitinib interactionDandelion Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion Root Extract + Abrocitinib interactionBlack Seed ExtractAnticoagulant/antiplatelet Drugs, Immunosuppressants +1 Moderate
Interaction Summary
Theoretically, black seed may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Black Seed Extract + Abrocitinib interactionBurdock Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking burdock with anticoagulant or antiplatelet drugs might increase the risk of bleeding.
Read the full Burdock Root Extract + Abrocitinib interactionElderberry Fruit ExtractImmunosuppressants Moderate
Interaction Summary
Theoretically, elderberry might interfere with immunosuppressant therapy due to its immunostimulant activity.
Read the full Elderberry Fruit Extract + Abrocitinib interactionManuka Honey, PowderAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, honey may increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Manuka Honey, Powder + Abrocitinib interactionKelp Herb Extract, PowderAnticoagulant/antiplatelet Drugs, Cytochrome P450 2c9 (cyp2c9) Substrates Minor
Interaction Summary
Theoretically, taking Fucus vesiculosus with antiplatelet or anticoagulant drugs might increase the risk of bruising and bleeding.
Read the full Kelp Herb Extract, Powder + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Multimineral — through 5 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Acalabrutinib interactionKelp Herb Extract, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP3A4 substrates might increase the risk for adverse effects.
Read the full Kelp Herb Extract, Powder + Acalabrutinib interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Acalabrutinib interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acalabrutinib interactionAshwagandha Herb ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha Herb Extract + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Multimineral — through 5 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs, Antidiabetes Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acarbose interactionDandelion Root ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase the risk for hypoglycemia when used with antidiabetes drugs.
Read the full Dandelion Root Extract + Acarbose interactionAshwagandha Herb ExtractAntidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Ashwagandha Herb Extract + Acarbose interactionBlack Seed ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking black seed with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Black Seed Extract + Acarbose interactionApple Cider Vinegar, PowderAntidiabetes Drugs Minor
Interaction Summary
Theoretically, taking apple cider vinegar with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Apple Cider Vinegar, Powder + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Multimineral — through 4 ingredients. Tap an ingredient for the detail:
Black Seed ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking black seed with antihypertensive drugs might increase the risk of hypotension.
Read the full Black Seed Extract + Acebutolol interactionTurmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acebutolol interactionSodium Copper ChlorophyllinAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium Copper Chlorophyllin + Acebutolol interactionAshwagandha Herb ExtractHepatotoxic Drugs, Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha Herb Extract + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Multimineral — through 6 ingredients. Tap an ingredient for the detail:
Burdock Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking burdock with anticoagulant or antiplatelet drugs might increase the risk of bleeding.
Read the full Burdock Root Extract + Acenocoumarol interactionBlack Seed ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black seed may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Black Seed Extract + Acenocoumarol interactionDandelion Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion Root Extract + Acenocoumarol interactionTurmeric Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Acenocoumarol interactionManuka Honey, PowderAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, honey may increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Manuka Honey, Powder + Acenocoumarol interactionKelp Herb Extract, PowderAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, taking Fucus vesiculosus with antiplatelet or anticoagulant drugs might increase the risk of bruising and bleeding.
Read the full Kelp Herb Extract, Powder + Acenocoumarol interactionAcepromazineAtravet
How Acepromazine interacts with Multimineral — through 2 ingredients. Tap an ingredient for the detail:
Black Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Black Seed Extract + Acepromazine interactionAshwagandha Herb ExtractCns Depressants Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ashwagandha Herb Extract + Acepromazine interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with Multimineral — through 4 ingredients. Tap an ingredient for the detail:
Ashwagandha Herb ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ashwagandha Herb Extract + Acetaminophen interactionDandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen interactionTurmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Multimineral — through 8 ingredients. Tap an ingredient for the detail:
Dandelion Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs +1 Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion Root Extract + Acetaminophen, Aspirin interactionTurmeric Root ExtractAnticoagulant/antiplatelet Drugs, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Acetaminophen, Aspirin interactionBlack Seed ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black seed may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Black Seed Extract + Acetaminophen, Aspirin interactionAshwagandha Herb ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha Herb Extract + Acetaminophen, Aspirin interactionBurdock Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking burdock with anticoagulant or antiplatelet drugs might increase the risk of bleeding.
Read the full Burdock Root Extract + Acetaminophen, Aspirin interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin interactionKelp Herb Extract, PowderAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, taking Fucus vesiculosus with antiplatelet or anticoagulant drugs might increase the risk of bruising and bleeding.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Aspirin interactionManuka Honey, PowderAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, honey may increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Manuka Honey, Powder + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Multimineral — through 9 ingredients. Tap an ingredient for the detail:
Black Seed ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black seed may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Black Seed Extract + Acetaminophen, Aspirin, Caffeine interactionDandelion Root ExtractAnticoagulant/antiplatelet Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion Root Extract + Acetaminophen, Aspirin, Caffeine interactionTurmeric Root ExtractAnticoagulant/antiplatelet Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Acetaminophen, Aspirin, Caffeine interactionBurdock Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking burdock with anticoagulant or antiplatelet drugs might increase the risk of bleeding.
Read the full Burdock Root Extract + Acetaminophen, Aspirin, Caffeine interactionAshwagandha Herb ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ashwagandha Herb Extract + Acetaminophen, Aspirin, Caffeine interactionManuka Honey, PowderAnticoagulant/antiplatelet Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey may increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Manuka Honey, Powder + Acetaminophen, Aspirin, Caffeine interactionKelp Herb Extract, PowderAnticoagulant/antiplatelet Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, taking Fucus vesiculosus with antiplatelet or anticoagulant drugs might increase the risk of bruising and bleeding.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Aspirin, Caffeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Aspirin, Caffeine interactionVitamin CAspirin, Acetaminophen (tylenol, Others) Minor
Interaction Summary
Acidification of the urine by vitamin C might increase aspirin levels.
Read the full Vitamin C + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with Multimineral — through 4 ingredients. Tap an ingredient for the detail:
Ashwagandha Herb ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha Herb Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionTurmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionDandelion Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion Root Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with Multimineral — through 4 ingredients. Tap an ingredient for the detail:
Dandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen, Butalbital interactionAshwagandha Herb ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ashwagandha Herb Extract + Acetaminophen, Butalbital interactionTurmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with Multimineral — through 7 ingredients. Tap an ingredient for the detail:
Dandelion Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion Root Extract + Acetaminophen, Butalbital, Caffeine interactionTurmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital, Caffeine interactionAshwagandha Herb ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha Herb Extract + Acetaminophen, Butalbital, Caffeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine interactionKelp Herb Extract, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP3A4 substrates might increase the risk for adverse effects.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Butalbital, Caffeine interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Acetaminophen, Butalbital, Caffeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Multimineral — through 8 ingredients. Tap an ingredient for the detail:
Ashwagandha Herb ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ashwagandha Herb Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionDandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionTurmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionBlack Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Black Seed Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine, Codeine interactionKelp Herb Extract, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP3A4 substrates might increase the risk for adverse effects.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Multimineral — through 6 ingredients. Tap an ingredient for the detail:
Black Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Black Seed Extract + Acetaminophen, Butalbital, Codeine interactionAshwagandha Herb ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha Herb Extract + Acetaminophen, Butalbital, Codeine interactionTurmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital, Codeine interactionDandelion Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion Root Extract + Acetaminophen, Butalbital, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine interactionKelp Herb Extract, PowderCytochrome P450 2d6 (cyp2d6) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP2D6 substrates might alter the effects of these substrates.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Multimineral — through 6 ingredients. Tap an ingredient for the detail:
Dandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionBlack Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Black Seed Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionTurmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionAshwagandha Herb ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ashwagandha Herb Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionKelp Herb Extract, PowderCytochrome P450 2d6 (cyp2d6) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP2D6 substrates might alter the effects of these substrates.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Butalbital, Codeine Phosphate interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Multimineral — through 8 ingredients. Tap an ingredient for the detail:
Ashwagandha Herb ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha Herb Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionDandelion Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion Root Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionTurmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionBlack Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Black Seed Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionKelp Herb Extract, PowderCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP2D6 substrates might alter the effects of these substrates.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Multimineral — through 8 ingredients. Tap an ingredient for the detail:
Black Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Black Seed Extract + Acetaminophen, Caffeine, Codeine interactionDandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen, Caffeine, Codeine interactionAshwagandha Herb ExtractCns Depressants, Hepatotoxic Drugs +2 Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ashwagandha Herb Extract + Acetaminophen, Caffeine, Codeine interactionTurmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Codeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Codeine interactionKelp Herb Extract, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP3A4 substrates might increase the risk for adverse effects.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with Multimineral — through 8 ingredients. Tap an ingredient for the detail:
Ashwagandha Herb ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ashwagandha Herb Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionBlack Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Black Seed Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionDandelion Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion Root Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionTurmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Acetaminophen, Caffeine, Codeine, Salicylamide interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Codeine, Salicylamide interactionKelp Herb Extract, PowderCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP2D6 substrates might alter the effects of these substrates.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Caffeine, Codeine, Salicylamide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with Multimineral — through 8 ingredients. Tap an ingredient for the detail:
Black Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Black Seed Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionAshwagandha Herb ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha Herb Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionTurmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionDandelion Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion Root Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Dihydrocodeine interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Acetaminophen, Caffeine, Dihydrocodeine interactionKelp Herb Extract, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP3A4 substrates might increase the risk for adverse effects.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with Multimineral — through 7 ingredients. Tap an ingredient for the detail:
Dandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen, Caffeine, Isometheptene interactionTurmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Isometheptene interactionAshwagandha Herb ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha Herb Extract + Acetaminophen, Caffeine, Isometheptene interactionKelp Herb Extract, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP3A4 substrates might increase the risk for adverse effects.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Caffeine, Isometheptene interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Acetaminophen, Caffeine, Isometheptene interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Isometheptene interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with Multimineral — through 8 ingredients. Tap an ingredient for the detail:
Black Seed ExtractSerotonergic Drugs Moderate
Interaction Summary
Theoretically, combining serotonergic drugs with black seed might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders.
Read the full Black Seed Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionDandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAshwagandha Herb ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ashwagandha Herb Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionTurmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionKelp Herb Extract, PowderCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP2D6 substrates might alter the effects of these substrates.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with Multimineral — through 8 ingredients. Tap an ingredient for the detail:
Ashwagandha Herb ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cns Depressants +3 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha Herb Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionBlack Seed ExtractCns Depressants, Serotonergic Drugs Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Black Seed Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionDandelion Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion Root Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionTurmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionManuka Honey, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Read the full Manuka Honey, Powder + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionKelp Herb Extract, PowderCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, concomitant use of Fucus vesiculosus with CYP2D6 substrates might alter the effects of these substrates.
Read the full Kelp Herb Extract, Powder + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Multimineral with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Ashwagandha Herb Extract
Antidiabetes Drugs
Theoretically, taking ashwagandha with antidiabetes drugs might increase the risk of hypoglycemia.
There is preliminary clinical evidence suggesting that ashwagandha might lower blood glucose levels. Theoretically, ashwagandha might have additive effects when used with antidiabetes drugs and increase the risk of hypoglycemia.
Antihypertensive Drugs
Theoretically, taking ashwagandha with antihypertensive drugs might increase the risk of hypotension.
Animal research suggests that ashwagandha might lower systolic and diastolic blood pressure. Theoretically, ashwagandha might have additive effects when used with antihypertensive drugs and increase the risk of hypotension.
Benzodiazepines
Theoretically, taking ashwagandha might increase the sedative effects of benzodiazepines.
There is preliminary evidence that ashwagandha might have an additive effect with diazepam (Valium) and clonazepam (Klonopin). This may also occur with other benzodiazepines.
Cns Depressants
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Ashwagandha seems to have sedative effects. Theoretically, this may potentiate the effects of barbiturates, other sedatives, and anxiolytics.
Hepatotoxic Drugs
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Ashwagandha has been linked to cases of acute hepatitis, liver failure, hepatic encephalopathy, autoimmune hepatitis, the need for liver transplantation, and death due to liver failure.
Immunosuppressants
Theoretically, taking ashwagandha might decrease the effects of immunosuppressants.
Ashwagandha has demonstrated immunostimulant effects in humans. Animal research has shown that ashwagandha can attenuate the immunosuppression caused by cyclophosphamide.
Thyroid Hormone
Ashwagandha might increase the effects and adverse effects of thyroid hormone.
Concomitant use of ashwagandha with thyroid hormones may cause additive therapeutic and adverse effects. Preliminary clinical research and animal studies suggest that ashwagandha boosts thyroid hormone synthesis and secretion. In one clinical study, ashwagandha increased triiodothyronine (T3) and thyroxine (T4) levels by 41.5% and 19.6%, respectively, and reduced serum TSH levels by 17.4% from baseline in adults with subclinical hypothyroidism.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
In vitro research shows that ashwagandha extract induces CYP1A2 enzymes.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
In vitro research shows that ashwagandha extract induces CYP3A4 enzymes.
Serotonergic Drugs
Some animal studies have reported that ashwagandha can enhance serotonergic transmission by altering certain serotonin (5-HT) receptors. However, there is no evidence to suggest that ashwagandha increases the risk of serotonin-related effects, and there have been no published case reports of serotonin syndrome when combined with other serotonergic drugs. Nevertheless, due to the lack of extensive studies on the matter and the fact that ashwagandha appears to affect serotonergic pathways, it would be prudent to exercise caution when combining it with drugs that affect serotonin. [References: - Effects of Withania somnifera (Ashwaga ndha) on Stress and the Stress-Related Neuropsychiatric Disorders Anxiety, Depression, and Insomnia. Curr Neuropharmacol. 2021 Sep 14; 19: 1468–1495. - A Prospective, Randomized Double-Blind, Placebo-Controlled Study of Safety and Efficacy of a High-Concentration Full-Spectrum Extract of Ashwagandha Root in Reducing Stress and Anxiety in Adults. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3573577/]
Turmeric Root Extract
Alkylating Agents
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research suggests that curcumin, a constituent of turmeric, inhibits mechlorethamine-induced apoptosis of breast cancer cells by up to 70%. Also, animal research shows that curcumin inhibits cyclophosphamide-induced tumor regression. However, some in vitro research shows that curcumin does not affect the apoptosis capacity of etoposide. Also, other laboratory research suggests that curcumin might augment the cytotoxic effects of alkylating agents. Reasons for the discrepancies may relate to the dose of curcumin and the specific chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have on alkylating agents.
Amlodipine (Norvasc)
Taking turmeric with amlodipine may increase levels of amlodipine.
Animal research shows that giving amlodipine 1 mg/kg as a single dose following the use of turmeric extract 200 mg/kg daily for 2 weeks increases the maximum concentration and area under the curve by 53% and 56%, respectively, when compared with amlodipine alone. Additional animal research shows that taking amlodipine 1 mg/kg with a curcumin 2 mg/kg pretreatment for 10 days increases the maximum concentration and area under the curve by about 2-fold when compared with amlodipine alone.
Anticoagulant/Antiplatelet Drugs
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs. However, research is conflicting.
Curcumin, a constituent of turmeric, has demonstrated antiplatelet effects in vitro. Furthermore, two case reports have found that taking turmeric along with warfarin or fluindione was associated with an increased international normalized ratio (INR). However, one clinical study in healthy volunteers shows that taking curcumin 500 mg daily for 3 weeks, alone or with aspirin 100 mg, does not increase antiplatelet effects or bleeding risk. It is possible that the dose of turmeric used in this study was too low to produce a notable effect.
Antidiabetes Drugs
Theoretically, taking turmeric with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research and case reports suggest that curcumin, a turmeric constituent, can reduce blood glucose levels in patients with diabetes. Furthermore, clinical research in adults with type 2 diabetes shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg decreased postprandial glucose levels for up to 24 hours when compared with glyburide alone, despite the lack of a significant pharmacokinetic interaction. Other clinical studies in patients with diabetes show that taking curcumin daily can reduce blood glucose levels when compared with placebo.
Antitumor Antibiotics
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro and animal research shows that curcumin, a constituent of turmeric, inhibits doxorubicin-induced apoptosis of breast cancer cells by up to 65%. However, curcumin does not seem to affect the apoptosis capacity of daunorubicin. In fact, some research shows that curcumin might augment the cytotoxic effects of antitumor antibiotics, increasing their effectiveness. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effects, if any, antioxidants such as turmeric have on antitumor antibiotics.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
In vitro and animal research show that turmeric and its constituents curcumin and curcuminoids inhibit CYP3A4. Also, 8 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking turmeric and cancer medications that are CYP3A4 substrates, including everolimus, ruxolitinib, ibrutinib, and palbociclib, and bortezomib. In another case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels after consuming turmeric powder at a dose of 15 or more spoonfuls daily for ten days prior. It was thought that turmeric increased levels of tacrolimus due to CYP3A4 inhibition.
Conversely, other in vitro research suggests that turmeric induces CYP3A4 activity, leading to reduced levels of CYP3A4 substrates. An animal model suggests that induction of CYP3A4 occurs after daily curcumin use for 1 week. However, the induction of CYP3A4 by turmeric has not been reported in humans.
Hepatotoxic Drugs
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
There is concern that turmeric might cause hepatotoxicity, especially when highly bioavailable formulations are used in high doses.
Methotrexate (Trexall, Others)
Theoretically, turmeric might have additive effects when used with hepatotoxic drugs such as methotrexate.
In one case report, a 39-year-old female taking methotrexate, turmeric, and linseed oil developed hepatotoxicity.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Theoretically, turmeric might increase blood levels of OATP4C1 substrates.
In vitro research shows that the turmeric constituent curcumin competitively inhibits OATP4C1 transport. This transporter is expressed in the kidney and facilitates the renal excretion of certain drugs. Theoretically, taking turmeric might decrease renal excretion of OATP substrates.
Sulfasalazine (Azulfidine)
Turmeric might increase the effects and adverse effects of sulfasalazine.
Clinical research shows that taking the turmeric constituent, curcumin, can increase blood levels of sulfasalazine by 3.2-fold.
Tacrolimus (Prograf)
Turmeric might increase the effects and adverse effects of tacrolimus.
In one case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels of 29 ng/mL. The patient previously had tacrolimus levels within the therapeutic range at 9.7 ng/mL. Ten days prior to presenting at the emergency room the patient started consumption of turmeric powder at a dose of 15 or more spoonfuls daily. It was thought that turmeric increased levels of tacrolimus due to cytochrome P450 3A4 (CYP3A4) inhibition. In vitro and animal research show that turmeric and its constituent curcumin inhibit CYP3A4.
Talinolol
Turmeric may reduce the absorption of talinolol in some situations.
Clinical research shows that taking curcumin for 6 days decreases the bioavailability of talinolol when taken together on the seventh day. The clinical significance of this effect is unclear.
Tamoxifen (Nolvadex)
Theoretically, turmeric might reduce the levels and clinical effects of tamoxifen.
In a small clinical trial in patients with breast cancer taking tamoxifen 20-30 mg daily, adding curcumin 1200 mg plus piperine 10 mg three times daily reduces the 24-hour area under the curve of tamoxifen and the active metabolite endoxifen by 12.8% and 12.4%, respectively, as well as the maximum concentrations of tamoxifen, when compared with tamoxifen alone. However, in the absence of piperine, the area under the curve for endoxifen and the maximum concentration of tamoxifen were not significantly reduced. Effects were most pronounced in patients who were extensive cytochrome P450 (CYP) 2D6 metabolizers.
Topoisomerase I Inhibitors
Turmeric has antioxidant effects. There is some concern that this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research shows that curcumin, a constituent of turmeric, inhibits camptothecin-induced apoptosis of breast cancer cells by up to 71%. However, other in vitro research shows that curcumin augments the cytotoxic effects of camptothecin. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agents. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have.
Tramadol (Ultram)
Theoretically, turmeric might increase or decrease levels of tramadol.
Animal research suggests that a single dose of curcumin, a constituent of turmeric, may increase tramadol's maximum concentration (Cmax) by inhibiting metabolism, while continued daily use for 7 days may reduce the area under the curve (AUC) due to the induction of drug-metabolizing enzymes such as cytochrome P450 3A4 (CYP3A4). However, this interaction has not been reported in humans.
Warfarin (Coumadin)
Turmeric might increase the risk of bleeding with warfarin.
One case of increased international normalized ratio (INR) has been reported for a patient taking warfarin who began taking turmeric. Prior to taking turmeric, the patient had stable INR measurements. Within a few weeks of starting turmeric supplementation, the patient's INR increased to 10. Additionally, curcumin, the active constituent in turmeric, has demonstrated antiplatelet effects in vitro, which may produce additive effects when taken with warfarin.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2. However, research is conflicting.
In vitro and animal research show that the turmeric constituent, curcumin, inhibits CYP1A2. However, other in vitro research suggests that curcumin does not significantly affect CYP1A2.
Docetaxel (Taxotere)
Theoretically, turmeric might increase blood levels of oral docetaxel.
Animal research suggests that the turmeric constituent, curcumin, enhances the oral bioavailability of docetaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
Estrogens
Theoretically, large amounts of turmeric might interfere with hormone replacement therapy through competition for estrogen receptors.
In vitro research shows that curcumin, a constituent of turmeric, displaces the binding of estrogen to its receptors.
Glyburide (Diabeta, Others)
Theoretically, taking turmeric and glyburide in combination might increase the risk of hypoglycemia.
Clinical research shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg increases blood levels of glyburide by 12% at 2 hours after the dose in patients with type 2 diabetes. While maximal blood concentrations of glyburide were not affected, turmeric modestly decreased postprandial glucose levels for up to 24 hours when compared to glyburide alone, possibly due to the hypoglycemic effect of turmeric demonstrated in animal research.
Losartan (Cozaar)
Theoretically, turmeric might increase the effects of losartan.
Research in hypertensive rats shows that taking turmeric can increase the hypotensive effects of losartan.
Norfloxacin (Noroxin)
Theoretically, turmeric might increase the effects and adverse effects of norfloxacin.
Animal research shows that taking curcumin, a turmeric constituent, can increase blood levels of orally administered norfloxacin.
P-Glycoprotein Substrates
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
In vitro and animal research shows that curcuminoids and other constituents found in turmeric can inhibit P-glycoprotein expression and activity.
Paclitaxel (Abraxane, Onxol)
Theoretically, turmeric might alter blood levels of paclitaxel, although any effect may not be clinically relevant.
Clinical research in adults with breast cancer receiving intravenous paclitaxel suggests that taking turmeric may modestly alter paclitaxel pharmacokinetics. Patients received paclitaxel on day 1, followed by either no treatment or turmeric 2 grams daily from days 2-22. Pharmacokinetic modeling suggests that turmeric reduces the maximum concentration and area under the curve of paclitaxel by 12.1% and 7.7%, respectively. However, these changes are not likely to be considered clinically relevant. Conversely, animal research suggests that curcumin, a constituent of turmeric, enhances the oral bioavailability of paclitaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
Black Seed Extract
Anticoagulant/Antiplatelet Drugs
Theoretically, black seed may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro and animal research suggests that black seed extract can inhibit platelet aggregation and clotting, and increase bleeding time. In addition, decreased platelet counts have occurred in a human case report and in animal research.
Antidiabetes Drugs
Theoretically, taking black seed with antidiabetes drugs might increase the risk of hypoglycemia.
Some clinical research and numerous animal studies suggest that black seed, especially its constituent thymoquinone, can have hypoglycemic effects.
Antihypertensive Drugs
Theoretically, taking black seed with antihypertensive drugs might increase the risk of hypotension.
Clinical research suggests that black seed powder and oil might reduce blood pressure by 2-3 mmHg. In animal research, black seed modestly reduces blood pressure and concomitant use of black seed and amlodipine (Norvasc) or metoprolol (Lopressor) increased the blood pressure lowering effects of these drugs.
Clopidogrel (Plavix)
Theoretically, black seed may increase the risk of bleeding if used with clopidogrel.
Animal research shows that taking black seed extract daily for 2 weeks prior to a single dose of clopidogrel increases maximum concentrations of clopidogrel by approximately 31% and modestly decreases oral clearance. Furthermore, bleeding time was increased by 12%. This has not been shown in humans.
Cns Depressants
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Animal research suggests that black seed may have CNS depressant effects.
Cyclosporine (Neoral, Sandimmune)
Theoretically taking black seed might reduce the levels and clinical effects of cyclosporine.
In animal research, black seed extract decreased the maximal levels of cyclosporine in the blood by 35.5%. This has not been shown in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, black seed might increase levels of drugs metabolized by CYP2C9.
In vitro research suggests that thymoquinone, a constituent of black seed, can decrease the metabolism of phenytoin by a mechanism possibly related to the inhibition of CYP2C9. The effect of black seed on CYP2C9 is unclear. This has not been shown in humans.
Diuretic Drugs
Theoretically, taking black seed with diuretic drugs might increase potassium loss and the risk of hypokalemia.
Black seed extract has shown diuretic effects in animals, which could theoretically increase potassium loss. This has not been shown in humans.
Immunosuppressants
Theoretically, black seed might interfere with immunosuppressive therapy.
Animal and in vitro studies suggest that black seed might stimulate immune function. However, other animal studies suggest that black seed may suppress immune function.
Phenytoin (Dilantin)
Theoretically, black seed might increase or decrease levels and effects of phenytoin.
In vitro research suggests that thymoquinone, a constituent of black seed, can decrease the metabolism of phenytoin. This effect may be due to inhibition of cytochrome P450 2C9 (CYP2C9). However, animal research shows that black seed decreases the maximum concentration of and total systemic exposure to phenytoin by 57% and 87%, respectively. This seems to be related to increased clearance and steady state volume of distribution. This interaction has not been shown in humans.
Serotonergic Drugs
Theoretically, combining serotonergic drugs with black seed might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders.
Animal research suggests that black seed can increase brain serotonin levels. In one case report, a 35-year-old man undergoing endoscopic surgery experienced immediate postoperative serotonin syndrome that was likely associated with the use of black seed oil 600 mg daily starting 4 days before surgery, and precipitated by the use of serotonergic pain medications, including fentanyl and oxycodone. Monitor patients for signs of serotonin syndrome and other serotonergic side effects if using black seed with serotonergic drugs.
Sildenafil (Viagra)
Theoretically, black seed might reduce plasma levels and the therapeutic effects of sildenafil.
Animal research shows that black seed reduces the total systemic exposure to sildenafil by 43%. So far, this interaction has not been reported in humans.
Warfarin (Coumadin)
Theoretically, black seed might increase levels of warfarin and increase the risk of bleeding.
In vitro research suggests that thymoquinone, a constituent of black seed, can decrease the metabolism of warfarin. This effect may be due to inhibition of cytochrome P450 2C9 (CYP2C9). The effect of black seed on warfarin metabolism is unclear. This has not been shown in humans.
Prednisolone
Theoretically black seed might reduce plasma levels and therapeutic effects of prednisolone.
In animal research, oral administration of a single dose of black seed oil 15 minutes prior to oral prednisolone decreases the prednisolone maximum plasma concentration by 65% and area under the curve by 25%. This has not been shown in humans.
Bladderwrack Whole Plant Extract
Amiodarone (Cordarone)
Theoretically, combining Fucus vesiculosus with amiodarone might cause excessively high iodine levels.
Fucus vesiculosus contains high concentrations of iodine. Amiodarone contains 37.3% iodine and can increase iodine levels. Concomitant use might increase the risk of having excessive iodine levels and adversely affecting thyroid function. Monitor thyroid function.
Antithyroid Drugs
Due to its iodine content, Fucus vesiculosus might alter the effects of antithyroid drugs.
Fucus vesiculosus contains high concentrations of iodine. Iodine in high doses has been reported to cause both hyperthyroidism and hypothyroidism, depending on the individual's past medical history. Taking Fucus vesiculosus while using antithyroid drugs could alter the effects of the antithyroid drugs.
Lithium
Concomitant use of Fucus vesiculosus and lithium has resulted in hyperthyroidism.
There is a case of hyperthyroidism occurring in a patient taking Fucus vesiculosus and lithium. Monitor thyroid hormones closely in patients taking lithium and Fucus vesiculosus concomitantly.
Thyroid Hormone
Due to its iodine content, Fucus vesiculosus might alter the effects of thyroid hormone.
Fucus vesiculosus contains high concentrations of iodine. Iodine in high doses has been reported to cause both hyperthyroidism and hypothyroidism, depending on the individual's past medical history. Taking Fucus vesiculosus while using thyroid hormone could alter the effects of thyroid hormone.
Anticoagulant/Antiplatelet Drugs
Theoretically, taking Fucus vesiculosus with antiplatelet or anticoagulant drugs might increase the risk of bruising and bleeding.
In vitro evidence suggests that a constituent of Fucus vesiculosus, known as fucoidan, has anticoagulant effects. However, in clinical research, fucoidan does not seem to have significant anticoagulant activity when taken orally, possibly due to poor absorption.
Cytochrome P450 2C8 (Cyp2C8) Substrates
Theoretically, concomitant use of Fucus vesiculosus with CYP2C8 substrates might increase the risk for adverse effects.
In vitro research shows that fucoidan, a constituent of Fucus vesiculosus, inhibits CYP2C8. This interaction has not been reported in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, concomitant use of Fucus vesiculosus with CYP2C9 substrates might increase the risk for adverse effects.
In vitro research shows that fucoidan, a constituent of Fucus vesiculosus, inhibits CYP2C9. This interaction has not been reported in humans.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, concomitant use of Fucus vesiculosus with CYP2D6 substrates might alter the effects of these substrates.
In vitro research shows that fucoidan, a constituent of Fucus vesiculosus, both inhibits and induces CYP2D6. This interaction has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, concomitant use of Fucus vesiculosus with CYP3A4 substrates might increase the risk for adverse effects.
In vitro research shows that fucoidan, a constituent of Fucus vesiculosus, inhibits CYP3A4. This interaction has not been reported in humans.
Manuka Honey, Powder
Phenytoin (Dilantin)
Theoretically, honey might increase levels of phenytoin.
In an animal model, the rate and extent of absorption of phenytoin was increased by honey. This effect has not been reported in humans.
Anticoagulant/Antiplatelet Drugs
Theoretically, honey may increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
In vitro, honey inhibits platelet aggregation and increases the time to clotting. Furthermore, animal research suggests that feeding mice large doses of honey for 12 days increases bleeding time when compared with no intervention. However, these effects have not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, honey might decrease levels of drugs metabolized by CYP3A4, but research is conflicting.
Some clinical research shows that honey induces CYP3A4. However, other clinical studies found no effect on CYP3A4 activity. Different honey preparations may have different effects on CYP3A4.
Vitamin D3
Aluminum
Vitamin D might increase aluminum absorption and toxicity, but this has only been reported in people with renal failure.
The protein that transports calcium across the intestinal wall can also bind and transport aluminum. This protein is stimulated by vitamin D, which may therefore increase aluminum absorption. This mechanism may contribute to increased aluminum levels and toxicity in people with renal failure, when they take vitamin D and aluminum-containing phosphate binders chronically.
Atorvastatin (Lipitor)
Vitamin D might reduce absorption of atorvastatin.
A small, low-quality clinical study shows that taking vitamin D reduces levels of atorvastatin and its active metabolites by up to 55%. However, while atorvastatin levels decreased, total cholesterol, low-density lipoprotein (LDL) cholesterol, and high-density lipoprotein (HDL) cholesterol levels did not substantially change. Atorvastatin is metabolized in the gut by CYP3A4 enzymes, and researchers theorized that vitamin D might induce CYP3A4, causing reduced levels of atorvastatin. However, this proposed mechanism was not specifically studied.
Calcipotriene (Dovonex)
Taking calcipotriene with vitamin D increases the risk for hypercalcemia.
Calcipotriene is a vitamin D analog used topically for psoriasis. It can be absorbed in sufficient amounts to cause systemic effects, including hypercalcemia. Theoretically, combining calcipotriene with vitamin D supplements might increase the risk of hypercalcemia.
Digoxin (Lanoxin)
Theoretically, hypercalcemia induced by high-dose vitamin D can increase the risk of arrhythmia from digoxin.
High doses of vitamin D can cause hypercalcemia. Hypercalcemia increases the risk of fatal cardiac arrhythmias with digoxin. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and digoxin concurrently.
Diltiazem (Cardizem, Others)
Theoretically, hypercalcemia induced by high-dose vitamin D can reduce the therapeutic effects of diltiazem for arrhythmia.
High doses of vitamin D can cause hypercalcemia. Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically this could also occur with diltiazem. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and diltiazem concurrently.
Thiazide Diuretics
Theoretically, taking thiazide diuretics and high-dose vitamin D can increase the risk of hypercalcemia.
Thiazide diuretics decrease urinary calcium excretion, which could lead to hypercalcemia if vitamin D supplements are taken concurrently. This has been reported in people being treated with vitamin D for hypoparathyroidism, and also in elderly people with normal parathyroid function who were taking a thiazide, vitamin D, and calcium-containing antacids daily.
Verapamil (Calan, Others)
Hypercalcemia induced by high-dose vitamin D can reduce the therapeutic effects of verapamil for arrhythmia.
Hypercalcemia due to high doses of vitamin D can reduce the effectiveness of verapamil in atrial fibrillation. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and verapamil concurrently.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
There is some concern that vitamin D might induce CYP3A4. In vitro research suggests that vitamin D induces CYP3A4 transcription. Additionally, observational research has found that increased UV light exposure and serum vitamin D levels are associated with decreased serum levels of CYP3A4 substrates such as tacrolimus and sirolimus, while no association between UV light exposure or vitamin D levels and levels of mycophenolic acid, a non-CYP3A4 substrate, was found. A small, low-quality clinical study shows that taking vitamin D reduces levels of the CYP3A4 substrate atorvastatin and its active metabolites by up to 55%; however, the clinical effects of atorvastatin were not reduced. While researchers theorized that vitamin D might induce CYP3A4, this proposed mechanism was not specifically studied.
Dandelion Root Extract
Anticoagulant/Antiplatelet Drugs
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
In vitro research suggests that dandelion root inhibits platelet aggregation.
Antidiabetes Drugs
Theoretically, dandelion might increase the risk for hypoglycemia when used with antidiabetes drugs.
Laboratory research suggests that dandelion extract may have moderate alpha-glucosidase inhibitor activity and might also increase insulin secretion. Also, in a case report, a 58-year-old woman with type 2 diabetes who was being treated with insulin developed hypoglycemia 2 weeks after beginning to eat salads containing dandelion.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Laboratory research suggests that dandelion might inhibit CYP1A2. So far, this interaction has not been reported in humans. However, until more is known, watch for an increase in the levels of drugs metabolized by CYP1A2 in patients taking dandelion.
Glucuronidated Drugs
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
There is some preliminary evidence that dandelion might induce UDP-glucuronosyltransferase, a phase II enzyme.
Lithium
Theoretically, through diuretic effects, dandelion might reduce excretion and increase levels of lithium.
Animal research suggests that dandelion has diuretic properties. As diuretics can increase serum lithium levels, the dose of lithium might need to be decreased when taken with dandelion.
Potassium-Sparing Diuretics
Theoretically, dandelion might increase the risk of hyperkalemia when taken with potassium-sparing diuretics.
Dandelion contains significant amounts of potassium.
Quinolone Antibiotics
Theoretically, dandelion might lower fluoroquinolone levels.
Animal research shows that dandelion reduces absorption of ciprofloxacin and can lower levels by 73%. However, this effect has not been reported in humans.
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Sodium Copper Chlorophyllin
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Apple Cider Vinegar, Powder
Digoxin (Lanoxin)
Theoretically, concomitant use of apple cider vinegar with digoxin might increase the risk of cardiac toxicity.
A case of hypokalemia related to chronic use of apple cider vinegar has been reported. Theoretically, overuse of apple cider vinegar could decrease potassium levels, increasing the risk of toxicity with digoxin.
Diuretic Drugs
Theoretically, concomitant use of apple cider vinegar with diuretic drugs might increase the risk of hypokalemia.
A case of hypokalemia related to chronic use of apple cider vinegar has been reported. There is some concern that people taking apple cider vinegar along with potassium depleting diuretics might have an increased risk for hypokalemia.
Insulin
Theoretically, concomitant use of apple cider vinegar with insulin might increase the risk of hypokalemia.
A case of hypokalemia related to chronic use of apple cider vinegar has been reported. Theoretically, overuse of apple cider vinegar concomitantly with insulin might increase the risk of hypokalemia.
Antidiabetes Drugs
Theoretically, taking apple cider vinegar with antidiabetes drugs might increase the risk of hypoglycemia.
Apple cider vinegar might reduce fasting and postprandial blood glucose levels and decrease gastric emptying in people with diabetes. However, not all research agrees. Theoretically, it might have additive effects on glucose levels when used with antidiabetes drugs.
Burdock Root Extract
Anticoagulant/Antiplatelet Drugs
Theoretically, taking burdock with anticoagulant or antiplatelet drugs might increase the risk of bleeding.
In vitro research shows that lignans from burdock reduce rabbit platelet aggregation by inhibiting platelet activating factor. This interaction has not been reported in humans.
Elderberry Fruit Extract
Immunosuppressants
Theoretically, elderberry might interfere with immunosuppressant therapy due to its immunostimulant activity.
Elderberry has immunostimulant activity, increasing the production of cytokines, including interleukin and tumor necrosis factor.
Pazopanib (Votrient)
Theoretically, elderberry might interact with pazopanib, potentially increasing the risk of adverse effects.
Yellow Dock, Powder
Digoxin (Lanoxin)
Theoretically, yellow dock might increase the risk of digoxin toxicity when used long-term or in large amount.
When yellow dock is used chronically or in large amounts, hypokalemia may occur. This might increase the toxic effects of digoxin.
Diuretic Drugs
Theoretically, yellow dock might increase the risk of hypokalemia when taken with diuretics.
When yellow dock is used chronically or in large amounts, hypokalemia may occur, and overuse of yellow dock might compound diuretic-induced potassium loss.
Warfarin (Coumadin)
Theoretically, the laxative effects of yellow dock might increase the effects of warfarin, including the risk of bleeding.
The anthraquinones in yellow dock have a mild stimulant laxative effect. Consuming excessive amounts can cause diarrhea. Diarrhea can increase the effects of warfarin, increase international normalized ratio (INR), and increase the risk of bleeding.
Sea Moss Whole Plant Extract
Amiodarone (Cordarone)
Theoretically, combining sea moss with amiodarone might cause excessively high iodine levels.
Amiodarone contains 37.3% iodine and can increase iodine levels. Concomitant use with sea moss, which contains approximately 4-7 mcg of iodine per gram, might increase the risk of adverse effects from iodine, including altered thyroid function.
Antithyroid Drugs
Due to its iodine content, sea moss might alter the effects of antithyroid drugs.
Sea moss contains approximately 4-7 mcg of iodine per gram. Iodine in high doses has been reported to cause both hyperthyroidism and hypothyroidism, depending on the individual's past medical history. Taking sea moss could theoretically alter the effects of antithyroid drugs.
Thyroid Hormone
Due to its iodine content, sea moss might alter the effects of thyroid hormone.
Sea moss contains approximately 4-7 mcg of iodine per gram. Iodine in high doses has been reported to cause both hyperthyroidism and hypothyroidism, depending on the individual's past medical history. Taking sea moss could theoretically alter the effects of thyroid hormone.
Brand information
Manufacturer and brand details for Multimineral, from the product label.
Clean Nutraceuticals
See all Clean Nutraceuticals products- Name
- Allseason Enterprises, LLC
- Street Address
- 7582 Las Vegas Blvd S. #3015
- City
- Las Vegas
- State
- NV
- ZipCode
- 89123
- Phone Number
- (866) 221-7374
Multimineral by Clean Nutraceuticals: Common Questions
Does Multimineral by Clean Nutraceuticals interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Does this multimineral work for everyday health?
Can I take this if I'm pregnant?
What's the laxative ingredient I've heard about in some of these herbs?
Is this safe to take with my blood pressure medication?
What are the side effects I should watch for?
Does this contain any fillers or 'junk' ingredients?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Multimineral is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Multimineral’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographVitamin D
Interacts with 715 drugsVitamin D is a fat-soluble vitamin that helps your body absorb calcium and is important for healthy bones, muscles, and immune function. Many people, especially those with low sun exposure,...
Read the full Vitamin D monograph → Herb & supplement monographTurmeric
Interacts with 1,133 drugsTurmeric is a popular spice whose main active compounds, curcuminoids, are studied mostly for inflammation and joint pain. Some research is promising, but quality is mixed and curcumin is po...
Read the full Turmeric monograph → Herb & supplement monographSea Moss
Interacts with 22 drugsSea moss is a type of red seaweed that is naturally rich in iodine and several minerals, and it is popular as a 'whole-food' supplement. Strong human evidence for most of its health claims i...
Read the full Sea Moss monograph → Herb & supplement monographBurdock
Interacts with 122 drugsBurdock is a traditional herb most often used for skin problems and as a so-called 'blood purifier,' but high-quality human studies are lacking and most claims are not well proven. It is wid...
Read the full Burdock monograph → Herb & supplement monographAshwagandha
Interacts with 1,372 drugsAshwagandha is an Ayurvedic herb most often taken to help with stress, anxiety, and sleep, and some small studies suggest it may help, though the evidence is still limited. It is generally w...
Read the full Ashwagandha monograph → Herb & supplement monographFucus Vesiculosus
Interacts with 891 drugsFucus vesiculosus (bladderwrack) is a brown seaweed rich in iodine that has been used traditionally for thyroid concerns, weight, and skin. There is little solid human evidence to support mo...
Read the full Fucus Vesiculosus monograph → Herb & supplement monographBlack Seed
Interacts with 912 drugsBlack seed (Nigella sativa) is a traditional spice and remedy that has been studied for asthma, blood sugar, cholesterol, and blood pressure, with early research showing some promise but no...
Read the full Black Seed monograph → Herb & supplement monographDandelion
Interacts with 457 drugsDandelion is a common plant used in food and traditional medicine, often promoted as a natural 'water pill' and digestive aid. Human evidence for these uses is very limited, so its benefits...
Read the full Dandelion monograph → Herb & supplement monographSodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph → Herb & supplement monographElderberry
Interacts with 121 drugsElderberry is a popular herbal supplement, mainly taken to help with colds and flu. Some small studies suggest it may modestly shorten cold or flu symptoms, but the evidence is limited and n...
Read the full Elderberry monograph → Herb & supplement monographHoney
Interacts with 736 drugsHoney is a natural food with some real, modest evidence for easing coughs and helping certain wounds, especially when special medical-grade or Manuka honey is used. It is generally safe for...
Read the full Honey monograph → Herb & supplement monographApple Cider Vinegar
Interacts with 162 drugsApple cider vinegar is a fermented apple product that many people use hoping to help with blood sugar, weight, or digestion. The evidence for most of these uses is limited and mixed, and the...
Read the full Apple Cider Vinegar monograph → Herb & supplement monographYellow Dock
Interacts with 78 drugsYellow dock is a traditional herb used mostly as a mild laxative and a digestive and skin tonic. Good-quality human studies are lacking, so its benefits are largely unproven, and its natural...
Read the full Yellow Dock monograph →Sources & How We Checked
Multimineral's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 430 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Vitamin D 26 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Tatro DS, ed. Drug Interactions Facts. Facts and Comparisons Inc., St. Louis, MO. 1999.
- Koutkia P, Chen TC, Holick MF. Vitamin D intoxication associated with an over-the-counter supplement. N Engl J Med 2001;345:66-7. PubMed
- Bar-Or D, Yoel G. Calcium and calciferol antagonize effect of verapamil in atrial fibrillation. Br Med J 1981;282:1585-6.
- Demontis R, Leflon A, Fournier A, et al. 1 alpha(OH) vitamin D3 increases plasma aluminum in hemodialyzed patients taking AI(OH)3. Clin Nephrol 1986;26:146-9.
- Crowe M, Wollner L, Griffiths RA. Hypercalcemia following vitamin D and thiazide therapy in the elderly. Practitioner 1984;228:312-3.
- Parfitt AM. Thiazide-induced hypercalcemia in vitamin D-treated hypoparathyroidism. Ann Intern Med 1972;77:557-63. PubMed
- Thiazide diuretics and the risk of osteoporosis. Pharmacist's Letter/Prescriber's Letter 2003;19(11):191105.
- Moon J. The role of vitamin D in toxic metal absorption. J Am Coll Nutr 1994;13:559-64.
- Demontis R, Reissi D, Noel C, et al. Indirect clinical evidence that 1alphaOH vitamin D<SUB>3</SUB> increases the intestinal absorption of aluminum. Clin Nephrol 1989;31:123-7.
- Adler AJ, Berlyne GM. Duodenal aluminum absorption in the rat: effect of vitamin D. Am J Physiol 1985;249:G209-13. PubMed
- Schwartz JB. Effects of vitamin D supplementation in atorvastatin-treated patients: A new drug interaction with an unexpected consequence. Clin Pharmacol Ther 2009;85:198-203. PubMed
- Dietary reference intakes for calcium and vitamin D. Institute of Medicine, November 30, 2010. Available at: http://www.iom.edu/~/media/Files/Report%20Files/2010/Dietary-Reference-Intakes-for-Calcium-and-Vitamin-D/Vitamin%20D%20and%20Calcium%202010%20Repo
- Cox KA, Dunn MA. Aluminum toxicity alters the regulation of calbindin-D28k protein and mRNA expression in chick intestine. J Nutr 2001;131:2007-13. PubMed
- Escribano, J., Balaguer, A., Pagone, F., Feliu, A., and Roque, I. Figuls. Pharmacological interventions for preventing complications in idiopathic hypercalciuria. Cochrane.Database.Syst.Rev. 2009;(1):CD004754. PubMed
- Carlton, S., Clopton, D., and Cappuzzo, K. A. Vitamin D deficiency: appropriate replenishment therapies and the effects of vitamin D toxicity. Consult Pharm 2010;25(3):171-177. PubMed
- Wang, H., Xia, N., Yang, Y., and Peng, D. Q. Influence of vitamin D supplementation on plasma lipid profiles: a meta-analysis of randomized controlled trials. Lipids Health Dis. 2012;11:42. PubMed
- Turner AN, Carr Reese P, Fields KS, Anderson J, Ervin M, Davis JA, Fichorova RN, Roberts MW, Klebanoff MA, Jackson RD. A blinded, randomized controlled trial of high-dose vitamin D supplementation to reduce recurrence of bacterial vaginosis. Am J Obstet G PubMed
- Weiner M, Epstein FH. Signs and symptoms of electrolyte disorders. Yale J Biol Med. 1970;43(2):76-109.
- Lappe J, Watson P, Travers-Gustafson D, Recker R, Garland C, Gorham E, Baggerly K, McDonnell SL. Effect of Vitamin D and Calcium Supplementation on Cancer Incidence in Older Women: A Randomized Clinical Trial. JAMA. 2017 Mar 28;317(12):1234-1243. PubMed
- Roth DE, Leung M, Mesfin E, Qamar H, Watterworth J, Papp E. Vitamin D supplementation during pregnancy: state of the evidence from a systematic review of randomised trials. BMJ. 2017;359:j5237. PubMed
- Murai IH, Fernandes AL, Sales LP, et al. Effect of a single high dose of vitamin D3 on hospital length of stay in patients with moderate to severe COVID-19: A randomized clinical trial. JAMA. 2021.
- Wang Z, Schuetz EG, Xu Y, Thummel KE. Interplay between vitamin D and the drug metabolizing enzyme CYP3A4. J Steroid Biochem Mol Biol 2013;136:54-8. PubMed
- Doyle D, Browne U, Brickley A, Murphy D. Vitamin D-induced hypercalcaemia and acute kidney injury in sarcoidosis. BMJ Case Rep 2023;16(1):e250580. PubMed
- Williamson A, Martineau AR, Sheikh A, Jolliffe D, Griffiths CJ. Vitamin D for the management of asthma. Cochrane Database Syst Rev 2023;2(2):CD011511. PubMed
- Kinesya E, Santoso D, Gde Arya N, et al. Vitamin D as adjuvant therapy for diabetic foot ulcers: Systematic review and meta-analysis approach. Clin Nutr ESPEN 2023;54:137-143. PubMed
Dandelion 27 references
- Maliakal PP, Wanwimolruk S. Effect of herbal teas on hepatic drug metabolizing enzymes in rats. J Pharm Pharmacol 2001;53:1323-9. PubMed
- Williams CA, Goldstone F, Greenham J. Flavonoids, cinnamic acids and coumarins from the different tissues and medicinal preparations of Taraxacum officinale. Phytochemistry 1996;42:121-7. PubMed
- Hussain Z, Waheed A, Qureshi RA, et al. The effect of medicinal plants of Islamabad and Murree region of Pakistan on insulin secretion from INS-1 cells. Phytother Res 2004;18:73-7. PubMed
- Racz-Kotilla E, Racz G, Solomon A. The action of Taraxacum officinale extracts on the body weight and diuresis of laboratory animals. Planta Med 1974;26:212-7. PubMed
- Zhu M, Wong PY, Li RC. Effects of taraxacum mongolicum on the bioavailability and disposition of ciprofloxacin in rats. J Pharm Sci 1999;88:632-4. PubMed
- Jovanovic M, Mimica-Dukic N, Poljacki M, Boza P. Erythema multiforme due to contact with weeds: a recurrence after patch testing. Contact Dermatitis 2003;48:17-25. PubMed
- Chivato T, Juan F, Montoro A, Laguna R. Anaphylaxis induced by ingestion of a pollen compound. J Investig Allergol Clin Immunol 1996;6:208-9.
- Cohen SH, Yunginger JW, Rosenberg N, Fink JN. Acute allergic reaction after composite pollen ingestion. J Allergy Clin Immunol 1979;64:270-4. PubMed
- Lovell CR, Rowan M. Dandelion dermatitis. Contact Dermatitis 1991;25:185-8. PubMed
- Agarwal SC, Crook JR, Pepper CB. Herbal remedies -- how safe are they? A case report of polymorphic ventricular tachycardia/ventricular fibrillation induced by herbal medication used for obesity. Int J Cardiol 2006;106:260-1. PubMed
- Martín-Muñoz MF, Bartolome B, Caminoa M, et al. Bee pollen: a dangerous food for allergic children. Identification of responsible allergens. Allergol Immunopathol (Madr) 2010;38:263-5. PubMed
- Neef H, Cilli F, Declerck PJ, et al. Platelet anti-aggregating activity of Taraxacum officinale Weber. Phytotherapy Research 1996;10:s138-s140.
- Cuzzolin L, Zaffani S, and Benoni G. Safety implications regarding use of phytomedicines. Eur.J Clin Pharmacol. 2006;62:37-42. PubMed
- Posadzki, P., Watson, L. K., and Ernst, E. Adverse effects of herbal medicines: an overview of systematic reviews. Clin Med 2013;13(1):7-12. PubMed
- Wakelin, S. H., Marren, P., Young, E., and Shaw, S. Compositae sensitivity and chronic hand dermatitis in a seven-year-old boy. Br J Dermatol 1997;137(2):289-291. PubMed
- Ingber, A. Seasonal allergic contact dermatitis from Taraxacum officinale (dandelion) in an Israeli florist. Contact Dermatitis 2000;43(1):49.
- Rodriguez, B., Rodriguez, A., de Barrio, M., Tornero, P., and Baeza, M. L. Asthma induced by canary food mix. Allergy Asthma Proc. 2003;24(4):265-268.
- Syhaieva, I. A. [Efficiency of specific immunotherapy in treatment of patients with seasonal allergic rhinitis]. Lik.Sprava. 2006;(1-2):51-53.
- Catania, M. A., Oteri, A., Caiello, P., Russo, A., Salvo, F., Giustini, E. S., Caputi, A. P., and Polimeni, G. Hemorrhagic cystitis induced by an herbal mixture. South.Med.J. 2010;103(1):90-92. PubMed
- Goksu, E., Eken, C., Karadeniz, O., and Kucukyilmaz, O. First report of hypoglycemia secondary to dandelion (Taraxacum officinale) ingestion. Am J Emerg.Med 2010;28(1):111-112. PubMed
- Fernandez-Gonzalez, D., Gonzalez-Parrado, Z., Vega-Maray, A. M., Valencia-Barrera, R. M., Camazon-Izquierdo, B., De, Nuntiis P., and Mandrioli, P. Platanus pollen allergen, Pla a 1: quantification in the atmosphere and influence on a sensitizing populati
- Liang, K. L., Su, M. C., Shiao, J. Y., Wu, S. H., Li, Y. H., and Jiang, R. S. Role of pollen allergy in Taiwanese patients with allergic rhinitis. J Formos.Med Assoc. 2010;109(12):879-885. PubMed
- Yang, Y., Zhao, Y., Wang, C. S., Wang, X. D., and Zhang, L. [Prevalence of sensitization to aeroallergens in 10 030 patients with allergic rhinitis]. Zhonghua Er.Bi Yan.Hou Tou.Jing.Wai Ke Za Zhi 2011;46(11):914-920.
- Davies, M. G. and Kersey, P. J. Contact allergy to yarrow and dandelion. Contact Dermatitis 1986;14(4):256-257. PubMed
- Collins JM and Miller DR. Dandelion green bezoar following antrectomy and vagotomy - case report. J Kansas Med Soc 1966;67(6):303-304.
- Moriarty B, Pinney JH, Owen-Casey MP, Rustin MH, Deroide F, Laing C, Davenport A. Digital necrosis from dandelion tea. Br J Dermatol. 2013 Jul;169(1):227-30. PubMed
- Onal S, Timur S, Okutucu B, Zihnioglu F. Inhibition of alphaglucosidase by aqueous extracts of some potent antidiabetic medicinal herbs. Prep Biochem Biotechnol 2005;35:29-36.
Turmeric 102 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Sharma RA, McLelland HR, Hill KA, et al. Pharmacodynamic and pharmacokinetic study of oral Curcuma extract in patients with colorectal cancer. Clin Cancer Res 2001;7:1894-900..
- Shah BH, Nawaz Z, Pertani SA. Inhibitory effect of curcumin, a food spice from turmeric, on platelet-activating factor- and arachidonic acid-mediated platelet aggregation through inhibition of thromboxane formation and Ca2+ signaling. Biochem Pharmacol 1 PubMed
- Hata M, Sasaki E, Ota M, et al . Allergic contact dermatitis from curcumin (turmeric). Contact Dermatitis 1997;36:107-8. PubMed
- Kuttan R, Sudheeran PC, Josph CD. Turmeric and curcumin as topical agents in cancer therapy. Tumori 1987;73:29-31.. PubMed
- Thapliyal R, Deshpande SS, Maru GB. Mechanism(s) of turmeric-mediated protective effects against benzo(a)pyrene-derived DNA adducts. Cancer Lett 2002;175:79-88. PubMed
- Lee SW, Nah SS, Byon JS, et al. Transient complete atrioventricular block associated with curcumin intake. Int J Cardiol 2011;150:e50-2. PubMed
- Kuptniratsaikul V, Thanakhumtorn S, Chinswangwatanakul P, et al. Efficacy and safety of Curcuma domestica extracts in patients with knee osteoarthritis. J Altern Complement Med 2009;15:891-7.
- Carroll RE, Benya RV, Turgeon DK, et al. Phase IIa clinical trial of curcumin for the prevention of colorectal neoplasia. Cancer Prev Res (Phila) 2011;4:354-64. PubMed
- Junyaprasert, V. B., Soonthornchareonnon, N., Thongpraditchote, S., Murakami, T., and Takano, M. Inhibitory effect of Thai plant extracts on P-glycoprotein mediated efflux. Phytother.Res 2006;20(1):79-81. PubMed
- Ampasavate, C., Sotanaphun, U., Phattanawasin, P., and Piyapolrungroj, N. Effects of Curcuma spp. on P-glycoprotein function. Phytomedicine. 2010;17(7):506-512. PubMed
- Hou, X. L., Takahashi, K., Tanaka, K., Tougou, K., Qiu, F., Komatsu, K., Takahashi, K., and Azuma, J. Curcuma drugs and curcumin regulate the expression and function of P-gp in Caco-2 cells in completely opposite ways. Int.J Pharm 6-24-2008;358(1-2):224-2 PubMed
- Choi, B. H., Kim, C. G., Lim, Y., Shin, S. Y., and Lee, Y. H. Curcumin down-regulates the multidrug-resistance mdr1b gene by inhibiting the PI3K/Akt/NF kappa B pathway. Cancer Lett. 1-18-2008;259(1):111-118.
- Zhang, W., Tan, T. M., and Lim, L. Y. Impact of curcumin-induced changes in P-glycoprotein and CYP3A expression on the pharmacokinetics of peroral celiprolol and midazolam in rats. Drug Metab Dispos. 2007;35(1):110-115. PubMed
- Limtrakul, P., Chearwae, W., Shukla, S., Phisalphong, C., and Ambudkar, S. V. Modulation of function of three ABC drug transporters, P-glycoprotein (ABCB1), mitoxantrone resistance protein (ABCG2) and multidrug resistance protein 1 (ABCC1) by tetrahydrocu
- Holland, M. L., Panetta, J. A., Hoskins, J. M., Bebawy, M., Roufogalis, B. D., Allen, J. D., and Arnold, J. C. The effects of cannabinoids on P-glycoprotein transport and expression in multidrug resistant cells. Biochem.Pharmacol 4-14-2006;71(8):1146-1154 PubMed
- Tang, X. Q., Bi, H., Feng, J. Q., and Cao, J. G. Effect of curcumin on multidrug resistance in resistant human gastric carcinoma cell line SGC7901/VCR. Acta Pharmacol Sin. 2005;26(8):1009-1016. PubMed
- Nabekura, T., Kamiyama, S., and Kitagawa, S. Effects of dietary chemopreventive phytochemicals on P-glycoprotein function. Biochem.Biophys.Res Commun. 2-18-2005;327(3):866-870. PubMed
- Romiti, N., Tongiani, R., Cervelli, F., and Chieli, E. Effects of curcumin on P-glycoprotein in primary cultures of rat hepatocytes. Life Sci. 1998;62(25):2349-2358. PubMed
- Yue, G. G., Cheng, S. W., Yu, H., Xu, Z. S., Lee, J. K., Hon, P. M., Lee, M. Y., Kennelly, E. J., Deng, G., Yeung, S. K., Cassileth, B. R., Fung, K. P., Leung, P. C., and Lau, C. B. The role of turmerones on curcumin transportation and P-glycoprotein acti
- Shenouda, N. S., Zhou, C., Browning, J. D., Ansell, P. J., Sakla, M. S., Lubahn, D. B., and MacDonald, R. S. Phytoestrogens in common herbs regulate prostate cancer cell growth in vitro. Nutr.Cancer 2004;49(2):200-208. PubMed
- Appiah-Opong, R., Commandeur, J. N., Vugt-Lussenburg, B., and Vermeulen, N. P. Inhibition of human recombinant cytochrome P450s by curcumin and curcumin decomposition products. Toxicology 6-3-2007;235(1-2):83-91. PubMed
- Hou, X. L., Takahashi, K., Kinoshita, N., Qiu, F., Tanaka, K., Komatsu, K., Takahashi, K., and Azuma, J. Possible inhibitory mechanism of Curcuma drugs on CYP3A4 in 1alpha,25 dihydroxyvitamin D3 treated Caco-2 cells. Int.J Pharm 6-7-2007;337(1-2):169-177.
- Valentine, S. P., Le Nedelec, M. J., Menzies, A. R., Scandlyn, M. J., Goodin, M. G., and Rosengren, R. J. Curcumin modulates drug metabolizing enzymes in the female Swiss Webster mouse. Life Sci. 4-11-2006;78(20):2391-2398. PubMed
- Price, R. J., Scott, M. P., Giddings, A. M., Walters, D. G., Stierum, R. H., Meredith, C., and Lake, B. G. Effect of butylated hydroxytoluene, curcumin, propyl gallate and thiabendazole on cytochrome P450 forms in cultured human hepatocytes. Xenobiotica 2 PubMed
- Ganta, S., Devalapally, H., and Amiji, M. Curcumin enhances oral bioavailability and anti-tumor therapeutic efficacy of paclitaxel upon administration in nanoemulsion formulation. J Pharm Sci 2010;99(11):4630-4641. PubMed
- Lamb, S. R. and Wilkinson, S. M. Contact allergy to tetrahydrocurcumin. Contact Dermatitis 2003;48(4):227. PubMed
- Joshi, J., Ghaisas, S., Vaidya, A., Vaidya, R., Kamat, D. V., Bhagwat, A. N., and Bhide, S. Early human safety study of turmeric oil (Curcuma longa oil) administered orally in healthy volunteers. J Assoc.Physicians India 2003;51:1055-1060.
- Mahesh, T., Balasubashini, M. S., and Menon, V. P. Effect of photo-irradiated curcumin treatment against oxidative stress in streptozotocin-induced diabetic rats. J Med.Food 2005;8(2):251-255. PubMed
- Thompson, D. A. and Tan, B. B. Tetrahydracurcumin-related allergic contact dermatitis. Contact Dermatitis 2006;55(4):254-255. PubMed
- Patumraj, S., Wongeakin, N., Sridulyakul, P., Jariyapongskul, A., Futrakul, N., and Bunnag, S. Combined effects of curcumin and vitamin C to protect endothelial dysfunction in the iris tissue of STZ-induced diabetic rats. Clin Hemorheol.Microcirc. 2006;3
- Liddle, M., Hull, C., Liu, C., and Powell, D. Contact urticaria from curcumin. Dermatitis 2006;17(4):196-197. PubMed
- Juan, H., Terhaag, B., Cong, Z., Bi-Kui, Z., Rong-Hua, Z., Feng, W., Fen-Li, S., Juan, S., Jing, T., and Wen-Xing, P. Unexpected effect of concomitantly administered curcumin on the pharmacokinetics of talinolol in healthy Chinese volunteers. Eur.J Clin PubMed
- Murugan, P. and Pari, L. Influence of tetrahydrocurcumin on erythrocyte membrane bound enzymes and antioxidant status in experimental type 2 diabetic rats. J Ethnopharmacol. 9-25-2007;113(3):479-486. PubMed
- Seo, K. I., Choi, M. S., Jung, U. J., Kim, H. J., Yeo, J., Jeon, S. M., and Lee, M. K. Effect of curcumin supplementation on blood glucose, plasma insulin, and glucose homeostasis related enzyme activities in diabetic db/db mice. Mol.Nutr.Food Res 2008;5
- Weisberg, S. P., Leibel, R., and Tortoriello, D. V. Dietary curcumin significantly improves obesity-associated inflammation and diabetes in mouse models of diabesity. Endocrinology 2008;149(7):3549-3558. PubMed
- Jain, S. K., Rains, J., Croad, J., Larson, B., and Jones, K. Curcumin supplementation lowers TNF-alpha, IL-6, IL-8, and MCP-1 secretion in high glucose-treated cultured monocytes and blood levels of TNF-alpha, IL-6, MCP-1, glucose, and glycosylated hemog
- Yu, Y., Hu, S. K., and Yan, H. [The study of insulin resistance and leptin resistance on the model of simplicity obesity rats by curcumin]. Zhonghua Yu Fang Yi.Xue.Za Zhi. 2008;42(11):818-822.
- Pavithra, B. H., Prakash, N., and Jayakumar, K. Modification of pharmacokinetics of norfloxacin following oral administration of curcumin in rabbits. J Vet.Sci. 2009;10(4):293-297. PubMed
- Yan, Y. D., Kim, D. H., Sung, J. H., Yong, C. S., and Choi, H. G. Enhanced oral bioavailability of docetaxel in rats by four consecutive days of pre-treatment with curcumin. Int J Pharm 10-31-2010;399(1-2):116-120. PubMed
- Epelbaum, R., Schaffer, M., Vizel, B., Badmaev, V., and Bar-Sela, G. Curcumin and gemcitabine in patients with advanced pancreatic cancer. Nutr Cancer 2010;62(8):1137-1141. PubMed
- Madkor, H. R., Mansour, S. W., and Ramadan, G. Modulatory effects of garlic, ginger, turmeric and their mixture on hyperglycaemia, dyslipidaemia and oxidative stress in streptozotocin-nicotinamide diabetic rats. Br J Nutr 2011;105(8):1210-1217. PubMed
- Pungcharoenkul, K. and Thongnopnua, P. Effect of different curcuminoid supplement dosages on total in vivo antioxidant capacity and cholesterol levels of healthy human subjects. Phytother Res 2011;25(11):1721-1726.
- Kusuhara, H., Furuie, H., Inano, A., Sunagawa, A., Yamada, S., Wu, C., Fukizawa, S., Morimoto, N., Ieiri, I., Morishita, M., Sumita, K., Mayahara, H., Fujita, T., Maeda, K., and Sugiyama, Y. Pharmacokinetic interaction study of sulphasalazine in healthy
- Mohammadi, A., Sahebkar, A., Iranshahi, M., Amini, M., Khojasteh, R., Ghayour-Mobarhan, M., and Ferns, G. A. Effects of supplementation with curcuminoids on dyslipidemia in obese patients: a randomized crossover trial. Phytother Res 2013;27(3):374-379. PubMed
- Chuengsamarn, S., Rattanamongkolgul, S., Luechapudiporn, R., Phisalaphong, C., and Jirawatnotai, S. Curcumin extract for prevention of type 2 diabetes. Diabetes Care 2012;35(11):2121-2127. PubMed
- Goh, C. L. and Ng, S. K. Allergic contact dermatitis to Curcuma longa (turmeric). Contact Dermatitis 1987;17(3):186. PubMed
- Srivastava, R., Puri, V., Srimal, R. C., and Dhawan, B. N. Effect of curcumin on platelet aggregation and vascular prostacyclin synthesis. Arzneimittelforschung. 1986;36(4):715-717.
- Srinivasan, M. Effect of curcumin on blood sugar as seen in a diabetic subject. Indian J Med Sci 1972;26(4):269-270.
- Srivastava, K. C., Bordia, A., and Verma, S. K. Curcumin, a major component of food spice turmeric (Curcuma longa) inhibits aggregation and alters eicosanoid metabolism in human blood platelets. Prostaglandins Leukot.Essent.Fatty Acids 1995;52(4):223-227 PubMed
- Oetari, S., Sudibyo, M., Commandeur, J. N., Samhoedi, R., and Vermeulen, N. P. Effects of curcumin on cytochrome P450 and glutathione S-transferase activities in rat liver. Biochem Pharmacol 1-12-1996;51(1):39-45. PubMed
- Kiec-Swierczynska, M. and Krecisz, B. Occupational allergic contact dermatitis due to curcumin food colour in a pasta factory worker. Contact Dermatitis 1998;39(1):30-31. PubMed
- Van Dau N, Ngoc Ham N, Huy Khac D, and et al. The effects of a traditional drug, tumeric (Curcuma longa), and placebo on the healing of duodenal ulcer. Phytomed 1998;5(1):29-34.
- Daveluy A, Géniaux H, Thibaud L, Mallaret M, Miremont-Salamé G, Haramburu F. Probable interaction between an oral vitamin K antagonist and turmeric (Curcuma longa). Therapie. 2014 Nov-Dec;69(6):519-20. PubMed
- Kuptniratsaikul V, Dajpratham P, Taechaarpornkul W, Buntragulpoontawee M, Lukkanapichonchut P, Chootip C, Saengsuwan J, Tantayakom K, Laongpech S. Efficacy and safety of Curcuma domestica extracts compared with ibuprofen in patients with knee osteoarthrit
- Madhu K, Chanda K, Saji MJ. Safety and efficacy of Curcuma longa extract in the treatment of painful knee osteoarthritis: a randomized placebo-controlled trial. Inflammopharmacology 2013;21(2):129-36. PubMed
- Mali AM, Behal R, Gilda SS. Comparative evaluation of 0.1% turmeric mouthwash with 0.2% chlorhexidine gluconate in prevention of plaque and gingivitis: A clinical and microbiological study. J Indian Soc Periodontol 2012;16(3):386-91. PubMed
- Sanmukhani J, Satodia V, Trivedi J, Patel T, Tiwari D, Panchal B, Goel A, Tripathi CB. Efficacy and safety of curcumin in major depressive disorder: a randomized controlled trial. Phytother Res 2014;28(4):579-85. PubMed
- Nayeri A, Wu S, Adams E, et al. Acute Calcineurin Inhibitor Nephrotoxicity Secondary to Turmeric Intake: A Case Report. Transplant Proc. 2017;49(1):198-200. PubMed
- Mitchell TM. Correspondence re: Somasundaram et al., Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2003;63(16):5165-6; author reply 5166-7.
- Somasundaram S, Edmund NA, Moore DT, Small GW, Shi YY, Orlowski RZ. Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2002;62(13):3868-75.
- Haroyan A, Mukuchyan V, Mkrtchyan N, et al. Efficacy and safety of curcumin and its combination with boswellic acid in osteoarthritis: a comparative, randomized, double-blind, placebo-controlled study. BMC Complement Altern Med. 2018;18(1):7. PubMed
- Al-Karawi D, Al Mamoori DA, Tayyar Y. The role of curcumin administration in patients with major depressive disorder: Mini meta-analysis of clinical trials. Phytother Res. 2016;30(2):175-83. PubMed
- Neerati P, Devde R, Gangi AK. Evaluation of the effect of curcumin capsules on glyburide therapy in patients with type-2 diabetes mellitus. Phytother Res. 2014;28(12):1796-800. PubMed
- Simental-Mendía LE, Pirro M, Gotto AM Jr, et al. Lipid-modifying activity of curcuminoids: A systematic review and meta-analysis of randomized controlled trials. Crit Rev Food Sci Nutr. 2017:1-10. PubMed
- Fung FY, Wong WH, Ang SK, et al. A randomized, double-blind, placebo- controlled study on the anti-haemostatic effects of Curcuma longa, Angelica sinensis and Panax ginseng. Phytomedicine. 2017;32:88-96. PubMed
- Small GW, Siddarth P, Li Z, et al. Memory and brain amyloid and tau effects of a bioavailable form of curcumin in non-demented adults: A double-blind, placebo-controlled 18-month trial. Am J Geriatr Psychiatry. 2018;26(3):266-277.
- Cruz-Correa M, Hylind LM, Marrero JH, et al. Efficacy and safety of curcumin in treatment of intestinal adenomas in patients with familial adenomatous polyposis. Gastroenterology. 2018 May 23. Pii:S0016-5085(18)34564-5. [Epub ahead of print] PubMed
- Rahmani S, Asgary S, Askari G, et al. Treatment of non-alcoholic fatty liver disease with curcumin: a randomized placebo-controlled trial. Phytother Res. 2016 Sep;30(9):1540-8. PubMed
- Lopez-Villafuerte L, CLores KH. Contact dermatitis caused by turmeric in a massage oil. Contact Dermatitis. 2016 Jul;75(1):52-3. PubMed
- Lukefahr AL, McEvoy S, Alfafara C, Funk JL. Drug-induced autoimmune hepatitis associated with turmeric dietary supplement use. BMJ Case Rep. 2018. pii: bcr-2018-224611. PubMed
- Medsafe Safety Communication- Turmeric/Curcumin Interaction with Warfarin. April 30, 2018. Accessed at: https://medsafe.govt.nz/safety/EWS/2018/Turmeric.asp.
- Imam Z, Khasawneh M, Jomaa D, Iftikhar H, Sayedahmad Z. Drug induced liver injury attributed to a curcumin supplement. Case Rep Gastrointest Med 2019 Oct 20;2019:6029403. doi: 10.1155/2019/6029403. PubMed
- Chand S, Hair C, Beswick L. A rare case of turmeric-induced hepatotoxicity. Intern Med J. 2020;50(2):258-259. PubMed
- Jiang N, Zhang M, Meng X, Sun B. Effects of Curcumin on the Pharmacokinetics of Amlodipine in Rats and Its Potential Mechanism. Pharm Biol. 2020;58(1):465-468. PubMed
- Lee BS, Bhatia T, Chaya CT, Wen R, Taira MT, Lim BS. Autoimmune Hepatitis Associated With Turmeric Consumption. ACG Case Rep J. 2020;7(3):e00320. PubMed
- Lombardi N, Crescioli G, Maggini V, et al. Acute liver injury following turmeric use in Tuscany: an analysis of the Italian Phytovigilance database and systematic review of case reports. Br J Clin Pharmacol. 2020. PubMed
- Suhail FK, Masood U, Sharma A, John S, Dhamoon A. Turmeric supplement induced hepatotoxicity: a rare complication of a poorly regulated substance. Clin Toxicol (Phila). 2020;58(3):216-217. PubMed
- Nakagawa Y, Mukai S, Yamada S, et al. The efficacy and safety of highly-bioavailable curcumin for treating knee osteoarthritis: a 6-month open-labeled prospective study. Clin Med Insights Arthritis Musculoskelet Disord. 2020;13:1179544120948471. PubMed
- Shafabakhsh R, Asemi Z, Reiner Z, Soleimani A, Aghadavod E, Bahmani F. The effects of nano-curcumin on metabolic status in patients with diabetes on hemodialysis, a randomized, double blind, placebo-controlled trial. Iran J Kidney Dis. 2020;14(4):290-9.
- Allegri P, Rosa R, Masala A, et al. Clinical effectiveness of a new oral curcumin formulation in acute non-infectious uveitic macular edema: a 12-month observational study. Eur Rev Med Pharmacol Sci 2022;26(1):46-53.
- Tsai IC, Hsu CW, Chang CH, Tseng PT, Chang KV. The effect of curcumin differs on individual cognitive domains across different patient populations: A systematic review and meta-analysis. Pharmaceuticals (Basel) 2021;14(12):1235. PubMed
- Alam MA, Bin Jardan YA, Raish M, Al-Mohizea AM, Ahad A, Al-Jenoobi FI. Herb-drug interaction: Pharmacokinetics and pharmacodynamics of anti-hypertensive drug amlodipine besylate in presence of lepidium sativum and curcuma longa. Xenobiotica 2022;1-9.
- Sohal A, Alhankawi D, Sandhu S, Chintanaboina J. Turmeric-induced hepatotoxicity: Report of 2 cases. Int Med Case Rep J 2021;14:849-852. PubMed
- Hussaarts KGAM, Hurkmans DP, Oomen-de Hoop E, et al. Impact of curcumin (with or without piperine) on the pharmacokinetics of tamoxifen. Cancers (Basel). 2019;11(3):403. PubMed
- Kalluru H, Mallayasamy SR, Kondaveeti SS, Chandrasekhar V, Kalachaveedu M. Effect of turmeric supplementation on the pharmacokinetics of paclitaxel in breast cancer patients: A study with population pharmacokinetics approach. Phytother Res 2022;36(4):1761 PubMed
- 109288 Halegoua-DeMarzio D, Navarro V, Ahmad J, et al. Liver injury associated with turmeric-A growing problem: Ten cases from the drug-induced liver injury network [DILIN]. Am J Med. 2022:S0002-9343(22)00740-9. PubMed
- Arzallus T, Izagirre A, Castiella A, Torrente S, Garmendia M, Zapata EM. Drug induced autoimmune hepatitis after turmeric intake. Gastroenterol Hepatol 2023. PubMed
- Gilad O, Rosner G, Ivancovsky-Wajcman D, et al. Efficacy of wholistic turmeric supplement on adenomatous polyps in patients with familial adenomatous polyposis-A randomized, double-blinded, placebo-controlled study. Genes (Basel) 2022;13(12):2182. PubMed
- Ahad A, Raish M, Abdelrahman IA, et al. Changes in pharmacokinetics and pharmacodynamics of losartan in experimental diseased rats treated with Curcuma longa and Lepidium sativum. Pharmaceuticals (Basel) 2022;16(1):33. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
- Kou H, Huang L, Jin M, He Q, Zhang R, Ma J. Effect of curcumin on rheumatoid arthritis: a systematic review and meta-analysis. Front Immunol 2023;14:1121655. PubMed
- Qiu L, Gao C, Wang H, et al. Effects of dietary polyphenol curcumin supplementation on metabolic, inflammatory, and oxidative stress indices in patients with metabolic syndrome: a systematic review and meta-analysis of randomized controlled trials. Front PubMed
- Sato T, Yagi A, Yamauchi M, et al. The use of an antioxidant enables accurate evaluation of the interaction of curcumin on organic anion-transporting polypeptides 4C1 by preventing auto-oxidation. Int J Mol Sci 2024;25(2):991. PubMed
- Washington O, Robinson E, Simh D, et al. Oxalate nephropathy and chronic turmeric supplementation: a case report. J Bras Nefrol 2024;46(1):99-106. PubMed
- Munshi R, Karande-Patil S, Kumbhar D, Deshmukh A, Hingorani L. A randomized, controlled, comparative, proof-of-concept study to evaluate the efficacy and safety of Nisha-Amalaki capsules in prediabetic patients for preventing progression to diabetes. J Ay PubMed
- Sharifi Razavi A, Mohajerani F, Niksolat F, Karimi N. Efficacy of topical curcumin on mild to moderate carpal tunnel syndrome: a randomized double-blind, placebo-controlled clinical trial. Pain Med 2024;25(5):327-333. PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. Curcumin Reduces Depression in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2414. PubMed
- Tehrani SD, Hosseini A, Shahzamani M, et al. Evaluation of the effectiveness of curcumin and piperine co-supplementation on inflammatory factors, cardiac biomarkers, atrial fibrillation, and clinical outcomes after coronary artery bypass graft surgery. Cl PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. The Effect of Curcumin on Reducing Atherogenic Risks in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2441. PubMed
- Dibaei M, Hosseini A, Lavasani H, Kiani-Dehkordi B, Rouini M. Assessment of metabolic interaction between curcumin and tramadol using the isolated perfused rat liver. Heliyon 2024;10(15):e35070. PubMed
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Sea Moss 3 references
- Darias-Rosales J, Rubio C, Gutiérrez ÁJ, Paz S, Hardisson A. Risk assessment of iodine intake from the consumption of red seaweeds (Palmaria palmata and Chondrus crispus). Environ Sci Pollut Res Int 2020;27(36):45737-45741. PubMed
- U.S. Department of Agriculture (USDA). Agricultural Research Service. FoodData Central. Seaweed, irishmoss, raw. April 2019. Available at: https://fdc.nal.usda.gov/fdc-app.html#/food-details/168456/nutrients. Accessed Aug. 30, 2022.
- Palmieri B, Vadalà M, Laurino C. Clinical effects of overwintered-stressed Chondrus Crispus and non-overwintered-stressed Chondrus crispus dietary supplementations. Asian J Med Sci. 2018; 9(6): 7-13. DOI
Elderberry 6 references
- Barak V, Halperin T, Kalickman I. The effect of Sambucol, a black elderberry-based, natural product, on the production of human cytokines: I. Inflammatory cytokines. Eur Cytokine Netw 2001;12:290-6..
- Elderberry (Sambucus species). The Poison Plant Patch, Novia Scotia Museum, 2007. Available at: http://museum.gov.ns.ca/poison/?section=species&id=117 (Accessed 16 October 2009).
- European elder. Canadian Poisonous Plants Information System. Available at: http://www.cbif.gc.ca/pls/pp/ppack.jump?p_null=all&p_psn=121&p_type=all&p_sci=comm&p_x=px (Accessed 16 October 2009).
- Raus K, Pleschka S, Klein P, Schoop R, Fisher P. Effect of an echinacea-based hot drink versus oseltamivir in Influenza treatment: a randomized, double-blind, double-dummy, multicenter, noninferiority clinical trial. . Curr Ther Res Clin Exp. 2015;20;77:6 PubMed
- Ramachandran A, Antala D, Pudasainee P, Panginikkod S, Gupta H. A Plausible Association Between the Use of Elderberry and Autoimmune Hepatitis. Cureus 2022;14(4):e24250. PubMed
- Agarwal N, Mangla A. Elderberry interaction with pazopanib in a patient with soft-tissue sarcoma: A case report and literature review. Mol Clin Oncol 2024;20(5):36. PubMed
Honey 40 references
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Bose B. Honey or sugar in treatment of infected wounds? Lancet 1982;1:963. PubMed
- Ozhan H, Akdemir R, Yazici M, et al. Cardiac emergencies caused by honey ingestion: a single centre experience. Emerg Med J 2004;21:742-4. PubMed
- Centers for Disease Control. Botulism in the Unites Sates, 1899-1996. Handbook for epidemiologists, clinicians, and laboratory workers, 1998. Available online: http://www.cdc.gov/ncidod/dbmd/diseaseinfo/botulism.PDF.
- Simon A, Traynor K, Santos K, et al. Medical honey for wound care - still the 'latest resort'? Evid Based Complement Alternat Med 2009;6:165-73. PubMed
- Gethin G, Cowman S. Case series of use of Manuka honey in leg ulceration. Int Wound J 2005;2:10-15. PubMed
- Ingle R, Levin J, Polinder K. Wound healing with honey - a randomised controlled trial. S Afr Med J 2006;96:831-5.
- Johnson DW, van Eps C, Mudge DW, et al. Randomized, controlled trial of topical exit-site application of honey (Medihoney) versus mupirocin for the prevention of catheter-associated infections in hemodialysis patients. J Am Soc Nephrol 2005;16:1456-62. PubMed
- Sukriti and Garg, S. K. Influence of honey on the pharmacokinetics of phenytoin in rabbits. Ind J Pharmacol 2002;34(147).
- Jung, A. and Ottosson, J. [Infantile botulism caused by honey]. Ugeskr Laeger 2001;163(2):169.
- Gunduz, A., Turedi, S., Uzun, H., and Topbas, M. Mad honey poisoning. Am J Emerg.Med 2006;24(5):595-598.
- van der Vorst, M. M., Jamal, W., Rotimi, V. O., and Moosa, A. Infant botulism due to consumption of contaminated commercially prepared honey. First report from the Arabian Gulf States. Med Princ.Pract. 2006;15(6):456-458. PubMed
- Tushar, T., Vinod, T., Rajan, S., Shashindran, C., and Adithan, C. Effect of honey on CYP3A4, CYP2D6 and CYP2C19 enzyme activity in healthy human volunteers. Basic Clin Pharmacol Toxicol 2007;100(4):269-272. PubMed
- Nilforoushzadeh, M. A., Jaffary, F., Moradi, S., Derakhshan, R., and Haftbaradaran, E. Effect of topical honey application along with intralesional injection of glucantime in the treatment of cutaneous leishmaniasis. BMC Complement Altern Med 2007;7:13. PubMed
- Koca, I. and Koca, A. F. Poisoning by mad honey: a brief review. Food Chem Toxicol 2007;45(8):1315-1318. PubMed
- Akinci, S., Arslan, U., Karakurt, K., and Cengel, A. An unusual presentation of mad honey poisoning: acute myocardial infarction. Int J Cardiol 2008;129(2):e56-e58. PubMed
- Yildirim, N., Aydin, M., Cam, F., and Celik, O. Clinical presentation of non-ST-segment elevation myocardial infarction in the course of intoxication with mad honey. Am J Emerg Med 2008;26(1):108.e-2. PubMed
- Shrestha, P., Vaidya, R., and Sherpa, K. Mad honey poisoning: a rare case report of seven cases. Nepal Med Coll J 2009;11(3):212-213.
- Fetzner, L., Burhenne, J., Weiss, J., Völker, M., Unger, M., Mikus, G., and Haefeli, W. E. Daily honey consumption does not change CYP3A activity in humans. J Clin Pharmacol 2011;51(8):1223-1232. PubMed
- Thamboo, A., Thamboo, A., Philpott, C., Javer, A., and Clark, A. Single-blind study of manuka honey in allergic fungal rhinosinusitis. J Otolaryngol Head Neck Surg 2011;40(3):238-243.
- Ahmed, A., Khan, R. A., Azim, M. K., Saeed, S. A., Mesaik, M. A., Ahmed, S., and Imran, I. Effect of natural honey on human platelets and blood coagulation proteins. Pak.J Pharm Sci 2011;24(3):389-397.
- Yarlioglues, M., Akpek, M., Ardic, I., Elcik, D., Sahin, O., and Kaya, M. G. Mad-honey sexual activity and acute inferior myocardial infarctions in a married couple. Tex.Heart Inst.J 2011;38(5):577-580.
- Biberoglu, S., Biberoglu, K., and Komsuoglu, B. Mad honey. JAMA 4-1-1988;259(13):1943.
- Biberoglu, K., Biberoglu, S., and Komsuoglu, B. Transient Wolff-Parkinson-White syndrome during honey intoxication. Isr.J.Med.Sci. 1988;24(4-5):253-254.
- Gössinger, H., Hruby, K., Pohl, A., Davogg, S., Sutterlütti, G., and Mathis, G. [Poisoning with andromedotoxin-containing honey]. Dtsch Med Wochenschr 1983;108(41):1555-1558.
- Fenicia, L., Ferrini, A. M., Aureli, P., and Pocecco, M. A case of infant botulism associated with honey feeding in Italy. Eur J Epidemiol 1993;9(6):671-673. PubMed
- Sutlupinar, N., Mat, A., and Satganoglu, Y. Poisoning by toxic honey in Turkey. Arch.Toxicol. 1993;67(2):148-150. PubMed
- von Malottki, K. and Wiechmann, H. W. [Acute life-threatening bradycardia: food poisoning by Turkish wild honey]. Dtsch.Med.Wochenschr. 7-26-1996;121(30):936-938.
- Abdulla CO, Ayubi A, Zulfiquer F, Santhanam G, Ahmed MA, Deeb J. Infant botulism following honey ingestion. BMJ Case Rep. 2012 Sep 7;2012.
- Johnson DW, Badve SV, Pascoe EM, Beller E, Cass A, Clark C, de Zoysa J, Isbel NM, McTaggart S, Morrish AT, Playford EG, Scaria A, Snelling P, Vergara LA, Hawley CM; HONEYPOT Study Collaborative Group. Antibacterial honey for the prevention of peritoneal-d
- Matos D, Serrano P, Menezes Brandão F. A case of allergic contact dermatitis caused by propolis-enriched honey. Contact Dermatitis. 2015 Jan;72(1):59-60. PubMed
- Oduwole O, Meremikwu MM, Oyo-Ita A, Udoh EE. Honey for acute cough in children. Cochrane Database Syst Rev. 2014 Dec 23;12:CD007094. PubMed
- Vezir E, Kaya A, Toyran M, Azkur D, Dibek Misirlioglu E, Kocabas CN. Anaphylaxis/angioedema caused by honey ingestion. Allergy Asthma Proc. 2014 Jan-Feb;35(1):71-4. PubMed
- Wang YT, Qi Y, Tang FY, et al. The effect of cupping therapy for low back pain: A meta-analysis based on existing randomized controlled trials. J Back Musculoskelet Rehabil. 2017;30(6):1187-1195. PubMed
- Oduwole O, Udoh EE, Oyo-Ita A, Meremikwu MM. Honey for acute cough in children. Cochrane Database Syst Rev. 2018;4:CD007094. PubMed
- Wong D, Albietz JM, Tran H, et al. Treatment of contact lens related dry eye with antibacterial honey. Cont Lens Anterior Eye. 2017;40(6):389-393. PubMed
- Martina SJ, Ramar LAP, Silaban MRI, Luthfi M, Govindan PAP. Antiplatelet Effectivity between Aspirin with Honey on Cardiovascular Disease Based on Bleeding Time Taken on Mice. Open Access Maced J Med Sci. 2019 Oct 14;7(20):3416-3420. PubMed
- Jhawar N, Gonzalez-Estrada A. Honey-induced anaphylaxis in an adult. QJM 2022;115(5):325-326. PubMed
- Di Costanzo M, De Paulis N, Peveri S, Montagni M, Berni Canani R, Biasucci G. Anaphylaxis caused by artisanal honey in a child: a case report. J Med Case Rep 2021;15(1):235. PubMed
Burdock 11 references
- Iwakami S, Wu JB, Ebizuka Y, Sankawa U. Platelet activating factor (PAF) antagonists contained in medicinal plants: lignans and sesquiterpenes. Chem Pharm Bull (Tokyo) 1992;40:1196-8. PubMed
- Sasaki Y, Kimura Y, Tsunoda T, Tagami H. Anaphylaxis due to burdock. Int J Dermatol 2003;42:472-3. PubMed
- Rhoads PM, Tong TG, Banner W Jr, Anderson R. Anticholinergic poisonings associated with commercial burdock root tea. J Toxicol Clin Toxicol 1984-85;22:581-4. PubMed
- Rodriguez P, Blanco J, Juste S, et al. Allergic contact dermatitis due to burdock (Arctium lappa). Contact Dermatitis 1995;33:134-5.
- Kassler, W. J., Blanc, P., and Greenblatt, R. The use of medicinal herbs by human immunodeficiency virus-infected patients. Arch Intern Med 1991;151(11):2281-2288. DOI
- Chan, Y. S., Cheng, L. N., Wu, J. H., Chan, E., Kwan, Y. W., Lee, S. M., Leung, G. P., Yu, P. H., and Chan, S. W. A review of the pharmacological effects of Arctium lappa (burdock). Inflammopharmacology. 2011;19(5):245-254. PubMed
- Breed, F. B. and Kuwabara, T. Burdock ophthalmia. Arch Ophthalmol 1966;75(1):16-20.
- Bryson, P. D., Watanabe, A. S., Rumack, B. H., and Murphy, R. C. Burdock root tea poisoning. Case report involving a commercial preparation. JAMA 5-19-1978;239(20):2157. DOI
- <p>Fletcher GF<span>, </span>Cantwell JD. Burdock root tea poisoning. JAMA <span>1978 Oct 6;240(15):1586.</span></p> DOI
- Latif A, Fichadiya H, Abid F, Capo G. Herbal Teas and Thrombocytopenia: A Curious Case of Yellow Dock and Burdock-Induced Thrombocytopenia. Eur J Case Rep Intern Med 2022;9(3):003247. PubMed
- Niazi B, Ahmed K, Ahmed M, Ali S, Song K, Elias S. Drug-Induced Liver Injury from Herbal Liver Detoxification Tea. Case Rep Gastroenterol 2022;16(3):612-617. PubMed
Ashwagandha 32 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Upton R, ed. Ashwagandha Root (Withania somnifera): Analytical, quality control, and therapuetic monograph. Santa Cruz, CA: American Herbal Pharmacopoeia 2000:1-25.
- Davis L, Kuttan G. Effect of Withania somnifera on cyclophosphamide-induced urotoxicity. Cancer Lett 2000;148:9-17. PubMed
- Davis L, Kuttan G. Suppressive effect of cyclophosphamide-induced toxicity by Withania somnifera extract in mice. J Ethnopharmacol 1998;62:209-14. PubMed
- Mishra LC, Singh BB, Dagenais S. Scientific basis for the therapeutic use of Withania somnifera (ashwagandha): a review. Altern Med Rev 2000;5:334-46. DOI
- Andallu B, Radhika B. Hypoglycemic, diuretic and hypocholesterolemic effect of winter cherry (Withania somnifera, Dunal) root. Indian J Exp Biol 2000;38:607-9.
- Kulkarni RR, Patki PS, Jog VP, et al. Treatment of osteoarthritis with a herbomineral formulation: a double-blind, placebo-controlled, cross-over study. J Ethnopharmacol 1991;33:91-5. PubMed
- Ahumada F, Aspee F, Wikman G, Hancke J. Withania somnifera exract. Its effects on arterial blood pressure in anaesthetized dogs. Phytother Res 1991;5:111-14.
- Panda S, Kar A. Withania somnifera and Bauhinia purpurea in the regulation of circulating thyroid hormone concentrations in female mice. J Ethnopharmacol 1999;67:233-39. PubMed
- Panda S, Kar A. Changes in thyroid hormone concentrations after administration of ashwagandha root extract to adult male mice. J Pharm Pharmacol 1998;50:1065-68. PubMed
- Sehgal, V. N., Verma, P., and Bhattacharya, S. N. Fixed-drug eruption caused by ashwagandha (Withania somnifera): a widely used Ayurvedic drug. Skinmed. 2012;10(1):48-49.
- Agnihotri AP, Sontakke SD, Thawani VR, Saoji A, Goswami VS. Effects of Withania somnifera in patients of schizophrenia: a randomized, double blind, placebo controlled pilot trial study. Indian J Pharmacol. 2013;45(4):417-8. PubMed
- Biswal BM, Sulaiman SA, Ismail HC, Zakaria H, Musa KI. Effect of Withania somnifera (Ashwagandha) on the development of chemotherapy-induced fatigue and quality of life in breast cancer patients. Integr Cancer Ther. 2013;12(4):312-22.
- Sharma AK, Basu I, Singh S. Efficacy and safety of Ashwagandha root extract in subclinical hypothyroid patients: a double-blind, randomized placebo-controlled trial. J Altern Complement Med. 2018 Mar;24(3):243-248. PubMed
- Durg S, Bavage S, Shivaram SB. Withania somnifera (Indian ginseng) in diabetes mellitus: A systematic review and meta-analysis of scientific evidence from experimental research to clinical application. Phytother Res. 2020;34(5):1041-1059.
- Björnsson HK, Björnsson ES, Avula B, et al. Ashwagandha-induced liver injury: A case series from Iceland and the US Drug-Induced Liver Injury Network. Liver Int. 2020;40(4):825-829. PubMed
- Tharakan A, Shukla H, Benny IR, Tharakan M, George L, Koshy S. Immunomodulatory Effect of Withania somnifera (Ashwagandha) Extract-A Randomized, Double-Blind, Placebo Controlled Trial with an Open Label Extension on Healthy Participants. J Clin Med 2021;1 PubMed
- Ireland PJ, Hardy T, Burt AD, Donnelly MC. Drug-induced hepatocellular injury due to herbal supplement ashwagandha. J R Coll Physicians Edinb. 2021;51(4):363-365. PubMed
- Kamal HI, Patel K, Brdak A, Heffernan J, Ahmad N. Ashwagandha as a unique cause of thyrotoxicosis presenting with supraventricular tachycardia. Cureus. 2022 Mar 25;14(3):e23494. PubMed
- Suryawanshi G, Abdallah M, Thomson M, Desai N, Chauhan A, Lim N. Ashwagandha-Associated Acute Liver Failure Requiring Liver Transplantation. Am J Ther 2023;30(1):e80-e83. PubMed
- Pusec CM, Wolsky R, Llerena C, Sura P. A Case of Supplement-Induced Hepatitis. Cureus 2022;14(10):e30433. PubMed
- Ajgaonkar A, Jain M, Debnath K. Efficacy and Safety of Ashwagandha (Withania somnifera) Root Extract for Improvement of Sexual Health in Healthy Women: A Prospective, Randomized, Placebo-Controlled Study. Cureus 2022;14(10):e30787. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Lubarska M, Halasinski P, Hryhorowicz S, et al. Liver Dangers of Herbal Products: A Case Report of Ashwagandha-Induced Liver Injury. Int J Environ Res Public Health 2023;20(5):3921. PubMed
- Tóth M, Benedek AE, Longerich T, Seitz HK. Ashwagandha-induced acute liver injury: A case report. Clin Case Rep 2023;11(3):e7078.
- Bokan G, Glamocanin T, Mavija Z, et al. Herb-Induced Liver Injury by Ayurvedic Ashwagandha as Assessed for Causality by the Updated RUCAM: An Emerging Cause. Pharmaceuticals (Basel) 2023;16(8):1129. PubMed
- Patel PA, Sanborn E, Then R, Williams DM. Recurrent Reversible Cerebral Vasoconstriction Syndrome: A Report of Two Cases. Cureus 2023;15(8):e42992. PubMed
- Majeed M, Nagabhushanam K, Murali A, Vishwanathan DT, Mamidala RV, Mundkur L. A Standardized Withania somniferra (Linn.) Root Extract with Piperine Alleviates the Symptoms of Anxiety and Depression by Increasing Serotonin Levels: A Double-Blind, Randomize
- Philips CA, Valsan A, Theruvath AH, et al. Ashwagandha-induced liver injury-A case series from India and literature review. Hepatol Commun 2023;7(10):e0270. PubMed
- Hayashi M, Hamada H, Azuma SI, Hayashi K. Painless Thyroiditis by Withania somnifera (Ashwagandha). Cureus 2024;16(3):e55352. PubMed
- Vazirani S, Kothari A, Fujimoto J, Gomez M. Supplements Are Not a Synonym for Safe: Suspected Liver Injury From Ashwagandha. Fed Pract 2023;40(9):315-319. PubMed
- Patel M, Newell R, Hillier M, Ramalingam R. Herbal remedies as a potential cause of hypoadrenalism. Br J Hosp Med (Lond) 2024;85(6):1-4. PubMed
Fucus Vesiculosus 15 references
- Goodman GA, Rall TW, Nies AS, Taylor P. The Pharmacological Basis of Therapeutics, 9th ed.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Phaneuf D, Cote I, Dumas P, et al. Evaluation of the contamination of marine algae (Seaweed) from the St. Lawrence River and likely to be consumed by humans. Environ Res 1999;80:S175-S182. PubMed
- Durig J, Bruhn T, Zurborn KH, et al. Anticoagulant fucoidan fractions from Fucus vesiculosus induce platelet activation in vitro. Thromb Res 1997;85:479-91. PubMed
- Conz PA, La Greca G, Benedetti P, et al. Fucus vesiculosus: a nephrotoxic alga? Nephrol Dial Transplant 1998;13:526-7.
- Ohye H, Fukata S, Kanoh M, et al. Thyrotoxicosis caused by weight-reducing herbal medicines. Arch Intern Med 2005;165:831-4. PubMed
- Okamura K, Inoue K, Omae T. A case of Hashimoto's thyroiditis with thyroid immunological abnormality manifested after habitual ingestion of seaweed. Acta Endocrinol (Copenh) 1978;88:703-12. PubMed
- Agarwal SC, Crook JR, Pepper CB. Herbal remedies -- how safe are they? A case report of polymorphic ventricular tachycardia/ventricular fibrillation induced by herbal medication used for obesity. Int J Cardiol 2006;106:260-1. PubMed
- Sterling JB, Heymann WR. Potassium iodide in dermatology: a 19th century drug for the 21st century-uses, pharmacology, adverse effects, and contraindications. J Am Acad Dermatol 2000;43:691-7. PubMed
- Catania, M. A., Oteri, A., Caiello, P., Russo, A., Salvo, F., Giustini, E. S., Caputi, A. P., and Polimeni, G. Hemorrhagic cystitis induced by an herbal mixture. South.Med.J. 2010;103(1):90-92. PubMed
- Cumashi, A., Ushakova, N. A., Preobrazhenskaya, M. E., D'Incecco, A., Piccoli, A., Totani, L., Tinari, N., Morozevich, G. E., Berman, A. E., Bilan, M. I., Usov, A. I., Ustyuzhanina, N. E., Grachev, A. A., Sanderson, C. J., Kelly, M., Rabinovich, G. A., I
- Irhimeh, M. R., Fitton, J. H., and Lowenthal, R. M. Pilot clinical study to evaluate the anticoagulant activity of fucoidan. Blood Coagul.Fibrinolysis 2009;20(7):607-610. PubMed
- Arbaizar, B. and Llorca, J. [Fucus vesiculosus induced hyperthyroidism in a patient undergoing concomitant treatment with lithium]. Actas Esp.Psiquiatr. 2011;39(6):401-403.
- Church FC, Meade JB, Treanor RE, and et al. Antithrombin activity of fucoidan. The interaction of fucoidan with heparin cofactor II, antithrombin III, and thrombin. J Biol Chem 2-25-1989;264(6):3618-3623. DOI
- Mathew L, Burney M, Gaikwad A, et al. Preclinical evaluation of safety of fucoidan extracts from Undaria pinnatifida and Fucus vesiculosus for use in cancer treatment. Integr Cancer Ther 2017;16(4):572-84.
Black Seed 60 references
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- Aqel M, Shaheen R. Effects of the volatile oil of black seed seeds on the uterine smooth muscle of rat and guinea pig. J Ethnopharmacol 1996;52:23-6.
- Keshri G, Singh MM, Lakshmi V, Kamboj VP. Post-coital contraceptive efficacy of the seeds of Black seed in rats. Indian J Physiol Pharmacol 1995;39:59-62.
- Tennekoon KH, Jeevathayaparan S, Kurukulasooriya AP, Karunanayake EH. Possible hepatotoxicity of Nigella sativa seeds and Dregea volubilis leaves. J Ethnopharmacol 1991;31:283-9. PubMed
- Dehkordi FR, Kamkhah AF. Antihypertensive effect of Nigella sativa seed extract in patients with mild hypertension. Fundam Clin Pharmacol 2008;22:447-52.
- Zaoui, A., Cherrah, Y., Lacaille-Dubois, M. A., Settaf, A., Amarouch, H., and Hassar, M. [Diuretic and hypotensive effects of Nigella sativa in the spontaneously hypertensive rat]. Therapie 2000;55(3):379-382.
- Enomoto, S., Asano, R., Iwahori, Y., Narui, T., Okada, Y., Singab, A. N., and Okuyama, T. Hematological studies on black cumin oil from the seeds of Nigella sativa L. Biol.Pharm.Bull 2001;24(3):307-310. PubMed
- Meral, I., Yener, Z., Kahraman, T., and Mert, N. Effect of Nigella sativa on glucose concentration, lipid peroxidation, anti-oxidant defence system and liver damage in experimentally-induced diabetic rabbits. J Vet.Med A Physiol Pathol.Clin Med 2001;48(1
- Al Jishi, S. A. and Abuo, Hozaifa B. Effect of Nigella sativa on blood hemostatic function in rats. J Ethnopharmacol. 2003;85(1):7-14. PubMed
- Ali, B. H. and Blunden, G. Pharmacological and toxicological properties of Nigella sativa. Phytother.Res. 2003;17(4):299-305.
- Al Naggar, T. B., Gomez-Serranillos, M. P., Carretero, M. E., and Villar, A. M. Neuropharmacological activity of Nigella sativa L. extracts. J Ethnopharmacol. 2003;88(1):63-68. PubMed
- Kalus, U., Pruss, A., Bystron, J., Jurecka, M., Smekalova, A., Lichius, J. J., and Kiesewetter, H. Effect of Nigella sativa (black seed) on subjective feeling in patients with allergic diseases. Phytother.Res. 2003;17(10):1209-1214.
- Islam, S. N., Begum, P., Ahsan, T., Huque, S., and Ahsan, M. Immunosuppressive and cytotoxic properties of Nigella sativa. Phytother.Res. 2004;18(5):395-398.
- Fararh, K. M., Atoji, Y., Shimizu, Y., Shiina, T., Nikami, H., and Takewaki, T. Mechanisms of the hypoglycaemic and immunopotentiating effects of Nigella sativa L. oil in streptozotocin-induced diabetic hamsters. Res Vet.Sci 2004;77(2):123-129. PubMed
- Awad, E. M. and Binder, B. R. In vitro induction of endothelial cell fibrinolytic alterations by Nigella sativa. Phytomedicine 2005;12(3):194-202. PubMed
- El Obeid, A., Al Harbi, S., Al Jomah, N., and Hassib, A. Herbal melanin modulates tumor necrosis factor alpha (TNF-alpha), interleukin 6 (IL-6) and vascular endothelial growth factor (VEGF) production. Phytomedicine. 2006;13(5):324-333.
- Abbas, A. T., Abdel-Aziz, M. M., Zalata, K. R., and Tel, Abd Al-Galel. Effect of dexamethasone and Nigella sativa on peripheral blood eosinophil count, IgG1 and IgG2a, cytokine profiles and lung inflammation in murine model of allergic asthma. Egypt J Im
- Kaleem, M., Kirmani, D., Asif, M., Ahmed, Q., and Bano, B. Biochemical effects of Nigella sativa L seeds in diabetic rats. Indian J Exp.Biol. 2006;44(9):745-748.
- Hawsawi, Z. A., Ali, B. A., and Bamosa, A. O. Effect of Nigella sativa (Black Seed) and thymoquinone on blood glucose in albino rats. Ann.Saudi Med 2001;21(3-4):242-244.
- Massadeh, A. M., Al Safi, S. A., Momani, I. F., Al Mahmoud, M., and Alkofahi, A. S. Analysis of cadmium and lead in mice organs: effect of Nigella sativa L. (Black Cumin) on the distribution and immunosuppressive effect of cadmium-lead mixture in mice. B PubMed
- Akhondian, J., Parsa, A., and Rakhshande, H. The effect of Nigella sativa L. (black cumin seed) on intractable pediatric seizures. Med Sci Monit. 2007;13(12):CR555-CR559.
- Meddah, B., Ducroc, R., El Abbes, Faouzi M., Eto, B., Mahraoui, L., Benhaddou-Andaloussi, A., Martineau, L. C., Cherrah, Y., and Haddad, P. S. Nigella sativa inhibits intestinal glucose absorption and improves glucose tolerance in rats. J Ethnopharmacol. PubMed
- Najmi, A., Nasiruddin, M., Khan, R. A., and Haque, S. F. Effect of Nigella sativa oil on various clinical and biochemical parameters of insulin resistance syndrome. Int J Diabetes Dev.Ctries. 2008;28(1):11-14.
- al Sheikh, O. A. and Gad el-Rab, M. O. Allergic contact dermatitis: clinical features and profile of sensitizing allergens in Riyadh, Saudi Arabia. Int J Dermatol. 1996;35(7):493-497.
- Steinmann, A., Schatzle, M., Agathos, M., and Breit, R. Allergic contact dermatitis from black cumin (Nigella sativa) oil after topical use. Contact Dermatitis 1997;36(5):268-269.
- Al-Jenoobi FI, Al-Suwayeh SA, Muzaffar I, et al. Effects of Nigella sativa and Lepidium sativum on cyclosporine pharmacokinetics. Biomed Res Int 2013;2013:953520.
- Arslan E, Sayin S, Demirbas S, et al. A case study report of acute renal failure associated with Nigella sativa in a diabetic patient. J Integr Med 2013;11:64-6. PubMed
- Bamosa AO, Kaatabi H, Lebdaa FM, et al. Effect of Nigella sativa seeds on the glycemic control of patients with type 2 diabetes mellitus. Indian J Physiol Pharmacol 2010;54:344-54.
- Bonhomme A, Poreaux C, Jouen F, et al. Bullous drug eruption to Nigella sativa oil: Consideration of the use of a herbal medicine - clinical report and review of the literature. J Eur Acad Dermatol Venereol 2017;31:e217-e219.
- Farhangi MA, Dehghan P, Tajmiri S, Abbasi MM. The effects of Nigella sativa on thyroid function, serum Vascular Endothelial Growth Factor (VEGF) - 1, Nesfatin-1 and anthropometric features in patients with Hashimoto's thyroiditis: a randomized controlled
- Kaatabi H, Bamosa AO, Badar A, et al. Nigella sativa improves glycemic control and ameliorates oxidative stress in patients with type 2 diabetes mellitus: placebo controlled participant blinded clinical trial. PLoS One 2015;10:e0113486. PubMed
- Mohtashami R, Huseini HF, Heydari M, et al. Efficacy and safety of honey based formulation of Nigella sativa seed oil in functional dyspepsia: A double blind randomized controlled clinical trial. J Ethnopharmacol 2015;175:147-52. PubMed
- Perveen T, Haider S, Zuberi NA, et al. Increased 5-HT levels following repeated administration of Nigella sativa L. (Black Seed) oil produce antidepressant effects in rats. Sci Pharm 2013;82:161-70. PubMed
- Sahebkar A, Soranna D, Liu X, et al. A systematic review and meta-analysis of randomized controlled trials investigating the effects of supplementation with Nigella sativa (black seed) on blood pressure. J Hypertens 2016;34:2127-35. PubMed
- Shawki M, El Wakeel L, Shatla R, et al. The clinical outcome of adjuvant therapy with black seed oil on intractable paediatric seizures: a pilot study. Epileptic Disord 2013;15:295-301. PubMed
- Muneera KE, Majeed A, Naveed AK. Comparative evaluation of nigella sativa (Kalonji) and simvastatin for the treatment of hyperlipidemia and in the induction of hepatotoxicity. Pak J Pharm Sci. 2015 Mar;28(2):493-8.
- Mahdavi R, Namazi N, Alizadeh M, Farajnia S. Effects of Nigella sativa oil with a low-calorie diet on cardiometabolic risk factors in obese women: a randomized controlled clinical trial. Food Funct. 2015;6(6):2041-8. PubMed
- Fallah Huseini H, Amini M, Mohtashami R, et al. Blood pressure lowering effect of Nigella sativa L. seed oil in healthy volunteers: a randomized, double-blind, placebo-controlled clinical trial. Phytother Res. 2013;27(12):1849-53.
- Dehavay F, Kolivras A, Scheers C. Local and systemic adverse skin reactions following the use of herbal products believed to contain Nigella sativa seeds and oil. Contact Dermatitis. 2019 Mar;80(3):176-177.
- Kooshki A, Tofighiyan T, Rastgoo N, Rakhshani MH, Miri M. Effect of Nigella sativa oil supplement on risk factors for cardiovascular diseases in patients with type 2 diabetes mellitus. Phytother Res. 2020.
- Warner ME, Warner PA, Sprung J, Warner MA. Black seed oil and perioperative serotonin syndrome: A case report. A A Pract. 2019;13(11):420-422. PubMed
- Alam MA, Bin Jardan YA, Raish M, Al-Mohizea AM, Ahad A, Al-Jenoobi FBI. Effect of Nigella sativa and fenugreek on the pharmacokinetics and pharmacodynamics of amlodipine in hypertensive rats. Curr Drug Metab. 2020;21(4):318-325. PubMed
- Moustafa HAM, El Wakeel LM, Halawa MR, Sabri NA, El-Bahy AZ, Singab AN. Effect of Nigella sativa oil versus metformin on glycemic control and biochemical parameters of newly diagnosed type 2 diabetes mellitus patients. Endocrine 2019;65(2):286-94. PubMed
- Safi S, Razmpoosh E, Fallahzadeh H, et al. The effect of Nigella sativa on appetite, anthropometric and body composition indices among overweight and obese women: A crossover, double-blind, placebo-controlled, randomized clinical trial. Complement Ther Me PubMed
- Wang X, Jiang A, Batra V. Severe thrombocytopenia associated with black seed oil and evening primrose oil. Cureus. 2020;12(6):e8390. PubMed
- Alkharfy K, Jan B, Alotaibi K, et al. Clopidogrel-herb Interactions: A Pharmacokinetic and Pharmacodynamic Assessment in a Rat Model. Curr Drug Metab 2021;22(12):969-977. PubMed
- Bin Jardan YA, Ahad A, Raish M, Alam MA, Al-Mohizea AM, Al-Jenoobi FI. Effects of garden cress, fenugreek and black seed on the pharmacodynamics of metoprolol: an herb-drug interaction study in rats with hypertension. Pharm Biol 2021;59(1):1088-1097. PubMed
- Thomas JV, Mohan ME, Prabhakaran P, Das S S, Maliakel B, I M K. A phase I clinical trial to evaluate the safety of thymoquinone-rich black cumin oil (BlaQmax®) on healthy subjects: Randomized, double-blinded, placebo-controlled prospective study. Toxicol PubMed
- Assier H, Kouby F, Ingen-Housz-Oro S, Roux C. Severe allergic contact connubial dermatitis to Nigella Sativa Seed Oil due to repeated contacts to beard cosmetics. Contact Dermatitis 2022. PubMed
- Koshak AE, Koshak EA, Mobeireek AF, et al. Nigella sativa for the treatment of COVID-19: An open-label randomized controlled clinical trial. Complement Ther Med 2021;61:102769. PubMed
- Hadi S, Daryabeygi-Khotbehsara R, Mirmiran P, et al. Effect of Nigella sativa oil extract on cardiometabolic risk factors in type 2 diabetes: A randomized, double-blind, placebo-controlled clinical trial. Phytother Res 2021;35(7):3747-3755.
- Ali SM, Chen P, Sheikh S, et al. Thymoquinone with metformin decreases fasting, post prandial glucose, and HbA1c in type 2 diabetic patients. Drug Res (Stuttg) 2021;71(6):302-306. PubMed
- Tavakoli-Rouzbehani OM, Abbasnezhad M, Kheirouri S, Alizadeh M. Effects of Nigella sativa oil supplementation on selected metabolic parameters and anthropometric indices in patients with coronary artery disease: A randomized, double-blind, placebo-control
- Fargeas M, Calugareanu A, Ben-Said B. Drug reaction with eosinophilia and systemic symptoms (DRESS) syndrome after topical use of Nigella sativa (black cumin) oil. Contact Dermatitis 2022;87(2):203-204.
- Wang Z, Wang Z, Wang X, et al. Potential food-drug interaction risk of thymoquinone with warfarin. Chem Biol Interact. 2022;365:110070. PubMed
- Wang Z, Wang X, Wang Z, et al. Potential herb-drug interaction risk of thymoquinone and phenytoin. Chem Biol Interact. 2022;353:109801. PubMed
- Al-Mohizea AM, Ahad A, El-Maghraby GM, et al. Effects of Nigella sativa, Lepidium sativum and Trigonella foenum-graecum on sildenafil disposition in beagle dogs. Eur J Drug Metab Pharmacokinet. 2015;40(2):219-24. PubMed
- Alkharfy KM, Al-Jenoobi FI, Al-Mohizea AM, et al. Effects of Lepidium sativum, Nigella sativa and Trigonella foenum-graceum on phenytoin pharmacokinetics in beagle dogs. Phytother Res. 2013;27(12):1800-4.
- Abutaima R, Al-Ebini Y, Alkofahi A, et al. In vivo assessment of black seed oil single dose on prednisolone pharmacokinetics. J Pharm Pharmacol 2024;76(1):57-63.
- Sener K, Cakir A, Yesiloglu O, Altug E, Guven R, Korkut S. Rhabdomyolysis and acute kidney injury after consumption of black seed oil. Toxicon 2024;245:107787. PubMed
Apple Cider Vinegar 11 references
- Lhotta K, Hofle G, Gasser R, Finkenstedt G. Hypokalemia, hyperreninemia, and osteoporosis in a patient ingesting large amounts of cider vinegar. Nephron 1998;80:242-3. PubMed
- Hill LL, Woodruff LH, Foote JC, Barreto-Alcoba M. Esophageal injury by apple cider vinegar tablets and subsequent evaluation of products. J Am Diet Assoc 2005;105:1141-4. PubMed
- Hlebowicz J, Darwiche G, Björgell O, Almér LO. Effect of apple cider vinegar on delayed gastric emptying in patients with type 1 diabetes mellitus: a pilot study. BMC Gastroenterol 2007;7:46. PubMed
- Johnston CS, Kim CM, Buller AJ. Vinegar improves insulin sensitivity to a high-carbohydrate meal in subjects with insulin resistance or type 2 diabetes. Diabetes Care 2004;27:281-2. PubMed
- Lhotta, K., Hofle, G., Gasser, R., and Finkenstedt, G. Hypokalemia, hyperreninemia and osteoporosis in a patient ingesting large amounts of cider vinegar. Nephron 1998;80(2):242-243. PubMed
- Bunick CG, Lott JP, Warren CB, et al. Chemical burn from topical apple cider vinegar. J Am Acad Dermatol 2012;67(4):e143-4. PubMed
- Feldstein S, Afshar M, Krakowski AC. Chemical Burn from Vinegar Following an Internet-based Protocol for Self-removal of Nevi. J Clin Aesthet Dermatol. 2015 Jun;8(6):50.
- Luu LA, Flowers RH, Kellams AL, et al. Apple cider vinegar soaks [0.5%] as a treatment for atopic dermatitis do not improve skin barrier integrity. Pediatr Dermatol. 2019;36(5):634-639. PubMed
- Hadi A, Pourmasoumi M, Najafgholizadeh A, Clark CCT, Esmaillzadeh A. The effect of apple cider vinegar on lipid profiles and glycemic parameters: a systematic review and meta-analysis of randomized clinical trials. BMC Complement Med Ther 2021;21(1):179. PubMed
- Feise NK, Johnston CS. Commercial vinegar tablets do not display the same physiological benefits for managing postprandial glucose concentrations as liquid vinegar. J Nutr Metab 2020;2020:9098739. PubMed
- Gheflati A, Bashiri R, Ghadiri-Anari A, Reza JZ, Kord MT, Nadjarzadeh A. The effect of apple vinegar consumption on glycemic indices, blood pressure, oxidative stress, and homocysteine in patients with type 2 diabetes and dyslipidemia: A randomized contro
Yellow Dock 8 references
- Newall CA, Anderson LA, Philpson JD. Herbal Medicine: A Guide for Healthcare Professionals. London, UK: The Pharmaceutical Press, 1996.
- Foster S, Tyler VE. Tyler's Honest Herbal: A Sensible Guide to the Use of Herbs and Related Remedies. 3rd ed., Binghamton, NY: Haworth Herbal Press, 1993.
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Ellenhorn MJ, et al. Ellenhorn's Medical Toxicology: Diagnoses and Treatment of Human Poisoning. 2nd ed. Baltimore, MD: Williams & Wilkins, 1997.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Latif A, Fichadiya H, Abid F, Capo G. Herbal Teas and Thrombocytopenia: A Curious Case of Yellow Dock and Burdock-Induced Thrombocytopenia. Eur J Case Rep Intern Med 2022;9(3):003247. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC