
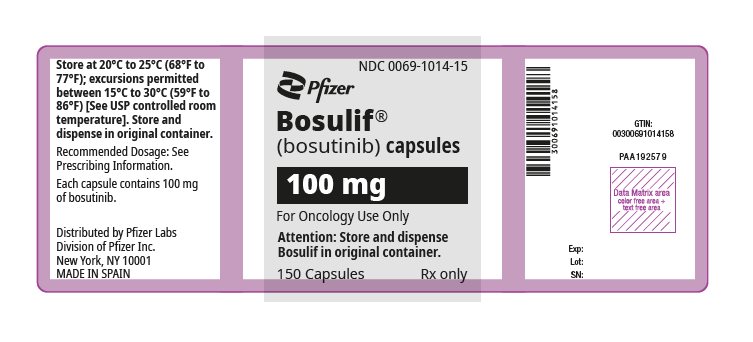
BOSULIF Bosutinib 100 mg Capsule, 150-count — NDC 0069-1014-15 (Billing 00069-1014-15)
This is a package of 150 capsules of BOSULIF Bosutinib 100 mg Capsule from Pfizer Laboratories Div Pfizer Inc, marketed since Jan 2024 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0069-1014-15 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0069 labeler · 1014 product · 15 package
- Package marketed since
- Jan 2, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 150 EA per package
- Barcode (UPC)
- 0300691014158, 0300690504308, 0300690193014, 0300690136011 +1 more
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 085626
- GCN: 55143
- GPI-14 (Medi-Span): 21531812000130
- HICL (First Databank): 039590
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 1307624
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Bosutinib is used to treat a certain type of chronic myeloid leukemia (CML; a type of cancer of the white blood cells), including treatment in adults who have been recently found to have this condition and in those who can no longer benefit from other medications for CML or who cannot take these medications because of side effects. Bosutinib is in a class of medications called kinase inhibitors. It works by blocking the action of an abnormal protein that signals cancer cells to multiply. This helps stop the spread of cancer cells.
Read the full MedlinePlus article ↗- You have a type of leukemia called Ph+ CML, which is driven by a faulty protein in your blood cells called BCR-ABL. Think of it like a stuck 'on' switch that keeps telling those ce...
- What exactly is bosutinib treating in my body?
- Yes — this is actually pretty important. Food significantly increases how much of the medicine your body absorbs, so taking it on an empty stomach means you'd be getting much less...
- Do I have to take it with food every single time?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Bosutinib — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $186.27 | $27,940.74 / 150 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00069-1014-15 You're viewing this Main listing | 150 CAPSULE in 1 BOTTLE | 2024-01-02 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bosulif 100 mgthis 00069-1014-15 | Pfizer | 150 capsules | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11103497 ↗ | Method of use | U-3216 | Feb 28, 2034 |
| US 11103497 ↗ | Method of use | U-3216 | Feb 28, 2034 |
| US 11103497 ↗ | Method of use | U-3217 | Feb 28, 2034 |
| US 11103497 ↗ | Method of use | U-3217 | Feb 28, 2034 |
| US 7417148 ↗ | Method of use | U-3707 | Dec 11, 2025 |
| US 7417148 ↗ | Method of use | U-3707 | Dec 11, 2025 |
| US 7417148 ↗ | Method of use | U-3708 | Dec 11, 2025 |
| US 7417148 ↗ | Method of use | U-3708 | Dec 11, 2025 |
| US 7919625 ↗ | Drug product | — | Dec 11, 2025 |
| US 7767678 ↗ | Drug substance | — | Nov 23, 2026 |
| US 7919625 ↗ | Drug product | — | Dec 11, 2025 |
| US 7767678 ↗ | Drug substance | — | Nov 23, 2026 |
| US 7919625*PED ↗ | Drug product | — | Jun 11, 2026 |
| US 11103497*PED ↗ | Drug product | — | Aug 28, 2034 |
| US 11103497*PED ↗ | Drug product | — | Aug 28, 2034 |
| US 7919625*PED ↗ | Drug product | — | Jun 11, 2026 |
| US 7767678*PED ↗ | Drug product | — | May 23, 2027 |
| US 7767678*PED ↗ | Drug product | — | May 23, 2027 |
| US 7417148*PED ↗ | Drug product | — | Jun 11, 2026 |
| US 7417148*PED ↗ | Drug product | — | Jun 11, 2026 |
| Code | What it grants | Expires |
|---|---|---|
| NP | New Product | Sep 26, 2026 |
| ODE-444 | Orphan Drug Exclusivity (7-year) | Sep 26, 2030 |
| NP | New Product | Sep 26, 2026 |
| ODE-444 | Orphan Drug Exclusivity (7-year) | Sep 26, 2030 |
| PED | Pediatric Exclusivity (+6 months) | Mar 26, 2031 |
| PED | Pediatric Exclusivity (+6 months) | Mar 26, 2031 |
| PED | Pediatric Exclusivity (+6 months) | Mar 26, 2027 |
| PED | Pediatric Exclusivity (+6 months) | Mar 26, 2027 |
Is there a generic version of BOSULIF 100 MG CAPSULE?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Bosutinib inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII K0KQV10C35
Povidone K25 is a synthetic polymer made from vinyl pyrrolidone. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach for better absorption.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
15 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Pfizer Laboratories Div Pfizer Inc labeler code 00069
- INFLECTRA infliximab-dyyb 100 mg/10mL Injection, Powder, Lyophilized, For Solution NDC 0069-0809-01
- SUTENT Sunitinib malate 37.5 mg Capsule NDC 0069-0830-38
- SUTENT Sunitinib malate 50 mg Capsule NDC 0069-0980-38
- Xeljanz tofacitinib 5 mg Tablet, Film Coated NDC 0069-1001-01
- Xeljanz tofacitinib 10 mg Tablet, Film Coated NDC 0069-1002-01
- Panzyga immune globulin intravenous (human) 100 mg/mL Solution NDC 0069-1011-02
- XELJANZ tofacitinib 1 mg/mL Solution NDC 0069-1029-02
- Cutaquig immunoglobulin G 165 mg/mL Solution NDC 0069-1061-02
- Panzyga immune globulin intravenous (human) 100 mg/mL Solution NDC 0069-1109-02
- Talzenna talazoparib 1 mg Capsule NDC 0069-1195-30
- Vizimpro dacomitinib 30 mg Tablet, Film Coated NDC 0069-1198-30
- Panzyga immune globulin intravenous (human) 100 mg/mL Solution NDC 0069-1224-02
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BOSULIF is indicated for the treatment of: • Adult and pediatric patients 1 year of age and older with chronic phase (CP) Philadelphia chromosome-positive chronic myelogenous leukemia (Ph+ CML), newly-diagnosed or resistant or intolerant to prior therapy [see Clinical Studies ( 14.1 , 14.2 , 14.3 )] . • Adult patients with accelerated phase (AP), or blast phase (BP) Ph+ CML with resistance or intolerance to prior therapy [see Clinical Studies (14.2) ] . BOSULIF is a kinase inhibitor indicated for the treatment of • adult and pediatric patients 1 year of age and older with chronic phase Ph+ chronic myelogenous leukemia (CML), newly-diagnosed or resistant or intolerant to prior therapy.
( 1 ) • adult patients with accelerated, or blast phase Ph+ CML with resistance or intolerance to prior therapy. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Adult patients with newly-diagnosed chronic phase Ph+ CML: 400 mg orally once daily with food. ( 2.1 ) • Adult patients with chronic, accelerated, or blast phase Ph+ CML with resistance or intolerance to prior therapy: 500 mg orally once daily with food. ( 2.1 ) • Pediatric patients with newly-diagnosed chronic phase Ph+ CML: 300 mg/m 2 orally once daily with food.
( 2.1 ) • Pediatric patients with chronic phase Ph+ CML with resistance or intolerance to prior therapy: 400 mg/m 2 orally once daily with food. ( 2.1 ) • Consider dose escalation by increments of 100 mg once daily to a maximum of 600 mg daily in adult patients who do not reach complete hematologic, cytogenetic, or molecular response and do not have Grade 3 or greater adverse reactions. ( 2.2 ) • Consider dose escalation by increments of 50 mg for those with a BSA <1.1 m 2 and 100 mg for those with a BSA ≥1.1 m 2 to a maximum of 600 mg daily in pediatric patients who do not reach sufficient response after 3 months.
( 2.2 ) • Adjust dosage for toxicity and organ impairment ( 2 )
2.1Recommended Dosage The recommended dosage is taken orally once daily with food. Swallow tablets whole. Do not cut, crush, break or chew tablets.
Continue treatment with BOSULIF until disease progression or intolerance to therapy. Capsules may be swallowed whole. For patients who are unable to swallow a whole capsule(s), each capsule can be opened and the contents mixed with applesauce or yogurt.
Mixing the capsule contents with applesauce or yogurt cannot be considered a substitute of a proper meal. If a dose is missed beyond 12 hours, the patient should skip the dose and take the usual prescribed dose on the following day. Dosage in Adult Patients with Newly-Diagnosed CP Ph+ CML The recommended dosage of BOSULIF is 400 mg orally once daily with food.
Dosage in Adult Patients with CP, AP, or BP Ph+ CML with Resistance or Intolerance to Prior Therapy The recommended dosage of BOSULIF is 500 mg orally once daily with food. Dosage in Pediatric Patients with Newly-Diagnosed CP Ph+ CML or with CP Ph+ CML with Resistance or Intolerance to Prior Therapy The recommended dose of BOSULIF for pediatric patients with newly-diagnosed CP Ph+ CML is 300 mg/m 2 orally once daily with food and the recommended dosage for pediatric patients with CP Ph+ CML that is resistant or intolerant to prior therapy is 400 mg/m 2 orally once daily with food and dose recommendations are provided in Table 1.
As appropriate, the desired dose can be attained by combining different strengths of BOSULIF tablets or capsules. Table 1: Dosing of BOSULIF for Pediatric Patients with Newly-Diagnosed CP Ph+ CML or with CP Ph+ CML with Resistance or Intolerance to Prior Therapy BSA BSA=Body Surface Area Newly-Diagnosed Recommended Dose (Once Daily) Resistant or Intolerant Recommended Dose (Once Daily) < 0.55 m 2 150 mg 200 mg 0.55 to < 0.63 m 2 200 mg 250 mg 0.63 to < 0.75 m 2 200 mg 300 mg 0.75 to < 0.9 m 2 250 mg 350 mg 0.9 to < 1.1 m 2 300 mg 400 mg ≥ 1.1 m 2 400 mg maximum starting dose (corresponding to maximum starting dose in adult indication) 500 mg Preparation Instructions for BOSULIF Capsules Mixed with Applesauce or Yogurt For patients who are unable to swallow capsules, the contents of the capsules can be mixed with applesauce or yogurt.
Remove the required number of capsules from the container to prepare the dose as instructed and the amount of either room temperature applesauce or yogurt in a clean container. Carefully open each capsule, add the entire capsule content of each capsule into the applesauce or yogurt, then mix the entire dose into the applesauce or yogurt. Patients should immediately consume the full mixture in its entirety, without chewing.
Do not store the mixture for later use. If the entire preparation is not swallowed do not take an additional dose. Wait until the next day to resume dosing.
Table 2: BOSULIF Dose Using Capsules and Soft Food Volumes Dose Volume of Applesau… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: • 100 mg: yellow, oval, biconvex, film-coated tablets debossed with "Pfizer" on one side and "100" on the other. • 400 mg: orange, oval, biconvex, film-coated tablets debossed with "Pfizer" on one side and "400" on the other. • 500 mg: red, oval, biconvex, film-coated tablets debossed with "Pfizer" on one side and "500" on the other. Capsules: • 50 mg: white body/orange cap with “BOS 50” printed on the body and “Pfizer” printed on the cap in black ink. • 100 mg: white body/brownish-red cap with “BOS 100” printed on the body and “Pfizer” printed on the cap in black ink. • Tablets: 100 mg, 400 mg, and 500 mg.
( 3 ) • Capsules 50 mg, 100 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS BOSULIF is contraindicated in patients with a history of hypersensitivity to BOSULIF. Reactions have included anaphylaxis [see Adverse Reactions (6.1) ] . Hypersensitivity to BOSULIF. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Gastrointestinal Toxicity: Monitor and manage as necessary. Withhold, dose reduce, or discontinue BOSULIF. ( 2.3 , 5.1 ) • Myelosuppression: Monitor blood counts and manage as necessary.
Withhold, dose reduce, or discontinue BOSULIF. ( 2.4 , 5.2 ) • Hepatic Toxicity: Monitor liver enzymes at least monthly for the first 3 months and as needed. Withhold, dose reduce, or discontinue BOSULIF.
( 2.3 , 5.3 ) • Cardiovascular Toxicity: Monitor and manage as necessary. Interrupt, dose reduce, or discontinue BOSULIF. ( 5.4 ) • Fluid Retention: Monitor patients and manage using standard of care treatment.
Interrupt, dose reduce, or discontinue BOSULIF. ( 2.3 , 5.5 ) • Renal Toxicity: Monitor patients for renal function at baseline and during therapy with BOSULIF. ( 5.6 ) • Embryo-Fetal Toxicity: BOSULIF can cause fetal harm.
Advise female patients of reproductive potential of potential risk to a fetus and to use effective contraception. ( 5.7 )
5.1Gastrointestinal Toxicity Diarrhea, nausea, vomiting, and abdominal pain occur with BOSULIF treatment. Monitor and manage patients using standards of care, including antidiarrheals, antiemetics, and fluid replacement. In the randomized clinical trial in adult patients with newly-diagnosed Ph+ CML, the median time to onset for diarrhea (all grades) was 4 days and the median duration per event was 3 days.
Among 546 adult patients in a single-arm study in patients with CML who were resistant or intolerant to prior therapy, the median time to onset for diarrhea (all grades) was 2 days and the median duration per event was 2 days. Among the patients who experienced diarrhea, the median number of episodes of diarrhea per patient during treatment with BOSULIF was 3 (range 1–268). Among 49 pediatric patients with newly-diagnosed CP Ph+ CML or who had CP Ph+ CML that was resistant or intolerant to prior therapy, the median time to onset for diarrhea (all grades) was 2 days and the duration was 2 days.
Among patients who experienced diarrhea, the median number of episodes of diarrhea per patient during treatment with BOSULIF was 2 (range 1 – 198). To manage gastrointestinal toxicity, withhold, dose reduce, or discontinue BOSULIF as necessary [see Dosage and Administration (2.3) and Adverse Reactions (6) ] .
5.2Myelosuppression Thrombocytopenia, anemia and neutropenia occur with BOSULIF treatment. Perform complete blood counts weekly for the first month of therapy and then monthly thereafter, or as clinically indicated. To manage myelosuppression, withhold, dose reduce, or discontinue BOSULIF as necessary [see Dosage and Administration (2.4) and Adverse Reactions (6) ] .
5.3Hepatic Toxicity Bosutinib may cause elevations in serum transaminases (alanine aminotransferase [ALT], aspartate aminotransferase [AST]). Two cases consistent with drug induced liver injury (defined as concurrent elevations in ALT or AST greater than or equal to 3×ULN with total bilirubin greater than 2×ULN and alkaline phosphatase less than 2×ULN) have occurred without alternative causes. This represented 2 out 1711 patients in BOSULIF clinical trials.
In the 268 adult patients from the safety population in the randomized clinical trial in patients with newly-diagnosed CML in the BOSULIF treatment group, the incidence of ALT elevation was 68.3% and increased AST was 56%. Of patients who experienced increased transaminases of any grade, 73% experienced their first increase within the first 3 months. The median time to onset of increased ALT and AST was 29 and 56 days, respectively, and the median duration was 19 and 15 days, respectively.
Among the 546 adult patients in a single-arm study in patients with CML who were resistant or intolerant to prior therapy, the incidence of increased ALT was 53.3% and AST elevation was 46.7%. Sixty percent of the patients experienced an increase in either ALT or AST. Most cases of transaminase elevations in this study occurred early in treatment; of patients who expe… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are discussed in greater detail in other sections of the labeling: • Gastrointestinal toxicity [see Warnings and Precautions (5.1) ] . • Myelosuppression [see Warnings and Precautions (5.2) ] . • Hepatic toxicity [see Warnings and Precautions (5.3) ] . • Cardiovascular toxicity [see Warnings and Precautions (5.4) ] . • Fluid retention [see Warnings and Precautions (5.5) ] . • Renal toxicity [see Warnings and Precautions (5.6) ] . • Most common adverse reactions (≥20%), in adult and pediatric patients with CML are diarrhea, abdominal pain, vomiting, nausea, rash, fatigue, hepatic dysfunction, headache, pyrexia, decreased appetite respiratory tract infection, and constipation.
The most common laboratory abnormalities (≥20%) in adult and pediatric patients are creatinine increased, hemoglobin decreased, lymphocyte count decreased, platelets decreased, ALT increased, calcium decreased, white blood cell count decreased, AST increased, absolute neutrophil count decreased, glucose increased, phosphorus decreased, urate increased, alkaline phosphatase increased, lipase increased, creatine kinase increased, and amylase increased. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc. at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The most common adverse reactions, in ≥20% of adults with newly diagnosed CP Ph+ CML or CP, AP, or BP Ph+ CML with resistance or intolerance to prior therapy (N=814) were diarrhea (80%), rash (44%), nausea (44%), abdominal pain (43%), vomiting (33%), fatigue (33%), hepatic dysfunction (33%), respiratory tract infection (25%), pyrexia (24%), and headache (21%).
The most common laboratory abnormalities that worsened from baseline in ≥20% of adults were creatinine increased (93%), hemoglobin decreased (90%), lymphocyte count decreased (72%), platelets decreased (69%), ALT increased (58%), calcium decreased (53%), white blood cell count decreased (52%), absolute neutrophils count decreased (50%), AST increased (50%), glucose increased (46%), phosphorus decreased (44%), urate increased (41%), alkaline phosphatase increased (40%), lipase increased (36%), creatine kinase increased (29%), and amylase increased (24%).
The most common adverse reactions, in ≥20% of pediatric patients (N=49) were diarrhea (82%), abdominal pain (73%), vomiting (55%), nausea (49%), rash (49%), fatigue (37%), hepatic dysfunction (37%), headache (35%), pyrexia (31%), decreased appetite (27%), and constipation (20%). The most common laboratory abnormalities that worsened from baseline in ≥20% of pediatric patients were creatinine increased (92%), alanine aminotransferase increased (59%), white blood cell count decreased (53%), aspartate aminotransferase increased (51%), platelet count decreased (49%), glucose increased (41%), calcium decreased (31%), hemoglobin decreased (31%), neutrophil count decreased (31%), lymphocyte count decreased (29%), serum amylase increased (27%), and CPK increased (25%).
Adverse Reactions in Adult Patients With Newly-Diagnosed CP CML The clinical trial randomized and treated 533 patients with newly-diagnosed CP CML to receive BOSULIF 400 mg daily or imatinib 400 mg daily as single agents (Newly-Diagnosed CP CML Study) [see Clinical Studies (14.1) ] . The safety population (received at least 1 dose of BOSULIF) included: • two hundred sixty-eight (268) patients with newly-diagnosed CP CML had a median duration of BOSULIF treatment of 55 months (range: 0.3 to 60 months) and a median dose intensity of 394 mg/day.
Serious adverse reactions occurred in 22% of patients with newly-diagnosed CP CML who received bosutinib. Serio… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong and Moderate CYP3A Inhibitors: Avoid concomitant use with BOSULIF. ( 7.1 ) • Strong CYP3A Inducers: Avoid concomitant use with BOSULIF. ( 7.1 ) • Proton Pump Inhibitors: Use short-acting antacids or H2 blockers as an alternative to proton pump inhibitors. ( 7.1 )
7.1Effect of Other Drugs on BOSULIF Strong or Moderate CYP3A Inhibitors Avoid the concomitant use of strong or moderate CYP3A inhibitors with BOSULIF. Bosutinib is a CYP3A substrate. Concomitant use with a strong or moderate CYP3A inhibitor increases bosutinib C max and AUC [see Clinical Pharmacology (12.3) ] which may increase the risk of toxicities.
Strong CYP3A Inducers Avoid the concomitant use of strong CYP3A inducers with BOSULIF. Bosutinib is a CYP3A substrate. Concomitant use with a strong CYP3A inducer decreases bosutinib C max and AUC [see Clinical Pharmacology (12.3) ] which may reduce BOSULIF efficacy.
Proton Pump Inhibitors (PPI) As an alternative to PPIs, use short-acting antacids or H2 blockers and separate dosing by more than 2 hours from BOSULIF dosing. Bosutinib displays pH dependent aqueous solubility, Concomitant use with a PPI decreases bosutinib C max and AUC [see Clinical Pharmacology (12.3) ] which may reduce BOSULIF efficacy.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise women not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action, BOSULIF can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data in pregnant women to inform the drug-associated risk. In animal reproduction studies conducted in rats and rabbits, oral administration of bosutinib during organogenesis caused adverse developmental outcomes, including structural abnormalities, embryo-fetal mortality, and alterations to growth at maternal exposures (AUC) as low as 1.2 times the human exposure at the dose of 500 mg/day ( see Data ).
Advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies are 2–4% and 15–20%, respectively. Data Animal Data In a rat fertility and early embryonic development study, bosutinib was administered orally to female rats for approximately 3 to 6 weeks, depending on day of mating (2 weeks prior to cohabitation with untreated breeder males until gestation day [GD] 7). Increased embryonic resorptions occurred at greater than or equal to 10 mg/kg/day of bosutinib (1.6 and 1.2 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively), and decreased implantations and reduced number of viable embryos at 30 mg/kg/day of bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
In an embryo-fetal development study conducted in rabbits, bosutinib was administered orally to pregnant animals during the period of organogenesis at doses of 3, 10, and 30 mg/kg/day. At the maternally-toxic dose of 30 mg/kg/day of bosutinib, there were fetal anomalies (fused sternebrae, and 2 fetuses had various visceral observations), and an approximate 6% decrease in fetal body weight. The dose of 30 mg/kg/day resulted in exposures (AUC) approximately 5.1 and 3.8 times the human exposures at the recommended doses of 400 and 500 mg/day, respectively.
Fetal exposure to bosutinib-derived radioactivity during pregnancy was demonstrated in a placental-transfer study in pregnant rats. In a rat pre- and postnatal development study, bosutinib was administered orally to pregnant animals during the period of organogenesis through lactation day 20 at doses of 10, 30, and 70 mg/kg/day. Reduced number of pups born occurred at greater than or equal to 30 mg/kg/day bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively), and increased incidence of total litter loss and decreased growth of offspring after birth occurred at 70 mg/kg/day bosutinib (6.9 and 5.1 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
8.2Lactation Risk Summary No data are available regarding the presence of bosutinib or its metabolites in human milk or its effects on a breastfed child or on milk production. However, bosutinib is present in the milk of lactating rats. Because of the potential for serious adverse reactions in a nursing child, breastfeeding is not recommended during treatment with BOSULIF and for 2 weeks after the last dose.
Animal Data After a single radiolabeled bosutinib dose to lactating rats, radioactivity was present in the plasma of suckling offspring for 24 to 48 hours.
8.3Females and Males of Reproductive Potential Based on findings from animal studies, BOSULIF can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Pregnancy Females of reproductive potential should have a pregnancy test prior to starting treatment with BOSULIF. Contraception Females Adv… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action, BOSULIF can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data in pregnant women to inform the drug-associated risk. In animal reproduction studies conducted in rats and rabbits, oral administration of bosutinib during organogenesis caused adverse developmental outcomes, including structural abnormalities, embryo-fetal mortality, and alterations to growth at maternal exposures (AUC) as low as 1.2 times the human exposure at the dose of 500 mg/day ( see Data ).
Advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies are 2–4% and 15–20%, respectively. Data Animal Data In a rat fertility and early embryonic development study, bosutinib was administered orally to female rats for approximately 3 to 6 weeks, depending on day of mating (2 weeks prior to cohabitation with untreated breeder males until gestation day [GD] 7). Increased embryonic resorptions occurred at greater than or equal to 10 mg/kg/day of bosutinib (1.6 and 1.2 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively), and decreased implantations and reduced number of viable embryos at 30 mg/kg/day of bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
In an embryo-fetal development study conducted in rabbits, bosutinib was administered orally to pregnant animals during the period of organogenesis at doses of 3, 10, and 30 mg/kg/day. At the maternally-toxic dose of 30 mg/kg/day of bosutinib, there were fetal anomalies (fused sternebrae, and 2 fetuses had various visceral observations), and an approximate 6% decrease in fetal body weight. The dose of 30 mg/kg/day resulted in exposures (AUC) approximately 5.1 and 3.8 times the human exposures at the recommended doses of 400 and 500 mg/day, respectively.
Fetal exposure to bosutinib-derived radioactivity during pregnancy was demonstrated in a placental-transfer study in pregnant rats. In a rat pre- and postnatal development study, bosutinib was administered orally to pregnant animals during the period of organogenesis through lactation day 20 at doses of 10, 30, and 70 mg/kg/day. Reduced number of pups born occurred at greater than or equal to 30 mg/kg/day bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively), and increased incidence of total litter loss and decreased growth of offspring after birth occurred at 70 mg/kg/day bosutinib (6.9 and 5.1 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of BOSULIF have been established in pediatric patients 1 year of age and older with newly-diagnosed CP Ph+ CML and CP Ph+ CML that is resistant or intolerant to prior therapy. Use of BOSULIF for these indications is based on data from BCHILD [NCT04258943]. The study included pediatric patients with newly diagnosed CP Ph+ CML in the following age groups: 2 patients 1 year of age to less than 6 years of age, 3 patients 6 years of age to less than 12 years of age, and 10 patients 12 years of age to less than 17 years of age.
The study also included pediatric patients with CP Ph+ CML that was resistant or intolerant to prior therapy in the following age groups: 4 patients 1 year of age to less than 6 years of age, 10 patients 6 years of age to less than 12 years of age, and 10 patients 12 years of age to less than 17 years of age [see Adverse Reactions (6.1) and Clinical Studies (14.3) ] . BSA-normalized apparent clearance in 27 pediatric patients aged 4 to <17 years (141.3 L/h/m 2 ) was 29% higher than BSA-normalized apparent clearance in adult patients with CP Ph+ CML (109.2 L/h/m 2 ) [see Clinical Pharmacology (12.3) ] .
The recommended dosage of BOSULIF in pediatric patients is based on body surface area (BSA) [see Dosage and Administration (2.1) ]. The safety and effectiveness of BOSULIF in pediatric patients younger than 1 year of age with newly diagnosed CP Ph+ CML, pediatric patients younger than 1 year of age with CP Ph+ CML that is resistant or intolerant to prior therapy, and pediatric patients with AP Ph+ CML or BP Ph+ CML have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In the single-arm study in patients with CML who were resistant or intolerant to prior therapy of BOSULIF in patients with Ph+ CML, 20% were age 65 and over, 4% were 75 and over. Of the 268 patients who received bosutinib in the study for newly diagnosed CML, 20% were age 65 and over, 5% were 75 and over. No overall differences in safety or effectiveness were observed between these patients and younger patients, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Experience with BOSULIF overdose in clinical studies was limited to isolated cases. There were no reports of any serious adverse events associated with the overdoses. Patients who take an overdose of BOSULIF should be observed and given appropriate supportive treatment.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Bosutinib is a TKI. Bosutinib inhibits the BCR-ABL kinase that promotes CML; it is also an inhibitor of Src-family kinases including Src, Lyn, and Hck. Bosutinib inhibited 16 of 18 imatinib-resistant forms of BCR-ABL kinase expressed in murine myeloid cell lines. Bosutinib did not inhibit the T315I and V299L mutant cells.
12.2Pharmacodynamics A greater likelihood of response and a greater likelihood of safety events were observed with higher bosutinib exposure in clinical studies. The time course of bosutinib pharmacodynamic response has not been fully characterized. Cardiac Electrophysiology At a single oral dose of 500 mg BOSULIF with ketoconazole (a strong CYP3A inhibitor), BOSULIF does not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics Bosutinib pharmacokinetics were assessed following oral dosing with food in adult patients with CML and were presented as geometric mean (CV%), unless otherwise specified. Bosutinib exhibits dose proportional increases in C max and AUC over the oral dose range of 200 to 800 mg (0.33 to 1.3 times the maximum approved recommended dosage of 600 mg). Bosutinib steady state C max was 127 ng/mL (31%), C trough was 68 ng/mL (39%) and AUC was 2370 ng•h/mL (34%) following multiple oral doses of BOSULIF 400 mg; Bosutinib steady state C max was 171 ng/mL (38%), C trough was 91 ng/mL (42%) and AUC was 3150 ng•h/mL (38%) following multiple oral doses of BOSULIF 500 mg.
No clinically significant differences in the pharmacokinetics of bosutinib were observed following administration of either the tablet or capsule dosage forms of BOSULIF at the same dose, under fed conditions. Absorption The median bosutinib (minimum, maximum) time-‑to-C max (t max ) was 6.0 (6.0, 6.0) hours following oral administration of a single oral dose of BOSULIF 500 mg with food. The absolute bioavailability was 34% in healthy subjects.
Effect of Food Bosutinib C max increased 1.8-fold and AUC increased 1.7-fold when BOSULIF tablets were given with a high fat meal to healthy subjects compared to administration under fasted condition. Bosutinib C max increased 1.6‑fold and AUC increased 1.5-fold when BOSULIF capsules were given with a high fat meal to healthy subjects compared to administration under fasted condition. The high-fat meal (800-1000 total calories) consisted of approximately 150 protein calories, 250 carbohydrate calories, and 500-600 fat calories.
No clinically significant differences in the pharmacokinetics of bosutinib were observed following administration of a BOSULIF capsule that was opened and the contents mixed with applesauce or yogurt immediately before use. Distribution The mean (SD) apparent bosutinib volume of distribution is 6080 (1230) L after an oral dose of 500 mg of BOSULIF. Bosutinib protein binding is 94% in vitro and 96% ex vivo , and is independent of concentration.
Elimination The mean (SD) bosutinib terminal phase elimination half life (t ½ ) was 22.5 (1.7) hours, and the mean (SD) apparent clearance was 189 (48) L/h following a single oral dose of BOSULIF. Metabolism Bosutinib is primarily metabolized by CYP3A4. Excretion Following a single oral dose of [ 14 C] radiolabeled bosutinib without food, 91.3% of the dose was recovered in feces and 3.3% of the dose recovered in urine.
Specific Populations Patients with Renal Impairment Bosutinib AUC increased 1.4-fold in subjects with moderate renal impairment (CL cr : 30 to 50 mL/min, estimated by Cockcroft-Gault (C-G)) and increased 1.6-fold in subjects with severe renal impairment (CL cr less than 30 mL/min) following a single oral dose of BOSULIF 200 mg (0.33 times the maximum approved recommended dosage of 600 mg). No clinically significant difference in the pharmacokinetics of bosutinib was observed in subjects with mild renal impairment (CL cr : 51 to 80 mL/min, C-G) .
BOSULIF has not been studied in patients undergoing hemodialysis. Patients with Hepatic Impair… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Bosutinib is a TKI. Bosutinib inhibits the BCR-ABL kinase that promotes CML; it is also an inhibitor of Src-family kinases including Src, Lyn, and Hck. Bosutinib inhibited 16 of 18 imatinib-resistant forms of BCR-ABL kinase expressed in murine myeloid cell lines. Bosutinib did not inhibit the T315I and V299L mutant cells.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Tablets – How Supplied BOSULIF (bosutinib) tablets are supplied for oral administration in 3 strengths: a 100 mg yellow, oval, biconvex, film-coated tablet debossed with "Pfizer" on one side and "100" on the other; a 400 mg orange, oval, biconvex, film coated tablet debossed with "Pfizer" on one side and "400" on the other; and a 500 mg red, oval, biconvex, film-coated tablet debossed with "Pfizer" on one side and "500" on the other. BOSULIF (bosutinib) tablets are available in the following packaging configurations with a child-resistant (CR) closure (Table 17).
Bottles contain a desiccant. Table 17: Tablet Presentations BOSULIF Tablets Package Configuration Tablet Strength (mg) NDC Tablet Description Abbreviation: NDC=National drug code. 120 tablets per bottle 100 mg 0069-0135-01 Yellow, oval, biconvex, film-coated tablets, debossed "Pfizer" on one side and "100" on the other.
30 tablets per bottle 400 mg 0069-0193-01 Orange, oval, biconvex, film-coated tablet debossed with "Pfizer" on one side and "400" on the other. 30 tablets per bottle 500 mg 0069-0136-01 Red, oval, biconvex, film-coated tablets, debossed "Pfizer" on one side and "500" on the other. Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Handling and Disposal Procedures for proper disposal of anticancer drugs should be considered. Touching or handling crushed or broken tablets is to be avoided. Any unused product or waste material should be disposed of in accordance with local requirements, or drug take back programs.
Capsules - How Supplied BOSULIF (bosutinib) capsules are supplied for oral administration in 2 strengths: 50 mg capsule: size 2 capsule, white body/orange cap with “BOS 50” printed on the body and “Pfizer” printed on the cap in black ink. 100 mg capsule: size 0 capsule, white body/brownish-red cap with “BOS 100” printed on the body and “Pfizer” printed on the cap in black ink. BOSULIF (bosutinib) capsules are available in the following packaging configurations with a CR closure (Table 18).
Table 18: Capsule Presentations Abbreviation: NDC=National drug code. BOSULIF Capsules Package Configuration Count Capsule Strength (mg) NDC Capsule Description 30 capsules per bottle 50 0069-0504-30 Size 2 capsule, white body/orange cap with “BOS 50” printed on the body and “Pfizer” printed on the cap in black ink. 150 capsules per bottle 100 0069-1014-15 Size 0 capsule, white body/brownish-red cap with “BOS 100” printed on the body and “Pfizer” printed on the cap in black ink.
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] and Store and Dispense in Original Container. Handling and Disposal Procedures for proper disposal of anticancer drugs should be considered. Patients and/or caregivers must wear gloves while handling the drug product, and wash their hands once finished.
Any unused product or waste material should be disposed of in accordance with local requirements.
📦 Storage and Handling ▾
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Handling and Disposal Procedures for proper disposal of anticancer drugs should be considered. Touching or handling crushed or broken tablets is to be avoided. Any unused product or waste material should be disposed of in accordance with local requirements, or drug take back programs.
Capsules - How Supplied BOSULIF (bosutinib) capsules are supplied for oral administration in 2 strengths: 50 mg capsule: size 2 capsule, white body/orange cap with “BOS 50” printed on the body and “Pfizer” printed on the cap in black ink. 100 mg capsule: size 0 capsule, white body/brownish-red cap with “BOS 100” printed on the body and “Pfizer” printed on the cap in black ink. BOSULIF (bosutinib) capsules are available in the following packaging configurations with a CR closure (Table 18).
Table 18: Capsule Presentations Abbreviation: NDC=National drug code. BOSULIF Capsules Package Configuration Count Capsule Strength (mg) NDC Capsule Description 30 capsules per bottle 50 0069-0504-30 Size 2 capsule, white body/orange cap with “BOS 50” printed on the body and “Pfizer” printed on the cap in black ink. 150 capsules per bottle 100 0069-1014-15 Size 0 capsule, white body/brownish-red cap with “BOS 100” printed on the body and “Pfizer” printed on the cap in black ink.
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] and Store and Dispense in Original Container. Handling and Disposal Procedures for proper disposal of anticancer drugs should be considered. Patients and/or caregivers must wear gloves while handling the drug product, and wash their hands once finished.
Any unused product or waste material should be disposed of in accordance with local requirements.
📋 Description ▾
11 DESCRIPTION BOSULIF contains bosutinib, a kinase inhibitor. Bosutinib is present as a monohydrate with a chemical name of 3-Quinolinecarbonitrile, 4-[(2,4-dichloro-5-methoxyphenyl)amino]-6-methoxy-7-[3-(4-methyl-1-piperazinyl) propoxy]-, hydrate (1:1). Its chemical formula is C 26 H 29 Cl 2 N 5 O 3 ∙H 2 O (monohydrate); its molecular weight is 548.46 (monohydrate), equivalent to 530.46 (anhydrous).
Bosutinib monohydrate has the following chemical structure: Bosutinib monohydrate is a white to yellowish-tan powder. Bosutinib monohydrate has a pH dependent solubility across the physiological pH range. At or below pH 5, bosutinib monohydrate behaves as a highly soluble compound.
Above pH 5, the solubility of bosutinib monohydrate reduces rapidly. BOSULIF ® (bosutinib) tablets are supplied for oral administration in 3 strengths: 100 mg, 400 mg and 500 mg. Each strength reflects the equivalent amount of bosutinib content (on anhydrous basis).
The tablets contain the following inactive ingredients: croscarmellose sodium, iron oxide red (for 400 mg, and 500 mg tablet) and iron oxide yellow (for 100 mg, and 400 mg tablet), magnesium stearate, microcrystalline cellulose, poloxamer, polyethylene glycol, polyvinyl alcohol, povidone, talc and titanium dioxide. BOSULIF ® (bosutinib) capsules are supplied for oral administration in 2 strengths: 50 mg and 100 mg. Each strength reflects the equivalent amount of bosutinib (on anhydrous basis).
The capsules contain the following inactive ingredients: croscarmellose sodium, gelatin, magnesium stearate, mannitol, microcrystalline cellulose, poloxamer, povidone, red iron oxide, titanium dioxide, yellow iron oxide. The printing ink contains black iron oxide, potassium hydroxide, propylene glycol, shellac, strong ammonia solution. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). • Dosage and Administration Instruct patients to take BOSULIF exactly as prescribed, not to change their dose or to stop taking BOSULIF unless they are told to do so by their doctor. If patients miss a dose beyond 12 hours, they should be advised to take the next scheduled dose at its regular time. A double dose should not be taken to make up for any missed dose.
Advise patients to take BOSULIF with food. Patients should be advised: “Swallow tablets whole. Do not crush, break, or cut tablet.
Do not touch or handle crushed or broken tablets.” Patients should be advised: “Capsules may be swallowed whole. For those that cannot swallow the capsule whole, the capsule can be opened and the contents mixed with applesauce or yogurt.” • Gastrointestinal Toxicity Advise patients that they may experience diarrhea, nausea, vomiting, abdominal pain, or blood in their stools with BOSULIF and to seek medical attention promptly for these symptoms [see Warnings and Precautions (5.1) ] . • Myelosuppression Advise patients of the possibility of developing low blood cell counts and to immediately report fever, any suggestion of infection, or signs or symptoms suggestive of bleeding or easy bruising [see Warnings and Precautions (5.2) ] . • Hepatic Toxicity Advise patients of the possibility of developing liver function abnormalities and to immediately report jaundice [see Warnings and Precautions (5.3) ] . • Cardiovascular Toxicity Advise patients that cardiac failure, left ventricular dysfunction, and cardiac ischemic events have been reported.
Advise patients to seek immediate medical attention if any symptoms suggestive of cardiac failure and cardiac ischemia occur, such as shortness of breath, weight gain, or fluid retention [see Warnings and Precautions (5.4) ] . • Fluid Retention Advise patients of the possibility of developing fluid retention (swelling, weight gain, or shortness of breath) and to seek medical attention promptly if these symptoms arise [see Warnings and Precautions (5.5) ] . • Renal Toxicity Advise patients of the possibility of developing renal problems and to immediately report frequent urination, polyuria or oliguria [see Warnings and Precautions (5.6) ] . • Adverse Reactions Advise patients that they may experience other adverse reactions such as respiratory tract infections, rash, fatigue, loss of appetite, headache, dizziness, back pain, arthralgia, pruritus or constipation with BOSULIF and to seek medical attention if symptoms are significant.
There is a possibility of anaphylactic shock [see Contraindications (4) and Adverse Reactions (6) ] . • Embryo-Fetal Toxicity Advise females to inform their healthcare provider if they are pregnant or become pregnant. Advise female patients of the risk to a fetus and potential loss of the pregnancy [see Use in Specific Populations (8.1) ] . Advise females of reproductive potential, to use effective contraception during treatment and for 2 weeks after receiving the last dose of BOSULIF [see Warnings and Precautions (5.7) and Use in Specific Populations (8.1 , 8.3) ] .
Advise lactating women not to breastfeed during treatment with BOSULIF and for 2 weeks after the last dose [see Use in Specific Populations (8.2) ] . • Drug Interactions Advise patients that BOSULIF and certain other medicines, including over the counter medications or herbal supplements (such as St. John's wort) can interact with each other and may alter the effects of BOSULIF [see Drug Interactions (7) ].
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Bosutinib pharmacokinetics were assessed following oral dosing with food in adult patients with CML and were presented as geometric mean (CV%), unless otherwise specified. Bosutinib exhibits dose proportional increases in C max and AUC over the oral dose range of 200 to 800 mg (0.33 to 1.3 times the maximum approved recommended dosage of 600 mg). Bosutinib steady state C max was 127 ng/mL (31%), C trough was 68 ng/mL (39%) and AUC was 2370 ng•h/mL (34%) following multiple oral doses of BOSULIF 400 mg; Bosutinib steady state C max was 171 ng/mL (38%), C trough was 91 ng/mL (42%) and AUC was 3150 ng•h/mL (38%) following multiple oral doses of BOSULIF 500 mg.
No clinically significant differences in the pharmacokinetics of bosutinib were observed following administration of either the tablet or capsule dosage forms of BOSULIF at the same dose, under fed conditions. Absorption The median bosutinib (minimum, maximum) time-‑to-C max (t max ) was 6.0 (6.0, 6.0) hours following oral administration of a single oral dose of BOSULIF 500 mg with food. The absolute bioavailability was 34% in healthy subjects.
Effect of Food Bosutinib C max increased 1.8-fold and AUC increased 1.7-fold when BOSULIF tablets were given with a high fat meal to healthy subjects compared to administration under fasted condition. Bosutinib C max increased 1.6‑fold and AUC increased 1.5-fold when BOSULIF capsules were given with a high fat meal to healthy subjects compared to administration under fasted condition. The high-fat meal (800-1000 total calories) consisted of approximately 150 protein calories, 250 carbohydrate calories, and 500-600 fat calories.
No clinically significant differences in the pharmacokinetics of bosutinib were observed following administration of a BOSULIF capsule that was opened and the contents mixed with applesauce or yogurt immediately before use. Distribution The mean (SD) apparent bosutinib volume of distribution is 6080 (1230) L after an oral dose of 500 mg of BOSULIF. Bosutinib protein binding is 94% in vitro and 96% ex vivo , and is independent of concentration.
Elimination The mean (SD) bosutinib terminal phase elimination half life (t ½ ) was 22.5 (1.7) hours, and the mean (SD) apparent clearance was 189 (48) L/h following a single oral dose of BOSULIF. Metabolism Bosutinib is primarily metabolized by CYP3A4. Excretion Following a single oral dose of [ 14 C] radiolabeled bosutinib without food, 91.3% of the dose was recovered in feces and 3.3% of the dose recovered in urine.
Specific Populations Patients with Renal Impairment Bosutinib AUC increased 1.4-fold in subjects with moderate renal impairment (CL cr : 30 to 50 mL/min, estimated by Cockcroft-Gault (C-G)) and increased 1.6-fold in subjects with severe renal impairment (CL cr less than 30 mL/min) following a single oral dose of BOSULIF 200 mg (0.33 times the maximum approved recommended dosage of 600 mg). No clinically significant difference in the pharmacokinetics of bosutinib was observed in subjects with mild renal impairment (CL cr : 51 to 80 mL/min, C-G) .
BOSULIF has not been studied in patients undergoing hemodialysis. Patients with Hepatic Impairment Bosutinib C max increased 2.4-fold, 2-fold, and 1.5-fold, and AUC increased 2.3-fold, 2-fold, and 1.9-fold in hepatic impairment Child-Pugh A, B, and C, respectively, following a single oral dose of BOSULIF 200 mg (0.33 times the maximum approved recommended dosage of 600 mg). Pediatric Patients The pharmacokinetics of bosutinib in 27 pediatric patients aged 4 to less than 17 years with newly diagnosed CP Ph+ CML or resistant/intolerant CP Ph+ CML were evaluated over the dose range of 300 mg/m 2 to 400 mg/m 2 administered orally once daily with food.
Exposures increased in a dose proportional manner over the dose range of 300 mg/m 2 to 400 mg/m 2 . The bosutinib median (min, max) t max is approximately 3 hours post-dose (1, 8 hours). In 15 pediatric patients aged 4 to less than 17 years who receiv… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics A greater likelihood of response and a greater likelihood of safety events were observed with higher bosutinib exposure in clinical studies. The time course of bosutinib pharmacodynamic response has not been fully characterized. Cardiac Electrophysiology At a single oral dose of 500 mg BOSULIF with ketoconazole (a strong CYP3A inhibitor), BOSULIF does not prolong the QT interval to any clinically relevant extent.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Adult Patients with Newly-Diagnosed CP Ph+ CML The efficacy of BOSULIF in patients with newly-diagnosed chronic phase Ph+ CML was evaluated in the B osutinib trial in F irst-line chr O nic myelogenous leukemia t RE atment (BFORE) Trial: "A Multicenter Phase 3, Open-Label Study of Bosutinib Versus Imatinib in Adult Patients With Newly Diagnosed Chronic Phase Chronic Myelogenous Leukemia" [NCT02130557]. The BFORE Trial is a 2-arm, open-label, randomized, multicenter trial conducted to investigate the efficacy and safety of BOSULIF 400 mg once daily alone compared with imatinib 400 mg once daily alone in adult patients with newly-diagnosed CP Ph+ CML.
The trial randomized 536 patients (268 in each arm) with Ph+ or Ph- newly-diagnosed CP CML (intent-to-treat [ITT] population) including 487 patients with Ph+ CML harboring b2a2 and/or b3a2 transcripts at baseline and baseline BCR-ABL copies >0 (modified intent-to-treat [mITT] population). Randomization was stratified by Sokal score and geographical region. All patients are being treated and/or followed for up to 5 years (240 weeks).
Efficacy was evaluated in the mITT population. The major efficacy outcome measure was major molecular response (MMR) at 12 months (48 weeks) defined as ≤0.1% BCR-ABL ratio on international scale (corresponding to ≥3 log reduction from standardized baseline) with a minimum of 3000 ABL transcripts as assessed by the central laboratory. Additional efficacy outcomes included CCyR by 12 months, defined as the absence of Ph+ metaphases in chromosome banding analysis of ≥20 metaphases derived from bone marrow aspirate or MMR if an adequate cytogenetic assessment was unavailable and MMR by 18 months (72 weeks).
In the mITT population in this study, 57% of patients were males, 78% were Caucasian, and 19% were 65 years or older. The median age was 53 years. At baseline, the distribution of Sokal risk scores was similar in bosutinib and imatinib-treated patients (low risk: 35% and 39%; intermediate risk: 44% and 38%; high risk: 22% and 22%, respectively).
After a minimum of 12 months follow-up, 78% of the 246 bosutinib-treated patients and 72% of the 239 imatinib-treated patients were still receiving treatment and with a minimum of 60 months of follow-up, 60% and 60% of patients, respectively, were still receiving treatment. The median treatment duration was 55.1 months for BOSULIF and 55.0 months for imatinib. The efficacy results from the BFORE trial are summarized in Table 13.
Table 13: Summary of Major Molecular Response (MMR) and Complete Cytogenetic Response (CCyR), by Treatment Group in the Modified Intent-to-Treat (mITT) Population Response Bosutinib N=246 n (%) Imatinib N=241 n (%) 2-sided p-value Abbreviations: CCyR=complete cytogenetic response; CI=confidence interval; CMH=Cochran-Mantel-Haenszel; MMR=major molecular response; N/n=number of patients. MMR at Month 12 (Week 48) MMR (%) 116 (47) 89 (37) 0.0200 Derived from CMH test stratified by Geographical region and Sokal score at randomization.
(95% CI) (41, 53) (31, 43) CCyR by Month 12 (Week 48) CCyR (%) 190 (77) 160 (66) (95% CI) (72, 83) (60, 72) 0.0075 MMR by Month 18 (Week 72) MMR (%) 150 (61) 127 (53) (95% CI) (55, 67) (46, 59) 0.0606 The MMR rate at Month 12 for all randomized patients (ITT population) was consistent with the mITT population (47% [95% CI: 41, 53] in the bosutinib treatment group and 36% [95% CI: 30, 42] in the imatinib treatment group; odds ratio of 1.57 [95% CI: 1.10, 2.22]). MMR by Month 60 (Week 240) in the mITT population was 74% (95% CI: 69, 80) in the bosutinib treatment group and 66% (95% CI: 60, 72) in the imatinib treatment group; odds ratio of 1.52 (95% CI: 1.02, 2.25).
MMR by Month 60 in the ITT population was also consistent with the mITT population (1.57 [95% CI: 1.08, 2.28]). After 60 months of follow-up, the median time to MMR in responders was 9.0 months for bosutinib and 11.9 months for imatinib. By 60 months, the MMR rates in each Sokal… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Bosutinib was not carcinogenic in rats or transgenic mice. The rat 2-year carcinogenicity study was conducted at bosutinib oral doses up to 25 mg/kg in males and 15 mg/kg in females. Exposures at these doses were approximately 1.5 times (males) and 3.1 times (females) the human exposure at the 400 mg dose and 1.2 times (males) and 2.4 times (females) exposure in humans at the 500 mg dose.
The 6-month RasH2 transgenic mouse carcinogenicity study was conducted at bosutinib oral doses up to 60 mg/kg. Bosutinib was not mutagenic or clastogenic in a battery of tests, including the bacteria reverse mutation assay (Ames Test), the in vitro assay using human peripheral blood lymphocytes and the micronucleus test in orally treated male mice. In a rat fertility study, drug-treated males were mated with untreated females, or untreated males were mated with drug-treated females.
Females were administered the drug from pre-mating through early embryonic development. The dose of 70 mg/kg/day of bosutinib resulted in reduced fertility in males as demonstrated by 16% reduction in the number of pregnancies. There were no lesions in the male reproductive organs at this dose.
This dose of 70 mg/kg/day resulted in exposure (AUC) in male rats approximately 1.5 times and equal to the human exposure at the recommended doses of 400 and 500 mg/day, respectively. Fertility (number of pregnancies) was not affected when female rats were treated with bosutinib. However, there were increased embryonic resorptions at greater than or equal to 10 mg/kg/day of bosutinib (1.6 and 1.2 times the human exposure at the recommended doses of 400 and 500 mg/day, respectively), and decreased implantations and reduced number of viable embryos at 30 mg/kg/day of bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Bosutinib was not carcinogenic in rats or transgenic mice. The rat 2-year carcinogenicity study was conducted at bosutinib oral doses up to 25 mg/kg in males and 15 mg/kg in females. Exposures at these doses were approximately 1.5 times (males) and 3.1 times (females) the human exposure at the 400 mg dose and 1.2 times (males) and 2.4 times (females) exposure in humans at the 500 mg dose.
The 6-month RasH2 transgenic mouse carcinogenicity study was conducted at bosutinib oral doses up to 60 mg/kg. Bosutinib was not mutagenic or clastogenic in a battery of tests, including the bacteria reverse mutation assay (Ames Test), the in vitro assay using human peripheral blood lymphocytes and the micronucleus test in orally treated male mice. In a rat fertility study, drug-treated males were mated with untreated females, or untreated males were mated with drug-treated females.
Females were administered the drug from pre-mating through early embryonic development. The dose of 70 mg/kg/day of bosutinib resulted in reduced fertility in males as demonstrated by 16% reduction in the number of pregnancies. There were no lesions in the male reproductive organs at this dose.
This dose of 70 mg/kg/day resulted in exposure (AUC) in male rats approximately 1.5 times and equal to the human exposure at the recommended doses of 400 and 500 mg/day, respectively. Fertility (number of pregnancies) was not affected when female rats were treated with bosutinib. However, there were increased embryonic resorptions at greater than or equal to 10 mg/kg/day of bosutinib (1.6 and 1.2 times the human exposure at the recommended doses of 400 and 500 mg/day, respectively), and decreased implantations and reduced number of viable embryos at 30 mg/kg/day of bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
📄 Patient Package Insert ▾
PATIENT INFORMATION BOSULIF ® (BAH-su-lif) (bosutinib) tablets BOSULIF ® (BAH-su-lif) (bosutinib) capsules What is BOSULIF? BOSULIF is a prescription medicine used to treat: • adults and children 1 year of age and older who have a certain type of leukemia called chronic phase (CP) Philadelphia chromosome-positive chronic myelogenous leukemia (Ph+ CML) who are newly-diagnosed or who no longer benefit from or did not tolerate other treatment. • adults with accelerated phase (AP), or blast phase (BP) Ph+ CML who can no longer benefit from or did not tolerate other treatment.
It is not known if BOSULIF is safe and effective in children less than 1 year of age with CP Ph+ CML who are newly‑diagnosed or who no longer benefit from or did not tolerate other treatment or in children with AP Ph+ CML or BP Ph+ CML. Do not take BOSULIF if you are allergic to bosutinib or any of the ingredients in BOSULIF. See the end of this leaflet for a complete list of ingredients of BOSULIF.
Before taking BOSULIF, tell your doctor about all of your medical conditions, including if you: • have liver problems • have heart problems • have kidney problems • have high blood pressure • have diabetes • are pregnant or plan to become pregnant. BOSULIF can harm your unborn baby. Females who are able to become pregnant should have a pregnancy test before starting treatment with BOSULIF.
Tell your doctor right away if you become pregnant during treatment with BOSULIF. o Females who are able to become pregnant should use effective birth control (contraception) during treatment with BOSULIF and for 2 weeks after the last dose. Talk to your doctor about birth control methods that may be right for you. • are breastfeeding or plan to breastfeed. It is not known if BOSULIF passes into your breast milk or if it can harm your baby.
Do not breastfeed during treatment with BOSULIF and for 2 weeks after the last dose. Tell your doctor about all the medicines you take, including prescription medicines, over-the-counter medicines, vitamins, and herbal supplements. When taken together, BOSULIF and certain other medicines can affect each other.
Know the medicines you take. Keep a list of your medicines and show it to your doctor and pharmacist when you get a new medicine. How should I take BOSULIF? • Take BOSULIF exactly as prescribed by your doctor. • Do not change your dose or stop taking BOSULIF without first talking with your doctor. • If your child takes BOSULIF, your healthcare provider will change the dose as your child grows. • Take BOSULIF with food. • Swallow BOSULIF tablets whole.
Do not crush, break, chew or cut BOSULIF tablets. Do not touch or handle crushed or broken BOSULIF tablets. • Swallow BOSULIF capsules whole. If you cannot swallow BOSULIF capsules whole, tell your healthcare provider. • If you cannot swallow BOSULIF capsules whole, see the “ Instructions for Use ” for detailed instructions on how to prepare and give a dose of BOSULIF capsules by opening the capsules and mixing the capsule contents with applesauce or yogurt. • If you take an antacid or H 2 blocker medicine, take it at least 2 hours before or 2 hours after BOSULIF.
If you take a Proton Pump Inhibitor (PPI) medicine, talk to your doctor or pharmacist. • You should avoid grapefruit, grapefruit juice, and supplements that contain grapefruit extract during treatment with BOSULIF. Grapefruit products increase the amount of BOSULIF in your body. • If you miss a dose of BOSULIF, take it as soon as you remember. If you miss a dose by more than 12 hours, skip that dose and take your next dose at your regular time.
Do not take 2 doses at the same time. • If you take too much BOSULIF, call your doctor or go to the nearest hospital emergency room right away. What are the possible side effects of BOSULIF? BOSULIF may cause serious side effects, including: • Stomach problems.
BOSULIF may cause stomach (abdomen) pain, nausea, diarrhea, vomiting, or blood in your stools. Get medical help right away for any… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE BOSULIF ® (BAH-su-lif) (bosutinib) capsules This Instructions for Use contains information on how to prepare and give a dose of BOSULIF capsules by opening the capsules and mixing the contents with applesauce or yogurt for people who cannot swallow capsules whole. Read this Instructions for Use before you prepare or give the first dose of BOSULIF, and each time you get a refill. Ask your healthcare provider or pharmacist if you have any questions.
Important information you need to know before preparing a dose of BOSULIF capsules: • BOSULIF capsules can be opened and the capsules contents mixed with room temperature applesauce or yogurt. • Only use applesauce or yogurt. Do not mix BOSULIF with other foods. • Swallow all of the mixture right away, without chewing. Do not store the mixture for later use. • If you do not swallow the entire BOSULIF mixture, do not mix another dose.
Wait until the next day to take your regularly scheduled dose. • Take the BOSULIF mixture with a full meal. Preparing a dose of BOSULIF capsules: Gather the following supplies: • BOSULIF capsules • small, clean container • yogurt or applesauce • teaspoon for mixing • disposable gloves Giving a dose of BOSULIF capsules: Step 1: Choose a clean, flat work surface. Place all supplies on the work surface.
Step 2: Wash and dry your hands well. Step 3: Put on disposable gloves Step 4: Get the prescribed number of BOSULIF capsule(s) needed to prepare the dose. Step 5: Add the amount of applesauce or yogurt needed for the prescribed dose to the container.
Dose Amount of Applesauce or Yogurt 100 mg 10 mL (2 teaspoons) 150 mg 15 mL (3 teaspoons) 200 mg 20 mL (4 teaspoons) 250 mg 25 mL (5 teaspoons) 300 mg 30 mL (6 teaspoons) 350 mg 30 mL (6 teaspoons) 400 mg 35 mL (7 teaspoons) 450 mg 40 mL (8 teaspoons) 500 mg 45 mL (9 teaspoons) 550 mg 45 mL (9 teaspoons) 600 mg 50 mL (10 teaspoons) Step 6: Carefully open each of the BOSULIF capsule(s) needed for the dose and empty the entire contents into the applesauce or yogurt. Mix the entire capsule contents with the applesauce or yogurt in the container.
Step 7: Swallow all of the mixture right away, without chewing. Step 8: Dispose of (throw away) the empty BOSULIF capsule shell(s) in the household trash. Step 9: Wash teaspoon and the container with soap and warm water.
Step 10: Remove disposable gloves and throw them away in the household trash. Step 11: Wash and dry your hands. How should I store BOSULIF capsules? • Store BOSULIF at room temperature between 68°F to 77°F (20°C to 25°C). • Store the BOSULIF capsules in the original bottle. • Ask your doctor or pharmacist about the right way to throw away outdated or unused BOSULIF.
Keep BOSULIF and all medicines out of the reach of children. LAB-0639-13.0 For more information, go to www.Bosulif.com or www.pfizermedicalinformation.com or call 1-800-438-1985. This Instructions for Use has been approved by the U.S.
Food and Drug Administration. Issued: 9 2023 logo
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 100 mg Bottle Label NDC 0069-0135-01 Pfizer Bosulif ® (bosutinib) tablets 100 mg Do not crush or cut tablet For Oncology Use Only 120 Tablets Rx only PRINCIPAL DISPLAY PANEL - 100 mg Bottle Label
PRINCIPAL DISPLAY PANEL - 500 mg Bottle Label NDC 0069-0136-01 Pfizer Bosulif ® (bosutinib) tablets 500 mg Do not crush or cut tablet For Oncology Use Only 30 Tablets Rx only PRINCIPAL DISPLAY PANEL - 500 mg Bottle Label
PRINCIPAL DISPLAY PANEL - 400 mg Tablet Bottle Label NDC 0069-0193-01 Pfizer Bosulif ® (bosutinib) tablets 400 mg Do not crush or cut tablet For Oncology Use Only 30 Tablets Rx only PRINCIPAL DISPLAY PANEL - 400 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 50 mg Capsule Bottle Label NDC 0069-0504-30 Pfizer Bosulif ® (bosutinib) capsules 50 mg For Oncology Use Only Attention: Store and dispense Bosulif in original container. 30 Capsules Rx only PRINCIPAL DISPLAY PANEL - 50 mg Capsule Bottle Label
PRINCIPAL DISPLAY PANEL - 100 mg Capsule Bottle Label NDC 0069-1014-15 Pfizer Bosulif ® (bosutinib) capsules 100 mg For Oncology Use Only Attention: Store and dispense Bosulif in original container. 150 Capsules Rx only PRINCIPAL DISPLAY PANEL - 100 mg Capsule Bottle Label
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |