
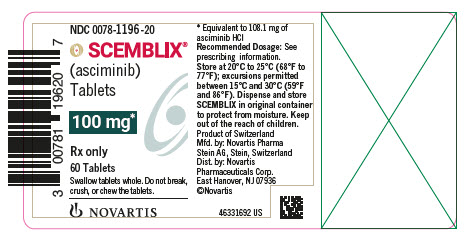
SCEMBLIX asciminib 100 mg Tablet, Film Coated, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the BCR-ABL tyrosine kinase inhibitors class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Asciminib is used to treat a certain type of chronic myeloid leukemia (CML; a type of cancer of the white blood cells). Asciminib is in a class of medications called kinase inhibitors. It works by blocking the action of an abnormal protein that signals cancer cells to multiply.
Read the full MedlinePlus article ↗- Scemblix is targeting your CML — a type of blood cancer caused by an abnormal protein called BCR-ABL1 that tells your blood cells to grow out of control. Asciminib blocks that prot...
- What exactly is Scemblix treating, and why do I need it?
- Food — especially a high-fat meal — can significantly reduce how much Scemblix your body actually absorbs, meaning you could be getting much less of the drug than you need. The lab...
- Why do I have to take it on an empty stomach? What if I accidentally eat first?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Asciminib — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 9XZ8H6N6OH
A plant-based cellulose derivative used as a binder to hold tablet ingredients together, a thickener in liquids, and a coating agent to control how fast the medicine dissolves.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 1DI56QDM62
A natural fatty substance from soybeans that helps mix oil and water-based ingredients together. It acts as an emulsifier and lubricant in medicines to improve texture and help the product break down properly in your body.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII TTV12P4NEE
Xanthan gum is a thickening and stabilizing ingredient made from fermented corn or other sugars. It's added to medicines to improve texture, prevent separation of liquids and solids, and help the product stay consistent.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $372.25 | $22,335.01 / 60 tablets |
| Medicare drug plans payPart D · Q2 2026 | $374.35 | $22,460.76 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Scemblix 100 mgthis 00078-1196-20 | Novartis | 60 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12252479 ↗ | Method of use | U-1374 | May 17, 2040 |
| US 12252479 ↗ | Method of use | U-1374 | May 17, 2040 |
| US 12252479 ↗ | Method of use | U-1374 | May 17, 2040 |
| US 8829195 ↗ | Drug substance | U-1374 | Oct 29, 2035 |
| US 8829195 ↗ | Drug substance | U-1374 | Oct 29, 2035 |
| US 8829195 ↗ | Drug substance | U-1374 | Oct 29, 2035 |
| US 12252478 ↗ | Drug product | — | May 14, 2040 |
| US 11407735 ↗ | Drug substance | — | May 14, 2040 |
| US 11407735 ↗ | Drug substance | — | May 14, 2040 |
| US 12252478 ↗ | Drug product | — | May 14, 2040 |
| US 11407735 ↗ | Drug substance | — | May 14, 2040 |
| US 12252478 ↗ | Drug product | — | May 14, 2040 |
| Code | What it grants | Expires |
|---|---|---|
| I-953 | New indication (3-year) | Oct 29, 2027 |
| I-954 | New indication (3-year) | Oct 29, 2027 |
| M-318 | New indication / labeling change (3-year) | Oct 2, 2028 |
| NCE | New Chemical Entity (5-year) | Oct 29, 2026 |
| ODE-381 | Orphan Drug Exclusivity (7-year) | Oct 29, 2028 |
| ODE-382 | Orphan Drug Exclusivity (7-year) | Oct 29, 2028 |
| ODE-499 | Orphan Drug Exclusivity (7-year) | Oct 29, 2031 |
| ODE-500 | Orphan Drug Exclusivity (7-year) | Oct 29, 2031 |
| I-953 | New indication (3-year) | Oct 29, 2027 |
| I-954 | New indication (3-year) | Oct 29, 2027 |
| M-318 | New indication / labeling change (3-year) | Oct 2, 2028 |
| NCE | New Chemical Entity (5-year) | Oct 29, 2026 |
| ODE-381 | Orphan Drug Exclusivity (7-year) | Oct 29, 2028 |
| ODE-382 | Orphan Drug Exclusivity (7-year) | Oct 29, 2028 |
| ODE-499 | Orphan Drug Exclusivity (7-year) | Oct 29, 2031 |
| ODE-500 | Orphan Drug Exclusivity (7-year) | Oct 29, 2031 |
| M-318 | New indication / labeling change (3-year) | Oct 2, 2028 |
| NCE | New Chemical Entity (5-year) | Oct 29, 2026 |
| ODE* | Orphan Drug Exclusivity (7-year) | Oct 29, 2028 |
Is there a generic version of SCEMBLIX 100 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00078-1196-20 You're viewing this | 60 TABLET, FILM COATED in 1 BOTTLE (0078-1196-20) | 2024-04-18 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SCEMBLIX is indicated for the treatment of adult patients with: Newly diagnosed Philadelphia chromosome-positive chronic myeloid leukemia (Ph+ CML) in chronic phase (CP). This indication is approved under accelerated approval based on major molecular response rate [see Clinical Studies (14.1)] . Continued approval for this indication may be contingent upon verification of clinical benefit in a confirmatory trial(s).
Previously treated Ph+ CML in CP. Ph+ CML in CP with the T315I mutation. SCEMBLIX is a kinase inhibitor indicated for the treatment of adult patients with: Newly diagnosed Philadelphia chromosome-positive chronic myeloid leukemia (Ph+ CML) in chronic phase (CP).
This indication is approved under accelerated approval based on major molecular response rate. Continued approval for this indication may be contingent upon verification of clinical benefit in a confirmatory trial(s). ( 1 ) Previously treated Ph+ CML in CP.
( 1 ) Ph+ CML in CP with the T315I mutation. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended Dosage in Ph+ CML in CP: 80 mg orally once daily or 40 mg orally twice daily. ( 2.1 ) Recommended Dosage in Ph+ CML in CP with the T315I Mutation: 200 mg orally twice daily. ( 2.2 ) Avoid food for at least 2 hours before and 1 hour after taking SCEMBLIX. ( 2.5 ) Swallow tablets whole. Do not break, crush, or chew the tablets. ( 2.5 )
2.1Recommended Dosage in Patients with Newly Diagnosed or Previously Treated Ph+ CML-CP The recommended dose of SCEMBLIX is 80 mg taken orally once daily at approximately the same time each day or 40 mg orally twice daily at approximately 12-hour intervals. The recommended dose of SCEMBLIX is taken orally without food. Avoid food consumption for at least 2 hours before and 1 hour after taking SCEMBLIX [see Clinical Pharmacology (12.2)] .
Continue treatment with SCEMBLIX as long as clinical benefit is observed or until unacceptable toxicity occurs.
2.2Recommended Dosage in Patients with Ph+ CML-CP with the T315I Mutation The recommended dose of SCEMBLIX is 200 mg taken orally twice daily at approximately 12-hour intervals. The recommended dose of SCEMBLIX is taken orally without food. Avoid food consumption for at least 2 hours before and 1 hour after taking SCEMBLIX [see Clinical Pharmacology (12.2)] .
2.3Missed Dose Once Daily Dosage Regimen: If a SCEMBLIX dose is missed by more than approximately 12 hours, skip the dose and take the next dose as scheduled. Twice Daily Dosage Regimens: If a SCEMBLIX dose is missed by more than approximately 6 hours, skip the dose and take the next dose as scheduled.
2.4Dosage Modifications Dosage Modifications for Patients with Newly Diagnosed or Previously Treated Ph+ CML-CP For the management of adverse reactions, reduce the SCEMBLIX dose as described in Table 1. Dosage Modifications for Patients with Ph+ CML-CP with the T315I Mutation For the management of adverse reactions, reduce the SCEMBLIX dose as described in Table 1. Table 1: Recommended Dosage Reductions for SCEMBLIX for Adverse Reactions Dosage reduction Dosage for Patients with newly diagnosed or previously treated Ph+ CML-CP Dosage for patients with Ph+ CML-CP with the T315I mutation First 40 mg once daily OR 20 mg twice daily 160 mg twice daily Subsequent reduction Permanently discontinue SCEMBLIX in patients unable to tolerate 40 mg once daily OR 20 mg twice daily.
Permanently discontinue SCEMBLIX in patients unable to tolerate 160 mg twice daily. The recommended dosage modifications for the management of selected adverse reactions are shown in Table 2. Table 2: SCEMBLIX Dosage Modification for the Management of Adverse Reactions Abbreviations: ANC, absolute neutrophil count; PLT, platelets; ULN, upper limit of normal. a Based on Common Terminology Criteria for Adverse Events (CTCAE) version 4.03.
Adverse reaction Dosage modification Thrombocytopenia and/or neutropenia [see Warnings and Precautions (5.1)] ANC less than 1 x 10 9 /L and/or PLT less than 50 x 10 9 /L Withhold SCEMBLIX until resolved to ANC greater than or equal to 1 x 10 9 /L and/or PLT greater than or equal to 50 x 10 9 /L. If resolved: Within 2 weeks: resume SCEMBLIX at starting dose. After more than 2 weeks: resume SCEMBLIX at reduced dose.
For recurrent severe thrombocytopenia and/or neutropenia, withhold SCEMBLIX until resolved to ANC greater than or equal to 1 x 10 9 /L and PLT greater than or equal to 50 x 10 9 /L, then resume at reduced dose. Asymptomatic amylase and/or lipase elevation [see Warnings and Precautions (5.2)] Elevation greater than 2 x ULN Withhold SCEMBLIX until resolved to less than 1.5 x ULN. If resolved: Resume SCEMBLIX at reduced dose.
If events reoccur at reduced dose, permanently discontinue SCEMBLIX. If not resolved: Permanently discontinue SCEMBLIX. Perform diagnostic tests to exclude pancreatitis.
Non-hematologic adverse reactions [see Warnings and Precautions (5.3, 5.4, 5.5)] Grade 3 a or higher Withhold SCEMBLIX until recovery to Grade 1 or less. If resolve…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 20 mg asciminib film-coated tablets: pale yellow, unscored, round, biconvex, with beveled edges, film-coated tablet debossed with “20” on one side and the “Novartis” logo on the other side. 40 mg asciminib film-coated tablets: violet white, unscored, round, biconvex, with beveled edges, film-coated tablet debossed with “40” on one side and the “Novartis” logo on the other side. 100 mg asciminib film-coated tablets: light red, unscored, round, biconvex, with beveled edges, film-coated tablet debossed with “100” on one side and the “Novartis” logo on the other side.
Film-coated tablets: 20 mg, 40 mg, and 100 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Myelosuppression: Severe thrombocytopenia and neutropenia events may occur. Monitor complete blood counts regularly during therapy and manage by treatment interruption or dose reduction. ( 2.4 , 5.1 ) Pancreatic Toxicity: Monitor serum lipase and amylase.
Interrupt, then resume at reduced dose or discontinue SCEMBLIX based on severity. Evaluate for pancreatitis when lipase elevation is accompanied by abdominal symptoms. ( 2.4 , 5.2 ) Hypertension: Monitor blood pressure and manage hypertension as clinically indicated.
Interrupt, dose reduce, or stop SCEMBLIX if hypertension is not medically controlled. ( 2.4 , 5.3 ) Hypersensitivity: May cause hypersensitivity reactions. Monitor patients for signs and symptoms and initiate appropriate treatment as clinically indicated.
( 5.4 ) Cardiovascular Toxicity: Cardiovascular toxicity may occur. Monitor patients with history of cardiovascular risk factors for cardiovascular signs and symptoms. Initiate appropriate treatment as clinically indicated.
( 5.5 ) Embryo-Fetal Toxicity: Can cause fetal harm. Advise females of reproductive potential of the potential risk to a fetus and to use effective contraception. ( 5.6 , 8.1 , 8.3 )
5.1Myelosuppression Thrombocytopenia, neutropenia, and anemia have occurred in patients receiving SCEMBLIX. Thrombocytopenia occurred in 156 of 556 (28%) patients receiving SCEMBLIX, with Grade 3 or 4 thrombocytopenia reported in 39 (7%) and 53 (10%) of patients, respectively. Among the patients with Grade 3 or 4 thrombocytopenia, median time to first occurrence of events was 6 weeks (range, 0.1 to 64 weeks).
SCEMBLIX was permanently discontinued in 11 (2%) patients, while it was temporarily withheld in 70 (13%) patients due to thrombocytopenia. Neutropenia occurred in 121 (22%) patients receiving SCEMBLIX, with Grade 3 and 4 neutropenia reported in 42 (8%) and 35 (6%) patients, respectively. Among the patients with Grade 3 or 4 neutropenia, median time to first occurrence of events was 7 weeks (range, 0.1 to 180 weeks).
SCEMBLIX was permanently discontinued in 7 (1.3%) patients, while it was temporarily withheld in 52 (9%) patients due to neutropenia. Anemia occurred in 72 (13%) patients receiving SCEMBLIX, with Grade 3 anemia occurring in 23 (4%) patients. Among the patients with Grade 3 or 4 anemia, median time to first occurrence of events was 24 weeks (range, 0.1 to 207 weeks).
SCEMBLIX was temporarily withheld in 3 (0.5%) patients due to anemia [see Adverse Reactions (6.1)] . Perform complete blood counts every two weeks for the first 3 months of treatment and monthly thereafter or as clinically indicated. Monitor patients for signs and symptoms of myelosuppression.
Based on the severity of thrombocytopenia and/or neutropenia, reduce dose, temporarily withhold, or permanently discontinue SCEMBLIX [see Dosage and Administration (2.4)] .
5.2Pancreatic Toxicity Pancreatitis occurred in 11 of 556 (2%) patients receiving SCEMBLIX, with Grade 3 pancreatitis occurring in 6 (1.1%) patients. SCEMBLIX was permanently discontinued in three (0.5%) patients, while it was temporarily withheld in 6 (1.1%) patients due to pancreatitis. Elevation of serum lipase and amylase occurred in 110 of 556 (20%) patients receiving SCEMBLIX, with Grade 3 and Grade 4 pancreatic enzyme elevations occurring in 41 (7%) and 11 (2%) patients, respectively.
SCEMBLIX was permanently discontinued in 11 (2%) patients due to the elevation of serum lipase and amylase [see Adverse Reactions (6.1)] . Assess serum lipase and amylase levels monthly during treatment with SCEMBLIX, or as clinically indicated. Monitor patients for signs and symptoms of pancreatic toxicity.
Perform more frequent monitoring in patients with a history of pancreatitis. If lipase and amylase elevation are accompanied by abdominal symptoms, temporarily withhold SCEMBLIX and consider appropriate diagnostic tests to exclude pancreatitis [see Dosage and Administration (2.4)] . Based on the severity o…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions can occur with SCEMBLIX and are discussed in greater detail in other sections of the labeling: Myelosuppression [see Warnings and Precautions (5.1)] Pancreatic Toxicity [see Warnings and Precautions (5.2)] Hypertension [see Warnings and Precautions (5.3)] Hypersensitivity [see Warnings and Precautions (5.4)] Cardiovascular Toxicity [see Warnings and Precautions (5.5)] Most common adverse reactions (≥ 20%) are musculoskeletal pain, rash, fatigue, upper respiratory tract infection, headache, abdominal pain, arthralgia, and diarrhea.
( 6.1 ) Most common select laboratory abnormalities (≥ 20%) are lymphocyte count decreased, leukocyte count decreased, platelet count decreased, neutrophil count decreased, calcium corrected decreased, lipase increased, cholesterol increased, uric acid increased, alanine aminotransferase (ALT) increased, alkaline phosphatase (ALP) increased, hemoglobin decreased, triglycerides increased, creatine kinase increased, amylase increased, and aspartate aminotransferase (AST) increased. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Novartis Pharmaceuticals Corporation at 1-888-669-6682 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The pooled safety population described in the WARNINGS AND PRECAUTIONS reflect exposure to SCEMBLIX at 10 mg to 200 mg orally twice daily (between 0.25 to 5 times the recommended dosage for the 80 mg daily dosage and between 0.05 times and up to the recommended dosage for the 200 mg twice daily dosage) in 556 patients enrolled in one of three clinical trials, including patients with Ph+ CML in CP receiving SCEMBLIX as monotherapy: study CABL001J12301 (ASC4FIRST), study CABL001A2301 (ASCEMBL) and study CABL001X2101 [see Clinical Studies (14)] .
Among the 556 patients receiving SCEMBLIX, the median duration of exposure to SCEMBLIX was 123 weeks (range, 0.1 to 439 weeks), with 79% of patients exposed for at least 48 weeks and 71% of patients exposed for at least 96 weeks, respectively. The most common (≥ 20%) adverse reactions in patients who received SCEMBLIX were musculoskeletal pain, rash, fatigue, upper respiratory tract infection, headache, abdominal pain, arthralgia, and diarrhea. Adverse Reactions in Patients with Newly Diagnosed Ph+ CML-CP The ASC4FIRST clinical trial randomized 405 patients with newly diagnosed Ph+ CML-CP to receive SCEMBLIX 80 mg once daily or investigator selected tyrosine kinase inhibitors (IS-TKIs).
IS-TKIs included imatinib (400 mg once daily), nilotinib (300 mg twice daily), dasatinib (100 mg once daily), or bosutinib (400 mg once daily) [see Clinical Studies (14.1)] . The safety population (received at least 1 dose of SCEMBLIX) included 200 patients with newly diagnosed Ph+ CML-CP. Among patients who received SCEMBLIX, 84% were exposed for 96 weeks or longer [see Clinical Studies (14.1)] .
Serious adverse reactions occurred in 15% of patients who received SCEMBLIX. Serious adverse reactions in ≥ 1% included pancreatitis (1%), musculoskeletal pain (1%), and peripheral neuropathy (1%). Permanent discontinuation due to an adverse reaction occurred in 5% of patients receiving SCEMBLIX.
Adverse reactions which resulted in permanent discontinuation of SCEMBLIX in ≥ 1% of patients included pancreatic enzymes increased (1.5%), cardiovascular toxicity (1%), and thrombocytopenia (1%). Dosage interruptions of SCEMBLIX due to an adverse reaction occurred in 33% of patients. Adverse reactions which required dosage interruption in > 5% of patients included thrombocytopenia (13%) and neutropenia (10%).
Dose reductions of SCEMBLIX due to an adverse reaction occurred in 6% of patients. Adver…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong CYP3A4 Inhibitors: Closely monitor for adverse reactions during concomitant use of SCEMBLIX at 200 mg twice daily. ( 7.1 ) Itraconazole Oral Solution Containing Hydroxypropyl-β-cyclodextrin: Avoid concomitant use of SCEMBLIX at all recommended doses. ( 7.1 ) Certain Substrates of CYP3A4: Closely monitor for adverse reactions during concomitant use of SCEMBLIX at 80 mg total daily dose.
Avoid use of SCEMBLIX at 200 mg twice daily. ( 7.2 ) Substrates of CYP2C9: Avoid concomitant use of SCEMBLIX at all recommended doses. 80 mg total daily dose: If unavoidable, reduce the CYP2C9 substrate dosage as necessary.
( 7.2 ) 200 mg twice daily: If unavoidable, consider alternative therapy with non-CYP2C9 substrate. ( 7.2 ) Certain P-gp Substrates: Closely monitor for adverse reactions during concomitant use of SCEMBLIX at all recommended doses. ( 7.2 ) Substrates of BCRP: Avoid concomitant use with rosuvastatin at all recommended doses.
Closely monitor for adverse reactions of other BCRP substrates during concomitant use of SCEMBLIX at all recommended doses. ( 7.2 )
7.1Effect of Other Drugs on SCEMBLIX Strong CYP3A4 Inhibitors Asciminib is a CYP3A4 substrate. Concomitant use of SCEMBLIX with a strong CYP3A4 inhibitor increases both the asciminib C max and AUC, which may increase the risk of adverse reactions [see Clinical Pharmacology (12.3)] . Closely monitor for adverse reactions in patients treated with SCEMBLIX at 200 mg twice daily with concomitant use of strong CYP3A4 inhibitors.
Itraconazole Oral Solution Containing Hydroxypropyl-β-cyclodextrin Concomitant use of SCEMBLIX with itraconazole oral solution containing hydroxypropyl-β-cyclodextrin decreases asciminib C max and AUC, which may reduce SCEMBLIX efficacy [see Clinical Pharmacology (12.3)] . Avoid coadministration of SCEMBLIX at all recommended doses with itraconazole oral solution containing hydroxypropyl-β-cyclodextrin. Strong CYP3A4 Inducers Concomitant use of SCEMBLIX with strong CYP3A4 inducers decreases both the asciminib C max and AUC [see Clinical Pharmacology (12.3)] .
7.2Effect of SCEMBLIX on Other Drugs Certain CYP3A4 Substrates Asciminib is a CYP3A4 inhibitor. Concomitant use of SCEMBLIX increases the C max and AUC of CYP3A4 substrates, which may increase the risk of adverse reactions of these substrates [see Clinical Pharmacology (12.3)] . Closely monitor for adverse reactions in patients treated with SCEMBLIX at 80 mg total daily dose with concomitant use of certain CYP3A4 substrates, where minimal concentration changes may lead to serious adverse reactions.
Avoid coadministration of SCEMBLIX at 200 mg twice daily with certain CYP3A4 substrates, where minimal concentration changes may lead to serious adverse reactions. CYP2C9 Substrates Asciminib is a CYP2C9 inhibitor. Concomitant use of SCEMBLIX increases the C max and AUC of CYP2C9 substrates, which may increase the risk of adverse reactions of these substrates [see Clinical Pharmacology (12.3)] .
Avoid coadministration of SCEMBLIX at 80 mg total daily dose with certain CYP2C9 substrates, where minimal concentration changes may lead to serious adverse reactions. If coadministration is unavoidable, reduce the CYP2C9 substrate dosage as recommended in its prescribing information. Avoid coadministration of SCEMBLIX at 200 mg twice daily with sensitive CYP2C9 substrates and certain CYP2C9 substrates, where minimal concentration changes may lead to serious adverse reactions.
If coadministration is unavoidable, consider alternative therapy with a non-CYP2C9 substrate. Certain P-gp Substrates Asciminib is a P-gp inhibitor. Concomitant use of SCEMBLIX increases the plasma concentrations of P-gp substrates, which may increase the risk of adverse reactions of these substrates [see Clinical Pharmacology (12.3)] .
Closely monitor for adverse reactions in patients treated with SCEMBLIX at all recommended doses with concomitant use of P-gp substrates, where minimal concentration changes may lead…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings from animal studies and the mechanism of action, SCEMBLIX can cause embryo-fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)] . There are no available data on SCEMBLIX use in pregnant women to evaluate a drug-associated risk. Animal reproduction studies in pregnant rats and rabbits demonstrated that oral administration of asciminib during organogenesis induced structural abnormalities, embryo-fetal mortality, and alterations to growth ( see Data ).
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In embryo-fetal development studies, pregnant animals received oral doses of asciminib at 25, 150, and 600 mg/kg/day in rats and at 15, 50, and 300 mg/kg/day in rabbits during the period of organogenesis.
In rats, maternal toxicity at the asciminib dose of 600 mg/kg/day resulted in the early termination of the dose group; a complete embryo-fetal examination was not conducted for this group. Adverse embryo-fetal findings were observed at 25 and 150 mg/kg; these doses did not cause maternal toxicities. Increases in fetal weights at 25 and 150 mg/kg/day were observed, which may be related to increased ossification (i.e., increased rate of development).
Malformations were evident at 150 mg/kg and included cleft palate, anasarca (edema), and cardiac abnormalities. Additional fetal findings included urinary tract and skeletal variations, observed primarily at 150 mg/kg/day. At the dose of 25 mg/kg/day, the area under the curve (AUC) exposures were equivalent to or below those achieved in patients at the 40 mg twice daily or 80 mg once daily doses, respectively.
At the dose of 25 mg/kg/day, the AUC exposures were below those achieved in patients at the 200 mg twice daily dose. In rabbits, maternal toxicities at the asciminib dose of 300 mg/kg/day resulted in the early termination of the dose group; a complete embryo-fetal examination was not conducted for this group. Adverse embryo-fetal findings were observed at 50 mg/kg; this dose did not cause maternal toxicities.
Findings at the 50 mg/kg dose included increases in early resorptions and post-implantation loss, decreases in the number of live fetuses, and cardiac malformations. At the dose of 50 mg/kg/day, the AUC exposures were 4-fold those achieved in patients at the 40 mg twice daily or 80 mg once daily doses. At the dose of 50 mg/kg/day, the AUC exposures were below those achieved in patients at the 200 mg twice daily dose.
8.2Lactation Risk Summary There are no data on the presence of asciminib or its metabolites in human milk, the effects on the breastfed child, or milk production. Because of the potential for serious adverse reactions in the breastfed child, advise women not to breastfeed during treatment with SCEMBLIX and for 1 week after the last dose.
8.3Females and Males of Reproductive Potential Based on findings from animal studies, SCEMBLIX can cause embryo-fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1)] . Pregnancy Testing Verify the pregnancy status of females of reproductive potential prior to starting treatment with SCEMBLIX. Contraception Females Females of reproductive potential should use effective contraception during treatment with SCEMBLIX and for 1 week after the last dose.
Infertility Based on findings in animals, SCEMBLIX may impair fertility in females of reproductive potential [see Nonclinical Toxicology (13.1)] . The reversibility of the effect on fertility is unknown.
8.4Pediatric Use The safety and efficacy of SCEMBLIX in pediatric patients have not been established.
8.5 Geriatric Use Among the 556 patients receiving SCEMBLIX i…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and the mechanism of action, SCEMBLIX can cause embryo-fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)] . There are no available data on SCEMBLIX use in pregnant women to evaluate a drug-associated risk. Animal reproduction studies in pregnant rats and rabbits demonstrated that oral administration of asciminib during organogenesis induced structural abnormalities, embryo-fetal mortality, and alterations to growth ( see Data ).
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In embryo-fetal development studies, pregnant animals received oral doses of asciminib at 25, 150, and 600 mg/kg/day in rats and at 15, 50, and 300 mg/kg/day in rabbits during the period of organogenesis.
In rats, maternal toxicity at the asciminib dose of 600 mg/kg/day resulted in the early termination of the dose group; a complete embryo-fetal examination was not conducted for this group. Adverse embryo-fetal findings were observed at 25 and 150 mg/kg; these doses did not cause maternal toxicities. Increases in fetal weights at 25 and 150 mg/kg/day were observed, which may be related to increased ossification (i.e., increased rate of development).
Malformations were evident at 150 mg/kg and included cleft palate, anasarca (edema), and cardiac abnormalities. Additional fetal findings included urinary tract and skeletal variations, observed primarily at 150 mg/kg/day. At the dose of 25 mg/kg/day, the area under the curve (AUC) exposures were equivalent to or below those achieved in patients at the 40 mg twice daily or 80 mg once daily doses, respectively.
At the dose of 25 mg/kg/day, the AUC exposures were below those achieved in patients at the 200 mg twice daily dose. In rabbits, maternal toxicities at the asciminib dose of 300 mg/kg/day resulted in the early termination of the dose group; a complete embryo-fetal examination was not conducted for this group. Adverse embryo-fetal findings were observed at 50 mg/kg; this dose did not cause maternal toxicities.
Findings at the 50 mg/kg dose included increases in early resorptions and post-implantation loss, decreases in the number of live fetuses, and cardiac malformations. At the dose of 50 mg/kg/day, the AUC exposures were 4-fold those achieved in patients at the 40 mg twice daily or 80 mg once daily doses. At the dose of 50 mg/kg/day, the AUC exposures were below those achieved in patients at the 200 mg twice daily dose.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of SCEMBLIX in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Among the 556 patients receiving SCEMBLIX in the ASC4FIRST, ASCEMBL and X2101 studies, 130 (23%) were 65 years of age and older and 31 (6%) were 75 years of age and older. Overall, no differences in safety or efficacy of SCEMBLIX were observed between patients 65 years of age and older compared to younger patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Asciminib is an ABL/BCR-ABL1 tyrosine kinase inhibitor. Asciminib inhibits the ABL1 kinase activity of the BCR::ABL1 fusion protein, by binding to the ABL myristoyl pocket. In studies conducted in vitro or in animal models of CML, asciminib showed activity against wild-type BCR::ABL1 and several mutant forms of the kinase, including the T315I mutation.
12.2Pharmacodynamics Exposure-Response Relationships Over asciminib dosages of 10 mg to 200 mg twice daily (0.25 to 5 times the recommended 80 mg daily dosage), a lower exposure was associated with a smaller decrease in BCR::ABL1 level and a lower MMR rate at Week 24. Over asciminib dosages of 10 mg to 280 mg twice daily (0.25 to 7 times the recommended 80 mg daily dosage), a higher exposure was associated with slightly higher incidence of some adverse reactions (e.g., Grade ≥ 3 lipase increase, Grade ≥ 3 hemoglobin decrease, Grade ≥ 2 ALT increase, Grade ≥ 2 AST increase, Grade ≥ 2 bilirubin increase, and any grade lipase increase).
Cardiac Electrophysiology Asciminib does not cause a large mean increase in QTc interval (i.e., > 20 msec) at the maximum recommended clinical dosage (200 mg twice daily). Based on available clinical data, small mean QTc increase (< 10 msec) cannot be excluded.
12.3Pharmacokinetics Asciminib steady-state exposure (AUC and C max ) increase slightly more than dose proportional across the dose range of 10 to 200 mg (0.25 to 5 times the recommended 80 mg daily dosage) administered once or twice daily. Pharmacokinetic parameters are presented as geometric mean (CV%) unless otherwise stated. The steady state C max and AUC tau of asciminib at recommended dosages are listed in Table 9.
Table 9: Steady State a Asciminib Exposure at Recommended Dosages a Steady state is achieved within 3 days. b AUC tau represents AUC 0-12h for twice daily dosing and AUC 0-24h for once daily dosing. Asciminib dosage C max (ng/mL) AUC tau b (ng*h/mL) Accumulation ratio 80 mg once daily 1781 (23%) 15112 (28%) 1.30 40 mg twice daily 793 (49%) 5262 (48%) 1.65 200 mg twice daily 5642 (40%) 37547 (41%)
1.92Absorption The median (range) T max of asciminib is 2.5 hours (2 to 3 hours). Effect of Food The AUC and C max of asciminib decreased by 62% and 68%, respectively, with a high-fat meal (1000 calories, 50% fat) and by 30% and 35%, respectively, with a low-fat meal (400 calories, 25% fat) compared to the fasted state following administration of SCEMBLIX. Distribution The apparent volume of distribution of asciminib at steady state is 151 L (135%).
Asciminib is the main circulating component in plasma (93% of the administered dose). Asciminib is 97% bound to human plasma proteins in vitro . Elimination The total apparent clearance of asciminib is
6.7 L/hour (48%) at 40 mg twice daily and 80 mg once daily, and
4.1L/hour (38%) at 200 mg twice daily. The terminal elimination half-life of asciminib is 5.5 hours (38%) at 40 mg twice daily and 80 mg once daily, and 9.0 hours (33%) at 200 mg twice daily. Metabolism Asciminib is metabolized by CYP3A4-mediated oxidation, UGT2B7- and UGT2B17-mediated glucuronidation.
Excretion Eighty percent (57% as unchanged) and 11% (2.5% as unchanged) of the asciminib dose were recovered in the feces and in the urine of healthy subjects, respectively, following oral administration of a single 80 mg dose of radio-labeled asciminib. Asciminib is eliminated by biliary secretion via breast cancer-resistant protein (BCRP). Specific Populations No clinically significant differences in the pharmacokinetics of asciminib were observed based on sex, age (20 to 88 years), race (Asian 20%, White 70%, Black/African American 4%), or body weight (42-184 kg), mild to moderate renal impairment (eGFR 30 to 89 mL/min/1.73 m 2 ), or mild (total bilirubin ≤ ULN and AST > ULN or total bilirubin > 1 to 1.5 times ULN and any AST) to moderate (total bilirubin > 1.5 to 3 times ULN and any AST) hepatic impairment.
Patients with R…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Asciminib is an ABL/BCR-ABL1 tyrosine kinase inhibitor. Asciminib inhibits the ABL1 kinase activity of the BCR::ABL1 fusion protein, by binding to the ABL myristoyl pocket. In studies conducted in vitro or in animal models of CML, asciminib showed activity against wild-type BCR::ABL1 and several mutant forms of the kinase, including the T315I mutation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING SCEMBLIX tablets are available as: Table 12: SCEMBLIX Package Configurations and NDC Numbers Package configuration Tablet strength NDC number Bottle of 60 tablets 20 mg NDC 0078-1091-20 Bottle of 60 tablets 40 mg NDC 0078-1098-20 Bottle of 60 tablets 100 mg NDC 0078-1196-20 SCEMBLIX (asciminib) 20 mg film-coated tablets are supplied as pale yellow, unscored, round, biconvex, with beveled edges, film-coated tablets containing 20 mg of asciminib. Each tablet is debossed with “20” on one side and the “Novartis” logo on the other side.
SCEMBLIX (asciminib) 40 mg film-coated tablets are supplied as violet white, unscored, round, biconvex, with beveled edges, film-coated tablets containing 40 mg of asciminib. Each tablet is debossed with “40” on one side and the “Novartis” logo on the other side. SCEMBLIX (asciminib) 100 mg film-coated tablets are supplied as light red, unscored, round, biconvex, with beveled edges, film-coated tablets containing 100 mg of asciminib.
Each tablet is debossed with “100” on one side and the “Novartis” logo on the other side. Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F) [see USP Controlled Room Temperature]. Dispense and store in the original container in order to protect from moisture.
📋 Description ▾
11 DESCRIPTION SCEMBLIX (asciminib) is a kinase inhibitor. The chemical name of the drug substance is N -[4-(Chlorodifluoromethoxy)phenyl]-6-[(3 R )-3-hydroxypyrrolidin-1-yl]-5-(1 H -pyrazol-3-yl)pyridine-3-carboxamide-hydrogen chloride (1/1). Asciminib hydrochloride is a white to slightly yellow powder.
The molecular formula of asciminib hydrochloride is C 20 H 18 ClF 2 N 5 O 3 .HCl, and the relative molecular mass is 486.30 g/mol for the hydrochloride salt and 449.84 g/mol for the free base. The chemical structure of asciminib hydrochloride is shown below: SCEMBLIX film-coated tablets are supplied for oral use with three strengths that contain 20 mg, 40 mg and 100 mg of asciminib (equivalent to 21.62 mg, 43.24 mg and 108.10 mg, respectively, of asciminib hydrochloride). The tablets contain colloidal silicon dioxide, croscarmellose sodium, ferric oxide, hydroxypropyl cellulose, lactose monohydrate, lecithin, magnesium stearate, microcrystalline cellulose, polyvinyl alcohol, talc, titanium dioxide, and xanthan gum.
The 20 mg tablets contain ferric oxide, yellow and ferric oxide, red. The 40 mg and 100 mg tablets contain ferrosoferric oxide and ferric oxide, red. chemical structure of asciminib hydrochloride
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Myelosuppression Inform patients of the possibility of developing low blood cell counts. Advise patients to immediately report fever, any suggestion of infection, or signs or symptoms suggestive of bleeding or easy bruising [see Warnings and Precautions (5.1)] .
Pancreatic Toxicity Inform patients of the possibility of developing pancreatitis that may be accompanied by nausea, vomiting, severe abdominal pain, or abdominal discomfort, and to promptly report these symptoms [see Warnings and Precautions (5.2)] . Hypertension Inform patients of the possibility of developing hypertension. Advise patients to contact their healthcare provider for elevated blood pressure or if symptoms of hypertension occur, including confusion, headache, dizziness, chest pain, or shortness of breath [see Warnings and Precautions (5.3)] .
Hypersensitivity Advise the patient to discontinue SCEMBLIX and seek immediate medical attention if any signs or symptoms of a hypersensitivity reaction, such as rash, edema, or bronchospasm occur [see Warnings and Precautions (5.4)] . Cardiovascular Toxicity Inform patients of the possibility of the occurrence of cardiovascular toxicity, especially those with a history of cardiovascular risk factors. Advise patients to immediately contact their healthcare provider or get medical help if they develop cardiovascular signs and symptoms [see Warnings and Precautions (5.5)] .
Embryo-Fetal Toxicity Advise females to inform their healthcare provider if they are pregnant or become pregnant. Inform female patients of the potential risk to a fetus [see Use in Specific Populations (8.1)] . Advise females of reproductive potential to use effective contraception during treatment and for 1 week after receiving the last dose of SCEMBLIX [see Warnings and Precautions (5.6), Use in Specific Populations (8.1, 8.3)] .
Lactation Advise women not to breastfeed during treatment with SCEMBLIX and for 1 week after the last dose [see Use in Specific Populations (8.2)] . Infertility Advise females of reproductive potential of the potential for impaired fertility from SCEMBLIX [see Use in Specific Populations (8.3), Nonclinical Toxicology (13.1)] . Drug Interactions Advise patients that SCEMBLIX and certain other medicines, including over-the-counter medications or herbal supplements, can interact with each other and may alter the effects of SCEMBLIX [see Drug Interactions (7)] .
Instructions for Taking SCEMBLIX Advise patients to take SCEMBLIX exactly as prescribed and not to change their dose or schedule or to stop taking SCEMBLIX unless they are told to do so by their healthcare provider. Advise patients to take SCEMBLIX orally without food. Advise patients to avoid food for at least 2 hours before and 1 hour after taking SCEMBLIX.
SCEMBLIX tablets should be swallowed whole. Patients should not break, crush, or chew the tablets [see Dosage and Administration (2.5)] . Advise patients that if they take SCEMBLIX once daily and miss a dose by more than 12 hours to skip the missed dose.
Advise patients that if they take SCEMBLIX twice daily and miss a dose by more than 6 hours to skip the missed dose. Advise patients to take the next dose as scheduled [see Dosage and Administration (2.3)] . Distributed by: Novartis Pharmaceuticals Corporation One Health Plaza East Hanover, New Jersey 07936 © Novartis T2025-68