
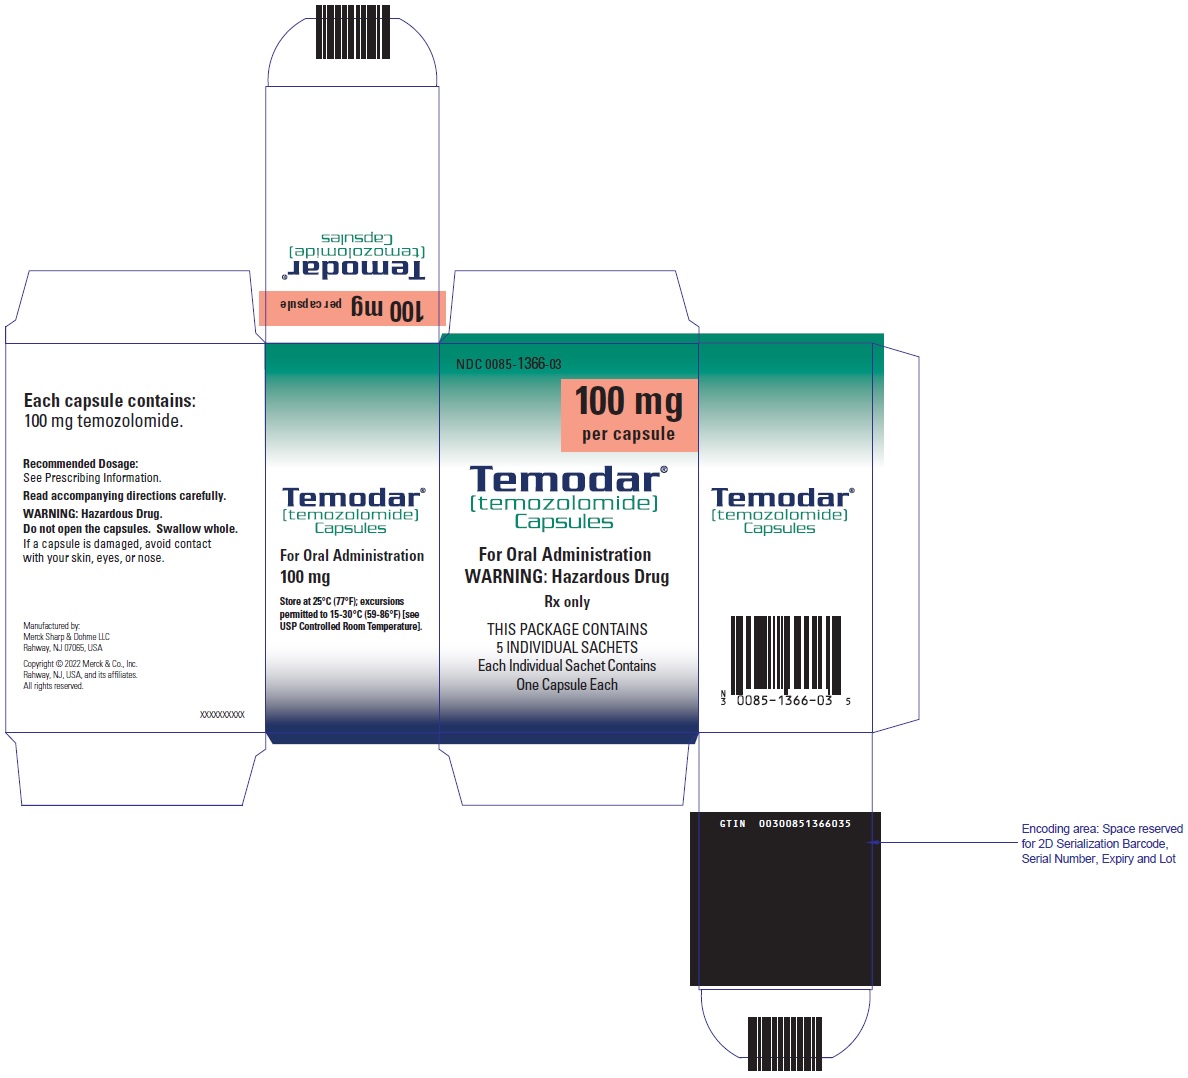
TEMODAR Temozolomide 100 mg Capsule, 14-count — NDC 0085-1366-04 (Billing 00085-1366-04)
This is a package of 14 capsules of TEMODAR Temozolomide 100 mg Capsule from Merck Sharp & Dohme LLC, marketed since Aug 1999 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 0085-1366-04 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0085 labeler · 1366 product · 04 package
- Package marketed since
- Aug 11, 1999
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 14 EA per package
- Barcode (UPC-A, from the NDC)
- 3 0085136604 2
- FDA record last changed
- Jul 24, 2026
Other active recalls for Temozolomide (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 043012
- GCN: 92913
- GPI-14 (Medi-Span): 21104070000140
- HICL (First Databank): 020355
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 261288
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Alkylating Drug class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Temozolomide is used to treat certain types of brain tumors. Temozolomide is in a class of medications called alkylating agents. It works by slowing or stopping the growth of cancer cells in your body.
Read the full MedlinePlus article ↗- Temozolomide is a chemotherapy used to treat aggressive brain tumors — specifically glioblastoma (a fast-growing brain tumor) and anaplastic astrocytoma. It works by getting into c...
- What exactly is temozolomide treating, and why do I need it?
- Yes, it does matter. Swallow the capsules whole with a full glass of water — never open, crush, or chew them. Try to avoid taking them right after a high-fat meal, because fat can...
- How should I take the capsules — does it matter when I take them or whether I eat first?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Temozolomide — tap one for details:
Temozolomide may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · NONE | No ASP payment limit on file for NONE this quarter. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00085-1366-03 0085-1366-03 Main listing | 5 PACKET in 1 CARTON / 1 CAPSULE in 1 PACKET | 1999-08-11 | — | Active |
| 00085-1366-04 You're viewing this | 14 PACKET in 1 CARTON / 1 CAPSULE in 1 PACKET | 1999-08-11 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00085-1366-03?
What NDC number is used to bill for this package of TEMODAR Temozolomide 100 mg Capsule?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Temozolomide 100 mg 16729-0050-53 | Accord | 5 capsules | $4.375 | AB | Availability likely | — |
| Temozolomide 100 mg 31722-0413-14 | Camber | 14 capsules | $4.375 | AB | Availability likely | — |
| Temozolomide 100 mg 65162-0803-14 | Amneal | 14 capsules | $4.375 | AB | Availability likely | — |
| Temozolomide 100 mg 67877-0539-07 | Ascend | 5 capsules | $4.375 | AB | Availability likely | — |
| Temozolomide 100 mg 73043-0013-05 | Devatis, | 5 capsules | $4.375 | AB | Availability likely | — |
| Temodar 100 mgthis 00085-1366-04 | Merck | 14 capsules | — | — | FDA listed | — |
| Temozolomide 100 mg 16571-0818-02 | Rising | 20 capsules | — | AB | FDA listed | — |
| Temozolomide 100 mg 47335-0892-21 | Sun | 14 capsules | — | AB | FDA listed | — |
| Temozolomide 100 mg 72162-2661-02 | Bryant | 5 capsules | — | AB | FDA listed | — |
| temozolomide 100 mg 75834-0143-05 | Nivagen | 5 capsules | — | — | FDA listed | — |
| Temozolomide 100 mg 82249-0408-05 | CivicaScript | 5 capsules | — | AB | FDA listed | — |
| Temozolomide 100 mg 70301-2005-01 | OPKO | 5 capsules | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Temozolomide inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Merck Sharp & Dohme LLC labeler code 00085
- NOXAFIL posaconazole 40 mg/mL Suspension NDC 0085-1328-01
- TEMODAR Temozolomide 2.5 mg/mL Injection, Powder, Lyophilized, For Solution NDC 0085-1381-01
- TEMODAR Temozolomide 250 mg Capsule NDC 0085-1417-02
- TEMODAR Temozolomide 140 mg Capsule NDC 0085-1425-03
- TEMODAR Temozolomide 180 mg Capsule NDC 0085-1430-03
- TEMODAR Temozolomide 20 mg Capsule NDC 0085-1519-03
- Noxafil posaconazole 300 mg Powder, For Suspension NDC 0085-2224-02
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE TEMODAR is an alkylating drug indicated for the treatment of adults with: Newly diagnosed glioblastoma concomitantly with radiotherapy and then as maintenance treatment. ( 1.1 ) Anaplastic astrocytoma. ( 1.2 ) Adjuvant treatment of adults with newly diagnosed anaplastic astrocytoma. ( 1.2 ) Treatment of adults with refractory anaplastic astrocytoma. ( 1.2 )
1.1Newly Diagnosed Glioblastoma TEMODAR is indicated for the treatment of adults with newly diagnosed glioblastoma, concomitantly with radiotherapy and then as maintenance treatment.
1.2Anaplastic Astrocytoma TEMODAR is indicated for the: adjuvant treatment of adults with newly diagnosed anaplastic astrocytoma; treatment of adults with refractory anaplastic astrocytoma.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administer either orally or intravenously. ( 2.4 ) Newly Diagnosed Glioblastoma : 75 mg/m 2 once daily for 42 to 49 days concomitant with focal radiotherapy followed by initial maintenance dose of 150 mg/m 2 once daily for Days 1 to 5 of each 28-day cycle for 6 cycles. May increase maintenance dose to 200 mg/m 2 for Cycles 2 to 6 based on toxicity.
( 2.1 ) Provide Pneumocystis pneumonia (PCP) prophylaxis during concomitant phase and continue in patients who develop lymphopenia until resolution to Grade 1 or less. ( 2.1 ) Adjuvant Treatment of Newly Diagnosed Anaplastic Astrocytoma: Beginning 4 weeks after the end of radiotherapy, administer TEMODAR orally in a single dose on days 1-5 of a 28-day cycle for 12 cycles. The recommended dosage for Cycle 1 is 150 mg/m 2 per day and for Cycles 2 to 12 is 200 mg/m 2 if patient experienced no or minimal toxicity in Cycle 1.
( 2.2 ) Refractory Anaplastic Astrocytoma: Initial dose of 150 mg/m 2 once daily on Days 1 to 5 of each 28-day cycle. ( 2.2 )
2.1Monitoring to Inform Dosage and Administration Prior to dosing, withhold TEMODAR until patients have an absolute neutrophil count (ANC) of 1.5 x 10 9 /L or greater and a platelet count of 100 x 10 9 /L or greater. For concomitant radiotherapy, obtain a complete blood count prior to initiation of treatment and weekly during treatment. For the 28-day treatment cycles, obtain a complete blood count prior to treatment on Day 1 and on Day 22 of each cycle.
Perform complete blood counts weekly until recovery if the ANC falls below 1.5 x 10 9 /L and the platelet count falls below 100 x 10 9 /L. For concomitant use with focal radiotherapy, obtain a complete blood count weekly and as clinically indicated.
2.2Recommended Dosage and Dosage Modifications for Newly Diagnosed Glioblastoma Administer TEMODAR either orally or intravenously once daily for 42 to 49 consecutive days during the concomitant use phase with focal radiotherapy, and then once daily on Days 1 to 5 of each 28-day cycle for 6 cycles during the maintenance use phase. Provide Pneumocystis pneumonia (PCP) prophylaxis during the concomitant use phase and continue in patients who develop lymphopenia until resolution to Grade 1 or less [see Warnings and Precautions (5.3) ] .
Concomitant Use Phase: The recommended dosage of TEMODAR is 75 mg/m 2 either orally or intravenously once daily for 42 to 49 days in combination with focal radiotherapy. Focal radiotherapy includes the tumor bed or resection site with a 2 to 3 cm margin. Other administration schedules have been used.
Obtain a complete blood count weekly. The recommended dosage modifications due to adverse reactions during concomitant use phase are provided in Table 1 . TABLE 1: Dosage Modifications Due to Adverse Reactions During Concomitant Use Phase Adverse Reaction Interruption Discontinuation Absolute Neutrophil Count Withhold TEMODAR if ANC is greater than or equal to 0.5 × 10 9 /L and less than 1.5 × 10 9 /L.
Discontinue TEMODAR if ANC is less than 0.5 × 10 9 /L. Resume TEMODAR at the same dose when ANC is greater than or equal to 1.5 × 10 9 /L. Platelet Count Withhold TEMODAR if platelet count is greater than or equal to 10 × 10 9 /L and less than 100 × 10 9 /L.
Discontinue TEMODAR if platelet count is less than 10 × 10 9 /L. Resume TEMODAR at the same dose when platelet count is greater than or equal to 100 × 10 9 /L. Non-hematological Adverse Reaction (except for alopecia, nausea, vomiting) Withhold TEMODAR if Grade 2 adverse reaction occurs.
Discontinue TEMODAR if Grade 3 or 4 adverse reaction occurs. Resume TEMODAR at the same dose when resolution to Grade 1 or less. Single Agent Maintenance Use Phase: Beginning 4 weeks after concomitant use phase completion, administer TEMODAR either orally or intravenously once daily on Days 1 to 5 of each 28-day cycle for 6 cycles.
The recommended dosage of TEMODAR in the maintenance use phase is: Cycle 1: 150 mg/m 2 per day on days 1 to 5. Cycles 2 to 6: May… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules: – 5 mg: opaque white bodies with green caps. The capsule body is imprinted with two stripes, the dosage strength, and the Schering-Plough logo. The cap is imprinted with “TEMODAR.” – 20 mg: opaque white bodies with yellow caps.
The capsule body is imprinted with two stripes, the dosage strength, and the Schering-Plough logo. The cap is imprinted with “TEMODAR.” – 100 mg: opaque white bodies with pink caps. The capsule body is imprinted with two stripes, the dosage strength, and the Schering-Plough logo.
The cap is imprinted with “TEMODAR.” – 140 mg: opaque white bodies with blue caps. The capsule body is imprinted with two stripes, the dosage strength, and the Schering-Plough logo. The cap is imprinted with “TEMODAR.” – 180 mg: opaque white bodies with orange caps.
The capsule body is imprinted with two stripes, the dosage strength, and the Schering-Plough logo. The cap is imprinted with “TEMODAR.” – 250 mg: opaque white bodies with white caps. The capsule body is imprinted with two stripes, the dosage strength, and the Schering-Plough logo.
The cap is imprinted with “TEMODAR.” For injection: 100 mg white to light tan or light pink lyophilized powder for reconstitution in a single-dose vial. Capsules: 5 mg, 20 mg, 100 mg, 140 mg, 180 mg, and 250 mg. ( 3 ) For injection: 100 mg as a lyophilized powder in single-dose vial for reconstitution.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS TEMODAR is contraindicated in patients with a history of serious hypersensitivity reactions to: temozolomide or any other ingredients in TEMODAR; and dacarbazine, since both temozolomide and dacarbazine are metabolized to the same active metabolite 5-(3-methyltriazen-1-yl)-imidazole-4-carboxamide. Reactions to TEMODAR have included anaphylaxis [see Adverse Reactions (6.2) ]. History of serious hypersensitivity to temozolomide or any other ingredients in TEMODAR and dacarbazine.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Myelosuppression : Monitor absolute neutrophil count (ANC) and platelet count prior to each cycle and during treatment. Geriatric patients and women have a higher risk of developing myelosuppression. ( 5.1 , 8.5 ) Hepatotoxicity : Fatal and severe hepatotoxicity have been reported.
Perform liver tests at baseline, midway through the first cycle, prior to each subsequent cycle, and approximately 2 to 4 weeks after the last dose of TEMODAR. ( 5.2 ) Pneumocystis Pneumonia (PCP) : Closely monitor all patients, particularly those receiving steroids, for the development of lymphopenia and PCP. ( 5.3 ) Secondary Malignancies: Myelodysplastic syndrome and secondary malignancies, including myeloid leukemia, have been observed.
( 5.4 ) Embryo-Fetal Toxicity : Can cause fetal harm. Advise females of reproductive potential of the potential risk to a fetus and to use effective contraception. Advise male patients with pregnant partners or female partners of reproductive potential to use condoms.
( 5.5 , 8.1 , 8.3 ) Exposure to Opened Capsules: TEMODAR capsules should not be opened, chewed, or dissolved but should be swallowed whole with a glass of water. ( 5.6 )
5.1Myelosuppression Myelosuppression, including pancytopenia, leukopenia, and anemia, some with fatal outcomes, have occurred with TEMODAR [see Adverse Reactions (6.1 , 6.2) ] . In MK-7365-006, myelosuppression usually occurred during the first few cycles of therapy and was generally not cumulative. The median nadirs occurred at 26 days for platelets (range: 21 to 40 days) and 28 days for neutrophils (range: 1 to 44 days).
Approximately 10% of patients required hospitalization, blood transfusion, or discontinuation of therapy due to myelosuppression. Geriatric patients and women have been shown in clinical trials to have a higher risk of developing myelosuppression. Obtain a complete blood count and monitor ANC and platelet counts before initiation of treatment and as clinically indicated during treatment.
When TEMODAR is used in combination with radiotherapy, obtain a complete blood count prior to initiation of treatment, weekly during treatment, and as clinically indicated [see Dosage and Administration (2.1 , 2.2 , 2.3) ]. For severe myelosuppression, withhold TEMODAR and then resume at same or reduced dose, or permanently discontinue, based on occurrence [see Dosage and Administration (2.1 , 2.2 , 2.3) ] .
5.2Hepatotoxicity Fatal and severe hepatotoxicity have been reported in patients receiving TEMODAR. Perform liver tests at baseline, midway through the first cycle, prior to each subsequent cycle, and approximately two to four weeks after the last dose of TEMODAR.
5.3Pneumocystis Pneumonia Pneumocystis pneumonia (PCP) has been reported in patients receiving TEMODAR. The risk of PCP is increased in patients receiving steroids or with longer treatment regimens of TEMODAR. For patients with newly diagnosed glioblastoma, provide PCP prophylaxis for all patients during the concomitant phase.
Continue PCP prophylaxis in patients who experience lymphopenia, until resolution to Grade 1 or less [see Dosage and Administration (2.1) ] . Monitor all patients receiving TEMODAR for the development of lymphopenia and PCP.
5.4Secondary Malignancies The incidence of secondary malignancies is increased in patients treated with TEMODAR-containing regimens. Cases of myelodysplastic syndrome and secondary malignancies, including myeloid leukemia, have been observed following TEMODAR administration.
5.5Embryo-Fetal Toxicity Based on findings from animal studies and its mechanism of action, TEMODAR can cause fetal harm when administered to a pregnant woman. Adverse developmental outcomes have been reported in both pregnant patients and pregnant partners of male patients. Oral administration of temozolomide to rats and rabbits during the period of organogenesis resulted in embryolethality and polymalformations at doses less than the maximum human dose based on body sur… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Myelosuppression [see Warnings and Precautions (5.1) ] Hepatotoxicity [see Warnings and Precautions (5.2) ] Pneumocystis Pneumonia [see Warnings and Precautions (5.3) ] Secondary Malignancies [see Warnings and Precautions (5.4) ] The most common adverse reactions (≥20%) are: alopecia, fatigue, nausea, vomiting, headache, constipation, anorexia, and convulsions. ( 6.1 ) The most common Grade 3 to 4 hematologic laboratory abnormalities (≥10%) in patients with anaplastic astrocytoma are: decreased lymphocytes, decreased platelets, decreased neutrophils, and decreased leukocytes.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Merck Sharp & Dohme LLC at 1-877-888-4231 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Newly Diagnosed Glioblastoma The safety of TEMODAR was evaluated in study MK-7365-051 [see Clinical Studies (14.1) ]. Severe or life-threatening adverse reactions occurred in 49% of patients treated with TEMODAR; the most common were fatigue (13%), convulsions (6%), headache (5%), and thrombocytopenia (5%).
The most common adverse reactions (≥20%) in patients treated with TEMODAR were alopecia, fatigue, nausea, anorexia, headache, constipation, and vomiting. Table 3 summarizes the adverse reactions in MK-7365-051. TABLE 3: Adverse Reactions (≥10%) in Patients with Newly Diagnosed Glioblastoma Adverse Reactions Concomitant Use Phase Maintenance Use Phase Radiation Therapy and TEMODAR N=288 One patient who was randomized to radiation therapy-only arm received radiation therapy and TEMODAR.
Radiation Therapy Alone N=285 TEMODAR N=224 All Grades (%) Grade ≥3 (%) All Grades (%) Grades ≥3 (%) All Grades (%) Grade ≥3 (%) Note: Grade 5 (fatal) adverse reactions are included in the Grade ≥3 column. Skin and Subcutaneous Tissue Alopecia 69 0 63 0 55 0 Rash 19 1 15 0 13 1 General Fatigue 54 7 49 5 61 9 Anorexia 19 1 9 <1 27 1 Headache 19 2 17 4 23 4 Gastrointestinal System Nausea 36 1 16 <1 49 1 Vomiting 20 <1 6 <1 29 2 Constipation 18 1 6 0 22 0 Diarrhea 6 0 3 0 10 1 Central and Peripheral Nervous System Convulsions 6 3 7 3 11 3 Clinically relevant adverse reactions in <10% of patients are presented below: Central & Peripheral Nervous System: memory impairment, confusion Eye: v ision blurred Gastrointestinal System: stomatitis, abdominal pain General: weakness, dizziness Immune System: allergic reaction Injury: radiation injury not otherwise specified Musculoskeletal System: arthralgia Platelet, Bleeding, & Clotting: thrombocytopenia Psychiatric: insomnia Respiratory System: coughing, dyspnea Special Senses Other: taste perversion Skin & Subcutaneous Tissue: dry skin, pruritus, erythema When laboratory abnormalities and adverse reactions were combined, Grade 3 or Grade 4 neutrophil abnormalities including neutropenic reactions were observed in 8% of patients, and Grade 3 or Grade 4 platelet abnormalities including thrombocytopenic reactions were observed in 14% of patients.
Newly Diagnosed Anaplastic Astrocytoma The safety of TEMODAR for the adjuvant treatment of adults with newly diagnosed anaplastic astrocytoma was derived from published literature [see Clinical Studies (14.2) ]. The safety of TEMODAR for the adjuvant treatment of patients with newly diagnosed anaplastic astrocytoma was consistent with the known safety profile of TEMODAR. Refractory Anaplastic Astrocytoma The safety of TEMODAR was evaluated in study MK-7365-006 [see Clinical Studies (14.2) ].
The most common adverse reactions (≥20%) were nausea, vomiting, headache, fatigue, constipation, and convulsions. Tables 4 and 5 summarize the adverse reactio… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology (12.1) ] , TEMODAR can cause fetal harm when administered to a pregnant woman. Available postmarketing reports describe cases of spontaneous abortions and congenital malformations, including polymalformations with central nervous system, facial, cardiac, skeletal, and genitourinary system anomalies with exposure to TEMODAR during pregnancy. These cases report similar adverse developmental outcomes to those observed in animal studies.
Administration of TEMODAR to rats and rabbits during the period of organogenesis caused numerous external, internal, and skeletal malformations at doses less than the maximum human dose based on body surface area (see Data ) . Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Five consecutive days of oral administration of temozolomide at doses of 75 and 150 mg/m 2 (0.38 and 0.75 times the human dose of 200 mg/m 2 ) in rats and rabbits, respectively, during the period of organogenesis (Gestation Days 8-12) caused numerous malformations of the external and internal organs and skeleton in both species. In rabbits, temozolomide at the 150 mg/m 2 dose (0.75 times the human dose of 200 mg/m 2 ) caused embryolethality as indicated by increased resorptions.
8.2Lactation There are no data on the presence of TEMODAR or its metabolites in human milk, the effects on a breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions, including myelosuppression from temozolomide in the breastfed children, advise women not to breastfeed during treatment with TEMODAR and for 1 week after the last dose.
8.3Females and Males of Reproductive Potential TEMODAR can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to initiating TEMODAR [see Use in Specific Populations (8.1) ] . Contraception Females Advise females of reproductive potential to use effective contraception during treatment with TEMODAR and for 6 months after the last dose.
Males Because of the potential for embryofetal toxicity and genotoxic effects on sperm cells, advise male patients with pregnant partners or female partners of reproductive potential to use condoms during treatment with TEMODAR and for 3 months after the last dose [see Use in Specific Populations (8.1) , Nonclinical Toxicology (13.1) ] . Advise male patients not to donate semen during treatment with TEMODAR and for 3 months after the last dose. Infertility TEMODAR may impair male fertility [see Nonclinical Toxicology (13.1) ] .
Limited data from male patients show changes in sperm parameters during treatment with TEMODAR; however, no information is available on the duration or reversibility of these changes.
8.4Pediatric Use Safety and effectiveness of TEMODAR have not been established in pediatric patients. Safety and effectiveness of TEMODAR capsules were assessed, but not established, in 2 open-label studies in pediatric patients aged 3 to 18 years. In one study, 29 patients with recurrent brain stem glioma and 34 patients with recurrent high-grade astrocytoma were enrolled.
In a second study conducted by the Children's Oncology Group (COG), 122 patients were enrolled, including patients with medulloblastoma/PNET (29), high grade astrocytoma (23), low grade astrocytoma (22), brain stem glioma (16), ependymoma (14), other CNS tumors (9), and non-CNS tumors (9). The adverse reaction profile in pediatric patients was similar to adults.
8.5Geriatric Use In MK-7365-051, 15% of patients with newly diagnosed glioblastoma w… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology (12.1) ] , TEMODAR can cause fetal harm when administered to a pregnant woman. Available postmarketing reports describe cases of spontaneous abortions and congenital malformations, including polymalformations with central nervous system, facial, cardiac, skeletal, and genitourinary system anomalies with exposure to TEMODAR during pregnancy. These cases report similar adverse developmental outcomes to those observed in animal studies.
Administration of TEMODAR to rats and rabbits during the period of organogenesis caused numerous external, internal, and skeletal malformations at doses less than the maximum human dose based on body surface area (see Data ) . Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Five consecutive days of oral administration of temozolomide at doses of 75 and 150 mg/m 2 (0.38 and 0.75 times the human dose of 200 mg/m 2 ) in rats and rabbits, respectively, during the period of organogenesis (Gestation Days 8-12) caused numerous malformations of the external and internal organs and skeleton in both species. In rabbits, temozolomide at the 150 mg/m 2 dose (0.75 times the human dose of 200 mg/m 2 ) caused embryolethality as indicated by increased resorptions.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of TEMODAR have not been established in pediatric patients. Safety and effectiveness of TEMODAR capsules were assessed, but not established, in 2 open-label studies in pediatric patients aged 3 to 18 years. In one study, 29 patients with recurrent brain stem glioma and 34 patients with recurrent high-grade astrocytoma were enrolled.
In a second study conducted by the Children's Oncology Group (COG), 122 patients were enrolled, including patients with medulloblastoma/PNET (29), high grade astrocytoma (23), low grade astrocytoma (22), brain stem glioma (16), ependymoma (14), other CNS tumors (9), and non-CNS tumors (9). The adverse reaction profile in pediatric patients was similar to adults.
🧓 Geriatric Use ▾
8.5Geriatric Use In MK-7365-051, 15% of patients with newly diagnosed glioblastoma were 65 years and older. This study did not include sufficient numbers of patients aged 65 years and older to determine differences in effectiveness from younger patients. No overall differences in safety were observed between patients ≥65 years and younger patients.
The CATNON trial did not include sufficient numbers of patients aged 65 years and older to determine differences in safety or effectiveness when compared to younger patients. In MK-7365-006, 4% of patients with refractory anaplastic astrocytoma were 70 years and older. This study did not include sufficient numbers of patients aged 70 years and older to determine differences in effectiveness from younger patients.
Patients 70 years and older had a higher incidence of Grade 4 neutropenia (25%) and Grade 4 thrombocytopenia (20%) in the first cycle of therapy than patients less than 70 years of age [see Warnings and Precautions (5.1) , Adverse Reactions (6.1) ] . In the entire safety database for which hematologic data exist (N=932), 7% (4/61) and 10% (6/63) of patients >70 years experienced Grade 4 neutropenia or thrombocytopenia in the first cycle, respectively. For patients ≤70 years, 7% (62/871) and 6% (48/879) experienced Grade 4 neutropenia or thrombocytopenia in the first cycle, respectively.
Pancytopenia, leukopenia, and anemia also occurred.
🆘 Overdosage ▾
10 OVERDOSAGE Dose-limiting toxicity was myelosuppression and was reported with any dose but is expected to be more severe at higher doses. An overdose of 2000 mg per day for 5 days was taken by one patient and the adverse reactions reported were pancytopenia, pyrexia, multi-organ failure, and death. There are reports of patients who have taken more than 5 days of treatment (up to 64 days), with adverse reactions reported including myelosuppression, which in some cases was severe and prolonged, and infections and resulted in death.
In the event of an overdose, monitor complete blood count and provide supportive measures as necessary.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Temozolomide is not directly active but undergoes rapid nonenzymatic conversion at physiologic pH to the reactive compound 5-(3-methyltriazen-1-yl)-imidazole-4-carboxamide (MTIC). The cytotoxicity of MTIC is thought to be primarily due to DNA alkylation, mainly at the O 6 and N 7 positions of guanine, which causes DNA double strand breaks and results in programmed cell death.
12.2Pharmacodynamics Temozolomide exposure-response relationships and the time course of pharmacodynamic response are unknown.
12.3Pharmacokinetics Following a single oral dose of 150 mg/m 2 , the mean C max is 7.5 mcg/mL for temozolomide and 282 ng/mL for MTIC. The mean AUC is 23.4 mcg∙hr/mL for temozolomide and 864 ng∙hr/mL for MTIC. Following a single 90-minute intravenous infusion of 150 mg/m 2 , the mean C max is 7.3 mcg/mL for temozolomide and 276 ng/mL for MTIC.
The mean AUC is 24.6 mcg∙hr/mL for temozolomide and 891 ng∙hr/mL for MTIC. Temozolomide exhibits linear kinetics over the therapeutic dosing range of 75 mg/m 2 /day to 250 mg/m 2 /day. Absorption The median T max is 1 hour.
Effect of Food The mean temozolomide C max and AUC decreased by 32% and 9%, respectively, and median T max increased by 2-fold (from 1 to 2.25 hours) when TEMODAR capsules were administered after a modified high-fat breakfast (587 calories comprised of 1 fried egg, 2 strips of bacon, 2 slices of toast, 2 pats of butter, and 8 oz whole milk). Distribution Temozolomide has a mean (CV%) apparent volume of distribution of
0.4L/kg (13%). The mean percent bound of drug-related total radioactivity is 15%. Elimination Clearance of temozolomide is approximately
5.5L/hr/m 2 and the mean elimination half-life is 1.8 hours. Metabolism Temozolomide is spontaneously hydrolyzed at physiologic pH to the active species, MTIC and to temozolomide acid metabolite. MTIC is further hydrolyzed to 5-amino-imidazole-4-carboxamide (AIC), which is known to be an intermediate in purine and nucleic acid biosynthesis, and to methylhydrazine, which is believed to be the active alkylating species.
Cytochrome P450 enzymes play a minor role in the metabolism of temozolomide and MTIC. Relative to the AUC of temozolomide, the exposure to MTIC and AIC is 2.4% and 23%, respectively. Excretion Approximately 38% of the administered temozolomide total radioactive dose is recovered over 7 days: 38% in urine and 0.8% in feces.
The majority of the recovered radioactivity in urine is unchanged temozolomide (6%), AIC (12%), temozolomide acid metabolite (2.3%), and unidentified polar metabolite(s) (17%). Specific Populations No clinically significant differences in the pharmacokinetics of temozolomide were observed based on age (range: 19 to 78 years), gender, smoking status (smoker vs. non-smoker), creatinine clearance (CLcr) of 36 to 130 mL/min/m 2 , or mild to moderate hepatic impairment (Child Pugh class A and B). The pharmacokinetics of temozolomide has not been studied in patients with CLcr <36 mL/min/m 2 , end-stage renal disease on dialysis, or severe hepatic impairment (Child-Pugh class C).
Drug Interaction Studies Clinical Studies and Model-Informed Approaches No clinically significant differences in the pharmacokinetics of temozolomide or MTIC were observed when co-administered with ranitidine. No clinically significant differences in the clearance of temozolomide or MTIC were predicted when co-administered with the following drugs: valproic acid, dexamethasone, prochlorperazine, phenytoin, carbamazepine, ondansetron, histamine-2-receptor antagonists, or phenobarbital.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Temozolomide is not directly active but undergoes rapid nonenzymatic conversion at physiologic pH to the reactive compound 5-(3-methyltriazen-1-yl)-imidazole-4-carboxamide (MTIC). The cytotoxicity of MTIC is thought to be primarily due to DNA alkylation, mainly at the O 6 and N 7 positions of guanine, which causes DNA double strand breaks and results in programmed cell death.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING TEMODAR is a hazardous drug. Follow applicable special handling and disposal procedures. 1 TEMODAR capsules TEMODAR capsules are supplied in child-resistant sachets containing the following capsule strengths: 5 mg: opaque white bodies with green caps.
The capsule body is imprinted with two stripes, the dosage strength, and the Schering-Plough logo. The cap is imprinted with “TEMODAR”. They are supplied as follows: 5-count – NDC 0085-3004-03 14-count – NDC 0085-3004-04 20 mg: opaque white bodies with yellow caps.
The capsule body is imprinted with two stripes, the dosage strength, and the Schering-Plough logo. The cap is imprinted with “TEMODAR”. They are supplied as follows: 5-count – NDC 0085-1519-03 14-count – NDC 0085-1519-04 100 mg: opaque white bodies with pink caps.
The capsule body is imprinted with two stripes, the dosage strength, and the Schering-Plough logo. The cap is imprinted with “TEMODAR”. They are supplied as follows: 5-count – NDC 0085-1366-03 14-count – NDC 0085-1366-04 140 mg: opaque white bodies with blue caps.
The capsule body is imprinted with two stripes, the dosage strength, and the Schering-Plough logo. The cap is imprinted with “TEMODAR”. They are supplied as follows: 5-count – NDC 0085-1425-03 14-count – NDC 0085-1425-04 180 mg: opaque white bodies with orange caps.
The capsule body is imprinted with two stripes, the dosage strength, and the Schering-Plough logo. The cap is imprinted with “TEMODAR”. They are supplied as follows: 5-count – NDC 0085-1430-03 14-count – NDC 0085-1430-04 250 mg: opaque white bodies with white caps.
The capsule body is imprinted with two stripes, the dosage strength, and the Schering-Plough logo. The cap is imprinted with “TEMODAR”. They are supplied as follows: 5-count – NDC 0085-1417-02 Store TEMODAR Capsules at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
TEMODAR for injection TEMODAR for injection is supplied in single-dose glass vials containing 100 mg temozolomide. The lyophilized powder is white to light tan or light pink. NDC 0085-1381-01 Store TEMODAR for injection refrigerated at 2°C to 8°C (36°F to 46°F).
📦 Storage and Handling ▾
Store TEMODAR Capsules at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Store TEMODAR for injection refrigerated at 2°C to 8°C (36°F to 46°F).
📋 Description ▾
11 DESCRIPTION Temozolomide is an alkylating drug. The chemical name of temozolomide is 3,4-dihydro-3-methyl-4-oxoimidazo[5,1-d]- as -tetrazine-8-carboxamide. The structural formula of temozolomide is: The material is a white to light tan or light pink powder with a molecular formula of C 6 H 6 N 6 O 2 and a molecular weight of 194.15.
The molecule is stable at acidic pH (<5) and labile at pH >7; hence TEMODAR can be administered orally and intravenously. The prodrug, temozolomide, is rapidly hydrolyzed to the active 5-(3-methyltriazen-1-yl) imidazole-4-carboxamide (MTIC) at neutral and alkaline pH values, with hydrolysis taking place even faster at alkaline pH. TEMODAR capsules TEMODAR (temozolomide) capsules for oral use contains either 5 mg, 20 mg, 100 mg, 140 mg, 180 mg, or 250 mg of temozolomide.
The inactive ingredients are as follows: TEMODAR 5 mg: lactose anhydrous (132.8 mg), colloidal silicon dioxide (0.2 mg), sodium starch glycolate (7.5 mg), tartaric acid (1.5 mg), and stearic acid (3 mg). TEMODAR 20 mg: lactose anhydrous (182.2 mg), colloidal silicon dioxide (0.2 mg), sodium starch glycolate (11 mg), tartaric acid (2.2 mg), and stearic acid (4.4 mg). TEMODAR 100 mg: lactose anhydrous (175.7 mg), colloidal silicon dioxide (0.3 mg), sodium starch glycolate (15 mg), tartaric acid (3 mg), and stearic acid (6 mg).
TEMODAR 140 mg: lactose anhydrous (246 mg), colloidal silicon dioxide (0.4 mg), sodium starch glycolate (21 mg), tartaric acid (4.2 mg), and stearic acid (8.4 mg). TEMODAR 180 mg: lactose anhydrous (316.3 mg), colloidal silicon dioxide (0.5 mg), sodium starch glycolate (27 mg), tartaric acid (5.4 mg), and stearic acid (10.8 mg). TEMODAR 250 mg: lactose anhydrous (154.3 mg), colloidal silicon dioxide (0.7 mg), sodium starch glycolate (22.5 mg), tartaric acid (9 mg), and stearic acid (13.5 mg).
The body of the capsules is made of gelatin and is opaque white. The cap is also made of gelatin, and the colors vary based on the dosage strength. The capsule body and cap are imprinted with pharmaceutical branding ink, which contains shellac, dehydrated alcohol, isopropyl alcohol, butyl alcohol, propylene glycol, purified water, strong ammonia solution, potassium hydroxide, and ferric oxide.
TEMODAR 5 mg: The green cap contains gelatin, titanium dioxide, iron oxide yellow, sodium lauryl sulfate, and FD&C Blue #2. TEMODAR 20 mg: The yellow cap contains gelatin, sodium lauryl sulfate, and iron oxide yellow. TEMODAR 100 mg: The pink cap contains gelatin, titanium dioxide, sodium lauryl sulfate, and iron oxide red.
TEMODAR 140 mg: The blue cap contains gelatin, sodium lauryl sulfate, and FD&C Blue #2. TEMODAR 180 mg: The orange cap contains gelatin, iron oxide red, iron oxide yellow, titanium dioxide, and sodium lauryl sulfate. TEMODAR 250 mg: The white cap contains gelatin, titanium dioxide, and sodium lauryl sulfate.
TEMODAR for injection TEMODAR (temozolomide) for injection is for intravenous use. Each single-dose vial contains 100 mg of sterile and pyrogen-free lyophilized powder. The inactive ingredients are: mannitol (600 mg), L-threonine (160 mg), polysorbate 80 (120 mg), sodium citrate dihydrate (235 mg), and hydrochloric acid (160 mg).
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Myelosuppression Inform patients that TEMODAR can cause low blood cell counts and the need for frequent monitoring of blood cell counts. Advise patients to contact their healthcare provider immediately for bleeding, fever, or other signs of infection [see Warnings and Precautions (5.1) ].
Hepatotoxicity Advise patients of the increased risk of hepatotoxicity and to contact their healthcare provider immediately for signs or symptoms of hepatotoxicity. Inform patients that they will have periodic liver enzyme tests during treatment and following the last dose of TEMODAR [see Warnings and Precautions (5.2) ] . Pneumocystis Pneumonia Advise patients of the increased risk of Pneumocystis pneumonia and to contact their healthcare provider immediately for new or worsening pulmonary symptoms.
Inform patients that prophylaxis for Pneumocystis pneumonia may be needed [see Dosage and Administration (2.1) , Warnings and Precautions (5.3) ] . Secondary Malignancies Advise patients of the increased risk of myelodysplastic syndrome and secondary malignancies [see Warnings and Precautions (5.4)]. Exposure to Opened Capsules Advise patient to not open, chew, or dissolve the capsules.
If capsules are accidentally opened or damaged, advise patients to take rigorous precautions with capsule contents to avoid inhalation or contact with the skin or mucous membranes [see Warnings and Precautions (5.6) ] . In case of powder contact, wash the affected area with water immediately [see Dosage and Administration (2.4) ] . Embryo-Fetal Toxicity Advise pregnant women and females of reproductive potential of the potential risk to a fetus.
Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.5) , Use in Specific Populations (8.1) ] . Advise females of reproductive potential to use effective contraception during treatment with TEMODAR and for 6 months after the last dose [see Use in Specific Populations (8.3) ] . Advise male patients with pregnant partners or female partners of reproductive potential to use condoms during treatment with TEMODAR and for 3 months after the last dose [see Use in Specific Populations (8.3) , Nonclinical Toxicology (13.1) ] .
Advise male patients not to donate semen during treatment with TEMODAR and for 3 months after the last dose [see Use in Specific Populations (8.3) , Nonclinical Toxicology (13.1) ] . Lactation Advise women not to breastfeed during treatment with TEMODAR and for 1 week after the last dose [see Use in Specific Populations (8.2) ] . Infertility Advise males of reproductive potential that TEMODAR may impair fertility [see Use in Specific Populations (8.3) , Nonclinical Toxicology (13.1) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following a single oral dose of 150 mg/m 2 , the mean C max is 7.5 mcg/mL for temozolomide and 282 ng/mL for MTIC. The mean AUC is 23.4 mcg∙hr/mL for temozolomide and 864 ng∙hr/mL for MTIC. Following a single 90-minute intravenous infusion of 150 mg/m 2 , the mean C max is 7.3 mcg/mL for temozolomide and 276 ng/mL for MTIC.
The mean AUC is 24.6 mcg∙hr/mL for temozolomide and 891 ng∙hr/mL for MTIC. Temozolomide exhibits linear kinetics over the therapeutic dosing range of 75 mg/m 2 /day to 250 mg/m 2 /day. Absorption The median T max is 1 hour.
Effect of Food The mean temozolomide C max and AUC decreased by 32% and 9%, respectively, and median T max increased by 2-fold (from 1 to 2.25 hours) when TEMODAR capsules were administered after a modified high-fat breakfast (587 calories comprised of 1 fried egg, 2 strips of bacon, 2 slices of toast, 2 pats of butter, and 8 oz whole milk). Distribution Temozolomide has a mean (CV%) apparent volume of distribution of
0.4L/kg (13%). The mean percent bound of drug-related total radioactivity is 15%. Elimination Clearance of temozolomide is approximately
5.5L/hr/m 2 and the mean elimination half-life is 1.8 hours. Metabolism Temozolomide is spontaneously hydrolyzed at physiologic pH to the active species, MTIC and to temozolomide acid metabolite. MTIC is further hydrolyzed to 5-amino-imidazole-4-carboxamide (AIC), which is known to be an intermediate in purine and nucleic acid biosynthesis, and to methylhydrazine, which is believed to be the active alkylating species.
Cytochrome P450 enzymes play a minor role in the metabolism of temozolomide and MTIC. Relative to the AUC of temozolomide, the exposure to MTIC and AIC is 2.4% and 23%, respectively. Excretion Approximately 38% of the administered temozolomide total radioactive dose is recovered over 7 days: 38% in urine and 0.8% in feces.
The majority of the recovered radioactivity in urine is unchanged temozolomide (6%), AIC (12%), temozolomide acid metabolite (2.3%), and unidentified polar metabolite(s) (17%). Specific Populations No clinically significant differences in the pharmacokinetics of temozolomide were observed based on age (range: 19 to 78 years), gender, smoking status (smoker vs. non-smoker), creatinine clearance (CLcr) of 36 to 130 mL/min/m 2 , or mild to moderate hepatic impairment (Child Pugh class A and B). The pharmacokinetics of temozolomide has not been studied in patients with CLcr <36 mL/min/m 2 , end-stage renal disease on dialysis, or severe hepatic impairment (Child-Pugh class C).
Drug Interaction Studies Clinical Studies and Model-Informed Approaches No clinically significant differences in the pharmacokinetics of temozolomide or MTIC were observed when co-administered with ranitidine. No clinically significant differences in the clearance of temozolomide or MTIC were predicted when co-administered with the following drugs: valproic acid, dexamethasone, prochlorperazine, phenytoin, carbamazepine, ondansetron, histamine-2-receptor antagonists, or phenobarbital.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Temozolomide exposure-response relationships and the time course of pharmacodynamic response are unknown.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Newly Diagnosed Glioblastoma The efficacy of TEMODAR was evaluated in MK-7365-051 (NCT00006353), a randomized (1:1), multicenter, open-label trial. Eligible patients were required to have newly diagnosed glioblastoma. Patients were randomized to receive either radiation therapy alone or concomitant TEMODAR 75 mg/m 2 once daily starting the first day of radiation therapy and continuing until the last day of radiation therapy for 42 days (with a maximum of 49 days), followed by TEMODAR 150 mg/m 2 or 200 mg/m 2 once daily on Days 1 to 5 of each 28-day cycle, starting 4 weeks after the end of radiation therapy and continuing for 6 cycles.
In both arms, focal radiation therapy was delivered as 60 Gy/30 fractions and included radiation to the tumor bed or resection site with a 2- to 3-cm margin. PCP prophylaxis was required during the concomitant phase regardless of lymphocyte count and continued until recovery of lymphocyte count to Grade 1 or less. The major efficacy outcome measure was overall survival.
A total of 573 patients were randomized, 287 to TEMODAR and radiation therapy and 286 to radiation therapy alone. At the time of disease progression, TEMODAR was administered as salvage therapy in 161 patients of the 282 (57%) in the radiation therapy alone arm and 62 patients of the 277 (22%) in the TEMODAR and radiation therapy arm. The addition of concomitant and maintenance TEMODAR to radiation therapy for the treatment of patients with newly diagnosed glioblastoma showed a statistically significant improvement in overall survival compared to radiotherapy alone ( Figure 1 ).
The hazard ratio (HR) for overall survival was 0.63 (95% CI: 0.52, 0.75) with a log-rank P <0.0001 in favor of the TEMODAR arm. The median overall survival was 14.6 months in the TEMODAR arm and 12.1 months for radiation therapy alone arm. FIGURE 1: Kaplan-Meier Curves for Overall Survival (ITT Population) in Patients with Newly Diagnosed Glioblastoma in MK-7365-051 Figure 1
14.2Anaplastic Astrocytoma Newly Diagnosed Anaplastic Astrocytoma The efficacy of TEMODAR for the adjuvant treatment of newly diagnosed anaplastic astrocytoma was derived from studies of TEMODAR in the published literature. TEMODAR was evaluated in CATNON (NCT00626990), a randomized, open-label, multicenter trial, where the major efficacy outcome measure was overall survival. Refractory Anaplastic Astrocytoma The efficacy of TEMODAR was evaluated in Study MK-7365-006, a single-arm, multicenter trial.
Eligible patients had anaplastic astrocytoma at first relapse and a baseline Karnofsky performance status (KPS) of 70 or greater. Patients had previously received radiation therapy and may also have previously received a nitrosourea with or without other chemotherapy. Fifty-four patients had disease progression on prior therapy with both a nitrosourea and procarbazine and their malignancy was considered refractory to chemotherapy (refractory anaplastic astrocytoma population).
TEMODAR capsules were given on Days 1 to 5 of each 28-day cycle at a starting dose of 150 mg/m 2 /day. If ANC was ≥1.5 × 10 9 /L and platelet count was ≥100 × 10 9 /L at the nadir and on Day 1 of the next cycle, the TEMODAR dose was increased to 200 mg/m 2 /day. The major efficacy outcome measure was progression-free survival at 6 months and the additional efficacy outcome measures were overall survival and overall response rate.
In the refractory anaplastic astrocytoma population (n=54), the median age was 42 years (range: 19 to 76); 65% were male; and 72% had a KPS of >80. Sixty-three percent of patients had surgery other than a biopsy at the time of initial diagnosis. Of those patients undergoing resection, 73% underwent a subtotal resection and 27% underwent a gross total resection.
Eighteen percent of patients had surgery at the time of first relapse. The median time from initial diagnosis to first relapse was 13.8 months (range: 4.2 months to 6.3 years). In the refractory anaplastic as… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Temozolomide is carcinogenic in rats at doses less than the maximum recommended human dose. Temozolomide induced mammary carcinomas in both males and females at doses 0.13 to 0.63 times the maximum human dose (25-125 mg/m 2 ) when administered orally on 5 consecutive days every 28 days for 6 cycles. Temozolomide also induced fibrosarcomas of the heart, eye, seminal vesicles, salivary glands, abdominal cavity, uterus, and prostate, carcinomas of the seminal vesicles, schwannomas of the heart, optic nerve, and harderian gland, and adenomas of the skin, lung, pituitary, and thyroid at doses 0.5 times the maximum daily dose.
Mammary tumors were also induced following 3 cycles of temozolomide at the maximum recommended daily dose. Temozolomide is a mutagen and a clastogen. In a reverse bacterial mutagenesis assay (Ames assay), temozolomide increased revertant frequency in the absence and presence of metabolic activation.
Temozolomide was clastogenic in human lymphocytes in the presence and absence of metabolic activation. Temozolomide impairs male fertility. Temozolomide caused syncytial cells/immature sperm formation at doses of 50 and 125 mg/m 2 (0.25 and 0.63 times the human dose of 200 mg/m 2 ) in rats and dogs, respectively, and testicular atrophy in dogs at 125 mg/m 2 .
13.2Animal Toxicology and/or Pharmacology Toxicology studies in rats and dogs identified a low incidence of hemorrhage, degeneration, and necrosis of the retina at temozolomide doses equal to or greater than 125 mg/m 2 (0.63 times the human dose of 200 mg/m 2 ). These changes were most commonly seen at doses where mortality was observed.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Temozolomide is carcinogenic in rats at doses less than the maximum recommended human dose. Temozolomide induced mammary carcinomas in both males and females at doses 0.13 to 0.63 times the maximum human dose (25-125 mg/m 2 ) when administered orally on 5 consecutive days every 28 days for 6 cycles. Temozolomide also induced fibrosarcomas of the heart, eye, seminal vesicles, salivary glands, abdominal cavity, uterus, and prostate, carcinomas of the seminal vesicles, schwannomas of the heart, optic nerve, and harderian gland, and adenomas of the skin, lung, pituitary, and thyroid at doses 0.5 times the maximum daily dose.
Mammary tumors were also induced following 3 cycles of temozolomide at the maximum recommended daily dose. Temozolomide is a mutagen and a clastogen. In a reverse bacterial mutagenesis assay (Ames assay), temozolomide increased revertant frequency in the absence and presence of metabolic activation.
Temozolomide was clastogenic in human lymphocytes in the presence and absence of metabolic activation. Temozolomide impairs male fertility. Temozolomide caused syncytial cells/immature sperm formation at doses of 50 and 125 mg/m 2 (0.25 and 0.63 times the human dose of 200 mg/m 2 ) in rats and dogs, respectively, and testicular atrophy in dogs at 125 mg/m 2 .
📚 References ▾
15 REFERENCES “OSHA Hazardous Drugs.” OSHA. http://www.osha.gov/hazardous-drugs
📄 Patient Package Insert ▾
Patient Information TEMODAR® (tem-o-dar) (temozolomide) capsules TEMODAR® (tem-o-dar) (temozolomide) for injection This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: 9/2023 What is TEMODAR?
TEMODAR is a prescription medicine used to treat adults with certain brain cancer tumors. It is not known if TEMODAR is safe and effective in children. Do not take TEMODAR if you: have had an allergic reaction to temozolomide or any of the other ingredients in TEMODAR.
See the end of this leaflet for a list of ingredients in TEMODAR. Symptoms of an allergic reaction with TEMODAR may include: a red itchy rash, or a severe allergic reaction, such as trouble breathing, swelling of the face, throat, or tongue, or severe skin reaction. If you are not sure, ask your healthcare provider. have had an allergic reaction to dacarbazine (DTIC), another cancer medicine.
Before taking or receiving TEMODAR, tell your healthcare provider about all of your medical conditions, including if you: have kidney problems have liver problems are pregnant or plan to become pregnant. TEMODAR can harm your unborn baby and cause birth defects. Females who can become pregnant: You should not become pregnant during treatment with TEMODAR.
You should use an effective form of birth control (contraception) during treatment and for 6 months after your last dose of TEMODAR. Your healthcare provider should do a pregnancy test to make sure that you are not pregnant before you start taking TEMODAR. Tell your healthcare provider right away if you become pregnant or think you may be pregnant during treatment with TEMODAR.
Males with a female partner who is pregnant or who can become pregnant: Use a condom for birth control (contraception) during treatment and for 3 months after taking your last dose of TEMODAR. Do not donate semen during treatment and for 3 months after your last dose of TEMODAR. are breastfeeding or plan to breastfeed. It is not known if TEMODAR passes into your breast milk.
Do not breastfeed during treatment and for 1 week after your last dose of TEMODAR. Tell your doctor about all the medicines you take, including prescription and non-prescription medicines, vitamins, and herbal supplements. Know the medicines you take.
Keep a list of them and show it to your healthcare provider and pharmacist when you get a new medicine. How should I take TEMODAR? TEMODAR may be taken 2 different ways: you may take TEMODAR by mouth as a capsule, or you may receive TEMODAR as an intravenous (IV) injection into your vein.
Your healthcare provider will decide the best way for you to take TEMODAR. If your healthcare provider prescribes TEMODAR capsules for you, take the capsules exactly as prescribed. There are 2 common dosing schedules for taking or receiving TEMODAR depending on the type of brain cancer tumor that you have.
People with certain brain cancer tumors take or receive TEMODAR: 1 time each day for 42 to 49 days in a row, along with receiving radiation treatment. This is 1 cycle of treatment. After this, your healthcare provider may prescribe 6 more cycles of TEMODAR as “maintenance” treatment.
For each of these cycles, you take or receive TEMODAR 1 time each day for 5 days in a row and then you stop taking it for the next 23 days. This is a 28-day maintenance treatment cycle. People with certain other brain cancer tumors take or receive TEMODAR: 1 time each day for 5 days in a row only, and then stop taking it for the next 23 days.
This is 1 cycle of treatment (28 days). Your healthcare provider will watch your progress on TEMODAR and decide how long you should take it. If your healthcare provider prescribes a treatment regimen that is different from the information in this leaflet, make sure you follow the instructions given to you by your healthcare provider.
Your healthcare provider may change your dose of TEMODAR, or tell you to stop TEMODAR for a short period of time or permanently if you have certain side effects. Your h… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 5 mg Capsule Sachet Carton NDC 0085-3004-03 5 mg per capsule Temodar ® [temozolomide] Capsules For Oral Administration WARNING: Hazardous Drug Rx only THIS PACKAGE CONTAINS 5 INDIVIDUAL SACHETS Each Individual Sachet Contains One Capsule Each PRINCIPAL DISPLAY PANEL - 5 mg Capsule Sachet Carton
PRINCIPAL DISPLAY PANEL - 20 mg Capsule Sachet Carton NDC 0085-1519-03 20 mg per capsule Temodar ® [temozolomide] Capsules For Oral Administration WARNING: Hazardous Drug Rx only THIS PACKAGE CONTAINS 5 INDIVIDUAL SACHETS Each Individual Sachet Contains One Capsule Each PRINCIPAL DISPLAY PANEL - 20 mg Capsule Sachet Carton
PRINCIPAL DISPLAY PANEL - 100 mg Capsule Sachet Carton NDC 0085-1366-03 100 mg per capsule Temodar ® [temozolomide] Capsules For Oral Administration WARNING: Hazardous Drug Rx only THIS PACKAGE CONTAINS 5 INDIVIDUAL SACHETS Each Individual Sachet Contains One Capsule Each PRINCIPAL DISPLAY PANEL - 100 mg Capsule Sachet Carton
PRINCIPAL DISPLAY PANEL - 140 mg Capsule Sachet Carton NDC 0085-1425-03 140 mg per capsule Temodar ® [temozolomide] Capsules For Oral Administration WARNING: Hazardous Drug Rx only THIS PACKAGE CONTAINS 5 INDIVIDUAL SACHETS Each Individual Sachet Contains One Capsule Each PRINCIPAL DISPLAY PANEL - 140 mg Capsule Sachet Carton
PRINCIPAL DISPLAY PANEL - 180 mg Capsule Sachet Carton NDC 0085-1430-03 180 mg per capsule Temodar ® [temozolomide] Capsules For Oral Administration WARNING: Hazardous Drug Rx only THIS PACKAGE CONTAINS 5 INDIVIDUAL SACHETS Each Individual Sachet Contains One Capsule Each PRINCIPAL DISPLAY PANEL - 180 mg Capsule Sachet Carton
PRINCIPAL DISPLAY PANEL - 250 mg Capsule Sachet Carton NDC 0085-1417-02 250 mg per capsule Temodar ® [temozolomide] Capsules For Oral Administration WARNING: Hazardous Drug Rx only THIS PACKAGE CONTAINS 5 INDIVIDUAL SACHETS Each Individual Sachet Contains One Capsule Each PRINCIPAL DISPLAY PANEL - 250 mg Capsule Sachet Carton
PRINCIPAL DISPLAY PANEL - 100 mg Vial Carton NDC 0085-1381-01 Temodar ® [temozolomide] for Injection 100 mg / VIAL For Intravenous Infusion after Reconstitution WARNING: Hazardous Drug Single-Dose Vial. Discard unused portion. Rx only Principal Display Panel - 100 mg Vial Carton
Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |