
temozolomide 100 mg Capsule, 5-count — NDC 75834-143-05 (Billing 75834-0143-05)
This is a package of 5 capsules of temozolomide 100 mg Capsule from Nivagen Pharmaceuticals, Inc., marketed since Dec 2021 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
Other active recalls for Temozolomide (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 043012
- GCN: 92913
- GPI-14 (Medi-Span): 21104070000140
- HICL (First Databank): 020355
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 313209
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Alkylating Drug class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Temozolomide is used to treat certain types of brain tumors. Temozolomide is in a class of medications called alkylating agents. It works by slowing or stopping the growth of cancer cells in your body.
Read the full MedlinePlus article ↗- Temozolomide is a chemotherapy used to treat aggressive brain tumors — specifically glioblastoma (a fast-growing brain tumor) and anaplastic astrocytoma. It works by getting into c...
- What exactly is temozolomide treating, and why do I need it?
- Yes, it does matter. Swallow the capsules whole with a full glass of water — never open, crush, or chew them. Try to avoid taking them right after a high-fat meal, because fat can...
- How should I take the capsules — does it matter when I take them or whether I eat first?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Temozolomide — tap one for details:
Temozolomide may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · NONE | No ASP payment limit on file for NONE this quarter. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 75834-0143-05 You're viewing this Main listing | 1 BOTTLE in 1 CARTON / 5 CAPSULE in 1 BOTTLE | 2021-12-07 | — | Active |
| 75834-0143-14 75834-143-14 | 1 CARTON in 1 CARTON / 14 CAPSULE in 1 CARTON | 2021-12-07 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 75834-0143-14?
What NDC number is used to bill for this package of temozolomide 100 mg Capsule?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Temozolomide 100 mg 16729-0050-53 | Accord | 5 capsules | $4.375 | AB | Availability likely | — |
| Temozolomide 100 mg 31722-0413-14 | Camber | 14 capsules | $4.375 | AB | Availability likely | — |
| Temozolomide 100 mg 65162-0803-14 | Amneal | 14 capsules | $4.375 | AB | Availability likely | — |
| Temozolomide 100 mg 67877-0539-07 | Ascend | 5 capsules | $4.375 | AB | Availability likely | — |
| Temozolomide 100 mg 73043-0013-05 | Devatis, | 5 capsules | $4.375 | AB | Availability likely | — |
| Temodar 100 mg 00085-1366-03 | Merck | 5 capsules | — | — | FDA listed | — |
| Temozolomide 100 mg 16571-0818-02 | Rising | 20 capsules | — | AB | FDA listed | — |
| Temozolomide 100 mg 47335-0892-21 | Sun | 14 capsules | — | AB | FDA listed | — |
| Temozolomide 100 mg 72162-2661-02 | Bryant | 5 capsules | — | AB | FDA listed | — |
| temozolomide 100 mgthis 75834-0143-05 | Nivagen | 5 capsules | — | — | FDA listed | — |
| Temozolomide 100 mg 82249-0408-05 | CivicaScript | 5 capsules | — | AB | FDA listed | — |
| Temozolomide 100 mg 70301-2005-01 | OPKO | 5 capsules | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
IMPORTANT DISPENSING INFORMATION For every patient, dispense Temozolomide capsules, USP in a separate vial or in its original package, making sure each container lists the strength per capsule and that patients take the appropriate number of capsules from each package or vial. Please see the dispensing instructions below for more information.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Temozolomide capsules, USP is an alkylating drug indicated for the treatment of adult patients with: • Newly diagnosed glioblastoma concomitantly with radiotherapy and then as maintenance treatment. (1.1) • Refractory anaplastic astrocytoma who have experienced disease progression on a drug regimen containing nitrosourea and procarbazine. (1.2)
1.1Newly Diagnosed Glioblastoma Temozolomide capsules, USP is indicated for the treatment of adult patients with newly diagnosed glioblastoma concomitantly with radiotherapy and then as maintenance treatment.
1.2Refractory Anaplastic Astrocytoma Temozolomide capsules, USP is indicated for the treatment of adult patients with refractory anaplastic astrocytoma who have experienced disease progression on a drug regimen containing nitrosourea and procarbazine.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administer orally. Newly Diagnosed Glioblastoma : 75 mg/m 2 once daily for 42 days concomitant with focal radiotherapy followed by initial maintenance dose of 150 mg/m 2 once daily for Days 1 to 5 of each 28-day cycle for 6 cycles. May increase maintenance dose to 200 mg/ m 2 for cycles 2 – 6 based on toxicity.
( 2.1 ) Provide Pneumocystis pneumonia (PCP) prophylaxis during concomitant phase and continue in patients who develop lymphopenia until resolution to grade 1 or less. ( 2.1 ) Refractory Anaplastic Astrocytoma : Initial dose of 150 mg/m 2 once daily on Days 1 to 5 of each 28-day cycle. ( 2.2 )
2.1Recommended Dosage and Dosage Modifications for Newly Diagnosed Glioblastoma Administer Temozolomide capsules, USP orally once daily for 42 consecutive days during the concomitant phase with focal radiotherapy and then once daily on Days 1 to 5 of each 28-day cycle for 6 cycles during the maintenance phase. Provide Pneumocystis pneumonia (PCP) prophylaxis during the concomitant phase and continue in patients who develop lymphocytopenia until resolution to grade 1 or less [see Warnings and Precautions (5.3) ]. Concomitant Phase The recommended dosage of Temozolomide capsules, USP is 75 mg/m 2 orally once daily for 42 days (up to 49 days) concomitant with focal radiotherapy (60 Gy administered in 30 fractions).
Focal radiotherapy includes the tumor bed or resection site with a 2- to 3-cm margin. Obtain a complete blood count weekly. No dose reductions are recommended during the concomitant phase.
The recommended dosage modifications during the concomitant phase are provided in Table 1 . TABLE 1: Temozolomide Dosage Modifications During Concomitant Phase Adverse Reaction Interruption Discontinuation Absolute Neutrophil Count Withhold Temozolomide if ANC is greater than or equal to 0.5 x 10 9 /L and less than 1.5 x 10 9 /L. Resume Temozolomide when ANC is greater than or equal to 1.5 x 10 9 /L.
Discontinue Temozolomide if platelet count is less than 0.5 x 10 9 /L. Platelet Count Withhold Temozolomide if platelet count is greater than or equal to 10 x 10 9 /L and less than 100 x 10 9 /L. Resume Temozolomide when platelet count is greater than or equal to 100 x 10 9 /L.
Discontinue Temozolomide if platelet count is less than 10 x 10 9 /L. Non-hematological Adverse Reaction (except for alopecia, nausea, vomiting) Withhold Temozolomide if Grade 2 adverse reaction occurs. Resume Temozolomide when resolution to Grade 1 or less.
Discontinue Temozolomide if Grade 3 or 4 adverse reaction occurs. Maintenance Phase Beginning 4 weeks after Concomitant Phase completion, administer Temozolomide capsules, USP orally once daily on Days 1 to 5 of each 28-day cycle for 6 cycles. The recommended dosage of Temozolomide capsules, USP is as follows: Cycle 1: 150 mg/m 2 per day Cycles 2 to 6: May increase to 200 mg/m 2 per day if the following conditions are met before starting cycle 2.
If the dose was not escalated at the onset of Cycle 2, do not increase the dose for Cycles 3 to 6. Nonhematologic toxicity is grade 2 or less (except for alopecia, nausea, and vomiting) ANC is greater than or equal to 1.5 x 10 9 /L and Platelet count is greater than or equal to 100 x 10 9 /L. Obtain a complete blood count on Day 22 and then weekly until the ANC is above 1.5 x 10 9 /L and the platelet count is above 100 x 10 9 /L.
Do not start the next cycle until the ANC and platelet count exceed these levels. The recommended dosage modifications during the maintenance phase are provided in Table 2 . If Temozolomide is withheld, reduce the dose for the next cycle by 50 mg/m 2 per day.
Permanently discontinue Temozolomide in patients who are unable to tolerate a dose of 100 mg/m 2 per day. TABLE 2: Temozolomide Dosage Modifications During Maintenance Treatment Toxicity Interruption and Dose Reduction Discontinuation Absolute Neutrophil Count Withhold Temozolomide if ANC less than 1 x 10 9 /L. When ANC is above 1.5 x 10 9 /L, resume Temozolomide… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules: - 5 mg: white opaque bodies with green opaque caps. The capsule body is imprinted with “5 mg”. The cap is imprinted with “NIV-132.” - 20 mg: white opaque bodies with rich yellow opaque caps.
The capsule body is imprinted with “20 mg”. The cap is imprinted with “NIV-142.” - 100 mg: buff opaque bodies with peach opaque caps. The capsule body is imprinted with “100 mg”.
The cap is imprinted with “NIV-143.” - 140 mg: white opaque bodies with blue opaque caps. The capsule body is imprinted with “140 mg”. The cap is imprinted with “NIV-144.” - 180 mg: white opaque bodies with red opaque caps.
The capsule body is imprinted with “180 mg”. The cap is imprinted with “NIV-145.” - 250 mg: white opaque bodies with white opaque caps. The capsule body is imprinted with “250 mg”.
The cap is imprinted with “NIV-146.” • Capsules : 5 mg, 20 mg, 100 mg, 140 mg, 180 mg, and 250 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Temozolomide capsules, USP is contraindicated in patients with a history of hypersensitivity reactions to: temozolomide or any other ingredients in Temozolomide capsules, USP; and dacarbazine, since both temozolomide and dacarbazine are metabolized to the same active metabolite 5-(3-methyltriazen-1-yl)-imidazole-4-carboxamide. Reactions to Temozolomide have included anaphylaxis [see Adverse Reactions (6.2) ]. History of hypersensitivity to temozolomide or any other ingredients in Temozolomide capsules, USP and dacarbazine.
( 4.1 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Myelosuppression : Monitor absolute neutrophil count (ANC) and platelet count prior to each cycle and during treatment. Geriatric patients and women have a higher risk of developing myelosuppression. ( 5.1 ) Myelodysplastic Syndrome and Secondary Malignancies , including myeloid leukemia, have been observed.
( 5.2 ) Pneumocystis P neumonia (PCP): Closely monitor all patients, particularly those receiving steroids, for the development of lymphopenia and PCP. ( 5.3 ) Hepatotoxicity: Fatal and severe hepatotoxicity have been reported. Perform liver tests at baseline, midway through the first cycle, prior to each subsequent cycle, and approximately 2 to 4 weeks after the last dose of Temozolomide capsules, USP.
( 5.4 ) Embryo-Fetal Toxicity : Can cause fetal harm. Advise females of reproductive potential of the potential risk to a fetus and to use effective contraception. Advise male patients with pregnant partners or female partners of reproductive potential to use condoms.
( 5.5 , 8.1 , 8.3 )
5.1Myelosuppression Myelosuppression, including pancytopenia, leukopenia and anemia, some with fatal outcomes, have occurred with Temozolomide [see Adverse Reactions ( 6.1 , 6.2 )]. Geriatric patients and women have been shown in clinical trials to have a higher risk of developing myelosuppression. Prior to dosing, patients must have an ANC of 1.5 x 10 9 /L or greater and a platelet count of 100 x 10 9 /L or greater.
For the concomitant phase with radiotherapy, obtain a complete blood count prior to initiation of treatment and weekly during treatment [see Dosage and Administration (2.1) ]. For the 28-day treatment cycles, obtain a complete blood count prior to treatment on Day 1 and on Day 22 of each cycle. Perform complete blood counts weekly until recovery if the ANC falls below 1.5 x 10 9 /L and the platelet count falls below 100 x 10 9 /L [see Dosage and Administration ( 2.1 , 2.2 )].
5.2Myelodysplastic Syndrome and Secondary Malignancies Cases of myelodysplastic syndrome and secondary malignancies, including myeloid leukemia, have been observed following Temozolomide administration.
5.3Pneumocystis Pneumonia Pneumocystis pneumonia (PCP) can occur in patients receiving Temozolomide. The risk of PCP is increased in patients receiving steroids or with longer treatment regimens. For patients with newly diagnosed glioblastoma, provide PCP prophylaxis for all patients during the concomitant phase.
Continue in patients who experience lymphopenia until resolution to Grade 1 or less [see Dosage and Administration (2.1) ]. Monitor all patients receiving Temozolomide capsules, USP for the development of lymphopenia and PCP.
5.4Hepatotoxicity Fatal and severe hepatotoxicity have been reported in patients receiving Temozolomide. Perform liver tests at baseline, midway through the first cycle, prior to each subsequent cycle, and approximately two to four weeks after the last dose of Temozolomide.
5.5Embryo-Fetal Toxicity Based on findings from animal studies and its mechanism of action, Temozolomide can cause fetal harm when administered to a pregnant woman. Adverse developmental outcomes have been reported in both pregnant patients and pregnant partners of male patients. Oral administration of temozolomide to rats and rabbits during the period of organogenesis resulted in embryolethality and polymalformations at doses less than the maximum human dose based on body surface area.
Advise pregnant women of the potential risk to the fetus. Advise females of reproductive potential to use effective contraception during treatment with Temozolomide and for at least 6 months after the final dose. Because of potential risk of genotoxic effects on sperm, advise male patients with female partners of reproductive potential to use condoms during treatment with Temozolomide and for at least 3 months after the final dose.
Advise male patients not to donate semen during treatment with Temozolomide and for at least 3 months after the f… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Myelosuppression [see Warnings and Precautions (5.1) ]. Myelodysplastic Syndrome and Secondary Malignancies [see Warnings and Precautions (5.2) ]. Pneumocystis Pneumonia [see Warnings and Precautions (5.3) ].
Hepatotoxicity [see Warnings and Precautions (5.4) ]. The most common adverse reactions (≥20% incidence) are: alopecia, fatigue, nausea, vomiting, headache, constipation, anorexia, and convulsions. ( 6.1 ) The most common Grade 3 to 4 hematologic laboratory abnormalities (≥10% incidence) in patients with anaplastic astrocytoma are: decreased lymphocytes, decreased platelets, decreased neutrophils, and decreased leukocytes.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Nivagen Pharmaceutical, Inc., at 1-877-977-0687 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Newly Diagnosed Glioblastoma The safety of Temozolomide was evaluated in Study MK-7365-051 [see Clinical Studies (14.1) ]. Forty-nine percent (49%) of patients treated with Temozolomide reported one or more severe or life-threatening reactions, most commonly fatigue (13%), convulsions (6%), headache (5%), and thrombocytopenia (5%).
The most common adverse reactions (≥20%) across the cumulative Temozolomide experience were alopecia, fatigue, nausea, and vomiting. Table 3 s ummarizes the adverse reactions in Newly Diagnosed Glioblastoma Trial. Overall, the pattern of reactions during the maintenance phase was consistent with the known safety profile of Temozolomide.
TABLE 3 : Adverse Reactions (≥5%) in Patients Receiving Temozolomide in Newly Diagnosed Glioblastoma Trial Adverse Reactions Concomitant Phase Maintenance Phase Radiation Therapy and Temozolomide N=288 One patient who was randomized to radiation therapy only arm received radiation therapy and Temozolomide. Radiation Therapy Alone N=285 Temozolomide N=224 All Grades (%) Grade ≥3 (%) All Grades (%) Grade ≥3 (%) All Grades (%) Grade ≥3 (%) Skin and Subcutaneous Tissue Alopecia 69 63 55 Rash 19 1 15 13 1 Dry Skin 2 2 5 <1 Pruritus 4 1 5 Erythema 5 5 1 General Fatigue 54 7 49 5 61 9 Anorexia 19 1 9 <1 27 1 Headache 19 2 17 4 23 4 Weakness 3 2 3 1 7 2 Dizziness 4 1 4 5 Gastrointestinal System Nausea 36 1 16 <1 49 1 Vomiting 20 <1 6 <1 29 2 Constipation 18 1 6 22 Diarrhea 6 3 10 1 Stomatitis 7 5 <1 9 1 Abdominal Pain 2 <1 1 5 <1 Eye Vision Blurred 9 1 9 1 8 Injury Radiation Injury NOS 7 4 <1 2 Central and Peripheral Nervous System Convulsions 6 3 7 3 11 3 Memory Impairment 3 <1 4 <1 7 1 Confusion 4 1 4 2 5 2 Special Senses Other Taste Perversion 6 2 5 Respiratory System Coughing 5 1 1 8 <1 Dyspnea 4 2 3 1 5 <1 Psychiatric Insomnia 5 3 <1 4 Immune System Allergic Reaction 5 2 <1 3 Platelet, Bleeding and Clotting Thrombocytopenia 4 3 1 8 4 Musculoskeletal System Arthralgia 2 <1 1 6 NOS=not otherwise specified.
Not e : Grade 5 (fatal) adverse reactions are included in the Grade ≥3 column. When laboratory abnormalities and adverse reactions were combined, Grade 3 or Grade 4 neutrophil abnormalities including neutropenic reactions were observed in 8% of patients, and Grade 3 or Grade 4 platelet abnormalities including thrombocytopenic reactions, were observed in 14% of patients. Refractory Anaplastic Astrocytoma The safety of Temozolomide was evaluated in Study MK-7365-006 [see Clinical Studies (14.2) ].
Myelosuppression (thrombocytopenia and neutropenia) was the dose-limiting adverse reaction. It usually occurred within the first few cycles of therapy and was not cumulative. Myelosuppression occurred late in the treatment cycle and returned to normal, on average, within 14 days of nadir counts.
The m… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to brestfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on its mechanism of action [see Clinical Pharmacology (12.1) ] and findings from animal studies, Temozolomide can cause fetal harm when administered to a pregnant woman. Available postmarketing reports describe cases of spontaneous abortions and congenital malformations, including polymalformations with central nervous system, facial, cardiac, skeletal, and genitourinary system anomalies with exposure to Temozolomide during pregnancy. These cases report similar adverse developmental outcomes to those observed in animal studies.
Administration of Temozolomide to rats and rabbits during the period of organogenesis caused numerous external, internal, and skeletal malformations at doses less than the maximum human dose based on body surface area (see Data). Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Five consecutive days of oral administration of temozolomide at doses of 75 and 150 mg/m 2 (0.38 and 0.75 times the human dose of 200 mg/m 2 ) in rats and rabbits, respectively, during the period of organogenesis (Gestation Days 8-12) caused numerous malformations of the external and internal organs and skeleton in both species. In rabbits, temozolomide at the 150 mg/m 2 dose (0.75 times the human dose of 200 mg/m 2 ) caused embryolethality as indicated by increased resorptions.
8.2Lactation There are no data on the presence of Temozolomide or its metabolites in human milk, the effects on a breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions, including myelosuppression from temozolomide in the breastfed children, advise women not to breastfeed during treatment with Temozolomide and for at least 1 week after the final dose.
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to initiating Temozolomide [see Use in Specific Populations (8.1) ]. Contraception Females Temozolomide can cause embryo-fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ]. Advise females of reproductive potential to use effective contraception during treatment with Temozolomide and for at least 6 months after the last dose.
Males Because of the potential for embryofetal toxicity and genotoxic effects on sperm cells, advise male patients with pregnant partners or female partners of reproductive potential to use condoms during treatment with Temozolomide and for at least 3 months after the final dose [see Use in Specific Populations (8.1) , Nonclinical Toxicology (13.1) ]. Advise male patients not to donate semen during treatment with Temozolomide and for at least 3 months after the final dose. Infertility Temozolomide may impair male fertility [see Nonclinical Toxicology (13.1) ] .
Limited data from male patients show changes in sperm parameters during treatment with Temozolomide; however, no information is available on the duration or reversibility of these changes.
8.4Pediatric Use Safety and effectiveness of Temozolomide have not been established in pediatric patients. Safety and effectiveness of Temozolomide capsules, USP were assessed, but not established, in 2 open-label studies in pediatric patients aged 3 to18 years. In one study, 29 patients with recurrent brain stem glioma and 34 patients with recurrent high-grade astrocytoma were enrolled.
In a second study conducted by the Children’s Oncology Group (COG), 122 patients were enrolled, including patients with medulloblastoma/PNET (29), high grade astrocytoma (23), low grade astrocytoma (22), brain stem glioma (16), ependymoma (14), other CNS tumors (9), and non-CNS tumors (9). The adverse reaction profile in pediatric pati… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on its mechanism of action [see Clinical Pharmacology (12.1) ] and findings from animal studies, Temozolomide can cause fetal harm when administered to a pregnant woman. Available postmarketing reports describe cases of spontaneous abortions and congenital malformations, including polymalformations with central nervous system, facial, cardiac, skeletal, and genitourinary system anomalies with exposure to Temozolomide during pregnancy. These cases report similar adverse developmental outcomes to those observed in animal studies.
Administration of Temozolomide to rats and rabbits during the period of organogenesis caused numerous external, internal, and skeletal malformations at doses less than the maximum human dose based on body surface area (see Data). Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Five consecutive days of oral administration of temozolomide at doses of 75 and 150 mg/m 2 (0.38 and 0.75 times the human dose of 200 mg/m 2 ) in rats and rabbits, respectively, during the period of organogenesis (Gestation Days 8-12) caused numerous malformations of the external and internal organs and skeleton in both species. In rabbits, temozolomide at the 150 mg/m 2 dose (0.75 times the human dose of 200 mg/m 2 ) caused embryolethality as indicated by increased resorptions.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of Temozolomide have not been established in pediatric patients. Safety and effectiveness of Temozolomide capsules, USP were assessed, but not established, in 2 open-label studies in pediatric patients aged 3 to18 years. In one study, 29 patients with recurrent brain stem glioma and 34 patients with recurrent high-grade astrocytoma were enrolled.
In a second study conducted by the Children’s Oncology Group (COG), 122 patients were enrolled, including patients with medulloblastoma/PNET (29), high grade astrocytoma (23), low grade astrocytoma (22), brain stem glioma (16), ependymoma (14), other CNS tumors (9), and non-CNS tumors (9). The adverse reaction profile in pediatric patients was similar to adults.
🧓 Geriatric Use ▾
8.5Geriatric Use In the Newly Diagnosed Glioblastoma trial, Study MK-7365-051, 15% of patients were 65 years and older. This study did not include sufficient numbers of patients aged 65 years and older to determine differences in effectiveness from younger patients. No overall differences in safety were observed between patients ≥65 years and younger patients.
In the Refractory Anaplastic Astrocytoma trial, Study MK-7365-0006, 4% of patients were 70 years and older. This study did not include sufficient numbers of patients aged 70 years and older to determine differences in effectiveness from younger patients. Patients 70 years and older had a higher incidence of Grade 4 neutropenia (25%) and Grade 4 thrombocytopenia (20%) in the first cycle of therapy than patients less than 70 years of age [see Warnings and Precautions (5.1) , Adverse Reactions (6.1) ].
🆘 Overdosage ▾
10 OVERDOSAGE Dose-limiting toxicity was myelosuppression and was reported with any dose but is expected to be more severe at higher doses. An overdose of 2000 mg per day for 5 days was taken by one patient and the adverse reactions reported were pancytopenia, pyrexia, multi-organ failure, and death. There are reports of patients who have taken more than 5 days of treatment (up to 64 days), with adverse reactions reported including myelosuppression, which in some cases was severe and prolonged, and infections and resulted in death.
In the event of an overdose, monitor complete blood count and provide supportive measures as necessary.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Temozolomide is not directly active but undergoes rapid nonenzymatic conversion at physiologic pH to the reactive compound 5-(3-methyltriazen-1-yl)-imidazole-4-carboxamide (MTIC). The cytotoxicity of MTIC is thought to be primarily due to alkylation of DNA. Alkylation (methylation) occurs mainly at the O 6 and N 7 positions of guanine.
12.3Pharmacokinetics Following a single oral dose of 150 mg/m 2 , the mean C max value for temozolomide was 7.5 mcg/mL and for MTIC was 282 ng/mL. The mean AUC value for temozolomide was 23.4 mcg·hr/mL and for MTIC was 864 ng·hr/mL. Temozolomide exhibits linear kinetics over the therapeutic dosing range of 75 mg/m 2 /day to 250 mg/m 2 /day.
Absorption The median T max is 1 hour. Effect of Food The mean C max and AUC decreased by 32% and 9%, respectively, and median T max increased by 2-fold (from 1-2.25 hours) when Temozolomide capsules, USP were administered after a modified high-fat breakfast (587 calories comprised of 1 fried egg, 2 strips of bacon, 2 slices of toast, 2 pats of butter, and 8 oz whole milk). Distribution Temozolomide has a mean apparent volume of distribution of
0.4L/kg (%CV=13%). The mean percent bound of drug-related total radioactivity is 15%. Elimination Clearance of temozolomide is about
5.5L/hr/m 2 and the mean elimination half-life is 1.8 hours. Metabolism Temozolomide is spontaneously hydrolyzed at physiologic pH to the active species, MTIC and to temozolomide acid metabolite. MTIC is further hydrolyzed to 5-amino-imidazole-4-carboxamide (AIC), which is known to be an intermediate in purine and nucleic acid biosynthesis, and to methylhydrazine, which is believed to be the active alkylating species.
Cytochrome P450 enzymes play only a minor role in the metabolism of temozolomide and MTIC. Relative to the AUC of temozolomide, the exposure to MTIC and AIC is 2.4% and 23%, respectively. Excretion About 38% of the administered temozolomide total radioactive dose is recovered over 7 days: 38% in urine and 0.8% in feces.
The majority of the recovery of radioactivity in urine is unchanged temozolomide (6%), AIC (12%), temozolomide acid metabolite (2.3%), and unidentified polar metabolite(s) (17%). Specific Populations No clinically meaningful differences in the pharmacokinetics of temozolomide were observed based on age (range: 19-78 years), gender, smoking status (smoker vs. non-smoker), creatinine clearance (CLcr) of 36 to 130 mL/min/m 2 , or mild to moderate hepatic impairment (Child Pugh class A and B). The pharmacokinetics of temozolomide has not been studied in patients with CLcr < 36 mL/min/m 2 , end-stage renal disease on dialysis, or severe hepatic impairment (Child-Pugh class C).
Drug Interaction Studies Effect of Other Drugs on Temozolomide Pharmacokinetics In a multiple-dose study, administration of Temozolomide capsules, USP with ranitidine did not change the C max or AUC values for temozolomide or MTIC. A population analysis indicated that administration of valproic acid decreases the clearance of temozolomide by about 5%. A population analysis did not demonstrate any influence of coadministered dexamethasone, prochlorperazine, phenytoin, carbamazepine, ondansetron, histamine-2-receptor antagonists, or phenobarbital on the clearance of orally administered Temozolomide capsules, USP.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Temozolomide is not directly active but undergoes rapid nonenzymatic conversion at physiologic pH to the reactive compound 5-(3-methyltriazen-1-yl)-imidazole-4-carboxamide (MTIC). The cytotoxicity of MTIC is thought to be primarily due to alkylation of DNA. Alkylation (methylation) occurs mainly at the O 6 and N 7 positions of guanine.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Temozolomide is a cytotoxic drug. Follow applicable special handling and disposal procedures. 1 Temozolomide capsules, USP Temozolomide capsules, USP are supplied in HDPE bottle with child-resistant Polypropylene closure containing the following capsule strengths: 5 mg : white opaque bodies with green opaque caps.
The capsule body is imprinted with “5 mg”. The cap is imprinted with “NIV-132”. They are supplied as follows: 5-count – NDC 75834-132-05 14-count – NDC 75834-132-14 20 mg : white opaque bodies with rich yellow opaque caps.
The capsule body is imprinted with “20 mg”. The cap is imprinted with “NIV-142”. They are supplied as follows: 5-count – NDC 75834-142-05 14-count – NDC 75834-142-14 100 mg : buff opaque bodies with peach opaque caps.
The capsule body is imprinted with “100 mg”. The cap is imprinted with “NIV-143”. They are supplied as follows: 5-count – NDC 75834-143-05 14-count – NDC 75834-143-14 140 mg : white opaque bodies with blue opaque caps.
The capsule body is imprinted with “140 mg”. The cap is imprinted with “NIV-144”. They are supplied as follows: 5-count – NDC 75834-144-05 14-count – NDC 75834-144-14 180 mg : white opaque bodies with red opaque caps.
The capsule body is imprinted with “180 mg”. The cap is imprinted with “NIV-145”. They are supplied as follows: 5-count – NDC 75834-145-05 14-count – NDC 75834-145-14 250 mg : white opaque bodies with white opaque caps.
The capsule body is imprinted with “250 mg”. The cap is imprinted with “NIV-146”. They are supplied as follows: 5-count – NDC 75834-146-05 Store Temozolomide capsules, USP at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Temozolomide is an alkylating drug. The chemical name of temozolomide is 3,4-dihydro-3-methyl-4-oxoimidazo[5,1-d]- as -tetrazine-8-carboxamide. The structural formula of temozolomide is: The material is a white to light tan/light pink powder with a molecular formula of C 6 H 6 N 6 O 2 and a molecular weight of 194.15.
The molecule is stable at acidic pH (<5) and labile at pH >7; hence Temozolomide capsules, USP can be administered orally. The prodrug, temozolomide, is rapidly hydrolyzed to the active 5-(3-methyltriazen-1-yl) imidazole-4-carboxamide (MTIC) at neutral and alkaline pH values, with hydrolysis taking place even faster at alkaline pH. Temozolomide capsules, USP: Temozolomide capsules, USP for oral use contains either 5 mg, 20 mg, 100 mg, 140 mg, 180 mg, or 250 mg of temozolomide.
The inactive ingredients are as follows: Temozolomide capsules, USP, 5 mg: lactose anhydrous (103.52 mg), colloidal silicon dioxide (0.180 mg), sodium starch glycolate (5.650 mg), tartaric acid (2.260 mg), and stearic acid (3.390 mg). Temozolomide capsules, USP, 20 mg: lactose anhydrous (179.0 mg), colloidal silicon dioxide (0.320 mg), sodium starch glycolate (10.350 mg), tartaric acid (4.140 mg), and stearic acid (6.210 mg). Temozolomide capsules, USP, 100 mg: lactose anhydrous (73.0 mg), colloidal silicon dioxide (0.280 mg), sodium starch glycolate (9.00 mg), tartaric acid (3.60 mg), and stearic acid (5.40 mg).
Temozolomide capsules, USP, 140 mg: lactose anhydrous (102.2 mg), colloidal silicon dioxide (0.390 mg), sodium starch glycolate (12.60 mg), tartaric acid (5.040 mg), and stearic acid (7.560 mg). Temozolomide capsules, USP, 180 mg: lactose anhydrous (131.4 mg), colloidal silicon dioxide (0.500 mg), sodium starch glycolate (16.20 mg), tartaric acid (6.480 mg), and stearic acid (9.720 mg). Temozolomide capsules, USP, 250 mg: lactose anhydrous (182.5 mg), colloidal silicon dioxide (0.700 mg), sodium starch glycolate (22.50 mg), tartaric acid (9.000 mg), and stearic acid (13.50 mg).
The body of the capsules for 5 mg, 20 mg, 140 mg, 180 mg and 250 mg strengths is made of gelatin, and titanium dioxide and is white opaque. The body of the capsules for 100 mg strengths is made of gelatin, titanium dioxide and ferric oxide yellow and is buff opaque. The cap is also made of gelatin, and the colors vary based on the dosage strength.
The capsule body and cap are imprinted with pharmaceutical branding ink, which contains shellac, dehydrated alcohol, isopropyl alcohol, butyl alcohol, propylene glycol, purified water, strong ammonia solution, potassium hydroxide, and Black Iron Oxide. Temozolomide capsules, USP, 5 mg: The green opaque cap contains gelatin, titanium dioxide, FDA/E172 yellow iron oxide, and FD&C Blue #2. Temozolomide capsules, USP, 20 mg: The rich yellow opaque cap contains gelatin, titanium dioxide, and FDA/E172 yellow iron oxide.
Temozolomide capsules, USP, 100 mg: The peach opaque cap contains gelatin, titanium dioxide, ferric oxide yellow, and ferric oxide red. Temozolomide capsules, USP, 140 mg: The blue opaque cap contains gelatin, titanium dioxide, and FD&C Blue#2. Temozolomide capsules, USP, 180 mg: The red opaque cap contains gelatin, titanium dioxide, and ferric oxide red.
Temozolomide capsules, USP, 250 mg: The white opaque cap contains gelatin, and titanium dioxide. structure
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to initiating Temozolomide [see Use in Specific Populations (8.1) ]. Contraception Females Temozolomide can cause embryo-fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ]. Advise females of reproductive potential to use effective contraception during treatment with Temozolomide and for at least 6 months after the last dose.
Males Because of the potential for embryofetal toxicity and genotoxic effects on sperm cells, advise male patients with pregnant partners or female partners of reproductive potential to use condoms during treatment with Temozolomide and for at least 3 months after the final dose [see Use in Specific Populations (8.1) , Nonclinical Toxicology (13.1) ]. Advise male patients not to donate semen during treatment with Temozolomide and for at least 3 months after the final dose. Infertility Temozolomide may impair male fertility [see Nonclinical Toxicology (13.1) ] .
Limited data from male patients show changes in sperm parameters during treatment with Temozolomide; however, no information is available on the duration or reversibility of these changes.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following a single oral dose of 150 mg/m 2 , the mean C max value for temozolomide was 7.5 mcg/mL and for MTIC was 282 ng/mL. The mean AUC value for temozolomide was 23.4 mcg·hr/mL and for MTIC was 864 ng·hr/mL. Temozolomide exhibits linear kinetics over the therapeutic dosing range of 75 mg/m 2 /day to 250 mg/m 2 /day.
Absorption The median T max is 1 hour. Effect of Food The mean C max and AUC decreased by 32% and 9%, respectively, and median T max increased by 2-fold (from 1-2.25 hours) when Temozolomide capsules, USP were administered after a modified high-fat breakfast (587 calories comprised of 1 fried egg, 2 strips of bacon, 2 slices of toast, 2 pats of butter, and 8 oz whole milk). Distribution Temozolomide has a mean apparent volume of distribution of
0.4L/kg (%CV=13%). The mean percent bound of drug-related total radioactivity is 15%. Elimination Clearance of temozolomide is about
5.5L/hr/m 2 and the mean elimination half-life is 1.8 hours. Metabolism Temozolomide is spontaneously hydrolyzed at physiologic pH to the active species, MTIC and to temozolomide acid metabolite. MTIC is further hydrolyzed to 5-amino-imidazole-4-carboxamide (AIC), which is known to be an intermediate in purine and nucleic acid biosynthesis, and to methylhydrazine, which is believed to be the active alkylating species.
Cytochrome P450 enzymes play only a minor role in the metabolism of temozolomide and MTIC. Relative to the AUC of temozolomide, the exposure to MTIC and AIC is 2.4% and 23%, respectively. Excretion About 38% of the administered temozolomide total radioactive dose is recovered over 7 days: 38% in urine and 0.8% in feces.
The majority of the recovery of radioactivity in urine is unchanged temozolomide (6%), AIC (12%), temozolomide acid metabolite (2.3%), and unidentified polar metabolite(s) (17%). Specific Populations No clinically meaningful differences in the pharmacokinetics of temozolomide were observed based on age (range: 19-78 years), gender, smoking status (smoker vs. non-smoker), creatinine clearance (CLcr) of 36 to 130 mL/min/m 2 , or mild to moderate hepatic impairment (Child Pugh class A and B). The pharmacokinetics of temozolomide has not been studied in patients with CLcr < 36 mL/min/m 2 , end-stage renal disease on dialysis, or severe hepatic impairment (Child-Pugh class C).
Drug Interaction Studies Effect of Other Drugs on Temozolomide Pharmacokinetics In a multiple-dose study, administration of Temozolomide capsules, USP with ranitidine did not change the C max or AUC values for temozolomide or MTIC. A population analysis indicated that administration of valproic acid decreases the clearance of temozolomide by about 5%. A population analysis did not demonstrate any influence of coadministered dexamethasone, prochlorperazine, phenytoin, carbamazepine, ondansetron, histamine-2-receptor antagonists, or phenobarbital on the clearance of orally administered Temozolomide capsules, USP.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Newly Diagnosed Glioblastoma The efficacy of Temozolomide was evaluated in Study MK-7365-051, a randomized (1:1), multicenter, open-label trial. Eligible patients were required to have newly diagnosed glioblastoma. Patients were randomized to receive either radiation therapy alone or concomitant Temozolomide 75 mg/m 2 once daily starting the first day of radiation therapy and continuing until the last day of radiation therapy for 42 days (with a maximum of 49 days), followed by Temozolomide 150 mg/m 2 or 200 mg/m 2 once daily on Days 1 to 5 of each 28-day cycle, starting 4 weeks after the end of radiation therapy and continuing for 6 cycles.
In both arms, focal radiation therapy was delivered as 60 Gy/30 fractions and included radiation to the tumor bed or resection site with a 2- to 3-cm margin. PCP prophylaxis was required during the concomitant phase, regardless of lymphocyte count and continued until recovery of lymphocyte count to grade 1 or less. The major efficacy outcome measure was overall survival.
A total of 573 patients were randomized, 287 to Temozolomide and radiation therapy and 286 to radiation therapy alone. At the time of disease progression, Temozolomide was administered as salvage therapy in 161 patients of the 282 (57%) in the radiation therapy alone arm and 62 patients of the 277 (22%) in the Temozolomide and radiation therapy arm. The addition of concomitant and maintenance Temozolomide to radiation therapy for the treatment of patients with newly diagnosed glioblastoma showed a statistically significant improvement in overall survival compared to radiotherapy alone ( Figure 1 ).
The hazard ratio (HR) for overall survival was 0.63 (95% CI: 0.52, 0.75) with a log-rank P <0.0001 in favor of the Temozolomide arm. The median survival was increased by 2.5 months in the Temozolomide arm. FIGURE 1: Kaplan-Meier Curves for Overall Survival (ITT Population) in Newly Diagnosed Glioblastoma Trial figure1
14.2Refractory Anaplastic Astrocytoma The efficacy of Temozolomide was evaluated in Study MK-7365-006, a single-arm, multicenter trial. Eligible patients had anaplastic astrocytoma at first relapse and a baseline Karnofsky performance status (KPS) of 70 or greater. Patients had previously received radiation therapy and may also have previously received a nitrosourea with or without other chemotherapy.
Fifty-four patients had disease progression on prior therapy with both a nitrosourea and procarbazine and their malignancy was considered refractory to chemotherapy (refractory anaplastic astrocytoma population). Temozolomide capsules, USP were given on Days 1 to 5 of each 28-day cycle at a starting dose of 150 mg/m 2 /day. If ANC was ≥1.5 x 10 9 /L and platelet count was ≥100 x 10 9 /L at the nadir and on Day 1 of the next cycle, the Temozolomide dose was increased to 200 mg/m 2 /day.
The major efficacy outcome measure was progression-free survival at 6 months and the additional efficacy outcome measures were overall survival and overall response rate. In the refractory anaplastic astrocytoma population (n=54), the median age was 42 years (range: 19 to 76); 65% were male; and 72% had a KPS of >80. Sixty-three percent of patients had surgery other than a biopsy at the time of initial diagnosis.
Of those patients undergoing resection, 73% underwent a subtotal resection and 27% underwent a gross total resection. Eighteen percent of patients had surgery at the time of first relapse. The median time from initial diagnosis to first relapse was 13.8 months (range: 4.2 months to 6.3 years).
In the refractory anaplastic astrocytoma population, the overall response rate (CR+PR) was 22% (12 of 54 patients) and the complete response rate was 9% (5 of 54 patients). The median duration of all responses was 50 weeks (range: 16 to 114 weeks) and the median duration of complete responses was 64 weeks (range: 52 to 114 weeks). In this population, progression-free survival at 6 months was 45% (95% CI: 31%, 58%… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Temozolomide is carcinogenic in rats at doses less than the maximum recommended human dose. Temozolomide induced mammary carcinomas in both males and females at doses 0.13 to 0.63 times the maximum human dose (25-125 mg/m 2 ) when administered orally on 5 consecutive days every 28 days for 6 cycles. Temozolomide also induced fibrosarcomas of the heart, eye, seminal vesicles, salivary glands, abdominal cavity, uterus, and prostate, carcinomas of the seminal vesicles, schwannomas of the heart, optic nerve, and harderian gland, and adenomas of the skin, lung, pituitary, and thyroid at doses 0.5 times the maximum daily dose.
Mammary tumors were also induced following 3 cycles of temozolomide at the maximum recommended daily dose. Temozolomide is a mutagen and a clastogen. In a reverse bacterial mutagenesis assay (Ames assay), temozolomide increased revertant frequency in the absence and presence of metabolic activation.
Temozolomide was clastogenic in human lymphocytes in the presence and absence of metabolic activation. Temozolomide impairs male fertility. Temozolomide caused syncytial cells/immature sperm formation at doses of 50 and 125 mg/m 2 (0.25 and 0.63 times the human dose of 200 mg/m 2 ) in rats and dogs, respectively, and testicular atrophy in dogs at 125 mg/m 2 .
13.2Animal Toxicology and/or Pharmacology Toxicology studies in rats and dogs identified a low incidence of hemorrhage, degeneration, and necrosis of the retina at temozolomide doses equal to or greater than 125 mg/m 2 (0.63 times the human dose of 200 mg/m 2 ). These changes were most commonly seen at doses where mortality was observed.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Temozolomide is carcinogenic in rats at doses less than the maximum recommended human dose. Temozolomide induced mammary carcinomas in both males and females at doses 0.13 to 0.63 times the maximum human dose (25-125 mg/m 2 ) when administered orally on 5 consecutive days every 28 days for 6 cycles. Temozolomide also induced fibrosarcomas of the heart, eye, seminal vesicles, salivary glands, abdominal cavity, uterus, and prostate, carcinomas of the seminal vesicles, schwannomas of the heart, optic nerve, and harderian gland, and adenomas of the skin, lung, pituitary, and thyroid at doses 0.5 times the maximum daily dose.
Mammary tumors were also induced following 3 cycles of temozolomide at the maximum recommended daily dose. Temozolomide is a mutagen and a clastogen. In a reverse bacterial mutagenesis assay (Ames assay), temozolomide increased revertant frequency in the absence and presence of metabolic activation.
Temozolomide was clastogenic in human lymphocytes in the presence and absence of metabolic activation. Temozolomide impairs male fertility. Temozolomide caused syncytial cells/immature sperm formation at doses of 50 and 125 mg/m 2 (0.25 and 0.63 times the human dose of 200 mg/m 2 ) in rats and dogs, respectively, and testicular atrophy in dogs at 125 mg/m 2 .
📚 References ▾
15 REFERENCES 1. “OSHA Hazardous Drugs.” OSHA . http://www.osha.gov/SLTC/hazardousdrugs/index.
📄 Patient Package Insert ▾
.
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.5 ) 11/2019
📄 Package Label / Principal Display Panel ▾
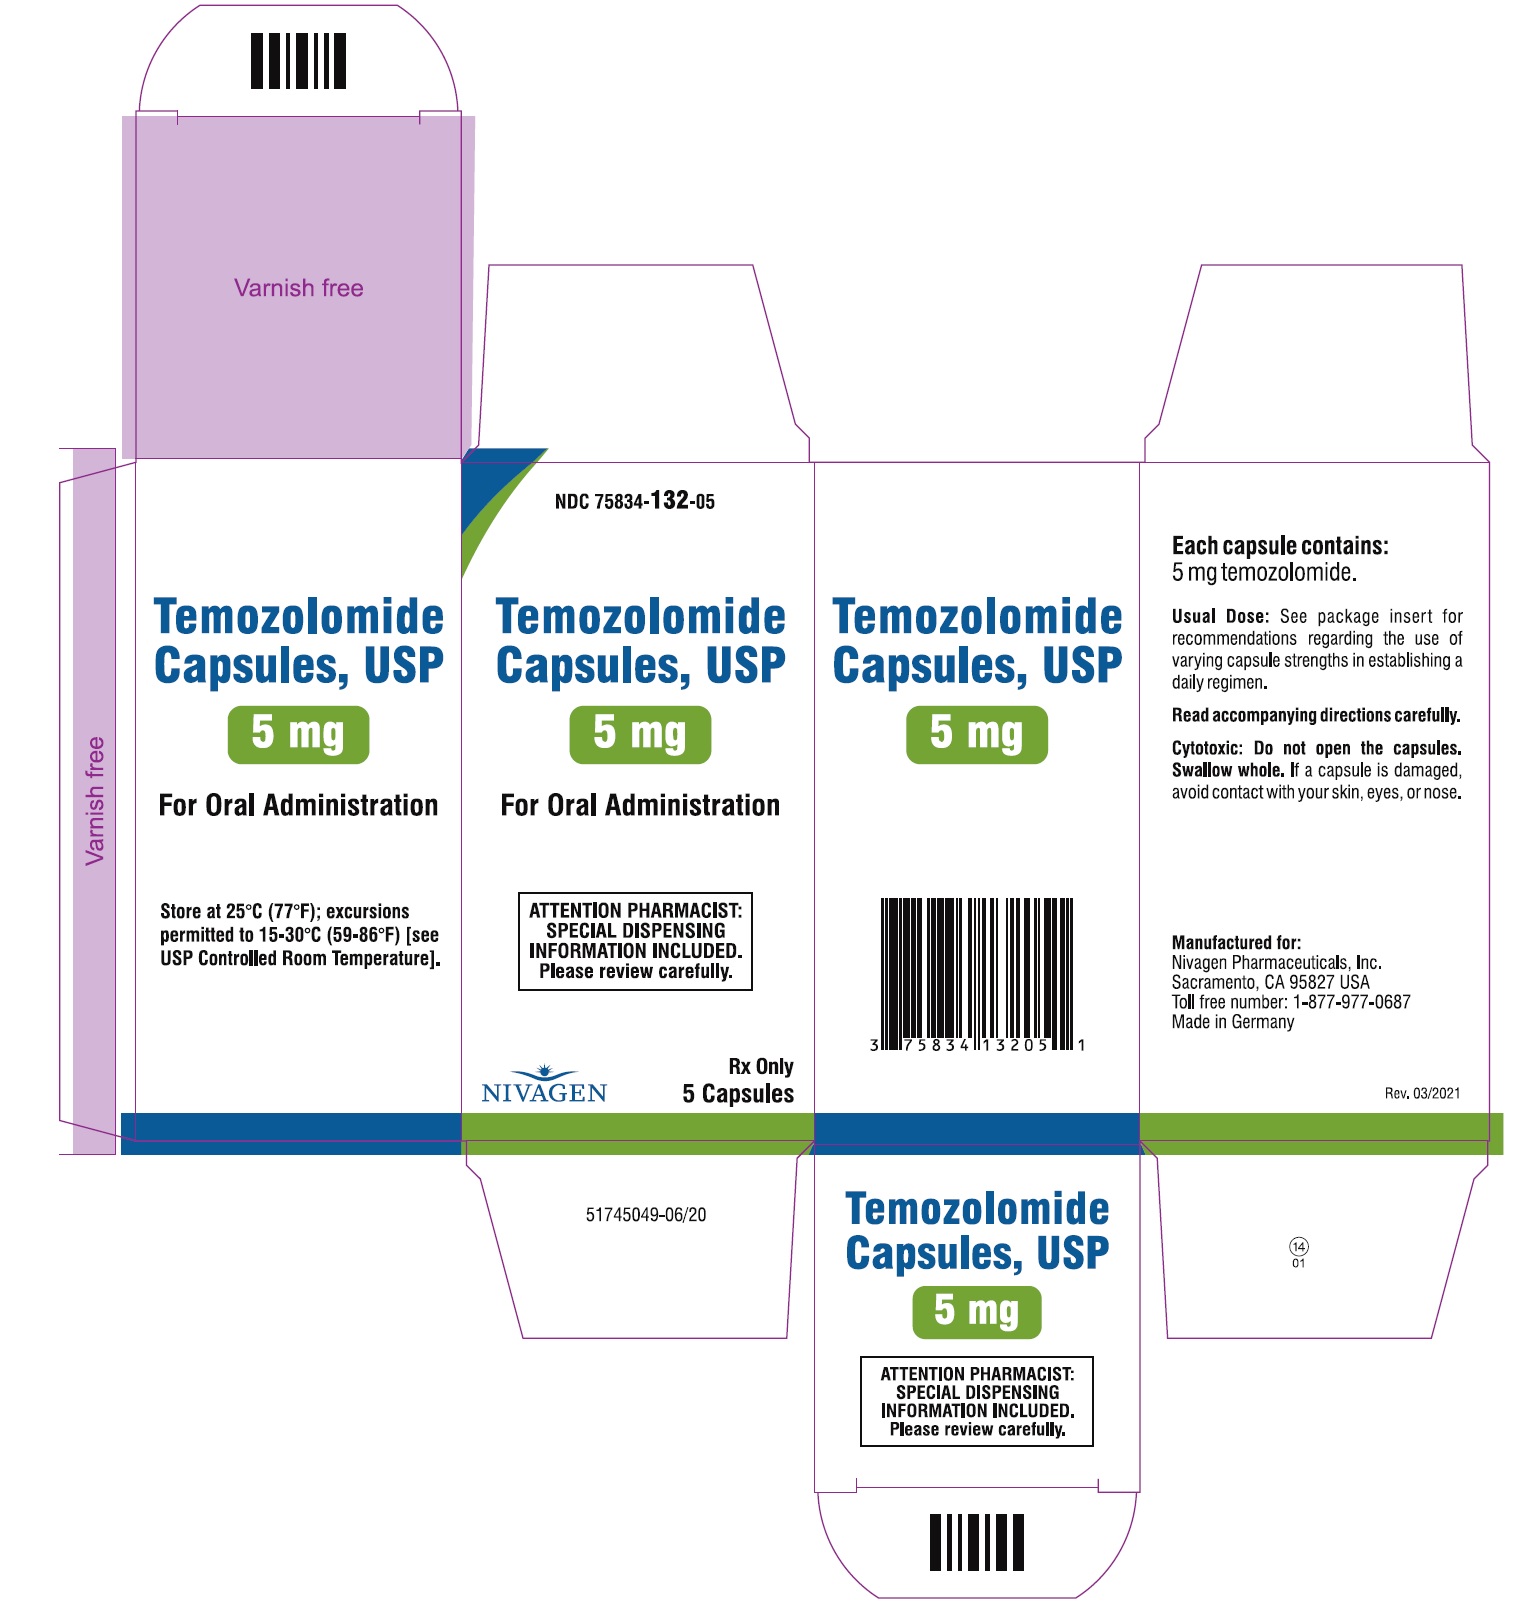
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 75834-132-05 Temozolomide 5mg per Capsule Bottle Label - 5 Capsules Count NDC 75834-132-05 Temozolomide 5mg per Capsule Bottle Carton - 5 Capsules Count NDC 75834-132-14 Temozolomide 5mg per Capsule Bottle Label - 14 Capsules Count NDC 75834-132-14 Temozolomide 5mg per Capsule Bottle Carton - 14 Capsules Count NDC 75834-142-05 Temozolomide 20mg per Capsule Bottle Label - 5 Capsules Count NDC 75834-142-05 Temozolomide 20mg per Capsule Bottle Carton - 5 Capsules Count NDC 75834-142-14 Temozolomide 20mg per Capsule Bottle Label - 14 Capsules Count NDC 75834-142-14 Temozolomide 20mg per Capsule Bottle Carton - 14 Capsules Count NDC 75834-143-05 Temozolomide 100mg per Capsule Bottle Label - 5 Capsules Count NDC 75834-143-05 Temozolomide 100mg per Capsule Bottle Carton - 5 Capsules Count NDC 75834-143-14 Temozolomide 100mg per Capsule Bottle Label - 14 Capsules Count NDC 75834-143-14 Temozolomide 100mg per Capsule Bottle Carton - 14 Capsules Count NDC 75834-144-05 Temozolomide 140mg per Capsule Bottle Label - 5 Capsules Count NDC 75834-144-05 Temozolomide 140mg per Capsule Bottle Carton - 5 Capsules Count NDC 75834-144-14 Temozolomide 140mg per Capsule Bottle Label - 14 Capsules Count NDC 75834-144-14 Temozolomide 140mg per Capsule Bottle Carton - 14 Capsules Count NDC 75834-145-05 Temozolomide 180mg per Capsule Bottle Label - 5 Capsules Count NDC 75834-145-05 Temozolomide 180mg per Capsule Bottle Carton - 5 Capsules Count NDC 75834-145-14 Temozolomide 180mg per Capsule Bottle Label - 14 Capsules Count NDC 75834-145-14 Temozolomide 180mg per Capsule Bottle Carton - 14 Capsules Count NDC 75834-146-05 Temozolomide 250mg per Capsule Bottle Label - 5 Capsules Count NDC 75834-146-05 Temozolomide 250mg per Capsule Bottle Carton - 5 Capsules Count 5mg-5count-label.jpg 5mg5c-carton.jpg 5mg-14count-label.jpg 5mg14c-carton.jpg 20mg-5count-label.jpg 20mg5c-carton.jpg 20mg-14count-label.jpg 20mg14c-carton.jpg 100mg-5count-label.jpg 100mg5c-carton.jpg 100mg-14count-label.jpg 100mg14c-carton.jpg 140mg-5count-label.jpg 140mg5c-carton.jpg 140mg-14count-label.jpg 140mg14c-carton.jpg 180mg-5count-label.jpg 180mg5c-carton.jpg 180mg-14count-label.jpg 180mg14c-carton.jpg 250mg-5count-label.jpg 250mg5c-carton.jpg
Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |