
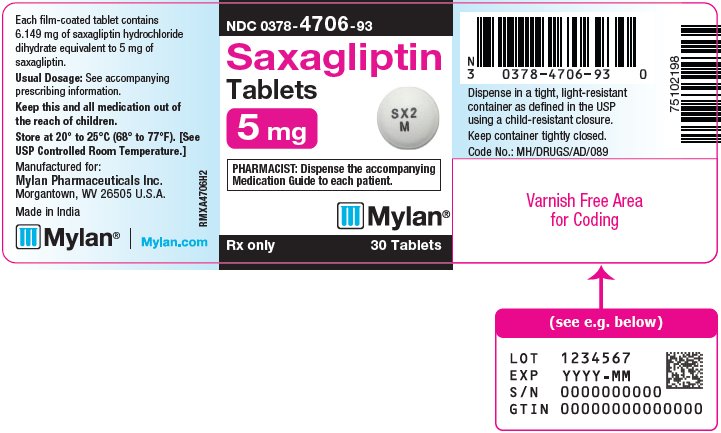
Saxagliptin 5 mg Tablet, Film Coated, 30-count
Other active recalls for Saxagliptin (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Dipeptidyl Peptidase 4 Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Saxagliptin is used along with diet and exercise to lower blood sugar levels in patients with type 2 diabetes (condition in which blood sugar is too high because the body does not produce or use insulin normally). Saxagliptin is in a class of medications called dipeptidyl peptidase-4 (DPP-4) inhibitors. It works by increasing the amount of insulin produced by the body after meals. People who have diabetes and high blood sugar can develop health problems over time. Taking medication(s), making changes (e.g., diet, exercise, quitting smoking) may help to manage your diabetes and improve your hea...
Read the full MedlinePlus article ↗- Saxagliptin works by blocking an enzyme called DPP-4, which normally destroys helpful hormones your gut releases after eating. By blocking that enzyme, saxagliptin lets those hormo...
- What exactly does saxagliptin do — and how is it different from other diabetes pills?
- You can take saxagliptin with or without food — whichever works best for your routine. A meal does slightly slow down how quickly it's absorbed, but it doesn't meaningfully change...
- Can I take this pill with food, or do I need to take it on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Saxagliptin — tap one for details:
Saxagliptin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 5XDI2TS1EZ
Microcrystalline cellulose is a refined plant fiber derived from wood pulp. It serves as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 4R4HFI6D95
Polyethylene glycol 4000 is a synthetic polymer derived from petroleum. It serves as a binder, filler, and lubricant in solid dosage forms, and helps control how quickly the medicine dissolves.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
15 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.050 | $31.49 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $4.54 | $136.17 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $8.94 | $268.08 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Saxagliptin 5 mgthis 00378-4706-93 | Mylan | 30 tablets | $1.049 | AB | Availability likely | — |
| Saxagliptin 5 mg 65862-0826-01 | Aurobindo | 100 tablets | — | AB | FDA listed | — |
| Saxagliptin 5 mg 68462-0727-05 | Glenmark | 500 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00378-4706-77 | 90 TABLET, FILM COATED in 1 BOTTLE, PLASTIC (0378-4706-77) | $1.05 / ea | $94.45 | 2023-08-04 | Active |
| 00378-4706-93 You're viewing this | 30 TABLET, FILM COATED in 1 BOTTLE, PLASTIC (0378-4706-93) | $1.05 / ea | $31.48 | 2023-08-04 | Active |
You're viewing the smallest of 2 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($1.05 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 95% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 00378-4706-93?
What is the difference between NDC 00378-4706-93 and NDC 00378-4706-77?
What NDC number is used to bill for this package of Saxagliptin 5 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Saxagliptin tablets are a dipeptidyl peptidase-4 (DPP-4) inhibitor indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. ( 1.1 ) Limitations of use: • Not recommended for the treatment of type 1 diabetes mellitus or diabetic ketoacidosis. ( 1.2 )
1.1Monotherapy and Combination Therapy Saxagliptin tablets are indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus [ see Clinical Studies (14) ].
1.2Limitations of Use Saxagliptin tablets are not recommended for the treatment of type 1 diabetes mellitus or diabetic ketoacidosis.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Recommended dosage is 2.5 mg or 5 mg orally once daily taken regardless of meals. ( 2.1 ) • Patients with an eGFR < 45 mL/min/1.73 m 2 (moderate or severe renal impairment, or end-stage renal disease): Recommended dosage is 2.5 mg once daily regardless of meals. ( 2.2 ) • Assess renal function before starting saxagliptin tablets and periodically thereafter.
( 2.2 ) • Limit the dosage of saxagliptin tablets to 2.5 mg daily for patients also taking strong cytochrome P450 3A4/5 (CYP3A4/5) inhibitors (e.g., ketoconazole). ( 2.3 )
2.1Recommended Dosage The recommended dosage of saxagliptin tablets is 2.5 mg or 5 mg orally once daily taken regardless of meals. Do not cut, crush, or chew saxagliptin tablets. If a dose is missed, advise patients not to take an extra dose. Resume treatment with the next dose.
2.2Dosage in Patients with Renal Impairment Assess renal function prior to initiation of saxagliptin tablets and then as clinically indicated [ see Use in Specific Populations (8.6) ]. The recommended dosage of saxagliptin tablets in patients with an eGFR greater than or equal to 45 mL/minute/1.73 m 2 is the same as the recommended dosage in patients with normal renal function [ see Dosage and Administration (2.1) ]. The dosage of saxagliptin tablets is 2.5 mg orally once daily for patients with eGFR < 45 mL/min/1.73 m 2 [which includes a subset of moderate or severe renal impairment, or with end-stage renal disease (ESRD) requiring hemodialysis] [ see Clinical Pharmacology (12.3) and Clinical Studies (14.2) ].
Saxagliptin tablets should be administered following hemodialysis. Saxagliptin tablets have not been studied in patients undergoing peritoneal dialysis.
2.3Dosage Modification with Concomitant Use of Strong CYP3A4/5 Inhibitors The dosage of saxagliptin tablets is 2.5 mg orally once daily when used concomitantly with strong cytochrome P450 3A4/5 (CYP3A4/5) inhibitors (e.g., ketoconazole, atazanavir, clarithromycin, indinavir, itraconazole, nefazodone, nelfinavir, ritonavir, saquinavir, and telithromycin) [ see Drug Interactions (7.1) and Clinical Pharmacology (12.3) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Saxagliptin Tablets are available containing 3.075 mg or 6.149 mg of saxagliptin hydrochloride dihydrate equivalent to 2.5 mg or 5 mg of saxagliptin. • The 2.5 mg tablets are yellow, film-coated, round, unscored tablets imprinted with SX1 over M in black ink on one side of the tablet and blank on the other side. • The 5 mg tablets are white to off-white, film-coated, round, unscored tablets imprinted with SX2 over M in black ink on one side of the tablet and blank on the other side. • Tablets: 5 mg and 2.5 mg.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Saxagliptin tablets are contraindicated in patients with a history of a serious hypersensitivity reaction to saxagliptin or any of the ingredients in saxagliptin tablets. Reactions such as anaphylaxis, angioedema, or exfoliative skin conditions have been reported with saxagliptin tablets [ see Warnings and Precautions (5.4) and Adverse Reactions (6.2) ]. • History of a serious hypersensitivity reaction (e.g., anaphylaxis, angioedema, exfoliative skin conditions) to saxagliptin or any of the ingredients in saxagliptin tablets.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Pancreatitis: There have been postmarketing reports of acute pancreatitis. If pancreatitis is suspected, promptly discontinue saxagliptin tablets. ( 5.1 ) • Heart Failure: Consider the risks and benefits of saxagliptin tablets in patients who have known risk factors for heart failure.
Monitor patients for signs and symptoms. ( 5.2 ) • Hypoglycemia with Concomitant Use of Insulin or Insulin Secretagogues: Consider a lower dosage of insulin or insulin secretagogue when used in combination with saxagliptin tablets. ( 5.3 ) • Hypersensitivity-Related Events: There have been postmarketing reports of serious hypersensitivity reactions such as anaphylaxis, angioedema, and exfoliative skin conditions.
If hypersensitivity reactions occur, discontinue saxagliptin tablets, treat promptly, and monitor until signs and symptoms resolve. ( 5.4 ) • Arthralgia : Severe and disabling arthralgia has been reported in patients taking DPP-4 inhibitors. Consider as a possible cause for severe joint pain and discontinue drug if appropriate.
( 5.5 ) • Bullous Pemphigoid: There have been postmarketing reports of bullous pemphigoid requiring hospitalization in patients taking DPP-4 inhibitors. Tell patients to report development of blisters or erosions. If bullous pemphigoid is suspected, discontinue saxagliptin tablets.
( 5.6 )
5.1Pancreatitis There have been postmarketing reports of acute pancreatitis in patients taking saxagliptin tablets. In a cardiovascular outcomes trial enrolling participants with established atherosclerotic cardiovascular disease (ASCVD) or multiple risk factors for ASCVD (SAVOR trial), cases of definite acute pancreatitis were confirmed in 17 of 8240 (0.2%) patients receiving saxagliptin tablets compared to 9 of 8173 (0.1%) receiving placebo. Preexisting risk factors for pancreatitis were identified in 88% (15/17) of those patients receiving saxagliptin tablets and in 100% (9/9) of those patients receiving placebo.
After initiation of saxagliptin tablets, observe patients for signs and symptoms of pancreatitis. If pancreatitis is suspected, promptly discontinue saxagliptin tablets and initiate appropriate management. It is unknown whether patients with a history of pancreatitis are at increased risk for the development of pancreatitis while using saxagliptin tablets.
5.2Heart Failure In a cardiovascular outcomes trial enrolling participants with established ASCVD or multiple risk factors for ASCVD (SAVOR trial), more patients randomized to saxagliptin tablets (289/8280, 3.5%) were hospitalized for heart failure compared to patients randomized to placebo (228/8212, 2.8%). In a time-to-first-event analysis the risk of hospitalization for heart failure was higher in the saxagliptin tablets group (estimated Hazard Ratio: 1.27; 95% CI: 1.07, 1.51). Patients with a prior history of heart failure and patients with renal impairment had a higher risk for hospitalization for heart failure, irrespective of treatment assignment.
Consider the risks and benefits of saxagliptin tablets prior to initiating treatment in patients at a higher risk for heart failure. Observe patients for signs and symptoms of heart failure during therapy. Advise patients of the characteristic symptoms of heart failure and to immediately report such symptoms.
If heart failure develops, evaluate and manage according to current standards of care and consider discontinuation of saxagliptin tablets.
5.3Hypoglycemia with Concomitant Use of Insulin or Insulin Secretagogues When saxagliptin tablets were used in combination with insulin or an insulin secretagogue, the incidence of confirmed hypoglycemia was increased over that of placebo used in combination with insulin or an insulin secretagogue [ see Adverse Reactions (6.1) ]. Therefore, a lower dosage of insulin or an insulin secretagogue may be required to reduce the risk of hypoglycemia when used in combination with saxagliptin tablets [ see Drug Interactions (7.2) ].
Inform patients us…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below or elsewhere in the prescribing information: • Pancreatitis [ see Warnings and Precautions (5.1) ] • Heart Failure [ see Warnings and Precautions (5.2) ] • Hypoglycemia with Concomitant Use of Insulin or Insulin Secretagogues [ see Warnings and Precautions (5.3) ] • Hypersensitivity Reactions [ see Warnings and Precautions (5.4) ] • Severe and disabling arthralgia [ see Warnings and Precautions (5.5) ] • Bullous pemphigoid [ see Warnings and Precautions (5.6) ] • Most common adverse reactions (incidence ≥ 5% and more often than placebo) are upper respiratory tract infection, urinary tract infection, and headache.
( 6.1 ) • Peripheral edema was reported more commonly in patients treated with the combination of saxagliptin tablets and a thiazolidinedione (TZD) than in patients treated with the combination of placebo and TZD. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions in Placebo-Controlled Trials in Adults with Type 2 Diabetes Mellitus The data in Table 1 are derived from a pool of 5 placebo-controlled clinical trials [ see Clinical Studies (14) ]. These data shown in the table reflect exposure of 882 patients to saxagliptin tablets and a mean duration of exposure to saxagliptin tablets of 21 weeks.
The mean age of these patients was 55 years, 1.4% were 75 years of age or older and 48.4% were male. The population was 67.5% White, 4.6% Black or African American, 17.4% Asian, 10.5% other races and 9.8% were of Hispanic or Latino ethnicity. At baseline, the population had type 2 diabetes mellitus for an average of 5.2 years and a mean HbA1c of 8.2%.
Baseline estimated renal function was normal or mildly impaired (eGFR ≥ 60 mL/min/1.73 m 2 ) in 91% of these patients. Table 1 shows common adverse reactions, excluding hypoglycemia, associated with the use of saxagliptin tablets. These adverse reactions occurred more commonly on saxagliptin tablets than on placebo and occurred in at least 5% of patients treated with saxagliptin tablets.
Table 1: Adverse Reactions in Placebo-Controlled Trials The 5 placebo-controlled trials include two monotherapy trials and one add-on combination therapy trial with each of the following: metformin hydrochloride (HCl), thiazolidinedione, or glyburide. Table shows 24-week data regardless of glycemic rescue. Reported in ≥ 5% of Patients Treated with Saxagliptin Tablets 5 mg and More Commonly than in Patients Treated with Placebo % of Patients Saxagliptin Tablets 5 mg N = 882 Placebo N = 799 Upper respiratory tract infection 7.7
7.6Urinary tract infection 6.8
6.1Headache 6.5
5.9In patients treated with saxagliptin tablets 2.5 mg, headache (6.5%) was the only adverse reaction reported at a rate ≥ 5% and more commonly than in patients treated with placebo. In the add-on to TZD trial, the incidence of peripheral edema was higher for saxagliptin tablets 5 mg versus placebo (8.1% and 4.3%, respectively). The incidence of peripheral edema for saxagliptin tablets 2.5 mg was 3.1%.
None of the reported adverse reactions of peripheral edema resulted in trial drug discontinuation. Rates of peripheral edema for saxagliptin tablets 2.5 mg and saxagliptin tablets 5 mg versus placebo were 3.6% and 2% versus 3% given as monotherapy, 2.1% and 2.1% versus 2.2% given as add-on therapy to metformin HCl, and 2.4% and 1.2% versus 2.2% given as add-on therapy to glyburide. The incidence rate of fractures was 1.0 and 0.6 per 100 patient-years, respectively, for saxagliptin tablets (pooled analysis of 2.5 mg, 5 mg, and 10 mg) and placebo.
Th…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong CYP3A4/5 inhibitors (e.g., ketoconazole): Coadministration with saxagliptin tablets significantly increases saxagliptin concentrations. Limit saxagliptin tablets dosage to 2.5 mg once daily when coadministered with a strong CYP3A4/5 inhibitor. ( 7.1 )
7.1Strong Inhibitors of CYP3A4/5 Enzymes Ketoconazole significantly increased saxagliptin exposure. Similar significant increases in plasma concentrations of saxagliptin are anticipated with other strong CYP3A4/5 inhibitors (e.g., atazanavir, clarithromycin, indinavir, itraconazole, nefazodone, nelfinavir, ritonavir, saquinavir, and telithromycin). The dosage of saxagliptin tablets should be limited to 2.5 mg when coadministered with a strong CYP3A4/5 inhibitor [ see Dosage and Administration (2.3) and Clinical Pharmacology (12.3) ].
7.2Insulin or Insulin Secretagogues Insulin and insulin secretagogues are known to cause hypoglycemia. Concomitant use of saxagliptin tablets with insulin or an insulin secretagogue may require lower dosages of insulin or the insulin secretagogue to reduce the risk of hypoglycemia [ see Warnings and Precautions (5.3) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Limited data with saxagliptin tablets in pregnant women are not sufficient to determine a drug-associated risk for major birth defects or miscarriages. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy [ see Clinical Considerations ]. No adverse developmental effects independent of maternal toxicity were observed when saxagliptin was administered to pregnant rats and rabbits during the period of organogenesis and in pregnant and lactating rats during the pre- and postnatal period [ see Data ].
The estimated background risk of major birth defects is 6 to 10% in women with pre-gestational diabetes with an HbA1c greater than 7 and has been reported to be as high as 20 to 25% in women with an HbA1c greater than 10. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, still birth and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data In embryo-fetal development studies, saxagliptin was administered to pregnant rats and rabbits during the period of organogenesis, corresponding to the first trimester of human pregnancy.
No adverse developmental effects were observed in either species at exposures 1503- and 152-times the 5 mg clinical dose in rats and rabbits, respectively, based on AUC. Saxagliptin crosses the placenta into the fetus following dosing in pregnant rats. In a prenatal and postnatal development study, no adverse developmental effects were observed in maternal rats administered saxagliptin from gestation day 6 through lactation day 21 at exposures up to 470-times the 5 mg clinical dose, based on AUC.
8.2Lactation Risk Summary There is no information regarding the presence of saxagliptin in human milk, the effects on the breastfed infant, or the effects on milk production. Saxagliptin is present in the milk of lactating rats [ see Data ]. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for saxagliptin tablets and any potential adverse effects on the breastfed infant from saxagliptin tablets or from the underlying maternal condition.
Data Saxagliptin is secreted in the milk of lactating rats at approximately a 1:1 ratio with plasma drug concentrations.
8.4Pediatric Use The safety and effectiveness of saxagliptin tablets as an adjunct to diet and exercise to improve glycemic control in patients with type 2 diabetes mellitus have not been established in pediatric patients. Effectiveness of saxagliptin tablets was not demonstrated in a 26-week, placebo-controlled, double-blind randomized clinical trial with a 26-week safety extension (NCT03199053) in 164 pediatric patients aged 10 to 17 years with inadequately controlled type 2 diabetes mellitus.
8.5Geriatric Use In the seven, double-blind, controlled clinical safety and efficacy trials of saxagliptin tablets, a total of 4751 (42.0%) of the 11301 patients randomized to saxagliptin tablets were 65 years and over, and 1210 (10.7%) were 75 years and over. No overall differences in safety or effectiveness were observed between patients 65 years of age and older and younger adult patients. Saxagliptin and its active metabolite are eliminated in part by the kidney.
Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection in the elderly based on renal function [ see Dosage and Administration (2.2) and Clinical Pharmaco…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited data with saxagliptin tablets in pregnant women are not sufficient to determine a drug-associated risk for major birth defects or miscarriages. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy [ see Clinical Considerations ]. No adverse developmental effects independent of maternal toxicity were observed when saxagliptin was administered to pregnant rats and rabbits during the period of organogenesis and in pregnant and lactating rats during the pre- and postnatal period [ see Data ].
The estimated background risk of major birth defects is 6 to 10% in women with pre-gestational diabetes with an HbA1c greater than 7 and has been reported to be as high as 20 to 25% in women with an HbA1c greater than 10. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, still birth and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data In embryo-fetal development studies, saxagliptin was administered to pregnant rats and rabbits during the period of organogenesis, corresponding to the first trimester of human pregnancy.
No adverse developmental effects were observed in either species at exposures 1503- and 152-times the 5 mg clinical dose in rats and rabbits, respectively, based on AUC. Saxagliptin crosses the placenta into the fetus following dosing in pregnant rats. In a prenatal and postnatal development study, no adverse developmental effects were observed in maternal rats administered saxagliptin from gestation day 6 through lactation day 21 at exposures up to 470-times the 5 mg clinical dose, based on AUC.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of saxagliptin tablets as an adjunct to diet and exercise to improve glycemic control in patients with type 2 diabetes mellitus have not been established in pediatric patients. Effectiveness of saxagliptin tablets was not demonstrated in a 26-week, placebo-controlled, double-blind randomized clinical trial with a 26-week safety extension (NCT03199053) in 164 pediatric patients aged 10 to 17 years with inadequately controlled type 2 diabetes mellitus.
🧓 Geriatric Use ▾
8.5Geriatric Use In the seven, double-blind, controlled clinical safety and efficacy trials of saxagliptin tablets, a total of 4751 (42.0%) of the 11301 patients randomized to saxagliptin tablets were 65 years and over, and 1210 (10.7%) were 75 years and over. No overall differences in safety or effectiveness were observed between patients 65 years of age and older and younger adult patients. Saxagliptin and its active metabolite are eliminated in part by the kidney.
Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection in the elderly based on renal function [ see Dosage and Administration (2.2) and Clinical Pharmacology (12.3) ].
🆘 Overdosage ▾
10 OVERDOSAGE In a controlled clinical trial, once-daily, orally-administered saxagliptin tablets in healthy patients at doses up to 400 mg daily for 2 weeks (80-times the MRHD) had no dose-related clinical adverse reactions and no clinically meaningful effect on QTc interval or heart rate. In the event of an overdose, initiate appropriate supportive treatment as dictated by the patient’s clinical status. Saxagliptin and its active metabolite are removed by hemodialysis (23% of dose over 4 hours).
Contact the Poison Help Line, (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Increased concentrations of the incretin hormones such as glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP) are released into the bloodstream from the small intestine in response to meals. These hormones cause insulin release from the pancreatic beta cells in a glucose-dependent manner but are inactivated by the DPP-4 enzyme within minutes. GLP-1 also lowers glucagon secretion from pancreatic alpha cells, reducing hepatic glucose production.
In patients with type 2 diabetes mellitus, concentrations of GLP-1 are reduced but the insulin response to GLP-1 is preserved. Saxagliptin is a competitive DPP-4 inhibitor that slows the inactivation of the incretin hormones, thereby increasing their bloodstream concentrations and reducing fasting and postprandial glucose concentrations in a glucose-dependent manner in patients with type 2 diabetes mellitus.
12.2Pharmacodynamics In patients with type 2 diabetes mellitus, administration of saxagliptin tablets inhibits DPP-4 enzyme activity for a 24-hour period. After an oral glucose load or a meal, this DPP-4 inhibition resulted in a 2- to 3-fold increase in circulating levels of active GLP-1 and GIP, decreased glucagon concentrations, and increased glucose-dependent insulin secretion from pancreatic beta cells. The rise in insulin and decrease in glucagon were associated with lower fasting glucose concentrations and reduced glucose excursion following an oral glucose load or a meal.
Cardiac Electrophysiology In a randomized, double-blind, placebo-controlled, 4-way crossover, active comparator trial using moxifloxacin in 40 healthy subjects, saxagliptin tablets were not associated with clinically meaningful prolongation of the QTc interval or heart rate at daily doses up to 40 mg (8-times the MRHD).
12.3Pharmacokinetics The pharmacokinetics of saxagliptin and its active metabolite, 5-hydroxy saxagliptin were similar in healthy subjects and in patients with type 2 diabetes mellitus. The C max and AUC values of saxagliptin and its active metabolite increased proportionally in the 2.5 to 400 mg dose range. Following a 5 mg single oral dose of saxagliptin to healthy subjects, the mean plasma AUC values for saxagliptin and its active metabolite were 78 ng•h/mL and 214 ng•h/mL, respectively.
The corresponding plasma C max values were 24 ng/mL and 47 ng/mL, respectively. The average variability (%CV) for AUC and C max for both saxagliptin and its active metabolite was less than 25%. No appreciable accumulation of either saxagliptin or its active metabolite was observed with repeated once-daily dosing at any dose level.
No dose- and time-dependence were observed in the clearance of saxagliptin and its active metabolite over 14 days of once-daily dosing with saxagliptin at doses ranging from 2.5 to 400 mg. Absorption The median time to maximum concentration (T max ) following the 5 mg once daily dose was 2 hours for saxagliptin and 4 hours for its active metabolite. Effect of Food Administration with a high-fat meal resulted in an increase in T max of saxagliptin by approximately 20 minutes as compared to fasted conditions.
There was a 27% increase in the AUC of saxagliptin when given with a meal as compared to fasted conditions. Saxagliptin tablets may be administered with or without food. Distribution The in vitro protein binding of saxagliptin and its active metabolite in human serum is negligible.
Therefore, changes in blood protein levels in various disease states (e.g., renal or hepatic impairment) are not expected to alter the disposition of saxagliptin. Elimination Metabolism The metabolism of saxagliptin is primarily mediated by cytochrome P450 3A4/5 (CYP3A4/5). The major metabolite of saxagliptin is also a DPP-4 inhibitor, which is one-half as potent as saxagliptin.
Therefore, strong CYP3A4/5 inhibitors and inducers will alter the pharmacokinetics of saxagliptin and its active metabolite [ see Drug Int…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Increased concentrations of the incretin hormones such as glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP) are released into the bloodstream from the small intestine in response to meals. These hormones cause insulin release from the pancreatic beta cells in a glucose-dependent manner but are inactivated by the DPP-4 enzyme within minutes. GLP-1 also lowers glucagon secretion from pancreatic alpha cells, reducing hepatic glucose production.
In patients with type 2 diabetes mellitus, concentrations of GLP-1 are reduced but the insulin response to GLP-1 is preserved. Saxagliptin is a competitive DPP-4 inhibitor that slows the inactivation of the incretin hormones, thereby increasing their bloodstream concentrations and reducing fasting and postprandial glucose concentrations in a glucose-dependent manner in patients with type 2 diabetes mellitus.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Saxagliptin Tablets are available containing 3.075 mg or 6.149 mg of saxagliptin hydrochloride dihydrate equivalent to 2.5 mg or 5 mg of saxagliptin. The 2.5 mg tablets are yellow, film-coated, round, unscored tablets imprinted with SX1 over M in black ink on one side of the tablet and blank on the other side. They are available as follows: NDC 0378-4705-93 bottles of 30 tablets NDC 0378-4705-77 bottles of 90 tablets The 5 mg tablets are white to off-white, film-coated, round, unscored tablets imprinted with SX2 over M in black ink on one side of the tablet and blank on the other side.
They are available as follows: NDC 0378-4706-93 bottles of 30 tablets NDC 0378-4706-77 bottles of 90 tablets Storage and Handling Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. PHARMACIST: Dispense a Medication Guide with each prescription.
📋 Description ▾
11 DESCRIPTION Saxagliptin is an orally-active inhibitor of the DPP-4 enzyme. Saxagliptin hydrochloride dihydrate is described chemically as (1S,3S,5S)-2-[(2S)-Amino-(3-hydroxytricyclo [3.3.1.1 3,7 ]dec-1-yl)acetyl]-2-azabicyclo[3.1.0] hexane-3-carbonitrile hydrochloride dihydrate or (1S,3S,5S)-2-[(2S)-2-Amino-2-(3-hydroxyadamantan-1-yl)acetyl]-2-azabicyclo [3.1.0] hexane-3-carbonitrile hydrochloride dihydrate. The empirical formula is C 18 H 25 N 3 O 2 •HCl•2H 2 O and the molecular weight is 387.92.
The structural formula is: Saxagliptin hydrochloride dihydrate is a white to off-white, non-hygroscopic, crystalline powder. It is sparingly soluble in water at 24°C ± 3°C, slightly soluble in ethyl acetate, and soluble in methanol, ethanol, isopropyl alcohol, acetonitrile, acetone, and polyethylene glycol 400 (PEG 400). Each film-coated tablet of saxagliptin for oral use contains either 3.075 mg saxagliptin hydrochloride dihydrate equivalent to 2.5 mg saxagliptin or 6.149 mg saxagliptin hydrochloride dihydrate equivalent to 5 mg saxagliptin and the following inactive ingredients: croscarmellose sodium, hydrochloric acid, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polyethylene glycol, polyvinyl alcohol, sodium hydroxide, talc and titanium dioxide.
The 2.5 mg tablets also contain yellow iron oxide. The imprinting ink contains ammonium hydroxide, black iron oxide, propylene glycol and shellac glaze. Saxagliptin Hydrochloride Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Pancreatitis Inform patients that acute pancreatitis has been reported during postmarketing use of saxagliptin tablets. Educate patients that persistent severe abdominal pain, sometimes radiating to the back, which may or may not be accompanied by vomiting, is the hallmark symptom of acute pancreatitis.
Instruct patients to promptly discontinue saxagliptin tablets and contact their health care provider if persistent severe abdominal pain occurs [ see Warnings and Precautions (5.1) ]. Heart Failure Inform patients of the signs and symptoms of heart failure. Before initiating saxagliptin tablets, ask patients if they have a history of heart failure or other risk factors for heart failure including moderate to severe renal impairment.
Instruct patients to contact their health care provider as soon as possible if they experience symptoms of heart failure, including increasing shortness of breath, rapid increase in weight or swelling of the feet [ see Warnings and Precautions (5.2) ]. Hypoglycemia with Concomitant Use with Insulin or Insulin Secretagogues Inform patients that hypoglycemia can occur, particularly when insulin or an insulin secretagogue is used in combination with saxagliptin tablets. Educate patients about the risks, symptoms and appropriate management of hypoglycemia [ see Warnings and Precautions (5.3) ].
Hypersensitivity Reactions Patients should be informed that serious allergic (hypersensitivity) reactions, such as angioedema, anaphylaxis, and exfoliative skin conditions, have been reported during postmarketing use of saxagliptin tablets. If symptoms of these allergic reactions (such as rash, skin flaking or peeling, urticaria, swelling of the skin, or swelling of the face, lips, tongue, and throat that may cause difficulty in breathing or swallowing) occur, patients must stop taking saxagliptin tablets and seek medical advice promptly [ see Warnings and Precautions (5.4) ].
Severe and Disabling Arthralgia Inform patients that severe and disabling joint pain may occur with this class of drugs. The time to onset of symptoms can range from one day to years. Instruct patients to seek medical advice if severe joint pain occurs [ see Warnings and Precautions (5.5) ].
Bullous Pemphigoid Inform patients that bullous pemphigoid may occur with this class of drugs. Instruct patients to seek medical advice if blisters or erosions occur [ see Warnings and Precautions (5.6) ]. Missed Dose If a dose is missed, advise patients to take saxagliptin tablets as soon as they remember unless it is time for their next dose.
Instruct patients not to take two doses of saxagliptin tablets at the same time. Administration Instructions Advise patients not to cut, crush, or chew saxagliptin tablets.
💬 Medication Guide ▾
Medication Guide Saxagliptin Tablets, for oral use (sax″ a glip′ tin) What is the most important information I should know about saxagliptin tablets? Serious side effects can happen to people taking saxagliptin tablets, including: 1. Inflammation of the pancreas (pancreatitis) which may be severe and lead to death.
Certain medical problems make you more likely to get pancreatitis. Before you start taking saxagliptin tablets: Tell your healthcare provider if you have ever had: • inflammation of your pancreas (pancreatitis) • a history of alcoholism • stones in your gallbladder (gallstones) • high blood triglyceride levels Stop taking saxagliptin tablets and contact your healthcare provider right away if you have pain in your stomach area (abdomen) that is severe and will not go away. The pain may be felt going from your abdomen through to your back.
The pain may happen with or without vomiting. These may be symptoms of pancreatitis. 2.
Heart failure. Heart failure means your heart does not pump blood well enough. Before you start taking saxagliptin tablets: Tell your healthcare provider if you: • have ever had heart failure or have problems with your kidneys.
Contact your healthcare provider right away if you have any of the following symptoms: • increasing shortness of breath or trouble breathing, especially when you lie down • swelling or fluid retention, especially in the feet, ankles or legs • an unusually fast increase in weight • unusual tiredness These may be symptoms of heart failure. What are saxagliptin tablets? • Saxagliptin tablets are a prescription medicine used along with diet and exercise to help control high blood sugar in adults with type 2 diabetes mellitus. • Saxagliptin tablets are not recommended for people with type 1 diabetes mellitus. • Saxagliptin tablets are not recommended for people with diabetic ketoacidosis (increased ketones in your blood or urine).
It is not known if saxagliptin tablets are safe and effective in children. Who should not take saxagliptin tablets? Do not take saxagliptin tablets if you: • are allergic to any ingredients in saxagliptin tablets.
See the end of this Medication Guide for a complete list of ingredients in saxagliptin tablets. Symptoms of a serious allergic reaction to saxagliptin tablets may include: • swelling of your face, lips, throat, and other areas on your skin • raised, red areas on your skin (hives) • difficulty with swallowing or breathing • skin rash, itching, flaking, or peeling If you have these symptoms, stop taking saxagliptin tablets and contact your healthcare provider right away. Before taking saxagliptin tablets, tell your healthcare provider about all of your medical conditions, including if you: • have heart failure • have or have had inflammation of your pancreas (pancreatitis) • have kidney problems. • are pregnant or plan to become pregnant.
It is not known if saxagliptin tablets will harm your unborn baby. If you are pregnant, talk with your healthcare provider about the best way to control your blood sugar while you are pregnant. • are breastfeeding or plan to breastfeed. Saxagliptin may be passed in your milk to your baby.
Talk with your healthcare provider about the best way to feed your baby while you take saxagliptin tablets. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. Know the medicines you take.
Keep a list of your medicines and show it to your healthcare provider and pharmacist when you get a new medicine. Saxagliptin tablets may affect the way other medicines work, and other medicines may affect how saxagliptin tablets work. Contact your healthcare provider if you will be starting or stopping certain other types of medicines, such as antibiotics, or medicines that treat fungus or HIV/AIDS, because your dose of saxagliptin tablets might need to be changed.
How should I take saxagliptin tablets? • Take saxagliptin tablets by mouth…