
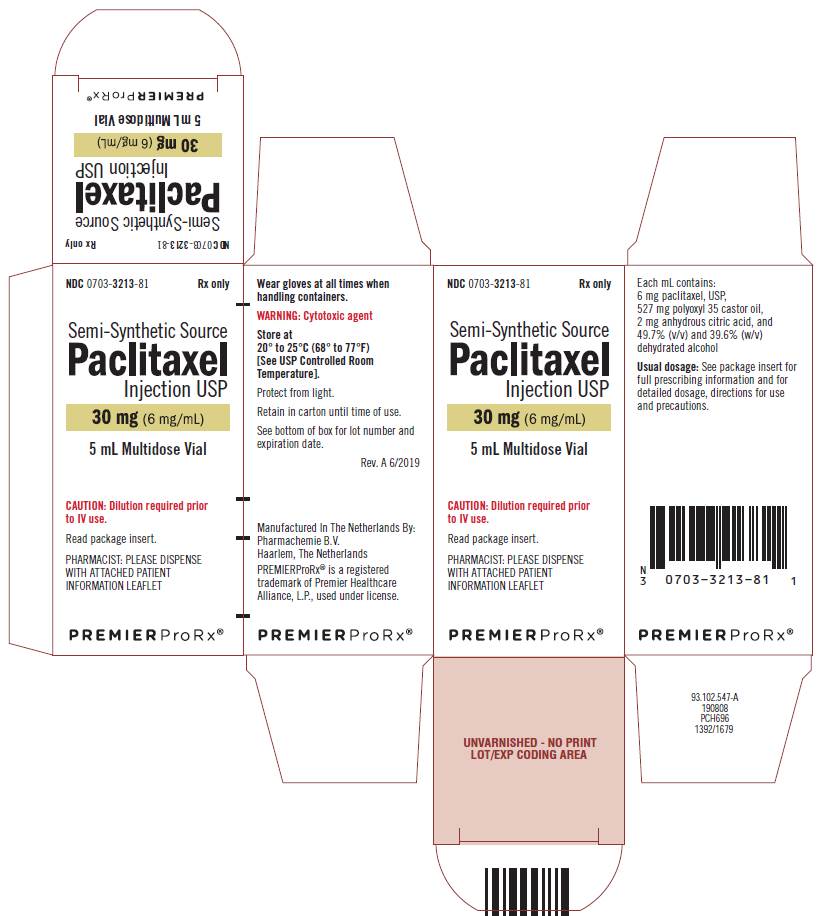
Paclitaxel 6 mg/mL Injection, Solution, Concentrate
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Microtubule Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Paclitaxel can trigger serious — sometimes life-threatening — allergic reactions, including anaphylaxis. Receiving antihistamines, steroids, and acid-blocking medicines before your...
- Why is it so important that I get pre-medications before my paclitaxel infusion?
- Paclitaxel lowers the number of white blood cells — especially neutrophils, the ones that fight infection — and this is the most common serious side effect. If your counts drop too...
- Why do they keep checking my blood counts before every treatment?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Paclitaxel — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII 6D4M1DAL6O
Polyoxyl 35 castor oil is a synthetic compound made by chemically treating castor oil. It works as a solubilizer and emulsifier to help dissolve and evenly mix oily and water-based ingredients in medicines.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $0.9576 | $4.79 / 5 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9267 | $0.112 / J9267 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Paclitaxel 6 mg/mLthis 00703-3213-81 | Teva | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 00703-3216-81 | Teva | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 00703-3217-01 | Teva | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 00703-3218-81 | Teva | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 16714-0137-01 | Northstar | 1 vial | — | AP | FDA listed | — |
| Paclitaxel Paclitaxel 6 mg/mL 23155-0882-31 | Heritage | 1 vial | — | AP | FDA listed | — |
| Paclitaxel Paclitaxel 6 mg/mL 23155-0883-31 | Heritage | 1 vial | — | AP | FDA listed | — |
| Paclitaxel Paclitaxel 6 mg/mL 23155-0884-31 | Heritage | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 25021-0255-05 | Sagent | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 46708-0620-05 | Alembic | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 46708-0621-17 | Alembic | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 46708-0622-50 | Alembic | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 61703-0015-04 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 61703-0342-09 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 62332-0620-05 | Alembic | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 62332-0621-17 | Alembic | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 62332-0622-50 | Alembic | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 63323-0763-05 | Fresenius | 1 vial | — | AP | Discontinued | — |
| Paclitaxel 6 mg/mL 68001-0516-27 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 68001-0705-27 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Paclitaxel Paclitaxel 6 mg/mL 68083-0178-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Paclitaxel Paclitaxel 6 mg/mL 68083-0179-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Paclitaxel Paclitaxel 6 mg/mL 68083-0180-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 69339-0227-05 | Natco | 1 vial | — | — | FDA listed | — |
| Paclitaxel 6 mg/mL 69339-0228-17 | Natco | 1 vial | — | — | FDA listed | — |
| Paclitaxel 6 mg/mL 69339-0229-50 | Natco | 1 vial | — | — | FDA listed | — |
| Paclitaxel 6 mg/mL 72162-2640-02 | Bryant | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 72205-0061-01 | Novadoz | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 72205-0062-01 | Novadoz | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 72205-0063-01 | Novadoz | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00703-3213-81 You're viewing this | 1 VIAL, MULTI-DOSE in 1 CARTON (0703-3213-81) / 5 mL in 1 VIAL, MULTI-DOSE | 2020-07-07 | Active |
| 00703-3213-01 | 1 VIAL, MULTI-DOSE in 1 CARTON (0703-3213-01) / 5 mL in 1 VIAL, MULTI-DOSE | 2020-07-07 | Active |
This pack accounts for about 5.3% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 00703-3213-81?
What NDC number is used to bill for this package of Paclitaxel 6 mg/mL Injection, Solution, Concentrate?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING Paclitaxel injection should be administered under the supervision of a physician experienced in the use of cancer chemotherapeutic agents. Appropriate management of complications is possible only when adequate diagnostic and treatment facilities are readily available. Anaphylaxis and severe hypersensitivity reactions characterized by dyspnea and hypotension requiring treatment, angioedema, and generalized urticaria have occurred in 2 to 4% of patients receiving paclitaxel in clinical trials.
Fatal reactions have occurred in patients despite premedication. All patients should be pretreated with corticosteroids, diphenhydramine, and H 2 antagonists (see DOSAGE AND ADMINISTRATION ). Patients who experience severe hypersensitivity reactions to paclitaxel injection should not be rechallenged with the drug.
Paclitaxel injection therapy should not be given to patients with solid tumors who have baseline neutrophil counts of less than 1500 cells/mm 3 and should not be given to patients with AIDS-related Kaposi’s sarcoma if the baseline neutrophil count is less than 1000 cells/mm 3 . In order to monitor the occurrence of bone marrow suppression, primarily neutropenia, which may be severe and result in infection, it is recommended that frequent peripheral blood cell counts be performed on all patients receiving paclitaxel injection.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Paclitaxel Injection USP is indicated as subsequent therapy for the treatment of advanced carcinoma of the ovary. As first-line therapy, paclitaxel injection is indicated in combination with cisplatin. Paclitaxel Injection USP is indicated for the adjuvant treatment of node-positive breast cancer administered sequentially to standard doxorubicin-containing combination chemotherapy.
In the clinical trial, there was an overall favorable effect on disease-free and overall survival in the total population of patients with receptor-positive and receptor-negative tumors, but the benefit has been specifically demonstrated by available data (median follow-up 30 months) only in the patients with estrogen and progesterone receptor-negative tumors (see CLINICAL STUDIES, Breast Carcinoma ). Paclitaxel Injection USP is indicated for the treatment of breast cancer after failure of combination chemotherapy for metastatic disease or relapse within 6 months of adjuvant chemotherapy.
Prior therapy should have included an anthracycline unless clinically contraindicated. Paclitaxel Injection USP, in combination with cisplatin, is indicated for the first-line treatment of non-small cell lung cancer in patients who are not candidates for potentially curative surgery and/or radiation therapy. Paclitaxel Injection USP is indicated for the second-line treatment of AIDS-related Kaposi’s sarcoma.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Note: Contact of the undiluted concentrate with plasticized PVC equipment or devices used to prepare solutions for infusion is not recommended. In order to minimize patient exposure to the plasticizer DEHP [di-(2-ethylhexyl)phthalate], which may be leached from PVC infusion bags or sets, diluted paclitaxel injection solutions should be stored in bottles (glass, polypropylene) or plastic bags (polypropylene, polyolefin) and administered through polyethylene-lined administration sets. All patients should be premedicated prior to paclitaxel injection administration in order to prevent severe hypersensitivity reactions.
Such premedication may consist of dexamethasone 20 mg PO administered approximately 12 and 6 hours before paclitaxel injection, diphenhydramine (or its equivalent) 50 mg IV 30 to 60 minutes prior to paclitaxel injection, and cimetidine (300 mg) or ranitidine (50 mg) IV 30 to 60 minutes before paclitaxel injection. For patients with carcinoma of the ovary , the following regimens are recommended (see CLINICAL STUDIES, Ovarian Carcinoma ): 1) For previously untreated patients with carcinoma of the ovary, one of the following recommended regimens may be given every 3 weeks.
In selecting the appropriate regimen, differences in toxicities should be considered (see TABLE 11 in ADVERSE REACTIONS, Disease-Specific Adverse Event Experiences ). Paclitaxel injection administered intravenously over 3 hours at a dose of 175 mg/m 2 followed by cisplatin at a dose of 75 mg/m 2 ; or Paclitaxel injection administered intravenously over 24 hours at a dose of 135 mg/m 2 followed by cisplatin at a dose of 75 mg/m 2 . 2) In patients previously treated with chemotherapy for carcinoma of the ovary, paclitaxel injection has been used at several doses and schedules; however, the optimal regimen is not yet clear (see CLINICAL STUDIES, Ovarian Carcinoma ).
The recommended regimen is paclitaxel injection 135 mg/m 2 or 175 mg/m 2 administered intravenously over 3 hours every 3 weeks. For patients with carcinoma of the breast , the following is recommended (see CLINICAL STUDIES, Breast Carcinoma ): 1) For the adjuvant treatment of node-positive breast cancer, the recommended regimen is paclitaxel injection, at a dose of 175 mg/m 2 intravenously over 3 hours every 3 weeks for 4 courses administered sequentially to doxorubicin-containing combination chemotherapy. The clinical trial used 4 courses of doxorubicin and cyclophosphamide (see CLINICAL STUDIES, Breast Carcinoma ).
2) After failure of initial chemotherapy for metastatic disease or relapse within 6 months of adjuvant chemotherapy, paclitaxel injection at a dose of 175 mg/m 2 administered intravenously over 3 hours every 3 weeks has been shown to be effective. For patients with non-small cell lung carcinoma , the recommended regimen, given every 3 weeks, is paclitaxel injection administered intravenously over 24 hours at a dose of 135 mg/m 2 followed by cisplatin, 75 mg/m 2 . For patients with AIDS-related Kaposi’s sarcoma , paclitaxel injection administered at a dose of 135 mg/m 2 given intravenously over 3 hours every 3 weeks or at a dose of 100 mg/m 2 given intravenously over 3 hours every 2 weeks is recommended (dose intensity 45 to 50 mg/m 2 /week).
In the 2 clinical trials evaluating these schedules (see CLINICAL STUDIES, AIDS-Related Kaposi’s Sarcoma ), the former schedule (135 mg/m 2 every 3 weeks) was more toxic than the latter. In addition, all patients with low performance status were treated with the latter schedule (100 mg/m 2 every 2 weeks). Based upon the immunosuppression in patients with advanced HIV disease, the following modifications are recommended in these patients: 1) Reduce the dose of dexamethasone as 1 of the 3 premedication drugs to 10 mg PO (instead of 20 mg PO); 2) Initiate or repeat treatment with paclitaxel injection only if the neutrophil count is at least 1000 cells/mm 3 ; 3) Reduce the dose of subsequent courses of paclitaxel inje…
⛔ Contraindications ▾
CONTRAINDICATIONS Paclitaxel injection is contraindicated in patients who have a history of hypersensitivity reactions to paclitaxel injection or other drugs formulated in polyoxyl 35 castor oil, NF. Paclitaxel injection should not be used in patients with solid tumors who have baseline neutrophil counts of < 1500 cells/mm 3 or in patients with AIDS-related Kaposi’s sarcoma with baseline neutrophil counts of < 1000 cells/mm 3 .
⚠️ Warnings ▾
WARNINGS Anaphylaxis and severe hypersensitivity reactions characterized by dyspnea and hypotension requiring treatment, angioedema, and generalized urticaria have occurred in 2 to 4% of patients receiving paclitaxel in clinical trials. Fatal reactions have occurred in patients despite premedication. All patients should be pretreated with corticosteroids, diphenhydramine, and H 2 antagonists (see DOSAGE AND ADMINISTRATION ).
Patients who experience severe hypersensitivity reactions to paclitaxel injection should not be rechallenged with the drug. Bone marrow suppression (primarily neutropenia) is dose-dependent and is the dose-limiting toxicity. Neutrophil nadirs occurred at a median of 11 days.
Paclitaxel injection should not be administered to patients with baseline neutrophil counts of less than 1500 cells/mm 3 (< 1000 cells/mm 3 for patients with KS). Frequent monitoring of blood counts should be instituted during paclitaxel injection treatment. Patients should not be re-treated with subsequent cycles of paclitaxel injection until neutrophils recover to a level > 1500 cells/mm 3 (> 1000 cells/mm 3 for patients with KS) and platelets recover to a level > 100,000 cells/mm 3 .
Severe conduction abnormalities have been documented in < 1% of patients during paclitaxel injection therapy and in some cases requiring pacemaker placement. If patients develop significant conduction abnormalities during paclitaxel infusion, appropriate therapy should be administered and continuous cardiac monitoring should be performed during subsequent therapy with paclitaxel injection. Pregnancy Paclitaxel injection can cause fetal harm when administered to a pregnant woman.
Administration of paclitaxel during the period of organogenesis to rabbits at doses of 3 mg/kg/day (about 0.2 the daily maximum recommended human dose on a mg/m 2 basis) caused embryo- and fetotoxicity, as indicated by intrauterine mortality, increased resorptions, and increased fetal deaths. Maternal toxicity was also observed at this dose. No teratogenic effects were observed at 1 mg/kg/day (about 1/15 the daily maximum recommended human dose on a mg/m 2 basis); teratogenic potential could not be assessed at higher doses due to extensive fetal mortality.
There are no adequate and well-controlled studies in pregnant women. If paclitaxel injection is used during pregnancy, or if the patient becomes pregnant while receiving this drug, the patient should be apprised of the potential hazard to the fetus. Women of childbearing potential should be advised to avoid becoming pregnant.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Pooled Analysis of Adverse Event Experiences from Single-Agent Studies Data in the following table are based on the experience of 812 patients (493 with ovarian carcinoma and 319 with breast carcinoma) enrolled in 10 studies who received single-agent paclitaxel. Two hundred and seventy-five patients were treated in 8, Phase 2 studies with paclitaxel doses ranging from 135 to 300 mg/m 2 administered over 24 hours (in 4 of these studies, G-CSF was administered as hematopoietic support). Three hundred and one patients were treated in the randomized Phase 3 ovarian carcinoma study which compared 2 doses (135 or 175 mg/m 2 ) and 2 schedules (3 or 24 hours) of paclitaxel.
Two hundred and thirty-six patients with breast carcinoma received paclitaxel (135 or 175 mg/m 2 ) administered over 3 hours in a controlled study. TABLE 10: SUMMARY a OF ADVERSE EVENTS IN PATIENTS WITH SOLID TUMORS RECEIVING SINGLE-AGENT PACLITAXEL Percent of Patients (n = 812) • Bone Marrow —Neutropenia < 2000/mm 3 90 < 500/mm 3 52 —Leukopenia < 4000/mm 3 90 < 1000/mm 3 17 —Thrombocytopenia < 100,000/mm 3 20 < 50,000/mm 3 7 —Anemia < 11 g/dL 78 < 8 g/dL 16 —Infections 30 —Bleeding 14 —Red Cell Transfusions 25 —Platelet Transfusions 2 • Hypersensitivity Reaction b —All 41 —Severe † 2 • Cardiovascular —Vital Sign Changes c —Bradycardia (n = 537) 3 —Hypotension (n = 532) 12 —Significant Cardiovascular Events 1 • Abnormal ECG —All Pts 23 —Pts with normal baseline (n = 559) 14 • Peripheral Neuropathy —Any symptoms 60 —Severe symptoms † 3 • Myalgia/Arthralgia —Any symptoms 60 —Severe symptoms † 8 • Gastrointestinal —Nausea and vomiting 52 —Diarrhea 38 —Mucositis 31 • Alopecia 87 • Hepatic (Pts with normal baseline and on study data) —Bilirubin elevations (n = 765) 7 —Alkaline phosphatase elevations (n = 575) 22 —AST (SGOT) elevations (n = 591) 19 • Injection Site Reaction 13 a Based on worst course analysis. b All patients received premedication. c During the first 3 hours of infusion. † Severe events are defined as at least Grade III toxicity.
None of the observed toxicities were clearly influenced by age. Disease-Specific Adverse Event Experiences First-Line Ovary in Combination For the 1084 patients who were evaluable for safety in the Phase 3 first-line ovary combination therapy studies, TABLE 11 shows the incidence of important adverse events. For both studies, the analysis of safety was based on all courses of therapy (6 courses for the GOG-111 study and up to 9 courses for the Intergroup study).
TABLE 11: FREQUENCY a OF IMPORTANT ADVERSE EVENTS IN THE PHASE 3 FIRST-LINE OVARIAN CARCINOMA STUDIES Percent of Patients Intergroup GOG-111 T175/3 b c75 c (n = 339) C750 c c75 c (n = 336) T135/24 b c75 c (n = 196) C750 c c75 c (n = 213) • Bone Marrow —Neutropenia < 2000/mm 3 91 d 95 d 96 92 < 500/mm 3 33 d 43 d 81 d 58 d —Thrombocytopenia < 100,000/mm 3e 21 d 33 d 26 30 < 50,000/mm 3 3 d 7 d 10 9 —Anemia < 11 g/dL f 96 97 88 86 < 8 g/dL 3 d 8 d 13 9 —Infections 25 27 21 15 —Febrile Neutropenia 4 7 15 d 4 d • Hypersensitivity Reaction —All 11 d 6 d 8 d,g 1 d,g —Severe † 1 1 3 d,g — d,g • Neurotoxicity h —Any symptoms 87 d 52 d 25 20 —Severe symptoms † 21 d 2 d 3 d — d • Nausea and Vomiting —Any symptoms 88 93 65 69 —Severe symptoms † 18 24 10 11 • Myalgia/Arthralgia —Any symptoms 60 d 27 d 9 d 2 d —Severe symptoms † 6 d 1 d 1 — • Diarrhea —Any symptoms 37 d 29 d 16 d 8 d —Severe symptoms † 2 3 4 1 • Asthenia —Any symptoms NC NC 17 d 10 d —Severe symptoms † NC NC 1 1 • Alopecia —Any symptoms 96 d 89 d 55 d 37 d —Severe symptoms † 51 d 21 d 6 8 a Based on worst course analysis. b Paclitaxel (T) dose in mg/m 2 /infusion duration in hours. c Cyclophosphamide (C) or cisplatin (c) dose in mg/m 2 . d p < 0.05 by Fisher exact test. e < 130,000/mm 3 in the Intergroup study. f < 12 g/dL in the Intergroup study. g All patients received premedication. h In the GOG-111 study, neurotoxicity was collected as peripheral neuropathy and in the Intergroup study, neurotoxi…
🆘 Overdosage ▾
OVERDOSAGE There is no known antidote for paclitaxel injection overdosage. The primary anticipated complications of overdosage would consist of bone marrow suppression, peripheral neurotoxicity, and mucositis. Overdoses in pediatric patients may be associated with acute ethanol toxicity (see PRECAUTIONS, Pediatric Use ).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Paclitaxel is a novel antimicrotubule agent that promotes the assembly of microtubules from tubulin dimers and stabilizes microtubules by preventing depolymerization. This stability results in the inhibition of the normal dynamic reorganization of the microtubule network that is essential for vital interphase and mitotic cellular functions. In addition, paclitaxel induces abnormal arrays or “bundles” of microtubules throughout the cell cycle and multiple asters of microtubules during mitosis.
Following intravenous administration of paclitaxel, paclitaxel plasma concentrations declined in a biphasic manner. The initial rapid decline represents distribution to the peripheral compartment and elimination of the drug. The later phase is due, in part, to a relatively slow efflux of paclitaxel from the peripheral compartment.
Pharmacokinetic parameters of paclitaxel following 3 and 24 hour infusions of paclitaxel at dose levels of 135 and 175 mg/m 2 were determined in a Phase 3 randomized study in ovarian cancer patients and are summarized in the following table. TABLE 1: SUMMARY OF PHARMACOKINETIC PARAMETERS—MEAN VALUES Dose (mg/m 2 ) Infusion Duration (h) N (patients) C max (ng/mL) AUC (0-∞) (ng•h/mL) T-HALF (h) CL T (L/h/m 2 ) 135 24 2 195 6300 52.7 21.7 175 24 4 365 7993 15.7 23.8 135 3 7 2170 7952 13.1 17.7 175 3 5 3650 15007 20.2
12.2C max = Maximum plasma concentration AUC (0-∞) = Area under the plasma concentration-time curve from time 0 to infinity CL T = Total body clearance It appeared that with the 24 hour infusion of paclitaxel, a 30% increase in dose (135 mg/m 2 vs. 175 mg/m 2 ) increased the C max by 87%, whereas the AUC (0-∞) remained proportional. However, with a 3 hour infusion, for a 30% increase in dose, the C max and AUC (0-∞) were increased by 68% and 89%, respectively.
The mean apparent volume of distribution at steady state, with the 24 hour infusion of paclitaxel, ranged from 227 to 688 L/m 2 , indicating extensive extravascular distribution and/or tissue binding of paclitaxel. The pharmacokinetics of paclitaxel were also evaluated in adult cancer patients who received single doses of 15 to 135 mg/m 2 given by 1 hour infusions (n = 15), 30 to 275 mg/m 2 given by 6 hour infusions (n = 36), and 200 to 275 mg/m 2 given by 24 hour infusions (n = 54) in Phase 1 and 2 studies. Values for CL T and volume of distribution were consistent with the findings in the Phase 3 study.
The pharmacokinetics of paclitaxel in patients with AIDS-related Kaposi’s sarcoma have not been studied. In vitro studies of binding to human serum proteins, using paclitaxel concentrations ranging from 0.1 to 50 mcg/mL, indicate that between 89 to 98% of drug is bound; the presence of cimetidine, ranitidine, dexamethasone, or diphenhydramine did not affect protein binding of paclitaxel. After intravenous administration of 15 to 275 mg/m 2 doses of paclitaxel as 1, 6, or 24 hour infusions, mean values for cumulative urinary recovery of unchanged drug ranged from 1.3% to 12.6% of the dose, indicating extensive non-renal clearance.
In 5 patients administered a 225 or 250 mg/m 2 dose of radiolabeled paclitaxel as a 3 hour infusion, a mean of 71% of the radioactivity was excreted in the feces in 120 hours, and 14% was recovered in the urine. Total recovery of radioactivity ranged from 56% to 101% of the dose. Paclitaxel represented a mean of 5% of the administered radioactivity recovered in the feces, while metabolites, primarily 6α-hydroxypaclitaxel, accounted for the balance.
In vitro studies with human liver microsomes and tissue slices showed that paclitaxel was metabolized primarily to 6α-hydroxypaclitaxel by the cytochrome P450 isozyme CYP2C8; and to 2 minor metabolites, 3′- p -hydroxypaclitaxel and 6α, 3′- p -dihydroxypaclitaxel, by CYP3A4. In vitro , the metabolism of paclitaxel to 6α-hydroxypaclitaxel was inhibited by a number of agents (ketoconazole, verapamil, diazepam, quinidine, dexamethasone, cyclosporin, tenipos…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Paclitaxel Injection USP is available as follows: NDC 0703- 3213 -81 30 mg/5 mL Carton containing 1 multiple-dose vial. NDC 0703- 3216 -81 100 mg/16.7 mL Carton containing 1 multiple-dose vial. NDC 0703- 3218 -81 300 mg/50 mL Carton containing 1 multiple-dose vial.
Storage Store the vials in original cartons at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Retain in the original package to protect from light. Handling and Disposal See DOSAGE AND ADMINISTRATION, Preparation and Administration Precautions .
📋 Description ▾
DESCRIPTION Paclitaxel Injection USP is a clear, colorless to slightly yellow viscous solution. It is supplied as a nonaqueous solution intended for dilution with a suitable parenteral fluid prior to intravenous infusion. Paclitaxel Injection USP is available in 30 mg (5 mL), 100 mg (16.7 mL), and 300 mg (50 mL) multidose vials.
Each mL of sterile nonpyrogenic solution contains 6 mg paclitaxel, USP, 527 mg of polyoxyl 35 castor oil, 2 mg of anhydrous citric acid, and 49.7% (v/v) and 39.6% (w/v) dehydrated alcohol. Paclitaxel, USP is a semi-synthetic product with antitumor activity. Paclitaxel, USP is obtained from Taxus species.
The chemical name for paclitaxel, USP is 5β,20-Epoxy-1,2α,4,7β,10β,13α-hexahydroxytax-11-en-9-one 4,10-diacetate 2-benzoate 13-ester with (2 R ,3 S )- N -benzoyl-3-phenylisoserine. Paclitaxel, USP has the following structural formula: C 47 H 51 NO 14 M.W. 853.9 Paclitaxel, USP is a white to off-white crystalline powder.
It is highly lipophilic, insoluble in water, and melts at around 216 to 217° C. structural formula