
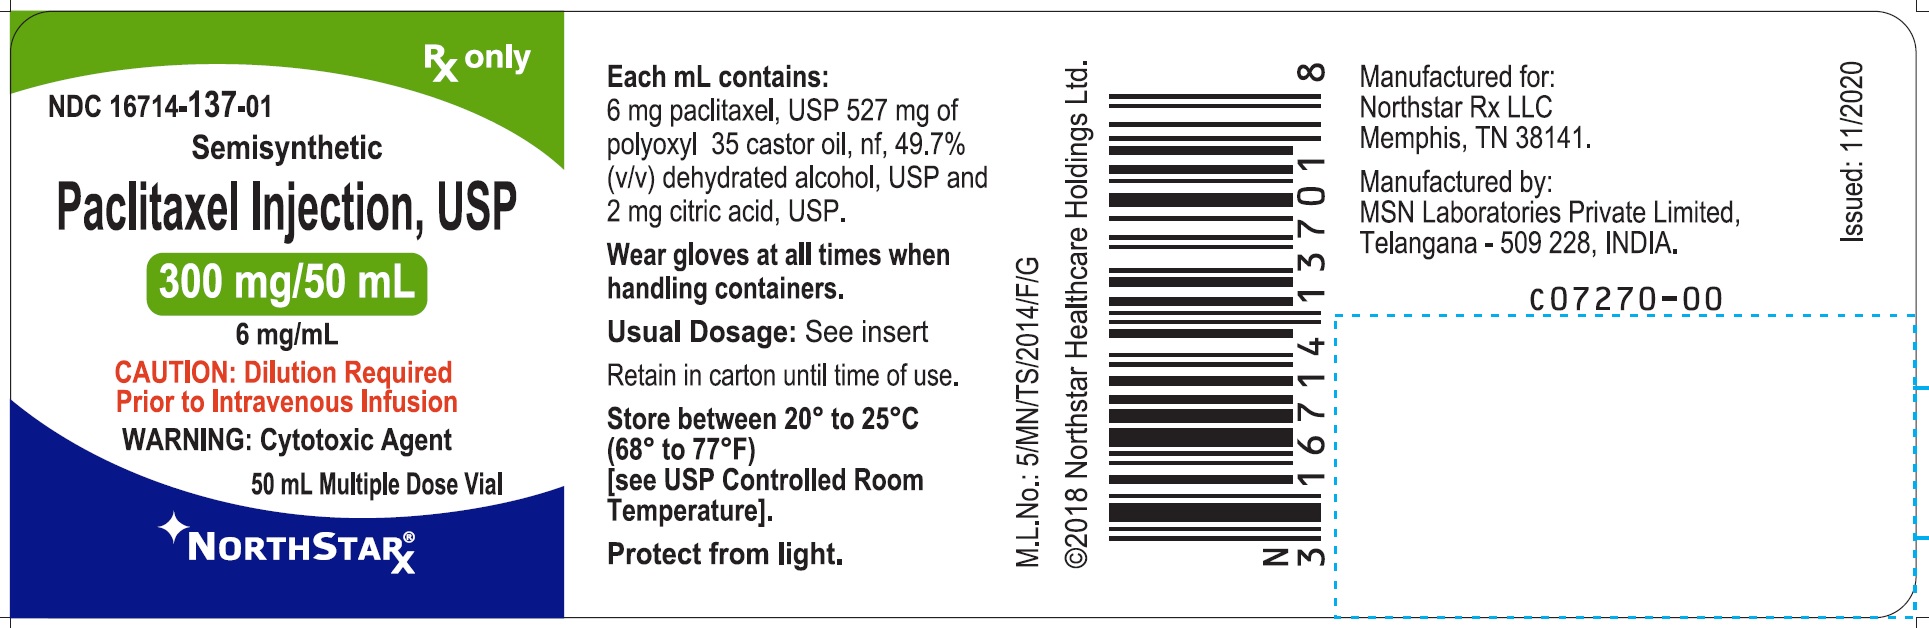
Paclitaxel 6 mg/mL Injection, Solution — NDC 16714-137-01 (Billing 16714-0137-01)
This is a package of Paclitaxel 6 mg/mL Injection, Solution from Northstar Rx LLC, marketed since Jan 2021 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 16714-137-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 16714 labeler · 137 product · 01 package
- Package marketed since
- Jan 25, 2021
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC)
- 0316714137018
- Medicaid fills, this package
- 7,018 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 046997
- GCN: 85602
- GPI-14 (Medi-Span): 21500012001350
- HICL (First Databank): 007625
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 312199
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Microtubule Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Paclitaxel can only be given intravenously — there's no pill form. It needs to get directly into your bloodstream to reach cancer cells throughout the body effectively. Your infusi...
- Why is paclitaxel given as an IV infusion instead of a pill?
- Yes, it matters a lot. Standard paclitaxel injection and albumin-bound paclitaxel (such as Abraxane) are not interchangeable — they work differently in the body, are approved for d...
- I've heard there are different 'versions' of paclitaxel — does it matter which one I get?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Paclitaxel — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $1.75 | $87.31 / 50 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9267 | $0.112 / J9267 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 16714-0137-01 You're viewing this Main listing | 1 VIAL, MULTI-DOSE in 1 CARTON / 50 mL in 1 VIAL, MULTI-DOSE | 2021-01-25 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Paclitaxel 6 mg/mL 00703-3213-81 | Teva | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 00703-3216-81 | Teva | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 00703-3217-01 | Teva | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 00703-3218-81 | Teva | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mLthis 16714-0137-01 | Northstar | 1 vial | — | AP | FDA listed | — |
| Paclitaxel Paclitaxel 6 mg/mL 23155-0882-31 | Heritage | 1 vial | — | AP | FDA listed | — |
| Paclitaxel Paclitaxel 6 mg/mL 23155-0883-31 | Heritage | 1 vial | — | AP | FDA listed | — |
| Paclitaxel Paclitaxel 6 mg/mL 23155-0884-31 | Heritage | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 25021-0255-05 | Sagent | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 46708-0620-05 | Alembic | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 46708-0621-17 | Alembic | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 46708-0622-50 | Alembic | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 61703-0015-04 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 61703-0342-09 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 62332-0620-05 | Alembic | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 62332-0621-17 | Alembic | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 62332-0622-50 | Alembic | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 63323-0763-05 | Fresenius | 1 vial | — | AP | Discontinued | — |
| Paclitaxel 6 mg/mL 68001-0516-27 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 68001-0705-27 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Paclitaxel Paclitaxel 6 mg/mL 68083-0178-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Paclitaxel Paclitaxel 6 mg/mL 68083-0179-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Paclitaxel Paclitaxel 6 mg/mL 68083-0180-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 69339-0227-05 | Natco | 1 vial | — | — | FDA listed | — |
| Paclitaxel 6 mg/mL 69339-0228-17 | Natco | 1 vial | — | — | FDA listed | — |
| Paclitaxel 6 mg/mL 69339-0229-50 | Natco | 1 vial | — | — | FDA listed | — |
| Paclitaxel 6 mg/mL 72162-2640-02 | Bryant | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 72205-0061-01 | Novadoz | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 72205-0062-01 | Novadoz | 1 vial | — | AP | FDA listed | — |
| Paclitaxel 6 mg/mL 72205-0063-01 | Novadoz | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII D5340Y2I9G
Castor oil is a natural plant-based oil used in medicines as a lubricant, laxative agent, and solvent. It helps medicine ingredients dissolve or flow smoothly and can aid bowel movement in formulations designed for that purpose.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII 6D4M1DAL6O
Polyoxyl 35 castor oil is a synthetic compound made by chemically treating castor oil. It works as a solubilizer and emulsifier to help dissolve and evenly mix oily and water-based ingredients in medicines.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Northstar Rx LLC labeler code 16714
- Tobramycin Inhalation Solution 300 mg/5mL Inhalant NDC 16714-119-03
- Omeprazole 40 mg Capsule, Delayed Release NDC 16714-123-01
- Chlorthalidone 25 mg Tablet NDC 16714-128-01
- Chlorthalidone 50 mg Tablet NDC 16714-129-01
- Triamcinolone Acetonide 40 mg/mL Injection, Suspension NDC 16714-130-01
- Irinotecan hydrochloride 20 mg/mL Injection NDC 16714-131-01
- Triamcinolone Acetonide 200 mg/5mL Injection, Suspension NDC 16714-140-01
- Aripiprazole 2 mg Tablet NDC 16714-141-01
- Aripiprazole 5 mg Tablet NDC 16714-142-01
- Aripiprazole 10 mg Tablet NDC 16714-143-01
- Aripiprazole 15 mg Tablet NDC 16714-144-01
- Aripiprazole 20 mg Tablet NDC 16714-145-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING Paclitaxel should be administered under the supervision of a physician experienced in the use of cancer chemotherapeutic agents. Appropriate management of complications is possible only when adequate diagnostic and treatment facilities are readily available. Anaphylaxis and severe hypersensitivity reactions characterized by dyspnea and hypotension requiring treatment, angioedema, and generalized urticaria have occurred in 2 to 4% of patients receiving paclitaxel in clinical trials.
Fatal reactions have occurred in patients despite premedication. All patients should be pretreated with corticosteroids, diphenhydramine, and H 2 antagonists (see DOSAGE AND ADMINISTRATION ). Patients who experience severe hypersensitivity reactions to paclitaxel should not be rechallenged with the drug.
Paclitaxel therapy should not be given to patients with solid tumors who have baseline neutrophil counts of less than 1,500 cells/mm 3 and should not be given to patients with AIDS-related Kaposi's sarcoma if the baseline neutrophil count is less than 1,000 cells/mm 3 . In order to monitor the occurrence of bone marrow suppression, primarily neutropenia, which may be severe and result in infection, it is recommended that frequent peripheral blood cell counts be performed on all patients receiving paclitaxel.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Paclitaxel Injection, USP is indicated as subsequent therapy for the treatment of advanced carcinoma of the ovary. As first-line therapy, Paclitaxel Injection, USP is indicated in combination with cisplatin. Paclitaxel Injection, USP is indicated for the adjuvant treatment of node-positive breast cancer administered sequentially to standard doxorubicin-containing combination chemotherapy.
In the clinical trial, there was an overall favorable effect on disease-free and overall survival in the total population of patients with receptor-positive and receptor-negative tumors, but the benefit has been specifically demonstrated by available data (median follow-up 30 months) only in the patients with estrogen and progesterone receptor-negative tumors ( see CLINICAL STUDIES: Breast Carcinoma ). Paclitaxel Injection, USP is indicated for the treatment of breast cancer after failure of combination chemotherapy for metastatic disease or relapse within 6 months of adjuvant chemotherapy.
Prior therapy should have included an anthracycline unless clinically contraindicated. Paclitaxel Injection, USP, in combination with cisplatin, is indicated for the first-line treatment of non-small cell lung cancer in patients who are not candidates for potentially curative surgery and/or radiation therapy. Paclitaxel Injection, USP is indicated for the second-line treatment of AIDS-related Kaposi's sarcoma.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Note: Contact of the undiluted concentrate with plasticized PVC equipment or devices used to prepare solutions for infusion is not recommended. In order to minimize patient exposure to the plasticizer DEHP [di-(2-ethylhexyl)phthalate], which may be leached from PVC infusion bags or sets, diluted paclitaxel solutions should be stored in bottles (glass, polypropylene) or plastic bags (polypropylene, polyolefin) and administered through polyethylene-lined administration sets. All patients should be premedicated prior to paclitaxel administration in order to prevent severe hypersensitivity reactions.
Such premedication may consist of dexamethasone 20 mg PO administered approximately 12 and 6 hours before paclitaxel, diphenhydramine (or its equivalent) 50 mg I.V. 30 to 60 minutes prior to paclitaxel, and cimetidine (300 mg) or ranitidine (50 mg) I.V. 30 to 60 minutes before paclitaxel.
For patients with carcinoma of the ovary , the following regimens are recommended (see CLINICAL STUDIES, Ovarian Carcinoma ): 1) For previously untreated patients with carcinoma of the ovary, one of the following recommended regimens may be given every 3 weeks. In selecting the appropriate regimen, differences in toxicities should be considered (see TABLE 11 in ADVERSE REACTIONS, Disease-Specific Adverse Event Experiences ). a. Paclitaxel administered intravenously over 3 hours at a dose of 175 mg/m 2 followed by cisplatin at a dose of 75 mg/m 2 ; or b.
Paclitaxel administered intravenously over 24 hours at a dose of 135 mg/m 2 followed by cisplatin at a dose of 75 mg/m 2 . 2) In patients previously treated with chemotherapy for carcinoma of the ovary, paclitaxel has been used at several doses and schedules; however, the optimal regimen is not yet clear (see CLINICAL STUDIES, Ovarian Carcinoma ). The recommended regimen is paclitaxel 135 mg/m 2 or 175 mg/m 2 administered intravenously over 3 hours every 3 weeks.
For patients with carcinoma of the breast , the following regimens are recommended (see CLINICAL STUDIES, Breast Carcinoma): 1) For the adjuvant treatment of node-positive breast cancer, the recommended regimen is paclitaxel, at a dose of 175 mg/m 2 intravenously over 3 hours every 3 weeks for 4 courses administered sequentially to doxorubicin-containing combination chemotherapy. The clinical trial used 4 courses of doxorubicin and cyclophosphamide (see CLINICAL STUDIES, Breast Carcinoma ). 2) After failure of initial chemotherapy for metastatic disease or relapse within 6 months of adjuvant chemotherapy, paclitaxel at a dose of 175 mg/m 2 administered intravenously over 3 hours every 3 weeks has been shown to be effective.
For patients with non-small cell lung carcinoma , the recommended regimen, given every 3 weeks, is paclitaxel administered intravenously over 24 hours at a dose of 135 mg/m 2 followed by cisplatin, 75 mg/m 2 . For patients with AIDS-related Kaposi's sarcoma , paclitaxel administered at a dose of 135 mg/m 2 given intravenously over 3 hours every 3 weeks or at a dose of 100 mg/m 2 given intravenously over 3 hours every 2 weeks is recommended (dose intensity 45 to 50 mg/m 2 /week). In the 2 clinical trials evaluating these schedules (see CLINICAL STUDIES, AIDS-Related Kaposi's Sarcoma ), the former schedule (135 mg/m 2 every 3 weeks) was more toxic than the latter.
In addition, all patients with low performance status were treated with the latter schedule (100 mg/m 2 every 2 weeks). Based upon the immunosuppression in patients with advanced HIV disease, the following modifications are recommended in these patients: 1) Reduce the dose of dexamethasone as 1 of the 3 premedication drugs to 10 mg PO (instead of 20 mg PO); 2) Initiate or repeat treatment with paclitaxel only if the neutrophil count is at least 1,000 cells/mm 3 ; 3) Reduce the dose of subsequent courses of paclitaxel by 20% for patients who experience severe neutropenia (neutrophil <500 cells/mm 3 for a week or longer); and 4) Initiate con… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Paclitaxel is contraindicated in patients who have a history of hypersensitivity reactions to Paclitaxel or other drugs formulated in polyoxyl 35 castor oil. Paclitaxel should not be used in patients with solid tumors who have baseline neutrophil counts of <1,500 cells/mm 3 or in patients with AIDS-related Kaposi's sarcoma with baseline neutrophil counts of <1,000 cells/mm 3 .
⚠️ Warnings ▾
WARNINGS Anaphylaxis and severe hypersensitivity reactions characterized by dyspnea and hypotension requiring treatment, angioedema, and generalized urticaria have occurred in 2 to 4% of patients receiving paclitaxel in clinical trials. Fatal reactions have occurred in patients despite premedication. All patients should be pretreated with corticosteroids, diphenhydramine, and H 2 antagonists.
(see DOSAGE AND ADMINISTRATION ). Patients who experience severe hypersensitivity reactions to Paclitaxel should not be rechallenged with the drug. Bone marrow suppression (primarily neutropenia) is dose-dependent and is the dose-limiting toxicity.
Neutrophil nadirs occurred at a median of 11 days. Paclitaxel should not be administered to patients with baseline neutrophil counts of less than 1,500 cells/mm 3 (<1,000 cells/mm 3 for patients with KS). Frequent monitoring of blood counts should be instituted during paclitaxel treatment.
Patients should not be re-treated with subsequent cycles of paclitaxel until neutrophils recover to a level >1,500 cells/mm3 (>1,000 cells/mm 3 for patients with KS) and platelets recover to a level >100,000 cells/mm 3 . Severe conduction abnormalities have been documented in <1% of patients during paclitaxel therapy and in some cases requiring pacemaker placement. If patients develop significant conduction abnormalities during paclitaxel infusion, appropriate therapy should be administered and continuous cardiac monitoring should be performed during subsequent therapy with paclitaxel.
Pregnancy Paclitaxel can cause fetal harm when administered to a pregnant woman. Administration of paclitaxel during the period of organogenesis to rabbits at doses of 3 mg/kg/day (about 0.2 the daily maximum recommended human dose on a mg/m 2 basis) caused embryo- and fetotoxicity, as indicated by intrauterine mortality, increased resorptions, and increased fetal deaths. Maternal toxicity was also observed at this dose.
No teratogenic effects were observed at 1 mg/kg/day (about 1/15 the daily maximum recommended human dose on a mg/m 2 basis); teratogenic potential could not be assessed at higher doses due to extensive fetal mortality. There are no adequate and well-controlled studies in pregnant women. If paclitaxel is used during pregnancy, or if the patient becomes pregnant while receiving this drug, the patient should be apprised of the potential hazard to the fetus.
Women of child-bearing potential should be advised to avoid becoming pregnant.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Pooled Analysis of Adverse Event Experiences from Single-Agent Studies Data in the following table are based on the experience of 812 patients (493 with ovarian carcinoma and 319 with breast carcinoma) enrolled in 10 studies who received single-agent paclitaxel injection. Two hundred and seventy-five patients were treated in 8, Phase 2 studies with paclitaxel doses ranging from 135 to 300 mg/m 2 administered over 24 hours (in 4 of these studies, G-CSF was administered as hematopoietic support). Three hundred and one patients were treated in the randomized Phase 3 ovarian carcinoma study which compared 2 doses (135 or 175 mg/m 2 ) and 2 schedules (3 or 24 hours) of paclitaxel.
Two hundred and thirty-six patients with breast carcinoma received paclitaxel (135 or 175 mg/m 2 ) administered over 3 hours in a controlled study. TABLE 10. SUMMARY a OF ADVERSE EVENTS IN PATIENTS WITH SOLID TUMORS RECEIVING SINGLE-AGENT PACLITAXEL Percent of Patients (n=812) · B one Marrow —Neutropenia <2,000/mm 3 90 <500/mm 3 52 —Leukopenia <4,000/mm 3 90 <1,000/mm 3 17 —Thrombocytopenia <100,000/mm 3 20 <50,000/mm 3 7 —Anemia <11 g/dL 78 <8 g/dL 16 —Infections 30 —Bleeding 14 —Red Cell Transfusions 25 —Platelet Transfusions · Hy persensitivity Reaction b 2 —All 41 —Severe † 2 · Card i ovascular —Vital Sign Changes c —Bradycardia (n=537) 3 —Hypotension (n=532) 12 —Significant Cardiovascular Events 1 · A bnormal ECG —All Pts 23 —Pts with normal baseline (n=559) 14 · Peripheral Neuropathy —Any symptoms 60 —Severe symptoms † 3 · My algia/Arthralgia —Any symptoms 60 —Severe symptoms † 8 · G astrointestinal —Nausea and vomiting 52 —Diarrhea 38 —Mucositis 31 · Alopecia 87 · Hep atic (Pts with normal baseline and on study data) —Bilirubin elevations (n=765) 7 —Alkaline phosphatase elevations (n=575) 22 —AST (SGOT) elevations (n=591) 19 · Injecti on Site Reaction 13 a Based on worst course analysis. b All patients received premedication. c During the first 3 hours of infusion. † Severe events are defined as at least Grade III toxicity.
None of the observed toxicities were clearly influenced by age. Disease-Specific Adverse Event Experiences First-Line Ovary in Combination For the 1084 patients who were evaluable for safety in the Phase 3 first-line ovary combination therapy studies, TABLE 11 shows the incidence of important adverse events. For both studies, the analysis of safety was based on all courses of therapy (6 courses for the GOG-111 study and up to 9 courses for the Intergroup study).
TABLE 11. FREQUENCY a OF IMPORTANT ADVERSE EVENTS IN THE PHASE 3 FIRST-LINE OVARIAN CARCINOMA STUDIES Percent of Patients Intergroup GOG-111 T175/3 b c75 c (n = 339) C750 c c75 c (n = 336) T135/24 b c75 c (n = 196) C750 c c75 c (n = 213) · B one Marrow —Neutropenia <2,000/mm 3 91 d 95 d 96 92 <500/mm 3 33 d 43 d 81 d 58 d —Thrombocytopenia <100,000/mm 3e 21 d 33 d 26 30 <50,000/mm 3 3 d 7 d 10 9 —Anemia <11 g/dL f 96 97 88 86 <8 g/dL 3 d 8 d 13 9 —Infections 25 27 21 15 —Febrile Neutropenia 4 7 15 d 4 d · Hypersensitivity Reaction —All 11 d 6 d 8 d.g 1 d.g —Severe † 1 1 3 d.g — d.g · Neurotoxicity h —Any symptoms 87 d 52 d 25 20 —Severe symptoms † 21 d 2 d 3 d — d · Nausea and Vomiting —Any symptoms 88 93 65 69 —Severe symptoms † 18 24 10 11 · Myalgia/Arthralgia —Any symptoms 60 d 27 d 9 d 2 d —Severe symptoms † 6 d 1 d 1 — · Diarrhea —Any symptoms 37 d 29 d 16 d 8 d —Severe symptoms † 2 3 4 1 · Asthenia —Any symptoms NC NC 17 d 10 d —Severe symptoms † NC NC 1 1 · Alopecia —Any symptoms 96 d 89 d 55 d 37 d —Severe symptoms † 51 d 21 d 6 8 a Based on worst course analysis. b Paclitaxel (T) dose in mg/m 2 /infusion duration in hours. c Cyclophosphamide (C) or cisplatin (c) dose in mg/m 2 . d P<0.05 by Fisher exact test. e <130,000/mm 3 in the Intergroup study. f <12 g/dL in the Intergroup study. g All patients received premedication. h In the GOG-111 study, neurotoxicity was collected as peripheral neuropathy and in the Intergroup study, neurotoxicity was… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
DRUG INTERACTIONS In a Phase 1 trial using escalating doses of paclitaxel (110 to 200 mg/m 2 ) and cisplatin (50 or 75 mg/m 2 ) given as sequential infusions, myelosuppression was more profound when paclitaxel was given after cisplatin than with the alternate sequence (i.e., paclitaxel before cisplatin). Pharmacokinetic data from these patients demonstrated a decrease in paclitaxel clearance of approximately 33% when paclitaxel was administered following cisplatin. The metabolism of paclitaxel is catalyzed by cytochrome P450 isoenzymes CYP2C8 and CYP3A4.
Caution should be exercised when administering paclitaxel concomitantly with known substrates or inhibitors of the cytochrome P450 isoenzymes CTP2C8 and CYP3A4. Caution should be exercised when paclitaxel is concomitantly administered with known substrates (e.g, midazolam, buspirone, felodipine, lovastatin, eletriptan, sildenafil, simvastatin, and triazolam), inhibitors (e.g., atazanavir, clarithromycin, indinavir, itraconazole, ketoconazole, nefazodone, nelfinavir, ritonavir, saquinavir, and telithromycin), and inducers (e.g., rifampin and carbamazepine) of CYP3A4.
(see CLINICAL PHARMACOLOGY ). Caution should also be exercised when paclitaxel is concomitantly administered with known substrates (e.g., repaglinide and rosiglitazone), inhibitors (e.g., gemfibrozil), and inducers (e.g., rifampin) of CYP2C8. (see CLINICAL PHARMACOLOGY ).
Potential interactions between paclitaxel, a substrate of CYP3A4, and protease inhibitors (ritonavir, saquinavir, indinavir, and nelfinavir), which are substrates and/or inhibitors of CYP3A4, have not been evaluated in clinical trials. Reports in the literature suggest that plasma levels of doxorubicin (and its active metabolite doxorubicinol) may be increased when paclitaxel and doxorubicin are used in combination. Hematology Paclitaxel therapy should not be administered to patients with baseline neutrophil counts of less than 1,500 cells/mm 3 .
In order to monitor the occurrence of myelotoxicity, it is recommended that frequent peripheral blood cell counts be performed on all patients receiving paclitaxel. Patients should not be re-treated with subsequent cycles of paclitaxel until neutrophils recover to a level >1,500 cells/mm 3 and platelets recover to a level >100,000 cells/mm 3 . In the case of severe neutropenia (<500 cells/mm 3 for 7 days or more)during a course of paclitaxel therapy, a 20% reduction in dose for subsequent courses of therapy is recommended.
For patients with advanced HIV disease and poor-risk AIDS-related Kaposi's sarcoma, paclitaxel, at the recommended dose for this disease, can be initiated and repeated if the neutrophil count is at least 1,000 cells/mm 3 . Hypersensitivity Reactions : Patients with a history of severe hypersensitivity reactions to products containing polyoxyl 35 castor oil (e.g., cyclosporin for injection concentrate and teniposide for injection concentrate) should not be treated with paclitaxel. In order to avoid the occurrence of severe hypersensitivity reactions, all patients treated with paclitaxel should be premedicated with corticosteroids (such as dexamethasone), diphenhydramine and H 2 antagonists (such as cimetidine or ranitidine).
Minor symptoms such as flushing, skin reactions, dyspnea, hypotension, or tachycardia do not require interruption of therapy. However, severe reactions, such as hypotension requiring treatment, dyspnea requiring bronchodilators, angioedema, or generalized urticaria require immediate discontinuation of paclitaxel and aggressive symptomatic therapy. Patients who have developed severe hypersensitivity reactions should not be rechallenged with paclitaxel.
Cardiovascular Hypotension, bradycardia, and hypertension have been observed during administration of paclitaxel, but generally do not require treatment. Occasionally paclitaxel infusions must be interrupted or discontinued because of initial or recurrent hypertension. Frequent vital sign monitoring, particularly during… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
Pediatric Use The safety and effectiveness of paclitaxel in pediatric patients have not been established. There have been reports of central nervous system (CNS) toxicity (rarely associated with death) in a clinical trial in pediatric patients in which paclitaxel was infused intravenously over 3 hours at doses ranging from 350 mg/m 2 to 420 mg/m 2 . The toxicity is most likely attributable to the high dose of the ethanol component of the paclitaxel vehicle given over a short infusion time.
The use of concomitant antihistamines may intensify this effect. Although a direct effect of the paclitaxel itself cannot be discounted, the high doses used in this study (over twice the recommended adult dosage) must be considered in assessing the safety of paclitaxel for use in this population.
🧓 Geriatric Use ▾
Geriatric Use Of 2228 patients who received paclitaxel in 8 clinical studies evaluating its safety and effectiveness in the treatment of advanced ovarian cancer, breast carcinoma, or NSCLC, and 1,570 patients who were randomized to receive paclitaxel in the adjuvant breast cancer study, 649 patients (17%) were 65 years or older and 49 patients (1%) were 75 years or older. In most studies, severe myelosuppression was more frequent in elderly patients; in some studies, severe neuropathy was more common in elderly patients.
In 2 clinical studies in NSCLC, the elderly patients treated with paclitaxel had a higher incidence of cardiovascular events. Estimates of efficacy appeared similar in elderly patients and in younger patients; however, comparative efficacy cannot be determined with confidence due to the small number of elderly patients studied. In a study of first-line treatment of ovarian cancer, elderly patients had a lower median survival than younger patients, but no other efficacy parameters favored the younger group.
TABLE 9 presents the incidences of Grade IV neutropenia and severe neuropathy in clinical studies according to age. TABLE 9. SELECTED ADVERSE EVENTS IN GERIATRIC PATIENTS RECEIVING PACLITAXEL IN CLINICAL STUDIES Patients (n/total [%]) Neutropenia (Grade IV) Peripheral Neuropathy (Grades III/IV) INDICATION Age (y) Age (y) (Study/Regimen) ³ 65 < 65 ³ 65 < 65 · OVARIA N Cancer (Intergroup First-Line/T175/3 c75 a ) 34/83 (41) 78/252 (31) 24/84 (29)* b 46/255 (18) b (GOG-111 First-Line/T135/24 c75 a ) 48/61 (79) 106/129 (82) 3/62 (5) 2/134 (1) (Phase 3 Second-Line/T175/3 c ) 5/19 (26) 21/76 (28) 1/19 (5) 0/76 (0) (Phase 3 Second-Line/T175/24 c ) 21/25 (84) 57/79 (72) 0/25 (0) 2/80 (3) (Phase 3 Second-Line/T135/3 c ) 4/16 (25) 10/81 (12) 0/17 (0) 0/81 (0) (Phase 3 Second-Line/T135/24 c ) 17/22 (77) 53/83 (64) 0/22 (0) 0/83 (0) (Phase 3 Second-Line Pooled) 47/82 (57)* 141/319 (44) 1/83 (1) 2/320 (1) · A djuvant BREAST Cancer (Intergroup/AC followed by T d ) 56/102 (55) 734/1468 (50) 5/102 (5) e 46/1468 (3) e · BREAST Cancer After Failure of Initial Therapy (Phase 3/T175/3 c ) 7/24 (29) 56/200 (28) 3/25 (12) 12/204 (6) (Phase 3/T135/3 c ) 7/20 (35) 37/207 (18) 0/20 (0) 6/209 (3) · Non-Small Cell LUNG Cancer (ECOG/T135/24 c75 a ) 58/71 (82) 86/124 (69) 9/71 (13) f 16/124 (13) f (Phase 3/T175/3 c80 a ) 37/89 (42)* 56/267 (21) 11/91 (12)* 11/271 (4) * p<0.05 a Paclitaxel dose in mg/m 2 /infusion duration in hours; cisplatin doses in mg/m 2 . b Peripheral neuropathy was included within the neurotoxicity category in the Intergroup First-Line Ovarian Cancer study (see TABLE 11 ). c Paclitaxel dose in mg/m 2 /infusion duration in hours. d Paclitaxel (T) following 4 courses of doxorubicin and cyclophosphamide (AC) at a dose of 175 mg/m 2 /3 hours every 3 weeks for 4 courses. e Peripheral neuropathy reported as neurosensory toxicity in the Intergroup Adjuvant Breast Cancer study (see TABLE 13 ). f Peripheral neuropathy reported as neurosensory toxicity in the ECOG NSCLC study (see TABLE 15 ).
Information for Patients (See Patient Information Leaflet).
🆘 Overdosage ▾
OVERDOSAGE There is no known antidote for paclitaxel overdosage. The primary anticipated complications of overdosage would consist of bone marrow suppression, peripheral neurotoxicity, and mucositis. Overdoses in pediatric patients may be associated with acute ethanol toxicity (see PRECAUTIONS, Pediatric Use ).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Paclitaxel is a novel antimicrotubule agent that promotes the assembly of microtubules from tubulin dimers and stabilizes microtubules by preventing depolymerization. This stability results in the inhibition of the normal dynamic reorganization of the microtubule network that is essential for vital interphase and mitotic cellular functions. In addition, paclitaxel induces abnormal arrays or “bundles” of microtubules throughout the cell cycle and multiple asters of microtubules during mitosis.
Following intravenous administration of paclitaxel, paclitaxel plasma concentrations declined in a biphasic manner. The initial rapid decline represents distribution to the peripheral compartment and elimination of the drug. The later phase is due, in part, to a relatively slow efflux of paclitaxel from the peripheral compartment.
Pharmacokinetic parameters of paclitaxel following 3- and 24-hour infusions of paclitaxel at dose levels of 135 and 175 mg/m 2 were determined in a Phase 3 randomized study in ovarian cancer patients and are summarized in the following table. TABLE 1. SUMMARY OF PHARMACOKINETIC PARAMETERS—MEAN VALUES Dose (mg/m 2 ) Infusion Duration (h) N (patients) C max (ng/mL) AUC (0-∞) (ng•h/mL) T-HALF (h) CL T (L/h/m 2 ) 135 24 2 195 6,300 52.7 21.7 175 24 4 365 7,993 15.7 23.8 135 3 7 2,170 7,952 13.1 17.7 175 3 5 3,650 15,007 20.2
12.2C max = Maximum plasma concentration AUC (0-∞) = Area under the plasma concentration-time curve from time 0 to infinity CL T = Total body clearance It appeared that with the 24-hour infusion of paclitaxel, a 30% increase in dose (135 mg/m 2 vs 175 mg/m 2 ) increased the C max by 87%, whereas the AUC (0-∞) remained proportional. However, with a 3-hour infusion, for a 30% increase in dose, the C max and AUC (0-∞) were increased by 68% and 89%, respectively. The mean apparent volume of distribution at steady state, with the 24-hour infusion of paclitaxel, ranged from 227 to 688 L/m 2 , indicating extensive extravascular distribution and/or tissue binding of paclitaxel.
The pharmacokinetics of paclitaxel were also evaluated in adult cancer patients who received single doses of 15 to 135 mg/m 2 given by 1-hour infusions (n=15), 30 to 275 mg/m 2 given by 6-hour infusions (n=36), and 200 to 275 mg/m 2 given by 24-hour infusions (n=54) in Phase 1 and 2 studies. Values for CL T and volume of distribution were consistent with the findings in the Phase 3 study. The pharmacokinetics of paclitaxel in patients with AIDS-related Kaposi's sarcoma have not been studied.
In vitro studies of binding to human serum proteins, using paclitaxel concentrations ranging from 0.1 to 50 mcg/mL, indicate that between 89 to 98% of drug is bound; the presence of cimetidine, ranitidine, dexamethasone, or diphenhydramine did not affect protein binding of paclitaxel. After intravenous administration of 15 to 275 mg/m 2 doses of paclitaxel as 1-, 6-, or 24-hour infusions, mean values for cumulative urinary recovery of unchanged drug ranged from 1.3% to 12.6% of the dose, indicating extensive non-renal clearance.
In 5 patients administered a 225 or 250 mg/m 2 dose of radiolabeled paclitaxel as a 3-hour infusion, a mean of 71% of the radioactivity was excreted in the feces in 120 hours, and 14% was recovered in the urine. Total recovery of radioactivity ranged from 56% to 101% of the dose. Paclitaxel represented a mean of 5% of the administered radioactivity recovered in the feces, while metabolites, primarily 6α-hydroxypaclitaxel, accounted for the balance.
In vitro studies with human liver microsomes and tissue slices showed that paclitaxel was metabolized primarily to 6α-hydroxypaclitaxel by the cytochrome P450 isozyme CYP2C8; and to 2 minor metabolites, 3'- p -hydroxypaclitaxel and 6α, 3'- p -dihydroxypaclitaxel, by CYP3A4. In vitro , the metabolism of paclitaxel to 6α-hydroxypaclitaxel was inhibited by a number of agents (ketoconazole, verapamil, diazepam, quinidine, dexamethasone, cyclosporin, tenip… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Paclitaxel Injection, USP (6 mg/mL) is available as follows: NDC 16714-137-01 300 mg/50 mL multidose vial individually packaged in a carton. Storage Store the vials in original cartons between 20 o to 25 o C (68 o to 77 o F)[See USP Controlled Room Temperature]. Retain in the original package to protect from light. Handling and Disposal See DOSAGE AND ADMINISTRATION, Preparation and Administration Precautions.
📋 Description ▾
DESCRIPTION Paclitaxel Injection, USP is a clear, colorless to slightly yellow viscous solution. It is supplied as a nonaqueous solution intended for dilution with a suitable parenteral fluid prior to intravenous infusion. Paclitaxel Injection, USP is available in 30 mg (5 mL), 100 mg (16.7 mL), and 300 mg (50 mL) multidose vials.
Each mL of sterile nonpyrogenic solution contains 6 mg paclitaxel, USP, 527 mg of purified polyoxyl 35 castor oil and 49.7% (v/v) dehydrated alcohol, USP and 2 mg citric acid, USP. Paclitaxel is a natural product with antitumor activity. Paclitaxel is obtained via an extraction process from Taxus X media .
The chemical name for paclitaxel is (2aR, 4S,4aS,6R, 9S ,11S ,12S ,12aR, 12bS )-1,2a,3,4, 4a,6,9,10, 11,12,12a,12b- Dodecahydro-4,6,9 ,11, 12, 12b-hexahydroxy-4a,8,13,13-tetramethyl-7,11-methano-5H-cyclodeca[3,4]-benz[1,2-b]oxet-5-one6,12b-diacetate,12-benzoate,9-esterwith(2R,3S)-N-benzoyl-3-phenylisoserine Paclitaxel has the following structural formula: Paclitaxel, USP is a white to off-white powder with the molecular formula C 47 H 51 NO 14 and a molecular weight of 853.91. It is highly lipophilic, insoluble in water, soluble in alcohol, and melts at around 213 o to 222 o C. structure
⚠️ Precautions ▾
PRECAUTIONS Contact of the undiluted concentrate with plasticized polyvinyl chloride (PVC) equipment or devices used to prepare solutions for infusion is not recommended. In order to minimize patient exposure to the plasticizer DEHP [di-(2-ethylhexyl)phthalate], which may be leached from PVC infusion bags or sets, diluted paclitaxel solutions should preferably be stored in bottles (glass, polypropylene) or plastic bags (polypropylene, polyolefin) and administered through polyethylene-lined administration sets. Paclitaxel should be administered through an in-line filter with a microporous membrane not greater than 0.22 microns.
Use of filter devices such as IVEX-2 ® filters which incorporate short inlet and outlet PVC-coated tubing has not resulted in significant leaching of DEHP. DRUG INTERACTIONS In a Phase 1 trial using escalating doses of paclitaxel (110 to 200 mg/m 2 ) and cisplatin (50 or 75 mg/m 2 ) given as sequential infusions, myelosuppression was more profound when paclitaxel was given after cisplatin than with the alternate sequence (i.e., paclitaxel before cisplatin). Pharmacokinetic data from these patients demonstrated a decrease in paclitaxel clearance of approximately 33% when paclitaxel was administered following cisplatin.
The metabolism of paclitaxel is catalyzed by cytochrome P450 isoenzymes CYP2C8 and CYP3A4. Caution should be exercised when administering paclitaxel concomitantly with known substrates or inhibitors of the cytochrome P450 isoenzymes CTP2C8 and CYP3A4. Caution should be exercised when paclitaxel is concomitantly administered with known substrates (e.g, midazolam, buspirone, felodipine, lovastatin, eletriptan, sildenafil, simvastatin, and triazolam), inhibitors (e.g., atazanavir, clarithromycin, indinavir, itraconazole, ketoconazole, nefazodone, nelfinavir, ritonavir, saquinavir, and telithromycin), and inducers (e.g., rifampin and carbamazepine) of CYP3A4.
(see CLINICAL PHARMACOLOGY ). Caution should also be exercised when paclitaxel is concomitantly administered with known substrates (e.g., repaglinide and rosiglitazone), inhibitors (e.g., gemfibrozil), and inducers (e.g., rifampin) of CYP2C8. (see CLINICAL PHARMACOLOGY ).
Potential interactions between paclitaxel, a substrate of CYP3A4, and protease inhibitors (ritonavir, saquinavir, indinavir, and nelfinavir), which are substrates and/or inhibitors of CYP3A4, have not been evaluated in clinical trials. Reports in the literature suggest that plasma levels of doxorubicin (and its active metabolite doxorubicinol) may be increased when paclitaxel and doxorubicin are used in combination. Hematology Paclitaxel therapy should not be administered to patients with baseline neutrophil counts of less than 1,500 cells/mm 3 .
In order to monitor the occurrence of myelotoxicity, it is recommended that frequent peripheral blood cell counts be performed on all patients receiving paclitaxel. Patients should not be re-treated with subsequent cycles of paclitaxel until neutrophils recover to a level >1,500 cells/mm 3 and platelets recover to a level >100,000 cells/mm 3 . In the case of severe neutropenia (<500 cells/mm 3 for 7 days or more)during a course of paclitaxel therapy, a 20% reduction in dose for subsequent courses of therapy is recommended.
For patients with advanced HIV disease and poor-risk AIDS-related Kaposi's sarcoma, paclitaxel, at the recommended dose for this disease, can be initiated and repeated if the neutrophil count is at least 1,000 cells/mm 3 . Hypersensitivity Reactions : Patients with a history of severe hypersensitivity reactions to products containing polyoxyl 35 castor oil (e.g., cyclosporin for injection concentrate and teniposide for injection concentrate) should not be treated with paclitaxel. In order to avoid the occurrence of severe hypersensitivity reactions, all patients treated with paclitaxel should be premedicated with corticosteroids (such as dexamethasone), diphenhydramine and H 2 antagonists (such as cimetidine or… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers It is not known whether the drug is excreted in human milk. Following intravenous administration of carbon 14-labeled paclitaxel to rats on days 9 to 10 postpartum, concentrations of radioactivity in milk were higher than in plasma and declined in parallel with the plasma concentrations. Because many drugs are excreted in human milk and because of the potential for serious adverse reactions in nursing infants, it is recommended that nursing be discontinued when receiving paclitaxel therapy.
🔬 Clinical Studies ▾
CLINICAL STUDIES Ovarian Carcinoma First-Line Data The safety and efficacy of paclitaxel followed by cisplatin in patients with advanced ovarian cancer and no prior chemotherapy were evaluated in 2, Phase 3 multicenter, randomized, controlled trials. In an Intergroup study led by the European Organization for Research and Treatment of Cancer involving the Scandinavian Group NOCOVA, the National Cancer Institute of Canada, and the Scottish Group, 680 patients with Stage II B-C , III, or IV disease (optimally or non-optimally debulked) received either paclitaxel 175 mg/m 2 infused over 3 hours followed by cisplatin 75 mg/m 2 (Tc) or cyclophosphamide 750 mg/m2 followed by cisplatin 75 mg/m2 (Cc) for a median of 6 courses.
Although the protocol allowed further therapy, only 15% received both drugs for 9 or more courses. In a study conducted by the Gynecological Oncology Group (GOG), 410 patients with Stage III or IV disease (>1 cm residual disease after staging laparotomy or distant metastases) received either paclitaxel 135 mg/m 2 infused over 24 hours followed by cisplatin 75 mg/m 2 or cyclophosphamide 750 mg/m 2 followed by cisplatin 75 mg/m 2 for 6 courses. In both studies, patients treated with paclitaxel in combination with cisplatin had significantly higher response rate, longer time to progression, and longer survival time compared with standard therapy.
These differences were also significant for the subset of patients in the Intergroup study with non-optimally debulked disease, although the study was not fully powered for subset analyses ( TABLES 2A and 2B ). Kaplan- Meier survival curves for each study are shown in FIGURES 1 and 2. TABLE 2A.
EFFICACY IN THE PHASE 3 FIRST-LINE OVARIAN CARCINOMA STUDIES Intergroup (non-optimally debulked subset) GOG-111 T175/3 a c75 (n = 218) C750 a c75 (n = 227) T135/24 a c75 (n = 196) C750 a c75 (n = 214) Clinical Response b (n=153) 0.016 (n=153) (n=113) 0.04 (n=127) —rate (percent) 58 43 62 48 —p-value c Time to Progression —median (months) 13.2 9.9 16.6 13 —p-value c 0.0060 0.0008 —hazard ratio (HR) c 0.76 0.70 —95% CI c 0.6 to 0.92 0.56 to
0.86Survival —median (months) 29.5 21.9 35.5 24.2 —p-value c 0.0057 0.0002 —hazard ratio (HR) c 0.73 0.64 —95% CI c 0.58 to 0.91 0.50 to 0.81 a Paclitaxel dose in mg/m 2 /infusion duration in hours; cyclophosphamide and cisplatin doses in mg/m 2 . b Among patients with measurable disease only. c Unstratified for the Intergroup Study, Stratified for Study GOG-111. TABLE 2B. EFFICACY IN THE PHASE 3 FIRST-LINE OVARIAN CARCINOMA INTERGROUP STUDY T175/3 a c75 (n = 342) C750 a c75 (n = 338) Clinical Response b (n=162) (n=161) —rate (percent) 59 45 —p-value c 0.014 Time to Progression —median (months) 15.3 11.5 —p-value c 0.0005 —hazard ratio (HR) c 0.74 —95% CI c 0.63 to
0.88Survival —median (months) 35.6 25.9 —p-value c 0.0016 —hazard ratio (HR) c 0.73 —95% CI c 0.60 to 0.89 a Paclitaxel dose in mg/m 2 /infusion duration in hours; cyclophosphamide and cisplatin doses in mg/m 2 . b Among patients with measurable disease only. c Unstratified. FIGURE 1. SURVIVAL: Cc VERSUS Tc (INTERGROUP) FIGURE 2.
SURVIVAL: Cc VERSUS Tc (GOG-111) The adverse event profile for patients receiving paclitaxel in combination with cisplatin in these studies was qualitatively consistent with that seen for the pooled analysis of data from 812 patients treated with single-agent paclitaxel in 10 clinical studies. These adverse events and adverse events from the Phase 3 first-line ovarian carcinoma studies are described in the ADVERSE REACTIONS section in tabular ( TABLES 10 and 11 ) and narrative form. Second-Line Data Data from 5, Phase 1 and 2 clinical studies (189 patients), a multicenter randomized Phase 3 study (407 patients), as well as an interim analysis of data from more than 300 patients enrolled in a treatment referral center program were used in support of the use of paclitaxel in patients who have failed initial or subsequent chemotherapy for metastatic carcinoma of… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility The carcinogenic potential of paclitaxel has not been studied. Paclitaxel has been shown to be clastogenic in vitro (chromosome aberrations in human lymphocytes) and in vivo (micronucleus test in mice). Paclitaxel was not mutagenic in the Ames test or the CHO/HGPRT gene mutation assay.
Administration of paclitaxel prior to and during mating produced impairment of fertility in male and female rats at doses equal to or greater than 1 mg/kg/day (about 0.04 the daily maximum recommended human dose on a mg/m 2 basis). At this dose, paclitaxel caused reduced fertility and reproductive indices, and increased embryo- and fetotoxicity. (See WARNINGS .)
📚 References ▾
REFERENCES 1. NIOSH Alert: Preventing occupational exposures to antineoplastic and other hazardous drugs in healthcare settings. 2004.
U.S. Department of Health and Human Services, Public Health Service, Centers for Disease Control and Prevention, National Institute for Occupational Safety and Health, DHHS (NIOSH) Publication No. 2004- 165.
2. OSHA Technical Manual, TED 1-0.15A, Section VI: Chapter 2. Controlling occupational exposure to hazardous drugs.
OSHA, 1999. http://www.osha.gov/dts/osta/otm/otm_vi/otm_vi_2.html. 3. American Society of Health-System Pharmacists.
ASHP guidelines on handling hazardous drugs. Am J Health-Syst Pharm. 2006;63:1172-1193.
4. Polovich M, White JM, Kelleher LO, eds. 2005.
Chemotherapy and biotherapy guidelines and recommendations for practice. 2nd ed. Pittsburgh, PA: Oncology Nursing Society.
Manufactured for: Northstar Rx LLC Memphis,TN 38141. Manufactured by: MSN Laboratories Private Limited Telangana – 509 228, INDIA Issued on: 01/2021
📄 Patient Package Insert ▾
PATIENT INFORMATION Paclitaxel (pak” li tax’ el) Injection, USP Read this patient information leaflet before you start taking paclitaxel. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or your treatment.
What is the most important information I should know about paclitaxel? Paclitaxel can cause serious side effects including death. Serious allergic reactions (anaphylaxis) can happen in people who receive paclitaxel.
Anaphylaxis is a serious medical emergency that can lead to death and must be treated right away. Tell your healthcare provider right away if you have any of these signs of an allergic reaction: • trouble breathing • sudden swelling of your face, lips, tongue, throat, or trouble swallowing • hives (raised bumps) or rash Your healthcare provider will give you medicines to lessen your chance of having an allergic reaction. What is paclitaxel?
Paclitaxel is a prescription medicine used to treat some forms of: • ovarian cancer • breast cancer • lung cancer • Kaposi’s sarcoma It is not known if paclitaxel injection is safe or effective in children. Who should not receive paclitaxel? Do not receive paclitaxel if: • you are allergic to any of the ingredients in paclitaxel.
See the end of this leaflet for a complete list of ingredients in paclitaxel. • are allergic to medicines containing polyoxyl 35 castor oil*. • you have low white blood cell counts. What should I tell my healthcare provider before receiving paclitaxel? Before receiving paclitaxel, tell your healthcare provider about all your medical conditions, including if you: • have liver problems • have heart problems • are pregnant or plan to become pregnant.
Paclitaxel can harm your unborn baby. Talk to your healthcare provider if you are pregnant or plan to become pregnant. • are breast-feeding or plan to breast-feed. It is not known if paclitaxel passes into your breast milk.
You and your healthcare provider should decide if you will receive paclitaxel or breast-feed. Tell your healthcare provider about all the medicines you take, including prescription and non-prescription medicines, vitamins, and herbal supplements. Know the medicines you take.
Keep a list of them and show it to your healthcare provider and pharmacist when you get a new medicine. How will I receive paclitaxel? • Paclitaxel is injected into a vein (intravenous [IV] infusion) by your healthcare provider. Your healthcare provider will do certain tests while you receive paclitaxel.
What are the possible side effects of paclitaxel? Tell your healthcare provider right away if you have: • severe stomach pain • severe diarrhea The most common side effects of Paclitaxel injection, USP include: • low red blood cell count (anemia) feeling weak or tired • hair loss • numbness, tingling, or burning in your hands or feet (neuropathy) • joint and muscle pain • nausea and vomiting • hypersensitivity reaction - trouble breathing; sudden swelling of your face, lips, tongue, throat, or trouble swallowing; hives (raised bumps) or rash • diarrhea • mouth or lip sores (mucositis) • infections - if you have a fever (temperature above 100.4°F) or other sign of infection, tell your healthcare provider right away • swelling of your hands, face, or feet • bleeding events • irritation at the injection site • low blood pressure (hypotension) Tell your healthcare provider if you have any side effect that bothers you or that does not go away.
These are not all the possible side effects of paclitaxel. For more information, ask your healthcare provider or pharmacist. Call your doctor for medical advice about side effects.
You may report side effects to FDA at 1-800-FDA-1088. General information about the safe and effective use of paclitaxel. Medicines are sometimes prescribed for purposes other than those listed in a patient information leaflet.
Do not use paclitaxel for a condition for which it was not prescribed. Do not give paclitax… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Paclitaxel injection-300 mg/50ml-vial-label Paclitaxel injection-300 mg/50ml-carton-label 300MG-VIAL 300mg-carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |