
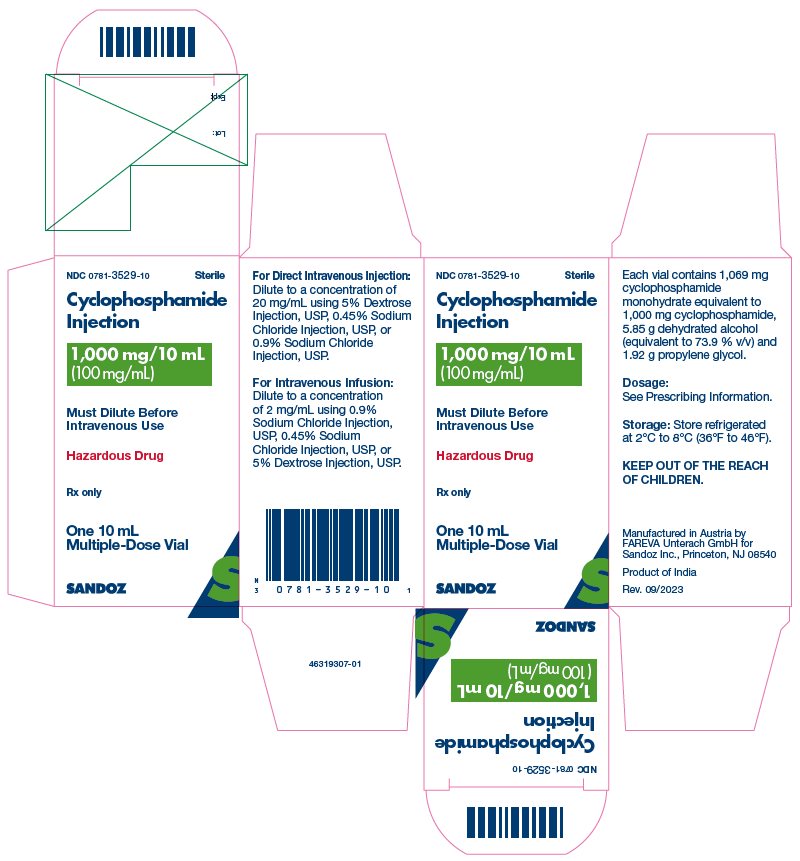
Cyclophosphamide 1000 mg/10mL Injection, Solution, Concentrate — NDC 0781-3529-10 (Billing 00781-3529-10)
This is a package of Cyclophosphamide 1000 mg/10mL Injection, Solution, Concentrate from Sandoz Inc, marketed since Apr 2024 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0781-3529-10 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0781 labeler · 3529 product · 10 package
- Package marketed since
- Apr 8, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 0781352910 1
- Medicaid fills, this package
- 25 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 085308
- GCN: 54762
- GPI-14 (Medi-Span): 21101020002010
- HICL (First Databank): 003893
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 2679073
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Alkylating Drug class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Cyclophosphamide is used to treat Hodgkin's lymphoma (Hodgkin's disease) and non-Hodgkin's lymphoma (types of cancer that begin in a type of white blood cells that normally fights infection); mycosis fungoides (a type of blood cancer that first appears as skin rashes); multiple myeloma (a type of cancer of the bone marrow); and certain types of leukemia (cancer of the white blood cells), including chronic lymphocytic leukemia (CLL), chronic myelogenous leukemia (CML), acute myeloid leukemia (AML, ANLL), and acute lymphoblastic leukemia (ALL). It is also used to treat retinoblastoma (cancer in...
Read the full MedlinePlus article ↗- It is mainly a chemotherapy drug for cancers such as lymphomas, multiple myeloma, leukemias and breast and ovarian cancer. Some oral and injection products are also approved for ch...
- It may be given into a vein or taken by mouth, depending on your product. Drink plenty of fluids and empty your bladder often to protect it. The label says morning dosing is best....
- Common ones are low white blood cell counts, fever, hair loss, nausea, vomiting and diarrhea. Your blood counts will be checked regularly. Call right away for fever or infection si...
- Tell us about everything you take. Protease inhibitors, warfarin, cyclosporine, tamoxifen and metronidazole can interact. Also tell any surgeon or anesthesiologist if you had cyclo...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cyclophosphamide — tap one for details:
Cyclophosphamide may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $81.08 | $810.76 / 10 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9074 | $3.438 / J9074 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00781-3529-10 You're viewing this Main listing | 1 VIAL, MULTI-DOSE in 1 CARTON / 10 mL in 1 VIAL, MULTI-DOSE | 2024-04-08 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cyclophosphamide 500 mg/5mL 00781-3528-10 | Sandoz | 1 vial | — | — | FDA listed | — |
| Cyclophosphamide 1000 mg/10mLthis 00781-3529-10 | Sandoz | 1 vial | — | — | FDA listed | — |
| Cyclophosphamide 2000 mg/20mL 00781-3530-10 | Sandoz | 1 vial | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Sandoz Inc labeler code 00781
- METHYLPREDNISOLONE ACETATE 80 mg/mL Injection, Suspension NDC 0781-3516-75
- Pemetrexed 100 mg/4mL Injection, Solution NDC 0781-3518-76
- Pemetrexed 500 mg/20mL Injection, Solution NDC 0781-3519-90
- METHYLPREDNISOLONE ACETATE 40 mg/mL Injection, Suspension NDC 0781-3522-70
- Edaravone 30 mg/100mL Injection NDC 0781-3527-20
- Cyclophosphamide 500 mg/5mL Injection, Solution, Concentrate NDC 0781-3528-10
- Cyclophosphamide 2000 mg/20mL Injection, Solution, Concentrate NDC 0781-3530-10
- Paclitaxel 100 mg/20mL Injection, Powder, Lyophilized, For Suspension NDC 0781-3531-91
- Fulvestrant 50 mg/mL Injection NDC 0781-3532-12
- Heparin Sodium 10000 [USP'U]/mL Injection, Solution NDC 0781-3533-25
- LIDOCAINE HYDROCHLORIDE 10 mg/mL Injection, Solution NDC 0781-3537-25
- Heparin Sodium 1000 [USP'U]/mL Injection, Solution NDC 0781-3538-25
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Malignant Diseases Cyclophosphamide Injection is indicated for the treatment of adult patients with: • malignant lymphomas (Stages III and IV of the Ann Arbor staging system), Hodgkin’s lymphoma, lymphocytic lymphoma (nodular or diffuse), mixed-cell type lymphoma, histiocytic lymphoma, Burkitt’s lymphoma • multiple myeloma • leukemias: Chronic lymphocytic leukemia, chronic granulocytic leukemia (it is usually ineffective in acute blastic crisis), acute myelogenous and monocytic leukemia, acute lymphoblastic (stem-cell) leukemia (cyclophosphamide given during remission is effective in prolonging its duration) • mycosis fungoides (advanced disease) • neuroblastoma (disseminated disease) • adenocarcinoma of the ovary • retinoblastoma • carcinoma of the breast Cyclophosphamide, although effective alone in susceptible malignancies, is more frequently used concurrently or sequentially with other antineoplastic drugs.
Limitations of Use This cyclophosphamide product is not indicated for use in pediatric patients due to the to the alcohol and propylene glycol content in this product. If treatment with cyclophosphamide is indicated in a pediatric patient, use a different cyclophosphamide product [see Warnings and Precautions ( 5.7 ), Use in Specific Populations ( 8.4 ), and Description ( 11 )] . Cyclophosphamide Injection is an alkylating drug indicated for treatment of adult patients with: Malignant Diseases: malignant lymphomas: Hodgkin’s lymphoma, lymphocytic lymphoma, mixed-cell type lymphoma, histiocytic lymphoma, Burkitt’s lymphoma; multiple myeloma, leukemias, mycosis fungoides, neuroblastoma, adenocarcinoma of ovary, retinoblastoma, breast carcinoma.
( 1 ) Limitations of Use This cyclophosphamide product is not indicated for use in pediatric patients due to the alcohol and propylene glycol content in this product. If treatment with cyclophosphamide is indicated in a pediatric patient, use a different cyclophosphamide product. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION During or immediately after Cyclophosphamide Injection administration, administer adequate amounts of fluid to reduce the risk of urinary tract toxicity ( 2.1 ). Malignant Diseases: Adult Patients ( 2.2 ) • Intravenous: Initial course for patients with no hematologic deficiency: 40 mg/kg to 50 mg/kg in divided doses over 2 to 5 days. Other regimens include 10 mg/kg to 15 mg/kg given every 7 to 10 days or 3 mg/kg to 5 mg/kg twice weekly.
( 2.2 ) • See full prescribing information for instructions on preparation, handling, and administration. ( 2.3 )
2.1Important Administration Information During or immediately after the administration, adequate amounts of fluid should be ingested or infused to force diuresis in order to reduce the risk of urinary tract toxicity. Therefore, Cyclophosphamide Injection should be administered in the morning.
2.2Recommended Dosage for Malignant Diseases Intravenous Use When used as the only oncolytic drug therapy, the recommended dosage for the initial course of Cyclophosphamide Injection for patients with no hematologic deficiency is 40 mg per kg to 50 mg per kg given intravenously in divided doses over a period of 2 to 5 days. Other intravenous regimens include 10 mg per kg to 15 mg per kg given every 7 to 10 days or 3 mg per kg to 5 mg per kg twice weekly. Adjust the dosage of Cyclophosphamide Injection based on the specific regimen administered, response to treatment, myelosuppression or other adverse reactions, and patient risk factors [see Warnings and Precautions ( 5 )] .
2.3Preparation, Handling and Administration Cyclophosphamide Injection is a hazardous drug. Follow applicable special handling and disposal procedures 1 . Caution should be exercised when handling and preparing Cyclophosphamide Injection.
To minimize the risk of dermal exposure, always wear gloves when handling vials containing Cyclophosphamide Injection. Cyclophosphamide Injection Intravenous Administration Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. Do not use Cyclophosphamide Injection vials if there are signs of particulate matter.
Cyclophosphamide Injection does not contain any antimicrobial preservative and thus care must be taken to assure the sterility of prepared solutions. Use aseptic technique. For Direct Intravenous Injection Aseptically withdraw the prescribed dose from the vial and dilute to a concentration of 20 mg/mL by using any of the following diluents: • 5% Dextrose Injection • 0.45% Sodium Chloride Injection • 0.9% Sodium Chloride Injection For Intravenous Infusion Aseptically withdraw the prescribed dose from the vial and dilute to a concentration of 2 mg/mL by using any of the following diluents: • 0.9% Sodium Chloride Injection • 0.45% Sodium Chloride Injection • 5% Dextrose Injection To reduce the likelihood of adverse reactions that appear to be administration rate dependent (e.g., facial swelling, headache, nasal congestion, scalp burning), Cyclophosphamide Injection should be injected or infused very slowly.
Duration of the infusion also should be appropriate for the volume and type of carrier fluid to be infused. Each vial is recommended for no more than a total of eight (8) dose withdrawals. Storage of Diluted Cyclophosphamide Injection Solution: If the diluted solution is not used immediately, store at room temperature at 68°F to 77°F (20°C to 25°C) for up to 24 hours or refrigerated at 36°F to 46°F (2°C to 8°C) for up to 6 days.
Storage of Undiluted Cyclophosphamide Injection Solution: After first use, the partially used vial should be stored in the refrigerator in the original carton at 2°C to 8°C (36ºF to 46°F) up to 28 days. Discard unused portion after 28 days.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Cyclophosphamide Injection is a 100 mg/mL sterile, clear, colorless to pale-yellow solution in a multiple-dose vial available in the following presentations: • 500 mg/5 mL • 1,000 mg/10 mL • 2,000 mg/20 mL Injection: 500 mg/5 mL (100 mg/mL), 1,000 mg/10 mL (100 mg/mL), 2,000 mg/20 mL (100 mg/mL) in multiple-dose vials ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Severe Hypersensitivity Cyclophosphamide Injection is contraindicated in patients who have a history of severe hypersensitivity reactions to cyclophosphamide, any of its metabolites, or to other components of the product. Anaphylactic reactions including death have been reported with cyclophosphamide. Cross-sensitivity with other alkylating agents can occur.
Urinary Outflow Obstruction Cyclophosphamide Injection is contraindicated in patients with urinary outflow obstruction [see Warnings and Precautions ( 5.2 )]. • Severe hypersensitivity to cyclophosphamide ( 4 ) • Urinary outflow obstruction ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Myelosuppression, Immunosuppression, Bone Marrow Failure, and Infections: Severe immunosuppression may lead to serious and sometimes fatal infections. Close hematological monitoring is required. ( 5.1 ) • Urinary Tract and Renal Toxicity: Hemorrhagic cystitis, pyelitis, ureteritis, and hematuria can occur.
Urotoxicity can be fatal. Exclude or correct any urinary tract obstructions prior to treatment. ( 5.2 ) • Cardiotoxicity: Myocarditis, myopericarditis, pericardial effusion, arrythmias and congestive heart failure, which may be fatal, have been reported.
Monitor patients, especially those with risk factors for cardiotoxicity or pre-existing cardiac disease. ( 5.3 ) • Pulmonary Toxicity: Pneumonitis, pulmonary fibrosis and pulmonary veno-occlusive disease leading to respiratory failure may occur. Monitor patients for signs and symptoms of pulmonary toxicity.
( 5.4 ) • Secondary Malignancies: Have been reported in patients treated with cyclophosphamide containing regimens. ( 5.5 ) • Veno-occlusive Liver Disease: Fatal outcome can occur. ( 5.6 ) • Alcohol Content: This product is not indicated for use in pediatric patients.
The alcohol content in a dose of Cyclophosphamide Injection may affect the central nervous system. This may include impairment of a patient's ability to drive or use machines immediately after infusion. ( 5.7 ) • Embryo-Fetal Toxicity: Can cause fetal harm.
Advise females of reproductive potential of potential risk to a fetus and to use effective contraception. Advise males with female partners of reproductive potential to use effective contraception ( 5.8 , 8.1 , 8.3 )
5.1Myelosuppression, Immunosuppression, Bone Marrow Failure and Infections Cyclophosphamide can cause myelosuppression (leukopenia, neutropenia, thrombocytopenia and anemia), bone marrow failure, and severe immunosuppression which may lead to serious and sometimes fatal infections, including sepsis and septic shock. Latent infections can be reactivated [see Adverse Reactions ( 6.2 )]. Antimicrobial prophylaxis may be indicated in certain cases of neutropenia at the discretion of the managing physician.
In case of neutropenic fever, antibiotic therapy is indicated. Antimycotics and/or antivirals may also be indicated. Monitoring of complete blood counts is essential during cyclophosphamide treatment so that the dose can be adjusted, if needed.
Cyclophosphamide Injection should not be administered to patients with neutrophils ≤1,500/mm3 and platelets < 50,000/mm 3 . Cyclophosphamide Injection treatment may not be indicated, or should be interrupted, or the dose reduced, in patients who have or who develop a serious infection. G-CSF may be administered to reduce the risks of neutropenia complications associated with cyclophosphamide use.
Primary and secondary prophylaxis with G-CSF should be considered in all patients considered to be at increased risk for neutropenia complications. The nadirs of the reduction in leukocyte count and thrombocyte count are usually reached in weeks 1 and 2 of treatment. Peripheral blood cell counts are expected to normalize after approximately 20 days.
Bone marrow failure has been reported. Severe myelosuppression may be expected particularly in patients pretreated with and/or receiving concomitant chemotherapy and/or radiation therapy.
5.2Urinary Tract and Renal Toxicity Hemorrhagic cystitis, pyelitis, ureteritis, and hematuria have been reported with cyclophosphamide. Medical and/or surgical supportive treatment may be required to treat protracted cases of severe hemorrhagic cystitis. Discontinue Cyclophosphamide Injection therapy in case of severe hemorrhagic cystitis.
Urotoxicity (bladder ulceration, necrosis, fibrosis, contracture and secondary cancer) may require interruption of cyclophosphamide treatment or cystectomy. Urotoxicity can be fatal. Urotoxicity can occur with short-term or long-term use of cyclophosphamide.
Before starting treatment, exclude or correct any urinary t… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more detail in other sections of the labeling. • Hypersensitivity [see Contraindications ( 4 )] • Myelosuppression, Immunosuppression, Bone Marrow Failure, and Infections [see Warnings and Precautions ( 5.1 )] • Urinary Tract and Renal Toxicity [see Warnings and Precautions ( 5.2 )] • Cardiotoxicity [see Warnings and Precautions ( 5.3 )] • Pulmonary Toxicity [see Warnings and Precautions ( 5.4 )] • Secondary Malignancies [see Warnings and Precautions ( 5.5 )] • Veno-occlusive Liver Disease [see Warnings and Precautions ( 5.6 )] • Alcohol Content [see Warnings and Precautions ( 5.7 )] • Infertility [see Warnings and Precautions ( 5.9 ) ] • Impaired Wound Healing [see Warnings and Precautions ( 5.10 )] • Hyponatremia [see Warnings and Precautions ( 5.11 )] The most common adverse reactions are neutropenia, febrile neutropenia, fever, alopecia, nausea, vomiting, and diarrhea.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Sandoz Inc. at 1-800-525-8747 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials and Postmarketing Experience The following adverse reactions associated with the use of cyclophosphamide were identified in clinical studies or postmarketing reports. Because some of these reactions were reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The most common adverse reactions were neutropenia, febrile neutropenia, fever, alopecia, nausea, vomiting, and diarrhea.
Cardiac: cardiac arrest, ventricular fibrillation, ventricular tachycardia, cardiogenic shock, pericardial effusion (progressing to cardiac tamponade), myocardial hemorrhage, myocardial infarction, cardiac failure (including fatal outcomes), cardiomyopathy, myocarditis, pericarditis, carditis, atrial fibrillation, supraventricular arrhythmia, ventricular arrhythmia, bradycardia, tachycardia, palpitations, QT prolongation. Congenital, Familial and Genetic : intra-uterine death, fetal malformation, fetal growth retardation, fetal toxicity (including myelosuppression, gastroenteritis).
Ear and Labyrinth: deafness, hearing impaired, tinnitus. Endocrine: water intoxication. Eye: visual impairment, conjunctivitis, lacrimation.
Gastrointestinal: gastrointestinal hemorrhage, acute pancreatitis, colitis, enteritis, cecitis, stomatitis, constipation, parotid gland inflammation, nausea, vomiting, diarrhea. General Disorders and Administrative Site Conditions: multiorgan failure, general physical deterioration, influenza-like illness, injection/infusion site reactions (thrombosis, necrosis, phlebitis, inflammation, pain, swelling, erythema), pyrexia, edema, chest pain, mucosal inflammation, asthenia, pain, chills, fatigue, malaise, headache, febrile neutropenia.
Hematologic: myelosuppression, bone marrow failure, disseminated intravascular coagulation and hemolytic uremic syndrome (with thrombotic microangiopathy). Hepatic: veno-occlusive liver disease, cholestatic hepatitis, cytolytic hepatitis, hepatitis, cholestasis; hepatotoxicity with hepatic failure, hepatic encephalopathy, ascites, hepatomegaly, blood bilirubin increased, hepatic function abnormal, hepatic enzymes increased. Immune: immunosuppression, anaphylactic shock and hypersensitivity reaction.
Infections: The following manifestations have been associated with myelosuppression and immunosuppression caused by cyclophosphamide: increased risk for and severity of pneumonias (including fatal outcomes), other bacterial, fungal, viral, protozoal, and parasitic infections; reactivation of latent infections, (including viral hepatitis, tuberculosis), pneumocystis jiroveci , herpes zoster, strongyloides , sepsis and septic shock. Investigations: blood lactate dehydrogenase increased, C-reactive protein increased. Metabolism and Nutrition: hyponatremia, fluid retention, blood glucose increased, blood glucos… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Effect of Other Drugs on Cyclophosphamide Exposure Protease Inhibitors Concomitant use of protease inhibitors may increase the concentration of cytotoxic metabolites and may enhance the toxicities of cyclophosphamide, including higher incidence of infections, neutropenia, and mucositis. Monitor for increased toxicities in patients receiving protease inhibitors.
7.2Drugs that Potentiate Cyclophosphamide Toxicities Radiation therapy or drugs with similar toxicities to Cyclophosphamide Injection can potentiate toxicities for cyclophosphamide. Monitor for increased toxicities in patients receiving radiation therapy or drugs known to cause: • Myelosuppression and/or immunosuppression [see Warnings and Precautions ( 5.1 )] • Nephrotoxicity including hemorrhagic cystitis [see Warnings and Precautions ( 5.2 )] • Cardiotoxicity [see Warnings and Precautions ( 5.3 )] • Pulmonary toxicity [see Warnings and Precautions ( 5.4 )] • Secondary malignancies [see Warnings and Precautions ( 5.5 )] • Hepatotoxicity including liver necrosis and VOD [see Warnings and Precautions ( 5.6) ]
7.3Effect of Cyclophosphamide on Other Drugs Metronidazole Acute encephalopathy has been reported in a patient receiving cyclophosphamide and metronidazole. Monitor for neurologic toxicities in patients receiving metronidazole. Tamoxifen Concomitant use of tamoxifen and a cyclophosphamide-containing chemotherapy regimen may increase the risk of thromboembolic complications.
Monitor for signs and symptoms of thromboembolic events in patients receiving tamoxifen. Coumarins Both increased and decreased warfarin effect have been reported in patients receiving warfarin and cyclophosphamide. Monitor anticoagulant activity closely in patients receiving warfarin or other coumarins.
Cyclosporine Concomitant administration of cyclophosphamide may decrease serum concentrations of cyclosporine. This interaction may result in an increased incidence of graft-versus-host disease. Monitor for signs and symptoms of graft-versus-host disease in patients receiving cyclosporine.
Depolarizing muscle relaxants If a patient has been treated with cyclophosphamide within 10 days of general anesthesia, alert the anesthesiologist. Cyclophosphamide causes a marked and persistent inhibition of cholinesterase activity. Prolonged apnea may occur with concurrent depolarizing muscle relaxants (e.g., succinylcholine).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Advise not to breastfeed. ( 8.2 ) • Renal Impairment: Monitor for toxicity in patients with moderate and severe renal impairment. ( 8.6 , 12.3 )
8.1Pregnancy Risk Summary Based on its mechanism of action and published reports of effects in pregnant patients or animals, Cyclophosphamide Injection can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology ( 12.1 ) and Nonclinical Toxicology ( 13.1 )] . Exposure to cyclophosphamide during pregnancy may cause fetal malformations, miscarriage, fetal growth retardation, and toxic effects in the newborn [see Data] . Cyclophosphamide is teratogenic and embryo-fetal toxic in mice, rats, rabbits and monkeys [see Data] .
Advise pregnant women and females of reproductive potential of the potential risk to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies.
Data Human Data Malformations of the skeleton, palate, limbs and eyes as well as miscarriage have been reported after exposure to cyclophosphamide in the first trimester. Fetal growth retardation and toxic effects manifesting in the newborn, including leukopenia, anemia, pancytopenia, severe bone marrow hypoplasia, and gastroenteritis have been reported after exposure to cyclophosphamide. Animal Data Administration of cyclophosphamide to pregnant mice, rats, rabbits, and monkeys during the period of organogenesis at doses at or below the dose in patients based on body surface area resulted in various malformations, which included neural tube defects, limb and digit defects and other skeletal anomalies, cleft lip and palate, and reduced skeletal ossification.
8.2Lactation Risk Summary Cyclophosphamide is present in breast milk. Neutropenia, thrombocytopenia, low hemoglobin, and diarrhea have been reported in infants breast fed by women treated with cyclophosphamide. Because of the potential for serious adverse reactions in a breastfed child, advise lactating women not to breastfeed during the treatment and for 1 week after the last dose.
8.3Females and Males of Reproductive Potential Cyclophosphamide Injection can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations ( 8.1 )] . Pregnancy Testing Verify the pregnancy status of females of reproductive potential prior to the initiation of Cyclophosphamide Injection. Contraception Females Advise female patients of reproductive potential to use effective contraception during treatment with Cyclophosphamide Injection and for up to 1 year after therapy.
Males Based on findings in genetic toxicity and animal reproduction studies, advise male patients with female partners of reproductive potential to use effective contraception during treatment with Cyclophosphamide Injection for 4 months after therapy [see Nonclinical Toxicology ( 13.1 )] . Infertility Females Amenorrhea, transient or permanent, associated with decreased estrogen and increased gonadotropin secretion develops in a proportion of women treated with cyclophosphamide. Affected patients generally resume regular menses within a few months after cessation of therapy.
The risk of premature menopause with cyclophosphamide increases with age. Oligomenorrhea has also been reported in association with cyclophosphamide treatment. Animal data suggest an increased risk of failed pregnancy and malformations may persist after discontinuation of cyclophosphamide as long as oocytes/follicles exist that were exposed to cyclophosphamide during any of their maturation phases.
The exact duration of follicular development in humans is not known but may be longer than 12 months [see Nonclinical Toxicology ( 13.1 )] . Males Men treated with cyclophosphamide may develop oligospermia or azoospermia which are normally as… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on its mechanism of action and published reports of effects in pregnant patients or animals, Cyclophosphamide Injection can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology ( 12.1 ) and Nonclinical Toxicology ( 13.1 )] . Exposure to cyclophosphamide during pregnancy may cause fetal malformations, miscarriage, fetal growth retardation, and toxic effects in the newborn [see Data] . Cyclophosphamide is teratogenic and embryo-fetal toxic in mice, rats, rabbits and monkeys [see Data] .
Advise pregnant women and females of reproductive potential of the potential risk to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies.
Data Human Data Malformations of the skeleton, palate, limbs and eyes as well as miscarriage have been reported after exposure to cyclophosphamide in the first trimester. Fetal growth retardation and toxic effects manifesting in the newborn, including leukopenia, anemia, pancytopenia, severe bone marrow hypoplasia, and gastroenteritis have been reported after exposure to cyclophosphamide. Animal Data Administration of cyclophosphamide to pregnant mice, rats, rabbits, and monkeys during the period of organogenesis at doses at or below the dose in patients based on body surface area resulted in various malformations, which included neural tube defects, limb and digit defects and other skeletal anomalies, cleft lip and palate, and reduced skeletal ossification.
🧒 Pediatric Use ▾
8.4Pediatric Use This cyclophosphamide product is not indicated for use in pediatric patients due to the alcohol and propylene glycol content in this product. If treatment with cyclophosphamide is indicated in a pediatric patient, use a different cyclophosphamide product. Since propylene glycol and alcohol are both metabolized by the same enzymes, co-administration of these excipients may raise systemic exposure to alcohol, particularly in pediatric patients. [see Indications and Usage ( 1 ), Warnings and Precautions ( 5.7 ), and Description ( 11 )] .
Other cyclophosphamide products may have a different amount of alcohol or no alcohol. Pre-pubescent girls treated with cyclophosphamide generally develop secondary sexual characteristics normally and have regular menses. Ovarian fibrosis with apparent complete loss of germ cells after prolonged cyclophosphamide treatment in late pre-pubescence has been reported.
Girls treated with cyclophosphamide who have retained ovarian function after completing treatment are at increased risk of developing premature menopause. Pre-pubescent boys treated with cyclophosphamide develop secondary sexual characteristics normally but may have oligospermia or azoospermia and increased gonadotropin secretion. Some degree of testicular atrophy may occur.
Cyclophosphamide induced azoospermia is reversible in some patients, though the reversibility may not occur for several years after cessation of therapy.
🧓 Geriatric Use ▾
8.5Geriatric Use There is insufficient data from clinical studies of cyclophosphamide available for patients 65 years of age and older to determine whether they respond differently than younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac functioning, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE No specific antidote for cyclophosphamide is known. Overdosage should be managed with supportive measures, including appropriate treatment for any concurrent infection, myelosuppression, or cardiac toxicity should it occur. Serious consequences of overdosage include manifestations of dose dependent toxicities such as myelosuppression, urotoxicity, cardiotoxicity (including cardiac failure), veno-occlusive hepatic disease, and stomatitis [see Warnings and Precautions ( 5.1 , 5.2 , 5.3 and 5.6 )] .
Patients who received an overdose should be closely monitored for the development of toxicities, and hematologic toxicity in particular. Cyclophosphamide and its metabolites are dialyzable. Therefore, rapid hemodialysis is indicated when treating any suicidal or accidental overdose or intoxication.
Cystitis prophylaxis with mesna may be helpful in preventing or limiting urotoxic effects with cyclophosphamide overdose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action has not been fully characterized. However, cross-linking of tumor cell DNA may be involved. The active alkylating metabolites of cyclophosphamide interfere with the growth of susceptible rapidly proliferating malignant cells.
12.2Pharmacodynamics Cyclophosphamide exposure-response relationships and the time course of pharmacodynamic response have not been fully characterized.
12.3Pharmacokinetics Cyclophosphamide is a prodrug. Cyclophosphamide pharmacokinetics are linear over the approved recommended dose range. Distribution The volume of distribution of cyclophosphamide is 30 to 50 L.
Cyclophosphamide is approximately 20% protein bound, with no dose dependent changes. Some metabolites are greater than 60% protein bound. Elimination The elimination half-life (t½) of cyclophosphamide ranges from 3 to 12 hours, and clearance (CL) ranges from 4 to
5.6L/h. When cyclophosphamide was administered at 4 g/m 2 (approximately 2 times the approved recommended dosage) over a 90-minutes infusion, concentration-time data demonstrate saturable elimination in parallel with first-order renal elimination. Metabolism Cyclophosphamide is metabolized by cytochrome P450s including CYP2A6, 2B6, 3A, 2C9, and 2C19.
Cyclophosphamide is activated to form 4-hydroxycyclophosphamide, which is in equilibrium with its ring-open tautomer aldophosphamide. 4-hydroxycyclophosphamide and aldophosphamide can undergo oxidation by aldehyde dehydrogenases to form the inactive metabolites 4-ketocyclophosphamide and carboxyphosphamide, respectively. Aldophosphamide can undergo β-elimination to form active metabolites phosphoramide mustard and acrolein.
This spontaneous conversion can be catalyzed by albumin and other proteins. At high doses, the fraction of parent compound cleared by 4-hydroxylation is reduced resulting in non-linear elimination of cyclophosphamide. Cyclophosphamide appears to induce its own metabolism.
This auto-induction results in an increase in CL, increased formation of active 4-hydroxycyclophosphamide and shortened t½ following multiple doses administered at 12-to-24-hour interval. Excretion Cyclophosphamide and its metabolites are eliminated by hepatic and renal pathways. Cyclophosphamide is primarily excreted as metabolites.
Ten to 20% is excreted unchanged in the urine. A small percentage of cyclophosphamide may be eliminated unchanged in bile. Specific Populations Renal Impairment Following one-hour intravenous infusion, cyclophosphamide AUC increased by 38% in patients with CLcr of 25 to 50 mL/min, by 77% in patients with CLcr of 10 to 24 mL/min and by 23% in the hemodialysis group (CLcr of < 10 mL/min) compared to the control group (CLcr≥ 80 mL/min).
Cyclophosphamide is dialyzable. Dialysis clearance averaged 104 mL/min, which is similar to the metabolic clearance of 95 mL/min for cyclophosphamide. A mean of 37% of the administered dose of cyclophosphamide was removed during a 4-hour hemodialysis period.
The t½ was 3.3 hours in patients during hemodialysis, a 49% reduction compared to t½ of 6.5 hours in uremic patients. Hepatic Impairment Cyclophosphamide CL is decreased by 40% (45 ±
8.6L/kg) and t½ is prolonged by 64% (12.5 ± 1 hours) in patients with hepatic impairment with a mean bilirubin 3.5 mg/dL and mean AST 90 IU/L compared to patients with normal hepatic function (mean bilirubin 0.5 mg/dL, mean AST 10 IU/L).
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action has not been fully characterized. However, cross-linking of tumor cell DNA may be involved. The active alkylating metabolites of cyclophosphamide interfere with the growth of susceptible rapidly proliferating malignant cells.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Cyclophosphamide Injection, 100 mg/mL is a sterile ready-to-dilute, clear, colorless to pale-yellow solution in a multiple-dose vial available in the following strengths: Strength NDC Number Volume 500 mg/5 mL 0781-3528-10 Carton of one 5 mL Multiple-Dose Vial 1,000 mg/10 mL 0781-3529-10 Carton of one 10 mL Multiple-Dose Vial 2,000 mg/20 mL 0781-3530-10 Carton of one 20 mL Multiple-Dose Vial Store vials refrigerated at 2°C to 8°C (36°F to 46°F). Cyclophosphamide is a hazardous product.
Follow special handling and disposal procedures. 1
📋 Description ▾
11 DESCRIPTION Cyclophosphamide is an alkylating drug. It is a synthetic antineoplastic drug chemically related to the nitrogen mustards. The chemical name for cyclophosphamide is 2-[bis(2-chloroethyl)amino]tetrahydro-2H-1,3,2-oxazaphosphorine 2-oxide monohydrate, and has the following structural formula: Cyclophosphamide is a white crystalline powder with the molecular formula C 7 H 15 Cl 2 N 2 O 2 P•H 2 O and a molecular weight of 279.1.
Cyclophosphamide is soluble in water and freely soluble in alcohol. Cyclophosphamide Injection, 100 mg/mL is a sterile ready-to-dilute, clear, colorless to pale-yellow solution in a multiple-dose vial available as 500 mg/5 mL, 1,000 mg/10 mL, and 2,000 mg/20 mL strengths. • 500 mg vial contains 534.5 mg cyclophosphamide monohydrate equivalent to 500 mg cyclophosphamide, 2.92 g dehydrated alcohol (equivalent to 73.9 % v/v) and 0.96 g propylene glycol. • 1,000 mg vial contains 1,069 mg cyclophosphamide monohydrate equivalent to 1,000 mg cyclophosphamide, 5.85 g dehydrated alcohol (equivalent to 73.9 % v/v) and 1.92 g propylene glycol. • 2,000 mg vial contains 2,138 mg cyclophosphamide monohydrate equivalent to 2,000 mg cyclophosphamide, 11.69 g dehydrated alcohol (equivalent to 73.9 % v/v) and 3.84 g propylene glycol. chemical-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient of the following: Myelosuppression, Immunosuppression, Bone Marrow Failure, and Infections • Inform patients of the possibility of myelosuppression, immunosuppression, and infections. Explain the need for routine blood cell counts. Instruct patients to monitor their temperature frequently and immediately report any occurrence of fever [see Warnings and Precautions ( 5.1 )] .
Urinary Tract and Renal Toxicity • Advise the patient to report urinary symptoms (patients should report if their urine has turned a pink or red color) and the need for increasing fluid intake and frequent voiding [see Warnings and Precautions ( 5.2 )] . Cardiotoxicity • Inform patients of the possibility of cardiotoxicity (which may be fatal). • Advise patients to contact a healthcare professional immediately for any of the following: new onset or worsening shortness of breath, cough, swelling of the ankles/legs, palpitations, weight gain of more than 5 pounds in 24 hours, dizziness or loss of consciousness [see Warnings and Precautions ( 5.3 )] .
Pulmonary Toxicity • Warn patients of the possibility of developing non-infectious pneumonitis. Advise patients to report promptly any new or worsening respiratory symptoms [see Warnings and Precautions ( 5.4 )] . Alcohol Content • Explain to patients the possible effects of the alcohol content in Cyclophosphamide Injection, including possible effects on the central nervous system.
Patients in whom alcohol should be avoided or minimized should consider the alcohol content of Cyclophosphamide Injection. Alcohol could impair their ability to drive or use machines immediately after infusion [see Warnings and Precautions ( 5.7 )] . Secondary Malignancies • Inform patients that there is an increased risk of secondary malignancies with Cyclophosphamide Injection [see Warnings and Precautions (5.5)].
Embryo-Fetal Toxicity • Inform female patients of the risk to a fetus and potential loss of the pregnancy. Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions ( 5.8 ) and Use in Specific Populations ( 8.1 )] . • Advise females of reproductive potential to use effective contraception during treatment and for up to 1 year after completion of therapy [see Warning and Precautions ( 5.8 ) and Use in Specific Population ( 8.1 , 8.3 )] . • Advise male patients with female partners of reproductive potential to use effective contraception during treatment and for 4 months after completion of therapy [see Warnings and Precautions ( 5.8 ) and Use in Specific Populations ( 8.1 , 8.3 )] .
Lactation • Advise women not to breastfeed during treatment and for 1 week after the last dose of Cyclophosphamide Injection [see Use in Specific Populations ( 8.2 )] . Infertility • Advise patients that Cyclophosphamide Injection may impair fertility in males and females of reproductive potential [see Warnings and Precautions ( 5.9 ) and Use in Specific Populations ( 8.3 , 8.4 )] . Common Adverse Reactions • Explain to patients that side effects such as nausea, vomiting, stomatitis, impaired wound healing, amenorrhea, premature menopause, sterility, and hair loss may be associated with cyclophosphamide administration.
Other undesirable effects (including, e.g., dizziness, blurred vision, visual impairment) could affect the ability to drive or use machines [see Adverse Reactions ( 6.1 )] . Hydration and Important Administration Instructions • Advise the patients that during or immediately after the administration, adequate amounts of fluid are required to reduce the risk of urinary tract toxicity [see Dosage and Administration ( 2.1 )] . Manufactured by FAREVA Unterach GmbH for Sandoz Inc., Princeton, NJ 08540
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Cyclophosphamide is a prodrug. Cyclophosphamide pharmacokinetics are linear over the approved recommended dose range. Distribution The volume of distribution of cyclophosphamide is 30 to 50 L.
Cyclophosphamide is approximately 20% protein bound, with no dose dependent changes. Some metabolites are greater than 60% protein bound. Elimination The elimination half-life (t½) of cyclophosphamide ranges from 3 to 12 hours, and clearance (CL) ranges from 4 to
5.6L/h. When cyclophosphamide was administered at 4 g/m 2 (approximately 2 times the approved recommended dosage) over a 90-minutes infusion, concentration-time data demonstrate saturable elimination in parallel with first-order renal elimination. Metabolism Cyclophosphamide is metabolized by cytochrome P450s including CYP2A6, 2B6, 3A, 2C9, and 2C19.
Cyclophosphamide is activated to form 4-hydroxycyclophosphamide, which is in equilibrium with its ring-open tautomer aldophosphamide. 4-hydroxycyclophosphamide and aldophosphamide can undergo oxidation by aldehyde dehydrogenases to form the inactive metabolites 4-ketocyclophosphamide and carboxyphosphamide, respectively. Aldophosphamide can undergo β-elimination to form active metabolites phosphoramide mustard and acrolein.
This spontaneous conversion can be catalyzed by albumin and other proteins. At high doses, the fraction of parent compound cleared by 4-hydroxylation is reduced resulting in non-linear elimination of cyclophosphamide. Cyclophosphamide appears to induce its own metabolism.
This auto-induction results in an increase in CL, increased formation of active 4-hydroxycyclophosphamide and shortened t½ following multiple doses administered at 12-to-24-hour interval. Excretion Cyclophosphamide and its metabolites are eliminated by hepatic and renal pathways. Cyclophosphamide is primarily excreted as metabolites.
Ten to 20% is excreted unchanged in the urine. A small percentage of cyclophosphamide may be eliminated unchanged in bile. Specific Populations Renal Impairment Following one-hour intravenous infusion, cyclophosphamide AUC increased by 38% in patients with CLcr of 25 to 50 mL/min, by 77% in patients with CLcr of 10 to 24 mL/min and by 23% in the hemodialysis group (CLcr of < 10 mL/min) compared to the control group (CLcr≥ 80 mL/min).
Cyclophosphamide is dialyzable. Dialysis clearance averaged 104 mL/min, which is similar to the metabolic clearance of 95 mL/min for cyclophosphamide. A mean of 37% of the administered dose of cyclophosphamide was removed during a 4-hour hemodialysis period.
The t½ was 3.3 hours in patients during hemodialysis, a 49% reduction compared to t½ of 6.5 hours in uremic patients. Hepatic Impairment Cyclophosphamide CL is decreased by 40% (45 ±
8.6L/kg) and t½ is prolonged by 64% (12.5 ± 1 hours) in patients with hepatic impairment with a mean bilirubin 3.5 mg/dL and mean AST 90 IU/L compared to patients with normal hepatic function (mean bilirubin 0.5 mg/dL, mean AST 10 IU/L).
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cyclophosphamide exposure-response relationships and the time course of pharmacodynamic response have not been fully characterized.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Cyclophosphamide administered by different routes, including intravenous, subcutaneous or intraperitoneal injection, or in drinking water, caused tumors in both mice and rats. In addition to leukemia and lymphoma, benign and malignant tumors were found at various tissue sites, including urinary bladder, mammary gland, lung, liver, and injection site [see Warnings and Precautions ( 5.5 )] . Cyclophosphamide was mutagenic and clastogenic in multiple in vitro and in vivo genetic toxicology studies.
Cyclophosphamide is genotoxic in male and female germ cells. Animal data indicate that exposure of oocytes to cyclophosphamide during follicular development may result in a decreased rate of implantations and viable pregnancies, and in an increased risk of malformations. Male mice and rats treated with cyclophosphamide show alterations in male reproductive organs (e.g., decreased weights, atrophy, changes in spermatogenesis), and decreases in reproductive potential (e.g., decreased implantations and increased post-implantation loss) and increases in fetal malformations when mated with untreated females [see Use in Specific Populations ( 8.3 )] .
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Cyclophosphamide administered by different routes, including intravenous, subcutaneous or intraperitoneal injection, or in drinking water, caused tumors in both mice and rats. In addition to leukemia and lymphoma, benign and malignant tumors were found at various tissue sites, including urinary bladder, mammary gland, lung, liver, and injection site [see Warnings and Precautions ( 5.5 )] . Cyclophosphamide was mutagenic and clastogenic in multiple in vitro and in vivo genetic toxicology studies.
Cyclophosphamide is genotoxic in male and female germ cells. Animal data indicate that exposure of oocytes to cyclophosphamide during follicular development may result in a decreased rate of implantations and viable pregnancies, and in an increased risk of malformations. Male mice and rats treated with cyclophosphamide show alterations in male reproductive organs (e.g., decreased weights, atrophy, changes in spermatogenesis), and decreases in reproductive potential (e.g., decreased implantations and increased post-implantation loss) and increases in fetal malformations when mated with untreated females [see Use in Specific Populations ( 8.3 )] .
📚 References ▾
15 REFERENCES 1. OSHA Hazardous Drugs. OSHA . http://www.osha.gov/SLTC/hazardousdrugs/index.html.
📄 Recent Major Changes ▾
Dosage and Administration ( 2.2 ) 12/2024
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL – 5 mL Carton NDC 0781-3528-10 Sterile Cyclophosphamide Injection 500 mg/5 mL (100 mg/mL) Must Dilute Before Intravenous Use Hazardous Drug Rx Only One 5 mL Multiple-Dose Vial SANDOZ 5ml-carton
PRINCIPAL DISPLAY PANEL – 10 mL Carton NDC 0781-3529-10 Sterile Cyclophosphamide Injection 1,000 mg/10 mL (100 mg/mL) Must Dilute Before Intravenous Use Hazardous Drug Rx Only One 10 mL Multiple-Dose Vial SANDOZ 10ml-carton
PRINCIPAL DISPLAY PANEL – 20 mL Carton NDC 0781-3530-10 Sterile Cyclophosphamide Injection 2,000 mg/20 mL (100 mg/mL) Must Dilute Before Intravenous Use Hazardous Drug Rx Only One 20 mL Multiple-Dose Vial SANDOZ 20ml-carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |