
bendamustine hydrochloride 100 mg/20mL Injection, Powder, Lyophilized, For Solution — NDC 16729-251-05 (Billing 16729-0251-05)
This is a package of bendamustine hydrochloride 100 mg/20mL Injection, Powder, Lyophilized, For Solution from Accord Healthcare, Inc., marketed since Dec 2022 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 16729-251-05 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 16729 labeler · 251 product · 05 package
- Package marketed since
- Dec 7, 2022
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC)
- 0316729251051
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 042496
- GCN: 12014
- HICL (First Databank): 016785
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 1805001
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Alkylating Drug class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Bendamustine injection is used to treat chronic lymphocytic leukemia (CLL; a type of cancer of the white blood cells). Bendamustine injection is also used to treat a type of non-Hodgkins lymphoma (NHL: cancer that begins in a type of white blood cell that normally fights infection) that is slow spreading, but has continued to worsen during or after treatment with another medication. Bendamustine is in a class of medications called alkylating agents. It works by killing existing cancer cells and limiting the growth of new cancer cells.
Read the full MedlinePlus article ↗- It treats chronic lymphocytic leukemia (CLL) and indolent B-cell non-Hodgkin lymphoma that has progressed during or within six months of rituximab. It is a chemotherapy drug given...
- A healthcare professional gives it as an IV infusion on two days in a row of each cycle. How long each infusion takes depends on the product. Your team will schedule everything and...
- Nausea, vomiting, tiredness and fever are common. Low blood counts are also common, and your team will monitor them. Diarrhea, constipation, rash and headache can happen too.
- Call right away for fever, chills or other signs of infection. Also call for rash, itching or swelling during or after an infusion, blistering or peeling skin, redness or pain at t...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Bendamustine Hydrochloride — tap one for details:
Bendamustine Hydrochloride may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9033 | $2.960 / J9033 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 16729-0251-05 You're viewing this Main listing | 1 VIAL, SINGLE-DOSE in 1 CARTON / 20 mL in 1 VIAL, SINGLE-DOSE | 2022-12-07 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| bendamustine hydrochloride 100 mg/20mLthis 16729-0251-05 | Accord | 1 vial | — | AP | FDA listed | — |
| Bendamustine Hydrochloride 100 mg/20mL 55150-0392-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Treanda 100 mg/20mL 63459-0391-20 | Cephalon, | 1 vial | — | AP | FDA listed | — |
| bendamustine hydrochloride 100 mg/20mL 68001-0572-41 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Bendamustine 100 mg/20mL 71288-0103-20 | Meitheal | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
1 inactive ingredient listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Accord Healthcare, Inc. labeler code 16729
- ropinirole 5 mg Tablet, Film Coated NDC 16729-238-01
- Dexmedetomidine 100 ug/mL Injection, Solution NDC 16729-239-93
- Zoledronic acid 4 mg/5mL Injection NDC 16729-242-31
- Topotecan 1 mg/mL Injection NDC 16729-243-31
- PEMETREXED 1 g/40mL Injection, Powder, Lyophilized, For Solution NDC 16729-244-38
- bendamustine hydrochloride 25 mg/5mL Injection, Powder, Lyophilized, For Solution NDC 16729-250-03
- Mycophenolic Acid 180 mg Tablet, Delayed Release NDC 16729-261-29
- DOCETAXEL 20 mg/mL Injection, Solution, Concentrate NDC 16729-267-63
- Prasugrel 5 mg Tablet, Film Coated NDC 16729-272-10
- Prasugrel 10 mg Tablet, Film Coated NDC 16729-273-10
- Bivalirudin 250 mg/5mL Injection, Powder, Lyophilized, For Solution NDC 16729-275-67
- Fluorouracil 50 mg/mL Injection, Solution NDC 16729-276-11
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Bendamustine hydrochloride for Injection is an alkylating drug indicated for treatment of patients with: Chronic lymphocytic leukemia (CLL). Efficacy relative to first line therapies other than chlorambucil has not been established. ( 1.1 ) Indolent B-cell non-Hodgkin lymphoma (NHL) that has progressed during or within six months of treatment with rituximab or a rituximab-containing regimen. ( 1.2 )
1.1Chronic Lymphocytic Leukemia (CLL) Bendamustine hydrochloride for Injection is indicated for the treatment of patients with chronic lymphocytic leukemia. Efficacy relative to first line therapies other than chlorambucil has not been established.
1.2Non-Hodgkin Lymphoma (NHL) Bendamustine hydrochloride for Injection is indicated for the treatment of patients with indolent B-cell non-Hodgkin lymphoma that has progressed during or within six months of treatment with rituximab or a rituximab-containing regimen.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Bendamustine hydrochloride is available in two formulations, a solution (Bendamustine Hydrochloride Injection) and a lyophilized powder (Bendamustine Hydrochloride for Injection). ( 2.1 ) For CLL : 100 mg/m 2 infused intravenously over 30 minutes on Days 1 and 2 of a 28-day cycle, up to 6 cycles ( 2.2 ) For NHL : 120 mg/m 2 infused intravenously over 60 minutes on Days 1 and 2 of a 21-day cycle, up to 8 cycles ( 2.3 )
2.1Selection of Bendamustine Hydrochloride Formulation to Administer Bendamustine hydrochloride is available in two formulations, a solution (Bendamustine hydrochloride Injection) and a lyophilized powder (Bendamustine hydrochloride for Injection). Bendamustine hydrochloride Injection and the reconstituted Bendamustine hydrochloride for Injection have different concentrations of bendamustine hydrochloride. The concentration of bendamustine hydrochloride in the solution is 90 mg/mL and the concentration of bendamustine hydrochloride in the reconstituted solution of lyophilized powder is 5 mg/mL.
Do not mix or combine the two formulations. If a closed system transfer device (CSTD) or adapter that contains polycarbonate or acrylonitrile-butadiene-styrene (ABS) is used as supplemental protection prior to dilution 1 , only use Bendamustine hydrochloride for Injection, the lyophilized powder formulation [see How Supplied/Storage and Handling ( 16 )] .
2.2Dosing Instructions for CLL Recommended Dosage: The recommended dose is 100 mg/m 2 administered intravenously over 30 minutes on Days 1 and 2 of a 28-day cycle, up to 6 cycles. Dose Delays, Dose Modifications and Reinitiation of Therapy for CLL: Delay Bendamustine hydrochloride for Injection administration in the event of Grade 4 hematologic toxicity or clinically significant ≥ Grade 2 non-hematologic toxicity. Once non-hematologic toxicity has recovered to less than or equal to Grade 1 and/or the blood counts have improved [Absolute Neutrophil Count (ANC) ≥ 1 x 10 9 /L, platelets ≥ 75 x 10 9 /L], reinitiate Bendamustine hydrochloride for Injection at the discretion of the treating physician.
In addition, consider dose reduction. [see Warnings and Precautions ( 5.1 )] Dose modifications for hematologic toxicity: for Grade 3 or greater toxicity, reduce the dose to 50 mg/m 2 on Days 1 and 2 of each cycle; if Grade 3 or greater toxicity recurs, reduce the dose to 25 mg/m 2 on Days 1 and 2 of each cycle. Dose modifications for non-hematologic toxicity: for clinically significant Grade 3 or greater toxicity, reduce the dose to 50 mg/m 2 on Days 1 and 2 of each cycle. Consider dose re-escalation in subsequent cycles at the discretion of the treating physician.
2.3Dosing Instructions for NHL Recommended Dosage: The recommended dose is 120 mg/m 2 administered intravenously over 60 minutes on Days 1 and 2 of a 21-day cycle, up to 8 cycles. Dose Delays, Dose Modifications and Reinitiation of Therapy for NHL: Delay Bendamustine hydrochloride for Injection administration in the event of a Grade 4 hematologic toxicity or clinically significant greater than or equal to Grade 2 non-hematologic toxicity. Once non-hematologic toxicity has recovered to ≤ Grade 1 and/or the blood counts have improved [Absolute Neutrophil Count (ANC) ≥ 1 x 10 9 /L, platelets ≥ 75 x 10 9 /L], reinitiate Bendamustine hydrochloride for Injection at the discretion of the treating physician.
In addition, consider dose reduction. [see Warnings and Precautions ( 5.1 )] Dose modifications for hematologic toxicity: for Grade 4 toxicity, reduce the dose to 90 mg/m 2 on Days 1 and 2 of each cycle; if Grade 4 toxicity recurs, reduce the dose to 60 mg/m 2 on Days 1 and 2 of each cycle. Dose modifications for non-hematologic toxicity: for Grade 3 or greater toxicity, reduce the dose to 90 mg/m 2 on Days 1 and 2 of each cycle; if Grade 3 or greater toxicity recurs, reduce the dose to 60 mg/m 2 on Days 1 and 2 of each cycle.
2.4Preparation for Intravenous Administration Bendamustine hydroc… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Bendamustine hydrochloride for Injection, USP: 25 mg or 100 mg white to off-white lyophilized powder in a single-dose vial for reconstitution. For Injection : 25 mg or 100 mg lyophilized powder in a single-dose vial for reconstitution. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Bendamustine hydrochloride for Injection is contraindicated in patients with a known hypersensitivity (e.g., anaphylactic and anaphylactoid reactions) to bendamustine. [see Warnings and Precautions ( 5.4 )] Bendamustine hydrochloride for Injection is contraindicated in patients with a history of a hypersensitivity reaction to bendamustine. Reactions have included anaphylaxis and anaphylactoid reactions. ( 4 , 5.4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Myelosuppression: Delay or reduce dose and restart treatment based on ANC and platelet count recovery. ( 5.1 ) Infections: Monitor for fever and other signs of infection or reactivation of infections and treat promptly. ( 5.2 ) Progressive multifocal leukoencephalopathy (PML): Monitor for new or worsening neurological, cognitive or behavioral signs or symptoms suggestive of PML.( 5.3 ) Anaphylaxis and Infusion Reactions: Severe and anaphylactic reactions have occurred; monitor clinically and discontinue drug for severe reactions.
Pre-medicate in subsequent cycles for milder reactions. ( 5.4 ) Tumor Lysis Syndrome: May lead to acute renal failure and death; anticipate and use supportive measures in patients at high risk. ( 5.5 ) Skin Reactions: Discontinue for severe skin reactions.
Cases of SJS, DRESS and TEN, some fatal, have been reported. ( 5.6 ) Hepatotoxicity: Monitor liver chemistry tests prior to and during treatment. ( 5.7 ) Other Malignancies: Pre-malignant and malignant diseases have been reported.
( 5.8 ) Extravasation Injury: Take precautions to avoid extravasation, including monitoring intravenous infusion site during and after administration. ( 5.9 ) Embryo-Fetal Toxicity: Can cause fetal harm. Advise females of reproductive potential of the potential risk to a fetus and to use an effective method of contraception.
( 5.10 , 8.1 , 8.3 )
5.1Myelosuppression Bendamustine hydrochloride caused severe myelosuppression (Grade 3-4) in 98% of patients in the two NHL studies [see Adverse Reactions ( 6.1 )]. Three patients (2%) died from myelosuppression-related adverse reactions; one each from neutropenic sepsis, diffuse alveolar hemorrhage with Grade 3 thrombocytopenia, and pneumonia from an opportunistic infection (CMV). Monitor complete blood counts, including leukocytes, platelets, hemoglobin (Hgb), and neutrophils frequently.
In the clinical trials, blood counts were monitored every week initially. Hematologic nadirs were observed predominantly in the third week of therapy. Myelosuppression may require dose delays and/or subsequent dose reductions if recovery to the recommended values has not occurred by the first day of the next scheduled cycle.
Prior to the initiation of the next cycle of therapy, the ANC should be ≥ 1 x 10 9 /L and the platelet count should be ≥ 75 x 10 9 /L. [see Dosage and Administration ( 2.2 ) and ( 2.3 )]
5.2Infections Infection, including pneumonia, sepsis, septic shock, hepatitis and death has occurred in adult and pediatric patients in clinical trials and in postmarketing reports [see Adverse Reactions ( 6.1 , 6.2 )] . Patients with myelosuppression following treatment with Bendamustine hydrochloride for Injection are more susceptible to infections. Advise patients with myelosuppression following bendamustine hydrochloride treatment to contact a physician if they have symptoms or signs of infection.
Patients treated with bendamustine hydrochloride are at risk for reactivation of infections including (but not limited to) hepatitis B, cytomegalovirus, Mycobacterium tuberculosis, and herpes zoster. Patients should undergo appropriate measures (including clinical and laboratory monitoring, prophylaxis, and treatment) for infection and infection reactivation prior to administration.
5.3Progressive Multifocal Leukoencephalopathy (PML) Progressive multifocal leukoencephalopathy (PML), including fatal cases, have occurred following treatment with bendamustine, primarily in combination with rituximab or obinutuzumab [see Adverse Reactions ( 6.2 )] . Consider PML in the differential diagnosis in patients with new or worsening neurological, cognitive or behavioral signs or symptoms. If PML is suspected, withhold bendamustine hydrochloride treatment and perform appropriate diagnostic evaluations.
Consider discontinuation or reduction of any concomitant chemotherapy or immunosuppressive therapy in patients who develop PML.
5.4Anaphylaxis and Infusion Reactions Infusion rea… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions have been associated with bendamustine hydrochloride in clinical trials and are discussed in greater detail in other sections of the label. Myelosuppression [see Warnings and Precautions ( 5.1 )] Infections [see Warnings and Precautions ( 5.2 )] Progressive Multifocal Leukoencephalopathy [see Warnings and Precautions ( 5.3 )] Anaphylaxis and Infusion Reactions [see Warnings and Precautions ( 5.4 )] Tumor Lysis Syndrome [see Warnings and Precautions ( 5.5 )] Skin Reactions [see Warnings and Precautions ( 5.6 )] Hepatotoxicity [see Warnings and Precautions ( 5.7 )] Other Malignancies [see Warnings and Precautions ( 5.8 )] Extravasation Injury [see Warnings and Precautions ( 5.9 )] Adverse reactions (frequency >5%) during infusion and within 24 hours post-infusion are nausea and fatigue.
( 6.1 ) Most common adverse reactions (≥15%) for CLL are anemia, thrombocytopenia, neutropenia, lymphopenia, leukopenia, pyrexia, nausea, vomiting. ( 6.1 , 6.2 ) Most common adverse reactions (≥15%) for NHL are lymphopenia, leukopenia, anemia, neutropenia, thrombocytopenia, nausea, fatigue, vomiting, diarrhea, pyrexia, constipation, anorexia, cough, headache, weight decreased, dyspnea, rash, and stomatitis. ( 6.1 , 6.2 ) To report SUSPECTED ADVERSE REACTIONS, contact Accord Healthcare Inc. at 1-866-941-7875 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Chronic Lymphocytic Leukemia The data described below reflect exposure to bendamustine hydrochloride in 153 patients. Bendamustine hydrochloride was studied in an active-controlled, randomized trial.
The population was 45-77 years of age, 63% male, 100% white, and had treatment naïve CLL. All patients started the study at a dose of 100 mg/m 2 intravenously over 30 minutes on Days 1 and 2 every 28 days. Adverse reactions were reported according to NCI CTC v.2.0.
In the randomized CLL clinical study, non-hematologic adverse reactions (any grade) in the bendamustine hydrochloride group that occurred with a frequency greater than 15% were pyrexia (24%), nausea (20%), and vomiting (16%). Other adverse reactions seen frequently in one or more studies included asthenia, fatigue, malaise, and weakness; dry mouth; somnolence; cough; constipation; headache; mucosal inflammation and stomatitis. Worsening hypertension was reported in 4 patients treated with bendamustine hydrochloride in the randomized CLL clinical study and in none treated with chlorambucil.
Three of these 4 adverse reactions were described as a hypertensive crisis and were managed with oral medications and resolved. The most frequent adverse reactions leading to study withdrawal for patients receiving bendamustine hydrochloride were hypersensitivity (2%) and pyrexia (1%). Table 1 contains the treatment emergent adverse reactions, regardless of attribution, that were reported in ≥ 5% of patients in either treatment group in the randomized CLL clinical study.
Table 1: Non- Hematologic Adverse Reactions Occurring in Randomized CLL Clinical Study in at Least 5% of Patients Number (%) of patients Bendamustine hydrochloride (N=153) Chlorambucil (N=143) Body System/ Adverse Reaction All Grades Grade 3/4 All Grades Grade 3/4 Total number of patients with at least 1 adverse reaction 121 (79) 52 (34) 96 (67) 25 (17) Gastrointestinal disorders Nausea 31 (20) 1 (<1) 21 (15) 1 (<1) Vomiting 24 (16) 1 (<1) 9 (6) 0 Diarrhea 14 (9) 2 (1) 5 (3) 0 General disorders and administration site conditions Pyrexia 36 (24) 6 (4) 8 (6) 2 (1) Fatigue 14 (9) 2 (1) 8 (6) 0 Asthenia 13 (8) 0 6 (4) 0 Chills 9 (6) 0 1 (<1) 0 Immune system disorders Hypersensitivity 7 (5) 2 (1) 3 (2) 0 Infections and infesta… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Consider alternative therapies that are not CYP1A2 inducers or inhibitors during treatment with Bendamustine hydrochloride. ( 7 )
7.1Effect of Other Drugs on Bendamustine Hydrochloride CYP1A2 Inhibitors The coadministration of bendamustine hydrochloride with CYP1A2 inhibitors may increase bendamustine plasma concentrations and may result in increased incidence of adverse reactions with bendamustine hydrochloride [see Clinical Pharmacology ( 12.3 )] . Consider alternative therapies that are not CYP1A2 inhibitors during treatment with bendamustine hydrochloride. CYP1A2 Inducers The coadministration of bendamustine hydrochloride with CYP1A2 inducers may decrease bendamustine plasma concentrations and may result in decreased efficacy of bendamustine hydrochloride [see Clinical Pharmacology ( 12.3 )] .
Consider alternative therapies that are not CYP1A2 inducers during treatment with bendamustine hydrochloride.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 ) Infertility: May impair fertility. ( 8.3 ) Renal Impairment: Do not use in patients with creatinine clearance <30 mL/min. ( 8.6 ) Hepatic Impairment: Do not use in patients with total bilirubin 1.5-3 x ULN and AST or ALT 2.5-10 x ULN, or total bilirubin >3 x ULN. ( 8.7 )
8.1Pregnancy Risk Summary In animal reproduction studies, intraperitoneal administration of bendamustine to pregnant mice and rats during organogenesis at doses 0.6 to 1.8 times the maximum recommended human dose (MRHD) resulted in embryo-fetal and/or infant mortality, structural abnormalities, and alterations to growth (see Data) . There are no available data on bendamustine hydrochloride use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
Advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal data Bendamustine hydrochloride was intraperitoneally administered once to mice from 210 mg/m 2 (approximately 1.8 times the MRHD) during organogenesis and caused an increase in resorptions, skeletal and visceral malformations (exencephaly, cleft palates, accessory rib, and spinal deformities), and decreased fetal body weights. This dose did not appear to be maternally toxic and lower doses were not evaluated.
Repeat intraperitoneal administration of bendamustine hydrochloride to mice on gestation days 7 to 11 resulted in an increase in resorptions from 75 mg/m 2 (approximately 0.6 times the MRHD) and an increase in abnormalities from 112.5 mg/m 2 (approximately 0.9 times the MRHD), similar to those seen after a single intraperitoneal administration. Bendamustine hydrochloride was intraperitoneally administered once to rats from 120 mg/m 2 (approximately the MRHD) on gestation days 4, 7, 9, 11, or 13 and caused embryo and fetal lethality as indicated by increased resorptions and a decrease in live fetuses.
A significant increase in external (effect on tail, head, and herniation of external organs [exomphalos]) and internal (hydronephrosis and hydrocephalus) malformations were seen in dosed rats.
8.2Lactation Risk Summary There are no data on the presence of bendamustine hydrochloride or its metabolites in either human or animal milk, the effects on the breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions in the breastfed child, advise patients that breastfeeding is not recommended during treatment with bendamustine hydrochloride, and for 1 week after the last dose.
8.3Females and Males of Reproductive Potential Bendamustine hydrochloride can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations ( 8.1 )]. Pregnancy Testing Pregnancy testing is recommended for females of reproductive potential prior to initiation of treatment with bendamustine hydrochloride. Contraception Females Bendamustine hydrochloride can cause embryo-fetal harm when administered to pregnant women [see Use in Specific Populations ( 8.1 )].
Advise female patients of reproductive potential to use effective contraception during treatment with bendamustine hydrochloride and for 6 months after the last dose. Males Based on genotoxicity findings, advise males with female partners of reproductive potential to use effective contraception during treatment with bendamustine hydrochloride and for 3 months after the last dose [see Nonclinical Toxicology ( 13.1 )] . Infertility Males Based on findings from clinical studies, bendamustine hydrochloride may impair male fertility.
Impaired… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary In animal reproduction studies, intraperitoneal administration of bendamustine to pregnant mice and rats during organogenesis at doses 0.6 to 1.8 times the maximum recommended human dose (MRHD) resulted in embryo-fetal and/or infant mortality, structural abnormalities, and alterations to growth (see Data) . There are no available data on bendamustine hydrochloride use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
Advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal data Bendamustine hydrochloride was intraperitoneally administered once to mice from 210 mg/m 2 (approximately 1.8 times the MRHD) during organogenesis and caused an increase in resorptions, skeletal and visceral malformations (exencephaly, cleft palates, accessory rib, and spinal deformities), and decreased fetal body weights. This dose did not appear to be maternally toxic and lower doses were not evaluated.
Repeat intraperitoneal administration of bendamustine hydrochloride to mice on gestation days 7 to 11 resulted in an increase in resorptions from 75 mg/m 2 (approximately 0.6 times the MRHD) and an increase in abnormalities from 112.5 mg/m 2 (approximately 0.9 times the MRHD), similar to those seen after a single intraperitoneal administration. Bendamustine hydrochloride was intraperitoneally administered once to rats from 120 mg/m 2 (approximately the MRHD) on gestation days 4, 7, 9, 11, or 13 and caused embryo and fetal lethality as indicated by increased resorptions and a decrease in live fetuses.
A significant increase in external (effect on tail, head, and herniation of external organs [exomphalos]) and internal (hydronephrosis and hydrocephalus) malformations were seen in dosed rats.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Safety, pharmacokinetics and efficacy were assessed in a single open-label trial (NCT01088984) in patients aged 1 to 19 years with relapsed or refractory acute leukemia, including 27 patients with acute lymphocytic leukemia (ALL) and 16 patients with acute myeloid leukemia (AML). Bendamustine hydrochloride was administered as an intravenous infusion over 60 minutes on Days 1 and 2 of each 21-day cycle.
There was no treatment response (CR+ CRp) in any patient in the Phase 2 portion of the trial at a dose of 120 mg/m 2 . However, 2 patients with ALL achieved CR at a dose of 90 mg/m 2 in the Phase 1 portion of the study. The safety profile in these patients was consistent with that seen in adults, and no new safety signals were identified.
The pharmacokinetics of bendamustine in 43 patients, aged 1 to 19 years (median age of 10 years) were within range of values previously observed in adults given the same dose based on body surface area.
🧓 Geriatric Use ▾
8.5Geriatric Use No overall differences in safety were observed between patients ≥65 years of age and younger patients. Efficacy was lower in patients 65 and over with CLL receiving bendamustine hydrochloride based upon an overall response rate of 47% for patients 65 and over and 70% for younger patients. Progression free survival was also longer in younger patients with CLL receiving bendamustine hydrochloride (19 months vs.
12 months). No overall differences in efficacy in patients with non-Hodgkin Lymphoma were observed between geriatric patients and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE The intravenous LD 50 of bendamustine HCl is 240 mg/m 2 in the mouse and rat. Toxicities included sedation, tremor, ataxia, convulsions and respiratory distress. Across all clinical experience, the reported maximum single dose received was 280 mg/m 2 .
Three of four patients treated at this dose showed ECG changes considered dose-limiting at 7 and 21 days post-dosing. These changes included QT prolongation (one patient), sinus tachycardia (one patient), ST and T wave deviations (two patients) and left anterior fascicular block (one patient). Cardiac enzymes and ejection fractions remained normal in all patients.
No specific antidote for bendamustine hydrochloride overdose is known. Management of overdosage should include general supportive measures, including monitoring of hematologic parameters and ECGs.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Bendamustine is a bifunctional mechlorethamine derivative containing a purine-like benzimidazole ring. Mechlorethamine and its derivatives form electrophilic alkyl groups. These groups form covalent bonds with electron-rich nucleophilic moieties, resulting in interstrand DNA crosslinks.
The bifunctional covalent linkage can lead to cell death via several pathways. Bendamustine is active against both quiescent and dividing cells. The exact mechanism of action of bendamustine remains unknown.
12.2Pharmacodynamics Based on the pharmacokinetics/pharmacodynamics analyses of data from adult NHL patients, nausea increased with increasing bendamustine C max . Cardiac Electrophysiology The effect of bendamustine on the QTc interval was evaluated in 53 patients with indolent NHL and mantle cell lymphoma on Day 1 of Cycle 1 after administration of rituximab at 375 mg/m 2 intravenous infusion followed by a 30-minute intravenous infusion of bendamustine at 90 mg/m 2 /day. No mean changes greater than 20 milliseconds were detected up to one hour post-infusion.
The potential for delayed effects on the QT interval after one hour was not evaluated.
12.3Pharmacokinetics Absorption Following a single IV dose of bendamustine hydrochloride C max typically occurred at the end of infusion. The dose proportionality of bendamustine has not been studied. Distribution The protein binding of bendamustine ranged from 94 to 96% and was concentration independent from 1 to 50 µg/mL.
The blood to plasma concentration ratios in human blood ranged from 0.84 to 0.86 over a concentration range of 10 to 100 µg/mL. The mean steady-state volume of distribution (V ss ) of bendamustine was approximately 20 to 25 L. Elimination After a single intravenous dose of 120 mg/m 2 of bendamustine over 1 hour, the intermediate half-life (t ½ ) of the parent compound is approximately 40 minutes.
The mean terminal elimination t ½ of two active metabolites, γ-hydroxybendamustine (M3) and N desmethylbendamustine (M4) are approximately 3 hours and 30 minutes, respectively. Bendamustine clearance in humans is approximately 700 mL/min. Metabolism Bendamustine is extensively metabolized via hydrolytic, oxidative, and conjugative pathways .
Bendamustine is primarily metabolized via hydrolysis to monohydroxy (HP1) and dihydroxy-bendamustine (HP2) metabolites with low cytotoxic activity in vitro. Two active minor metabolites, M3 and M4, are primarily formed via CYP1A2 in vitro. M3 and M4 concentrations in plasma are 1/10 th and 1/100 th that of the parent compound, respectively.
Excretion Following IV infusion of radiolabeled bendamustine hydrochloride in cancer patients, approximately 76% of the dose was recovered. Approximately 50% of the dose was recovered in the urine (3.3% unchanged) and approximately 25% of the dose was recovered in the feces. Less than 1% of the dose was recovered in the urine as M3 and M4, and less than 5% of the dose was recovered in the urine as HP2.
Specific Populations No clinically meaningful effects on the pharmacokinetics of bendamustine were observed based on age (31 to 84 years), sex, mild to moderate renal impairment (CLcr ≥ 30 mL/min), or hepatic impairment with total bilirubin 1.5 < ULN and AST or ALT < 2.5 × ULN. The effects of severe renal impairment (CLcr < 30 mL/min), or hepatic impairment with total bilirubin 1.5-3 × ULN and AST or ALT 2.5-10 × ULN or total bilirubin > 3 × ULN on the pharmacokinetics of bendamustine is unknown. Race/Ethnicity Exposures in Japanese subjects (n=6) were 40% higher than that in non-Japanese subjects receiving the same dose.
The clinical importance of this difference on the safety and efficacy of bendamustine hydrochloride in Japanese subjects has not been established. Drug Interaction Studies In Vitro Studies Effect of Bendamustine on CYP Substrates Bendamustine did not inhibit CYP1A2, 2C9/10, 2D6, 2E1, or 3A4/5. Bendamustine did not induce metabolism of CYP1A2, CYP2… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Bendamustine is a bifunctional mechlorethamine derivative containing a purine-like benzimidazole ring. Mechlorethamine and its derivatives form electrophilic alkyl groups. These groups form covalent bonds with electron-rich nucleophilic moieties, resulting in interstrand DNA crosslinks.
The bifunctional covalent linkage can lead to cell death via several pathways. Bendamustine is active against both quiescent and dividing cells. The exact mechanism of action of bendamustine remains unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Safe Handling and Disposal Bendamustine hydrochloride is a hazardous drug. Follow applicable special handling and disposal procedures 1 . Care should be exercised in the handling and preparation of solutions prepared from Bendamustine hydrochloride for Injection, USP.
The use of gloves and safety glasses is recommended to avoid exposure in case of breakage of the vial or other accidental spillage. If gloves come in contact with Bendamustine hydrochloride for Injection, USP prior to dilution, remove gloves and follow disposal procedures 1 . If a solution of bendamustine hydrochloride contacts the skin, wash the skin immediately and thoroughly with soap and water.
If bendamustine hydrochloride contacts the mucous membranes, flush thoroughly with water. How Supplied Bendamustine hydrochloride for Injection, USP is supplied in individual cartons as follows: NDC 16729-250-03: 25 mg white to off-white lyophilized powder in a 10 mL amber single-dose vial NDC 16729-251-05: 100 mg white to off-white lyophilized powder in a 20 mL amber single-dose vial Storage Bendamustine hydrochloride for Injection, USP (25 mg/vial or 100 mg/vial lyophilized powder) Bendamustine hydrochloride for Injection, USP may be stored up to 25°C (77°F) with excursions permitted up to 30°C (86°F) (see USP Controlled Room Temperature).
Retain in original package until time of use to protect from light.
📋 Description ▾
11 DESCRIPTION Bendamustine hydrochloride is an alkylating agent. The chemical name of bendamustine hydrochloride, USP is 1H-benzimidazole-2-butanoic acid, 5-[bis(2-chloroethyl)amino]-1- methyl-, monohydrochloride. Its empirical molecular formula is C 16 H 21 Cl 2 N 3 O 2 ∙ HCl, and the molecular weight is 394.7.
Bendamustine hydrochloride contains a mechlorethamine group and a benzimidazole heterocyclic ring with a butyric acid substituent, and has the following structural formula: Bendamustine hydrochloride for Injection, USP (25 mg/vial or 100 mg/vial lyophilized powder) Bendamustine hydrochloride for Injection, USP for intravenous use is supplied as a sterile non-pyrogenic white to off-white lyophilized powder in a single-dose vial. Each 25-mg vial contains 25 mg of bendamustine hydrochloride, USP and 42.5 mg of mannitol, USP.
Each 100-mg vial contains 100 mg of bendamustine hydrochloride, USP and 170 mg of mannitol, USP. The pH of the reconstituted solution is 2.5 to 3.5. Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Allergic (Hypersensitivity) Reactions Inform patients of the possibility of mild or serious allergic reactions and to immediately report rash, facial swelling, or difficulty breathing during or soon after infusion [see Warnings and Precautions ( 5.4 )] . Myelosuppression Inform patients of the likelihood that Bendamustine hydrochloride for Injection will cause a decrease in white blood cells, platelets, and red blood cells, and the need for frequent monitoring of blood counts. Advise patients to report shortness of breath, significant fatigue, bleeding, fever, or other signs of infection [see Warnings and Precautions ( 5.1 )] .
Progressive Multifocal Leukoencephalopathy (PML) Inform patients to immediately contact their healthcare provider if they experience confusion, memory loss, trouble thinking, difficulty talking or walking, vision loss or other neurological or cognitive symptoms [see Warnings and Precautions ( 5.3 )] . Hepatotoxicity Inform patients of the possibility of developing liver function abnormalities and serious hepatic toxicity. Advise patients to immediately contact their health care provider if signs of liver failure occur, including jaundice, anorexia, bleeding or bruising [see Warnings and Precautions ( 5.7 )] .
Fatigue Advise patients that Bendamustine hydrochloride for Injection may cause tiredness and to avoid driving any vehicle or operating any dangerous tools or machinery if they experience this side effect [see Adverse Reactions ( 6.1 )] . Nausea and Vomiting Advise patients that Bendamustine hydrochloride for Injection may cause nausea and/or vomiting. Patients should report nausea and vomiting so that symptomatic treatment may be provided [see Adverse Reactions ( 6.1 )] .
Diarrhea Advise patients that Bendamustine hydrochloride for Injection may cause diarrhea. Patients should report diarrhea to the physician so that symptomatic treatment may be provided [see Adverse Reactions ( 6.1 )] . Rash Advise patients that a rash or itching may occur during treatment with Bendamustine hydrochloride for Injection.
Advise patients to immediately report severe or worsening rash or itching [see Warnings and Precautions ( 5.6 )] . Non-Melanoma Skin Cancer (NMSC) Advise patients to undergo regular skin cancer screenings, and to report any suspicious skin changes to their healthcare provider [see Warnings and Precautions ( 5.8 )] . Embryo-Fetal Toxicity Advise pregnant women and females of reproductive potential of the potential risk to a fetus.
Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions ( 5.10 ), Use in Specific Populations ( 8.1 , 8.3 ), and Nonclinical Toxicology ( 13.1 )] . Advise female patients of reproductive potential to use effective contraception during treatment with Bendamustine hydrochloride for Injection and for 6 months after the last dose [see Use in Specific Populations ( 8.1 , 8.3 )] . Advise males with female partners of reproductive potential to use effective contraception during treatment with Bendamustine hydrochloride for Injection and for 3 months after the last dose [see Use in Specific Populations ( 8.3 ), and Nonclinical Toxicology ( 13.1 )] .
Lactation Advise females not to breastfeed during treatment with Bendamustine hydrochloride for Injection and for 1 week after the last dose [see Use in Specific Populations ( 8.2 )] . Infertility Advise males of reproductive potential that Bendamustine hydrochloride for Injection may impair fertility [see Use in Specific Populations ( 8.3 )] . Manufactured For: Accord Healthcare, Inc., 8041 Arco Corporate Drive, Suite 200, Raleigh, NC 27617, USA.
Manufactured By: Intas Pharmaceuticals Limited, Plot No. : 457, 458, Village – Matoda, Bavla Road, Ta.- Sanand, Dist.- Ahmedabad – 382 210. India. 10 3737 2 6026184 Issued October 2023
🍼 Nursing Mothers ▾
8.2Lactation Risk Summary There are no data on the presence of bendamustine hydrochloride or its metabolites in either human or animal milk, the effects on the breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions in the breastfed child, advise patients that breastfeeding is not recommended during treatment with bendamustine hydrochloride, and for 1 week after the last dose.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Following a single IV dose of bendamustine hydrochloride C max typically occurred at the end of infusion. The dose proportionality of bendamustine has not been studied. Distribution The protein binding of bendamustine ranged from 94 to 96% and was concentration independent from 1 to 50 µg/mL.
The blood to plasma concentration ratios in human blood ranged from 0.84 to 0.86 over a concentration range of 10 to 100 µg/mL. The mean steady-state volume of distribution (V ss ) of bendamustine was approximately 20 to 25 L. Elimination After a single intravenous dose of 120 mg/m 2 of bendamustine over 1 hour, the intermediate half-life (t ½ ) of the parent compound is approximately 40 minutes.
The mean terminal elimination t ½ of two active metabolites, γ-hydroxybendamustine (M3) and N desmethylbendamustine (M4) are approximately 3 hours and 30 minutes, respectively. Bendamustine clearance in humans is approximately 700 mL/min. Metabolism Bendamustine is extensively metabolized via hydrolytic, oxidative, and conjugative pathways .
Bendamustine is primarily metabolized via hydrolysis to monohydroxy (HP1) and dihydroxy-bendamustine (HP2) metabolites with low cytotoxic activity in vitro. Two active minor metabolites, M3 and M4, are primarily formed via CYP1A2 in vitro. M3 and M4 concentrations in plasma are 1/10 th and 1/100 th that of the parent compound, respectively.
Excretion Following IV infusion of radiolabeled bendamustine hydrochloride in cancer patients, approximately 76% of the dose was recovered. Approximately 50% of the dose was recovered in the urine (3.3% unchanged) and approximately 25% of the dose was recovered in the feces. Less than 1% of the dose was recovered in the urine as M3 and M4, and less than 5% of the dose was recovered in the urine as HP2.
Specific Populations No clinically meaningful effects on the pharmacokinetics of bendamustine were observed based on age (31 to 84 years), sex, mild to moderate renal impairment (CLcr ≥ 30 mL/min), or hepatic impairment with total bilirubin 1.5 < ULN and AST or ALT < 2.5 × ULN. The effects of severe renal impairment (CLcr < 30 mL/min), or hepatic impairment with total bilirubin 1.5-3 × ULN and AST or ALT 2.5-10 × ULN or total bilirubin > 3 × ULN on the pharmacokinetics of bendamustine is unknown. Race/Ethnicity Exposures in Japanese subjects (n=6) were 40% higher than that in non-Japanese subjects receiving the same dose.
The clinical importance of this difference on the safety and efficacy of bendamustine hydrochloride in Japanese subjects has not been established. Drug Interaction Studies In Vitro Studies Effect of Bendamustine on CYP Substrates Bendamustine did not inhibit CYP1A2, 2C9/10, 2D6, 2E1, or 3A4/5. Bendamustine did not induce metabolism of CYP1A2, CYP2A6, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2E1, or CYP3A4/5.
Effect of Transporters on Bendamustine Hydrochloride Bendamustine is a substrate of P-glycoprotein and breast cancer resistance protein (BCRP).
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Based on the pharmacokinetics/pharmacodynamics analyses of data from adult NHL patients, nausea increased with increasing bendamustine C max . Cardiac Electrophysiology The effect of bendamustine on the QTc interval was evaluated in 53 patients with indolent NHL and mantle cell lymphoma on Day 1 of Cycle 1 after administration of rituximab at 375 mg/m 2 intravenous infusion followed by a 30-minute intravenous infusion of bendamustine at 90 mg/m 2 /day. No mean changes greater than 20 milliseconds were detected up to one hour post-infusion.
The potential for delayed effects on the QT interval after one hour was not evaluated.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Chronic Lymphocytic Leukemia (CLL) The safety and efficacy of bendamustine hydrochloride were evaluated in an open-label, randomized, controlled multicenter trial comparing bendamustine hydrochloride to chlorambucil. The trial was conducted in 301 previously-untreated patients with Binet Stage B or C (Rai Stages I - IV) CLL requiring treatment. Need-to-treat criteria included hematopoietic insufficiency, B-symptoms, rapidly progressive disease or risk of complications from bulky lymphadenopathy.
Patients with autoimmune hemolytic anemia or autoimmune thrombocytopenia, Richter’s syndrome, or transformation to prolymphocytic leukemia were excluded from the study. The patient populations in the bendamustine hydrochloride and chlorambucil treatment groups were balanced with regard to the following baseline characteristics: age (median 63 vs. 66 years), gender (63% vs.
61% male), Binet stage (71% vs. 69% Binet B), lymphadenopathy (79% vs. 82%), enlarged spleen (76% vs.
80%), enlarged liver (48% vs. 46%), hypercellular bone marrow (79% vs. 73%), “B” symptoms (51% vs.
53%), lymphocyte count (mean 65.7x10 9 /L vs. 65.1x10 9 /L), and serum lactate dehydrogenase concentration (mean 370.2 vs. 388.4 U/L).
Ninety percent of patients in both treatment groups had immuno-phenotypic confirmation of CLL (CD5, CD23 and either CD19 or CD20 or both). Patients were randomly assigned to receive either bendamustine hydrochloride at 100 mg/m 2 , administered intravenously over a period of 30 minutes on Days 1 and 2 or chlorambucil at 0.8 mg/kg (Broca’s normal weight) administered orally on Days 1 and 15 of each 28-day cycle. Efficacy endpoints of objective response rate and progression-free survival were calculated using a pre-specified algorithm based on NCI working group criteria for CLL.
The results of this open-label randomized study demonstrated a higher rate of overall response and a longer progression-free survival for bendamustine hydrochloride compared to chlorambucil (see Table 5). Survival data are not mature. Table 5: Efficacy Data for CLL Bendamustine hydrochloride (N=153) Chlorambucil (N=148) p-value Response Rate n (%) Overall response rate 90 (59) 38 (26) <0.0001 (95% CI) (51.0, 66.6) (18.6, 32.7) Complete response (CR)* 13 (8) 1 (<1) Nodular partial response (nPR)** 4 (3) 0 Partial response (PR) † 73 (48) 37 (25) Progression-Free Survival †† Median, months (95% CI) 18 (11.7, 23.5) 6 (5.6, 8.6) Hazard ratio (95% CI) 0.27 (0.17, 0.43) <0.0001 CI = confidence interval * CR was defined as peripheral lymphocyte count ≤ 4.0 x 10 9 /L, neutrophils ≥ 1.5 x 10 9 /L, platelets >100 x 10 9 /L, hemoglobin > 110g/L, without transfusions, absence of palpable hepatosplenomegaly, lymph nodes ≤ 1.5 cm, < 30% lymphocytes without nodularity in at least a normocellular bone marrow and absence of “B” symptoms.
The clinical and laboratory criteria were required to be maintained for a period of at least 56 days. ** nPR was defined as described for CR with the exception that the bone marrow biopsy shows persistent nodules. † PR was defined as ≥ 50% decrease in peripheral lymphocyte count from the pretreatment baseline value, and either ≥50% reduction in lymphadenopathy, or ≥50% reduction in the size of spleen or liver, as well as one of the following hematologic improvements: neutrophils ≥ 1.5 x 10 9 /L or 50% improvement over baseline, platelets >100 x 10 9 /L or 50% improvement over baseline, hemoglobin >110g/L or 50% improvement over baseline without transfusions, for a period of at least 56 days. †† PFS was defined as time from randomization to progression or death from any cause.
Kaplan-Meier estimates of progression-free survival comparing bendamustine hydrochloride with chlorambucil are shown in Figure 1. Figure 1. Progression-Free Survival
14.2Non-Hodgkin Lymphoma (NHL) The efficacy of bendamustine hydrochloride was evaluated in a single arm study of 100 patients with indolent B-cell NHL that had progressed during or within… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Bendamustine was carcinogenic in mice. After intraperitoneal injections at 37.5 mg/m 2 /day (the lowest dose tested, approximately 0.3 times the maximum recommended human dose [MRHD])) and 75 mg/m 2 /day (approximately 0.6 times the MRHD) for 4 days, peritoneal sarcomas in female AB/Jena mice were produced. Oral administration at 187.5 mg/m 2 /day (the only dose tested, approximately 1.6 times the MRHD) for 4 days induced mammary carcinomas and pulmonary adenomas.
Bendamustine is a mutagen and clastogen. In a bacterial reverse mutation assay (Ames assay), bendamustine was shown to increase revertant frequency in the absence and presence of metabolic activation. Bendamustine was clastogenic in human lymphocytes in vitro, and in rat bone marrow cells in vivo (increase in micronucleated polychromatic erythrocytes) from 37.5 mg/m 2 (the lowest dose tested, approximately 0.3 times the MRHD).
Bendamustine induced morphologic abnormalities in spermatozoa in mice. Following tail vein injection of bendamustine at 120 mg/m 2 or a saline control on days 1 and 2 for a total of 3 weeks, the number of spermatozoa with morphologic abnormalities was 16% higher in the bendamustine-treated group as compared to the saline control group.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Bendamustine was carcinogenic in mice. After intraperitoneal injections at 37.5 mg/m 2 /day (the lowest dose tested, approximately 0.3 times the maximum recommended human dose [MRHD])) and 75 mg/m 2 /day (approximately 0.6 times the MRHD) for 4 days, peritoneal sarcomas in female AB/Jena mice were produced. Oral administration at 187.5 mg/m 2 /day (the only dose tested, approximately 1.6 times the MRHD) for 4 days induced mammary carcinomas and pulmonary adenomas.
Bendamustine is a mutagen and clastogen. In a bacterial reverse mutation assay (Ames assay), bendamustine was shown to increase revertant frequency in the absence and presence of metabolic activation. Bendamustine was clastogenic in human lymphocytes in vitro, and in rat bone marrow cells in vivo (increase in micronucleated polychromatic erythrocytes) from 37.5 mg/m 2 (the lowest dose tested, approximately 0.3 times the MRHD).
Bendamustine induced morphologic abnormalities in spermatozoa in mice. Following tail vein injection of bendamustine at 120 mg/m 2 or a saline control on days 1 and 2 for a total of 3 weeks, the number of spermatozoa with morphologic abnormalities was 16% higher in the bendamustine-treated group as compared to the saline control group.
📚 References ▾
15 REFERENCES OSHA Hazardous Drugs. OSHA . http://www.osha.gov/SLTC/hazardousdrugs/index.html
📄 Package Label / Principal Display Panel ▾
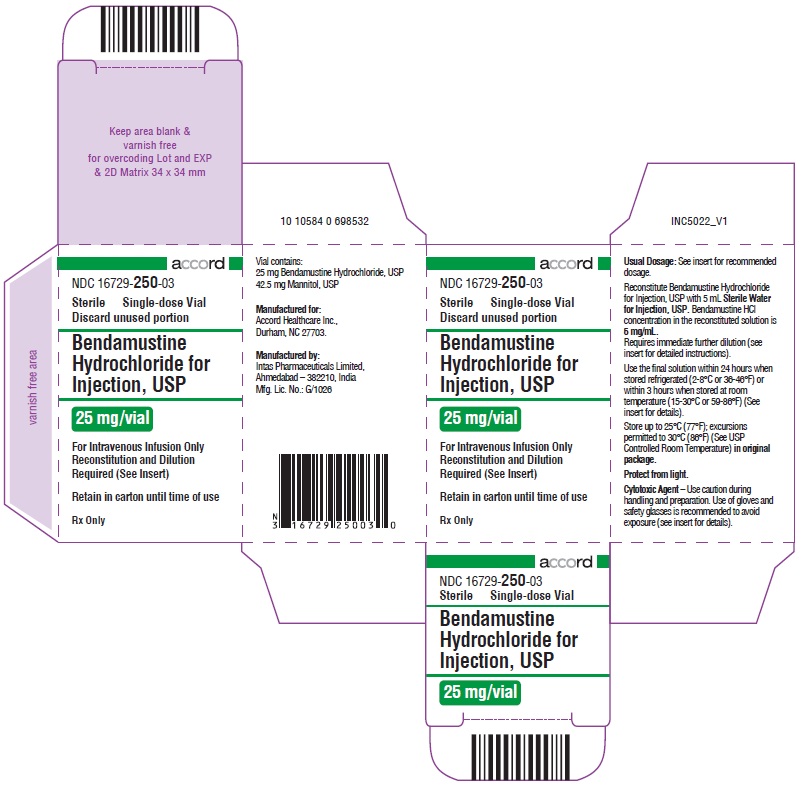
PRINCIPAL DISPLAY PANEL Bendamustine label
PRINCIPAL DISPLAY PANEL Bendamustine label
PRINCIPAL DISPLAY PANEL Bendamustine label
PRINCIPAL DISPLAY PANEL Bendamustine label
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |