
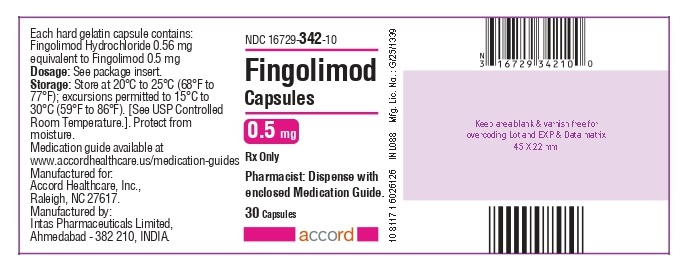
FINGOLIMOD HYDROCHLORIDE .5 mg Capsule, 30-count
Other active recalls for Fingolimod Hydrochloride (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Sphingosine 1-phosphate Receptor Modulator class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Fingolimod is used to treat certain types of multiple sclerosis (MS; a disease that damages nerves causing weakness, numbness, loss of muscle coordination, and problems with vision, speech, and bladder control). Fingolimod is in a class of medications called sphingosine l-phosphate receptor modulators. It works by decreasing the action of immune cells that may cause nerve damage.
Read the full MedlinePlus article ↗- Fingolimod works by keeping certain immune cells — the ones that damage your nerves — locked inside your lymph nodes so they can't travel to your brain or spinal cord. This reduces...
- What exactly is fingolimod doing for my MS?
- Fingolimod slows your heart rate — especially after that very first dose. The drop can be significant in the first few hours, and in some people it can cause symptoms like dizzines...
- Why do I have to be monitored for hours after my first dose?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $3.563 | $106.89 / 30 capsules |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $24.12 | $723.68 / 30 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Fingolimod .5 mg 00480-7820-56 | Teva | 30 capsules | $2.097 | AB | Availability likely | save 41% |
| Fingolimod .5 mg 31722-0889-30 | Camber | 30 capsules | $2.097 | AB | Availability likely | save 41% |
| Fingolimod .5 mg 43598-0285-30 | Dr. | 30 capsules | $2.097 | AB | Availability likely | save 41% |
| Fingolimod .5 mg 60505-4332-03 | Apotex | 30 capsules | $2.097 | AB | Availability likely | save 41% |
| fingolimod .5 mg 64980-0449-03 | Rising | 30 capsules | $2.097 | AB | Availability likely | save 41% |
| Fingolimod .5 mg 67877-0476-30 | Ascend | 30 capsules | $2.097 | AB | Availability likely | save 41% |
| Fingolimod .5 mg 82009-0143-30 | Quallent | 30 capsules | $2.097 | AB | Availability likely | save 41% |
| Fingolimod .5 mg 82249-0385-30 | CivicaScript | 30 capsules | $2.097 | AB | Availability likely | save 41% |
| Fingolimod Hydrochloride .5 mgthis 16729-0342-10 | Accord | 30 capsules | $3.563 | AB | Availability likely | — |
| Gilenya .5 mg 00078-0607-15 | Novartis | 30 capsules | $414.711 | AB | FDA listed | +11539% |
| Fingolimod .5 mg 42291-0048-30 | AvKARE | 30 capsules | — | AB | FDA listed | — |
| Fingolimod .5 mg 43547-0003-03 | Solco | 30 capsules | — | AB | FDA listed | — |
| Fingolimod .5 mg 46708-0228-10 | Alembic | 1000 capsules | — | AB | FDA listed | — |
| Fingolimod .5 mg 62332-0228-10 | Alembic | 1000 capsules | — | AB | FDA listed | — |
| Fingolimod .5 mg 62756-0064-57 | Sun | 28 capsules | — | — | FDA listed | — |
| Fingolimod .5 mg 65862-0952-07 | Aurobindo | 7 capsules | — | AB | FDA listed | — |
| Fingolimod .5 mg 68382-0912-01 | Zydus | 100 capsules | — | AB | FDA listed | — |
| fingolimod .5 mg 68462-0166-07 | Glenmark | 49 capsules | — | AB | FDA listed | — |
| Fingolimod .5 mg 70377-0019-11 | Biocon | 30 capsules | — | AB | FDA listed | — |
| Fingolimod .5 mg 70771-1603-01 | Zydus | 100 capsules | — | AB | FDA listed | — |
| Fingolimod .5 mg 72865-0257-30 | XLCare | 30 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 16729-0342-10 You're viewing this | 30 CAPSULE in 1 BOTTLE (16729-342-10) | 2022-10-18 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Fingolimod capsules are indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in patients 10 years of age and older. Fingolimod hydrochloride is a sphingosine 1-phosphate receptor modulator indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in patients 10 years of age and older.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Assessments are required prior to initiating fingolimod. ( 2.1 ) Recommended dosage for adults and pediatric patients (10 years of age and older) weighing more than 40 kg: 0.5 mg orally once-daily, with or without food. ( 2.2 , 2.3 ) First-Dose Monitoring (including reinitiation after discontinuation greater than 14 days and dose increases): Observe all patients for bradycardia for at least 6 hours; monitor pulse and blood pressure hourly.
Electrocardiograms (ECGs) prior to dosing and at end of observation period required. ( 2.4 ) Monitor until resolution if heart rate <45 beats per minute (bpm) in adults, < 55 bpm in patients aged 12 years and above, or < 60 bpm in pediatric patients aged 10 to below 12 years,atrioventricular (AV) block, or if lowest postdose heart rate is at the end of the observation period. ( 2.4 ) Monitor symptomatic bradycardia with ECG until resolved.
Continue overnight if intervention is required; repeat first-dose monitoring for second dose. ( 2.4 ) Observe patients overnight if at higher risk of symptomatic bradycardia, heart block, prolonged QTc interval, or if taking drugs with known risk of torsades de pointes. ( 2.4 , 7.1 )
2.1Assessment Prior to Initiating Fingolimod Capsules Cardiac Evaluation Obtain a cardiac evaluation in patients with certain preexisting conditions [ see Warnings and Precautions (5.1) ] Prior to starting treatment, determine whether patients are taking drugs that could slow heart rate or atrioventricular (AV) conduction [ see Dosage and Administration (2.4) , Drug Interactions (7.5) ] Complete Blood Count (CBC) Review results of a recent CBC [ see Warnings and Precautions (5.2) , Drug Interactions (7.6) ] Serum Transaminases (ALT and AST) and Total Bilirubin Levels Prior to starting treatment with fingolimod capsules (i.e., within 6 months), obtain serum transaminases [alanine transaminase (ALT) and aspartate transferase (AST)] and total bilirubin levels [see Warnings and Precautions (5.5) ] .
Prior Medications If patients are taking antineoplastic, immunosuppressive, or immune-modulating therapies, or if there is a history of prior use of these drugs, consider possible unintended additive immunosuppressive effects before initiating treatment with fingolimod capsules[ see Warnings and Precautions (5.2) , Drug Interactions (7.4) ] Vaccinations Test patients for antibodies to varicella zoster virus (VZV) before initiating fingolimod capsules; VZV vaccination of antibody-negative patients is recommended prior to commencing treatment with fingolimod capsules[ see Warnings and Precautions (5.2). ] It is recommended that pediatric patients if possible, complete all immunizations in accordance with current immunization guidelines prior to initiating fingolimod capsules therapy.
2.2Important Administration Instructions Patients who initiate fingolimod capsules, and those who reinitiate treatment after discontinuation for longer than 14 days, require first-dose monitoring. This monitoring is also recommended when the dose is increased in pediatric patients.[ see Dosage and Administration (2.4, 2.5) ] Fingolimod capsules can be taken with or without food.
2.3Recommended Dosage In adults and pediatric patients 10 years of age and older weighing more than 40 kg, the recommended dosage of fingolimod capsules is 0.5 mg orally once-daily. Fingolimod doses higher than 0.5 mg are associated with a greater incidence of adverse reactions without additional benefit.
2.4First-Dose Monitoring Initiation of fingolimod capsules treatment results in a decrease in heart rate, for which monitoring is recommended [ see Warnings and Precautions (5.1) , Clinical Pharmacology (12.2) ]. Prior to dosing and at the end of the observation period, obtain an electrocardiogram (ECG) in all patients. First 6-Hour Monitoring Administer the first dose of fingolimod capsules in a setting in which resources to appropriately manage symptomatic bradycardia are available.
Monitor all pati…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Fingolimod capsules are available as: Fingolimod capsules are available as 0.5 mg with bright yellow opaque/white opaque size “3” hard gelatin capsules imprinted with “FO 0.5 mg” on cap and two radial bands on the capsule body with yellow ink containing white to off white powder. 0.5 mg hard capsules ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Fingolimod capsules are contraindicated in patients who have: in the last 6 months experienced myocardial infarction, unstable angina, stroke, transient ischemic attack (TIA), decompensated heart failure requiring hospitalization or Class III/IV heart failure a history or presence of Mobitz Type II second-degree or third-degree AV block or sick sinus syndrome, unless patient has a functioning pacemaker [ see Warnings and Precautions (5.1) ] a baseline QTc interval ≥500 msec cardiac arrhythmias requiring anti-arrhythmic treatment with Class Ia or Class III anti-arrhythmic drugs had a hypersensitivity reaction to fingolimod or any of the excipients in fingolimod capsules.
Observed reactions include rash, urticaria and angioedema upon treatment initiation. [see Warnings and Precautions (5.14) ] Recent myocardial infarction, unstable angina, stroke, transient ischemic attack (TIA), decompensated heart failure with hospitalization, or Class III/IV heart failure. ( 4 ) History of Mobitz Type II 2 nd degree or 3 rd degree AV block or sick sinus syndrome, unless patient has a pacemaker. ( 4 ) Baseline QTc interval ≥500 msec.
( 4 ) Cardiac arrhythmias requiring anti-arrhythmic treatment with Class Ia or Class III anti-arrhythmic drugs. ( 4 ) Hypersensitivity to fingolimod or its excipients. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Infections: Fingolimod hydrochloride may increase the risk. Obtain a complete blood count (CBC) before initiating treatment. Monitor for infection during treatment and for 2 months after discontinuation.
Do not start in patients with active infections. ( 5.2 ) Progressive Multifocal Leukoencephalopathy (PML): Withhold fingolimod hydrochloride at the first sign or symptom suggestive of PML. ( 5.3 ) Macular Edema: Examine the fundus before and 3 to 4 months after treatment start.
Diabetes mellitus and uveitis increase the risk. ( 5.4 ) Liver Injury: Obtain liver enzyme results before initiation and periodically during treatment. Closely monitor patients with severe hepatic impairment.
Discontinue if there is evidence of liver injury without other cause. ( 5.5 , 8.6 , 12.3 ) Posterior Reversible Encephalopathy Syndrome (PRES): If suspected, discontinue fingolimod hydrochloride. ( 5.6 ) Respiratory Effects: Evaluate when clinically indicated.
( 5.7 ) Fetal Risk: May cause fetal harm. Advise females of reproductive potential of the potential risk to a fetus and to use an effective method of contraception during treatment and for 2 months after stopping fingolimod hydrochloride. ( 5.8 , 8.1 , 8.3 ) Severe Increase in Disability After Stopping Fingolimod Hydrochloride: Monitor for development of severe increase in disability following discontinuation and begin appropriate treatment as needed.
( 5.9 ) Tumefactive MS: Consider when severe MS relapse occurs during treatment or after discontinuation. Obtain imaging and begin treatment as needed. ( 5.10 ) Increased Blood Pressure (BP): Monitor BP during treatment.
( 5.11 ) Malignancies: Suspicious skin lesions should be evaluated. ( 5.12 )
5.1Bradyarrhythmia and Atrioventricular Blocks Because of a risk for bradyarrhythmia and AV blocks, patients should be monitored during fingolimod hydrochloride treatment initiation [ see Dosage and Administration (2.4) ]. Reduction in Heart Rate After the first dose of fingolimod hydrochloride, the heart rate decrease starts within an hour. On Day 1, the maximum decline in heart rate generally occurs within 6 hours and recovers, although not to baseline levels, by 8 to 10 hours postdose.
Because of physiological diurnal variation, there is a second period of heart rate decrease within 24 hours after the first dose. In some patients, heart rate decrease during the second period is more pronounced than the decrease observed in the first 6 hours. Heart rates below 40 bpm in adults, and below 50 bpm in pediatric patients occurred rarely.
In controlled clinical trials in adult patients, adverse reactions of symptomatic bradycardia following the first dose were reported in 0.6% of patients receiving fingolimod hydrochloride 0.5 mg, and in 0.1% of patients on placebo. Patients who experienced bradycardia were generally asymptomatic, but some patients experienced hypotension, dizziness, fatigue, palpitations, and/or chest pain that usually resolved within the first 24 hours on treatment. Patients with some preexisting conditions (e.g., ischemic heart disease, history of myocardial infarction, congestive heart failure, history of cardiac arrest, cerebrovascular disease, uncontrolled hypertension, history of symptomatic bradycardia, history of recurrent syncope, severe untreated sleep apnea, AV block, sinoatrial heart block) may poorly tolerate the fingolimod hydrochloride-induced bradycardia, or experience serious rhythm disturbances after the first dose of fingolimod hydrochloride.
Prior to treatment with fingolimod hydrochloride, these patients should have a cardiac evaluation by a physician appropriately trained to conduct such evaluation, and if treated with fingolimod hydrochloride, should be monitored overnight with continuous ECG in a medical facility after the first dose. Since initiation of fingolimod hydrochloride treatment, results in decreased heart rate and may prolong the QT interval, patients with a prolonged QTc inter…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in labeling: Bradyarrhythmia and Atrioventricular Blocks [ see Warnings and Precautions (5.1) ] Infections [ see Warnings and Precautions (5.2) ] Progressive Multifocal Leukoencephalopathy [ see Warnings and Precautions (5.3) ] Macular Edema [ see Warnings and Precautions (5.4) ] Liver Injury [ see Warnings and Precautions (5.5) ] Posterior Reversible Encephalopathy Syndrome [ see Warnings and Precautions (5.6) ] Respiratory Effects [ see Warnings and Precautions (5.7) ] Fetal Risk [see Warnings and Precautions (5.8) ] Severe Increase in Disability after Stopping Fingolimod Hydrochloride [see Warnings and Precautions (5.9) ] Tumefactive Multiple Sclerosis [see Warnings and Precautions (5.10) ] Increased Blood Pressure [see Warnings and Precautions (5.11) ] Malignancies [see Warnings and Precautions (5.12) ] Immune System Effects Following Fingolimod Hydrochloride Discontinuation [see Warnings and Precautions (5.13) ] Hypersensitivity Reactions [see Warnings and Precautions (5.14) ] Most common adverse reactions (incidence ≥10% and greater than placebo): Headache, liver transaminase elevation, diarrhea, cough, influenza, sinusitis, back pain, abdominal pain, and pain in extremity ( 6.1 ).
To report SUSPECTED ADVERSE REACTIONS, contact Accord Healthcare Inc. at 1-866-941-7875 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adults In clinical trials (Studies 1, 2, and 3), a total of 1212 patients with relapsing forms of multiple sclerosis received fingolimod hydrochloride 0.5 mg. This included 783 patients who received fingolimod hydrochloride 0.5 mg in the 2-year placebo-controlled trials (Studies 1 and 3) and 429 patients who received fingolimod hydrochloride 0.5 mg in the 1-year active-controlled trial (Study 2).
The overall exposure in the controlled trials was equivalent to 1716 person-years. Approximately 1000 patients received at least 2 years of treatment with fingolimod hydrochloride 0.5 mg. In all clinical studies, including uncontrolled extension studies, the exposure to fingolimod hydrochloride 0.5 mg was approximately 4119 person-years.
In placebo-controlled trials, the most frequent adverse reactions (incidence ≥10% and greater than placebo) for fingolimod hydrochloride 0.5 mg were headache, liver transaminase elevation, diarrhea, cough, influenza, sinusitis, back pain, abdominal pain, and pain in extremity. Adverse events that led to treatment discontinuation and occurred in more than 1% of patients taking fingolimod hydrochloride 0.5 mg, were serum transaminase elevations (4.7% compared to 1% on placebo) and basal cell carcinoma (1% compared to 0.5% on placebo).
Table 1 lists adverse reactions in clinical studies in adults that occurred in ≥ 1% of fingolimod hydrochloride-treated patients and ≥ 1% higher rate than for placebo. Table 1: Adverse Reactions Reported in Adult Studies 1 and 3 (Occurring in ≥1% of Patients and Reported for Fingolimod Hydrochloride 0.5 mg at ≥1% Higher Rate Than for Placebo) Abbreviations: ALT, alanine transaminase; AST, aspartate transferase; GGT, gamma-glutamyl transferase. Adverse drug reactions Fingolimod Hydrochloride 0.5 mg N=783 % Placebo N=773 % Infections Influenza 11 8 Sinusitis 11 8 Bronchitis 8 5 Herpes zoster 2 1 Tinea versicolor 2 <1 Cardiac disorders Bradycardia 3 1 Nervous system disorders Headache 25 24 Migraine 6 4 Gastrointestinal disorders Nausea 13 12 Diarrhea 13 10 Abdominal pain 11 10 General disorders and administration-site conditions Asthenia 2 1 Musculoskeletal and connective tissue disorders Back pain 10 9 Pain in extremity 10 7 Skin and subcutaneous tissue disorders Alopecia 3 2 Actini…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Systemic Ketoconazole: Monitor during concomitant use. ( 7.2 , 12.3 ) Vaccines: Avoid live attenuated vaccines during, and for 2 months after stopping fingolimod hydrochloride treatment. ( 5.2 , 7.3 )
7.1QT Prolonging Drugs Fingolimod hydrochloride has not been studied in patients treated with drugs that prolong the QT interval. Drugs that prolong the QT interval have been associated with cases of torsades de pointes in patients with bradycardia. Since initiation of fingolimod hydrochloride treatment results in decreased heart rate and may prolong the QT interval, patients on QT prolonging drugs with a known risk of torsades de pointes (e.g., citalopram, chlorpromazine, haloperidol, methadone, erythromycin) should be monitored overnight with continuous ECG in a medical facility [ see Dosage and Administration (2.4) , Warnings and Precautions (5.1) ].
7.2Ketoconazole The blood levels of fingolimod and fingolimod-phosphate are increased by 1.7-fold when used concomitantly with ketoconazole. Patients who use fingolimod hydrochloride and systemic ketoconazole concomitantly should be closely monitored, as the risk of adverse reactions is greater.
7.3Vaccines Fingolimod hydrochloride reduces the immune response to vaccination. Vaccination may be less effective during and for up to 2 months after discontinuation of treatment with fingolimod hydrochloride [ see Clinical Pharmacology (12.2) ]. Avoid the use of live attenuated vaccines during and for 2 months after treatment with fingolimod hydrochloride because of the risk of infection..
It is recommended that pediatric patients, if possible, be brought up to date with all immunizations in agreement with current immunization guidelines prior to initiating fingolimod capsules therapy.
7.4Antineoplastic, Immunosuppressive, or Immune-Modulating Therapies Antineoplastic, immune-modulating, or immunosuppressive therapies, (including corticosteroids) are expected to increase the risk of immunosuppression, and the risk of additive immune system effects must be considered if these therapies are coadministered with fingolimod hydrochloride. When switching from drugs with prolonged immune effects, such as natalizumab, teriflunomide or mitoxantrone, the duration and mode of action of these drugs must be considered to avoid unintended additive immunosuppressive effects when initiating fingolimod hydrochloride [ see Warnings and Precautions (5.2) ].
7.5Drugs That Slow Heart Rate or Atrioventricular Conduction (e.g., beta blockers or diltiazem) Experience with fingolimod hydrochloride in patients receiving concurrent therapy with drugs that slow the heart rate or AV conduction (e.g., beta blockers, digoxin, or heart rate-slowing calcium channel blockers, such as diltiazem or verapamil) is limited. Because initiation of fingolimod hydrochloride treatment may result in an additional decrease in heart rate, concomitant use of these drugs during fingolimod hydrochloride initiation may be associated with severe bradycardia or heart block.
Seek advice from the physician prescribing these drugs regarding the possibility to switch to drugs that do not slow the heart rate or atrioventricular conduction before initiating fingolimod hydrochloride. Patients who cannot switch should have overnight continuous ECG monitoring after the first dose [ see Dosage and Administration (2.4) , Warnings and Precautions (5.1) ].
7.6Laboratory Test Interaction Because fingolimod hydrochloride reduces blood lymphocyte counts via redistribution in secondary lymphoid organs, peripheral blood lymphocyte counts cannot be utilized to evaluate the lymphocyte subset status of a patient treated with fingolimod hydrochloride. A recent CBC should be available before initiating treatment with fingolimod hydrochloride.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Based on findings from animal studies, fingolimod hydrochloride may cause fetal harm when administered to a pregnant woman. Data from prospective reports to the fingolimod pregnancy registry are currently not sufficient to allow for an adequate assessment of the drug-associated risk for birth defects and miscarriage in humans. In oral studies conducted in rats and rabbits, fingolimod demonstrated developmental toxicity, including an increase in malformations (rats) and embryolethality, when given to pregnant animals.
In rats, the highest no-effect dose was less than the recommended human dose of 0.5 mg/day on a body surface area (mg/m 2 ) basis. The most common fetal visceral malformations in rats were persistent truncus arteriosus and ventricular septal defect. The receptor affected by fingolimod (sphingosine 1-phosphate receptor) is known to be involved in vascular formation during embryogenesis (see Data) .
Advise pregnant women of the potential risk to a fetus. In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Clinical Considerations In females planning to become pregnant, fingolimod hydrochloride should be stopped 2 months before planned conception. The possibility of severe increase in disability should be considered in women who discontinue or are considering discontinuation of fingolimod hydrochloride because of pregnancy or planned pregnancy. In many of the cases in which increase in disability was reported after stopping fingolimod hydrochloride, patients had stopped fingolimod hydrochloride because of pregnancy or planned pregnancy [see Warnings and Precautions (5.9) ] .
Data Animal Data When fingolimod was orally administered to pregnant rats during the period of organogenesis (0, 0.03, 0.1, and 0.3 mg/kg/day or 0, 1, 3, and 10 mg/kg/day), increased incidences of fetal malformations and embryofetal deaths were observed at all but the lowest dose tested (0.03 mg/kg/day), which is less than the recommended human dose (RHD) on a mg/m 2 basis. Oral administration to pregnant rabbits during organogenesis (0, 0.5, 1.5, and 5 mg/kg/day) resulted in increased incidences of embryofetal mortality and fetal growth retardation at the mid and high doses.
The no-effect dose for these effects in rabbits (0.5 mg/kg/day) is approximately 20 times the RHD on a mg/m 2 basis. When fingolimod was orally administered to female rats during pregnancy and lactation (0, 0.05, 0.15, and 0.5 mg/kg/day), pup survival was decreased at all doses and a neurobehavioral (learning) deficit was seen in offspring at the high dose. The low-effect dose of 0.05 mg/kg/day is similar to the RHD on a mg/m 2 basis.
8.2Lactation Risk Summary There are no data on the presence of fingolimod in human milk, the effects on the breastfed infant, or the effects of the drug on milk production. Fingolimod is excreted in the milk of treated rats. When a drug is present in animal milk, it is likely that the drug will be present in human milk.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for fingolimod hydrochloride and any potential adverse effects on the breastfed infant from fingolimod hydrochloride or from the underlying maternal condition.
8.3Females and Males of Reproductive Potential Pregnancy Testing The pregnancy status of females of reproductive potential should be verified prior to starting treatment with fingolimod hydrochloride [see Use in Specific Populations (8.1) ]. . Contraception Before initiation of fingolimod hydrochloride treatment, females of reproductive potential should be counseled on the potential for a serious risk to the fetus and the need for effective contraception during treatment with fingo…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies, fingolimod hydrochloride may cause fetal harm when administered to a pregnant woman. Data from prospective reports to the fingolimod pregnancy registry are currently not sufficient to allow for an adequate assessment of the drug-associated risk for birth defects and miscarriage in humans. In oral studies conducted in rats and rabbits, fingolimod demonstrated developmental toxicity, including an increase in malformations (rats) and embryolethality, when given to pregnant animals.
In rats, the highest no-effect dose was less than the recommended human dose of 0.5 mg/day on a body surface area (mg/m 2 ) basis. The most common fetal visceral malformations in rats were persistent truncus arteriosus and ventricular septal defect. The receptor affected by fingolimod (sphingosine 1-phosphate receptor) is known to be involved in vascular formation during embryogenesis (see Data) .
Advise pregnant women of the potential risk to a fetus. In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Clinical Considerations In females planning to become pregnant, fingolimod hydrochloride should be stopped 2 months before planned conception. The possibility of severe increase in disability should be considered in women who discontinue or are considering discontinuation of fingolimod hydrochloride because of pregnancy or planned pregnancy. In many of the cases in which increase in disability was reported after stopping fingolimod hydrochloride, patients had stopped fingolimod hydrochloride because of pregnancy or planned pregnancy [see Warnings and Precautions (5.9) ] .
Data Animal Data When fingolimod was orally administered to pregnant rats during the period of organogenesis (0, 0.03, 0.1, and 0.3 mg/kg/day or 0, 1, 3, and 10 mg/kg/day), increased incidences of fetal malformations and embryofetal deaths were observed at all but the lowest dose tested (0.03 mg/kg/day), which is less than the recommended human dose (RHD) on a mg/m 2 basis. Oral administration to pregnant rabbits during organogenesis (0, 0.5, 1.5, and 5 mg/kg/day) resulted in increased incidences of embryofetal mortality and fetal growth retardation at the mid and high doses.
The no-effect dose for these effects in rabbits (0.5 mg/kg/day) is approximately 20 times the RHD on a mg/m 2 basis. When fingolimod was orally administered to female rats during pregnancy and lactation (0, 0.05, 0.15, and 0.5 mg/kg/day), pup survival was decreased at all doses and a neurobehavioral (learning) deficit was seen in offspring at the high dose. The low-effect dose of 0.05 mg/kg/day is similar to the RHD on a mg/m 2 basis.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of fingolimod hydrochloride for the treatment of relapsing forms of multiple sclerosis in pediatric patients 10 to less than 18 years of age were established in one randomized, double-blind clinical study in 215 patients (fingolimod hydrochloride n = 107; intramuscular interferon (IFN) beta-1a n = 108) [see Clinical Studies (14.2) ]. In the controlled pediatric study, the safety profile in pediatric patients (10 to less than 18 years of age) receiving fingolimod hydrochloride 0.5 mg daily was similar to that seen in adult patients.
In the pediatric study, cases of seizures were reported in 5.6% of fingolimod-treated patients and 0.9% of interferon beta-1a-treated patients It is recommended that pediatric patients if possible, complete all immunizations in accordance with current immunization guidelines prior to initiating fingolimod capsules therapy. Safety and effectiveness of fingolimod hydrochloride in pediatric patients below the age of 10 years have not been established. Juvenile Animal Toxicity Data In a study in which fingolimod (0.3, 1.5, or 7.5 mg/kg/day) was orally administered to young rats from weaning through sexual maturity, changes in bone mineral density and persistent neurobehavioral impairment (altered auditory startle) were observed at all doses.
Delayed sexual maturation was noted in females at the highest dose tested and in males at all doses. The bone changes observed in fingolimod-treated juvenile rats are consistent with a reported role of S1P in the regulation of bone mineral homeostasis. When fingolimod (0.5 or 5 mg/kg/day) was orally administered to rats from the neonatal period through sexual maturity, a marked decrease in T-cell dependent antibody response was observed at both doses.
This effect had not fully recovered by 6 to 8 weeks after the end of treatment. Overall, a no-effect dose for adverse developmental effects in juvenile animals was not identified.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical MS studies of fingolimod hydrochloride did not include sufficient numbers of patients aged 65 years and over to determine whether they respond differently than younger patients. Fingolimod hydrochloride should be used with caution in patients aged 65 years and over, reflecting the greater frequency of decreased hepatic, or renal, function and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Fingolimod hydrochloride can induce bradycardia as well as AV conduction blocks (including complete AV block). The decline in heart rate usually starts within 1 hour of the first dose and is maximal within 6 hours in most patients [ see Warnings and Precautions (5.1) ]. In case of fingolimod hydrochloride overdosage, observe patients overnight with continuous ECG monitoring in a medical facility, and obtain regular measurements of blood pressure [ see Dosage and Administration (2.4) ].
Neither dialysis nor plasma exchange results in removal of fingolimod from the body.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Fingolimod is metabolized by sphingosine kinase to the active metabolite, fingolimod-phosphate. Fingolimod-phosphate is a sphingosine 1-phosphate receptor modulator, and binds with high affinity to sphingosine 1-phosphate receptors 1, 3, 4, and 5. Fingolimod-phosphate blocks the capacity of lymphocytes to egress from lymph nodes, reducing the number of lymphocytes in peripheral blood.
The mechanism by which fingolimod exerts therapeutic effects in multiple sclerosis is unknown, but may involve reduction of lymphocyte migration into the central nervous system.
12.2Pharmacodynamics Heart Rate and Rhythm Fingolimod causes a transient reduction in heart rate and AV conduction at treatment initiation [ see Warnings and Precautions (5.1) ]. Heart rate progressively increases after the first day, returning to baseline values within 1 month of the start of chronic treatment. Autonomic responses of the heart, including diurnal variation of heart rate and response to exercise, are not affected by fingolimod treatment.
Fingolimod treatment is not associated with a decrease in cardiac output. Potential to Prolong the QT Interval In a thorough QT interval study of doses of 1.25 or 2.5 mg fingolimod at steady-state, when a negative chronotropic effect of fingolimod was still present, fingolimod treatment resulted in a prolongation of QTc, with the upper boundary of the 90% confidence interval (CI) of 14.0 msec. There is no consistent signal of increased incidence of QTc outliers, either absolute or change from baseline, associated with fingolimod treatment.
In MS studies, there was no clinically relevant prolongation of the QT interval, but patients at risk for QT prolongation were not included in clinical studies. Immune System Effects on Immune Cell Numbers in the Blood In a study in which 12 adult subjects received fingolimod hydrochloride 0.5 mg daily, the lymphocyte count decreased to approximately 60% of baseline within 4 to 6 hours after the first dose. With continued daily dosing, the lymphocyte count continued to decrease over a 2-week period, reaching a nadir count of approximately 500 cells/mcL or approximately 30% of baseline.
In a placebo-controlled study in 1272 MS patients (of whom 425 received fingolimod 0.5 mg daily and 418 received placebo), 18% (N=78) of patients on fingolimod 0.5 mg reached a nadir of <200 cells/mcL on at least 1 occasion. No patient on placebo reached a nadir of <200 cells/mcL. Low lymphocyte counts are maintained with chronic daily dosing of fingolimod hydrochloride 0.5 mg daily.
Chronic fingolimod dosing leads to a mild decrease in the neutrophil count to approximately 80% of baseline. Monocytes are unaffected by fingolimod. Peripheral lymphocyte count increases are evident within days of stopping fingolimod treatment and typically normal counts are reached within 1 to 2 months.
Effect on Antibody Response Fingolimod hydrochloride reduces the immune response to vaccination, as evaluated in 2 studies. In the first study, the immunogenicity of keyhole limpet hemocyanin (KLH) and pneumococcal polysaccharide vaccine (PPV-23) immunization were assessed by IgM and IgG titers in a steady-state, randomized, placebo-controlled study in healthy adult volunteers. Compared to placebo, antigen-specific IgM titers were decreased by 91% and 25% in response to KLH and PPV-23, respectively, in subjects on fingolimod hydrochloride 0.5 mg.
Similarly, IgG titers were decreased by 45% and 50%, in response to KLH and PPV-23, respectively, in subjects on fingolimod hydrochloride 0.5 mg daily compared to placebo. The responder rate for fingolimod hydrochloride 0.5 mg as measured by the number of subjects with a >4-fold increase in KLH IgG was comparable to placebo and 25% lower for PPV-23 IgG, while the number of subjects with a >4 fold increase in KLH and PPV-23 IgM was 75% and 40% lower, respectively, compared to placebo. The capacity to mount a skin delayed-type hypersens…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Fingolimod is metabolized by sphingosine kinase to the active metabolite, fingolimod-phosphate. Fingolimod-phosphate is a sphingosine 1-phosphate receptor modulator, and binds with high affinity to sphingosine 1-phosphate receptors 1, 3, 4, and 5. Fingolimod-phosphate blocks the capacity of lymphocytes to egress from lymph nodes, reducing the number of lymphocytes in peripheral blood.
The mechanism by which fingolimod exerts therapeutic effects in multiple sclerosis is unknown, but may involve reduction of lymphocyte migration into the central nervous system.
📦 How Supplied / Storage and Handling ▾
16.1How Supplied 0.5 mg fingolimod capsules are bright yellow opaque/white opaque size “3” hard gelatin capsules imprinted with “FO 0.5 mg” on cap and two radial bands on the capsule body with yellow ink containing white to off white powder. Fingolimod capsules are supplied in HDPE bottle and blister packs as follow. HDPE Bottles: Bottles of 7 count comes in a child-resistant package: NDC 16729-342-89 Bottles of 30 count comes in a child-resistant package: NDC 16729-342-10 Bottles of 90 count comes in a child-resistant package: NDC 16729-342-15 Bottles of 1000 count: NDC 16729-342-17 Blister Packs: Carton of 28 capsules containing 4 blister strips of 7 capsules per blister strip comes in a child-resistant package: NDC 16729-342-88 Carton of 7 capsules containing 1 blister strip of 7 capsules per blister strip comes in a child-resistant package: NDC 16729-342-87
📦 Storage and Handling ▾
16.2Storage and Handling Fingolimod hydrochloride capsules should be stored at 20ºC to 25ºC (68ºF to 77ºF); excursions permitted to 15ºC to 30ºC (59ºF to 86ºF) [See USP Controlled Room Temperature] Protect from moisture.
📋 Description ▾
11 DESCRIPTION Fingolimod is a sphingosine 1-phosphate receptor modulator. Chemically, fingolimod is 2-amino-2-[2-(4-octylphenyl)ethyl]propan-1,3-diol hydrochloride. Its structure is shown below: Fingolimod hydrochloride is a white to practically white powder that is freely soluble in water and alcohol and soluble in propylene glycol.
It has a molecular weight of 343.93 g/mol. Fingolimod hydrochloride is provided as 0.5 mg hard gelatin capsules for oral use. Each capsule contains 0.56 mg of fingolimod hydrochloride, equivalent to 0.5 mg of fingolimod.
Each fingolimod 0.5 mg capsule contains the following inactive ingredients: magnesium stearate, pregelatinized starch (maize). Capsule shell contains gelatin, iron oxide yellow and titanium dioxide; Black imprinting ink contains shellac, iron oxide black and potassium hydroxide. Yellow imprinting ink contains shellac and iron oxide yellow.
Fingolimod chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Tell patients not to discontinue fingolimod capsules without first discussing this with the prescribing physician. Advise patients to contact their physician if they accidently take more fingolimod capsules than prescribed.
Cardiac Effects Advise patients that initiation of fingolimod hydrochloride treatment results in a transient decrease in heart rate. Inform patients that they will need to be observed in the doctor's office or other facility for at least 6 hours after the first dose, after reinitiation if treatment is interrupted or discontinued for certain periods, and after the dosage is increased. [ see Dosage and Administration (2.4) , Warnings and Precautions (5.1) ] Risk of Infections Inform patients that they may have an increased risk of infections, some of which could be life-threatening, when taking fingolimod hydrochloride, and that they should contact their physician if they develop symptoms of infection.
Advise patients that the use of some vaccines should be avoided during treatment with fingolimod hydrochloride and for 2 months after discontinuation. Recommend to patients that they delay treatment with fingolimod hydrochloride until after VZV vaccination if they have not had chickenpox or a previous VZV vaccination. Inform patients that prior or concomitant use of drugs that suppress the immune system may increase the risk of infection. [ see Warnings and Precautions (5.2) ] Progressive Multifocal Leukoencephalopathy Inform patients that cases of progressive multifocal leukoencephalopathy (PML) have occurred in patients who received fingolimod hydrochloride.
Inform the patient that PML is characterized by a progression of deficits and usually leads to death or severe disability over weeks or months. Instruct the patient of the importance of contacting their doctor if they develop any symptoms suggestive of PML. Inform the patient that typical symptoms associated with PML are diverse, progress over days to weeks, and include progressive weakness on one side of the body or clumsiness of limbs, disturbance of vision, and changes in thinking, memory, and orientation leading to confusion and personality changes [see Warnings and Precautions (5.3) ].
Macular Edema Advise patients that fingolimod hydrochloride may cause macular edema, and that they should contact their physician if they experience any changes in their vision. Inform patients with diabetes mellitus or a history of uveitis that their risk of macular edema is increased. [ see Warnings and Precautions (5.4) ] Hepatic Effects Inform patients that fingolimod hydrochloride may cause liver injury. Advise patients that they should contact their physician if they have any unexplained nausea, vomiting, abdominal pain, fatigue, anorexia, or jaundice and/or dark urine [ see Warnings and Precautions (5.5) ].
Posterior Reversible Encephalopathy Syndrome Advise patients to immediately report to their healthcare provider any symptoms involving sudden onset of severe headache, altered mental status, visual disturbances, or seizure. Inform patients that delayed treatment could lead to permanent neurological sequelae [ see Warnings and Precautions (5.6) ] Respiratory Effects Advise patients that they should contact their physician if they experience new onset or worsening of dyspnea. [ see Warnings and Precautions (5.7) ] Fetal Risk Advise pregnant women and females of reproductive potential of the potential risk to a fetus.
Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.8) and Use in Specific Populations (8.1 , 8.3) ] . Advise female patients of reproductive potential to use effective contraception during treatment with fingolimod capsules and for 2 months after the final dose [see Use in Specific Populations (8.3) ] . Severe Increase in Disability After Stopping Fingolimod Hydrochlori…
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: February 2024 MEDICATION GUIDE Fingolimod Capsules (fin-GOL-i-mod) Read this Medication Guide before you start taking fingolimod capsules and each time you get a refill.
There may be new information. If you are the parent of a child who is being treated with fingolimod capsules, the following information applies to your child. This information does not take the place of talking to your doctor about your medical condition or your treatment.
What is the most important information I should know about fingolimod capsules? Fingolimod capsules may cause serious side effects, including: Slow heart rate (bradycardia or bradyarrhythmia) when you start taking fingolimod capsules. Fingolimod capsules can cause your heart rate to slow down, especially after you take your first dose.
You will have a test, called an electrocardiogram (ECG), to check the electrical activity of your heart before you take your first dose of fingolimod capsules. All adults and children will be observed by a healthcare professional for at least 6 hours after taking their first dose of fingolimod capsules. Children should also be observed by a healthcare professional for at least 6 hours after taking their first dose of 0.5 mg of fingolimod capsules when switching from the 0.25 mg dose.
After you take your first dose of fingolimod capsules, and after a child takes their first dose of 0.5 mg of fingolimod capsules when switching from the 0.25 mg dose: Your pulse and blood pressure should be checked every hour. You should be observed by a healthcare professional to see if you have any serious side effects. If your heart rate slows down too much, you may have symptoms, such as: dizziness tiredness feeling like your heart is beating slowly or skipping beats chest pain If you have any of the symptoms of slow heart rate, they will usually happen during the first 6 hours after your first dose of fingolimod capsules.
Symptoms can happen up to 24 hours after you take your first fingolimod capsules dose. 6 hours after you take your first dose of fingolimod capsules you will have another ECG. If your ECG shows any heart problems or if your heart rate is still too low or continues to decrease, you will continue to be observed.
If you have any serious side effects after your first dose of fingolimod capsules, especially those that require treatment with other medicines, you will stay in the medical facility to be observed overnight. You will also be observed for any serious side effects for at least 6 hours after you take your second dose of fingolimod capsules the next day. If you have certain types of heart problems, or if you are taking certain types of medicines that can affect your heart, you will be observed overnight after you take your first dose of fingolimod capsules.
Your slow heart rate will usually return to normal within 1 month after you start taking fingolimod capsules. Call your doctor or go to the nearest hospital emergency room right away if you have any symptoms of a slow heart rate. If you miss 1 or more doses of fingolimod capsules, you may need to be observed by a healthcare professional when you take your next dose.
Call your doctor if you miss a dose of fingolimod capsules. See “How should I take fingolimod capsules?” Pregnancy. Please consult your doctor before getting pregnant.
You should avoid becoming pregnant while taking fingolimod capsules or in the two months after you stop taking it because of the risk of harm to the baby. Infections. Fingolimod capsules can increase your risk of serious infections that can be life-threatening and cause death.
You should not receive live vaccines during treatment with fingolimod capsules and for 2 months after you stop taking fingolimod capsules. Talk to your doctor before you receive a vaccine during treatment and for 2 months after treatment with fingolimod capsules. If you receive a live vaccine, you may get the infe…