
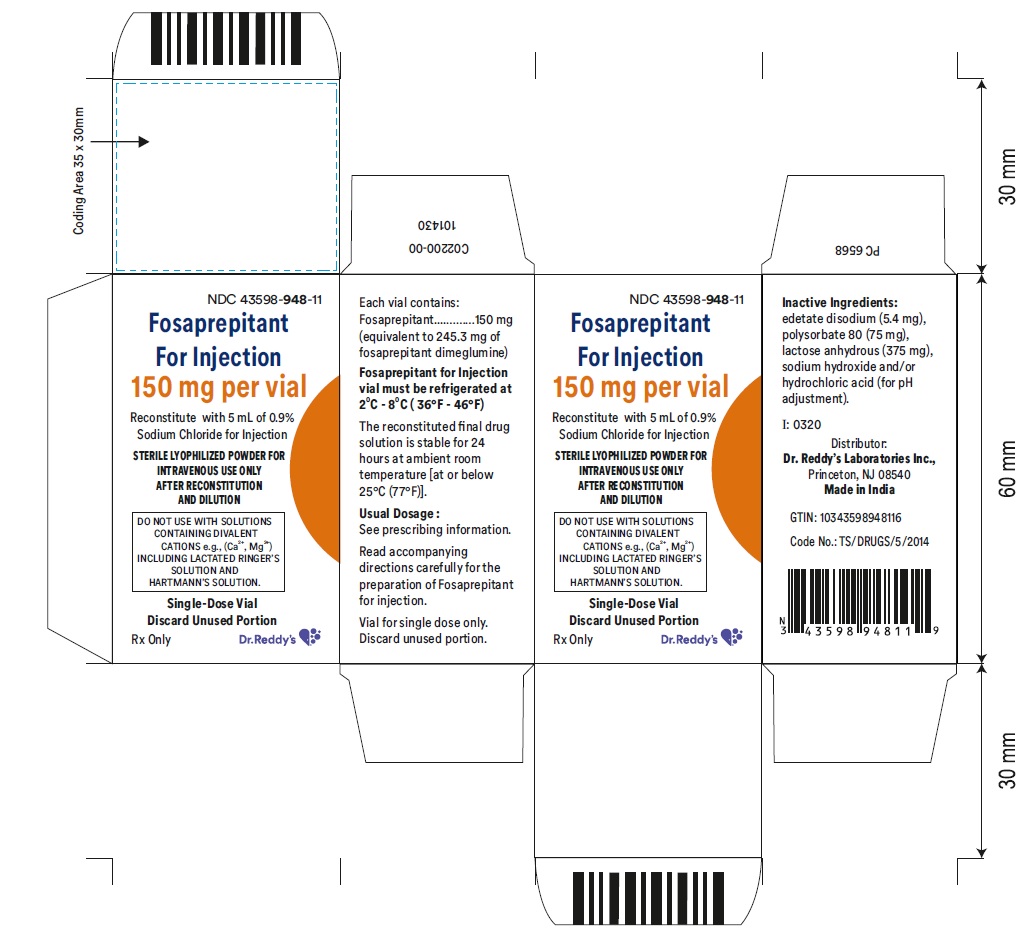
Fosaprepitant 150 mg/5mL Injection, Powder, Lyophilized, For Solution, 1 vial — NDC 43598-948-11 (Billing 43598-0948-11)
This is a package of 1 vial of Fosaprepitant 150 mg/5mL Injection, Powder, Lyophilized, For Solution from Dr. Reddy's Laboratories Inc.,, marketed since Jul 2020 and currently FDA-listed, this package's marketing is listed to end Jun 2029. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 066837
- GCN: 29247
- HICL (First Databank): 035346
- AHFS class code: 56:22.32.00
- RxCUI (RxNorm): 1731077
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
Aprepitant injection and fosaprepitant injection are used along with other medications to prevent nausea and vomiting in adults that may occur within 24 hours or several days after receiving certain cancer chemotherapy treatments. Fosaprepitant injection can also be used in children 6 months of age and older. Aprepitant and fosaprepitant injections are not used to treat nausea and vomiting that you already have. Aprepitant and fosaprepitant injections are in a class of medications called antiemetics. They work by blocking the action of neurokinin, a natural substance in the brain that causes n...
Read the full MedlinePlus article ↗- It helps prevent nausea and vomiting caused by cancer chemotherapy. You get it along with other anti-nausea medicines. It prevents symptoms but is not studied for treating nausea t...
- A healthcare professional gives it as an IV infusion, usually on the first day of chemotherapy. It finishes about 30 minutes before chemo begins. You will also get a steroid and an...
- Fatigue, diarrhea, low blood counts and weakness are common. Some people have pain or redness at the IV site. Tell your team about any discomfort at the site.
- Tell your nurse immediately if you feel flushed, short of breath, faint or have a rash during or after the infusion. Also report severe pain or swelling where the IV is.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Fosaprepitant — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $98.09 | $98.09 / 1 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J1453 | $0.123 / J1453 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 43598-0948-11 You're viewing this Main listing | 1 VIAL in 1 CARTON / 1 mL in 1 VIAL | 2020-07-01 | Jun 30, 2029 | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Emend 150 mg/5mL 00006-3061-00 | Merck | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant Dimeglumine 150 mg/5mL 00143-9384-01 | Hikma | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant Dimeglumine 150 mg/5mL 00143-9428-01 | Hikma | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 00338-0008-01 | Baxter | 1 vial | — | — | FDA listed | — |
| Fosaprepitant 150 mg 00591-4385-79 | Actavis | 1 injection | — | — | FDA listed | — |
| Fosaprepitant 150 mg/5mL 16714-0248-01 | NorthStar | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 31722-0165-31 | Camber | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg 43598-0671-11 | Dr. | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 43598-0859-11 | Dr. | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mLthis 43598-0948-11 | Dr. | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant Dimeglumine 150 mg/5mL 55150-0299-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 63323-0972-10 | Fresenius | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant Dimeglumine 150 mg/5mL 67184-0540-01 | Qilu | 1 vial | — | AP | FDA listed | — |
| fosaprepitant 150 mg/5mL 67457-0889-10 | Mylan | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 68001-0523-36 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 68001-0675-25 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 71731-5111-01 | Chia | 1 vial | — | AP | FDA listed | — |
| fosaprepitant 150 mg/5mL 71839-0104-01 | BE | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 72162-2636-02 | Bryant | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 72205-0054-01 | Novadoz | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 72205-0083-01 | Novadoz | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 72603-0450-01 | Northstar | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 83634-0776-10 | Avenacy, | 1 vial | — | AP | FDA listed | — |
| Fosaprepitant 150 mg/5mL 68001-0421-22 | BluePoint | 1 vial | — | — | Discontinued | — |
| Navitrux 150 mg/5mL 83831-0153-01 | AVYXA | 1 vial | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
375 mg / 5 mL
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
5.4 mg / 5 mL
UNII MP1J8420LU
A salt derived from edetic acid that binds to trace metals in medicines. It serves as a chelating agent and preservative to prevent metal-catalyzed breakdown of the drug and extend shelf life.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
75 mg / 5 mL
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Fosaprepitant for injection, in combination with other antiemetic agents, is indicated in adults for the prevention of: acute and delayed nauseaand vomiting associated with initial and repeat coursesof highly emetogenic cancer chemotherapy (HEC) including high-dose cisplatin. delayed nausea and vomiting associated with initial and repeat courses of moderately emetogenic cancer chemotherapy (MEC). Limitations of Use Fosaprepitant for injection has not been studied for the treatment of established nausea and vomiting.
Pediatric use information is approved for Merck Sharp & Dohme Corp., a subsidiary of Merck & Co., Inc.’s Emend (fosaprepitant) for injection. However, due to Merck Sharp & Dohme Corp., a subsidiary of Merck & Co., Inc.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information. Fosaprepitant for injection is a substance P/neurokinin-1 (NK 1 ) receptor antagonist, indicated in adults, in combination with other antiemetic agents, for the prevention of ( 1 ): acute and delayed nausea and vomiting associated with initial and repeat coursesof highly emetogenic cancer chemotherapy (HEC) including high-dose cisplatin delayed nausea and vomiting associated with initial and repeat courses of moderately emetogenic cancer chemotherapy (MEC).
Limitations of Use ( 1 ) Fosaprepitant for injection has not been studied for treatment of established nausea and vomiting.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended Dosage ( 2.1 ) Administer fosaprepitant for injection as an intravenous infusion; complete the infusion approximately 30 minutes prior to chemotherapy. Adults: 150 mg on Day 1. Administer fosaprepitant for injection on Day 1 as an intravenous infusion over 20 to 30 minutes (adults). completing the infusion approximately 30 minutes prior to chemotherapy.
See Full Prescribing Information for dosages of concomitantantiemetic(s). ( 2.1 )
2.1Prevention of Nausea and Vomiting Associated with HEC and MEC in Adult Patients The recommended dosage of fosaprepitant for injection, dexamethasone, and a 5-HT 3 antagonist for the prevention of nausea and vomiting associated with administration of HEC or MEC in adults is shown in Table 1 or Table 2, respectively. Administer fosaprepitant for injectionas an intravenous infusion on Day 1 over 20 to 30 minutes, completing the infusion approximately 30 minutes priorto chemotherapy. Table 1 Recommended Adult Dosing for the Prevention of Nausea and Vomiting Associated with HEC Day 1 Day 2 Day 3 Day 4 Fosaprepitant for injection 150 mg intravenously over 20 to 30 minutes approximately 30 minutes prior to chemotherapy none none none Dexamethasone * 12 mg orally 8 mg orally 8 mg orally twice daily 8 mg orally twice daily 5-HT 3 antagonist See selected 5-HT 3 antagonist prescribing information for the recommended dosage none none none * Administer dexamethasone 30 minutes prior to chemotherapy treatment on Day 1 and in the morning on Days 2 through 4.
Also administer dexamethasone in the evenings on Days 3 and 4. A 50% dosage reduction of dexamethasone on Days 1 and 2 is recommended to account for a drug interaction with fosaprepitant for injection [see ClinicalPharmacology ( 12.3 )]. Table 2 Recommended Adult Dosing for the Prevention of Nausea and Vomiting Associated with MEC Day 1 Fosaprepitant for injection 150 mg intravenously over 20 to 30 minutes approximately 30 minutes prior to chemotherapy Dexamethasone * 12 mg orally 5-HT 3 antagonist See selected 5-HT 3 antagonist prescribing information for the recommended dosage * Administer dexamethasone 30 minutes prior to chemotherapy treatment on Day 1.
A 50% dosage reduction of dexamethasone is recommended to account for a drug interaction with fosaprepitant dimeglumine [see Clinical Pharmacology ( 12.3 )]. Pediatric use information is approved for Merck Sharp & Dohme Corp., a subsidiary of Merck & Co., Inc.’s Emend (fosaprepitant) for injection. However, due to Merck Sharp & Dohme Corp., a subsidiary of Merck & Co., Inc.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
2.3Preparation of Fosaprepitant for Injection Table 5 Preparation Instructions for Fosaprepitant for Injection (150 mg) Step 1 Aseptically inject 5 mL 0.9% Sodium Chloride Injection, USP into the vial. Assure that 0.9% Sodium Chloride Injection, USP is added to the vial along the vial wall in order to prevent foaming. Swirl the vial gently.
Avoid shaking and jetting 0.9% Sodium Chloride Injection, USP into the vial. Step 2 Aseptically prepare an infusion bag filled with 145 mL of 0.9% Sodium Chloride Injection, USP. Step 3 Aseptically withdraw the entire volume from the vial and transfer it into the infusion bag containing 145 mL of 0.9% Sodium Chloride Injection, USP to yield a total volume of 150 mL and a final concentration of 1 mg/mL .
Step 4 Gently invert the bag 2 to 3 times. Step 5 AdultsThe entire volume of the prepared infusion bag (150 mL) should be administered. Step 6 Before administration, inspect the bag for particulate matter and discoloration.
Discard the bag if particulate and/or discoloration are observed. Caution: Do not mix or reconstitute fosaprepitant for injection with solutions for which physicaland chemical compatibility have not been established. Fosaprepitant for injection is incompatible with any solutions containing divalent cations (e.g., Ca 2+ , Mg 2+ ), including… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Fosaprepitant for injection: 150 mg fosaprepitant, white to off white cake or powder in single-dose glass vial for reconstitution. Fosaprepitant for injection: 150 mg fosaprepitant, lyophilized cake or powder in single-dose vial for reconstitution ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Fosaprepitant is contraindicated in patients: who are hypersensitive to any component of the product Hypersensitivity reactions includinganaphylactic reactions, flushing, erythema, and dyspnea have been reported [see Warnings and Precautions ( 5.2 ), Adverse Reactions ( 6.2 )]. taking pimozide. Inhibition of CYP3A4 by aprepitant, the active moiety,could result in elevated plasma concentrations of this drug, which is a CYP3A4 substrate, potentially causing serious or life- threatening reactions, such as QT prolongation, a known adverse reaction of pimozide [see Warnings and Precautions( 5.1 )].
Known hypersensitivity to any component of this drug. ( 4 , 5.2 ) Concurrent use with pimozide. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS CYP3A4 Interactions: Fosaprepitant is a weak inhibitor of CYP3A4, and aprepitant, the active moiety, is a substrate, inhibitor, and inducer of CYP3A4; see Full Prescribing Information for recommendations regarding contraindications, risk of adverse reactions, and dosage adjustment of fosaprepitant and concomitant drugs. ( 4 , 5.1 , 7.1 , 7.2 ) Hypersensitivity Reactions (including anaphylaxis and anaphylactic shock): May occur during or soon after infusion; if symptoms occur, discontinue the drug.
Do not reinitiate fosaprepitant if symptoms occur with previous use. (4 , 5.2 ) Infusion Site Reactions (including thrombophlebitis, necrosis, and vasculitis): Majority of reactions reported in patients receiving vesicant chemotherapy. Avoid infusion into small veins.
Discontinue infusion and administer treatment if a severe reaction develops. ( 5.3 ) Warfarin (a CYP2C9 substrate): Risk of decreased INR of prothrombin time; monitor INR in 2–week period, particularly at 7 to 10 days, following initiation of fosaprepitant. ( 5.4 , 7.1 ) Hormonal Contraceptives: Efficacy of contraceptives may be reduced during and for 28 days following administration of fosaprepitant.
Use effective alternative or back-up methods of contraception. ( 5.5 , 7.1 , 8.3 )
5.1Clinically Significant CYP3A4 Drug Interactions Fosaprepitant, a prodrug of aprepitant, is a weak inhibitor of CYP3A4, and aprepitant is a substrate, inhibitor, and inducer of CYP3A4. Use of fosaprepitant with other drugs that are CYP3A4 substrates, may result in increased plasma concentration of the concomitant drug. o Use of pimozidewith fosaprepitant is contraindicated due to the risk of significantly increased plasma concentrations of pimozide, potentially resulting in prolongation of the QT interval, a known adverse reactionof pimozide [seeContraindications (4)].
Use of Fosaprepitant with strong or moderate CYP3A4 inhibitors (e.g., ketoconazole, diltiazem) may increase plasma concentrations of aprepitant and result in an increased risk of adversereactions related to fosaprepitant. Use of fosaprepitant with strong CYP3A4 inducers(e.g., rifampin) may result in a reductionin aprepitant plasma concentrations and decreased efficacy of fosaprepitant. See Table 7 and Table 8 for a listing of potentially significant drug interactions [see Drug Interactions ( 7.1 , 7.2 )].
5.2Hypersensitivity Reactions Serious hypersensitivity reactions, including anaphylaxis and anaphylactic shock, during or soon after infusionof fosaprepitant have occurred. Symptoms including flushing, erythema,dyspnea, hypotension and syncope have been reported [see Adverse Reactions (6.2)]. Monitor patients during and after infusion.
If hypersensitivity reactions occur, discontinue the infusion and administer appropriate medicaltherapy. Do not reinitiate fosaprepitant in patients who experience thesesymptoms with previous use [see contraindications (4)].
5.3Infusion Site Reactions Infusion site reactions (ISRs) have been reported with the use of fosaprepitant for injection [see Adverse Reactions (6.1) ] . The majority of severe ISRs, including thrombophlebitis and vasculitis, were reported with concomitant vesicant (anthracycline-based) chemotherapy administration, particularly when associated with extravasation. Necrosis was also reported in some patients with concomitant vesicant chemotherapy.
Most ISRs occurred with the first, second or third exposure to single doses of fosaprepitant for injection and in some cases, reactions persisted for two weeks or longer. Treatment of severe ISRs consisted of medical, and in some cases surgical, intervention. Avoid infusion of fosaprepitant for injection into small veins or through a butterfly catheter.
If a severe ISR develops during infusion, discontinue the infusion and administer appropriate medical treatment.
5.4Decrease in INR with Concomitant Warfarin Coadministration of fosaprepitant with warfarin, a CYP2C9 substrate, may result in a clinical… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Hypersensitivity Reactions [see Warnings and Precautions (5.2) ] Infusion Site Reactions [see Warnings and Precautions (5.3) ] Most common adverse reactions in adults (≥2%) are: fatigue, diarrhea, neutropenia, asthenia, anemia, peripheral neuropathy, leukopenia, dyspepsia, urinary tract infection, pain in extremity. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, Dr. Reddy’s Laboratories Inc., at 1-888-375-3784 at 1-848-200-1906 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The overall safety of fosaprepitant for injection was evaluated in approximately 1600 adult patients. Adverse Reactions in Adults for the Prevention of Nausea and Vomiting Associated with MEC In an active-controlled clinical trial in patients receiving MEC, safety was evaluated in 504 patients receiving a single dose of fosaprepitant for injection in combination with ondansetron and dexamethasone (fosaprepitant dimeglumine regimen) compared to 497 patients receiving ondansetron and dexamethasone alone (standard therapy).
The most common adverse reactions are listed in Table 6. Table 6 Most Common Adverse Reactions in Patients Receiving MEC * Fosaprepitant for injection, ondansetron, and dexamethasone † (N=504) Ondansetron and dexamethasone ‡ (N=497) fatigue 15% 13% diarrhea 13% 11% neutropenia 8% 7% asthenia 4% 3% anemia 3% 2% peripheral neuropathy 3% 2% leukopenia 2% 1% dyspepsia 2% 1% urinary tract infection 2% 1% pain in extremity 2% 1% * Reported in ≥2% of patients treated with the fosaprepitant dimeglumine regimen and at a greater incidence than standard therapy. † fosaprepitant dimeglumine regimen ‡ Standard therapy Infusion-site reactions were reported in 2.2% of patients treated with the fosaprepitant dimeglumine regimen compared to 0.6% of patients treated with standard therapy.
The infusion-site reactions included: infusion-site pain (1.2%, 0.4%), injection-site irritation (0.2%, 0.0%), vessel puncture-site pain (0.2%, 0.0%), and infusion-site thrombophlebitis (0.6%, 0.0%), reported in the fosaprepitant dimeglumine regimen compared to standard therapy, respectively. Adverse Reactions in Adults for the Prevention of Nausea and Vomiting Associated with HEC In an active-controlled clinical study in patients receiving HEC, safety was evaluated for 1143 patients receiving a single dose of fosaprepitant for injection compared to 1169 patientsreceiving the 3-day regimen of oral aprepitant [see Clinical Studies (14.1) ] .
The safety profile was generallysimilar to that seen in the MEC study with fosaprepitant and prior HEC studies with aprepitant. However,infusion- site reactionsoccurred at a higher incidence in patients in the fosaprepitant group (3.0%) comparedto those in the aprepitant group (0.5%). The following additional infusion-site reactions occurredin HEC study and were not reportedin the MEC study describedabove: infusion-site erythema(0.5%, 0.1%), infusion-site pruritus (0.3%, 0.0%), and infusion-site induration (0.2%, 0.1%), reported in the fosaprepitant group compared to the aprepitant group, respectively.Because fosaprepitant is converted to aprepitant, those adverse reactions associated with aprepitant might also be expected to occur with fosaprepitant for injection.
See the full prescribing information for aprepitant capsules for complete safety information regarding studies performed with oral aprepitant. Pediatric use information is approved for Merck Sharp & Dohme Corp., a subsidiary of Merck & Co., Inc.’s Emend (fosaprepitant) for injection. However, due to Merck Sharp & Dohme Corp., a subsidiary of Merck & Co., Inc.’s… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS See Full Prescribing Information for a list of clinicallysignificant drug interactions. ( 4 , 5.1 , 5.4 , 5.5 , 7.1 , 7.2 ) Pediatric use information is approved for Merck Sharp & Dohme Corp., a subsidiary of Merck & Co., Inc.’s Emend (fosaprepitant) for injection. However, due to Merck Sharp & Dohme Corp., a subsidiary of Merck & Co., Inc.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
7.1Effect of Fosaprepitant/Aprepitant on the Pharmacokinetics of Other Drugs When administered intravenously, fosaprepitant, a prodrug of aprepitant, is converted to aprepitant within 30 minutes.Therefore, drug interactions following administration of fosaprepitant for injection are likely to occur with drugs that interact with oral aprepitant. Fosaprepitant, given as a single 150-mg dose, is a weak inhibitor of CYP3A4, and the weak inhibition of CYP3A4 continues for 2 days after single dose administration. Single dose fosaprepitant does not induce CYP3A4.
Aprepitant is a substrate, an inhibitor, and an inducer of CYP3A4. Aprepitant is also an inducerof CYP2C9 [seeClinical Pharmacology (12.3) ] . Some substrates of CYP3A4 are contraindicated with fosaprepitant [see Contraindications (4) ] .
Dosage adjustment of some CYP3A4 and CYP2C9 substrates may be warranted, as shown in Table 7. Table 7 Effects of Fosaprepitant/Aprepitant on the Pharmacokinetics of Other Drugs CYP3A4 Substrates Pimozide Clinical Impact Increased pimozide exposure Intervention Fosaprepitant is contraindicated [see Contraindications (4) ] . Benzodiazepines Clinical Impact Increased exposure to midazolam or other benzodiazepines metabolized via CYP3A4(alprazolam, triazolam) may increase the risk of adverse reactions [see Clinical Pharmacology (12.3) ].
Intervention Monitor for benzodiazepine-related adverse reactions. Dexamethasone Clinical Impact Increased dexamethasone exposure [see Clinical Pharmacology (12.3) ] . Intervention Reducethe dose of oral dexamethasone by approximately 50% [see Dosageand Administration (2.1) ] .
Methylprednisolone Clinical Impact Increased methylprednisolone exposure [see Clinical Pharmacology (12.3) ] . Intervention Reduce the dose of oral methylprednisolone by approximately 50% on Days 1 and 2 for patients receiving HEC and on Day 1 for patients receiving MEC.Reduce the dose of intravenous methylprednisolone by 25% on Days 1 and 2 for patients receiving HEC and on Day 1 for patients receiving MEC. Chemotherapeutic agents that are metabolized by CYP3A4 Clinical Impact Increased exposure of the chemotherapeutic agentmay increase the risk of adverse reactions [see Clinical Pharmacology (12.3) ] .
Intervention Vinblastine, vincristine, or ifosfamide or other chemotherapeutic agentsMonitor for chemotherapeutic-related adverse reactions.Etoposide, vinorelbine, paclitaxel, and docetaxelNo dosage adjustment needed. Hormonal Contraceptives Clinical Impact Decreased hormonal exposure duringadministration of and for 28 days after administration of the last dose of fosaprepitant [see Warnings and Precautions (5.5) , Use in Specific Populations (8.3) , and Clinical Pharmacology (12.3) ]. Intervention Effective alternative or back-up methods of contraception (such as condoms and spermicides) should be used during treatment with fosaprepitant and for 1 month following administration of fosaprepitant.
Examples birth control pills, skin patches, implants, and certain IUDs CYP2C9 Substrates Warfarin Clinical Impact Decreased warfarin exposure and decreased prolongation of prothrombin time (INR) [see Warnings and Precautions (5.4) , Clinical Pharmacology (12.3) ] . Intervention In patients on chronic warfarin therapy, monitor the prothrombin time(INR) in the2-week period, particularly at 7 to 10 days, following administration of fosaprepitant with each chemotherapy cycle. Other 5-HT 3 Antagonists Clinical Impact No change in the exposure of the 5-HT 3 antagonist [see Clinical Pharmacology (12… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are insufficient data on use of fosaprepitant in pregnant women to inform a drug associated risk. In animal reproduction studies, no adverse developmental effects were observed in rats or rabbits exposed during the period of organogenesis to systemic drug levels (AUC) approximately equivalent to the exposure at the recommended human dose (RHD) of 150 mg [seeData] . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
In the U.S. general population, the estimated background risk of majorbirth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data In embryofetal development studies in rats and rabbits, aprepitant was administered during the period of organogenesis at oral dosesup to 1,000 mg/kg twicedaily (rats) and up to the maximum tolerated dose of 25 mg/kg/day (rabbits). No embryofetal lethality or malformations were observed at any dose level in eitherspecies.
The exposures(AUC) in pregnantrats at 1,000 mg/kg twice daily and in pregnant rabbits at 25 mg/kg/day were approximately equivalent to the exposure at the RHD of 150 mg. Aprepitant crosses the placenta in rats and rabbits.
8.2Lactation Risk Summary Lactation studies have not been conducted to assess the presence of aprepitant in human milk, the effects on the breastfed infant,or the effects on milk production. Aprepitant is present in rat milk. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for fosaprepitant and any potential adverse effects on the breastfed infant from fosaprepitant or from the underlying maternal condition.
8.3Females and Males of Reproductive Potential Contraception Upon administration of fosaprepitant, the efficacy of hormonal contraceptives may be reduced. Advise females of reproductive potential using hormonal contraceptives to use an effective alternative or back-up non-hormonal contraceptive (such as condoms and spermicides) during treatment with fosaprepitant and for 1 month following the last dose [see Drug Interactions (7.1) ,Clinical Pharmacology (12.3) ] .
8.4Pediatric Use The safety and effectiveness of fosaprepitant dimeglumine for the prevention of nausea and vomiting associated with HEC or MEC have not been established in patients less than 6 months of age. Juvenile Animal Toxicity Data In juvenile dogs treated with fosaprepitant, changes in reproductive organs were observed. In juvenile rats treated with aprepitant, slight changes in sexual maturation were observed without an effect on reproduction.
No effects on neurobehavior, sensory and motor function, or learning and memory were observed in rats. In a toxicity study in juvenile dogs treated with fosaprepitant from postnatal day 14 (equivalent to a newborn human) to day 42 (approximately equivalent to a 2 year old human), decreased testicular weight and Leydig cell size were seen in the males at 6 mg/kg/day and increased uterine weight, hypertrophy of the uterus and cervix, and edema of vaginal tissues were seen in females from 4 mg/kg/day. A study was also conducted in young rats to evaluate the effects of aprepitant on growth and on neurobehavioral and sexual development.
Rats were treated at oral doses up to the maximum feasible dose of 1000 mg/kg twice daily from the early postnatal period (Postnatal Day 10 (equivalent to a newborn human) through Postnatal Day 58 (approximately equivalent to a 15 year old human)). Slight changes in the onset of sexual maturation were observed in female and male rats; however, there were no effects on mating, fertility, embryonic-fetal survival, or histomorphology of the reproductive organs. There were no effects in neurobehavioral tests of sensory function, motor function, and learning and memory.
Pediatric use information is approved for Merck Sharp & Dohme Corp., a subsidiary of Merck & Co.,… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are insufficient data on use of fosaprepitant in pregnant women to inform a drug associated risk. In animal reproduction studies, no adverse developmental effects were observed in rats or rabbits exposed during the period of organogenesis to systemic drug levels (AUC) approximately equivalent to the exposure at the recommended human dose (RHD) of 150 mg [seeData] . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
In the U.S. general population, the estimated background risk of majorbirth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data In embryofetal development studies in rats and rabbits, aprepitant was administered during the period of organogenesis at oral dosesup to 1,000 mg/kg twicedaily (rats) and up to the maximum tolerated dose of 25 mg/kg/day (rabbits). No embryofetal lethality or malformations were observed at any dose level in eitherspecies.
The exposures(AUC) in pregnantrats at 1,000 mg/kg twice daily and in pregnant rabbits at 25 mg/kg/day were approximately equivalent to the exposure at the RHD of 150 mg. Aprepitant crosses the placenta in rats and rabbits.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of fosaprepitant dimeglumine for the prevention of nausea and vomiting associated with HEC or MEC have not been established in patients less than 6 months of age. Juvenile Animal Toxicity Data In juvenile dogs treated with fosaprepitant, changes in reproductive organs were observed. In juvenile rats treated with aprepitant, slight changes in sexual maturation were observed without an effect on reproduction.
No effects on neurobehavior, sensory and motor function, or learning and memory were observed in rats. In a toxicity study in juvenile dogs treated with fosaprepitant from postnatal day 14 (equivalent to a newborn human) to day 42 (approximately equivalent to a 2 year old human), decreased testicular weight and Leydig cell size were seen in the males at 6 mg/kg/day and increased uterine weight, hypertrophy of the uterus and cervix, and edema of vaginal tissues were seen in females from 4 mg/kg/day. A study was also conducted in young rats to evaluate the effects of aprepitant on growth and on neurobehavioral and sexual development.
Rats were treated at oral doses up to the maximum feasible dose of 1000 mg/kg twice daily from the early postnatal period (Postnatal Day 10 (equivalent to a newborn human) through Postnatal Day 58 (approximately equivalent to a 15 year old human)). Slight changes in the onset of sexual maturation were observed in female and male rats; however, there were no effects on mating, fertility, embryonic-fetal survival, or histomorphology of the reproductive organs. There were no effects in neurobehavioral tests of sensory function, motor function, and learning and memory.
Pediatric use information is approved for Merck Sharp & Dohme Corp., a subsidiary of Merck & Co., Inc.’s Emend (fosaprepitant) for injection. However, due to Merck Sharp & Dohme Corp., a subsidiary of Merck & Co., Inc.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 1649 adult cancer patients treated with intravenous fosaprepitant in HEC and MEC clinical studies, 27% were aged 65 and over, while 5% were aged 75 and over. Other reported clinical experience with fosaprepitant has not identified differences in responses between elderly and younger patients. In general, use caution when dosing elderly patients as they have a greater frequency of decreased hepatic, renal or cardiac function and concomitant disease or other drug therapy [see Clinical Pharmacology (12.3) ].
🆘 Overdosage ▾
10 OVERDOSAGE There is no specificinformation on the treatment of overdosage with fosaprepitant or aprepitant.In the event of overdose, fosaprepitant should be discontinued and general supportive treatment and monitoring should be provided. Because of the antiemetic activity of fosaprepitant, drug-induced emesis may not be effective in cases of fosaprepitant overdosage.Aprepitant is not removedby hemodialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Fosaprepitant is a prodrugof aprepitant and accordingly, its antiemetic effectsare attributable to aprepitant.Aprepitant is a selectivehigh-affinity antagonist of human substanceP/neurokinin 1(NK1) receptors. Aprepitant has little or no affinity for serotonin (5-HT 3 ), dopamine, and corticosteroid receptors, the targets of existing therapiesfor chemotherapy-induced nausea and vomiting(CINV). Aprepitant has been shown in animal models to inhibit emesis induced by cytotoxicchemotherapeutic agents, such as cisplatin, via central actions.
Animal and human Positron Emission Tomography (PET) studies with aprepitant have shown that it crosses the blood brain barrier and occupies brain NK 1 receptors. Animal and humanstudies have shown that aprepitant augmentsthe antiemetic activityof the 5-HT 3 -receptor antagonist ondansetron and the corticosteroid dexamethasone and inhibitsboth the acuteand delayed phasesof cisplatin-induced emesis.
12.2Pharmacodynamics Cardiac Electrophysiology In a randomized, double-blind, positive-controlled, thorough QTc study, a single 200-mgdose of fosaprepitant (approximately 1.3 times the recommended dose) had no effect on the QTc interval.
12.3Pharmacokinetics Aprepitant after Fosaprepitant Administration Following administration of a single intravenous 150-mg dose of fosaprepitant, a prodrug of aprepitant administered as a 20-minute infusion to healthy subjects, the mean AUC 0-∞ of aprepitant was 37.4 (±14.8) mcg • hr/mL and the mean maximal aprepitant concentration (C max ) was 4.2 (±1.2) mcg/mL. Plasma concentrations of fosaprepitant are below the limits of quantification (10 ng/mL) within 30 minutes of the completion of infusion. Distribution Aprepitant is greater than 95% bound to plasma proteins.
The mean apparent volume of distribution at steady state(Vd ss ) was approximately 70 L in humans. Aprepitant crossesthe blood brainbarrier in humans[see Clinical Pharmacology ( 12.1 )]. Elimination Metabolism Fosaprepitant is converted to aprepitant in in vitro incubations with human liver preparations and in S9 preparations from multiple other human tissues including kidney, lung and ileum.
Thus, it appears that the conversion of fosaprepitant to aprepitant can occur in multiple extrahepatic tissues in addition to the liver. Aprepitant undergoes extensive metabolism. In vitro studies using human liver microsomes indicate that aprepitant is metabolized primarily by CYP3A4 with minor metabolism by CYP1A2 and CYP2C19.
Metabolism is largely via oxidation at the morpholine ring and its side chains. No metabolism by CYP2D6, CYP2C9, or CYP2E1 was detected. In healthy young adults,aprepitant accounts for approximately 24% of the radioactivity in plasma over 72 hours following a single oral 300-mg dose of [ 14 C]-aprepitant, indicating a substantial presence of metabolites in the plasma.
Seven metabolites of aprepitant, which are only weakly active, havebeen identified in human plasma. Excretion Following administration of a singleintravenous 100-mg dose of [ 14 C]-fosaprepitant to healthy subjects, 57% of the radioactivity was recovered in urine and 45% in feces.Aprepitant is eliminated primarilyby metabolism; aprepitant is not renally excreted. The apparent terminal half-liferanged from approximately 9 to 13 hours.
Specific Populations Age: Geriatric Population Following oral administration of a single 125-mg dose of aprepitant on Day 1 and 80 mg once daily on Days 2 through 5, the AUC 0-24hr of aprepitant was 21% higher on Day 1 and 36% higher on Day 5 in elderly (65 years and older) relativeto younger adults.The C max was 10% higher on Day 1 and 24% higher on Day 5 in elderly relative to younger adults. These differences are not considered clinically meaningful [see Use in Specific Populations (8.5)]. Sex Following oral administration of a single dose of aprepitant, ranging from 40 mg to 375 mg, the AUC 0-24hr and C max are 9% and 17% higher in females as co… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Fosaprepitant is a prodrugof aprepitant and accordingly, its antiemetic effectsare attributable to aprepitant.Aprepitant is a selectivehigh-affinity antagonist of human substanceP/neurokinin 1(NK1) receptors. Aprepitant has little or no affinity for serotonin (5-HT 3 ), dopamine, and corticosteroid receptors, the targets of existing therapiesfor chemotherapy-induced nausea and vomiting(CINV). Aprepitant has been shown in animal models to inhibit emesis induced by cytotoxicchemotherapeutic agents, such as cisplatin, via central actions.
Animal and human Positron Emission Tomography (PET) studies with aprepitant have shown that it crosses the blood brain barrier and occupies brain NK 1 receptors. Animal and humanstudies have shown that aprepitant augmentsthe antiemetic activityof the 5-HT 3 -receptor antagonist ondansetron and the corticosteroid dexamethasone and inhibitsboth the acuteand delayed phasesof cisplatin-induced emesis.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING No.948 —Single-dose glass vial containing 150 mg of fosaprepitant as a white to off white lyophilized cake or powder for reconstitution. Supplied as follows: NDC43598-948-11 1 vial per carton. StorageFosaprepitant for injection vials must be refrigerated, store at 2°C - 8°C(36°F - 46°F).The reconstituted final drug solution is stable for 24 hours at ambient room temperature [at or below 25°C (77°F)].
📋 Description ▾
11 DESCRIPTION Fosaprepitant for injection is a sterile, lyophilized formulation containing fosaprepitant dimeglumine,a prodrug of aprepitant a substance P/neurokinin-1 (NK 1 ) receptor antagonist, an antiemetic agent, chemically described as 1 Deoxy-1-(methylamino)-D-glucito[3-[[(2R,3S)-2-[(1R)-1-[3,5- bis(trifluoromethyl)phenyl]ethoxy]-3-(4 fluorophenyl)-4-morpholinyl]methyl]-2,5-dihydro-5-oxo-1H-1,2,4-triazol-1-yl]phosphonate(2:1) (salt).Its empirical formula is C 23 H 22 F 7 N 4 O 6 P • 2(C 7 H 17 NO 5 ) and its structural formula is: Fosaprepitant dimeglumine is a white to off-white powder with a molecular weight of 1004.83.
It is freely soluble in water soluble in N,N-Dimethylsulfoxide and insoluble in n-hexane.Each vial of fosaprepitant for injection for administration as an intravenous infusion contains 245.3 mg of fosaprepitant dimeglumine equivalent to 150 mg of fosaprepitant free acid and the following inactive ingredients: edetate disodium (5.4 mg), lactose anhydrous(375 mg), polysorbate 80 (75 mg), sodium hydroxide and/or hydrochloric acid (for pH adjustment).
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDAapproved patientlabeling (Patient Information). Hypersensitivity Advise patientsthat hypersensitivity reactions, including anaphylaxis and anaphylactic shock, have been reported in patients taking fosaprepitant. Advisepatients to seek immediate medical attention if they experience signs or symptoms of a hypersensitivity reaction, such as hives, rash and itching, skin peeling or sores, flushing, difficulty in breathingor swallowing, or dizziness, rapid or weak heartbeat or feeling faint [see warnings and precautions ( 5.2 )].
Infusion Site Reactions Advise patients to seek medical attention if they experience new or worsening signs or symptoms of an infusion site reaction, such as erythema, edema, pain, necrosis, vasculitis, or thrombophlebitis at or near the infusion site [see Warnings and Precautions ( 5.3 )]. Drug Interactions Advise patients to discuss all medications they are taking, including other prescription, non prescription medication or herbal products[see Contraindications (4 ), Warnings and Precautions ( 5.1 )]. Warfarin: Instruct patientson chronic warfarintherapy to follow instructions from their healthcare provider regarding blood draws to monitor their INR during the 2-week period, particularly at 7 to 10 days, followinginitiation of fosaprepitant with each chemotherapy cycle [see Warningsand Precautions ( 5.4 )].
Hormonal Contraceptives: Advise patients that administration of fosaprepitant may reduce the efficacy of hormonal contraceptives. Instruct patients to use effectivealternative or back-upmethods of contraception (such as condomsand spermicides) during treatment with fosaprepitant and for 1 month following administration of fosaprepitant [see Warnings and Precautions ( 5.5 ),Use in Specific Populations ( 8.3 )]. Distributor: Dr.
Reddy’s Laboratories Inc., Princeton, NJ 08540 Made in India Issued: 0320
💬 Patient Medication Information ▾
Patient Information Fosaprepitant (FOS a PREP i tant) for Injection Read this patientinformation before you start receivingfosaprepitant for injection and each time you are scheduled to receive fosaprepitant for injection. There may be new information. This information does not take the place of talking with your healthcare provider about your medical condition or treatment.
What is fosaprepitant for injection? Fosaprepitant for injection is a prescription medicine used with other medicines that treat nausea and vomiting in patients 18 years of age and older to prevent nausea and vomiting caused by certain anti-cancer (chemotherapy) medicines. Fosaprepitant for injection is not used to treat nausea and vomiting that you already have.
It is not known if fosaprepitant for injection is safe and effective in children less than 6 months of age. Who should not recieve fosaprepitant for injection? Do not receive fosaprepitant for injection if you: are allergic to fosaprepitant, aprepitant, or any of the ingredients in fosaprepitant for injection.
See the end of this leaflet for a complete list of the ingredients in fosaprepitant for injection.are taking pimozide (ORAP ® ) What should I tell my healthcare provider before receiving fosaprepitant for injection? Before receiving fosaprepitant for injection, tell your healthcare provider if you: have liver problems are pregnant or plan to become pregnant. It is not known if fosaprepitant for injection can harm your unborn baby.
Women who use birth control medicines containing hormones to prevent pregnancy (birth control pills, skin patches, implants, and certain IUDs) should also use a backup method of birth control that does not contain hormones, such as condoms and spermicides, during treatment with fosaprepitant for injection and for 1 month after receiving fosaprepitant for injection. are breastfeeding or plan to breastfeed. It is not known if fosaprepitant for injection passes into your breast milk. Talk to your healthcare provider about the best way to feed your baby if you receive fosaprepitant for injection.
Tell your healthcare provider about all the medicinesyou take , including prescription and over-the-counter medicines, vitamins, and herbal supplements.Fosaprepitant for injection may affect the way other medicines work, and other medicines may affect the way fosaprepitant for injection works, causing serious side effects.Know the medicines you take. Keep a list of them to show your healthcare provider or pharmacist when you get a new medicine. How will I receive fosaprepitant for injection?
Adults 18 years of age and older :Fosaprepitant for injection will be given on Day 1 of chemotherapy treatment. It will be given to you by intravenous (IV) infusion in your vein about 50 to 60 minutes before you start your chemotherapy treatment.If you take the blood thinner medicine warfarin sodium (COUMADIN ® , JANTOVEN ®) , your healthcare provider may do blood tests after you receive fosaprepitant for injection to check your blood clotting. What are the possible side effectsof fosaprepitant for injection?
Fosaprepitant for injection may cause serious side effects, including: Serious allergic reactions. Allergic reactions can happen with fosaprepitant for injection and may be serious. Tell your doctor or nurse right away if you have hives, rash, itching, flushing or redness of your face or skin, trouble breathing or swallowing, dizziness, a rapid or weak heartbeat, or you feel faint during or soon after you receive fosaprepitant for injection, as you may need emergency medical care.
Severe skin reactions, which may include rash, skin peeling, or sores, may occur. Infusion site reactions (ISR) at or near the infusion site have happened with fosaprepitant for injection. Most severe ISR have happened with a certain type of chemotherapy medicine that can burn or blister your skin (vesicant) with side effects, including pain, swelling and redness.
Death of skin tissue (necrosis) has happened… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Contraception Upon administration of fosaprepitant, the efficacy of hormonal contraceptives may be reduced. Advise females of reproductive potential using hormonal contraceptives to use an effective alternative or back-up non-hormonal contraceptive (such as condoms and spermicides) during treatment with fosaprepitant and for 1 month following the last dose [see Drug Interactions (7.1) ,Clinical Pharmacology (12.3) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Aprepitant after Fosaprepitant Administration Following administration of a single intravenous 150-mg dose of fosaprepitant, a prodrug of aprepitant administered as a 20-minute infusion to healthy subjects, the mean AUC 0-∞ of aprepitant was 37.4 (±14.8) mcg • hr/mL and the mean maximal aprepitant concentration (C max ) was 4.2 (±1.2) mcg/mL. Plasma concentrations of fosaprepitant are below the limits of quantification (10 ng/mL) within 30 minutes of the completion of infusion. Distribution Aprepitant is greater than 95% bound to plasma proteins.
The mean apparent volume of distribution at steady state(Vd ss ) was approximately 70 L in humans. Aprepitant crossesthe blood brainbarrier in humans[see Clinical Pharmacology ( 12.1 )]. Elimination Metabolism Fosaprepitant is converted to aprepitant in in vitro incubations with human liver preparations and in S9 preparations from multiple other human tissues including kidney, lung and ileum.
Thus, it appears that the conversion of fosaprepitant to aprepitant can occur in multiple extrahepatic tissues in addition to the liver. Aprepitant undergoes extensive metabolism. In vitro studies using human liver microsomes indicate that aprepitant is metabolized primarily by CYP3A4 with minor metabolism by CYP1A2 and CYP2C19.
Metabolism is largely via oxidation at the morpholine ring and its side chains. No metabolism by CYP2D6, CYP2C9, or CYP2E1 was detected. In healthy young adults,aprepitant accounts for approximately 24% of the radioactivity in plasma over 72 hours following a single oral 300-mg dose of [ 14 C]-aprepitant, indicating a substantial presence of metabolites in the plasma.
Seven metabolites of aprepitant, which are only weakly active, havebeen identified in human plasma. Excretion Following administration of a singleintravenous 100-mg dose of [ 14 C]-fosaprepitant to healthy subjects, 57% of the radioactivity was recovered in urine and 45% in feces.Aprepitant is eliminated primarilyby metabolism; aprepitant is not renally excreted. The apparent terminal half-liferanged from approximately 9 to 13 hours.
Specific Populations Age: Geriatric Population Following oral administration of a single 125-mg dose of aprepitant on Day 1 and 80 mg once daily on Days 2 through 5, the AUC 0-24hr of aprepitant was 21% higher on Day 1 and 36% higher on Day 5 in elderly (65 years and older) relativeto younger adults.The C max was 10% higher on Day 1 and 24% higher on Day 5 in elderly relative to younger adults. These differences are not considered clinically meaningful [see Use in Specific Populations (8.5)]. Sex Following oral administration of a single dose of aprepitant, ranging from 40 mg to 375 mg, the AUC 0-24hr and C max are 9% and 17% higher in females as compared with males.
The half-life of aprepitantis approximately 25% lower in femalesas compared with males and T max occursat approximately the same time. These differences are not considered clinically meaningful. Race/Ethnicity Following oral administration of a single dose of aprepitant, ranging from 40 mg to 375 mg, the AUC 0-24hr and C max are approximately 27% and 19% higher in Hispanicsas compared with Caucasians.
The AUC 0-24hr and C max were 74% and 47% higher in Asians as compared to Caucasians. There was no difference in AUC 0-24hr or C max between Caucasians and Blacks.These differences are not considered clinicallymeaningful. Renal Impairment A single 240-mg oral dose of aprepitant was administered to patients with severe renal impairment (creatinine clearance less than 30 mL/min/1.73 m 2 as measured by 24-hour urinary creatinine clearance) and to patients with end stage renal disease(ESRD) requiring hemodialysis.
In patients with severe renal impairment, the AUC 0-∞ of total aprepitant (unbound and protein bound) decreased by 21% and Cmax decreased by 32%, relative to healthy subjects (creatinine clearance greater than 80 mL/min estimated by Cockcroft-Gault method). In patients with ESRD undergoing h… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology In a randomized, double-blind, positive-controlled, thorough QTc study, a single 200-mgdose of fosaprepitant (approximately 1.3 times the recommended dose) had no effect on the QTc interval.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Prevention of Nausea and Vomiting Associated with HEC in Adults In a randomized, parallel,double-blind, active-controlled study, fosaprepitant for injection 150 mg as a single intravenous infusion(N=1147) was comparedto a 3-day oral aprepitant regimen (N=1175) in patientsreceiving a HEC regimen that included cisplatin (≥70 mg/m 2 ). All patients in both groups received dexamethasone and ondansetron (see Table 11). Patient demographics were similar betweenthe two treatment groups.
Of the total 2322 patients, 63% were men, 56% White,26% Asian, 3% American Indian/Alaska Native,2% Black, 13% Multi-Racial, and 33% Hispanic/Latino ethnicity. Patient ages ranged from 19 to 86 years of age, with a mean age of 56 years.Other concomitant chemotherapy agents commonly administered were fluorouracil (17%),gemcitabine (16%), paclitaxel (15%), and etoposide (12%). T a ble 11: Treatment Regimens in Adult HEC Trial* Day 1 Day 2 Day 3 Day 4 Fosaprepitant Regimen Fosaprepitant for injection 150 mg intravenously over 20 to 30 minutes approximately 30 minutes prior to chemotherapy none none none Oral dexamethasone † 12 mg 8 mg 8 mg twice daily 8 mg twice daily Ondansetron Ondansetron ‡ none none none Oral Aprepitant Regimen Aprepitant capsules 125 mg 80 mg 80 mg none Oral dexamethasone § 12 mg 8 mg 8 mg 8 mg Ondansetron Ondansetron ‡ none none none * fosaprepitant for injection placebo, aprepitant capsules placebo and dexamethasone placebo (in the evenings on Days 3 and 4) were used to maintain blinding. † Dexamethasone was administered 30 minutes prior to chemotherapy treatment on Day 1 and in the morning on Days 2 through 4.
Dexamethasone was also administered in the evenings on Days 3 and 4. The 12 mg dose of dexamethasone on Day 1 and the 8 mg once daily dose on Day 2 reflects a dosage adjustment to account for a drug interaction with the fosaprepitant for injection regimen [see Clinical Pharmacology ( 12.3 )]. ‡Ondansetron 32 mg intravenous was used in the clinical trials of fosaprepitant. Although this dose was used in clinical trials, this is no longer the currently recommended dose.
Refer to the ondansetron prescribing information for the current recommended dose. § Dexamethasone was administered 30 minutes prior to chemotherapy treatment on Day 1 and in the morning on Days 2 through 4. The 12 mg dose of dexamethasone on Day 1 and the 8 mg once daily dose on Days 2 through 4 reflects a dosage adjustment to account for a drug interaction with the oral aprepitant regimen [see Clinical Pharmacology( 12.3 )]. The efficacy of fosaprepitant for injection was evaluated based on the primary and secondary endpoints listed in Table 12 and was shown to be non-inferior to that of the 3-day oral aprepitant regimen with regard to complete response in each of the evaluated phases.
The pre-specified non-inferiority margin for complete response in the overall phase was 7%. The pre-specified non-inferiority margin for complete response in the delayedphase was 7.3%. Thepre-specified non-inferiority margin for no vomiting in the overall phase was 8.2%.
T a ble 12 Percent of Adult Patients Receiving HEC Responding by Treatment Group and Phase — Cycle 1 ENDPOINTS Fosaprepitant for Injection Regimen (N = 1106) * % Oral Ap repitant Regimen (N = 1134) * % Difference† (95% CI) PRIMARY ENDPOINT Complete Response ‡ Overall § 71.9 72.3 -0.4 (-4.1, 3.3) SECONDARYENDPOINTS Complete Response ‡ Delayedphase ¶ 74.3 74.2 0.1 (-3.5, 3.7) No Vomiting Overall § 72.9 74.6 -1.7 (-5.3, 2.0) * N: Number of patients included in the primary analysis of completeresponse. † Difference and Confidence interval (CI) were calculated using the method proposed by Miettinen and Nurminen and adjusted for Gender. ‡ Complete Response = no vomiting and no use of rescue therapy. § Overall = 0 to 120 hours post-initiation of cisplatin chemotherapy. ¶ Delayed phase = 25 to 120 hours post-initiation of cisplatin chemotherapy.
14.2Prevention of Nausea and Vomiting Associated… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment Of Fertility Carcinogenesis Carcinogenicity studieswere conducted in Sprague-Dawley rats and in CD-1 mice for 2 years. In the rat carcinogenicity studies, animals were treated with oral doses ranging from 0.05 to 1,000 mg/kg twice daily. The highest dose produced systemic exposuresto aprepitant approximately equivalent to (female rats) or less than (male rats) the adulthuman exposure at the RHD of 150 mg.
Treatment with aprepitant at doses of 5 to 1,000 mg/kg twicedaily caused an increase in the incidences of thyroid follicular cell adenomas and carcinomas in male rats. In female rats, it produced hepatocellular adenomas at 5 to 1,000 mg/kg twicedaily and hepatocellular carcinomas and thyroidfollicular cell adenomasat 125 to 1000mg/kg twice daily. In the mouse carcinogenicity studies,the animals were treated with oral doses ranging from 2.5 to 2,000 mg/kg/day.
The highest dose produced a systemic exposureapproximately 2 times the adult human exposure at the RHD of 150 mg. Treatment with aprepitant produced skin fibrosarcomas at 125 and 500 mg/kg/day doses in male mice. Carcinogenicity studies were not conducted with fosaprepitant.
Mutagenesis Aprepitant and fosaprepitant were not genotoxicin the Ames test, the human lymphoblastoid cell (TK6) mutagenesis test, the rat hepatocyte DNA strand break test, the Chinese hamster ovary (CHO) cell chromosome aberration test and the mouse micronucleustest. Impairment of Fertility Fosaprepitant, when administered intravenously, is rapidly convertedto aprepitant. In the fertilitystudies conducted with fosaprepitant and aprepitant, the highest systemic exposures to aprepitant were obtained following oral administration of aprepitant.
Oral aprepitant did not affectthe fertility or general reproductive performance of male or female rats at doses up to the maximum feasible dose of 1,000 mg/kg twice daily (providingexposure in male rats lower than the exposure at the recommended adult human dose of 150 mg and exposurein female rats approximately equivalent to the adult human exposure).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment Of Fertility Carcinogenesis Carcinogenicity studieswere conducted in Sprague-Dawley rats and in CD-1 mice for 2 years. In the rat carcinogenicity studies, animals were treated with oral doses ranging from 0.05 to 1,000 mg/kg twice daily. The highest dose produced systemic exposuresto aprepitant approximately equivalent to (female rats) or less than (male rats) the adulthuman exposure at the RHD of 150 mg.
Treatment with aprepitant at doses of 5 to 1,000 mg/kg twicedaily caused an increase in the incidences of thyroid follicular cell adenomas and carcinomas in male rats. In female rats, it produced hepatocellular adenomas at 5 to 1,000 mg/kg twicedaily and hepatocellular carcinomas and thyroidfollicular cell adenomasat 125 to 1000mg/kg twice daily. In the mouse carcinogenicity studies,the animals were treated with oral doses ranging from 2.5 to 2,000 mg/kg/day.
The highest dose produced a systemic exposureapproximately 2 times the adult human exposure at the RHD of 150 mg. Treatment with aprepitant produced skin fibrosarcomas at 125 and 500 mg/kg/day doses in male mice. Carcinogenicity studies were not conducted with fosaprepitant.
Mutagenesis Aprepitant and fosaprepitant were not genotoxicin the Ames test, the human lymphoblastoid cell (TK6) mutagenesis test, the rat hepatocyte DNA strand break test, the Chinese hamster ovary (CHO) cell chromosome aberration test and the mouse micronucleustest. Impairment of Fertility Fosaprepitant, when administered intravenously, is rapidly convertedto aprepitant. In the fertilitystudies conducted with fosaprepitant and aprepitant, the highest systemic exposures to aprepitant were obtained following oral administration of aprepitant.
Oral aprepitant did not affectthe fertility or general reproductive performance of male or female rats at doses up to the maximum feasible dose of 1,000 mg/kg twice daily (providingexposure in male rats lower than the exposure at the recommended adult human dose of 150 mg and exposurein female rats approximately equivalent to the adult human exposure).
📄 Recent Major Changes ▾
RECENT MAJORCHANGES Warnings and Precautions ( 5.2 ) 08/2017 Warnings and Precautions ( 5.3 ) 03/2018
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL PRINCIPAL DISPLAY PANEL SECTION Vial Label:
Carton label: Unvarnished Area Consists of: 2D Barcode, Lot Number, Expiry Date and Serial Number
Medicaid utilization & spend
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |