
Felbamate 400 mg Tablet, 90-count — NDC 53746-734-90 (Billing 53746-0734-90)
This is a package of 90 tablets of Felbamate 400 mg Tablet from Amneal Pharmaceuticals of New York LLC, marketed since Aug 2022 and currently FDA-listed; retail pharmacies pay about $0.7978 per tablet (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 53746-734-90 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 53746 labeler · 734 product · 90 package
- Package marketed since
- Aug 10, 2022
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 90 EA per package
- Barcode (UPC)
- 0353746735300
- Medicaid fills, this package
- 1,352 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 020041
- GCN: 38021
- GPI-14 (Medi-Span): 72120020000310
- HICL (First Databank): 008186
- AHFS class code: 28:12.92.00
- RxCUI (RxNorm): 198358
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Anti-epileptic Agent class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Felbamate is used to treat certain seizures in adults and children with epilepsy whose seizures have not improved with other treatments. It is used alone or in combination with other medications to treat partial seizures in adults. It is used in combination with other medications to treat partial and generalized seizures in children with Lennox-Gastaut syndrome (a disorder that causes seizures and developmental delays). Felbamate is in a class of medications called anticonvulsants. It works by decreasing abnormal activity in the brain.
Read the full MedlinePlus article ↗- It treats severe epilepsy when other medicines haven't worked well enough. It's used for partial seizures in adults and for Lennox-Gastaut syndrome in children. It isn't a first-ch...
- You take it by mouth, as tablets or liquid, several times a day. Follow your prescriber's schedule exactly. Never stop it suddenly, because seizures could increase.
- Common ones include poor appetite, nausea, vomiting, trouble sleeping, headache, dizziness and sleepiness. Tell your doctor if they bother you or don't go away.
- Call for signs of infection, unusual bleeding or bruising, or unusual paleness. Also call for yellow skin or eyes, dark urine, a serious rash, or any mood changes or thoughts of se...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Felbamate — tap one for details:
Felbamate may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.798 | $71.80 / 90 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.14 | $102.36 / 90 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1.31 | $117.80 / 90 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 53746-0734-30 53746-734-30 | 30 TABLET in 1 BOTTLE | — | — | 2022-08-10 | — | Active |
| 53746-0734-90 You're viewing this Main listing | 90 TABLET in 1 BOTTLE | $0.7978 / ea | $71.80 | 2022-08-10 | — | Active |
You're viewing the largest of 2 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 53746-0734-30?
What NDC number is used to bill for this package of Felbamate 400 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Felbamate 400 mg 51672-4185-01 | Sun | 100 tablets | $0.798 | AB | Availability likely | — |
| Felbamate 400 mgthis 53746-0734-90 | Amneal | 90 tablets | $0.798 | AB | Availability likely | — |
| Felbamate 400 mg 62559-0730-01 | ANI | 100 tablets | $0.798 | AB | Availability likely | — |
| Felbamate 400 mg 72578-0056-01 | Viona | 100 tablets | $0.798 | AB | Availability likely | — |
| Felbamate 400 mg 65162-0734-03 | Amneal | 30 tablets | $1.001 | AB | FDA listed | +26% |
| Felbatol 400 mg 00037-0430-01 | Viatris | 100 tablets | $14.685 | AB | Availability likely | +1741% |
| Felbamate 400 mg 63629-1937-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Felbamate 400 mg 70771-1077-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Felbamate 400 mg 72162-1770-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Amneal Pharmaceuticals of New York LLC labeler code 53746
- Flecainide Acetate 100 mg Tablet NDC 53746-642-01
- Flecainide Acetate 150 mg Tablet NDC 53746-643-01
- Acebutolol Hydrochloride 200 mg Capsule NDC 53746-669-01
- Acebutolol Hydrochloride 400 mg Capsule NDC 53746-670-01
- Guanfacine Hydrochloride 1 mg Tablet NDC 53746-711-01
- Guanfacine Hydrochloride 2 mg Tablet NDC 53746-713-01
- Felbamate 600 mg Tablet NDC 53746-735-18
- Promethazine Hydrochloride 12.5 mg Tablet NDC 53746-745-01
- Benazepril Hydrochloride 5 mg Tablet NDC 53746-751-01
- Benazepril Hydrochloride 10 mg Tablet NDC 53746-752-01
- Benazepril Hydrochloride 20 mg Tablet NDC 53746-753-01
- Benazepril Hydrochloride 40 mg Tablet NDC 53746-754-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING 1. APLASTIC ANEMIA THE USE OF FELBAMATE IS ASSOCIATED WITH A MARKED INCREASE IN THE INCIDENCE OF APLASTIC ANEMIA. ACCORDINGLY, FELBAMATE SHOULD ONLY BE USED IN PATIENTS WHOSE EPILEPSY IS SO SEVERE THAT THE RISK OF APLASTIC ANEMIA IS DEEMED ACCEPTABLE IN LIGHT OF THE BENEFITS CONFERRED BY ITS USE (SEE INDICATIONS ).
ORDINARILY, A PATIENT SHOULD NOT BE PLACED ON AND/OR CONTINUED ON FELBAMATE WITHOUT CONSIDERATION OF APPROPRIATE EXPERT HEMATOLOGIC CONSULTATION. AMONG FELBAMATE TREATED PATIENTS, APLASTIC ANEMIA (PANCYTOPENIA IN THE PRESENCE OF A BONE MARROW LARGELY DEPLETED OF HEMATOPOIETIC PRECURSORS) OCCURS AT AN INCIDENCE THAT MAY BE MORE THAN A 100 FOLD GREATER THAN THAT SEEN IN THE UNTREATED POPULATION (I.E., 2 TO 5 PER MILLION PERSONS PER YEAR). THE RISK OF DEATH IN PATIENTS WITH APLASTIC ANEMIA GENERALLY VARIES AS A FUNCTION OF ITS SEVERITY AND ETIOLOGY; CURRENT ESTIMATES OF THE OVERALL CASE FATALITY RATE ARE IN THE RANGE OF 20% TO 30%, BUT RATES AS HIGH AS 70% HAVE BEEN REPORTED IN THE PAST.
THERE ARE TOO FEW FELBAMATE ASSOCIATED CASES, AND TOO LITTLE KNOWN ABOUT THEM TO PROVIDE A RELIABLE ESTIMATE OF THE SYNDROME'S INCIDENCE OR ITS CASE FATALITY RATE OR TO IDENTIFY THE FACTORS, IF ANY, THAT MIGHT CONCEIVABLY BE USED TO PREDICT WHO IS AT GREATER OR LESSER RISK. IN MANAGING PATIENTS ON FELBAMATE, IT SHOULD BE BORNE IN MIND THAT THE CLINICAL MANIFESTATION OF APLASTIC ANEMIA MAY NOT BE SEEN UNTIL AFTER A PATIENT HAS BEEN ON FELBAMATE FOR SEVERAL MONTHS (E.G., ONSET OF APLASTIC ANEMIA AMONG FELBAMATE EXPOSED PATIENTS FOR WHOM DATA ARE AVAILABLE HAS RANGED FROM 5 TO 30 WEEKS).
HOWEVER, THE INJURY TO BONE MARROW STEM CELLS THAT IS HELD TO BE ULTIMATELY RESPONSIBLE FOR THE ANEMIA MAY OCCUR WEEKS TO MONTHS EARLIER. ACCORDINGLY, PATIENTS WHO ARE DISCONTINUED FROM FELBAMATE REMAIN AT RISK FOR DEVELOPING ANEMIA FOR A VARIABLE, AND UNKNOWN, PERIOD AFTERWARDS. IT IS NOT KNOWN WHETHER OR NOT THE RISK OF DEVELOPING APLASTIC ANEMIA CHANGES WITH DURATION OF EXPOSURE.
CONSEQUENTLY, IT IS NOT SAFE TO ASSUME THAT A PATIENT WHO HAS BEEN ON FELBAMATEWITHOUT SIGNS OF HEMATOLOGIC ABNORMALITY FOR LONG PERIODS OF TIME IS WITHOUT RISK. IT IS NOT KNOWN WHETHER OR NOT THE DOSE OF FELBAMATE AFFECTS THE INCIDENCE OF APLASTIC ANEMIA. IT IS NOT KNOWN WHETHER OR NOT CONCOMITANT USE OF ANTIEPILEPTIC DRUGS AND/OR OTHER DRUGS AFFECTS THE INCIDENCE OF APLASTIC ANEMIA.
APLASTIC ANEMIA TYPICALLY DEVELOPS WITHOUT PREMONITORY CLINICAL OR LABORATORY SIGNS, THE FULL BLOWN SYNDROME PRESENTING WITH SIGNS OF INFECTION, BLEEDING, OR ANEMIA. ACCORDINGLY, ROUTINE BLOOD TESTING CANNOT BE RELIABLY USED TO REDUCE THE INCIDENCE OF APLASTIC ANEMIA, BUT, IT WILL, IN SOME CASES, ALLOW THE DETECTION OF THE HEMATOLOGIC CHANGES BEFORE THE SYNDROME DECLARES ITSELF CLINICALLY. FELBAMATE SHOULD BE DISCONTINUED IF ANY EVIDENCE OF BONE MARROW DEPRESSION OCCURS.
2. HEPATIC FAILURE EVALUATION OF POSTMARKETING EXPERIENCE SUGGESTS THAT ACUTE LIVER FAILURE IS ASSOCIATED WITH THE USE OF FELBAMATE. THE REPORTED RATE IN THE U.S.
HAS BEEN ABOUT 6 CASES OF LIVER FAILURE LEADING TO DEATH OR TRANSPLANT PER 75,000 PATIENT YEARS OF USE. THIS RATE IS AN UNDERESTIMATE BECAUSE OF UNDER REPORTING, AND THE TRUE RATE COULD BE CONSIDERABLY GREATER THAN THIS. FOR EXAMPLE, IF THE REPORTING RATE IS 10%, THE TRUE RATE WOULD BE ONE CASE PER 1,250 PATIENT YEARS OF USE.
OF THE CASES REPORTED, ABOUT 67% RESULTED IN DEATH OR LIVER TRANSPLANTATION, USUALLY WITHIN 5 WEEKS OF THE ONSET OF SIGNS AND SYMPTOMS OF LIVER FAILURE. THE EARLIEST ONSET OF SEVERE HEPATIC DYSFUNCTION FOLLOWED SUBSEQUENTLY BY LIVER FAILURE WAS 3 WEEKS AFTER INITIATION OF FELBAMATE. ALTHOUGH SOME REPORTS DESCRIBED DARK URINE AND NONSPECIFIC PRODROMAL SYMPTOMS (E.G., ANOREXIA, MALAISE AND GASTROINTESTINAL SYMPTOMS), IN OTHER REPORTS IT WAS NOT CLEAR IF ANY PRODROMAL SYMPTOMS PRECEDED THE ONSET OF JAUNDICE.
IT IS NOT KNOWN WHETHER OR NOT THE RISK OF DEVELOPING HEPATIC FAILURE CHANGES WITH DURATION OF EXPOSURE. IT IS NOT KNOWN WHETHER OR NOT T… [Excerpted — this section continues on DailyMed.]
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Felbamate tablets, USP are not indicated as a first line antiepileptic treatment (see WARNINGS ). Felbamate tablets, USP are recommended for use only in those patients who respond inadequately to alternative treatments and whose epilepsy is so severe that a substantial risk of aplastic anemia and/or liver failure is deemed acceptable in light of the benefits conferred by its use. If these criteria are met and the patient has been fully advised of the risk, and has provided written acknowledgement, felbamate tablets, USP can be considered for either monotherapy or adjunctive therapy in the treatment of partial seizures, with and without generalization, in adults with epilepsy and as adjunctive therapy in the treatment of partial and generalized seizures associated with Lennox-Gastaut syndrome in children.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Felbamate tablets have been studied as monotherapy and adjunctive therapy in adults and as adjunctive therapy in children with seizures associated with Lennox-Gastaut syndrome. As felbamate tablets are added to or substituted for existing AEDs, it is strongly recommended to reduce the dosage of those AEDs in the range of 20% to 33% to minimize side effects (see Drug Interactions subsection). Dosage Adjustment in the Renally Impaired: Felbamate should be used with caution in patients with renal dysfunction.
In the renally impaired, starting and maintenance doses should be reduced by one-half (See CLINICAL PHARMACOLOGY / Pharmacokinetics and PRECAUTIONS ). Adjunctive therapy with medications which affect felbamate plasma concentrations, especially AEDs, may warrant further reductions in felbamate daily doses in patients with renal dysfunction. Adults (14 years of age and over) The majority of patients received 3,600 mg/day in clinical trials evaluating its use as both monotherapy and adjunctive therapy.
Monotherapy: (Initial therapy) Felbamate tablets have not been systematically evaluated as initial monotherapy. Initiate felbamate tablets at 1,200 mg/day in divided doses three or four times daily. The prescriber is advised to titrate previously untreated patients under close clinical supervision, increasing the dosage in 600 mg increments every 2 weeks to 2,400 mg/day based on clinical response and thereafter to 3,600 mg/day if clinically indicated.
Conversion to Monotherapy: Initiate felbamate tablets at 1,200 mg/day in divided doses three or four times daily. Reduce the dosage of concomitant AEDs by one-third at initiation of felbamate tablets therapy. At week 2, increase the felbamate tablets dosage to 2,400 mg/day while reducing the dosage of other AEDs up to an additional one-third of their original dosage.
At week 3, increase the felbamate tablets dosage up to 3,600 mg/day and continue to reduce the dosage of other AEDs as clinically indicated. Adjunctive Therapy: Felbamate tablets should be added at 1,200 mg/day in divided doses three or four times daily while reducing present AEDs by 20% in order to control plasma concentrations of concurrent phenytoin, valproic acid, phenobarbital and carbamazepine and its metabolites. Further reductions of the concomitant AEDs dosage may be necessary to minimize side effects due to drug interactions.
Increase the dosage of felbamate by 1,200 mg/day increments at weekly intervals to 3,600 mg/day. Most side effects seen during felbamate tablets adjunctive therapy resolve as the dosage of concomitant AEDs is decreased. Table 6: Dosage Table (adults) Dosage reduction of concomitant AEDs WEEK 1 REDUCE original dose by 20% to 33%* WEEK 2 REDUCE original dose by up to an additional 1/3* WEEK 3 REDUCE as clinically indicated Felbamate Tablets Dosage 1,200 mg/day Initial dose 2,400 mg/day Therapeutic dosage range 3,600 mg/day Therapeutic dosage range *See Adjunctive and Conversion to Monotherapy sections.
While the above felbamate tablets conversion guidelines may result in a felbamate tablets 3,600 mg/day dose within 3 weeks, in some patients titration to a 3,600 mg/day felbamate tablets dose has been achieved in as little as 3 days with appropriate adjustment of other AEDs. Children with Lennox-Gastaut Syndrome (Ages 2 to 14 years) Adjunctive Therapy: Felbamate tablets should be added at 15 mg/kg/day in divided doses three or four times daily while reducing present AEDs by 20% in order to control plasma levels of concurrent phenytoin, valproic acid, phenobarbital and carbamazepine, and its metabolites.
Further reductions of the concomitant AEDs dosage may be necessary to minimize side effects due to drug interactions. Increase the dosage of felbamate tablets by 15 mg/kg/day increments at weekly intervals to 45 mg/kg/day. Most side effects seen during felbamate tablets adjunctive therapy resolve as the dosage of concomitant AEDs is decreased.
⛔ Contraindications ▾
CONTRAINDICATIONS Felbamate tablets are contraindicated in patients with known hypersensitivity to felbamate, its ingredients, or known sensitivity to other carbamates. It should not be used in patients with a history of any blood dyscrasia or hepatic dysfunction.
⚠️ Warnings ▾
WARNINGS See Boxed Warning regarding aplastic anemia and hepatic failure. Antiepileptic drugs should not be suddenly discontinued because of the possibility of increasing seizure frequency. Suicidal Behavior and Ideation Antiepileptic drugs (AEDs) including felbamate, increase the risk of suicidal thoughts or behavior in patients taking these drugs for any indication.
Patients treated with any AED for any indication should be monitored for the emergence or worsening of depression, suicidal thoughts or behavior, and/or any unusual changes in mood or behavior. Pooled analyses of 199 placebo-controlled clinical trials (mono- and adjunctive therapy) of 11 different AEDs showed that patients randomized to one of the AEDs had approximately twice the risk (adjusted Relative Risk 1.8, 95% CI:1.2, 2.7) of suicidal thinking or behavior compared to patients randomized to placebo. In these trials, which had a median treatment duration of 12 weeks, the estimated incidence rate of suicidal behavior or ideation among 27,863 AED-treated patients was 0.43%, compared to 0.24% among 16,029 placebo-treated patients, representing an increase of approximately one case of suicidal thinking or behavior for every 530 patients treated.
There were four suicides in drug-treated patients in the trials and none in placebo-treated patients, but the number is too small to allow any conclusion about drug effect on suicide. The increased risk of suicidal thoughts or behavior with AEDs was observed as early as one week after starting drug treatment with AEDs and persisted for the duration of treatment assessed. Because most trials included in the analysis did not extend beyond 24 weeks, the risk of suicidal thoughts or behavior beyond 24 weeks could not be assessed.
The risk of suicidal thoughts or behavior was generally consistent among drugs in the data analyzed. The finding of increased risk with AEDs of varying mechanisms of action and across a range of indications suggests that the risk applies to all AEDs used for any indication. The risk did not vary substantially by age (5 to 100 years) in the clinical trials analyzed.
Table 1 shows absolute and relative risk by indication for all evaluated AEDs. Table 1: Risk by Indication for Antiepileptic Drugs in the Pooled Analysis Indication Placebo Patients with Events Per 1000 Patients Drug Patients with Events Per 1000 Patients Relative Risk: Incidence of Events in Drug Patients/Incidence in Placebo Patients Risk Difference: Additional Drug Patients with Events Per 1000 Patients Epilepsy 1 3.4 3.5
2.4Psychiatric 5.7 8.5 1.5
2.9Other 1 1.8 1.9
0.9Total 2.4 4.3 1.8
1.9The relative risk for suicidal thoughts or behavior was higher in clinical trials for epilepsy than in clinical trials for psychiatric or other conditions, but the absolute risk differences were similar for the epilepsy and psychiatric indications. Anyone considering prescribing felbamate or any other AED must balance the risk of suicidal thoughts or behavior with the risk of untreated illness. Epilepsy and many other illnesses for which AEDs are prescribed are themselves associated with morbidity and mortality and an increased risk of suicidal thoughts and behavior.
Should suicidal thoughts and behavior emerge during treatment, the prescriber needs to consider whether the emergence of these symptoms in any given patient may be related to the illness being treated. Patients, their caregivers, and families should be informed that AEDs increase the risk of suicidal thoughts and behavior and should be advised of the need to be alert for the emergence or worsening of the signs and symptoms of depression, any unusual changes in mood or behavior, or the emergence of suicidal thoughts, behavior, or thoughts about self-harm.
Behaviors of concern should be reported immediately to healthcare providers.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The most common adverse reactions seen in association with felbamate in adults during monotherapy are anorexia, vomiting, insomnia, nausea and headache. The most common adverse reactions seen in association with felbamate in adults during adjunctive therapy are anorexia, vomiting, insomnia, nausea, dizziness, somnolence and headache. The most common adverse reactions seen in association with felbamate in children during adjunctive therapy are anorexia, vomiting, insomnia, headache and somnolence.
The dropout rate because of adverse experiences or intercurrent illnesses among adult felbamate patients was 12 percent (120/977). The dropout rate because of adverse experiences or intercurrent illnesses among pediatric felbamate patients was six percent (22/357). In adults, the body systems associated with causing these withdrawals in order of frequency were: digestive (4.3%), psychological (2.2%), whole body (1.7%), neurological (1.5%) and dermatological (1.5%).
In children, the body systems associated with causing these withdrawals in order of frequency were: digestive (1.7%), neurological (1.4%), dermatological (1.4%), psychological (1.1%) and whole body (1%). In adults, specific events with an incidence of 1% or greater associated with causing these withdrawals, in order of frequency were: anorexia (1.6%), nausea (1.4%), rash (1.2%) and weight decrease (1.1%). In children, specific events with an incidence of 1% or greater associated with causing these withdrawals, in order of frequency was rash (1.1%).
Incidence in Clinical Trials: The prescriber should be aware that the figures cited in the following table cannot be used to predict the incidence of side effects in the course of usual medical practice where patient characteristics and other factors differ from those which prevailed in the clinical trials. Similarly, the cited frequencies cannot be compared with figures obtained from other clinical investigations involving different investigators, treatments, and uses including the use of felbamate as adjunctive therapy where the incidence of adverse events may be higher due to drug interactions.
The cited figures, however, do provide the prescribing physician with some basis for estimating the relative contribution of drug and nondrug factors to the side effect incidence rate in the population studied. Adults Incidence in Controlled Clinical Trials--Monotherapy Studies in Adults: The table that follows enumerates adverse events that occurred at an incidence of 2% or more among 58 adult patients who received felbamate monotherapy at dosages of 3,600 mg/day in double-blind controlled trials. Table 3 presents reported adverse events that were classified using standard WHO-based dictionary terminology.
Table 3: Adults Treatment-Emergent Adverse Event Incidence in Controlled Monotherapy Trials Felbamate* (N=58) Low Dose Valproate** (N=50) Body System Event % % Body as a Whole Fatigue Weight Decrease Face Edema 6.9 3.4 3.4 4 0 0 Central Nervous System Insomnia Headache Anxiety 8.6 6.9 5.2 4 18 2 Dermatological Acne Rash 3.4 3.4 0 0 Digestive Dyspepsia Vomiting Constipation Diarrhea SGPT Increased 8.6 8.6 6.9 5.2 5.2 2 2 2 0 2 Metabolic/Nutritional Hypophosphatemia 3.4 0 Respiratory Upper Respiratory Tract Infection Rhinitis 8.6 6.9 4 0 Special Senses Diplopia Otitis Media 3.4 3.4 4 0 Urogenital Intramenstrual Bleeding Urinary Tract Infection 3.4 3.4 0 2 *3,600 mg/day, ** 15 mg/kg/day Incidence in Controlled Add-On Clinical Studies in Adults: Table 4 enumerates adverse events that occurred at an incidence of 2% or more among 114 adult patients who received felbamate adjunctive therapy in add-on controlled trials at dosages up to 3,600 mg/day.
Reported adverse events were classified using standard WHO-based dictionary terminology. Many adverse experiences that occurred during adjunctive therapy may be a result of drug interactions. Adverse experiences during adjunctive therapy typically resolved with conversion to mon… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
OVERDOSAGE Four subjects inadvertently received felbamate as adjunctive therapy in dosages ranging from 5,400 mg/day to 7,200 mg/day for durations between 6 and 51 days. One subject who received 5,400 mg/day as monotherapy for 1 week reported no adverse experiences. Another subject attempted suicide by ingesting 12,000 mg of felbamate in a 12-hour period.
The only adverse experiences reported were mild gastric distress and a resting heart rate of 100 bpm. No serious adverse reactions have been reported. General supportive measures should be employed if overdosage occurs.
It is not known if felbamate is dialyzable.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action: The mechanism by which felbamate exerts its anticonvulsant activity is unknown, but in animal test systems designed to detect anticonvulsant activity, felbamate has properties in common with other marketed anticonvulsants. Felbamate is effective in mice and rats in the maximal electroshock test, the subcutaneous pentylenetetrazol seizure test, and the subcutaneous picrotoxin seizure test. Felbamate also exhibits anticonvulsant activity against seizures induced by intracerebroventricular administration of glutamate in rats and N-methyl-D,L-aspartic acid in mice.
Protection against maximal electroshock-induced seizures suggests that felbamate may reduce seizure spread, an effect possibly predictive of efficacy in generalized tonic-clonic or partial seizures. Protection against pentylenetetrazol-induced seizures suggests that felbamate may increase seizure threshold, an effect considered to be predictive of potential efficacy in absence seizures. Receptor-binding studies in vitro indicate that felbamate has weak inhibitory effects on GABA-receptor binding, benzodiazepine receptor binding, and is devoid of activity at the MK-801 receptor binding site of the NMDA receptor-ionophore complex.
However, felbamate does interact as an antagonist at the strychnine-insensitive glycine recognition site of the NMDA receptor-ionophore complex. Felbamate is not effective in protecting chick embryo retina tissue against the neurotoxic effects of the excitatory amino acid agonists NMDA, kainate, or quisqualate in vitro. The monocarbamate, p-hydroxy, and 2-hydroxy metabolites were inactive in the maximal electroshock-induced seizure test in mice.
The monocarbamate and p-hydroxy metabolites had only weak (0.2 to 0.6) activity compared with felbamate in the subcutaneous pentylenetetrazol seizure test. These metabolites did not contribute significantly to the anticonvulsant action of felbamate. Pharmacokinetics: The numbers in the pharmacokinetic section are mean ± standard deviation.
Felbamate is well-absorbed after oral administration. Over 90% of the radioactivity after a dose of 1,000 mg 14 C felbamate was found in the urine. Absolute bioavailability (oral vs. parenteral) has not been measured.
The tablet was shown to be bioequivalent to the capsule used in clinical trials, and pharmacokinetic parameters of the tablet and suspension are similar. There was no effect of food on absorption of the tablet. Following oral administration, felbamate is the predominant plasma species (about 90% of plasma radioactivity).
About 40% to 50% of absorbed dose appears unchanged in urine, and an additional 40% is present as unidentified metabolites and conjugates. About 15% is present as parahydroxyfelbamate, 2-hydroxyfelbamate, and felbamate monocarbamate, none of which have significant anticonvulsant activity. Binding of felbamate to human plasma protein was independent of felbamate concentrations between 10 micrograms/mL and 310 micrograms/mL.
Binding ranged from 22% to 25%, mostly to albumin, and was dependent on the albumin concentration. Felbamate is excreted with a terminal half-life of 20 to 23 hours, which is unaltered after multiple doses. Clearance after a single 1,200 mg dose is 26 ± 3 mL/hr/kg, and after multiple daily doses of 3,600 mg is 30 ± 8 mL/hr/kg.
The apparent volume of distribution was 756 ± 82 mL/kg after a 1,200 mg dose. Felbamate C max and AUC are proportionate to dose after single and multiple doses over a range of 100 mg to 800 mg single doses and 1,200 mg to 3,600 mg daily doses. C min (trough) blood levels are also dose proportional.
Multiple daily doses of 1,200 mg, 2,400 mg and 3,600 mg gave C min values of 30 ± 5, 55 ± 8 and 83 ± 21 micrograms/mL (N=10 patients). Linear and dose proportional pharmacokinetics were also observed at doses above 3,600 mg/day up to the maximum dose studied of 6,000 mg/day. Felbamate gave dose proportional steady-state peak plasma concentrations in children… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Felbamate Tablets USP, 400 mg , are yellow, oval shaped, biconvex tablets, with bisect on one side and “AN 734” on the other side. They are available as follows: Bottles of 30: NDC 53746-734-30 Bottles of 90: NDC 53746-734-90 Felbamate Tablets USP, 600 mg , are peach, oval shaped, biconvex tablets, with a bisect on one side and “AN 735” on the other side. They are available as follows: Bottles of 30: NDC 53746-735-30 Bottles of 90: NDC 53746-735-90 Bottles of 180: NDC 53746-735-18 Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
Dispense in tight container. To report SUSPECTED ADVERSE REACTIONS, contact Amneal Pharmaceuticals at 1-877-835-5472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. Manufactured by: Amneal Pharmaceuticals Pvt.
Ltd. Oral Solid Dosage Unit Ahmedabad 382213, INDIA Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev. 10-2024-01
📋 Description ▾
DESCRIPTION Felbamate, USP is an antiepileptic available as 400 mg and 600 mg tablets for oral administration. Its chemical name is 2-phenyl-1,3-propanediol dicarbamate. Felbamate, USP is a white to off-white crystalline powder, with a characteristic odor.
It is freely soluble in dimethyl sulfoxide and dimethyl formamide, sparingly soluble in acetone, chloroform methanol and in water, slightly soluble in ethanol, very slightly soluble dichloromethane. The molecular weight is 238.24 g/mol; felbamate's molecular formula is C 11 H 14 N 2 O 4 ; its structural formula is: The inactive ingredients for felbamate tablets, USP 400 mg and 600 mg are croscarmellose sodium, FD&C Yellow No. 6, D&C Yellow No.
10 and FD&C Red No. 40 (600 mg tablets only), lactose monohydrate, magnesium stearate, microcrystalline cellulose and pregelatinized starch. 1
💬 Medication Guide ▾
Medication Guide Felbamate (fel bam’ ate) Tablets, USP Read this Medication Guide before you start taking felbamate tablets and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or treatment.
What is the most important information I should know about felbamate tablets? Do not stop taking felbamate tablets without first talking to your healthcare provider. Stopping felbamate tablets suddenly can cause serious problems.
Felbamate tablets can cause serious side effects, including: 1. Felbamate tablets may cause serious blood problems that may be life-threatening. Call your healthcare provider right away if you have any of the following symptoms: Fever, sore throat or other infections that come and go or do not go away Frequent infections or an infection that does not go away Easy bruising Red or purple spots on your body Bleeding gums or nose bleeds Severe fatigue or weakness 2.
Liver problems that may be life-threatening. Call your healthcare provider right away if you have any of these symptoms: yellowing of your skin or the whites of your eyes (jaundice) dark urine nausea or vomiting loss of appetite pain on the right side of your stomach (abdomen) 3. Like other antiepileptic drugs, felbamate tablets may cause suicidal thoughts or actions in a very small number of people, about 1 in 500.
Call your healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood How can I watch for early symptoms of suicidal thoughts and actions?
Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you are worried about symptoms.
Do not stop felbamate tablets without first talking to a healthcare provider. Stopping felbamate tablets suddenly can cause serious problems. You should talk to your health care provider before stopping.
Stopping a seizure medicine suddenly in a patient who has epilepsy can cause seizures. Suicidal thoughts or actions can be caused by things other than medicines. If you have suicidal thoughts or actions, your healthcare provider may check for other causes.
What is felbamate tablets? Felbamate tablets is a prescription medicine used when other treatments have failed in: adults alone or with other medicines to treat: partial seizures with and without generalization children with other medicines to treat: seizures associated with Lennox-Gastaut syndrome Who should not take felbamate tablets? Do not take felbamate tablets if you: are allergic to felbamate, carbamates or any of the ingredients in felbamate tablets.
See the end of this Medication Guide for a complete list of ingredients in felbamate tablets. have or have had blood problems have or have had liver problems What should I tell my healthcare provider before taking felbamate tablets? Before you take felbamate tablets, tell your healthcare provider if you: have kidney problems have or have had depression, mood problems, or suicidal thoughts or behavior have any other medical conditions are pregnant or plan to become pregnant. It is not known if felbamate tablets can harm your unborn baby.
Tell your healthcare provider right away if you become pregnant while taking felbamate tablets. You and your healthcare provider will decide if you should take felbamate tablets while you are pregnant. If you become pregnant while taking felbamate tablets, talk to your heal… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS Dosage Adjustment in the Renally Impaired: A study in otherwise healthy individuals with renal dysfunction indicated that prolonged half-life and reduced clearance of felbamate are associated with diminishing renal function. Felbamate should be used with caution in patients with renal dysfunction (see DOSAGE AND ADMINISTRATION ). Information for Patients: Patients should be informed that the use of felbamate is associated with aplastic anemia and hepatic failure, potentially fatal conditions acutely or over a long term.
The physician should obtain written acknowledgement prior to initiation of felbamate therapy (see PATIENT/PHYSICIAN ACKNOWLEDGEMENT FORM section). Patients should be instructed to read the Medication Guide supplied as required by law when felbamate tablets are dispensed. The complete text of the Medication Guide is reprinted at the end of this document.
Aplastic anemia in the general population is relatively rare. The absolute risk for the individual patient is not known with any degree of reliability, but patients on felbamate may be at more than a 100 fold greater risk for developing the syndrome than the general population. The long-term outlook for patients with aplastic anemia is variable.
Although many patients are apparently cured, others require repeated transfusions and other treatments for relapses, and some, although surviving for years, ultimately develop serious complications that sometimes prove fatal (e.g., leukemia). At present there is no way to predict who is likely to get aplastic anemia, nor is there a documented effective means to monitor the patient so as to avoid and/or reduce the risk. Patients with a history of any blood dyscrasia should not receive felbamate.
Patients should be advised to be alert for signs of infection, bleeding, easy bruising, or signs of anemia (fatigue, weakness, lassitude, etc.) and should be advised to report to the physician immediately if any such signs or symptoms appear. Hepatic failure in the general population is relatively rare. The absolute risk for an individual patient is not known with any degree of reliability but patients on felbamate are at a greater risk for developing hepatic failure than the general population.
At present, there is no way to predict who is likely to develop hepatic failure, however, patients with a history of hepatic dysfunction should not be started on felbamate. Patients should be advised to follow their physician's directives for liver function testing both before starting felbamate and at frequent intervals while taking felbamate. Patients should be advised to be alert for signs of liver dysfunction (jaundice, anorexia, gastrointestinal complaints, malaise, etc.) and to report them to their doctor immediately if they should occur.
Laboratory Tests: Full hematologic evaluations should be performed before felbamate therapy, frequently during therapy, and for a significant period of time after discontinuation of felbamate therapy. While it might appear prudent to perform frequent CBCs in patients continuing on felbamate, there is no evidence that such monitoring will allow early detection of marrow suppression before aplastic anemia occurs. (see Boxed Warnings ).
Complete pre-treatment blood counts, including platelets and reticulocytes should be obtained as a baseline. If any hematologic abnormalities are detected during the course of treatment, immediate consultation with a hematologist is advised. Felbamate should be discontinued if any evidence of bone marrow depression occurs.
See Box Warnings for recommended monitoring of serum transaminases. If significant, confirmed liver abnormalities are detected during the course of felbamate treatment, felbamate should be discontinued immediately with continued liver function monitoring until values return to normal. (see PATIENT/PHYSICIAN ACKNOWLEDGEMENT FORM ).
Suicidal Thinking and Behavior - Patients, their caregivers, and families should be counseled that AEDs, inclu… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
DRUG ABUSE AND DEPENDENCE Abuse: Abuse potential was not evaluated in human studies. Dependence: Rats administered felbamate orally at doses 8.3 times the recommended human dose 6 days each week for 5 consecutive weeks demonstrated no signs of physical dependence as measured by weight loss following drug withdrawal on day 7 of each week.
📄 Package Label / Principal Display Panel ▾
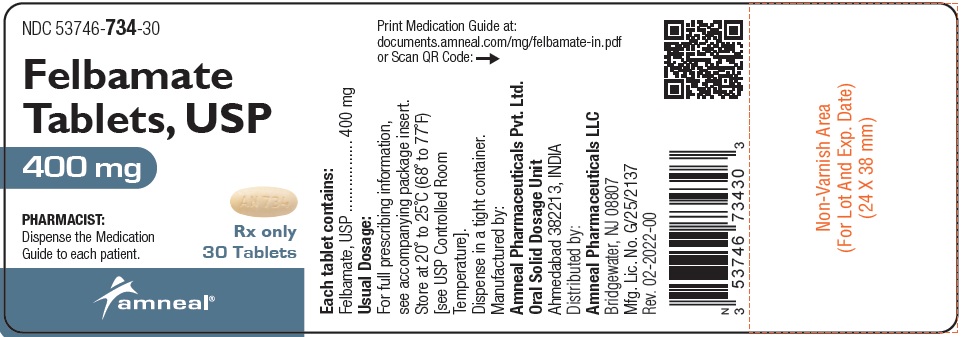
PRINCIPAL DISPLAY PANEL NDC 53746-734-30 Felbamate Tablets USP, 400 mg Rx only 30 Tablets Amneal Pharmaceuticals LLC NDC 53746-735-30 Felbamate Tablets USP, 600 mg Rx only 30 Tablets Amneal Pharmaceuticals LLC 1 1