
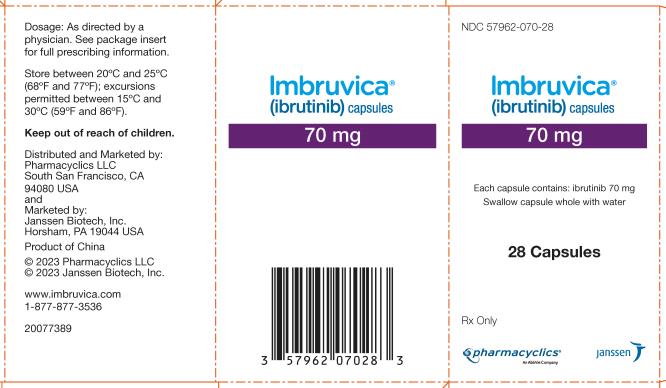
Imbruvica Ibrutinib 70 mg Capsule, 28-count — NDC 57962-070-28 (Billing 57962-0070-28)
This is a package of 28 capsules of Imbruvica Ibrutinib 70 mg Capsule from Pharmacyclics LLC, marketed since Dec 2017 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 57962-070-28 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 57962 labeler · 070 product · 28 package
- Package marketed since
- Dec 20, 2017
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 28 EA per package
- Barcode (UPC-A, from the NDC)
- 3 5796207028 3
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 078192
- GCN: 44475
- GPI-14 (Medi-Span): 21532133000110
- HICL (First Databank): 040745
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 1442986
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Ibrutinib is used to treat adults with chronic lymphocytic leukemia (CLL; a type of cancer that begins in the white blood cells) and small lymphocytic lymphoma (SLL; a type of cancer that begins mostly in the lymph nodes). Ibrutinib is also used to treat adults with Waldenstrom's macroglobulinemia (WM; a slow-growing cancer that begins in certain white blood cells in your bone marrow). It is also used to treat adults and children 1 year of age with chronic graft vs host disease (cGVHD; a complication of hematopoietic stem-cell transplant [HSCT; a procedure that replaces diseased bone marrow wi...
Read the full MedlinePlus article ↗- It treats certain blood cancers in adults: CLL/SLL (including with 17p deletion) and Waldenström’s macroglobulinemia. Imbruvica is also used for chronic graft versus host disease i...
- Take Imbruvica by mouth once a day at about the same time. Swallow tablets or capsules whole with a glass of water, and don’t crush, chew, cut or open them. If you miss a dose, tak...
- Common ones are diarrhea, tiredness, muscle and bone pain, rash, nausea and easy bruising. Blood counts can also drop, so you’ll have regular blood tests. Call us about bleeding, f...
- Check with me first. Some antifungals and antibiotics raise ibrutinib levels, and some drugs like rifampin lower them. Blood thinners raise the bleeding risk. Avoid grapefruit and...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ibrutinib — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $354.00 | $9,912.07 / 28 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 57962-0070-28 You're viewing this Main listing | 28 CAPSULE in 1 BOTTLE, PLASTIC | 2017-12-20 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Imbruvica 70 mgthis 57962-0070-28 | Pharmacyclics | 28 capsules | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9125889 ↗ | Method of use | U-1745 | Jun 3, 2031 |
| US 8999999 ↗ | Method of use | U-1684 | Jun 3, 2031 |
| US 8476284 ↗ | Method of use | U-1650 | Dec 28, 2026 |
| US 8497277 ↗ | Method of use | U-1491 | Dec 28, 2026 |
| US 8497277 ↗ | Method of use | U-1946 | Dec 28, 2026 |
| US 8952015 ↗ | Method of use | U-1650 | Dec 28, 2026 |
| US 8952015 ↗ | Method of use | U-1491 | Dec 28, 2026 |
| US 9801881 ↗ | Method of use | U-1491 | Jun 3, 2031 |
| US 9795604 ↗ | Method of use | U-2150 | Oct 24, 2034 |
| US 10004746 ↗ | Method of use | U-2242 | Jun 3, 2031 |
| US 10004746 ↗ | Method of use | U-2241 | Jun 3, 2031 |
| US 10004746 ↗ | Method of use | U-2242 | Jun 3, 2031 |
| US 10004746 ↗ | Method of use | U-1946 | Jun 3, 2031 |
| US 10016435 ↗ | Method of use | U-1650 | Jun 3, 2031 |
| US 8563563 ↗ | Method of use | U-1946 | Apr 26, 2027 |
| US 8563563 ↗ | Method of use | U-2219 | Apr 26, 2027 |
| US 8563563 ↗ | Method of use | U-1946 | Apr 26, 2027 |
| US 8563563 ↗ | Method of use | U-1650 | Apr 26, 2027 |
| US 8952015 ↗ | Method of use | U-1650 | Dec 28, 2026 |
| US 8952015 ↗ | Method of use | U-1946 | Dec 28, 2026 |
| US 9801881 ↗ | Method of use | U-1491 | Jun 3, 2031 |
| US 8497277 ↗ | Method of use | U-1946 | Dec 28, 2026 |
| US 8497277 ↗ | Method of use | U-1491 | Dec 28, 2026 |
| US 8999999 ↗ | Method of use | U-2228 | Jun 3, 2031 |
| US 8999999 ↗ | Method of use | U-1491 | Jun 3, 2031 |
| US 9540382 ↗ | Method of use | U-1491 | Aug 18, 2033 |
| US 9540382 ↗ | Method of use | U-1946 | Aug 18, 2033 |
| US 8703780 ↗ | Method of use | U-1491 | Dec 28, 2026 |
| US 8476284 ↗ | Method of use | U-1946 | Dec 28, 2026 |
| US 9801883 ↗ | Method of use | U-2159 | Jun 3, 2031 |
| US 9125889 ↗ | Method of use | U-1650 | Jun 3, 2031 |
| US 9540382 ↗ | Method of use | U-1650 | Aug 18, 2033 |
| US 9540382 ↗ | Method of use | U-1946 | Aug 18, 2033 |
| US 9801883 ↗ | Method of use | U-2159 | Jun 3, 2031 |
| US 10004746 ↗ | Method of use | U-1946 | Jun 3, 2031 |
| US 10004746 ↗ | Method of use | U-1684 | Jun 3, 2031 |
| US 10004746 ↗ | Method of use | U-1684 | Jun 3, 2031 |
| US 10016435 ↗ | Method of use | U-1650 | Jun 3, 2031 |
| US 8999999 ↗ | Method of use | U-1683 | Jun 3, 2031 |
| US 8563563 ↗ | Method of use | U-2219 | Apr 26, 2027 |
| US 10463668 ↗ | Method of use | U-2654 | Oct 24, 2034 |
| US 10463668 ↗ | Method of use | U-2654 | Oct 24, 2034 |
| US 10478439 ↗ | Method of use | U-1684 | Jun 3, 2031 |
| US 10478439 ↗ | Method of use | U-1946 | Jun 3, 2031 |
| US 10478439 ↗ | Method of use | U-2665 | Jun 3, 2031 |
| US 10478439 ↗ | Method of use | U-1650 | Jun 3, 2031 |
| US 10478439 ↗ | Method of use | U-2241 | Jun 3, 2031 |
| US 10478439 ↗ | Method of use | U-2242 | Jun 3, 2031 |
| US 10478439 ↗ | Method of use | U-1650 | Jun 3, 2031 |
| US 10478439 ↗ | Method of use | U-2241 | Jun 3, 2031 |
| US 10478439 ↗ | Method of use | U-2665 | Jun 3, 2031 |
| US 10478439 ↗ | Method of use | U-1946 | Jun 3, 2031 |
| US 10478439 ↗ | Method of use | U-2242 | Jun 3, 2031 |
| US 10478439 ↗ | Method of use | U-1684 | Jun 3, 2031 |
| US 10004746 ↗ | Method of use | U-2241 | Jun 3, 2031 |
| US 8497277 ↗ | Method of use | U-1650 | Dec 28, 2026 |
| US 8999999 ↗ | Method of use | U-1946 | Jun 3, 2031 |
| US 9540382 ↗ | Method of use | U-1650 | Aug 18, 2033 |
| US 8563563 ↗ | Method of use | U-1650 | Apr 26, 2027 |
| US 8563563 ↗ | Method of use | U-1491 | Apr 26, 2027 |
| US 9540382 ↗ | Method of use | U-1684 | Aug 18, 2033 |
| US 11672803 ↗ | Method of use | U-1684 | Jun 3, 2031 |
| US 11672803 ↗ | Method of use | U-2242 | Jun 3, 2031 |
| US 11672803 ↗ | Method of use | U-2242 | Jun 3, 2031 |
| US 11672803 ↗ | Method of use | U-2241 | Jun 3, 2031 |
| US 11672803 ↗ | Method of use | U-2241 | Jun 3, 2031 |
| US 11672803 ↗ | Method of use | U-1946 | Jun 3, 2031 |
| US 11672803 ↗ | Method of use | U-1946 | Jun 3, 2031 |
| US 11672803 ↗ | Method of use | U-1684 | Jun 3, 2031 |
| US 8497277 ↗ | Method of use | U-2242 | Dec 28, 2026 |
| US 8497277 ↗ | Method of use | U-2241 | Dec 28, 2026 |
| US 8497277 ↗ | Method of use | U-2241 | Dec 28, 2026 |
| US 8497277 ↗ | Method of use | U-2242 | Dec 28, 2026 |
| US 10695350 ↗ | Method of use | U-2846 | Oct 24, 2034 |
| US 10695350 ↗ | Method of use | U-2846 | Oct 24, 2034 |
| US 8476284 ↗ | Method of use | U-1650 | Dec 28, 2026 |
| US 8952015 ↗ | Method of use | U-1491 | Dec 28, 2026 |
| US 8563563 ↗ | Method of use | U-1491 | Apr 26, 2027 |
| US 8952015 ↗ | Method of use | U-1946 | Dec 28, 2026 |
| US 8497277 ↗ | Method of use | U-3422 | Dec 28, 2026 |
| US 8497277 ↗ | Method of use | U-3422 | Dec 28, 2026 |
| US 10478439 ↗ | Method of use | U-3422 | Jun 3, 2031 |
| US 10478439 ↗ | Method of use | U-3422 | Jun 3, 2031 |
| US 10751342 ↗ | Method of use | U-2944 | Jun 3, 2031 |
| US 10751342 ↗ | Method of use | U-1946 | Jun 3, 2031 |
| US 10751342 ↗ | Method of use | U-1491 | Jun 3, 2031 |
| US 10751342 ↗ | Method of use | U-2943 | Jun 3, 2031 |
| US 10751342 ↗ | Method of use | U-1946 | Jun 3, 2031 |
| US 10751342 ↗ | Method of use | U-2944 | Jun 3, 2031 |
| US 10751342 ↗ | Method of use | U-1491 | Jun 3, 2031 |
| US 10751342 ↗ | Method of use | U-2943 | Jun 3, 2031 |
| US 9795604 ↗ | Method of use | U-3422 | Oct 24, 2034 |
| US 9795604 ↗ | Method of use | U-3422 | Oct 24, 2034 |
| US 9795604 ↗ | Method of use | U-2970 | Oct 24, 2034 |
| US 9795604 ↗ | Method of use | U-2969 | Oct 24, 2034 |
| US 9795604 ↗ | Method of use | U-2970 | Oct 24, 2034 |
| US 9795604 ↗ | Method of use | U-2969 | Oct 24, 2034 |
| US 8476284 ↗ | Method of use | U-1946 | Dec 28, 2026 |
| US 8497277 ↗ | Method of use | U-1650 | Dec 28, 2026 |
| US 8703780 ↗ | Method of use | U-1491 | Dec 28, 2026 |
| US 10961251 ↗ | Drug product | — | Jun 3, 2033 |
| US 9296753 ↗ | Drug substance | — | Oct 30, 2033 |
| US 8735403 ↗ | Drug substance | — | Dec 28, 2026 |
| US 8735403 ↗ | Drug substance | — | Dec 28, 2026 |
| US 10106548 ↗ | Drug substance | — | Jun 3, 2033 |
| US 10752634 ↗ | Drug product | — | Jun 3, 2033 |
| US 9713617 ↗ | Drug product | — | Jun 3, 2033 |
| US 7514444 ↗ | Drug substance | — | Dec 28, 2026 |
| US 8957079 ↗ | Drug substance | — | Dec 28, 2026 |
| US 10294231 ↗ | Drug product | — | Jun 3, 2033 |
| US 10294231 ↗ | Drug product | — | Jun 3, 2033 |
| US 9725455 ↗ | Drug substance | — | Jun 3, 2033 |
| US 10294232 ↗ | Drug product | — | Jun 3, 2033 |
| US 9713617 ↗ | Drug product | — | Jun 3, 2033 |
| US 8008309 ↗ | Drug substance | — | Nov 13, 2027 |
| US 9181257 ↗ | Drug substance | — | Dec 28, 2026 |
| US 9296753 ↗ | Drug substance | — | Oct 30, 2033 |
| US 10125140 ↗ | Drug substance | — | Jun 3, 2033 |
| US 10294232 ↗ | Drug product | — | Jun 3, 2033 |
| US 8008309 ↗ | Drug substance | — | Nov 13, 2027 |
| US 8957079 ↗ | Drug substance | — | Dec 28, 2026 |
| US 9181257 ↗ | Drug substance | — | Dec 28, 2026 |
| US 10125140 ↗ | Drug substance | — | Jun 3, 2033 |
| US 10961251 ↗ | Drug product | — | Jun 3, 2033 |
| US 7514444 ↗ | Drug substance | — | Dec 28, 2026 |
| US 8697711 ↗ | Drug substance | — | Dec 28, 2026 |
| US 8754091 ↗ | Drug product | — | Dec 28, 2026 |
| US 10106548 ↗ | Drug substance | — | Jun 3, 2033 |
| US 8754091 ↗ | Drug product | — | Dec 28, 2026 |
| US 8697711 ↗ | Drug substance | — | Dec 28, 2026 |
| US 9725455 ↗ | Drug substance | — | Jun 3, 2033 |
| US 8008309*PED ↗ | Drug product | — | May 13, 2028 |
| US 7514444*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8476284*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8497277*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8754091*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8697711*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8703780*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8735403*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 9125889*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 8957079*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 9181257*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 9296753*PED ↗ | Drug product | — | Apr 30, 2034 |
| US 9795604*PED ↗ | Drug product | — | Apr 24, 2035 |
| US 10004746*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 10004746*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 9801883*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 9801881*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 7514444*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8008309*PED ↗ | Drug product | — | May 13, 2028 |
| US 8476284*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8497277*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8703780*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8735403*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8697711*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8754091*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8952015*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8999999*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 8957079*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 9125889*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 9181257*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 9296753*PED ↗ | Drug product | — | Apr 30, 2034 |
| US 9540382*PED ↗ | Drug product | — | Feb 18, 2034 |
| US 9713617*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 9795604*PED ↗ | Drug product | — | Apr 24, 2035 |
| US 9801881*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 9725455*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 9801883*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 8563563*PED ↗ | Drug product | — | Oct 26, 2027 |
| US 8563563*PED ↗ | Drug product | — | Oct 26, 2027 |
| US 8952015*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 9540382*PED ↗ | Drug product | — | Feb 18, 2034 |
| US 10016435*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 10016435*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 10106548*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 10106548*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 9713617*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 9725455*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 8999999*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 10125140*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 10125140*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 10294232*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 10294231*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 10294231*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 10294232*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 10751342*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 10751342*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 10752634*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 10478439*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 10478439*PED ↗ | Drug product | — | Dec 3, 2031 |
| US 10961251*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 10961251*PED ↗ | Drug product | — | Dec 3, 2033 |
| US 10463668*PED ↗ | Drug product | — | Apr 24, 2035 |
| US 10463668*PED ↗ | Drug product | — | Apr 24, 2035 |
| US 10695350*PED ↗ | Drug product | — | Apr 24, 2035 |
| US 10695350*PED ↗ | Drug product | — | Apr 24, 2035 |
| Code | What it grants | Expires |
|---|---|---|
| NPP | New Patient Population | Aug 24, 2025 |
| ODE-405 | Orphan Drug Exclusivity (7-year) | Aug 24, 2029 |
| NPP | New Patient Population | Aug 24, 2025 |
| ODE-405 | Orphan Drug Exclusivity (7-year) | Aug 24, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Feb 24, 2030 |
| PED | Pediatric Exclusivity (+6 months) | Feb 24, 2030 |
| PED | Pediatric Exclusivity (+6 months) | Feb 24, 2026 |
| PED | Pediatric Exclusivity (+6 months) | Feb 24, 2026 |
Is there a generic version of IMBRUVICA 70 MG CAPSULE?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Pharmacyclics LLC labeler code 57962
- Imbruvica Ibrutinib 70 mg/mL Suspension NDC 57962-007-12
- Imbruvica Ibrutinib 140 mg Tablet, Film Coated NDC 57962-014-28
- Imbruvica Ibrutinib 140 mg Capsule NDC 57962-140-09
- Imbruvica Ibrutinib 280 mg Tablet, Film Coated NDC 57962-280-28
- Imbruvica Ibrutinib 420 mg Tablet, Film Coated NDC 57962-420-28
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE IMBRUVICA is a kinase inhibitor indicated for the treatment of: Adult patients with chronic lymphocytic leukemia (CLL)/Small lymphocytic lymphoma (SLL) ( 1.1 ). Adult patients with chronic lymphocytic leukemia (CLL)/Small lymphocytic lymphoma (SLL) with 17p deletion ( 1.2 ). Adult patients with Waldenström’s macroglobulinemia (WM) ( 1.3 ).
Adult and pediatric patients age 1 year and older with chronic graft versus host disease (cGVHD) after failure of one or more lines of systemic therapy ( 1.4 ).
1.1Chronic Lymphocytic Leukemia/Small Lymphocytic Lymphoma IMBRUVICA is indicated for the treatment of adult patients with chronic lymphocytic leukemia (CLL)/small lymphocytic lymphoma (SLL). 1. 2 Chronic Lymphocytic Leukemia/Small Lymphocytic Lymphoma with 17p deletion IMBRUVICA is indicated for the treatment of adult patients with chronic lymphocytic leukemia (CLL)/small lymphocytic lymphoma (SLL) with 17p deletion.
1. 3 Waldenström’s Macroglobulinemia IMBRUVICA is indicated for the treatment of adult patients with Waldenström’s macroglobulinemia (WM). 1.
4 Chronic Graft versus Host Disease IMBRUVICA is indicated for the treatment of adult and pediatric patients age 1 year and older with chronic graft-versus-host disease (cGVHD) after failure of one or more lines of systemic therapy.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION CLL/SLL and WM : 420 mg taken orally once daily ( 2.1 ). cGVHD : ◦ Patients 12 years and older: 420 mg taken orally once daily ( 2.1 ). ◦ Patients 1 to less than 12 years of age: 240 mg/m 2 taken orally once daily (up to a dose of 420 mg) ( 2.1 ). Tablets or capsules should be taken orally with a glass of water. Do not open, break, or chew the capsules.
Do not cut, crush, or chew the tablets. See full prescribing information for oral suspension administration instructions ( 2.1 ).
2.1Recommended Dosage Chronic Lymphocytic Leukemia/Small Lymphocytic Lymphoma and Waldenström’s Macroglobulinemia The recommended dosage of IMBRUVICA for CLL/SLL and WM is 420 mg orally once daily until disease progression or unacceptable toxicity. For CLL/SLL, IMBRUVICA can be administered as a single agent, in combination with rituximab or obinutuzumab, or in combination with bendamustine and rituximab (BR). For WM, IMBRUVICA can be administered as a single agent or in combination with rituximab.
When administering IMBRUVICA in combination with rituximab or obinutuzumab, consider administering IMBRUVICA prior to rituximab or obinutuzumab when given on the same day. Chronic Graft versus Host Disease The recommended dosage of IMBRUVICA for patients age 12 years and older with cGVHD is 420 mg orally once daily, and for patients 1 to less than 12 years of age with cGVHD is 240 mg/m 2 orally once daily (up to a dose of 420 mg), until cGVHD progression, recurrence of an underlying malignancy, or unacceptable toxicity.
When a patient no longer requires therapy for the treatment of cGVHD, IMBRUVICA should be discontinued considering the medical assessment of the individual patient. Table 1: Recommended dosage based on body surface area (BSA) for patients 1 to less than 12 years of age using either IMBRUVICA capsules/tablets or oral suspension Recommended dose to achieve 240 mg/m 2 BSA* (m 2 ) Range Dose (mg) of IMBRUVICA Capsules/Tablets to Administer Volume (mL) of IMBRUVICA Oral Suspension (70 mg/mL) to Administer > 0.3 to 0.4 - 1.2 mL > 0.4 to 0.5 - 1.5 mL > 0.5 to 0.6 - 1.9 mL > 0.6 to 0.7 - 2.2 mL > 0.7 to 0.8 210 mg 2.6 mL > 0.8 to 0.9 210 mg 2.9 mL > 0.9 to 1 210 mg 3.3 mL > 1 to 1.1 280 mg 3.6 mL > 1.1 to 1.2 280 mg 4 mL > 1.2 to 1.3 280 mg 4.3 mL > 1.3 to 1.4 350 mg 4.6 mL > 1.4 to 1.5 350 mg 5 mL > 1.5 to 1.6 350 mg 5.3 mL > 1.6 420 mg 6 mL *BSA = body surface area.
Administration Administer IMBRUVICA at approximately the same time each day. Swallow tablets or capsules whole with a glass of water. Do not open, break, or chew the capsules.
Do not cut, crush, or chew the tablets. Follow Instructions for Use for further administration details of IMBRUVICA oral suspension. If a dose of IMBRUVICA is not taken at the scheduled time, it can be taken as soon as possible on the same day with a return to the normal schedule the following day.
Do not take extra doses of IMBRUVICA to make up for the missed dose.
2.2Dosage Modifications for Adverse Reactions For adverse reactions listed in Table 2 , interrupt IMBRUVICA therapy. Once the adverse reaction has improved to Grade 1 or baseline (recovery), follow the recommended dosage modifications (see Table 2 ). Table 2: Recommended Dosage Modifications for Adverse Reactions Adverse Reaction a,b Occurrence Dose Modification for CLL/SLL, WM, and Patients 12 Years or older with cGVHD After Recovery Starting Dose = 420 mg Dose Modification for Patients 1 Year to less than 12 Years with cGVHD After Recovery Starting Dose = 240 mg/m 2 Grade 2 cardiac failure First Restart at 280 mg daily c Restart at 160 mg/m 2 daily c Second Restart at 140 mg daily c Restart at 80 mg/m 2 daily c Third Discontinue IMBRUVICA Discontinue IMBRUVICA Grade 3 cardiac arrhythmias First Restart at 280 mg daily c Restart at 160 mg/m 2 daily c Second Discontinue IMBRUVICA Discontinue IMBRUVICA Grade 3 or 4 cardiac failure Grade 4 cardiac arrhythmias First Discontinue IMBRUVICA Discontinue IMBRUVICA Other Grade 3 o… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules: Each 70 mg capsule is a yellow, opaque capsule marked with “ibr 70 mg” in black ink. Each 140 mg capsule is a white, opaque capsule marked with “ibr 140 mg” in black ink. Tablets: Each 140 mg tablet is a yellow green to green round tablet debossed with “ibr” on one side and “140” on the other side.
Each 280 mg tablet is a purple oblong tablet debossed with “ibr” on one side and “280” on the other side. Each 420 mg tablet is a yellow green to green oblong tablet debossed with “ibr” on one side and “420” on the other side. Oral Suspension: 70 mg/mL, white to off-white suspension.
Capsules: 70 mg and 140 mg ( 3 ) Tablets: 140 mg, 280 mg, and 420 mg ( 3 ) Oral suspension: 70 mg/mL ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hemorrhage : Monitor for bleeding and manage ( 5.1 ). Infections : Monitor patients for fever and infections, evaluate promptly, and treat ( 5.2 ). Cardiac Arrhythmias , Cardiac Failure , and Sudden Death : Monitor for symptoms of arrhythmias and cardiac failure and manage ( 5.3 ).
Hypertension : Monitor blood pressure and treat ( 5.4 ). Cytopenias : Check complete blood counts monthly ( 5.5 ). Second Primary Malignancies : Other malignancies have occurred in patients, including skin cancers, and other carcinomas ( 5.6 ).
Hepatotoxicity, Including Drug- Induced Liver Injury : Monitor hepatic function throughout treatment ( 5.7 ). Tumor Lysis Syndrome (TLS) : Assess baseline risk and take precautions. Monitor and treat for TLS ( 5.8 ).
Embryo-Fetal Toxicity : Can cause fetal harm. Advise females of reproductive potential of the potential risk to a fetus and to use effective contraception ( 5.9 , 8.1 , 8.3 ).
5.1Hemorrhage Fatal bleeding events have occurred in patients who received IMBRUVICA. Major hemorrhage (≥ Grade 3, serious, or any central nervous system events; e.g., intracranial hemorrhage [including subdural hematoma], gastrointestinal bleeding, hematuria, and post procedural hemorrhage) occurred in 4.2% of patients, with fatalities occurring in 0.4% of 2,838 patients who received IMBRUVICA in 27 clinical trials. Bleeding events of any grade including bruising and petechiae occurred in 39%, and excluding bruising and petechiae occurred in 23% of patients who received IMBRUVICA, respectively [see Adverse Reactions ( 6.1 )] .
The mechanism for the bleeding events is not well understood. Use of either anticoagulant or antiplatelet agents concomitantly with IMBRUVICA increases the risk of major hemorrhage. Across clinical trials, 3.1% of 2,838 patients who received IMBRUVICA without antiplatelet or anticoagulant therapy experienced major hemorrhage.
The addition of antiplatelet therapy with or without anticoagulant therapy increased this percentage to 4.4%, and the addition of anticoagulant therapy with or without antiplatelet therapy increased this percentage to 6.1%. Consider the risks and benefits of anticoagulant or antiplatelet therapy when co-administered with IMBRUVICA. Monitor for signs and symptoms of bleeding.
Consider the benefit-risk of withholding IMBRUVICA for at least 3 to 7 days pre- and post-surgery depending upon the type of surgery and the risk of bleeding [see Clinical Studies ( 14 )].
5.2Infections Fatal and non-fatal infections (including bacterial, viral, or fungal) have occurred with IMBRUVICA therapy. Grade 3 or greater infections occurred in 21% of 1,476 patients with B-cell malignancies who received IMBRUVICA in clinical trials [see Adverse Reactions ( 6.1 , 6.2 )] . Cases of progressive multifocal leukoencephalopathy (PML) and Pneumocystis jirovecii pneumonia (PJP) have occurred in patients treated with IMBRUVICA.
Consider prophylaxis according to standard of care in patients who are at increased risk for opportunistic infections. Monitor and evaluate patients for fever and infections and treat appropriately.
5.3Cardiac Arrhythmias, Cardiac Failure, and Sudden Death Fatal and serious cardiac arrhythmias and cardiac failure have occurred with IMBRUVICA. Deaths due to cardiac causes or sudden deaths occurred in 1% of 4,896 patients who received IMBRUVICA in clinical trials, including in patients who received IMBRUVICA in unapproved monotherapy or combination regimens. These adverse reactions occurred in patients with and without preexisting hypertension or cardiac comorbidities.
Patients with cardiac comorbidities may be at greater risk of these events. Grade 3 or greater ventricular tachyarrhythmias were reported in 0.2%, Grade 3 or greater atrial fibrillation and atrial flutter were reported in 3.7%, and Grade 3 or greater cardiac failure was reported in 1.3% of 4,896 patients who received IMBRUVICA in clinical trials, including in patients who received IMBRUVICA in… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Hemorrhage [see Warnings and Precautions ( 5.1 )] Infections [see Warnings and Precautions ( 5.2 )] Cardiac Arrhythmias, Cardiac Failure, and Sudden Death [see Warnings and Precautions ( 5.3 )] Hypertension [see Warnings and Precautions ( 5.4 )] Cytopenias [see Warnings and Precautions ( 5.5 )] Second Primary Malignancies [see Warnings and Precautions ( 5.6 )] Hepatotoxicity, including DILI [see Warning s and Precautions ( 5.7 )] Tumor Lysis Syndrome [see Warnings and Precautions ( 5.8 )] The most common (≥30%) adverse reactions in patients with B-cell malignancies are thrombocytopenia, diarrhea, fatigue, musculoskeletal pain, neutropenia, rash, anemia, bruising, and nausea ( 6 ).
The most common (≥20%) adverse reactions in adult or pediatric patients with cGVHD are fatigue, anemia, bruising, diarrhea, thrombocytopenia, musculoskeletal pain, pyrexia, muscle spasms, stomatitis, hemorrhage, nausea, abdominal pain, pneumonia, and headache ( 6 ). To report SUSPECTED ADVERSE REACTIONS, contact AbbVie at 1-800-633-9110 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely variable conditions, adverse reaction rates observed in clinical trials of a drug cannot be directly compared with rates of clinical trials of another drug and may not reflect the rates observed in practice. Unless otherwise specified, the pooled safety population described in the WARNINGS AND PRECAUTIONS reflects exposure to IMBRUVICA in 6 trials. IMBRUVICA was administered as a single agent at 420 mg orally once daily (475 patients), as a single agent at 560 mg orally once daily [1.3 times the recommended adult dosage (174 patients)], and in combination with other drugs at 420 mg orally once daily (827 patients) in patients with B-cell malignancies.
In this pooled safety population of 1,476 patients, 87% were exposed for 6 months or longer and 68% were exposed for greater than one year. The most common adverse reactions (≥ 30%) were thrombocytopenia, diarrhea, fatigue, musculoskeletal pain, neutropenia, rash, anemia, bruising, and nausea. Certain subsections in the WARNINGS AND PRECAUTIONS include patients who received IMBRUVICA in unapproved monotherapy or combination regimens.
Chronic Lymphocytic Leukemia/Small Lymphocytic Lymphoma The data described below reflect exposure to IMBRUVICA in one single-arm, open-label clinical trial (Study 1102) and five randomized controlled clinical trials (RESONATE, RESONATE-2, HELIOS, iLLUMINATE, and E1912) in patients with CLL/SLL (n=2,016 total, including n=1,133 patients exposed to IMBRUVICA). In general, patients with creatinine clearance (CLcr) ≤ 30 mL/min, AST or ALT ≥ 2.5 x ULN, or total bilirubin ≥ 1.5 x ULN (unless of non-hepatic origin) were excluded from these trials.
In Study E1912, patients with AST or ALT > 3 x ULN or total bilirubin > 2.5 x ULN were excluded. Study 1102 included 51 patients with previously treated CLL/SLL. RESONATE included 386 randomized patients with previously treated CLL or SLL who received single agent IMBRUVICA or ofatumumab.
RESONATE-2 included 267 randomized patients with treatment naïve CLL or SLL who were 65 years or older and received single agent IMBRUVICA or chlorambucil. HELIOS included 574 randomized patients with previously treated CLL or SLL who received IMBRUVICA in combination with BR or placebo in combination with BR. iLLUMINATE included 228 randomized patients with treatment naïve CLL/SLL who were 65 years or older or with coexisting medical conditions and received IMBRUVICA in combination with obinutuzumab or chlorambucil in combination with obinutuzumab.
E1912 included 510 patients with previously untreated CLL/SLL who were 70 years or younger and received IMBRUVICA in combination with rituximab or received fludarabine, cyclophosphamide, and rituximab (FCR). The most common adverse… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CYP3A Inhibitors: Modify IMBRUVICA dose as described ( 2.3 , 7.1 ). CYP3A Inducers: Avoid coadministration with strong CYP3A inducers ( 7.2 ).
7.1Effect of CYP3A Inhibitors on Ibrutinib The coadministration of IMBRUVICA with a strong or moderate CYP3A inhibitor may increase ibrutinib plasma concentrations [see Clinical Pharmacology ( 12.3 )] . Increased ibrutinib concentrations may increase the risk of drug-related toxicity. Dose modifications of IMBRUVICA are recommended when used concomitantly with posaconazole, voriconazole and moderate CYP3A inhibitors [see Dosage and Administration ( 2.3 )].
Avoid concomitant use of other strong CYP3A inhibitors. Interrupt IMBRUVICA if these inhibitors will be used short-term (such as anti-infectives for seven days or less) [see Dosage and Administration ( 2.3 ) ] . Avoid grapefruit and Seville oranges during IMBRUVICA treatment, as these contain strong or moderate inhibitors of CYP3A.
7.2Effect of CYP3A Inducers on Ibrutinib The coadministration of IMBRUVICA with strong CYP3A inducers may decrease ibrutinib concentrations. Avoid coadministration with strong CYP3A inducers [see Clinical Pharmacology ( 12.3 ) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation : Advise not to breastfeed ( 8.2 ). Hepatic Impairment : Avoid use of IMBRUVICA in patients with severe hepatic impairment. In patients with mild or moderate impairment, reduce IMBRUVICA dose ( 2.4 , 8.6 ).
8.1Pregnancy Risk Summary IMBRUVICA can cause fetal harm based on findings from animal studies. There are no available data on IMBRUVICA use in pregnant women to inform a drug-associated risk of major birth defects and miscarriage. In animal reproduction studies, administration of ibrutinib to pregnant rats and rabbits during the period of organogenesis at exposures up to 3-20 times the clinical dose of 420 mg daily produced embryofetal toxicity including structural abnormalities (see Data) .
Advise pregnant women of the potential risk to a fetus. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data Ibrutinib was administered orally to pregnant rats during the period of organogenesis at doses of 10, 40 and 80 mg/kg/day. Ibrutinib at a dose of 80 mg/kg/day was associated with visceral malformations (heart and major vessels) and increased resorptions and post-implantation loss.
The dose of 80 mg/kg/day in rats is approximately 20 times the exposure in patients with CLL/SLL or WM administered a dose of 420 mg daily. Ibrutinib at doses of 40 mg/kg/day or greater was associated with decreased fetal weights. The dose of 40 mg/kg/day in rats is approximately 8 times the exposure (AUC) in patients administered a dose of 420 mg daily.
Ibrutinib was also administered orally to pregnant rabbits during the period of organogenesis at doses of 5, 15, and 45 mg/kg/day. Ibrutinib at a dose of 15 mg/kg/day or greater was associated with skeletal variations (fused sternebrae) and ibrutinib at a dose of 45 mg/kg/day was associated with increased resorptions and post-implantation loss. The dose of 15 mg/kg/day in rabbits is approximately 2.8 times the exposure in patients with CLL/SLL or WM administered a dose of 420 mg daily.
8.2Lactation Risk Summary There is no information regarding the presence of ibrutinib or its metabolites in human milk, the effects on the breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions in the breastfed child, advise women not to breastfeed during treatment with IMBRUVICA and for 1 week after the last dose.
8.3Females and Males of Reproductive Potential IMBRUVICA can cause fetal harm when administered to pregnant women [see Use in Specific Populations ( 8.1 )] . Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to initiating IMBRUVICA. Contraception Females Advise females of reproductive potential to use effective contraception during treatment with IMBRUVICA and for 1 month after the last dose.
Males Advise males with female partners of reproductive potential to use effective contraception during treatment with IMBRUVICA and for 1 month following the last dose.
8.4Pediatric Use Chronic GVHD The safety and effectiveness of IMBRUVICA have been established for treatment of cGVHD after failure of one or more lines of systemic therapy in pediatric patients 1 year of age and older. Use of IMBRUVICA for this indication is supported by evidence from iMAGINE, a study which included pediatric patients age 1 year and older with previously treated cGVHD, including patients in the following age groups: one patient 1 year to less than 2 years of age, 20 patients 2 years to less than 12 years of age, and 19 patients 12 years to less than 17 years of age.
Additional supportive efficacy data was provided from Study 1129 in adults [see Adverse Reactions ( 6.1 ), Clinical P… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary IMBRUVICA can cause fetal harm based on findings from animal studies. There are no available data on IMBRUVICA use in pregnant women to inform a drug-associated risk of major birth defects and miscarriage. In animal reproduction studies, administration of ibrutinib to pregnant rats and rabbits during the period of organogenesis at exposures up to 3-20 times the clinical dose of 420 mg daily produced embryofetal toxicity including structural abnormalities (see Data) .
Advise pregnant women of the potential risk to a fetus. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data Ibrutinib was administered orally to pregnant rats during the period of organogenesis at doses of 10, 40 and 80 mg/kg/day. Ibrutinib at a dose of 80 mg/kg/day was associated with visceral malformations (heart and major vessels) and increased resorptions and post-implantation loss.
The dose of 80 mg/kg/day in rats is approximately 20 times the exposure in patients with CLL/SLL or WM administered a dose of 420 mg daily. Ibrutinib at doses of 40 mg/kg/day or greater was associated with decreased fetal weights. The dose of 40 mg/kg/day in rats is approximately 8 times the exposure (AUC) in patients administered a dose of 420 mg daily.
Ibrutinib was also administered orally to pregnant rabbits during the period of organogenesis at doses of 5, 15, and 45 mg/kg/day. Ibrutinib at a dose of 15 mg/kg/day or greater was associated with skeletal variations (fused sternebrae) and ibrutinib at a dose of 45 mg/kg/day was associated with increased resorptions and post-implantation loss. The dose of 15 mg/kg/day in rabbits is approximately 2.8 times the exposure in patients with CLL/SLL or WM administered a dose of 420 mg daily.
🧒 Pediatric Use ▾
8.4Pediatric Use Chronic GVHD The safety and effectiveness of IMBRUVICA have been established for treatment of cGVHD after failure of one or more lines of systemic therapy in pediatric patients 1 year of age and older. Use of IMBRUVICA for this indication is supported by evidence from iMAGINE, a study which included pediatric patients age 1 year and older with previously treated cGVHD, including patients in the following age groups: one patient 1 year to less than 2 years of age, 20 patients 2 years to less than 12 years of age, and 19 patients 12 years to less than 17 years of age.
Additional supportive efficacy data was provided from Study 1129 in adults [see Adverse Reactions ( 6.1 ), Clinical Pharmacology ( 12.3 ), and Clinical Studies ( 14.3 )] . The recommended dosage of IMBRUVICA in patients age 12 years and older is the same as that in adults, and the recommended dosage in patients age 1 year to less than 12 years old is based on body-surface area (BSA) [see Dosage and Administration ( 2.1 )] . The safety and effectiveness of IMBRUVICA have not been established for this indication in pediatric patients less than 1 year of age.
Mature B-cell Non-Hodgkin Lymphoma The safety and effectiveness of IMBRUVICA in combination with chemoimmunotherapy were assessed but have not been established based on an open-label, randomized study (NCT02703272) in 35 patients, which included 26 pediatric patients age 5 to less than 17 years, with previously treated mature B-cell non-Hodgkin lymphoma. The study was stopped for futility. In the randomized population, major hemorrhage and discontinuation of chemoimmunotherapy due to adverse reactions occurred more frequently in the ibrutinib plus chemoimmunotherapy arm compared to the chemoimmunotherapy alone arm.
CLL/SLL, CLL/SLL with 17p deletion, WM The safety and effectiveness of IMBRUVICA in pediatric patients have not been established in CLL/SLL, CLL/SLL with 17p deletion, or WM.
🧓 Geriatric Use ▾
8.5Geriatric Use Of 992 patients in clinical studies of IMBRUVICA for B-cell malignancies or cGVHD, 62% were ≥ 65 years of age, while 22% were ≥ 75 years of age [see Clinical Studies ( 14.1 , 14.2 , 14.3 )] . No overall differences in effectiveness were observed between younger and older patients. Anemia (all grades), pneumonia (Grade 3 or higher), thrombocytopenia, hypertension, and atrial fibrillation occurred more frequently among older patients treated with IMBRUVICA [see Adverse Reactions ( 6.1 )] .
🆘 Overdosage ▾
10 OVERDOSAGE There is no specific experience in the management of ibrutinib overdose in patients. One healthy subject experienced reversible Grade 4 hepatic enzyme increases (AST and ALT) after a dose of 1680 mg. Closely monitor patients who ingest more than the recommended dosage and provide appropriate supportive treatment.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ibrutinib is a small-molecule inhibitor of Bruton’s tyrosine kinase (BTK). Ibrutinib forms a covalent bond with a cysteine residue in the BTK active site, leading to inhibition of BTK enzymatic activity. BTK is a signaling molecule of the B-cell antigen receptor (BCR) and cytokine receptor pathways.
BTK’s role in signaling through the B-cell surface receptors results in activation of pathways necessary for B-cell trafficking, chemotaxis, and adhesion. Nonclinical studies show that ibrutinib inhibits malignant B-cell proliferation and survival in vivo as well as cell migration and substrate adhesion in vitro .
12.2Pharmacodynamics In patients with recurrent B-cell lymphoma > 90% occupancy of the BTK active site in peripheral blood mononuclear cells was observed up to 24 hours after ibrutinib doses of ≥ 2.5 mg/kg/day (≥ 175 mg/day for average weight of 70 kg). In adult patients with cGVHD, 93% occupancy of the BTK active site in peripheral blood mononuclear cells was observed at the ibrutinib recommended dose. The mean BTK occupancy in pediatric patients ranged from 95.1% to 99.6%.
In vitro Platelet Aggregation Ibrutinib demonstrated inhibition of collagen-induced platelet aggregation, with IC50 values at 4.6 µM (2026 ng/mL), 0.8 µM (352 ng/mL), and 3 µM (1321 ng/mL) in blood samples from healthy donors, donors taking warfarin, and donors with severe renal dysfunction, respectively. Ibrutinib did not show meaningful inhibition of platelet aggregation for ADP, arachidonic acid, ristocetin, and TRAP-6. Cardiac Electrophysiology At a single dose 4 times the maximum recommended dose (1680 mg), IMBRUVICA did not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics Ibrutinib exposure increases with doses up to 840 mg (2 times the maximum approved recommended dosage) in patients with B-cell malignancies. The mean steady-state AUC (% coefficient of variation) observed in patients at 420 mg with CLL/SLL is 708 (71%) ng×h/mL, with WM is 707 (72%) ng×h/mL, and in adult patients with previously treated cGVHD is 1159 (50%) ng×h/mL. Steady-state concentrations of ibrutinib without CYP3A inhibitors were achieved with an accumulation ratio of 1 to 1.6 after 1 week of multiple daily doses of 420 mg.
Absorption Absolute bioavailability of ibrutinib in fasted condition was 2.9% (90% CI: 2.1, 3.9) in healthy subjects. Ibrutinib is absorbed after oral administration with a median T max of 1 hour to 2 hours. Effect of Food The administration of IMBRUVICA with a high-fat and high-calorie meal (800 calories to 1,000 calories with approximately 50% of total caloric content of the meal from fat) increased ibrutinib C max by 2- to 4-fold and AUC by approximately 2-fold, compared with administration of ibrutinib after overnight fasting.
In vitro studies suggest that ibrutinib is not a substrate of p-glycoprotein (P-gp) or breast cancer resistance protein (BCRP). Distribution Reversible binding of ibrutinib to human plasma protein in vitro was 97.3% with no concentration dependence in the range of 50 ng/mL to 1000 ng/mL. The volume of distribution (V d ) was 683 L, and the apparent volume of distribution at steady state (V d,ss /F) was approximately 10,000 L.
Elimination Intravenous clearance was 62 L/h in fasted conditions and 76 L/h in fed conditions. In line with the high first-pass effect, the apparent oral clearance is 2000 L/h in fasted conditions and 1000 L/h in fed conditions. The half-life of ibrutinib is 4 hours to 6 hours.
Metabolism Metabolism is the main route of elimination for ibrutinib. It is metabolized to several metabolites primarily by cytochrome P450 (CYP) 3A and to a minor extent by CYP2D6. The active metabolite, PCI-45227, is a dihydrodiol metabolite with inhibitory activity towards BTK approximately 15 times lower than that of ibrutinib.
The range of the mean metabolite to parent ratio for PCI-45227 at steady-state is 1 to 2.8. Excretion Ibrutinib, mainly… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ibrutinib is a small-molecule inhibitor of Bruton’s tyrosine kinase (BTK). Ibrutinib forms a covalent bond with a cysteine residue in the BTK active site, leading to inhibition of BTK enzymatic activity. BTK is a signaling molecule of the B-cell antigen receptor (BCR) and cytokine receptor pathways.
BTK’s role in signaling through the B-cell surface receptors results in activation of pathways necessary for B-cell trafficking, chemotaxis, and adhesion. Nonclinical studies show that ibrutinib inhibits malignant B-cell proliferation and survival in vivo as well as cell migration and substrate adhesion in vitro .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Capsules The 70 mg capsules are supplied as yellow opaque capsules, marked with “ibr 70 mg” in black ink, in white HDPE bottles with a child-resistant closure: 28 capsules per bottle: NDC 57962-070-28 The 140 mg capsules are supplied as white opaque capsules, marked with “ibr 140 mg” in black ink, in white HDPE bottles with a child-resistant closure: 90 capsules per bottle: NDC 57962-140-09 120 capsules per bottle: NDC 57962-140-12 Store bottles at room temperature 20°C to 25°C (68°F to 77°F).
Brief exposure to 15°C to 30°C (59°F to 86°F) permitted (see USP Controlled Room Temperature). Retain in original package until dispensing. Tablets The IMBRUVICA (ibrutinib) tablets are supplied in 3 strengths in the following packaging configurations: 140 mg tablets: Yellow green to green round tablets debossed with “ibr” on one side and “140” on the other side.
Carton of one folded blister card containing two 14-count blister strips for a total of 28 tablets: NDC 57962-014-28 280 mg tablets: Purple oblong tablets debossed with “ibr” on one side and “280” on the other side. Carton of one folded blister card containing two 14-count blister strips for a total of 28 tablets: NDC 57962-280-28 420 mg tablets: Yellow green to green oblong tablets debossed with “ibr” on one side and “420” on the other side. Carton of one folded blister card containing two 14-count blister strips for a total of 28 tablets: NDC 57962-420-28 Store tablets in original packaging at room temperature 20°C to 25°C (68°F to 77°F).
Brief exposure to 15°C to 30°C (59°F to 86°F) permitted (see USP Controlled Room Temperature). Oral Suspension The IMBRUVICA (ibrutinib) oral suspension is a white to off-white suspension supplied as 108 mL in a 150 mL amber glass bottle with a pre-inserted bottle adapter and a child-resistant closure. Each mL contains 70 mg of ibrutinib.
The oral suspension bottle is provided in a carton with two 3 mL reusable oral dosing syringes: NDC 57962-007-12. Store the oral suspension bottle at 2°C to 25°C (36°F to 77°F). Do not freeze.
Dispense in original sealed container. Do not use if the carton seal is broken or missing. Discard any unused IMBRUVICA oral suspension remaining 60 days after first opening the bottle.
📋 Description ▾
11 DESCRIPTION Ibrutinib is a kinase inhibitor. It is a white to off-white solid with the empirical formula C 25 H 24 N 6 O 2 and a molecular weight 440.50. Ibrutinib is freely soluble in dimethyl sulfoxide, soluble in methanol and practically insoluble in water.
The chemical name for ibrutinib is 1-[(3R)-3-[4-amino-3-(4-phenoxyphenyl)-1H-pyrazolo[3,4-d]pyrimidin-1-yl]-1-piperidinyl]-2-propen-1-one and has the following structure: IMBRUVICA (ibrutinib) is available as immediate-release oral capsules, immediate-release oral tablets, and immediate-release oral suspension. IMBRUVICA (ibrutinib) capsules for oral use are available in the following dosage strengths: 70 mg and 140 mg. Each capsule contains ibrutinib (active ingredient) and the following inactive ingredients: croscarmellose sodium, magnesium stearate, microcrystalline cellulose, sodium lauryl sulfate.
The capsule shell contains gelatin, titanium dioxide, yellow iron oxide (70 mg capsule only), and black ink. IMBRUVICA (ibrutinib) tablets for oral use are available in the following dosage strengths: 140 mg, 280 mg, and 420 mg. Each tablet contains ibrutinib (active ingredient) and the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, lactose monohydrate, magnesium stearate, microcrystalline cellulose, povidone, and sodium lauryl sulfate.
The film coating for each tablet contains ferrosoferric oxide (140 mg, 280 mg, and 420 mg tablets), polyvinyl alcohol, polyethylene glycol, red iron oxide (280 mg tablets), talc, titanium dioxide, and yellow iron oxide (140 mg and 420 mg tablets). IMBRUVICA (ibrutinib) oral suspension contains 70 mg/mL ibrutinib (active ingredient) and the following inactive ingredients: benzyl alcohol, citric acid monohydrate, disodium hydrogen phosphate, hypromellose, microcrystalline cellulose and carboxymethylcellulose sodium, purified water and sucralose.
The following structure for Ibrutinib is kinase inhibitor. It is a white to off-white solid with the empirical formula C25H24N6O2 and a molecular weight 440.50. Ibrutinib is freely soluble in dimethyl sulfoxide, soluble in methanol and practically insoluble in water.
The chemical name for ibrutinib is 1-[(3R)-3-[4-amino-3-(4-phenoxyphenyl)-1H-pyrazolo[3,4 d]pyrimidin-1-yl]-1-piperidinyl]-2-propen-1-one and has
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patients and caregivers to read the FDA-approved patient labeling ( Patient Information and Instructions for Use ). Hemorrhage: Inform patients of the possibility of bleeding, and to report any signs or symptoms (severe headache, blood in stools or urine, prolonged or uncontrolled bleeding). Inform the patient that IMBRUVICA may need to be interrupted for medical or dental procedures [see Warnings and Precautions ( 5.1 )] .
Infections: Inform patients of the possibility of serious infection, and to report any signs or symptoms (fever, chills, weakness, confusion) suggestive of infection [see Warnings and Precautions ( 5.2 )] . Cardiac arrhythmias , cardiac failure , and sudden death : Inform patients of the possibility of irregular heart rhythm, heart failure and sudden death. Counsel patients to report any signs of palpitations, lightheadedness, dizziness, fainting, shortness of breath, chest discomfort, or edema [see Warning s and Precautions ( 5.3 )] .
Hypertension : Inform patients that high blood pressure has occurred in patients taking IMBRUVICA, which may require treatment with anti-hypertensive therapy [see Warnings and Precautions ( 5.4 )] . Second primary malignancies: Inform patients that other malignancies have occurred in patients who have been treated with IMBRUVICA, including skin cancers and other carcinomas [see Warnings and Precautions ( 5.6 )] . Hepatotoxicity, including drug-induced liver injury: Inform patients that liver problems, including drug-induced liver injury and abnormalities in liver tests, may develop during IMBRUVICA treatment.
Advise patients to contact their healthcare provider immediately if they experience abdominal discomfort, dark urine, or jaundice [see Warnings and Precautions ( 5.7 )]. Tumor lysis syndrome: Inform patients of the potential risk of tumor lysis syndrome and to report any signs and symptoms associated with this event to their healthcare provider for evaluation [see Warnings and Precautions ( 5.8 )]. Embryo-fetal toxicity: Advise women of the potential risk to a fetus.
Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions ( 5.9 ), Use in Specific Populations ( 8.1 )] . Advise females of reproductive potential to use effective contraception during treatment with IMBRUVICA and for 1 month after the last dose [see Use in Specific Populations ( 8.3 ) ] . Advise males with female partners of reproductive potential to use effective contraception during treatment with IMBRUVICA and for 1 month after the last dose [see Use in Specific Populations ( 8.3 ), Nonclinical Toxicology ( 13.1 )] .
Lactation: Advise women not to breastfeed during treatment with IMBRUVICA and for 1 week after the last dose [see Use in Specific Populations ( 8.2 )] . Other Important Information: Inform patients to take IMBRUVICA orally once daily according to their physician’s instructions and that the oral dosage (capsules or tablets) should be swallowed whole with a glass of water without opening, breaking or chewing the capsules or cutting, crushing or chewing the tablets approximately the same time each day [see Dosage and Administration ( 2.1 )] .
Advise patients that in the event of a missed daily dose of IMBRUVICA, it should be taken as soon as possible on the same day with a return to the normal schedule the following day. Patients should not take extra doses to make up the missed dose [see Dosage and Administration ( 2.1 )] . For IMBRUVICA oral suspension, instruct patients or caregivers to read and follow the Instructions for Use for proper preparation, administration, storage and disposal [see Dosage and Administration ( 2.1 )] .
Advise patients of the common side effects associated with IMBRUVICA [see Adverse Reactions ( 6 )] . Direct the patient to a complete list of adverse drug reactions in PATIENT INFORMATION . Advise patients to inform their health care provider… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Ibrutinib exposure increases with doses up to 840 mg (2 times the maximum approved recommended dosage) in patients with B-cell malignancies. The mean steady-state AUC (% coefficient of variation) observed in patients at 420 mg with CLL/SLL is 708 (71%) ng×h/mL, with WM is 707 (72%) ng×h/mL, and in adult patients with previously treated cGVHD is 1159 (50%) ng×h/mL. Steady-state concentrations of ibrutinib without CYP3A inhibitors were achieved with an accumulation ratio of 1 to 1.6 after 1 week of multiple daily doses of 420 mg.
Absorption Absolute bioavailability of ibrutinib in fasted condition was 2.9% (90% CI: 2.1, 3.9) in healthy subjects. Ibrutinib is absorbed after oral administration with a median T max of 1 hour to 2 hours. Effect of Food The administration of IMBRUVICA with a high-fat and high-calorie meal (800 calories to 1,000 calories with approximately 50% of total caloric content of the meal from fat) increased ibrutinib C max by 2- to 4-fold and AUC by approximately 2-fold, compared with administration of ibrutinib after overnight fasting.
In vitro studies suggest that ibrutinib is not a substrate of p-glycoprotein (P-gp) or breast cancer resistance protein (BCRP). Distribution Reversible binding of ibrutinib to human plasma protein in vitro was 97.3% with no concentration dependence in the range of 50 ng/mL to 1000 ng/mL. The volume of distribution (V d ) was 683 L, and the apparent volume of distribution at steady state (V d,ss /F) was approximately 10,000 L.
Elimination Intravenous clearance was 62 L/h in fasted conditions and 76 L/h in fed conditions. In line with the high first-pass effect, the apparent oral clearance is 2000 L/h in fasted conditions and 1000 L/h in fed conditions. The half-life of ibrutinib is 4 hours to 6 hours.
Metabolism Metabolism is the main route of elimination for ibrutinib. It is metabolized to several metabolites primarily by cytochrome P450 (CYP) 3A and to a minor extent by CYP2D6. The active metabolite, PCI-45227, is a dihydrodiol metabolite with inhibitory activity towards BTK approximately 15 times lower than that of ibrutinib.
The range of the mean metabolite to parent ratio for PCI-45227 at steady-state is 1 to 2.8. Excretion Ibrutinib, mainly in the form of metabolites, is eliminated primarily via feces. After a single oral administration of radiolabeled ibrutinib, 90% of radioactivity was excreted within 168 hours, with 80% excreted in the feces and less than 10% eliminated in urine.
Unchanged ibrutinib accounted for 1% of the radiolabeled excreted dose in feces and none in urine, with the remainder of the excreted dose being metabolites. Specific Populations Age and Sex Age and sex have no clinically meaningful effect on ibrutinib pharmacokinetics. Patients with Renal Impairment Mild and moderate renal impairment (creatinine clearance [CLcr] > 25 mL/min as estimated by Cockcroft-Gault equation) had no influence on the exposure of ibrutinib.
No data is available in patients with severe renal impairment (CLcr < 25 mL/min) or in patients on dialysis. Patients with Hepatic Impairment The AUC of ibrutinib increased 2.7-fold in subjects with mild hepatic impairment (Child-Pugh class A), 8.2-fold in subjects with moderate hepatic impairment (Child-Pugh class B) and 9.8-fold in subjects with severe hepatic impairment (Child-Pugh class C) relative to subjects with normal liver function. The C max of ibrutinib increased 5.2-fold in mild hepatic impairment, 8.8-fold in moderate hepatic impairment and 7-fold in severe hepatic impairment relative to subjects with normal liver function [see Use in Specific Populations ( 8.6 )].
Pediatric Patients In pediatric patients with cGVHD treated with ibrutinib at 240 mg/m 2 once daily (patients age ≥ 1 to < 12 years) or 420 mg once daily (patients age ≥ 12 years), the geometric mean (%CV) steady state AUC and C max in patients age ≥ 1 to < 12 years is 467 (102%) ng×h/mL and 65.7 (96%) ng/mL, respectively, and in patients a… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics In patients with recurrent B-cell lymphoma > 90% occupancy of the BTK active site in peripheral blood mononuclear cells was observed up to 24 hours after ibrutinib doses of ≥ 2.5 mg/kg/day (≥ 175 mg/day for average weight of 70 kg). In adult patients with cGVHD, 93% occupancy of the BTK active site in peripheral blood mononuclear cells was observed at the ibrutinib recommended dose. The mean BTK occupancy in pediatric patients ranged from 95.1% to 99.6%.
In vitro Platelet Aggregation Ibrutinib demonstrated inhibition of collagen-induced platelet aggregation, with IC50 values at 4.6 µM (2026 ng/mL), 0.8 µM (352 ng/mL), and 3 µM (1321 ng/mL) in blood samples from healthy donors, donors taking warfarin, and donors with severe renal dysfunction, respectively. Ibrutinib did not show meaningful inhibition of platelet aggregation for ADP, arachidonic acid, ristocetin, and TRAP-6. Cardiac Electrophysiology At a single dose 4 times the maximum recommended dose (1680 mg), IMBRUVICA did not prolong the QT interval to any clinically relevant extent.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES A graph showing the number of the number of the number of the number of the number of the number of the number of the number of the number of the number of the number of the number of AI-generated content may be incorrect. A graph showing the number of numbers AI-generated content may be incorrect. A graph showing the number of patients AI-generated content may be incorrect.
Figure 4: Kaplan-Meier Curve of Progression-Free Survival (ITT Population) in Patients with CLL/SLL in HELIOS A graph showing the number of patients AI-generated content may be incorrect. A graph showing the number of objects AI-generated content may be incorrect. A graph showing the growth of a stock market AI-generated content may be incorrect.
14.1Chronic Lymphocytic Leukemia / Small Lymphocytic Lymphoma The safety and efficacy of IMBRUVICA in patients with CLL/SLL were demonstrated in one uncontrolled trial and five randomized, controlled trials. Study 1102 Study 1102 (NCT01105247), an open-label, multi-center trial, was conducted in 48 previously treated CLL patients. IMBRUVICA was administered orally at 420 mg once daily until disease progression or unacceptable toxicity.
The ORR and DOR were assessed using a modified version of the International Workshop on CLL Criteria by an Independent Review Committee. The median age was 67 years (range, 37 to 82 years), 71% were male, and 94% were White. All patients had a baseline ECOG performance status of 0 or 1.
The median time since diagnosis was 80 months and the median number of prior treatments was 4 (range, 1 to 12 treatments). At baseline, 46% of subjects had at least one tumor ≥ 5 cm. The ORR was 58.3% (95% CI: 43.2%, 72.4%), all partial responses.
None of the patients achieved a complete response. The DOR ranged from 5.6 to 24.2+ months. The median DOR was not reached.
RESONATE The RESONATE study, a randomized, multicenter, open-label, phase 3 study of IMBRUVICA versus ofatumumab (NCT01578707), was conducted in patients with previously treated CLL or SLL. Patients (n=391) were randomized 1:1 to receive either IMBRUVICA 420 mg daily until disease progression, or unacceptable toxicity or ofatumumab at an initial dose of 300 mg, followed one week later by a dose of 2000 mg weekly for 7 doses and then every 4 weeks for 4 additional doses. Fifty-seven patients randomized to ofatumumab crossed over following progression to receive IMBRUVICA.
The median age was 67 years (range, 30 to 88 years), 68% were male, and 90% were White. All patients had a baseline ECOG performance status of 0 or 1. The trial enrolled 373 patients with CLL and 18 patients with SLL.
The median time since diagnosis was 91 months and the median number of prior treatments was 2 (range, 1 to 13 treatments). At baseline, 58% of patients had at least one tumor ≥ 5 cm. Thirty-two percent of patients had 17p deletion.
Efficacy results for RESONATE are shown in Table 22 and the Kaplan-Meier curves for PFS, assessed by an IRC according to IWCLL criteria, and OS are shown in Figure 1 and Figure 2 , respectively. Table 22: Efficacy Results in Patients with CLL/SLL in RESONATE Endpoint IMBRUVICA N=195 Ofatumumab N=196 Progression - Free Survival b Number of events (%) 35 (17.9) 111 (56.6) Disease progression 26 93 Death events 9 18 Median (95% CI), months NE 8.1 (7.2, 8.3) HR (95% CI) 0.22 (0.15, 0.32) Overall Survival a Number of deaths (%) 16 (8.2) 33 (16.8) HR (95% CI) 0.43 (0.24, 0.79) Overall Response Rate b 42.6% 4.1% a Median OS not evaluable for either arm. b IRC evaluated.
All partial responses achieved; none of the patients achieved a complete response. CI = confidence interval; HR = hazard ratio; NE = not evaluable. Figure 1: Kaplan-Meier Curve of Progression - Free Survival (ITT Population) in Patients with CLL/SLL in RESONATE Figure 2 : Kaplan-Meier Curve of Overall Survival (ITT Population) in Patients with CLL/SLL in RESONATE 63-Month Follow-Up With an overall follow-up of 63 months, the median investigator-ass… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Ibrutinib was not carcinogenic in a 6-month rasH2 mouse study at oral doses up to 2000 mg/kg/day resulting in exposures approximately 32 (males) to 52 (females) times higher than the exposure in humans at a dose of 420 mg daily [see Warnings and Precautions ( 5.6 )] . Ibrutinib was not mutagenic in a bacterial mutagenicity (Ames) assay, was not clastogenic in a chromosome aberration assay in mammalian (CHO) cells, nor was it clastogenic in an in vivo bone marrow micronucleus assay in mice at doses up to 2000 mg/kg.
Rats were administered oral daily doses of ibrutinib for 4 weeks prior to pairing and during pairing in males and 2 weeks prior to pairing and during pairing in females. Treatment of female rats continued following pregnancy up to gestation day (GD) 7, and treatment of male rats continued until end of study. No effects on fertility or reproductive capacities were observed in male or female rats up to the maximum dose tested, 100 mg/kg/day (Human Equivalent Dose [HED] 16 mg/kg).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Ibrutinib was not carcinogenic in a 6-month rasH2 mouse study at oral doses up to 2000 mg/kg/day resulting in exposures approximately 32 (males) to 52 (females) times higher than the exposure in humans at a dose of 420 mg daily [see Warnings and Precautions ( 5.6 )] . Ibrutinib was not mutagenic in a bacterial mutagenicity (Ames) assay, was not clastogenic in a chromosome aberration assay in mammalian (CHO) cells, nor was it clastogenic in an in vivo bone marrow micronucleus assay in mice at doses up to 2000 mg/kg.
Rats were administered oral daily doses of ibrutinib for 4 weeks prior to pairing and during pairing in males and 2 weeks prior to pairing and during pairing in females. Treatment of female rats continued following pregnancy up to gestation day (GD) 7, and treatment of male rats continued until end of study. No effects on fertility or reproductive capacities were observed in male or female rats up to the maximum dose tested, 100 mg/kg/day (Human Equivalent Dose [HED] 16 mg/kg).
📄 Patient Package Insert ▾
PATIENT INFORMATION IMBRUVICA (im-BRU-vih-kuh) (ibrutinib) capsules IMBRUVICA (im-BRU-vih-kuh) (ibrutinib) tablets IMBRUVICA (im-BRU-vih-kuh) (ibrutinib) oral suspension What is IMBRUVICA? IMBRUVICA is a prescription medicine used to treat: Adults with chronic lymphocytic leukemia (CLL)/Small lymphocytic lymphoma (SLL). Adults with chronic lymphocytic leukemia (CLL)/Small lymphocytic lymphoma (SLL) with 17p deletion.
Adults with Waldenström’s macroglobulinemia (WM). Adults and children 1 year of age and older with chronic graft versus host disease (cGVHD) after failure of 1 or more lines of systemic therapy. It is not known if IMBRUVICA is safe and effective in children under 1 year of age.
Before taking IMBRUVICA, tell your healthcare provider about all of your medical conditions, including if you: have had recent surgery or plan to have surgery. Your healthcare provider may stop IMBRUVICA for any planned medical, surgical, or dental procedure. have bleeding problems or are taking a blood thinner medicine. have an infection. have or had heart rhythm problems, smoke, or have a medical condition that increases your risk of heart disease, such as high blood pressure, high cholesterol, or diabetes. have liver problems. are pregnant or plan to become pregnant.
IMBRUVICA can harm your unborn baby. If you are able to become pregnant, your healthcare provider will do a pregnancy test before starting treatment with IMBRUVICA. Tell your healthcare provider if you are pregnant or think you may be pregnant during treatment with IMBRUVICA. ○ Females who are able to become pregnant should use effective birth control (contraception) during treatment with IMBRUVICA and for 1 month after the last dose. ○ Males with female partners who are able to become pregnant should use effective birth control, such as condoms, during treatment with IMBRUVICA and for 1 month after the last dose. are breastfeeding or plan to breastfeed.
Do not breastfeed during treatment with IMBRUVICA and for 1 week after the last dose. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. Taking IMBRUVICA with certain other medicines may affect how IMBRUVICA works and can cause side effects.
How should I take or give IMBRUVICA? Take or give IMBRUVICA exactly as your healthcare provider tells you to take or give it. Take or give IMBRUVICA 1 time a day at about the same time each day.
IMBRUVICA comes as capsules, tablets, and oral suspension. If your healthcare provider prescribes IMBRUVICA capsules or tablets: ◦ Swallow IMBRUVICA capsules or tablets whole with a glass of water. ◦ Do not open, break, or chew IMBRUVICA capsules. ◦ Do not cut, crush, or chew IMBRUVICA tablets. If your healthcare provider prescribes IMBRUVICA oral suspension: ◦ See the detailed Instructions for Use that comes with IMBRUVICA oral suspension for information about the correct way to take or give a dose.
If you have questions about how to take or give IMBRUVICA oral suspension, talk to your healthcare provider. ◦ Do not use if the carton seal is broken or missing. If you miss a dose of IMBRUVICA, take or give it as soon as you remember on the same day. Take or give the next dose of IMBRUVICA at the regular time on the next day.
Do not take or give extra doses of IMBRUVICA to make up for a missed dose. If you take too much IMBRUVICA, call your healthcare provider, or go to the nearest hospital emergency room right away. What should I avoid while taking IMBRUVICA?
You should not drink grapefruit juice, eat grapefruit, or eat Seville oranges (often used in marmalades) during treatment with IMBRUVICA. These products may increase the amount of IMBRUVICA in your blood. What are the possible side effects of IMBRUVICA?
IMBRUVICA may cause serious side effects, including: Bleeding problems (hemorrhage) are common during treatment with IMBRUVICA and can also be serious and may lead to death. Your risk of bleed… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE IMBRUVICA (im-BRU-vih-kuh) (ibrutinib) oral suspension This Instructions for Use contains information about how to prepare and take or give a dose of IMBRUVICA oral suspension . Read this Instructions for Use before you take or give IMBRUVICA and each time you get a refill. There may be new information.
This Instructions for Use does not take the place of talking to your healthcare provider about your or your child’s medical condition or treatment. Call your healthcare provider or 1-877-877-3536 if you need help or have any questions about how to take or give IMBRUVICA the right way. Important information you need to know before taking or giving IMBRUVICA.
IMBRUVICA is for oral use only. Take or give IMBRUVICA exactly as your healthcare provider tells you to. If you miss a dose of IMBRUVICA, it can be taken or given as soon as possible on the same day.
Do not take or give more than the prescribed dose in 1 day. If you or your child take too much IMBRUVICA, call your healthcare provider for help. Keep these instructions for future use.
Each IMBRUVICA carton contains (see Figure A ): 1 bottle of IMBRUVICA (called ‘bottle’ in this Instructions for Use) with pre-inserted bottle adapter (called ‘adapter’ in this Instructions for Use). Do not remove the bottle adapt e r. 2 reusable 3 mL oral dosing syringes (called ‘syringe’ in this Instructions for Use) measuring in 0.1 mL increments.
Only use the syringes that come with IMBRUVICA . Do not use the syringes for other patients or with other medicines. If you cannot read the markings on the syringes, throw them away and call 1-877-877-3536 to get new ones.
P reparing and taking or giving a dose of IMBRUVICA Step 1: Gather and check supplies . Check the prescribed dose in milliliters (mLs). Find this mL marking on the syringe.
If the dose is more than the marking on the syringe, split the dose between syringes as prescribed. Gather bottle and syringe(s) (see Figure A ). Check the bottle and make sure that the bottle has IMBRUVICA Oral Suspension printed on it and the expiration date (“EXP”) has not passed .
Figure A Do not use IMBRUVICA after the “EXP” date printed on the carton and on the bottle. Do not use if the IMBRUVICA carton seal appears to be tampered with. Step 2: Record or check the discard date .
When opening the bottle for the first time, record the date that is 60 days from the day the bottle is opened underneath the words “Discard Date” (see Figure B ). Use IMBRUVICA within 60 days after first opening the bottle. Figure B Do not use IMBRUVICA past the discard date recorded on the bottle.
Step 3: Shake the bottle . Shake the bottle well before each use (see Figure C ) . Figure C Step 4: Remove the cap from the bottle .
Press down and twist the cap counterclockwise to remove it from the bottle (see Figure D ). If there is fluid on top of the adapter, you may wipe it with a clean disposable tissue. Do not remove the bottle adapter.
Figure D Step 5: Attach the syringe to the bottle . Make sure the syringe is clean and dry before use. Push the plunger down all the way.
Gently insert tip of the syringe into the adapter. Turn the assembled bottle and syringe upside down (see Figure E ). Figure E Step 6: Fill the syringe .
Slowly pull the syringe plunger down, past the number of mLs for your prescribed dose (see Figure F ). Check for air bubbles and proceed to Step 7 for instructions on how to remove air bubbles. Figure F Step 7: Remove air bubbles and adjust to the prescribed dose (mL) .
Hold the syringe and tap the sides to send bubbles to the tip. With the syringe attached to the bottle, push the plunger up to remove the air bubbles from the top (see Figure G ). After the bubbles are removed, push the plunger up until the top of the colored plunger is even with the markings on the syringe for the prescribed dose.
Figure G Air bubbles must be removed to ensure the correct dose. Note: Repeat steps 6 and 7 if any air bubbles remain. Step 8: Remove the syringe… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 28 Capsule Bottle Carton NDC 57962-070-28 Imbruvica ® (ibrutinib) capsules 70 mg Each capsule contains: ibrutinib 70 mg Swallow capsules whole with water 28 Capsules Rx Only p harmacyclics ® An AbbVie Company j anssen NDC 57962-070-28 Imbruvica® (ibrutinib) capsules 70 mg Each capsule contains: ibrutinib 70 mg Swallow capsules whole with water 28 Capsules Rx Only pharmacyclics® An AbbVie Company janssen
PRINCIPAL DISPLAY PANEL - 90 Capsule Bottle Carton NDC 57962-140-09 Imbruvica ® (ibrutinib) capsules 140 mg Each capsule contains: ibrutinib 140 mg Swallow capsules whole with water 90 Capsules Rx Only p harmacyclics ® An AbbVie Company j anssen NDC 57962-140-09 Imbruvica® (ibrutinib) capsules 140 mg Each capsule contains: ibrutinib 140 mg Swallow capsules whole with water 90 Capsules Rx Only pharmacyclics® An AbbVie Company janssen
PRINCIPAL DISPLAY PANEL - 28 Tablet Blister Carton NDC 57962-014-28 Imbruvica ® (ibrutinib) tablets 140 mg per tablet Each tablet contains ibrutinib 140 mg Wallet card contains 28 tablets Rx Only p harmacyclics ® An AbbVie Company j anssen NDC 57962-014-28 Imbruvica® (ibrutinib) tablets 140 mg per tablet Each tablet contains ibrutinib 140 mg Wallet card contains 28 tablets Rx Only pharmacyclics® An AbbVie Company janssen
PRINCIPAL DISPLAY PANEL - 28 Tablet Blister Carton NDC 57962-280-28 Imbruvica ® (ibrutinib) tablets 280 mg per tablet Each tablet contains ibrutinib 280 mg Wallet card contains 28 tablets Rx Only p harmacyclics ® An AbbVie Company j anssen NDC 57962-280-28 Imbruvica® (ibrutinib) tablets 280 mg per tablet Each tablet contains ibrutinib 280 mg Wallet card contains 28 tablets Rx Only pharmacyclics® An AbbVie Company janssen
PRINCIPAL DISPLAY PANEL - 28 Tablet Blister Carton NDC 57962-420-28 Imbruvica ® (ibrutinib) tablets 420 mg per tablet Each tablet contains ibrutinib 420 mg Wallet card contains 28 tablets Rx Only p harmacyclics ® An AbbVie Company j anssen NDC 57962-420-28 Imbruvica® (ibrutinib) tablets 420 mg per tablet Each tablet contains ibrutinib 420 mg Wallet card contains 28 tablets Rx Only pharmacyclics® An AbbVie Company janssen
PRINCIPAL DISPLAY PANEL NDC 57962-007-12 Imbruvica ® (ibrutinib) Oral Suspension 70 mg/mL For Oral Use Only Shake well before each use Discard after 60 Days Rx Only 108mL per Bottle pharmacyclics ® An AbbVie Company j anssen NDC 57962-007-12 Imbruvica® (ibrutinib) Oral Suspension 70 mg/mL For Oral Use Only Shake well before each use Discard after 60 Days Rx Only 108mL per Bottle pharmacyclics® An AbbVie Company janssen
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |