
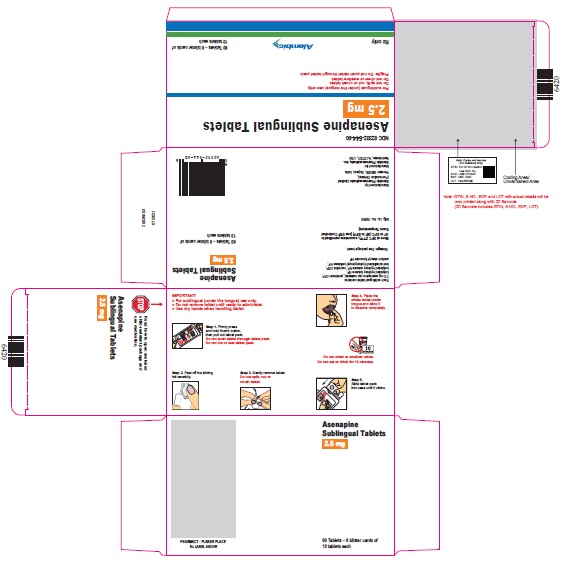
Asenapine 2.5 mg Tablet, 1,000-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Atypical Antipsychotic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Asenapine is used to treat the symptoms of schizophrenia (a mental illness that affects how a person thinks, feels and behaves) and bipolar I disorder (a disease that causes depression, mania, and other abnormal moods). Asenapine is in a class of medications called atypical antipsychotics. It works by changing the activity of certain natural substances in the brain.
Read the full MedlinePlus article ↗- This is really important — swallowing the tablet dramatically reduces how much of the medication actually gets into your system. When it dissolves under your tongue, it absorbs dir...
- Why do I have to let the tablet dissolve under my tongue instead of just swallowing it?
- Yes, sleepiness and dizziness are among the most commonly reported side effects, especially early on. The dizziness can be worse when you stand up quickly, because asenapine can ca...
- I feel really sleepy and dizzy since starting this — is that normal?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Asenapine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII REK4960K2U
Butylated hydroxyanisole is a synthetic preservative that prevents oils and fats in medicines from spoiling or becoming rancid. It keeps the medicine stable and extends its shelf life.
-
UNII 1P9D0Z171K
BHT is a synthetic antioxidant that prevents fats and oils in medicines from breaking down and becoming rancid. It helps keep the product stable and effective during storage.
-
UNII 2165RE0K14
A plant-based thickener made from cellulose that helps control how quickly the medicine dissolves and releases its active ingredient. It also binds ingredients together and improves the tablet's texture and handling during manufacturing.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $4.02 | $4,015.10 / 1000 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Saphris 2.5 mg 00456-2402-10 | Allergan, | 10 tablets | — | AB | FDA listed | — |
| Asenapine 2.5 mg 46708-0544-31 | Alembic | 1000 tablets | — | AB | FDA listed | — |
| Asenapine 2.5 mg 51991-0928-11 | Breckenridge | 100 tablets | — | AB | FDA listed | — |
| Asenapine 2.5 mgthis 62332-0544-31 | Alembic | 1000 tablets | — | AB | FDA listed | — |
| Asenapine 2.5 mg 69539-0245-34 | MSN | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 62332-0544-31 You're viewing this | 100 BLISTER PACK in 1 CARTON (62332-544-31) / 10 TABLET in 1 BLISTER PACK | — | — | 2021-07-20 | Active |
| 62332-0544-60 | 60 BLISTER PACK in 1 CARTON (62332-544-60) / 10 TABLET in 1 BLISTER PACK (62332-544-10) | $3.12 / ea | $1,870.15 | 2021-07-20 | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 62332-0544-31?
What is the difference between NDC 62332-0544-31 and NDC 62332-0544-60?
What NDC number is used to bill for this package of Asenapine 2.5 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: INCREASED MORTALITY IN ELDERLY PATIENTS WITH DEMENTIA-RELATED PSYCHOSIS Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Asenapine is not approved for the treatment of patients with dementia-related psychosis [see Warnings and Precautions (5.1, 5.2)]. WARNING: INCREASED MORTALITY IN ELDERLY PATIENTS WITH DEMENTIA-RELATED PSYCHOSIS See full prescribing information for complete boxed warning.
Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Asenapine is not approved for the treatment of patients with dementia-related psychosis. ( 5.1 , 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Asenapine is indicated for: • Bipolar I disorder [see Clinical Studies (14.2)] • Acute monotherapy of manic or mixed episodes, in pediatric patients 10 to 17 years of age • Adjunctive treatment to lithium or valproate in adults Asenapine is an atypical antipsychotic indicated for ( 1 ): Bipolar I disorder o Acute monotherapy treatment of manic or mixed episodes, in pediatric patients 10 to 17 years of age o Adjunctive treatment to lithium or valproate in adults
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Starting Dose Recommended Dose Maximum Dose Bipolar mania – pediatric patients (10 to 17 years): monotherapy ( 2.3 ) 2.5 mg sublingually twice daily 2.5 to 10 mg sublingually twice daily 10 mg sublingually twice daily Bipolar mania – adults: as an adjunct to lithium or valproate ( 2.3 ) 5 mg sublingually twice daily 5 to 10 mg sublingually twice daily 10 mg sublingually twice daily • Do not swallow tablet. Asenapine sublingual tablets should be placed under the tongue and left to dissolve completely.
The tablet will dissolve in saliva within seconds. Eating and drinking should be avoided for 10 minutes after administration. ( 2.1 , 17 )
2.1Administration Instructions Asenapine is a sublingual tablet. To ensure optimal absorption, patients should be instructed to place the tablet under the tongue and allow it to dissolve completely. The tablet will dissolve in saliva within seconds.
Asenapine sublingual tablets should not be split, crushed, chewed, or swallowed [see Clinical Pharmacology (12.3)]. Patients should be instructed to not eat or drink for 10 minutes after administration [see Clinical Pharmacology (12.3)].
2.3Bipolar I Disorder Acute Treatment of Manic or Mixed Episodes: Monotherapy in Pediatric Patients: The recommended dose of asenapine is 2.5 mg to 10 mg twice daily in pediatric patients 10 to 17 years of age, and dose may be adjusted for individual response and tolerability. The starting dose of asenapine is 2.5 mg twice daily. After 3 days, the dose can be increased to 5 mg twice daily, and from 5 mg to 10 mg twice daily after 3 additional days.
Pediatric patients aged 10 to 17 years appear to be more sensitive to dystonia with initial dosing with asenapine when the recommended escalation schedule is not followed [see Use in Specific Populations (8.4)] . The safety of doses greater than 10 mg twice daily has not been evaluated in clinical trials [see Use in Specific Populations (8.4) and Clinical Pharmacology (12.3)] . Adjunctive Therapy in Adults: The recommended starting dose of asenapine is 5 mg twice daily when administered as adjunctive therapy with either lithium or valproate.
Depending on the clinical response and tolerability in the individual patient, the dose can be increased to 10 mg twice daily. The safety of doses above 10 mg twice daily as adjunctive therapy with lithium or valproate has not been evaluated in clinical trials. For patients on asenapine, used as adjunctive therapy with lithium or valproate, it is generally recommended that responding patients continue treatment beyond the acute episode.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 2.5 mg: White to off white, round tablets debossed with ‘L’ on one side and ‘70’ on the other side. 5 mg: White to off white, round tablets debossed with “464” on one side and plain on other side. 10 mg: White to off white round tablets debossed with “465” on one side and plain on other side. Sublingual tablets: 2.5 mg, 5 mg and 10 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Asenapine is contraindicated in patients with: Severe hepatic impairment (Child-Pugh C) [see Specific Populations (8.7), Clinical Pharmacology (12.3)] . A history of hypersensitivity reactions to asenapine. Reactions have included anaphylaxis, angioedema, hypotension, tachycardia, swollen tongue, dyspnea, wheezing and rash [see Warnings and Precautions (5.6), Adverse Reactions (6)] . • Severe hepatic impairment (Child-Pugh C).
( 8.7 , 12.3 ) • Known hypersensitivity to asenapine, or to any components in the formulation. ( 4 , 5.6 , 17 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Cerebrovascular Adverse Reactions in Elderly Patients with Dementia-Related Psychosis: Increased incidence of cerebrovascular adverse reactions (e.g., stroke, transient ischemic attack). ( 5.2 ) • Neuroleptic Malignant Syndrome: Manage with immediate discontinuation and close monitoring. ( 5.3 ) • Tardive Dyskinesia: Discontinue if clinically appropriate.
( 5.4 ) • Metabolic Changes: Monitor for hyperglycemia/diabetes mellitus, dyslipidemia, and weight gain. ( 5.5 ) • Orthostatic Hypotension: Monitor heart rate and blood pressure and warn patients with known cardiovascular or cerebrovascular disease, and risk of dehydration or syncope. ( 5.7 ) • Leukopenia, Neutropenia, and Agranulocytosis: Perform complete blood counts (CBC) in patients with pre-existing low white blood cell count (WBC) or history of leukopenia or neutropenia.
Consider discontinuing asenapine if a clinically significant decline in WBC occurs in absence of other causative factors. ( 5.9 ) • QT Prolongation: Increases in QT interval; avoid use with drugs that also increase the QT interval and in patients with risk factors for prolonged QT interval. ( 5.10 ) • Seizures: Use cautiously in patients with a history of seizures or with conditions that lower the seizure threshold.
( 5.12 ) • Potential for Cognitive and Motor Impairment: Use caution when operating machinery. ( 5.13 )
5.1Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Analyses of 17 placebo-controlled trials (modal duration of 10 weeks), largely in patients taking atypical antipsychotic drugs, revealed a risk of death in drug-treated patients of between 1.6 to 1.7 times the risk of death in placebo-treated patients. Over the course of a typical 10-week controlled trial, the rate of death in drug-treated patients was about 4.5%, compared to a rate of about 2.6% in the placebo group.
Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature. Asenapine is not approved for the treatment of patients with dementia-related psychosis [see Boxed Warning and Warnings and Precautions (5.2)].
5.2Cerebrovascular Adverse Events, Including Stroke, In Elderly Patients with Dementia-Related Psychosis In placebo-controlled trials in elderly subjects with dementia, patients randomized to risperidone, aripiprazole, and olanzapine had a higher incidence of stroke and transient ischemic attack, including fatal stroke. Asenapine is not approved for the treatment of patients with dementia-related psychosis [see Boxed Warning and Warnings and Precautions (5.1)].
5.3Neuroleptic Malignant Syndrome A potentially fatal symptom complex sometimes referred to as Neuroleptic Malignant Syndrome (NMS) has been reported in association with administration of antipsychotic drugs. Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, delirium, and autonomic instability. Additional signs may include elevated creatine phosphokinase, myoglobinuria (rhabdomyolysis), and acute renal failure.
If NMS is suspected, immediately discontinue asenapine and provide intensive symptomatic treatment and monitoring.
5.4Tardive Dyskinesia Tardive dyskinesia, a syndrome consisting of potentially irreversible, involuntary, dyskinetic movements, may develop in patients treated with antipsychotic drugs, including asenapine. The risk appears to be highest among the elderly, especially elderly women, but it is not possible to predict which patients are likely to develop the syndrome. Whether antipsychotic drug products differ in their potential to cause tardive dyskinesia is unknown.
The risk of tardive dyskinesia and the likelihood that it will become irreversible increase with the duration of treatment and the cumulative dose. The syndrome can develop after a relat…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more detail in other sections of the labeling: Use in Elderly Patients with Dementia-Related Psychosis [see Boxed Warning and Warnings and Precautions (5.1 and 5.2)] Neuroleptic Malignant Syndrome [see Warnings and Precautions (5.3)] Tardive Dyskinesia [see Warnings and Precautions (5.4)] Metabolic Changes [see Warnings and Precautions (5.5)] Hypersensitivity Reactions [see Contraindications, Warnings and Precautions (5.6)] Orthostatic Hypotension, Syncope, and other Hemodynamic Effects [see Warnings and Precautions (5.7)] Falls [see Warnings and Precautions (5.8)] Leukopenia, Neutropenia, and Agranulocytosis [see Warnings and Precautions (5.9)] QT Interval Prolongation [see Warnings and Precautions (5.10)] Hyperprolactinemia [see Warnings and Precautions (5.11)] Seizures [see Warnings and Precautions (5.12)] Potential for Cognitive and Motor Impairment [see Warnings and Precautions (5.13)] Body Temperature Regulation [see Warnings and Precautions (5.14)] Dysphagia [see Warnings and Precautions (5.15)] The most common adverse reactions (≥5% and at least twice the rate of placebo) reported during the adjunctive therapy trial in bipolar I disorder in adults were somnolence and oral hypoesthesia.
The rates were lower at the 5 mg twice daily dose than the 10 mg twice daily dose for all of these most common adverse reactions. The adult information below is derived from a clinical trial database for asenapine consisting of over 5355 patients and/or healthy subjects exposed to one or more sublingual doses of asenapine. A total of 1427 asenapine-treated patients were treated for at least 24 weeks and 785 asenapine-treated patients had at least 52 weeks of exposure at therapeutic doses.
In a 3-week monotherapy trial, the most common adverse reactions (≥5% and at least twice the rate of placebo) reported in pediatric patients with bipolar I disorder treated with asenapine were somnolence, dizziness, dysgeusia, oral hypoesthesia, nausea, increased appetite, fatigue, and increased weight. No new major safety findings were reported from a 50-week, open-label, uncontrolled safety trial. A total of 651 pediatric patients were treated with asenapine.
Of these patients, 352 pediatric patients were treated with asenapine for at least 180 days and 58 pediatric patients treated with asenapine had at least 1 year of exposure. The safety of asenapine was evaluated in 403 pediatric patients with bipolar I disorder who participated in a 3-week, placebo-controlled, double-blind trial, of whom 302 patients received asenapine at fixed doses ranging from 2.5 mg to 10 mg twice daily. The stated frequencies of adverse reactions represent the proportion of individuals who experienced a treatment-emergent adverse event of the type listed.
A reaction was considered treatment emergent if it occurred for the first time or worsened while receiving therapy following baseline evaluation. The most commonly observed adverse reactions (incidence ≥5% and at least twice that for placebo) were ( 6.1 ): Bipolar I Disorder Pediatric Patients (Monotherapy): somnolence, dizziness, dysgeusia, oral paresthesia, nausea, increased appetite, fatigue, increased weight. • Bipolar I Disorder Adults (Adjunctive): somnolence, oral hypoesthesia. To report SUSPECTED ADVERSE REACTIONS, contact Alembic Pharmaceuticals Limited at 1-866-210-9797 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Monotherapy in Pediatric Patients with Bipolar Mania: The following findings are based on a 3-week , placebo-controlled trial for bipolar mania in which asenapine was administered at doses of 2.5 mg, 5 mg, or 10 mg twice daily.
Adverse React…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Antihypertensive Drugs: Asenapine may cause hypotension. ( 5.7 , 7.1 , 12.3 ) • Paroxetine (CYP2D6 substrate and inhibitor): Reduce paroxetine by half when used in combination with asenapine. ( 7.1 , 12.3 )
7.1Drugs Having Clinically Important Drug Interactions with Asenapine Table 12: Clinically Important Drug Interactions with Asenapine Concomitant Drug Name or Drug Class Clinical Rationale Clinical Recommendation Antihypertensive Drugs Because of its α 1 -adrenergic antagonism with potential for inducing hypotension, asenapine may enhance the effects of certain antihypertensive agents [see Warnings and Precautions (5.7)] . Monitor blood pressure and adjust dosage of antihypertensive drug accordingly. Strong CYP1A2 Inhibitors (e.g., Fluvoxamine) Asenapine is metabolized by CYP1A2.
Marginal increase of asenapine exposure was observed when asenapine is used with fluvoxamine at 25 mg administered twice daily [see Clinical Pharmacology (12.3)] . However, the tested fluvoxamine dose was suboptimal. Full therapeutic dose of fluvoxamine is expected to cause a greater increase in asenapine exposure.
Dosage reduction for asenapine based on clinical response may be necessary. CYP2D6 substrates and inhibitors (e.g., paroxetine) Asenapine may enhance the inhibitory effects of paroxetine on its own metabolism. Concomitant use of paroxetine with asenapine increased the paroxetine exposure by 2-fold as compared to use paroxetine alone [see Clinical Pharmacology (12.3)].
Reduce paroxetine dose by half when paroxetine is used in combination with asenapine.
7.2Drugs Having No Clinically Important Interactions with Asenapine No dosage adjustment of asenapine is necessary when administered concomitantly with paroxetine (see Table 12 in Drug Interactions (7.1) for paroxetine dosage adjustment), imipramine, cimetidine, valporate, lithium, or a CYP3A4 inducer (e.g., carbamazepine, phenytoin, rifampin). In addition, valproic acid and lithium pre-dose serum concentrations collected from an adjunctive therapy study were comparable between asenapine-treated patients and placebo-treated patients indicating a lack of effect of asenapine on valproic and lithium plasma levels.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: May cause extrapyramidal and/or withdrawal symptoms in neonates with third trimester exposure. ( 8.1 ) Pediatric Use: Safety and efficacy in the treatment of bipolar I disorder in patients less than 10 years of age have not been evaluated. ( 8.4 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to asenapine during pregnancy. For more information contact the National Pregnancy Registry for Atypical Antipsychotics at 1-866-961-2388 or visit http://womensmentalhealth.org/clinical-and-research-programs/pregnancyregistry/. Risk Summary Neonates exposed to antipsychotic drugs during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms.
Studies have not been conducted with asenapine in pregnant women. There are no available human data informing the drug-associated risk. The background risk of major birth defects and miscarriage for the indicated populations are unknown.
However, the background risk in the U.S. general population of major birth defects is 2 to 4% and of miscarriage is 15 to 20% of clinically recognized pregnancies. No teratogenicity was observed in animal reproduction studies with intravenous administration of asenapine to rats and rabbits during organogenesis at doses 0.7 and 0.4 times, respectively, the maximum recommended human dose (MRHD) of 10 mg sublingually twice daily. In a pre-and post-natal study in rats, intravenous administration of asenapine at doses up to 0.7 times the MRHD produced increases in post-implantation loss and early pup deaths, and decreases in subsequent pup survival and weight gain [see Data].
Advise pregnant women of the potential risk to a fetus. Clinical Considerations Fetal/Neonatal Adverse Reactions Extrapyramidal and/or withdrawal symptoms, including agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress and feeding disorder have been reported in neonates who were exposed to antipsychotic drugs during the third trimester of pregnancy. These symptoms have varied in severity.
Some neonates recovered within hours or days without specific treatment; others required prolonged hospitalization. Monitor neonates for extrapyramidal and/or withdrawal symptoms and manage symptoms appropriately. Data Animal Data In animal studies, asenapine increased post-implantation loss and decreased pup weight and survival at doses similar to or less than recommended clinical doses.
In these studies there was no increase in the incidence of structural abnormalities caused by asenapine. Asenapine was not teratogenic in reproduction studies in rats and rabbits at intravenous doses up to 1.5 mg/kg in rats and 0.44 mg/kg in rabbits administered during organogenesis. These doses are 0.7 and 0.4 times, respectively, the maximum recommended human dose (MRHD) of 10 mg twice daily given sublingually on a mg/m 2 basis.
Plasma levels of asenapine were measured in the rabbit study, and the area under the curve (AUC) at the highest dose tested was 2 times that in humans receiving the MRHD. In a study in which rats were treated from day 6 of gestation through day 21 postpartum with intravenous doses of asenapine of 0.3, 0.9, and 1.5 mg/kg/day (0.15, 0.4, and 0.7 times the MRHD of 10 mg twice daily given sublingually on a mg/m 2 basis), increases in post-implantation loss and early pup deaths were seen at all doses, and decreases in subsequent pup survival and weight gain were seen at the two higher doses.
A cross-fostering study indicated that the decreases in pup survival were largely due to prenatal drug effects. Increases in post-implantation loss and decreases in pup weight and survival were also seen when pregnant rats were dosed orally with asenapine.
8.2Lactation Risk Summary Lactation studies have not been conducted to assess the presence of asenapine in human milk, the effects of asenapine on the breastfed infant, or the effects of as…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to asenapine during pregnancy. For more information contact the National Pregnancy Registry for Atypical Antipsychotics at 1-866-961-2388 or visit http://womensmentalhealth.org/clinical-and-research-programs/pregnancyregistry/. Risk Summary Neonates exposed to antipsychotic drugs during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms.
Studies have not been conducted with asenapine in pregnant women. There are no available human data informing the drug-associated risk. The background risk of major birth defects and miscarriage for the indicated populations are unknown.
However, the background risk in the U.S. general population of major birth defects is 2 to 4% and of miscarriage is 15 to 20% of clinically recognized pregnancies. No teratogenicity was observed in animal reproduction studies with intravenous administration of asenapine to rats and rabbits during organogenesis at doses 0.7 and 0.4 times, respectively, the maximum recommended human dose (MRHD) of 10 mg sublingually twice daily. In a pre-and post-natal study in rats, intravenous administration of asenapine at doses up to 0.7 times the MRHD produced increases in post-implantation loss and early pup deaths, and decreases in subsequent pup survival and weight gain [see Data].
Advise pregnant women of the potential risk to a fetus. Clinical Considerations Fetal/Neonatal Adverse Reactions Extrapyramidal and/or withdrawal symptoms, including agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress and feeding disorder have been reported in neonates who were exposed to antipsychotic drugs during the third trimester of pregnancy. These symptoms have varied in severity.
Some neonates recovered within hours or days without specific treatment; others required prolonged hospitalization. Monitor neonates for extrapyramidal and/or withdrawal symptoms and manage symptoms appropriately. Data Animal Data In animal studies, asenapine increased post-implantation loss and decreased pup weight and survival at doses similar to or less than recommended clinical doses.
In these studies there was no increase in the incidence of structural abnormalities caused by asenapine. Asenapine was not teratogenic in reproduction studies in rats and rabbits at intravenous doses up to 1.5 mg/kg in rats and 0.44 mg/kg in rabbits administered during organogenesis. These doses are 0.7 and 0.4 times, respectively, the maximum recommended human dose (MRHD) of 10 mg twice daily given sublingually on a mg/m 2 basis.
Plasma levels of asenapine were measured in the rabbit study, and the area under the curve (AUC) at the highest dose tested was 2 times that in humans receiving the MRHD. In a study in which rats were treated from day 6 of gestation through day 21 postpartum with intravenous doses of asenapine of 0.3, 0.9, and 1.5 mg/kg/day (0.15, 0.4, and 0.7 times the MRHD of 10 mg twice daily given sublingually on a mg/m 2 basis), increases in post-implantation loss and early pup deaths were seen at all doses, and decreases in subsequent pup survival and weight gain were seen at the two higher doses.
A cross-fostering study indicated that the decreases in pup survival were largely due to prenatal drug effects. Increases in post-implantation loss and decreases in pup weight and survival were also seen when pregnant rats were dosed orally with asenapine.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and efficacy of asenapine in pediatric patients below the age of 10 years of age have not been evaluated. Bipolar I Disorder The safety and efficacy of asenapine as monotherapy in the treatment of bipolar I disorder were established in a 3week, placebo-controlled, double-blind trial of 403 pediatric patients 10 to 17 years of age, of whom 302 patients received asenapine at fixed doses ranging from 2.5 mg to 10 mg twice daily [see Dosage and Administration (2.3), Adverse Reactions (6.1), Clinical Pharmacology (12.3), and Clinical Studies (14.2)] .
In a Phase 1 study, pediatric patients aged 10 to 17 years appeared to be more sensitive to dystonia with initial dosing with asenapine when the recommended dose escalation schedule was not followed. Similar safety findings were reported from a 50-week, open-label, uncontrolled safety trial in pediatric patients with bipolar I disorder treated with asenapine monotherapy. The safety and efficacy of asenapine as adjunctive therapy in the treatment of bipolar I disorder have not been established in the pediatric population.
In general, the pharmacokinetics of asenapine in pediatric patients (10 to 17 years) and adults are similar [see Clinical Pharmacology (12.3)] . Juvenile Animal Data Subcutaneous administration of asenapine to juvenile rats for 56 days from day 14 of age to day 69 of age at 0.4, 1.2, and 3.2 mg/kg/day (0.2, 0.6 and 1.5 times the maximum recommended human dose of 10 mg twice daily given sublingually on a mg/m 2 basis) resulted in significant reduction in body weight gain in animals of both sexes at all dose levels from the start of dosing until weaning.
Body weight gain remained reduced in males to the end of treatment, however, recovery was observed once treatment ended. Neurobehavioral assessment indicated increased motor activity in animals at all dose levels following the completion of treatment, with the evidence of recovery in males. There was no recovery after the end of treatment in female activity pattern as late as day 30 following the completion of treatment (last retesting).
Therefore, a No Observed Adverse Effect Level (NOAEL) for the juvenile animal toxicity of asenapine could not be determined. There were no treatment-related effects on the startle response, learning/memory, organ weights, microscopic evaluations of the brain and, reproductive performance (except for minimally reduced conception rate and fertility index in males and females administered 1.2 and 3.2 mg/kg/day).
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of asenapine in the treatment of bipolar mania and another indication did not include sufficient numbers of patients aged 65 and over to determine whether or not they respond differently than younger patients. Of the approximately 2250 patients in pre-marketing clinical studies of asenapine, 1.1% (25) were 65 years of age or over. Multiple factors that might increase the pharmacodynamic response to asenapine, causing poorer tolerance or orthostasis, could be present in elderly patients, and these patients should be monitored carefully.
Based on a pharmacokinetic study in elderly patients, dosage adjustments are not recommended based on age alone [see Clinical Pharmacology (12.3)] . Elderly patients with dementia-related psychosis treated with asenapine are at an increased risk of death compared to placebo. Asenapine is not approved for the treatment of patients with dementia-related psychosis [see Boxed Warning] .
🆘 Overdosage ▾
10 OVERDOSAGE Human Experience: In adult pre-marketing clinical studies involving more than 3350 patients and/or healthy subjects, accidental or intentional acute over dosage of asenapine was identified in 3 patients. Among these few reported cases of overdose, the highest estimated ingestion of asenapine was 400 mg. Reported adverse reactions at the highest dosage included agitation and confusion.
Management of Overdosage: There is no specific antidote to asenapine. The possibility of multiple drug involvement should be considered. An electrocardiogram should be obtained and management of overdose should concentrate on supportive therapy, maintaining an adequate airway, oxygenation and ventilation, and management of symptoms.
Consult with a Certified Poison Control Center for up-to-date guidance and advice on the management of overdosage (1-800-222-1222.) Hypotension and circulatory collapse should be treated with appropriate measures, such as intravenous fluids and/or sympathomimetic agents (epinephrine and dopamine should not be used, since beta stimulation may worsen hypotension in the setting of asenapine-induced alpha blockade). In case of severe extrapyramidal symptoms, anticholinergic medication should be administered. Close medical supervision and monitoring should continue until the patient recovers.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of asenapine in bipolar I disorder is unknown.
12.2Pharmacodynamics Asenapine exhibits high affinity for serotonin 5-HT 1A , 5-HT 1B , 5-HT 2A , 5-HT 2B , 5-HT 2C , 5-HT 5A , 5-HT 6 , and 5-HT 7 receptors (Ki values of 2.5, 2.7, 0.07, 0.18, 0.03, 1.6, 0.25, and 0.11 nM, respectively), dopamine D 2A , D 2B , D 3 , D 4 , and D 1 receptors (Ki values of 1.3, 1.4, 0.42, 1.1, and 1.4 nM, respectively), α 1A , α 2A , α 2B , and α 2C -adrenergic receptors (Ki values of 1.2, 1.2, 0.33 and 1.2 nM, respectively), and histamine H 1 receptors (Ki value 1 nM), and moderate affinity for H 2 receptors (Ki value of 6.2 nM).
In in vitro assays asenapine acts as an antagonist at these receptors. Asenapine has no appreciable affinity for muscarinic cholinergic receptors (e.g., Ki value of 8128 nM for M 1 ).
12.3Pharmacokinetics Following a single 5 mg dose of asenapine, the mean C max was approximately 4 ng/mL and was observed at a mean t max of 1 hour. Elimination of asenapine is primarily through direct glucuronidation by UGT1A4 and oxidative metabolism by cytochrome P450 isoenzymes (predominantly CYP1A2). Following an initial more rapid distribution phase, the mean terminal half-life is approximately 24 hrs.
With multiple-dose twice-daily dosing, steady-state is attained within 3 days. Overall, steady-state asenapine pharmacokinetics are similar to single-dose pharmacokinetics. Absorption: Following sublingual administration, asenapine is rapidly absorbed with peak plasma concentrations occurring within 0.5 to 1.5 hours.
The absolute bioavailability of sublingual asenapine at 5 mg is 35%. Increasing the dose from 5 mg to 10 mg twice daily (a two-fold increase) results in less than linear (1.7 times) increases in both the extent of exposure and maximum concentration. The absolute bioavailability of asenapine when swallowed is low (<2% with an oral tablet formulation).
The intake of water several (2 or 5) minutes after asenapine administration resulted in decreased asenapine exposure. Therefore, eating and drinking should be avoided for 10 minutes after administration [see Dosage and Administration (2.1)] . Distribution: Asenapine is rapidly distributed and has a large volume of distribution (approximately 20 to 25 L/kg), indicating extensive extravascular distribution.
Asenapine is highly bound (95%) to plasma proteins, including albumin and α 1 -acid glycoprotein. Metabolism and Elimination: Direct glucuronidation by UGT1A4 and oxidative metabolism by cytochrome P450 isoenzymes (predominantly CYP1A2) are the primary metabolic pathways for asenapine. Asenapine is a high clearance drug with a clearance after intravenous administration of 52 L/h.
In this circumstance, hepatic clearance is influenced primarily by changes in liver blood flow rather than by changes in the intrinsic clearance, i.e., the metabolizing enzymatic activity. Following an initial more rapid distribution phase, the terminal half-life of asenapine is approximately 24 hours. Steady-state concentrations of asenapine are reached within 3 days of twice daily dosing.
After administration of a single dose of [ 14 C]-labeled asenapine, about 90% of the dose was recovered; approximately 50% was recovered in urine, and 40% recovered in feces. About 50% of the circulating species in plasma have been identified. The predominant species was asenapine N + -glucuronide; others included N-desmethylasenapine, N-desmethylasenapine N-carbamoyl glucuronide, and unchanged asenapine in smaller amounts.
Asenapine activity is primarily due to the parent drug. In vitro studies indicate that asenapine is a substrate for UGT1A4, CYP1A2 and to a lesser extent CYP3A4 and CYP2D6. Asenapine is a weak inhibitor of CYP2D6.
Asenapine does not cause induction of CYP1A2 or CYP3A4 activities in cultured human hepatocytes. Coadministration of asenapine with known inhibitors, inducers or substrates of these metabolic pathways has been st…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of asenapine in bipolar I disorder is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Asenapine sublingual tablets are supplied as: 2.5-mg Tablets: White to off white, round tablets debossed with ‘L’ on one side and ‘70’ on the other side. Cartons of 60 - 6 blister cards of 10 tablets each NDC 62332-544-60 Cartons of 100 - 10 blister cards of 10 tablets each NDC 62332-544-31 5-mg Tablets: White to off white, round tablets debossed with “464” on one side and plain on other side. Cartons of 60 - 6 blister cards of 10 tablets each NDC 62332-198-60 Cartons of 100 - 10 blister cards of 10 tablets each NDC 62332-198-31 10-mg Tablets: White to off white, round tablets debossed with “465” on one side and plain on other side.
Cartons of 60 - 6 blister cards of 10 tablets each NDC 62332-199-60 Cartons of 100 - 10 blister cards of 10 tablets each NDC 62332-199-31 Storage Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Asenapine sublingual tablet contains asenapine maleate which is an atypical antipsychotic that is available for sublingual administration. Asenapine belongs to the class dibenzo-oxepino pyrroles. The chemical designation is (3a RS ,12b RS )-5-Chloro-2-methyl-2,3,3a,12b-tetrahydro-1 H dibenzo[2,3:6,7]oxepino[4,5- c ]pyrrole (2 Z )-2 butenedioate (1:1).
Its molecular formula is C 17 H 16 ClNO⋅C 4 H 4 O 4 and its molecular weight is 401.84 (free base: 285.8). The chemical structure is: Asenapine maleate is off-white to white powder. Asenapine is supplied for sublingual administration in tablets containing 2.5-mg, 5-mg or 10-mg asenapine; inactive ingredients include butylated hydroxy anisole, butylated hydroxy toluene, low-substituted hydroxypropyl cellulose, mannitol, povidone, sodium stearyl fumarate. asenapine-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Instructions for Use). Dosage and Administration Counsel patients on proper sublingual administration of asenapine and advise them to read the FDA-approved patient labeling (Instructions for Use). When initiating treatment with asenapine, provide dosage escalation instructions [see Dosage and Administration (2)].
Hypersensitivity Reactions Counsel patients on the signs and symptoms of a serious allergic reaction (e.g., difficulty breathing, itching, swelling of the face, tongue or throat, feeling lightheaded etc.) and to seek immediate emergency assistance if they develop any of these signs and symptoms [see Contraindications (4), Warnings and Precautions (5.6) and Adverse Reactions (6)] . Application Site Reactions Inform patients that application site reactions, primarily in the sublingual area, including oral ulcers, blisters, peeling/sloughing and inflammation have been reported.
Instruct patients to monitor for these reactions [see Adverse Reactions (6.2)]. Inform patients that numbness or tingling of the mouth or throat may occur directly after administration of asenapine and usually resolves within 1 hour [see Adverse Reactions (6.1)] . Neuroleptic Malignant Syndrome Counsel patients about a potentially fatal symptom complex sometimes referred to as Neuroleptic Malignant Syndrome (NMS) that has been reported in association with administration of antipsychotic drugs.
Patients should contact their health care provider or report to the emergency room if they experience the following signs and symptoms of NMS, including hyperpyrexia, muscle rigidity, altered mental status, and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis, and cardiac dysrhythmia) [see Warnings and Precautions (5.3)] . Tardive Dyskinesia Counsel patients on the signs and symptoms of tardive dyskinesia and to contact their health care provider if these abnormal movements occur [see Warnings and Precautions (5.4)].
Metabolic Changes ( Hyperglycemia and Diabetes Mellitus, Dyslipidemia, and Weight Gain) Educate patients about the risk of metabolic changes, how to recognize symptoms of hyperglycemia (high blood sugar) and diabetes mellitus, and the need for specific monitoring, including blood glucose, lipids, and weight [see Warnings and Precautions (5.5)]. Orthostatic Hypotension Educate patients about the risk of orthostatic hypotension (symptoms include feeling dizzy or lightheaded upon standing) especially early in treatment, and also at times of re-initiating treatment or increases in dose [see Warnings and Precautions (5.7)] .
Leukopenia/Neutropenia Advise patients with a pre-existing low WBC or a history of drug induced leukopenia/neutropenia they should have their CBC monitored while taking asenapine [see Warnings and Precautions (5.9)] . Hyperprolactinemia Counsel patients on the signs and symptoms of hyperprolactinemia and to contact their health care provider if these abnormalities occur [see Warnings and Precautions (5.11)]. Interference with Cognitive and Motor Performance Caution patients about performing activities requiring mental alertness, such as operating hazardous machinery or operating a motor vehicle, until they are reasonably certain that asenapine therapy does not affect them adversely [see Warnings and Precautions (5.13)] .
Heat Exposure and Dehydration Counsel patients regarding appropriate care in avoiding overheating and dehydration [see Warnings and Precautions (5.14)] . Concomitant Medications Advise patients to inform their health care provider if they are taking, or plan to take, any prescription or over-the-counter medications since there is a potential for interactions [see Drug Interactions (7.1)] . Pregnancy Advise patients that asenapine may cause fetal harm as well as extrapyramidal and/or withdrawal symptoms in a neonate.
Advise patients to notify their healthcare provider with a…