
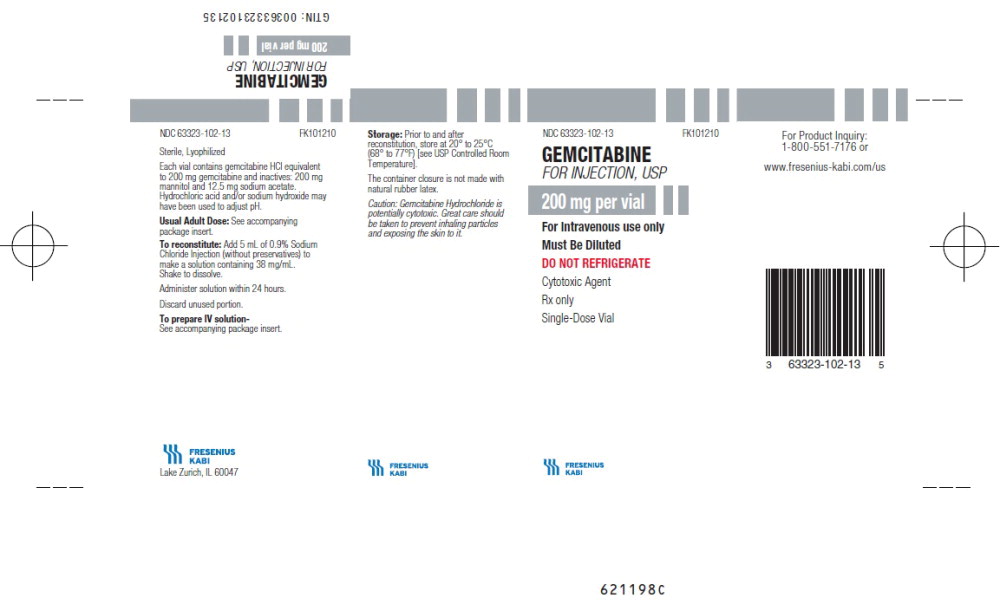
GEMCITABINE 200 mg/5mL Injection, Powder, Lyophilized, For Solution — NDC 63323-102-13 (Billing 63323-0102-13)
This is a package of GEMCITABINE 200 mg/5mL Injection, Powder, Lyophilized, For Solution from Fresenius Kabi USA, LLC, marketed since Jul 2011 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 63323-102-13 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 63323 labeler · 102 product · 13 package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC)
- 0363323125530, 0363323126032, 0363323102135
- Medicaid fills, this package
- 51 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Other active recalls for Gemcitabine (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 025728
- GCN: 38530
- GPI-14 (Medi-Span): 21300034102110
- HICL (First Databank): 010798
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 1719000
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Nucleoside Metabolic Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Gemcitabine is used in combination with carboplatin to treat ovarian cancer (cancer that begins in the female reproductive organs where eggs are formed) that returned at least 6 months after finishing a previous treatment. It also used in combination with paclitaxel (Abraxane®, Taxol®) to treat breast cancer that has not improved or that has worsened after treatment with other medications. Gemcitabine is used in combination with cisplatin to treat a type of lung cancer (non-small cell lung cancer; NSCLC) that has spread to other parts of the body and cannot be treated with surgery. Gemcitabine...
Read the full MedlinePlus article ↗- It's a chemotherapy medicine. The IV forms treat ovarian, breast, non-small cell lung and pancreatic cancers, often alongside other cancer drugs. A separate product, Inlexzo, is pl...
- The IV forms are given by a healthcare professional as an infusion of about 30 minutes on set days of a treatment cycle. Inlexzo is placed in and removed from the bladder by a trai...
- Nausea and vomiting, low blood counts, fever, rash, swelling, shortness of breath and changes in liver or urine tests are common. Your blood is checked before each dose to catch pr...
- Call for new or unexplained shortness of breath, fever or signs of infection, unusual bleeding, severe headache, seizure, confusion, vision changes, or a drop in urine. Get emergen...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Gemcitabine — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $36.58 | $182.92 / 5 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9201 | $2.884 / J9201 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 63323-0102-13 You're viewing this Main listing | 1 VIAL, SINGLE-DOSE in 1 BOX / 5 mL in 1 VIAL, SINGLE-DOSE | 2011-07-26 | — | Active |
| 63323-0102-94 63323-102-94 | 1 VIAL, SINGLE-DOSE in 1 BOX / 5 mL in 1 VIAL, SINGLE-DOSE | 2011-07-26 | — | Active |
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of GEMCITABINE 200 mg/5mL Injection, Powder, Lyophilized, For Solution?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Gemcitabine 38 mg/mL 00409-0185-01 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Gemcitabine 200 mg 16714-0909-01 | NorthStar | 1 vial | — | AP | FDA listed | — |
| gemcitabine 200 mg/5mL 25021-0234-10 | Sagent | 1 vial | — | AP | FDA listed | — |
| gemcitabine 200 mg/5mL 55111-0686-07 | Dr. | 1 vial | — | AP | FDA listed | — |
| Gemcitabine 200 mg/5mLthis 63323-0102-13 | Fresenius | 1 vial | — | AP | FDA listed | — |
| gemcitabine hydrochloride 200 mg/5mL 68083-0148-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Gemcitabine 200 mg 71288-0113-10 | Meitheal | 1 vial | — | AP | FDA listed | — |
| Gemcitabine hydrochloride 200 mg/5mL 82511-0008-20 | Teyro | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 4550K0SC9B
Sodium acetate is a salt derived from acetic acid. It acts as a buffer to help maintain the medicine's pH stability and may serve as a preservative or solubilizer in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Fresenius Kabi USA, LLC labeler code 63323
- Sodium Bicarbonate 84 mg/mL Injection, Solution NDC 63323-089-50
- Sodium Chloride 2.5 meq/mL Injection, Solution, Concentrate NDC 63323-090-20
- Sodium Chloride 4 meq/mL Injection, Solution, Concentrate NDC 63323-093-30
- Sodium Chloride 4 meq/mL Injection, Solution, Concentrate NDC 63323-095-61
- Sodium Chloride 4 meq/mL Injection, Solution, Concentrate NDC 63323-099-63
- Doxorubicin Hydrochloride 2 mg/mL Injection, Solution NDC 63323-101-61
- Cisplatin 1 mg/mL Injection, Solution NDC 63323-103-51
- Etoposide 20 mg/mL Injection, Solution NDC 63323-104-05
- magnesium sulfate 40 mg/mL Injection, Solution NDC 63323-106-01
- magnesium sulfate 80 mg/mL Injection, Solution NDC 63323-107-05
- Magnesium Sulfate in 5% Dextrose Magnesium Sulfate Heptahydrate 1 g/100mL Injection, Solution NDC 63323-108-01
- Pentam 300 PENTAMIDINE ISETHIONATE 300 mg/3mL Injection, Powder, Lyophilized, For Solution NDC 63323-113-10
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Gemcitabine for Injection is a nucleoside metabolic inhibitor indicated: in combination with carboplatin, for the treatment of advanced ovarian cancer that has relapsed at least 6 months after completion of platinum-based therapy. ( 1.1 ) in combination with paclitaxel, for first-line treatment of metastatic breast cancer after failure of prior anthracycline-containing adjuvant chemotherapy, unless anthracyclines were clinically contraindicated. ( 1.2 ) in combination with cisplatin, for the treatment of non-small cell lung cancer.
( 1.3 ) as a single agent for the treatment of pancreatic cancer. ( 1.4 )
1.1Ovarian Cancer Gemcitabine for Injection in combination with carboplatin is indicated for the treatment of patients with advanced ovarian cancer that has relapsed at least 6 months after completion of platinum-based therapy.
1.2Breast Cancer Gemcitabine for Injection in combination with paclitaxel is indicated for the first-line treatment of patients with metastatic breast cancer after failure of prior anthracycline-containing adjuvant chemotherapy, unless anthracyclines were clinically contraindicated.
1.3Non-Small Cell Lung Cancer Gemcitabine for Injection in combination with cisplatin is indicated for the first-line treatment of patients with inoperable, locally advanced (Stage IIIA or IIIB) or metastatic (Stage IV) non-small cell lung cancer (NSCLC).
1.4Pancreatic Cancer Gemcitabine for Injection is indicated as first-line treatment for patients with locally advanced (nonresectable Stage II or Stage III) or metastatic (Stage IV) adenocarcinoma of the pancreas. Gemcitabine for Injection is indicated for patients previously treated with fluorouracil.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Gemcitabine for Injection is for intravenous use only. Ovarian Cancer: 1,000 mg/m 2 over 30 minutes on Days 1 and 8 of each 21-day cycle. ( 2.1 ) Breast Cancer: 1,250 mg/m 2 over 30 minutes on Days 1 and 8 of each 21-day cycle.
( 2.2 ) Non-Small Cell Lung Cancer: 1,000 mg/m 2 over 30 minutes on Days 1, 8, and 15 of each 28-day cycle or 1,250 mg/m 2 over 30 minutes on Days 1 and 8 of each 21-day cycle. ( 2.3 ) Pancreatic Cancer: 1,000 mg/m 2 over 30 minutes once weekly for the first 7 weeks, then one week rest, then once weekly for 3 weeks of each 28-day cycle. ( 2.4 )
2.1Ovarian Cancer Recommended Dose and Schedule The recommended dosage of Gemcitabine for Injection is 1,000 mg/m 2 intravenously over 30 minutes on Days 1 and 8 of each 21-day cycle in combination with carboplatin AUC 4 administered intravenously on Day 1 after Gemcitabine for Injection administration. Refer to carboplatin prescribing information for additional information. Dosage Modifications Recommended Gemcitabine for Injection dosage modifications for myelosuppression are described in Tables 1 and 2 [see Warnings and Precautions ( 5.2 )] .
Refer to the recommended dosage modifications for non-hematologic adverse reactions [see Dosage and Administration ( 2.5 )]. Table 1: Recommended Dosage Modifications for Gemcitabine for Injection for Myelosuppression on Day of Treatment in Ovarian Cancer Treatment Day Absolute Neutrophil Count (x 10 6 /L) Platelet Count (x 10 6 /L) Dosage Modification Day 1 Greater than or equal to 1,500 And Greater than or equal to 100,000 None Less than1,500 Or Less than 100,000 Delay Treatment Cycle Day 8 Greater than or equal to 1,500 And Greater than or equal to 100,000 None 1,000 to 1,499 Or 75,000 to 99,999 50% of full dose Less than1,000 Or Less than 75,000 Hold Table 2: Recommended Dosage Modifications for Gemcitabine for Injection for Myelosuppression in Previous Cycle in Ovarian Cancer Occurrence Myelosuppression During Treatment Cycle Dosage Modification Initial Occurrence Absolute neutrophil count less than 500 x 10 6 /L for more than 5 days or Absolute neutrophil count less than 100 x 10 6 /L for more than 3 days or Febrile neutropenia or Platelets less than 25,000x10 6 /L or Cycle delay for more than one week due to toxicity Permanently reduce Gemcitabine for Injection 800 mg/m 2 on Days 1 and 8 Subsequent Occurrence If any of the above toxicities occur after the initial dose reduction Permanently reduce Gemcitabine for Injection to 800 mg/m 2 on Day 1 only
2.2Breast Cancer Recommended Dose and Schedule The recommended dosage of Gemcitabine for Injection is 1,250 mg/m 2 intravenously over 30 minutes on Days 1 and 8 of each 21-day cycle in combination with paclitaxel 175 mg/m 2 administered as a 3-hour intravenous infusion on Day 1 before Gemcitabine for Injection administration. Refer to paclitaxel prescribing information for additional information. Dosage Modifications Recommended Gemcitabine for Injection dosage modifications for myelosuppression are described in Table 3 [see Warnings and Precautions ( 5.2 )].
Refer to the recommended dosage modifications for non-hematologic adverse reactions [see Dosage and Administration ( 2.5 )]. Table 3: Recommended Dosage Modifications for Gemcitabine for Injection for Myelosuppression on Day of Treatment in Breast Cancer Treatment Day Absolute Neutrophil Count (x 10 6 /L) Platelet Count (x 10 6 /L) Dosage Modification Day 1 Greater than or equal to 1,500 And Greater than or equal to 100,000 None Less than 1,500 Or Less than 100,000 Hold Day 8 Greater than or equal to 1,200 And Greater than 75,000 None 1,000 to 1,199 Or 50,000 to 75,000 75% of full dose 700 to 999 And Greater than or equal to 50,000 50% of full dose Less than 700 Or Less than 50,000 Hold
2.3Non-Small Cell Lung Cancer Recommended Dose and Schedule 28-day schedule The recommended dosage of Gemcitabine for Injection is 1,000 mg/m 2 intravenously over 30 minutes on Days 1, 8, and 15 of eac… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For injection: 200 mg gemcitabine, 1 g gemcitabine or 2 g gemcitabine as a sterile white to off-white lyophilized powder in a single-dose vial for reconstitution. For injection: 200 mg, 1 g or 2 g lyophilized powder or cake in single-dose vials for reconstitution. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Gemcitabine for Injection is contraindicated in patients with a known hypersensitivity to gemcitabine. Reactions include anaphylaxis [see Adverse Reactions ( 6.1 )]. Patients with a known hypersensitivity to gemcitabine. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Schedule-Dependent Toxicity: Increased toxicity with infusion time greater than 60 minutes or dosing more frequently than once weekly. ( 5.1 ) Myelosuppression: Monitor for myelosuppression prior to each cycle and reduce or withhold dose for severe myelosuppression. ( 5.2 , 5.7 ) Pulmonary Toxicity and Respiratory Failure: Discontinue gemcitabine for unexplained dyspnea or other evidence of severe pulmonary toxicity.
( 5.3 ) Hemolytic Uremic Syndrome (HUS): Monitor renal function prior to initiation and during treatment. Discontinue gemcitabine for HUS or severe renal impairment. ( 5.4 ) Hepatic Toxicity: Monitor hepatic function prior to initiation and during treatment.
Discontinue gemcitabine for severe hepatic toxicity. ( 5.5 ) Embryo-Fetal Toxicity: Can cause fetal harm. Advise females and males of reproductive potential to use effective contraception.
( 5.6 , 8.1 ) Exacerbation of Radiation Therapy Toxicity: May cause severe and life-threatening toxicity when administered during or within 7 days of radiation therapy. ( 5.7 ) Capillary Leak Syndrome: Discontinue gemcitabine. ( 5.8 ) Posterior Reversible Encephalopathy Syndrome (PRES): Discontinue gemcitabine.
( 5.9 )
5.1Schedule-Dependent Toxicity In clinical trials evaluating the maximum tolerated dose of gemcitabine, prolongation of the infusion time beyond 60 minutes or more frequent than weekly dosing resulted in an increased incidence of clinically significant hypotension, severe flu-like symptoms, myelosuppression, and asthenia. The half-life of gemcitabine is influenced by the length of the infusion [see Clinical Pharmacology ( 12.3 )] . Refer to the recommended gemcitabine dosage [see Dosage and Administration ( 2.1 , 2.2 , 2.3 , 2.4 )].
5.2Myelosuppression Myelosuppression manifested by neutropenia, thrombocytopenia, and anemia occurs with gemcitabine as a single agent and the risks are increased when gemcitabine is combined with other cytotoxic drugs. In clinical trials, Grade 3-4 neutropenia, anemia, and thrombocytopenia occurred in 25%, 8%, and 5%, respectively of the 979 patients who received single agent gemcitabine. The frequencies of Grade 3-4 neutropenia, anemia, and thrombocytopenia varied from 48% to 71%, 8% to 28%, and 5% to 55%, respectively, in patients receiving gemcitabine in combination with another drug [see Adverse Reactions ( 6.1 )].
Prior to each dose of gemcitabine, obtain a complete blood count (CBC) with a differential and a platelet count. Modify the dosage as recommended [see Dosage and Administration ( 2.1 , 2.2 , 2.3 , 2.4 )].
5.3Pulmonary Toxicity and Respiratory Failure Pulmonary toxicity, including interstitial pneumonitis, pulmonary fibrosis, pulmonary edema, and adult respiratory distress syndrome (ARDS), has been reported. In some cases, these pulmonary events can lead to fatal respiratory failure despite the discontinuation of therapy. The onset of pulmonary symptoms may occur up to 2 weeks after the last dose of gemcitabine [see Adverse Reactions ( 6.1 , 6.2 )] .
Permanently discontinue gemcitabine in patients who develop unexplained dyspnea, with or without bronchospasm, or evidence of severe pulmonary toxicity.
5.4Hemolytic Uremic Syndrome Hemolytic uremic syndrome (HUS), including fatalities from renal failure or the requirement for dialysis, can occur with gemcitabine. In clinical trials, HUS occurred in 0.25% of 2429 patients. Most fatal cases of renal failure were due to HUS [see Adverse Reactions ( 6.1 )].
Serious cases of thrombotic microangiopathy other than HUS have been reported with gemcitabine [see Adverse Reactions ( 6.2 )]. Assess renal function prior to initiation of gemcitabine and periodically during treatment. Consider the diagnosis of HUS in patients who develop anemia with evidence of microangiopathic hemolysis; increased bilirubin or LDH; reticulocytosis; severe thrombocytopenia; or renal failure (increased serum creatinine or BUN).
Permanently discontinue gemcitabine in patien… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Hypersensitivity [see Contraindications ( 4 )] Schedule-Dependent Toxicity [see Warnings and Precautions ( 5.1 )] Myelosuppression [see Warnings and Precautions ( 5.2 )] Pulmonary Toxicity and Respiratory Failure [see Warnings and Precautions ( 5.3 )] Hemolytic Uremic Syndrome [see Warnings and Precautions ( 5.4 )] Hepatic Toxicity [see Warnings and Precautions ( 5.5 )] Exacerbation of Radiation Therapy Toxicity [see Warnings and Precautions ( 5.7 )] Capillary Leak Syndrome [see Warnings and Precautions ( 5.8 )] Posterior Reversible Encephalopathy Syndrome [see Warnings and Precautions ( 5.9 )] The most common adverse reactions for the single agent (≥20%) are nausea/vomiting, anemia, increased aspartate aminotransferase (AST), increased alanine aminotransferase (ALT), neutropenia, increased alkaline phosphatase, proteinuria, fever, hematuria, rash, thrombocytopenia, dyspnea, and edema.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Fresenius Kabi USA, LLC at 1-800- 551-7176 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Single Agent The data described below reflect exposure to gemcitabine as a single agent administered at doses between 800 mg/m 2 to 1,250 mg/m 2 intravenously over 30 minutes once weekly in 979 patients with various malignancies.
The most common (≥20%) adverse reactions of single agent gemcitabine are nausea/vomiting, anemia, increased alanine aminotransferase (ALT), increased aspartate aminotransferase (AST), neutropenia, increased alkaline phosphatase, proteinuria, fever, hematuria, rash, thrombocytopenia, dyspnea, and edema. The most common (≥5%) Grade 3 or 4 adverse reactions were neutropenia, nausea/vomiting, increased ALT, increased alkaline phosphatase, anemia, increased AST, and thrombocytopenia. Approximately 10% of the 979 patients discontinued gemcitabine due to adverse reactions.
Adverse reactions resulting in discontinuation of gemcitabine in 2% of 979 patients were cardiovascular adverse reactions (myocardial infarction, cerebrovascular accident, arrhythmia, and hypertension) and adverse reactions resulting in discontinuation of gemcitabine in <1% of 979 patients were anemia, thrombocytopenia, hepatic dysfunction, renal dysfunction, nausea/vomiting, fever, rash, dyspnea, hemorrhage, infection, stomatitis, somnolence, flu-like syndrome, and edema. Tables 5 and 6 present the incidence of selected adverse reactions and laboratory abnormalities reported in patients with various malignancies receiving single agent gemcitabine across 5 clinical trials.
Additional clinically significant adverse reactions are provided following Table 6 . Table 5: Selected Adverse Reactions Occurring in ≥10% of Patients Receiving Single Agent Gemcitabine a a Grade based on criteria from the World Health Organization (WHO). b For approximately 60% of patients, non-laboratory adverse reactions were graded only if assessed to be possibly drug-related. c N=699-974; all patients with laboratory or non-laboratory data. Adverse Reactions b Gemcitabine c All Grades (%) Grade 3 (%) Grade 4 (%) Nausea and Vomiting 69 13 1 Fever 41 2 0 Rash 30 <1 0 Dyspnea 23 3 <1 Diarrhea 19 1 0 Hemorrhage 17 <1 <1 Infection 16 1 <1 Alopecia 15 <1 0 Stomatitis 11 <1 0 Somnolence 11 <1 <1 Paresthesias 10 <1 0 Table 6: Selected Laboratory Abnormalities Occurring in Patients Receiving Single Agent Gemcitabine a a Grade based on criteria from the WHO. b Regardless of causality. c N=699-974; all patients with laboratory or non-laboratory data.
Laboratory Abnormality b Gemcitabine c All Grades (%) Grade 3 (%) Grade 4 (%) Hematologic Anemia 6… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on animal data and its mechanism of action, gemcitabine can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology ( 12.1 )]. There are no available data on the use of gemcitabine in pregnant women. In animal reproduction studies, gemcitabine was teratogenic, embryotoxic, and fetotoxic in mice and rabbits (see Data).
Advise pregnant women of the potential risk to a fetus [see Use in Special Populations ( 8.3 )]. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies 2-4% and 15-20% respectively. Data Animal Data Gemcitabine is embryotoxic in mice.
Daily dosing of gemcitabine to pregnant mice increased the incidence of fetal malformation (cleft palate, incomplete ossification) at doses of 1.5 mg/kg/day [approximately 0.005 times the 1000 mg/m 2 clinical dose based on body surface area (BSA)]. Gemcitabine was embryotoxic and fetotoxic in rabbits. Daily dosing of gemcitabine to pregnant rabbits resulted in fetotoxicity (decreased fetal viability, reduced litter sizes, and developmental delays) and increased the incidence of fetal malformations (fused pulmonary artery, absence of gall bladder) at doses of 0.1 mg/kg/day (approximately 0.002 times the 1000 mg/m 2 clinical dose based on BSA).
8.2Lactation Risk Summary There is no information regarding the presence of gemcitabine or its metabolites in human milk, or their effects on the breastfed infant or on milk production. Due to the potential for serious adverse reactions in breastfed infants from gemcitabine, advise women not to breastfeed during treatment with gemcitabine and for at least one week following the last dose.
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to initiating gemcitabine [see Use in Specific Populations ( 8.1 )]. Contraception Gemcitabine can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations ( 8.1 )]. Females Because of the potential for genotoxicity, advise females of reproductive potential to use effective contraception during treatment with gemcitabine and for 6 months after the final dose of gemcitabine.
Males Because of the potential for genotoxicity, advise males with female partners of reproductive potential to use effective contraception during treatment with gemcitabine and for 3 months after the final dose [see Nonclinical Toxicology ( 13.1 )]. Infertility Males Based on animal studies, gemcitabine may impair fertility in males of reproductive potential [see Nonclinical Toxicology ( 13.1 )] . It is not known whether these effects on fertility are reversible.
8.4Pediatric Use The safety and effectiveness of gemcitabine have not been established in pediatric patients. The safety and pharmacokinetics of gemcitabine were evaluated in a trial in pediatric patients with refractory leukemia. The maximum tolerated dose was 10 mg/m 2 /min for 360 minutes weekly for three weeks followed by a one-week rest period.
The safety and activity of gemcitabine were evaluated in a trial of pediatric patients with relapsed acute lymphoblastic leukemia (22 patients) and acute myelogenous leukemia (10 patients) at a dose of 10 mg/m 2 /min administered over 360 minutes weekly for three weeks followed by a one-week rest period. Patients with M1 or M2 bone marrow on Day 28 who did not experience unacceptable toxicity were eligible to receive a maximum of one additional four-week course. Toxicities observed included myelosuppression, febrile neutropenia, increased serum transaminases, nausea, and rash/desquamation.
No meaningful clinical activity was observed in this trial.
8.5Geriatric Use In clinical studies which enrolled 979 patients with various malignancies who received single agent gemcitabine, no overall differences in safety… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on animal data and its mechanism of action, gemcitabine can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology ( 12.1 )]. There are no available data on the use of gemcitabine in pregnant women. In animal reproduction studies, gemcitabine was teratogenic, embryotoxic, and fetotoxic in mice and rabbits (see Data).
Advise pregnant women of the potential risk to a fetus [see Use in Special Populations ( 8.3 )]. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies 2-4% and 15-20% respectively. Data Animal Data Gemcitabine is embryotoxic in mice.
Daily dosing of gemcitabine to pregnant mice increased the incidence of fetal malformation (cleft palate, incomplete ossification) at doses of 1.5 mg/kg/day [approximately 0.005 times the 1000 mg/m 2 clinical dose based on body surface area (BSA)]. Gemcitabine was embryotoxic and fetotoxic in rabbits. Daily dosing of gemcitabine to pregnant rabbits resulted in fetotoxicity (decreased fetal viability, reduced litter sizes, and developmental delays) and increased the incidence of fetal malformations (fused pulmonary artery, absence of gall bladder) at doses of 0.1 mg/kg/day (approximately 0.002 times the 1000 mg/m 2 clinical dose based on BSA).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of gemcitabine have not been established in pediatric patients. The safety and pharmacokinetics of gemcitabine were evaluated in a trial in pediatric patients with refractory leukemia. The maximum tolerated dose was 10 mg/m 2 /min for 360 minutes weekly for three weeks followed by a one-week rest period.
The safety and activity of gemcitabine were evaluated in a trial of pediatric patients with relapsed acute lymphoblastic leukemia (22 patients) and acute myelogenous leukemia (10 patients) at a dose of 10 mg/m 2 /min administered over 360 minutes weekly for three weeks followed by a one-week rest period. Patients with M1 or M2 bone marrow on Day 28 who did not experience unacceptable toxicity were eligible to receive a maximum of one additional four-week course. Toxicities observed included myelosuppression, febrile neutropenia, increased serum transaminases, nausea, and rash/desquamation.
No meaningful clinical activity was observed in this trial.
🧓 Geriatric Use ▾
8.5Geriatric Use In clinical studies which enrolled 979 patients with various malignancies who received single agent gemcitabine, no overall differences in safety were observed between patients aged 65 and older and younger patients, with the exception of a higher rate of Grade 3-4 thrombocytopenia in older patients as compared to younger patients. In a randomized trial in women with ovarian cancer (Study 1), 175 women received gemcitabine with carboplatin, of which 29% were age 65 years or older. Similar effectiveness was observed between older and younger women.
There was significantly higher Grade 3-4 neutropenia in women 65 years of age or older [see Dosage and Administration ( 2.1 )]. Gemcitabine clearance is affected by age; however, there are no recommended dose adjustments based on patients' age [see Clinical Pharmacology ( 12.3 )] .
🆘 Overdosage ▾
10 OVERDOSAGE There is no known antidote for overdoses of gemcitabine. Myelosuppression, paresthesias, and severe rash were the principal toxicities seen when a single dose as high as 5,700 mg/m 2 was administered by intravenous infusion over 30 minutes every 2 weeks to several patients in a dose-escalation study. In the event of suspected overdose, monitor with appropriate blood counts and provide supportive therapy, as necessary.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Gemcitabine kills cells undergoing DNA synthesis and blocks the progression of cells through the G1/S-phase boundary. Gemcitabine is metabolized by nucleoside kinases to diphosphate (dFdCDP) and triphosphate (dFdCTP) nucleosides. Gemcitabine diphosphate inhibits ribonucleotide reductase, an enzyme responsible for catalyzing the reactions that generate deoxynucleoside triphosphates for DNA synthesis, resulting in reductions in deoxynucleotide concentrations, including dCTP.
Gemcitabine triphosphate competes with dCTP for incorporation into DNA. The reduction in the intracellular concentration of dCTP by the action of the diphosphate enhances the incorporation of gemcitabine triphosphate into DNA (self-potentiation). After the gemcitabine nucleotide is incorporated into DNA, only one additional nucleotide is added to the growing DNA strands, which eventually results in the initiation of apoptotic cell death.
12.3Pharmacokinetics The pharmacokinetics of gemcitabine were examined in 353 patients with various solid tumors. Pharmacokinetic parameters were derived using data from patients treated for varying durations of therapy given weekly with periodic rest weeks and using both short infusions (<70 minutes) and long infusions (70 to 285 minutes). The total gemcitabine dose varied from 500 mg/m 2 to 3,600 mg/m 2 .
Distribution The volume of distribution was increased with infusion length. Volume of distribution of gemcitabine was 50 L/m 2 following infusions lasting <70 minutes. For long infusions, the volume of distribution rose to 370 L/m 2 .
Gemcitabine pharmacokinetics are linear and are described by a 2-compartment model. Population pharmacokinetic analyses of combined single and multiple dose studies showed that the volume of distribution of gemcitabine was significantly influenced by duration of infusion and sex. Gemcitabine plasma protein binding is negligible.
Elimination Metabolism The active metabolite, gemcitabine triphosphate, can be extracted from peripheral blood mononuclear cells. The half-life of the terminal phase for gemcitabine triphosphate from mononuclear cells ranges from 1.7 to 19.4 hours. Excretion Gemcitabine disposition was studied in 5 patients who received a single 1,000 mg/m 2 of radiolabeled drug as a 30-minute infusion.
Within one week, 92% to 98% of the dose was recovered, almost entirely in the urine. Gemcitabine (<10%) and the inactive uracil metabolite, 2′-deoxy-2′, 2′-difluorouridine (dFdU) accounted for 99% of the excreted dose. The metabolite dFdU is also found in plasma.
Specific Populations Geriatric Patients Clearance of gemcitabine was affected by age. The lower clearance in geriatric patients results in higher concentrations of gemcitabine for any given dose. Differences in either clearance or volume of distribution based on patient characteristics or the duration of infusion result in changes in half-life and plasma concentrations.
Table 15 shows plasma clearance and half-life of gemcitabine following short infusions for typical patients by age and sex. Table 15: Gemcitabine Clearance and Half-Life for the “Typical” Patient a Half-life for patients receiving a <70 minute infusion. Age Clearance Men (L/hr/m 2 ) Clearance Women (L/hr/m 2 ) Half-Life a Men (min) Half-Life a Women (min) 29 92.2 69.4 42 49 45 75.7 57.0 48 57 65 55.1 41.5 61 73 79 40.7 30.7 79 94 Gemcitabine half-life for short infusions ranged from 42 to 94 minutes and for long infusions varied from 245 to 638 minutes, depending on age and sex, reflecting a greatly increased volume of distribution with longer infusions.
Male and Female Patients Females have lower clearance and longer half-lives than male patients as described in Table 15 . Patients with Renal Impairment No clinical studies have been conducted with gemcitabine in patients with decreased renal function. Patients with Hepatic Impairment No clinical studies have been conducted with gemcitabine in patients with de… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Gemcitabine kills cells undergoing DNA synthesis and blocks the progression of cells through the G1/S-phase boundary. Gemcitabine is metabolized by nucleoside kinases to diphosphate (dFdCDP) and triphosphate (dFdCTP) nucleosides. Gemcitabine diphosphate inhibits ribonucleotide reductase, an enzyme responsible for catalyzing the reactions that generate deoxynucleoside triphosphates for DNA synthesis, resulting in reductions in deoxynucleotide concentrations, including dCTP.
Gemcitabine triphosphate competes with dCTP for incorporation into DNA. The reduction in the intracellular concentration of dCTP by the action of the diphosphate enhances the incorporation of gemcitabine triphosphate into DNA (self-potentiation). After the gemcitabine nucleotide is incorporated into DNA, only one additional nucleotide is added to the growing DNA strands, which eventually results in the initiation of apoptotic cell death.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Gemcitabine for Injection, USP is a sterile white to off-white lyophilized powder available in single-dose vials individually packaged in a carton containing 200 mg, 1 g or 2 g gemcitabine: Product Code Unit of Sale Strength FK101210 NDC 63323-102-13 Individually packaged 200 mg per vial FK102550 NDC 63323-125-53 Individually packaged 1 gram per vial FK102600 NDC 63323-126-03 Individually packaged 2 grams per vial Gemcitabine for Injection, USP is a cytotoxic drug. Follow applicable special handling and disposal procedures.
1 Store at controlled room temperature 20ºC to 25ºC (68ºF to 77ºF); excursions permitted between 15ºC and 30ºC (59ºF and 86ºF) [see USP Controlled Room Temperature]. The container closure is not made with natural rubber latex.
📋 Description ▾
11 DESCRIPTION Gemcitabine is a nucleoside metabolic inhibitor. Gemcitabine hydrochloride is 2′-deoxy-2′, 2′-difluorocytidine monohydrochloride (β-isomer) with the following structural formula: The empirical formula for gemcitabine hydrochloride is C 9 H 11 F 2 N 3 O 4 • HCl. It has a molecular weight of 299.66 g/mol.
Gemcitabine hydrochloride is soluble in water, slightly soluble in methanol, and practically insoluble in ethanol and polar organic solvents. Gemcitabine for Injection, USP is a sterile white to off-white lyophilized powder and available as 200 mg, 1 g and 2 g single-dose vials for intravenous use only. Each 200 mg vial contains 200 mg gemcitabine (equivalent to 227.7 mg gemcitabine hydrochloride), 200 mg mannitol and 12.5 mg sodium acetate.
Each 1 g vial contains 1 g gemcitabine (equivalent to 1.139 g gemcitabine hydrochloride), 1 g mannitol, and 62.5 mg sodium acetate. Each 2 g vial contains 2 g gemcitabine (equivalent to 2.276 g gemcitabine hydrochloride), 2 g mannitol, and 125 mg sodium acetate. Hydrochloric acid and/or sodium hydroxide may have been added for pH adjustment.
Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Myelosuppression Advise patients of the risks of myelosuppression. Instruct patients to immediately contact their healthcare provider should any signs or symptoms of infection, including fever, or if bleeding or signs of anemia, occur [see Warnings and Precautions ( 5.2 )]. Pulmonary Toxicity Advise patients of the risks of pulmonary toxicity, including respiratory failure and death.
Instruct patients to immediately contact their healthcare provider for development of shortness of breath, wheezing, or cough [see Warnings and Precautions ( 5.3 )]. Hemolytic-Uremic Syndrome and Renal Failure Advise patients of the risks of hemolytic-uremic syndrome and associated renal failure. Instruct patients to immediately contact their healthcare provider for changes in the color or volume of urine output or for increased bruising or bleeding [see Warnings and Precautions ( 5.4 )].
Hepatic Toxicity Advise patients of the risks of hepatic toxicity including liver failure and death. Instruct patients to immediately contact their healthcare provider for signs of jaundice or for pain/tenderness in the right upper abdominal quadrant [see Warnings and Precautions ( 5.5 )]. Embryo-Fetal Toxicity Advise females and males of reproductive potential that gemcitabine can cause fetal harm.
Advise females of reproductive potential to use effective contraception during treatment with gemcitabine and for 6 months after the final dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with gemcitabine and for 3 months after the final dose [see Warnings and Precaution ( 5.6 ), Use in Specific Populations ( 8.1 , 8.3 )]. Lactation Advise women not to breastfeed during treatment with gemcitabine and for at least one week after the last dose [see Use in Specific Populations ( 8.2 )].
Infertility Advise males of reproductive potential of the potential for reduced fertility with gemcitabine [see Use in Specific Populations ( 8.3 ), Nonclinical Toxicology ( 13.1 )]. Lake Zurich, IL 60047 For Product Inquiry: 1-800-551-7176 or www.fresenius-kabi.com/us 451258E/Revised: September 2019 Fresenius Kabi Logo
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of gemcitabine were examined in 353 patients with various solid tumors. Pharmacokinetic parameters were derived using data from patients treated for varying durations of therapy given weekly with periodic rest weeks and using both short infusions (<70 minutes) and long infusions (70 to 285 minutes). The total gemcitabine dose varied from 500 mg/m 2 to 3,600 mg/m 2 .
Distribution The volume of distribution was increased with infusion length. Volume of distribution of gemcitabine was 50 L/m 2 following infusions lasting <70 minutes. For long infusions, the volume of distribution rose to 370 L/m 2 .
Gemcitabine pharmacokinetics are linear and are described by a 2-compartment model. Population pharmacokinetic analyses of combined single and multiple dose studies showed that the volume of distribution of gemcitabine was significantly influenced by duration of infusion and sex. Gemcitabine plasma protein binding is negligible.
Elimination Metabolism The active metabolite, gemcitabine triphosphate, can be extracted from peripheral blood mononuclear cells. The half-life of the terminal phase for gemcitabine triphosphate from mononuclear cells ranges from 1.7 to 19.4 hours. Excretion Gemcitabine disposition was studied in 5 patients who received a single 1,000 mg/m 2 of radiolabeled drug as a 30-minute infusion.
Within one week, 92% to 98% of the dose was recovered, almost entirely in the urine. Gemcitabine (<10%) and the inactive uracil metabolite, 2′-deoxy-2′, 2′-difluorouridine (dFdU) accounted for 99% of the excreted dose. The metabolite dFdU is also found in plasma.
Specific Populations Geriatric Patients Clearance of gemcitabine was affected by age. The lower clearance in geriatric patients results in higher concentrations of gemcitabine for any given dose. Differences in either clearance or volume of distribution based on patient characteristics or the duration of infusion result in changes in half-life and plasma concentrations.
Table 15 shows plasma clearance and half-life of gemcitabine following short infusions for typical patients by age and sex. Table 15: Gemcitabine Clearance and Half-Life for the “Typical” Patient a Half-life for patients receiving a <70 minute infusion. Age Clearance Men (L/hr/m 2 ) Clearance Women (L/hr/m 2 ) Half-Life a Men (min) Half-Life a Women (min) 29 92.2 69.4 42 49 45 75.7 57.0 48 57 65 55.1 41.5 61 73 79 40.7 30.7 79 94 Gemcitabine half-life for short infusions ranged from 42 to 94 minutes and for long infusions varied from 245 to 638 minutes, depending on age and sex, reflecting a greatly increased volume of distribution with longer infusions.
Male and Female Patients Females have lower clearance and longer half-lives than male patients as described in Table 15 . Patients with Renal Impairment No clinical studies have been conducted with gemcitabine in patients with decreased renal function. Patients with Hepatic Impairment No clinical studies have been conducted with gemcitabine in patients with decreased hepatic function.
Drug Interaction Studies When gemcitabine (1,250 mg/m 2 on Days 1 and 8) and cisplatin (75 mg/m 2 on Day 1) were administered in patients with NSCLC, the clearance of gemcitabine on Day 1 was 128 L/hr/m 2 and on Day 8 was 107 L/hr/m 2 . Data from patients with NSCLC demonstrate that gemcitabine and carboplatin given in combination does not alter the pharmacokinetics of gemcitabine or carboplatin compared to administration of either single agent; however, due to wide confidence intervals and small sample size, interpatient variability may be observed.
Data from metastatic breast cancer patients shows that gemcitabine has little or no effect on the pharmacokinetics (clearance and half-life) of paclitaxel and paclitaxel has little or no effect on the pharmacokinetics of gemcitabine.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Ovarian Cancer The efficacy of gemcitabine was evaluated in a randomized trial (Study 1) conducted in women with advanced ovarian cancer that had relapsed at least 6 months after first-line platinum-based therapy. Patients were randomized to receive either gemcitabine 1,000 mg/m 2 on Days 1 and 8 of each 21-day cycle with carboplatin AUC 4 on Day 1 after gemcitabine administration (n=178) or carboplatin AUC 5 on Day 1 of each 21-day cycle (n=178). The major efficacy outcome measure was progression-free survival (PFS).
A total of 356 patients were enrolled. Demographics and baseline characteristics are shown in Table 16 . Efficacy results are presented in Table 17 and Figure 1 .
The addition of gemcitabine to carboplatin resulted in statistically significant improvements in PFS and overall response rate. Approximately 75% of patients in each arm received additional chemotherapy for disease progression; 13 of 120 patients in the carboplatin alone arm received gemcitabine for treatment of disease progression. There was no significant difference in overall survival between the treatment arms.
Table 16: Baseline Demographics and Clinical Characteristics for Study 1 Gemcitabine/Carboplatin (N=178) Carboplatin (N=178) Median age, years 59 58 Range 36 to 78 21 to 81 Baseline ECOG performance status 0-1 a 94% 95% Disease Status Evaluable 8% 3% Bidimensionally measurable 92% 96% Platinum-free interval b 6-12 months 40% 40% >12 months 59% 60% First-line therapy Platinum-taxane combination 70% 71% Platinum-non-taxane combination 29% 28% Platinum monotherapy 1% 1% a 5 patients on Gemcitabine with carboplatin arm and 4 patients on carboplatin arm had no baseline Eastern Cooperative Oncology Group (ECOG) performance status. b 2 patients on Gemcitabine with carboplatin arm and 1 patient on carboplatin arm had platinum-free interval <6 months.
Table 17: Efficacy Results in Study 1 a CI=confidence interval. b Log rank, unadjusted. c Chi square. d CR=Complete response. e PR with PRNM=Partial response with partial response, non-measurable disease. f Independently reviewed cohort - gemcitabine/carboplatin (n=121), carboplatin (n=101); independent reviewers unable to measure disease detected by sonography or physical exam. Efficacy Parameter Gemcitabine/Carboplatin (N=178) Carboplatin (N=178) Progression-Free Survival Median (95% CI a ) in months 8.6 (8.0, 9.7) 5.8 (5.2, 7.1) Hazard Ratio (95% CI) 0.72 (0.57, 0.90) p-value b p=0.0038 Overall Survival Median (95% CI) in months 18.0 (16.2, 20.3) 17.3 (15.2, 19.3) Hazard Ratio (95% CI) 0.98 (0.78, 1.24) p-value b p=0.8977 Overall Response Rate by Investigator Review 47.2% 30.9% p-value c p=0.0016 CR d 14.6% 6.2% PR with PRNM e 32.6% 24.7% Overall Response Rate f by Independent Review 46.3% 35.6% p-value c p=0.11 CR d 9.1% 4.0% PR with PRNM e 37.2% 31.7% Figure 1: Kaplan-Meier Curves for Progression-Free Survival in Study 1 Figure 1
14.2Breast Cancer The efficacy of gemcitabine was evaluated in a multinational, randomized, open-label trial (Study 2) conducted in women receiving initial treatment for metastatic breast cancer and who have received prior adjuvant/neoadjuvant anthracycline chemotherapy unless clinically contraindicated. Patients were randomized to receive either gemcitabine 1,250 mg/m 2 on Days 1 and 8 of each 21-day cycle with paclitaxel 175 mg/m 2 administered on Day 1 before gemcitabine administration (n=267) or paclitaxel 175 mg/m 2 on Day 1 of each 21-day cycle (n=262).
The major efficacy outcome measure was time to documented disease progression. A total of 529 patients were enrolled. Demographic and baseline characteristics were similar between treatment arms ( Table 18 ).
Efficacy results are presented in Table 19 and Figure 2 . The addition of gemcitabine to paclitaxel resulted in statistically significant improvement in time to documented disease progression and overall response rate compared to paclitaxel alone. There was no significant difference in ov… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term animal studies to evaluate the carcinogenic potential of gemcitabine have not been conducted. Gemcitabine was mutagenic in an in vitro mouse lymphoma (L5178Y) assay and was clastogenic in an in vivo mouse micronucleus assay. Gemcitabine intraperitoneal doses of 0.5 mg/kg/day [about 1/700 the 1,000 mg/m 2 clinical dose based on body surface area (BSA)] in male mice resulted in moderate to severe hypospermatogenesis, decreased fertility, and decreased implantations.
In female mice, fertility was not affected but maternal toxicities were observed at 1.5 mg/kg/day administered intravenously (about 1/200 the 1,000 mg/m 2 clinical dose based on BSA) and fetotoxicity or embryolethality was observed at 0.25 mg/kg/day administered intravenously (about 1/1,300 the 1,000 mg/m 2 clinical dose based on BSA).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term animal studies to evaluate the carcinogenic potential of gemcitabine have not been conducted. Gemcitabine was mutagenic in an in vitro mouse lymphoma (L5178Y) assay and was clastogenic in an in vivo mouse micronucleus assay. Gemcitabine intraperitoneal doses of 0.5 mg/kg/day [about 1/700 the 1,000 mg/m 2 clinical dose based on body surface area (BSA)] in male mice resulted in moderate to severe hypospermatogenesis, decreased fertility, and decreased implantations.
In female mice, fertility was not affected but maternal toxicities were observed at 1.5 mg/kg/day administered intravenously (about 1/200 the 1,000 mg/m 2 clinical dose based on BSA) and fetotoxicity or embryolethality was observed at 0.25 mg/kg/day administered intravenously (about 1/1,300 the 1,000 mg/m 2 clinical dose based on BSA).
📚 References ▾
15 REFERENCES OSHA Hazardous Drugs.” OSHA. http://www.osha.gov/SLTC/hazardousdrugs/index.html
📄 Recent Major Changes ▾
Warnings and Precautions, Hemolytic Uremic Syndrome ( 5.4 ) 5/2019
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL - PRINCIPAL DISPLAY PANEL - Gemcitabine 200mg-Vial Carton NDC: 63323-102-13 FK101210 GEMCITABINE FOR INJECTION, USP 200 mg per vial For Intravenous use only Must Be Diluted DO NOT REFRIGERATE Cytotoxic Agent Rx only Single-Dose Vial PACKAGE LABEL - PRINCIPAL DISPLAY PANEL - Gemcitabine 200 mg- Vial Label NDC: 63323-102-13 FK101210 GEMCITABINE FOR INJECTION, USP 200 mg per vial For Intravenous use only Must Be Diluted Rx only Single-Dose Vial 200mg vial-200mg
PACKAGE LABEL - PRINCIPAL DISPLAY PANEL - Gemcitabine 1g-Vial Carton NDC 63323-125-53 FK102550 GEMCITABINE FOR INJECTION, USP 1 g per vial For Intravenous use only Must Be Diluted DO NOT REFRIGERATE Cytotoxic Agent Rx only Single-Dose Vial PACKAGE LABEL - PRINCIPAL DISPLAY PANEL - Gemcitabine 1 g- Vial Label NDC 63323-125-53 FK102550 GEMCITABINE FOR INJECTION, USP 1 g per vial For Intravenous use only Must Be Diluted Rx only Single-Dose Vial carton-1g vial-1g
PACKAGE LABEL - PRINCIPAL DISPLAY PANEL - Gemcitabine 2g-Vial Carton NDC 63323-126-03 FK102600 GEMCITABINE FOR INJECTION, USP 2 g per vial For Intravenous use only Must Be Diluted DO NOT REFRIGERATE Cytotoxic Agent Rx only Single-Dose Vial PACKAGE LABEL - PRINCIPAL DISPLAY PANEL - Gemcitabine 2 g- Vial Label NDC 63323-126-03 FK102600 GEMCITABINE FOR INJECTION, USP 2 g per vial For Intravenous use only Must Be Diluted Rx only Single-Dose Vial carton-2g vial-2g
Medicaid utilization & spend
Medicaid utilization by pack size
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |