
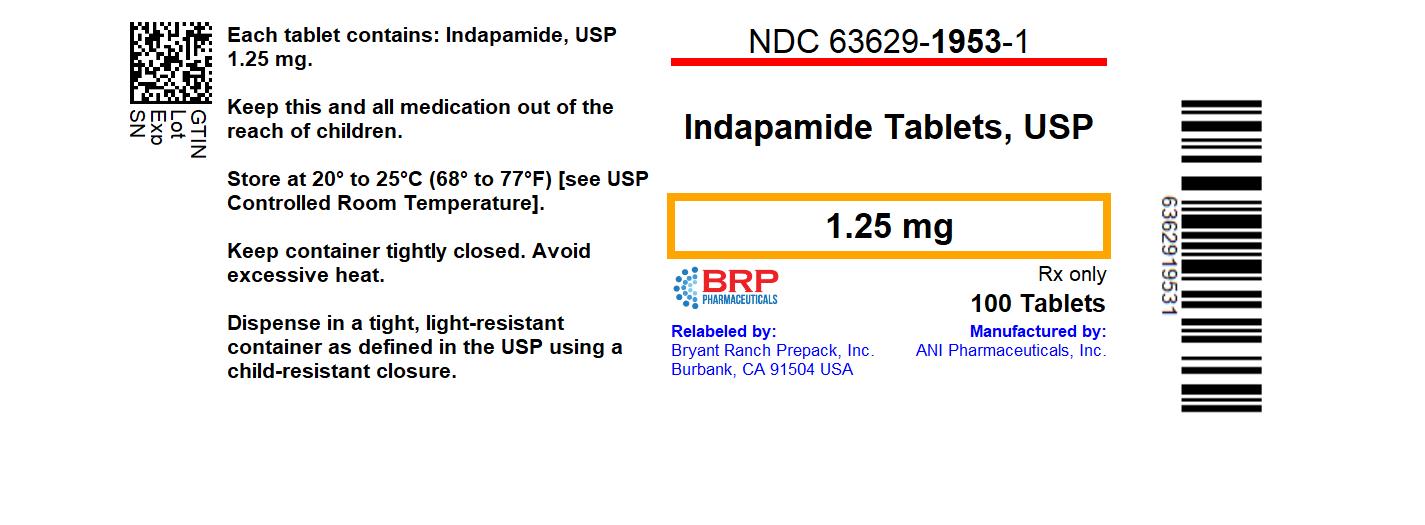
Indapamide 1.25 mg Tablet, Film Coated, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Thiazide-like Diuretic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Indapamide is used to treat hypertension (high blood pressure) and fluid retention (swelling caused by body fluid pooling in certain tissues) that can happen with heart failure(HF; a condition where the heart muscle weakens and cannot blood as well). Indapamide is in a class of medications called diuretics ("water pills"). It works by causing the kidneys to get rid of unneeded salt and water from the body into the urine. Untreated high blood pressure can damage the brain, heart, blood vessels, kidneys and other parts of the body. This damage may cause heart disease, a heart attack, stroke, kid...
Read the full MedlinePlus article ↗- Indapamide is a 'water pill' (diuretic) that's approved for two things: lowering high blood pressure, and reducing the fluid buildup (swelling) that can happen with congestive hear...
- The label recommends taking it once a day in the morning — that way, most of the diuretic (fluid-removing) effect happens during daytime hours so you're not running to the bathroom...
- When should I take indapamide, and does it matter if I take it with food?
- The most common ones are headache, dizziness, fatigue, muscle cramps, and more frequent urination — especially when you first start. Low potassium is also pretty common with this t...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Indapamide — tap one for details:
Indapamide may be associated with lower levels of 8 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2159 | $21.59 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Indapamide 1.25 mg 00228-2597-11 | Actavis | 100 tablets | $0.107 | AB | Availability likely | — |
| Indapamide 1.25 mg 16571-0875-01 | Rising | 100 tablets | $0.107 | AB | Availability likely | — |
| Indapamide 1.25 mg 62559-0510-01 | ANI | 100 tablets | $0.107 | AB | Availability likely | — |
| Indapamide 1.25 mg 50090-7828-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Indapamide 1.25 mg 51407-0024-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Indapamide 1.25 mgthis 63629-1953-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Indapamide 1.25 mg 71335-1541-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Indapamide 1.25 mg 72162-1766-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 63629-1953-01 You're viewing this | 100 TABLET, FILM COATED in 1 BOTTLE (63629-1953-1) | 2021-06-29 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Hypertension The adult starting indapamide dose for hypertension is 1.25 mg as a single daily dose taken in the morning. If the response to 1.25 mg is not satisfactory after 4 weeks, the daily dose may be increased to 2.5 mg taken once daily. If the response to 2.5 mg is not satisfactory after 4 weeks, the daily dose may be increased to 5 mg taken once daily, but adding another antihypertensive should be considered.
Edema of Congestive Heart Failure The adult starting indapamide dose for edema of congestive heart failure is 2.5 mg as a single daily dose taken in the morning. If the response to 2.5 mg is not satisfactory after one week, the daily dose may be increased to 5 mg taken once daily. If the antihypertensive response to indapamide is insufficient, indapamide may be combined with other antihypertensive drugs, with careful monitoring of blood pressure.
It is recommended that the usual dose of other agents be reduced by 50% during initial combination therapy. As the blood pressure response becomes evident, further dosage adjustments may be necessary. In general, doses of 5 mg and larger have not appeared to provide additional effects on blood pressure or heart failure, but are associated with a greater degree of hypokalemia.
There is minimal clinical trial experience in patients with doses greater than 5 mg once a day.
⛔ Contraindications ▾
CONTRAINDICATIONS Anuria. Known hypersensitivity to indapamide or to other sulfonamide-derived drugs.
⚠️ Warnings ▾
WARNINGS Severe cases of hyponatremia, accompanied by hypokalemia have been reported with recommended doses of indapamide. This occurred primarily in elderly females. (See PRECAUTIONS, Geriatric Use .) This appears to be dose related.
Also, a large case-controlled pharmacoepidemiology study indicates that there is an increased risk of hyponatremia with indapamide 2.5 mg and 5 mg doses. Hyponatremia considered possibly clinically significant (< 125 mEq/L) has not been observed in clinical trials with the 1.25 mg dosage (see PRECAUTIONS ). Thus, patients should be started at the 1.25 mg dose and maintained at the lowest possible dose.
(See DOSAGE AND ADMINISTRATION .) Hypokalemia occurs commonly with diuretics (see ADVERSE REACTIONS, Hypokalemia ), and electrolyte monitoring is essential, particularly in patients who would be at increased risk from hypokalemia, such as those with cardiac arrhythmias or who are receiving concomitant cardiac glycosides. In general, diuretics should not be given concomitantly with lithium because they reduce its renal clearance and add a high risk of lithium toxicity. Read prescribing information for lithium preparations before use of such concomitant therapy.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Most adverse effects have been mild and transient. The clinical adverse reactions listed in Table 1 represent data from Phase II/III placebo-controlled studies (306 patients given indapamide 1.25 mg). The clinical adverse reactions listed in Table 2 represent data from Phase II placebo-controlled studies and long-term controlled clinical trials (426 patients given indapamide 2.5 mg or 5 mg).
The reactions are arranged into two groups: 1) a cumulative incidence equal to or greater than 5%; 2) a cumulative incidence less than 5%. Reactions are counted regardless of relation to drug. TABLE 1: Adverse Reactions from Studies of 1.25 mg Incidence ≥ 5% Incidence < 5% 1 BODY AS A WHOLE Headache Infection Pain Back Pain Asthenia Flu Syndrome Abdominal Pain Chest Pain GASTROINTESTINAL SYSTEM Constipation Diarrhea Dyspepsia Nausea METABOLIC SYSTEM Peripheral Edema CENTRAL NERVOUS SYSTEM Dizziness Nervousness Hypertonia RESPIRATORY SYSTEM Rhinitis Cough Pharyngitis Sinusitis SPECIAL SENSES Conjunctivitis 1 OTHER All other clinical adverse reactions occurred at an incidence of < 1%.
Approximately 4% of patients given indapamide 1.25 mg compared to 5% of the patients given placebo discontinued treatment in the trials of up to 8 weeks because of adverse reactions. In controlled clinical trials of 6 to 8 weeks in duration, 20% of patients receiving indapamide 1.25 mg, 61% of patients receiving indapamide 5 mg, and 80% of patients receiving indapamide 10 mg had at least one potassium value below 3.4 mEq/L. In the indapamide 1.25 mg group, about 40% of those patients who reported hypokalemia as a laboratory adverse event returned to normal serum potassium values without intervention.
Hypokalemia with concomitant clinical signs or symptoms occurred in 2% of patients receiving indapamide 1.25 mg. TABLE 2: Adverse Reactions from Studies of 2.5 mg and 5 mg Incidence ≥ 5% Incidence < 5% CENTRAL NERVOUS SYSTEM/NEUROMUSCULAR Headache Dizziness Fatigue, weakness, loss of energy, lethargy, tiredness, or malaise Muscle cramps or spasm, or numbness of the extremities Nervousness, tension, anxiety, irritability, or agitation Lightheadedness Drowsiness Vertigo Insomnia Depression Blurred Vision GASTROINTESTINAL SYSTEM Constipation Nausea Vomiting Diarrhea Gastric irritation Abdominal pain or cramps Anorexia CARDIOVASCULAR SYSTEM Orthostatic hypotension Premature ventricular contractions Irregular heart beat Palpitations GENITOURINARY SYSTEM Frequency of urination Nocturia Polyuria DERMATOLOGIC/HYPERSENSITIVITY Rash Hives Pruritus Vasculitis OTHER Impotence or reduced libido Rhinorrhea Flushing Hyperuricemia Hyperglycemia Hyponatremia Hypochloremia Increase in serum urea nitrogen (BUN) or creatinine Glycosuria Weight loss Dry mouth Tingling of extremities Because most of these data are from long-term studies (up to 40 weeks of treatment), it is probable that many of the adverse experiences reported are due to causes other than the drug.
Approximately 10% of patients given indapamide discontinued treatment in long-term trials because of reactions either related or unrelated to the drug. Hypokalemia with concomitant clinical signs or symptoms occurred in 3% of patients receiving indapamide 2.5 mg q.d. and 7% of patients receiving indapamide 5 mg q.d. In long-term controlled clinical trials comparing the hypokalemic effects of daily doses of indapamide and hydrochlorothiazide, however, 47% of patients receiving indapamide 2.5 mg, 72% of patients receiving indapamide 5 mg, and 44% of patients receiving hydrochlorothiazide 50 mg had at least one potassium value (out of a total of 11 taken during the study) below 3.5 mEq/L.
In the indapamide 2.5 mg group, over 50% of those patients returned to normal serum potassium values without intervention. In clinical trials of 6 to 8 weeks, the mean changes in selected values were as shown in the tables below. Mean Changes from Baseline after 8 Weeks of Treatment - 1.25 mg Serum Electrolytes (mEq/L) Serum U…
🔄 Drug Interactions ▾
Drug Interactions Other Antihypertensives Indapamide may add to or potentiate the action of other antihypertensive drugs. In limited controlled trials that compared the effect of indapamide combined with other antihypertensive drugs with the effect of the other drugs administered alone, there was no notable change in the nature or frequency of adverse reactions associated with the combined therapy. Lithium See WARNINGS .
Post-Sympathectomy Patient The antihypertensive effect of the drug may be enhanced in the post-sympathectomized patient. Norepinephrine Indapamide, like the thiazides, may decrease arterial responsiveness to norepinephrine, but this diminution is not sufficient to preclude effectiveness of the pressor agent for therapeutic use.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Reproduction studies have been performed in rats, mice and rabbits at doses up to 6,250 times the therapeutic human dose and have revealed no evidence of impaired fertility or harm to the fetus due to indapamide. Postnatal development in rats and mice was unaffected by pretreatment of parent animals during gestation. There are, however, no adequate and well controlled studies in pregnant women.
Moreover, diuretics are known to cross the placental barrier and appear in cord blood. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed. There may be hazards associated with this use such as fetal or neonatal jaundice, thrombocytopenia, and possibly other adverse reactions that have occurred in the adult.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness of indapamide in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of indapamide did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Severe cases of hyponatremia, accompanied by hypokalemia have been reported with recommended doses of indapamide in elderly females (see WARNINGS ).
🆘 Overdosage ▾
OVERDOSAGE Symptoms of overdosage include nausea, vomiting, weakness, gastrointestinal disorders, and disturbances of electrolyte balance. In severe instances, hypotension and depressed respiration may be observed. If this occurs, support of respiration and cardiac circulation should be instituted.
There is no specific antidote. An evacuation of the stomach is recommended by emesis and gastric lavage after which the electrolyte and fluid balance should be evaluated carefully.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Indapamide is the first of a new class of antihypertensive/diuretics, the indolines. The oral administration of 2.5 mg (two 1.25 mg tablets) of indapamide to male subjects produced peak concentrations of approximately 115 ng/mL of the drug in the blood within 2 hours. The oral administration of 5 mg (two 2.5 mg tablets) of indapamide to healthy male subjects produced peak concentrations of approximately 260 ng/mL of the drug in the blood within 2 hours.
A minimum of 70% of a single oral dose is eliminated by the kidneys and an additional 23% by the gastrointestinal tract, probably including the biliary route. The half-life of indapamide in whole blood is approximately 14 hours. Indapamide is preferentially and reversibly taken up by the erythrocytes in the peripheral blood.
The whole blood/plasma ratio is approximately 6:1 at the time of peak concentration and decreases to 3.5:1 at 8 hours. From 71% to 79% of the indapamide in plasma is reversibly bound to plasma proteins. Indapamide is an extensively metabolized drug, with only about 7% of the total dose administered, recovered in the urine as unchanged drug during the first 48 hours after administration.
The urinary elimination of 14 C-labeled indapamide and metabolites is biphasic with a terminal half-life of excretion of total radioactivity of 26 hours. In a parallel design double-blind, placebo controlled trial in hypertension, daily doses of indapamide between 1.25 mg and 10 mg produced dose-related antihypertensive effects. Doses of 5 mg and 10 mg were not distinguishable from each other although each was differentiated from placebo and 1.25 mg indapamide.
At daily doses of 1.25 mg, 5 mg and 10 mg, a mean decrease of serum potassium of 0.28, 0.61 and 0.76 mEq/L, respectively, was observed and uric acid increased by about 0.69 mg/100 mL. In other parallel design, dose-ranging clinical trials in hypertension and edema, daily doses of indapamide between 0.5 mg and 5 mg produced dose related effects. Generally, doses of 2.5 mg and 5 mg were not distinguishable from each other although each was differentiated from placebo and from 0.5 mg or 1 mg indapamide.
At daily doses of 2.5 mg and 5 mg a mean decrease of serum potassium of 0.5 and 0.6 mEq/Liter, respectively, was observed and uric acid increased by about 1 mg/100 mL. At these doses, the effects of indapamide on blood pressure and edema are approximately equal to those obtained with conventional doses of other antihypertensive/diuretics. In hypertensive patients, daily doses of 1.25 mg, 2.5 mg and 5 mg of indapamide have no appreciable cardiac inotropic or chronotropic effect.
The drug decreases peripheral resistance with little or no effect on cardiac output, rate or rhythm. Chronic administration of indapamide to hypertensive patients has little or no effect on glomerular filtration rate or renal plasma flow. Indapamide had an antihypertensive effect in patients with varying degrees of renal impairment, although in general, diuretic effects declined as renal function decreased.
In a small number of controlled studies, indapamide taken with other antihypertensive drugs such as hydralazine, propranolol, guanethidine, and methyldopa, appeared to have the additive effect typical of thiazide-type diuretics.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Indapamide Tablets USP are available containing 1.25 mg of indapamide USP. The 1.25 mg tablets are orange, round, film coated tablets debossed ‘ANI’ over ‘510’ on one side and plain on the other side. They are available in bottles of 100 tablets (NDC 63629-1953-1).
Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Keep container tightly closed. Avoid excessive heat.
Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
DESCRIPTION Indapamide is an oral antihypertensive/diuretic. Its molecule contains both a polar sulfamoyl chlorobenzamide moiety and a lipid-soluble methylindoline moiety. It differs chemically from the thiazides in that it does not possess the thiazide ring system and contains only one sulfonamide group.
The chemical name of indapamide is 4-Chloro- N -(2-methyl-1-indolinyl)-3-sulfamoylbenzamide, and its molecular weight is 365.84. The compound is a weak acid, pK a =8.8, and is soluble in aqueous solutions of strong bases. It is a white to yellow-white crystalline (tetragonal) powder.
C 16 H 16 ClN 3 O 3 S Each tablet, for oral administration, contains 1.25 mg or 2.5 mg of indapamide USP and the following inactive ingredients: corn starch, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polyethylene glycol, polysorbate 80, talc, and titanium dioxide. Additionally, the 1.25 mg product contains FD&C yellow #6 aluminum lake.