
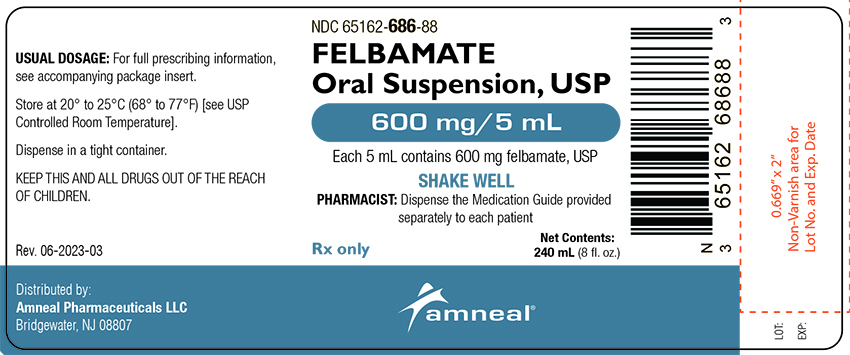
Felbamate 600 mg/5mL Suspension, 237 mL — NDC 65162-686-88 (Billing 65162-0686-88)
This is a package of 237 mL of Felbamate 600 mg/5mL Suspension from Amneal Pharmaceuticals LLC, marketed since Dec 2011 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 65162-686-88 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 65162 labeler · 686 product · 88 package
- Package marketed since
- Dec 16, 2011
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 237 mL per package
- Barcode (UPC-A, from the NDC)
- 3 6516268688 3
- Medicaid fills, this package
- 502 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 020040
- GCN: 38020
- GPI-14 (Medi-Span): 72120020001810
- HICL (First Databank): 008186
- AHFS class code: 28:12.92.00
- RxCUI (RxNorm): 310285
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Anti-epileptic Agent class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Felbamate is used to treat certain seizures in adults and children with epilepsy whose seizures have not improved with other treatments. It is used alone or in combination with other medications to treat partial seizures in adults. It is used in combination with other medications to treat partial and generalized seizures in children with Lennox-Gastaut syndrome (a disorder that causes seizures and developmental delays). Felbamate is in a class of medications called anticonvulsants. It works by decreasing abnormal activity in the brain.
Read the full MedlinePlus article ↗- It treats severe epilepsy when other medicines haven't worked well enough. It's used for partial seizures in adults and for Lennox-Gastaut syndrome in children. It isn't a first-ch...
- You take it by mouth, as tablets or liquid, several times a day. Follow your prescriber's schedule exactly. Never stop it suddenly, because seizures could increase.
- Common ones include poor appetite, nausea, vomiting, trouble sleeping, headache, dizziness and sleepiness. Tell your doctor if they bother you or don't go away.
- Call for signs of infection, unusual bleeding or bruising, or unusual paleness. Also call for yellow skin or eyes, dark urine, a serious rash, or any mood changes or thoughts of se...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Felbamate — tap one for details:
Felbamate may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $0.5943 | $140.85 / 237 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.4633 | $109.80 / 237 ml |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 65162-0686-88 You're viewing this Main listing | 237 mL in 1 BOTTLE | 2011-12-16 | — | Active |
| 65162-0686-90 65162-686-90 | 473 mL in 1 BOTTLE | 2011-12-16 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 85% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 65162-0686-90?
What NDC number is used to bill for this package of Felbamate 600 mg/5mL Suspension?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Felbamate 600 mg/5mL 16714-0775-01 | NORTHSTAR | 237 ml | $0.356 | AB | Availability likely | — |
| Felbamate 600 mg/5mL 51672-4172-01 | Sun | 237 ml | $0.356 | AB | Availability likely | — |
| Felbamate 600 mg/5mL 70954-0051-10 | Novitium | 237 ml | $0.356 | AB | Availability likely | — |
| Felbamate 600 mg/5mLthis 65162-0686-88 | Amneal | 237 ml | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Felbamate inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII K679OBS311
Carboxymethylcellulose sodium is a plant-derived thickening agent made from cellulose. In medicines, it acts as a binder to hold ingredients together, a disintegrant to help the tablet break apart, or a thickener in liquids.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII Z8IX2SC1OH
Propylparaben is a chemical preservative used to prevent bacterial and fungal growth in medicines and personal care products. It helps extend shelf life and maintain product safety during storage.
-
UNII SB8ZUX40TY
Saccharin sodium is an artificial sweetener made from saccharin salt. It's added to medicines to improve taste, especially in liquid formulations for children or bitter drugs.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Amneal Pharmaceuticals LLC labeler code 65162
- Promethazine Hydrochloride and Dextromethorphan Hydrobromide 6.25 mg/5mL; 15 mg/5mL Solution NDC 65162-680-86
- Phenazopyridine Hydrochloride 100 mg Tablet NDC 65162-681-10
- Phenazopyridine Hydrochloride 200 mg Tablet NDC 65162-682-10
- Diclofenac Sodium 20 mg/g Solution NDC 65162-683-12
- Cetirizine Hydrochloride 5 mg/5mL Solution NDC 65162-684-86
- Levetiracetam 100 mg/mL Solution NDC 65162-685-86
- Lorazepam 2 mg/mL Concentrate NDC 65162-687-84
- Nitrofurantoin 25 mg/5mL Suspension NDC 65162-689-88
- Ondansetron 4 mg/5mL Solution NDC 65162-691-19
- ATOVAQUONE 750 mg/5mL Suspension NDC 65162-693-88
- Promethazine and Phenylephrine HCl, and Codeine Phosphate 6.25 mg/5mL; 5 mg/5mL; 10 mg/5mL Syrup NDC 65162-694-86
- Gabapentin 250 mg/5mL Solution NDC 65162-698-54
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING 1. APLASTIC ANEMIA THE USE OF FELBAMATE IS ASSOCIATED WITH A MARKED INCREASE IN THE INCIDENCE OF APLASTIC ANEMIA. ACCORDINGLY, FELBAMATE SHOULD ONLY BE USED IN PATIENTS WHOSE EPILEPSY IS SO SEVERE THAT THE RISK OF APLASTIC ANEMIA IS DEEMED ACCEPTABLE IN LIGHT OF THE BENEFITS CONFERRED BY ITS USE (SEE INDICATIONS ).
ORDINARILY, A PATIENT SHOULD NOT BE PLACED ON AND/OR CONTINUED ON FELBAMATE WITHOUT CONSIDERATION OF APPROPRIATE EXPERT HEMATOLOGIC CONSULTATION. AMONG FELBAMATE TREATED PATIENTS, APLASTIC ANEMIA (PANCYTOPENIA IN THE PRESENCE OF A BONE MARROW LARGELY DEPLETED OF HEMATOPOIETIC PRECURSORS) OCCURS AT AN INCIDENCE THAT MAY BE MORE THAN A 100 FOLD GREATER THAN THAT SEEN IN THE UNTREATED POPULATION (I.E., 2 TO 5 PER MILLION PERSONS PER YEAR). THE RISK OF DEATH IN PATIENTS WITH APLASTIC ANEMIA GENERALLY VARIES AS A FUNCTION OF ITS SEVERITY AND ETIOLOGY; CURRENT ESTIMATES OF THE OVERALL CASE FATALITY RATE ARE IN THE RANGE OF 20 TO 30%, BUT RATES AS HIGH AS 70% HAVE BEEN REPORTED IN THE PAST.
THERE ARE TOO FEW FELBAMATE ASSOCIATED CASES, AND TOO LITTLE KNOWN ABOUT THEM TO PROVIDE A RELIABLE ESTIMATE OF THE SYNDROME'S INCIDENCE OR ITS CASE FATALITY RATE OR TO IDENTIFY THE FACTORS, IF ANY, THAT MIGHT CONCEIVABLY BE USED TO PREDICT WHO IS AT GREATER OR LESSER RISK. IN MANAGING PATIENTS ON FELBAMATE, IT SHOULD BE BORNE IN MIND THAT THE CLINICAL MANIFESTATION OF APLASTIC ANEMIA MAY NOT BE SEEN UNTIL AFTER A PATIENT HAS BEEN ON FELBAMATE FOR SEVERAL MONTHS (E.G., ONSET OF APLASTIC ANEMIA AMONG FELBAMATE EXPOSED PATIENTS FOR WHOM DATA ARE AVAILABLE HAS RANGED FROM 5 TO 30 WEEKS).
HOWEVER, THE INJURY TO BONE MARROW STEM CELLS THAT IS HELD TO BE ULTIMATELY RESPONSIBLE FOR THE ANEMIA MAY OCCUR WEEKS TO MONTHS EARLIER. ACCORDINGLY, PATIENTS WHO ARE DISCONTINUED FROM FELBAMATE REMAIN AT RISK FOR DEVELOPING ANEMIA FOR A VARIABLE, AND UNKNOWN, PERIOD AFTERWARDS. IT IS NOT KNOWN WHETHER OR NOT THE RISK OF DEVELOPING APLASTIC ANEMIA CHANGES WITH DURATION OF EXPOSURE.
CONSEQUENTLY, IT IS NOT SAFE TO ASSUME THAT A PATIENT WHO HAS BEEN ON FELBAMATE WITHOUT SIGNS OF HEMATOLOGIC ABNORMALITY FOR LONG PERIODS OF TIME IS WITHOUT RISK. IT IS NOT KNOWN WHETHER OR NOT THE DOSE OF FELBAMATE AFFECTS THE INCIDENCE OF APLASTIC ANEMIA. IT IS NOT KNOWN WHETHER OR NOT CONCOMITANT USE OF ANTIEPILEPTIC DRUGS AND/OR OTHER DRUGS AFFECTS THE INCIDENCE OF APLASTIC ANEMIA.
APLASTIC ANEMIA TYPICALLY DEVELOPS WITHOUT PREMONITORY CLINICAL OR LABORATORY SIGNS, THE FULL BLOWN SYNDROME PRESENTING WITH SIGNS OF INFECTION, BLEEDING, OR ANEMIA. ACCORDINGLY, ROUTINE BLOOD TESTING CANNOT BE RELIABLY USED TO REDUCE THE INCIDENCE OF APLASTIC ANEMIA, BUT, IT WILL, IN SOME CASES, ALLOW THE DETECTION OF THE HEMATOLOGIC CHANGES BEFORE THE SYNDROME DECLARES ITSELF CLINICALLY. FELBAMATE SHOULD BE DISCONTINUED IF ANY EVIDENCE OF BONE MARROW DEPRESSION OCCURS.
2. HEPATIC FAILURE EVALUATION OF POSTMARKETING EXPERIENCE SUGGESTS THAT ACUTE LIVER FAILURE IS ASSOCIATED WITH THE USE OF FELBAMATE. THE REPORTED RATE IN THE U.S.
HAS BEEN ABOUT 6 CASES OF LIVER FAILURE LEADING TO DEATH OR TRANSPLANT PER 75,000 PATIENT YEARS OF USE. THIS RATE IS AN UNDERESTIMATE BECAUSE OF UNDER REPORTING, AND THE TRUE RATE COULD BE CONSIDERABLY GREATER THAN THIS. FOR EXAMPLE, IF THE REPORTING RATE IS 10%, THE TRUE RATE WOULD BE ONE CASE PER 1,250 PATIENT YEARS OF USE.
OF THE CASES REPORTED, ABOUT 67% RESULTED IN DEATH OR LIVER TRANSPLANTATION, USUALLY WITHIN 5 WEEKS OF THE ONSET OF SIGNS AND SYMPTOMS OF LIVER FAILURE. THE EARLIEST ONSET OF SEVERE HEPATIC DYSFUNCTION FOLLOWED SUBSEQUENTLY BY LIVER FAILURE WAS 3 WEEKS AFTER INITIATION OF FELBAMATE. ALTHOUGH SOME REPORTS DESCRIBED DARK URINE AND NONSPECIFIC PRODROMAL SYMPTOMS (E.G., ANOREXIA, MALAISE, AND GASTROINTESTINAL SYMPTOMS), IN OTHER REPORTS IT WAS NOT CLEAR IF ANY PRODROMAL SYMPTOMS PRECEDED THE ONSET OF JAUNDICE.
IT IS NOT KNOWN WHETHER OR NOT THE RISK OF DEVELOPING HEPATIC FAILURE CHANGES WITH DURATION OF EXPOSURE. IT IS NOT KNOWN WHETHER OR NOT… [Excerpted — this section continues on DailyMed.]
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Felbamate oral suspension is not indicated as a first line antiepileptic treatment (see Warnings ). Felbamate oral suspension is recommended for use only in those patients who respond inadequately to alternative treatments and whose epilepsy is so severe that a substantial risk of aplastic anemia and/or liver failure is deemed acceptable in light of the benefits conferred by its use. If these criteria are met and the patient has been fully advised of the risk, and has provided written acknowledgment, felbamate oral suspension can be considered for either monotherapy or adjunctive therapy in the treatment of partial seizures, with and without generalization, in adults with epilepsy and as adjunctive therapy in the treatment of partial and generalized seizures associated with Lennox-Gastaut syndrome in children.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Felbamate oral suspension has been studied as monotherapy and adjunctive therapy in adults and as adjunctive therapy in children with seizures associated with Lennox-Gastaut syndrome. As felbamate oral suspension is added to or substituted for existing AEDs, it is strongly recommended to reduce the dosage of those AEDs in the range of 20% to 33% to minimize side effects (see Drug Interactions subsection). Dosage Adjustment in the Renally Impaired: Felbamate should be used with caution in patients with renal dysfunction.
In the renally impaired, starting and maintenance doses should be reduced by one-half (see CLINICAL PHARMACOLOGY / Pharmacokinetics and PRECAUTIONS ). Adjunctive therapy with medications which affect felbamate plasma concentrations, especially AEDs, may warrant further reductions in felbamate daily doses in patients with renal dysfunction. Adults (14 years of age and over) The majority of patients received 3600 mg/day in clinical trials evaluating its use as both monotherapy and adjunctive therapy.
Monotherapy: (Initial therapy) Felbamate oral suspension has not been systematically evaluated as initial monotherapy. Initiate felbamate oral suspension at 1200 mg/day in divided doses three or four times daily. The prescriber is advised to titrate previously untreated patients under close clinical supervision, increasing the dosage in 600-mg increments every 2 weeks to 2400 mg/day based on clinical response and thereafter to 3600 mg/day if clinically indicated.
Conversion to Monotherapy: Initiate felbamate oral suspension at 1200 mg/day in divided doses three or four times daily. Reduce the dosage of concomitant AEDs by one-third at initiation of felbamate oral suspension therapy. At week 2, increase the felbamate oral suspension dosage to 2400 mg/day while reducing the dosage of other AEDs up to an additional one-third of their original dosage.
At week 3, increase the felbamate oral suspension dosage up to 3600 mg/day and continue to reduce the dosage of other AEDs as clinically indicated. Adjunctive Therapy: Felbamate oral suspension should be added at 1200 mg/day in divided doses three or four times daily while reducing present AEDs by 20% in order to control plasma concentrations of concurrent phenytoin, valproic acid, phenobarbital, and carbamazepine and its metabolites. Further reductions of the concomitant AEDs dosage may be necessary to minimize side effects due to drug interactions.
Increase the dosage of felbamate oral suspension by 1200 mg/day increments at weekly intervals to 3600 mg/day. Most side effects seen during felbamate oral suspension adjunctive therapy resolve as the dosage of concomitant AEDs is decreased. Table 6 Dosage Table (adults) Dosage reduction of concomitant AEDs WEEK 1 REDUCE original dose by 20% to 33%* WEEK 2 REDUCE original dose by up to an additional 1/3* WEEK 3 REDUCE as clinically indicated Felbamate Oral Suspension Dosage 1200 mg/day Initial dose 2400 mg/day Therapeutic dosage range 3600 mg/day Therapeutic dosage range *See Adjunctive and Conversion to Monotherapy sections.
While the above felbamate oral suspension conversion guidelines may result in a felbamate oral suspension 3600 mg/day dose within 3 weeks, in some patients titration to a 3600 mg/day felbamate oral suspension, USP dose has been achieved in as little as 3 days with appropriate adjustment of other AEDs. Children with Lennox-Gastaut Syndrome (Ages 2 to 14 years) Adjunctive Therapy: Felbamate oral suspension should be added at 15 mg/kg/day in divided doses three or four times daily while reducing present AEDs by 20% in order to control plasma levels of concurrent phenytoin, valproic acid, phenobarbital, and carbamazepine and its metabolites.
Further reductions of the concomitant AEDs dosage may be necessary to minimize side effects due to drug interactions. Increase the dosage of felbamate oral suspension by 15 mg/kg/day increments at weekly intervals to 45 mg/kg/day. Most side effect… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Felbamate oral suspension is contraindicated in patients with known hypersensitivity to felbamate, its ingredients, or known sensitivity to other carbamates. It should not be used in patients with a history of any blood dyscrasia or hepatic dysfunction.
⚠️ Warnings ▾
WARNINGS See Boxed Warning regarding aplastic anemia and hepatic failure. Antiepileptic drugs should not be suddenly discontinued because of the possibility of increasing seizure frequency. Suicidal Behavior and Ideation Antiepileptic drugs (AEDs) including felbamate, increase the risk of suicidal thoughts or behavior in patients taking these drugs for any indication.
Patients treated with any AED for any indication should be monitored for the emergence or worsening of depression, suicidal thoughts or behavior, and/or any unusual changes in mood or behavior. Pooled analyses of 199 placebo-controlled clinical trials (mono- and adjunctive therapy) of 11 different AEDs showed that patients randomized to one of the AEDs had approximately twice the risk (adjusted Relative Risk 1.8, 95% CI:1.2, 2.7) of suicidal thinking or behavior compared to patients randomized to placebo. In these trials, which had a median treatment duration of 12 weeks, the estimated incidence rate of suicidal behavior or ideation among 27,863 AED-treated patients was 0.43%, compared to 0.24% among 16,029 placebo-treated patients, representing an increase of approximately one case of suicidal thinking or behavior for every 530 patients treated.
There were four suicides in drug-treated patients in the trials and none in placebo-treated patients, but the number is too small to allow any conclusion about drug effect on suicide. The increased risk of suicidal thoughts or behavior with AEDs was observed as early as one week after starting drug treatment with AEDs and persisted for the duration of treatment assessed. Because most trials included in the analysis did not extend beyond 24 weeks, the risk of suicidal thoughts or behavior beyond 24 weeks could not be assessed.
The risk of suicidal thoughts or behavior was generally consistent among drugs in the data analyzed. The finding of increased risk with AEDs of varying mechanisms of action and across a range of indications suggests that the risk applies to all AEDs used for any indication. The risk did not vary substantially by age (5 to 100 years) in the clinical trials analyzed.
Table 1 shows absolute and relative risk by indication for all evaluated AEDs. Table 1 Risk by Indication for Antiepileptic Drugs in the Pooled Analysis Indication Placebo Patientswith Events Per 1000 Patients Drug Patients with Events Per1000 Patients Relative Risk:Incidence ofEvents in DrugPatients/Incidencein Placebo Patients Risk Difference:Additional DrugPatients withEvents Per 1000Patients Epilepsy 1 3.4 3.5
2.4Psychiatric 5.7 8.5 1.5
2.9Other 1 1.8 1.9
0.9Total 2.4 4.3 1.8
1.9The relative risk for suicidal thoughts or behavior was higher in clinical trials for epilepsy than in clinical trials for psychiatric or other conditions, but the absolute risk differences were similar for the epilepsy and psychiatric indications. Anyone considering prescribing felbamate or any other AED must balance the risk of suicidal thoughts or behavior with the risk of untreated illness. Epilepsy and many other illnesses for which AEDs are prescribed are themselves associated with morbidity and mortality and an increased risk of suicidal thoughts and behavior.
Should suicidal thoughts and behavior emerge during treatment, the prescriber needs to consider whether the emergence of these symptoms in any given patient may be related to the illness being treated. Patients, their caregivers, and families should be informed that AEDs increase the risk of suicidal thoughts and behavior and should be advised of the need to be alert for the emergence or worsening of the signs and symptoms of depression, any unusual changes in mood or behavior, or the emergence of suicidal thoughts, behavior, or thoughts about self-harm.
Behaviors of concern should be reported immediately to healthcare providers.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The most common adverse reactions seen in association with felbamate in adults during monotherapy, are anorexia, vomiting, insomnia, nausea, and headache. The most common adverse reactions seen in association with felbamate in adults during adjunctive therapy are anorexia, vomiting, insomnia, nausea, dizziness, somnolence, and headache. The most common adverse reactions seen in association with felbamate in children during adjunctive therapy are anorexia, vomiting, insomnia, headache, and somnolence.
The dropout rate because of adverse experiences or intercurrent illnesses among adult felbamate patients was 12 percent (120/977). The dropout rate because of adverse experiences or intercurrent illnesses among pediatric felbamate patients was six percent (22/357). In adults, the body systems associated with causing these withdrawals in order of frequency were: digestive (4.3%), psychological (2.2%), whole body (1.7%), neurological (1.5%), and dermatological (1.5%).
In children, the body systems associated with causing these withdrawals in order of frequency were: digestive (1.7%), neurological (1.4%), dermatological (1.4%), psychological (1.1%), and whole body (1%). In adults, specific events with an incidence of 1% or greater associated with causing these withdrawals, in order of frequency were: anorexia (1.6%), nausea (1.4%), rash (1.2%), and weight decrease (1.1%). In children, specific events with an incidence of 1% or greater associated with causing these withdrawals, in order of frequency was rash (1.1%).
Incidence in Clinical Trials: The prescriber should be aware that the figures cited in the following table cannot be used to predict the incidence of side effects in the course of usual medical practice where patient characteristics and other factors differ from those which prevailed in the clinical trials. Similarly, the cited frequencies cannot be compared with figures obtained from other clinical investigations involving different investigators, treatments, and uses including the use of felbamate as adjunctive therapy where the incidence of adverse events may be higher due to drug interactions.
The cited figures, however, do provide the prescribing physician with some basis for estimating the relative contribution of drug and nondrug factors to the side effect incidence rate in the population studied. Adults Incidence in Controlled Clinical Trials--Monotherapy Studies in Adults: The table that follows enumerates adverse events that occurred at an incidence of 2% or more among 58 adult patients who received felbamate monotherapy at dosages of 3600 mg/day in double-blind controlled trials. Table 3 presents reported adverse events that were classified using standard WHO-based dictionary terminology.
Table 3 Adults Treatment-Emergent Adverse Event Incidence in Controlled Monotherapy Trials Felbamate* (N=58) Low Dose Valproate** (N=50) Body System Event % % Body as a Whole Fatigue 6.9 4 Weight Decrease 3.4 0 Face Edema 3.4 0 Central Nervous System Insomnia 8.6 4 Headache 6.9 18 Anxiety 5.2 2 Dermatological Acne 3.4 0 Rash 3.4 0 Digestive Dyspepsia 8.6 2 Vomiting 8.6 2 Constipation 6.9 2 Diarrhea 5.2 0 SGPT Increased 5.2 2 Metabolic/Nutritional Hypophosphatemia 3.4 0 Respiratory Upper Respiratory Tract Infection 8.6 4 Rhinitis 6.9 0 Special Senses Diplopia 3.4 4 Otitis Media 3.4 0 Urogenital Intramenstrual Bleeding 3.4 0 Urinary Tract Infection 3.4 2 *3600 mg/day, ** 15 mg/kg/day Incidence in Controlled Add-On Clinical Studies in Adults: Table 4 enumerates adverse events that occurred at an incidence of 2% or more among 114 adult patients who received felbamate adjunctive therapy in add-on controlled trials at dosages up to 3600 mg/day.
Reported adverse events were classified using standard WHO-based dictionary terminology. Many adverse experiences that occurred during adjunctive therapy may be a result of drug interactions. Adverse experiences during adjunctive therapy typically resolved with conversion to… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
OVERDOSAGE Four subjects inadvertently received felbamate as adjunctive therapy in dosages ranging from 5400 to 7200 mg/day for durations between 6 and 51 days. One subject who received 5400 mg/day as monotherapy for 1 week reported no adverse experiences. Another subject attempted suicide by ingesting 12,000 mg of felbamate in a 12-hour period.
The only adverse experiences reported were mild gastric distress and a resting heart rate of 100 bpm. No serious adverse reactions have been reported. General supportive measures should be employed if overdosage occurs.
It is not known if felbamate is dialyzable.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action: The mechanism by which felbamate exerts its anticonvulsant activity is unknown, but in animal test systems designed to detect anticonvulsant activity, felbamate has properties in common with other marketed anticonvulsants. Felbamate is effective in mice and rats in the maximal electroshock test, the subcutaneous pentylenetetrazol seizure test, and the subcutaneous picrotoxin seizure test. Felbamate also exhibits anticonvulsant activity against seizures induced by intracerebroventricular administration of glutamate in rats and N-methyl-D,L-aspartic acid in mice.
Protection against maximal electroshock-induced seizures suggests that felbamate may reduce seizure spread, an effect possibly predictive of efficacy in generalized tonic-clonic or partial seizures. Protection against pentylenetetrazol-induced seizures suggests that felbamate may increase seizure threshold, an effect considered to be predictive of potential efficacy in absence seizures. Receptor-binding studies in vitro indicate that felbamate has weak inhibitory effects on GABA-receptor binding, benzodiazepine receptor binding, and is devoid of activity at the MK-801 receptor binding site of the NMDA receptor-ionophore complex.
However, felbamate does interact as an antagonist at the strychnine-insensitive glycine recognition site of the NMDA receptor-ionophore complex. Felbamate is not effective in protecting chick embryo retina tissue against the neurotoxic effects of the excitatory amino acid agonists NMDA, kainate, or quisqualate in vitro. The monocarbamate, p-hydroxy, and 2-hydroxy metabolites were inactive in the maximal electroshockinduced seizure test in mice.
The monocarbamate and p-hydroxy metabolites had only weak (0.2 to 0.6) activity compared with felbamate in the subcutaneous pentylenetetrazol seizure test. These metabolites did not contribute significantly to the anticonvulsant action of felbamate. Pharmacokinetics: The numbers in the pharmacokinetic section are mean ± standard deviation.
Felbamate is well-absorbed after oral administration. Over 90% of the radioactivity after a dose of 1000 mg 14 C felbamate was found in the urine. Absolute bioavailability (oral vs. parenteral) has not been measured.
The suspension was shown to be bioequivalent to the capsule used in clinical trials, and pharmacokinetic parameters of the tablet and suspension are similar. The effect of food on absorption of the suspension has not been evaluated. Following oral administration, felbamate is the predominant plasma species (about 90% of plasma radioactivity).
About 40% to 50% of absorbed dose appears unchanged in urine, and an additional 40% is present as unidentified metabolites and conjugates. About 15% is present as parahydroxyfelbamate, 2hydroxyfelbamate, and felbamate monocarbamate, none of which have significant anticonvulsant activity. Binding of felbamate to human plasma protein was independent of felbamate concentrations between 10 and 310 micrograms/mL.
Binding ranged from 22% to 25%, mostly to albumin, and was dependent on the albumin concentration. Felbamate is excreted with a terminal half-life of 20 to 23 hours, which is unaltered after multiple doses. Clearance after a single 1200 mg dose is 26±3 mL/hr/kg, and after multiple daily doses of 3600 mg is 30±8 mL/hr/kg.
The apparent volume of distribution was 756±82 mL/kg after a 1200 mg dose. Felbamate C max and AUC are proportionate to dose after single and multiple doses over a range of 100 to 800 mg single doses and 1200 to 3600 mg daily doses. C min (trough) blood levels are also dose proportional.
Multiple daily doses of 1200, 2400, and 3600 mg gave C min values of 30±5, 55±8, and 83±21 micrograms/mL (N=10 patients). Linear and dose proportional pharmacokinetics were also observed at doses above 3600 mg/day up to the maximum dose studied of 6000 mg/day. Felbamate gave dose proportional steady-state peak plasma concentrations in children age 4 to 12 over a range of… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Felbamate Oral Suspension, USP, 600 mg/5 mL , is a pink-colored bubble gum flavored suspension; available in 8 oz bottles (NDC 65162-686-88) and 16 oz bottles (NDC 65162-686-90). Shake suspension well before using. Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Dispense in a tight container. Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev. 02-2017-03
📋 Description ▾
DESCRIPTION Felbamate, USP is an antiepileptic available as a 600 mg/5 mL suspension for oral administration. Its chemical name is 2-phenyl-1,3-propanediol dicarbamate. Felbamate, USP is a white to off-white crystalline powder with a characteristic odor.
It is very slightly soluble in water, slightly soluble in ethanol, sparingly soluble in methanol, and freely soluble in dimethyl sulfoxide. The molecular weight is 238.24; felbamate, USP molecular formula is C 11 H 14 N 2 O 4 ; its structural formula is: The inactive ingredients for felbamate oral suspension, USP 600 mg/5 mL are bubble gum flavor, carboxymethyl cellulose sodium, FD&C Yellow No. 6, FD&C Red No.
40, glycerin, methylparaben, microcrystalline cellulose, polysorbate 80, propylparaben, purified water, saccharin sodium, simethicone, and sorbitol. 8e2ca93c-figure-01
💬 Medication Guide ▾
Medication Guide Felbamate (fel-BAM-ate) Oral Suspension, USP Read this Medication Guide before you start taking felbamate oral suspension and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or treatment.
What is the most important information I should know about felbamate oral suspension? Do not stop taking felbamate oral suspension without first talking to your healthcare provider. Stopping felbamate oral suspension suddenly can cause serious problems.
Felbamate oral suspension can cause serious side effects, including: 1. Felbamate oral suspension may cause serious blood problems that may be life-threatening. Call your healthcare provider right away if you have any of the following symptoms: Fever, sore throat or other infections that come and go or do not go away Frequent infections or an infection that does not go away Easy bruising Red or purple spots on your body Bleeding gums or nose bleeds Severe fatigue or weakness 2.
Liver problems that may be life-threatening. Call your healthcare provider right away if you have any of these symptoms: yellowing of your skin or the whites of your eyes (jaundice) dark urine nausea or vomiting loss of appetite pain on the right side of your stomach (abdomen) 3. Like other antiepileptic drugs, felbamate oral suspension may cause suicidal thoughts or actions in a very small number of people, about 1 in 500.
Call your healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood How can I watch for early symptoms of suicidal thoughts and actions?
Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you are worried about symptoms.
Do not stop felbamate oral suspension without first talking to a healthcare provider. Stopping felbamate oral suspension suddenly can cause serious problems. You should talk to your health care provider before stopping.
Stopping a seizure medicine suddenly in a patient who has epilepsy can cause seizures. Suicidal thoughts or actions can be caused by things other than medicines. If you have suicidal thoughts or actions, your healthcare provider may check for other causes.
What is felbamate oral suspension? Felbamate oral suspension is a prescription medicine used when other treatments have failed in: adults alone or with other medicines to treat: partial seizures with and without generalization children with other medicines to treat: seizures associated with Lennox-Gastaut syndrome Who should not take felbamate oral suspension? Do not take felbamate oral suspension if you: are allergic to felbamate, carbamates or any of the ingredients in felbamate oral suspension.
See the end of this Medication Guide for a complete list of ingredients in felbamate oral suspension. have or have had blood problems have or have had liver problems What should I tell my healthcare provider before taking felbamate oral suspension? Before you take felbamate oral suspension, tell your healthcare provider if you: have kidney problems have or have had depression, mood problems, or suicidal thoughts or behavior have any other medical conditions are pregnant or plan to become pregnant. It is not known if felbamate oral suspension can harm your unborn baby.
Tell your healthcare provider right away if you become pregnant while taking felbamate oral suspension. You and your health… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS Dosage Adjustment in the Renally Impaired: A study in otherwise healthy individuals with renal dysfunction indicated that prolonged half-life and reduced clearance of felbamate are associated with diminishing renal function. Felbamate should be used with caution in patients with renal dysfunction (see DOSAGE AND ADMINISTRATION ) . Information for Patients: Patients should be informed that the use of felbamate is associated with aplastic anemia and hepatic failure, potentially fatal conditions acutely or over a long term.
The physician should obtain written acknowledgment prior to initiation of felbamate therapy (see PATIENT/PHYSICIAN ACKNOWLEDGMENT FORM section). Patients should be instructed to read the Medication Guide supplied as required by law when felbamate is dispensed. The complete text of the Medication Guide is reprinted at the end of this document.
Aplastic anemia in the general population is relatively rare. The absolute risk for the individual patient is not known with any degree of reliability, but patients on felbamate may be at more than a 100 fold greater risk for developing the syndrome than the general population. The long term outlook for patients with aplastic anemia is variable.
Although many patients are apparently cured, others require repeated transfusions and other treatments for relapses, and some, although surviving for years, ultimately develop serious complications that sometimes prove fatal (e.g., leukemia). At present there is no way to predict who is likely to get aplastic anemia, nor is there a documented effective means to monitor the patient so as to avoid and/or reduce the risk. Patients with a history of any blood dyscrasia should not receive felbamate.
Patients should be advised to be alert for signs of infection, bleeding, easy bruising, or signs of anemia (fatigue, weakness, lassitude, etc.) and should be advised to report to the physician immediately if any such signs or symptoms appear. Hepatic failure in the general population is relatively rare. The absolute risk for an individual patient is not known with any degree of reliability but patients on felbamate are at a greater risk for developing hepatic failure than the general population.
At present, there is no way to predict who is likely to develop hepatic failure, however, patients with a history of hepatic dysfunction should not be started on felbamate. Patients should be advised to follow their physician's directives for liver function testing both before starting felbamate and at frequent intervals while taking felbamate. Patients should be advised to be alert for signs of liver dysfunction (jaundice, anorexia, gastrointestinal complaints, malaise, etc.) and to report them to their doctor immediately if they should occur.
Laboratory Tests: Full hematologic evaluations should be performed before felbamate therapy, frequently during therapy, and for a significant period of time after discontinuation of felbamate therapy. While it might appear prudent to perform frequent CBCs in patients continuing on felbamate, there is no evidence that such monitoring will allow early detection of marrow suppression before aplastic anemia occurs (see Boxed Warnings ). Complete pretreatment blood counts, including platelets and reticulocytes should be obtained as a baseline.
If any hematologic abnormalities are detected during the course of treatment, immediate consultation with a hematologist is advised. Felbamate should be discontinued if any evidence of bone marrow depression occurs. See Box Warnings for recommended monitoring of serum transaminases.
If significant, confirmed liver abnormalities are detected during the course of felbamate treatment, felbamate should be discontinued immediately with continued liver function monitoring until values return to normal (see PATIENT/PHYSICIAN ACKNOWLEDGMENT FORM ). Suicidal Thinking and Behavior: Patients, their caregivers, and families should be counseled that AEDs, including felbamate,… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
CLINICAL STUDIES The results of controlled clinical trials established the efficacy of felbamate as monotherapy and adjunctive therapy in adults with partial-onset seizures with or without secondary generalization and in partial and generalized seizures associated with Lennox-Gastaut syndrome in children. Felbamate Monotherapy Trials in Adults Felbamate (3600 mg/day given QID) and low-dose valproate (15 mg/kg/day) were compared as monotherapy during a 112-day treatment period in a multicenter and a single-center double-blind efficacy trial.
Both trials were conducted according to an identical study design. During a 56-day baseline period, all patients had at least four partial-onset seizures per 28 days and were receiving one antiepileptic drug at a therapeutic level, the most common being carbamazepine. In the multicenter trial, baseline seizure frequencies were 12.4 per 28 days in the felbamate group and 21.3 per 28 days in the low-dose valproate group.
In the single-center trial, baseline seizure frequencies were 18.1 per 28 days in the felbamate group and 15.9 per 28 days in the low-dose valproate group. Patients were converted to monotherapy with felbamate or low-dose valproic acid during the first 28 days of the 112-day treatment period. Study endpoints were completion of 112 study days or fulfilling an escape criterion.
Criteria for escape relative to baseline were: (1) twofold increase in monthly seizure frequency, (2) twofold increase in highest 2-day seizure frequency, (3) single generalized tonic-clonic seizure (GTC) if none occurred during baseline, or (4) significant prolongation of GTCs. The primary efficacy variable was the number of patients in each treatment group who met escape criteria. In the multicenter trial, the percentage of patients who met escape criteria was 40% (18/45) in the felbamate group and 78% (39/50) in the low-dose valproate group.
In the single-center trial, the percentage of patients who met escape criteria was 14% (3/21) in the felbamate group and 90% (19/21) in the low-dose valproate group. In both trials, the difference in the percentage of patients meeting escape criteria was statistically significant (P<.001) in favor of felbamate. These two studies by design were intended to demonstrate the effectiveness of Felbamate monotherapy.
The studies were not designed or intended to demonstrate comparative efficacy of the two drugs. For example, valproate was not used at the maximally effective dose. Felbamate Adjunctive Therapy Trials in Adults A double-blind, placebo-controlled crossover trial consisted of two 10-week outpatient treatment periods.
Patients with refractory partial-onset seizures who were receiving phenytoin and carbamazepine at therapeutic levels were administered felbamate as add-on therapy at a starting dosage of 1400 mg/day in three divided doses, which was increased to 2600 mg/day in three divided doses. Among the 56 patients who completed the study, the baseline seizure frequency was 20 per month. Patients treated with felbamate had fewer seizures than patients treated with placebo for each treatment sequence.
There was a 23% (P=.018) difference in percentage seizure frequency reduction in favor of felbamate. Felbamate 3600 mg/day given QID and placebo were compared in a 28-day double-blind add-on trial in patients who had their standard antiepileptic drugs reduced while undergoing evaluations for surgery of intractable epilepsy. All patients had confirmed partial-onset seizures with or without generalization, seizure frequency during surgical evaluation not exceeding an average of four partial seizures per day or more than one generalized seizure per day, and a minimum average of one partial or generalized tonicclonic seizure per day for the last 3 days of the surgical evaluation.
The primary efficacy variable was time to fourth seizure after randomization to treatment with felbamate or placebo. Thirteen (46%) of 28 patients in the felbamate group versus 29 (88%) of 3… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
DRUG ABUSE AND DEPENDENCE Abuse: Abuse potential was not evaluated in human studies. Dependence: Rats administered felbamate orally at doses 8.3 times the recommended human dose 6 days each week for 5 consecutive weeks demonstrated no signs of physical dependence as measured by weight loss following drug withdrawal on day 7 of each week.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Bottle Label
Medicaid utilization & spend
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |