
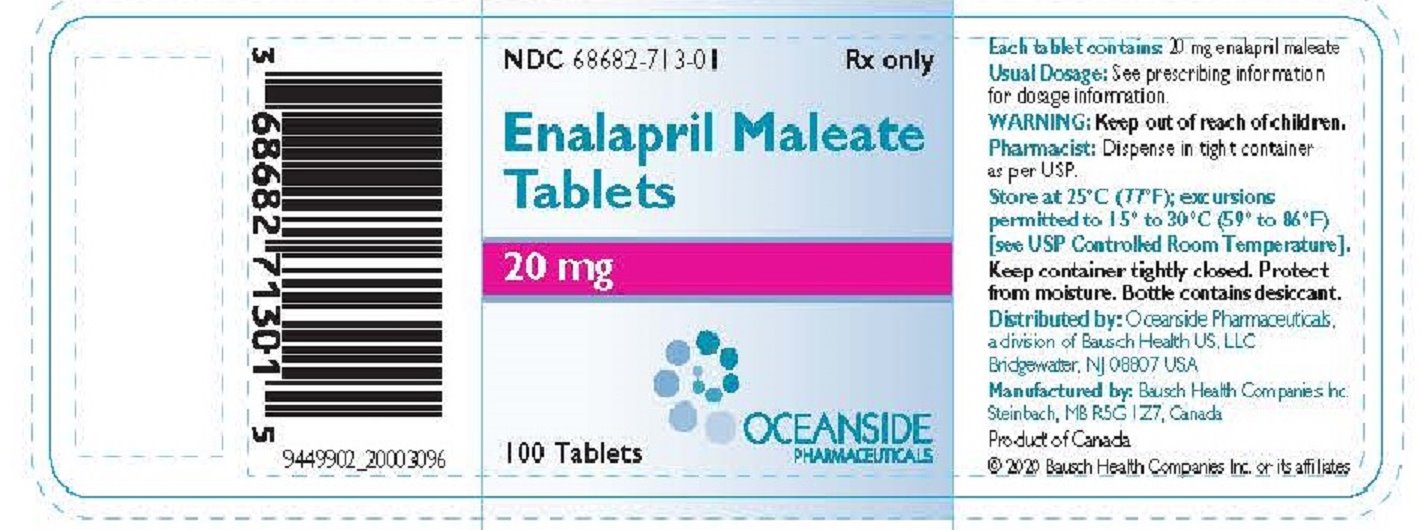
Enalapril Maleate 20 mg Tablet, 1,000-count
Other active recalls for Enalapril Maleate (different manufacturers) — 5 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Angiotensin Converting Enzyme Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Enalapril is mainly used for three things: lowering high blood pressure, treating heart failure when you have symptoms like breathlessness or fatigue, and treating a condition wher...
- A dry, persistent cough is one of the most common side effects of enalapril and other ACE inhibitors — it affects some people more than others. If the cough becomes bothersome, let...
- No — enalapril is not safe during pregnancy. It can seriously injure or even cause the death of an unborn baby, especially in the second and third trimesters. If you're planning a...
- Is it safe to take enalapril if I'm pregnant or trying to get pregnant?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Enalapril Maleate — tap one for details:
Enalapril Maleate may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII J2B2A4N98G
Lactose is a natural sugar derived from milk. In medications, it serves as a filler and binder to add bulk and help hold tablet or capsule ingredients together during manufacturing.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 8MDF5V39QO
A white powder form of baking soda that acts as a buffer and pH regulator in medicines. It helps maintain the right acid-base balance and may aid tablet disintegration.
-
UNII QU7E2XA9TG
Sodium stearate is a salt derived from stearic acid, a natural fatty substance. It acts as a lubricant and binder in tablets and capsules, helping the medicine hold together and flow smoothly during manufacturing.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.116 | $116.30 / 1000 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.1937 | $193.70 / 1000 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.1390 | $139.00 / 1000 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Enalapril maleate 20 mg 00904-7312-61 | Major | 100 tablets | $0.099 | AB | Availability likely | save 15% |
| Enalapril Maleate 20 mg 16714-0445-01 | Northstar | 100 tablets | $0.099 | AB | Availability likely | save 15% |
| Enalapril maleate 20 mg 23155-0773-01 | Heritage | 100 tablets | $0.099 | AB | Availability likely | save 15% |
| Enalapril Maleate 20 mg 50228-0231-01 | ScieGen | 100 tablets | $0.099 | AB | Availability likely | save 15% |
| Enalapril Maleate 20 mg 51672-4040-01 | Sun | 100 tablets | $0.099 | AB | Availability likely | save 15% |
| Enalapril maleate 20 mg 62135-0592-90 | Chartwell | 90 tablets | $0.099 | AB | Availability likely | save 15% |
| Enalapril Maleate 20 mg 64980-0688-01 | Rising | 100 tablets | $0.099 | AB | Availability likely | save 15% |
| Enalapril maleate 20 mg 68645-0607-90 | Legacy | 90 tablets | $0.099 | AB | Availability likely | save 15% |
| Enalapril Maleate 20 mg 69292-0546-01 | Amici | 100 tablets | $0.099 | AB | Availability likely | save 15% |
| Enalapril Maleate 20 mgthis 68682-0713-10 | OCEANSIDE | 1000 tablets | $0.116 | AB | FDA listed | — |
| Vasotec 20 mg 00187-0143-10 | Bausch | 1000 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 43547-0548-03 | Solco | 30 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 50090-4560-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Enalapril maleate 20 mg 50090-6437-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 50090-7677-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Enalapril maleate 20 mg 51655-0058-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 51655-0341-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 60429-0186-10 | Golden | 1000 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 60760-0575-30 | St. | 30 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 63187-0977-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 68071-3408-01 | NuCare | 100 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 68071-3820-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 68788-8320-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 70518-4011-01 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Enalapril maleate 20 mg 70518-4153-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 71335-9649-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 71335-9698-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 72789-0318-90 | PD-Rx | 90 tablets | — | AB | FDA listed | — |
| Enalapril Maleate 20 mg 68788-4147-00 | Preferred | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 68682-0713-01 | 100 TABLET in 1 BOTTLE (68682-713-01) | $0.1163 / ea | $11.63 | 1985-12-24 | Active |
| 68682-0713-10 You're viewing this | 1000 TABLET in 1 BOTTLE (68682-713-10) | $0.1163 / ea | $116.34 | 1985-12-24 | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($0.1163 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 76% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 68682-0713-10?
What is the difference between NDC 68682-0713-10 and NDC 68682-0713-01?
What NDC number is used to bill for this package of Enalapril Maleate 20 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning. • When pregnancy is detected, discontinue Enalapril Maleate Tablets as soon as possible. • Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. (See WARNINGS, Fetal Toxicity .)
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Hypertension Enalapril Maleate Tablets are indicated for the treatment of hypertension. Enalapril Maleate Tablets are effective alone or in combination with other antihypertensive agents, especially thiazide-type diuretics. The blood pressure lowering effects of Enalapril Maleate Tablets and thiazides are approximately additive.
Heart Failure Enalapril Maleate Tablets are indicated for the treatment of symptomatic congestive heart failure, usually in combination with diuretics and digitalis. In these patients Enalapril Maleate Tablets improve symptoms, increases survival, and decreases the frequency of hospitalization (see CLINICAL PHARMACOLOGY, Heart Failure, Mortality Trials for details and limitations of survival trials). Asymptomatic Left Ventricular Dysfunction In clinically stable asymptomatic patients with left ventricular dysfunction (ejection fraction ≤35 percent), Enalapril Maleate Tablets decrease the rate of development of overt heart failure and decreases the incidence of hospitalization for heart failure (see CLINICAL PHARMACOLOGY , Heart Failure , Mortality Trials for details and limitations of survival trials).
In using Enalapril Maleate Tablets consideration should be given to the fact that another angiotensin- converting enzyme inhibitor, captopril, has caused agranulocytosis, particularly in patients with renal impairment or collagen vascular disease, and that available data are insufficient to show that Enalapril Maleate Tablets do not have a similar risk (see WARNINGS , Neutropenia/Agranulocytosis ). In considering use of Enalapril Maleate Tablets, it should be noted that in controlled clinical trials ACE inhibitors have an effect on blood pressure that is less in black patients than in non-blacks.
In addition, it should be noted that black patients receiving ACE inhibitors have been reported to have a higher incidence of angioedema compared to non-blacks (see WARNINGS , Head and Neck Angioedema ).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Hypertension In patients who are currently being treated with a diuretic, symptomatic hypotension occasionally may occur following the initial dose of Enalapril Maleate Tablets. The diuretic should, if possible, be discontinued for two to three days before beginning therapy with Enalapril Maleate Tablets to reduce the likelihood of hypotension (see WARNINGS , Hypotension ). If the patient’s blood pressure is not controlled with Enalapril Maleate Tablets alone, diuretic therapy may be resumed.
If the diuretic cannot be discontinued an initial dose of 2.5 mg should be used under medical supervision for at least two hours and until blood pressure has stabilized for at least an additional hour (see WARNINGS , Hypotension and PRECAUTIONS , Drug Interactions ). The recommended initial dose in patients not on diuretics is 5 mg once a day. Dosage should be adjusted according to blood pressure response.
The usual dosage range is 10 to 40 mg per day administered in a single dose or two divided doses. In some patients treated once daily, the antihypertensive effect may diminish toward the end of the dosing interval. In such patients, an increase in dosage or twice daily administration should be considered.
If blood pressure is not controlled with Enalapril Maleate Tablets alone, a diuretic may be added. Concomitant administration of Enalapril Maleate Tablets with potassium supplements, potassium salt substitutes, or potassium-sparing diuretics may lead to increases of serum potassium (see PRECAUTIONS ). Dosage Adjustment in Hypertensive Patients with Renal Impairment The usual dose of enalapril is recommended for patients with a creatinine clearance more than 30 mL/min (serum creatinine of up to approximately 3 mg/dL).
For patients with creatinine clearance less than or equal to 30 mL/min (serum creatinine more than or equal to 3 mg/dL), the first dose is 2.5 mg once daily. The dosage may be titrated upward until blood pressure is controlled or to a maximum of 40 mg daily. Renal Status Creatinine Clearance (mL/min) Initial Dose (mg/day) Normal Renal Function >80 mL/min 5 mg Mild Impairment ≤80 >30 mL/min 5 mg Moderate to Severe Impairment ≤30 mL/min 2.5 mg Dialysis Patients¹ 2.5 mg on dialysis days ² * See WARNINGS , Anaphylactoid Reactions During Membrane Exposure . ² Dosage on nondialysis days should be adjusted depending on the blood pressure response.
Heart Failure Enalapril Maleate Tablets are indicated for the treatment of symptomatic heart failure, usually in combination with diuretics and digitalis. In the placebo-controlled studies that demonstrated improved survival, patients were titrated as tolerated up to 40 mg, administered in two divided doses. The recommended initial dose is 2.5 mg.
The recommended dosing range is 2.5 to 20 mg given twice a day. Doses should be titrated upward, as tolerated, over a period of a few days or weeks. The maximum daily dose administered in clinical trials was 40 mg in divided doses.
After the initial dose of Enalapril Maleate Tablets, the patient should be observed under medical supervision for at least two hours and until blood pressure has stabilized for at least an additional hour (see WARNINGS and PRECAUTIONS , Drug Interactions ). If possible, the dose of any concomitant diuretic should be reduced which may diminish the likelihood of hypotension. The appearance of hypotension after the initial dose of Enalapril Maleate Tablets does not preclude subsequent careful dose titration with the drug, following effective management of the hypotension.
Asymptomatic Left Ventricular Dysfunction In the trial that demonstrated efficacy, patients were started on 2.5 mg twice daily and were titrated as tolerated to the targeted daily dose of 20 mg (in divided doses). After the initial dose of Enalapril Maleate Tablets, the patient should be observed under medical supervision for at least two hours and until blood pressure has stabilized for at least an additional hour (see WARNI…
⛔ Contraindications ▾
CONTRAINDICATIONS Enalapril Maleate Tablets are contraindicated in patients who are hypersensitive to this product and in patients with a history of angioedema related to previous treatment with an angiotensin-converting enzyme inhibitor and in patients with hereditary or idiopathic angioedema. Do not coadminister aliskiren with Enalapril Maleate Tablets in patients with diabetes (see PRECAUTIONS, Drug Interactions ). Enalapril Maleate Tablets is contraindicated in combination with a neprilysin inhibitor (e.g., sacubitril).
Do not administer Enalapril Maleate Tablets within 36 hours of switching to or from sacubitril/valsartan, a neprilysin inhibitor (see WARNINGS , Head and Neck Angioedema ).
⚠️ Warnings ▾
WARNINGS Anaphylactoid and Possibly Related Reactions Presumably because angiotensin-converting enzyme inhibitors affect the metabolism of eicosanoids and polypeptides, including endogenous bradykinin, patients receiving ACE inhibitors (including Enalapril Maleate Tablets) may be subject to a variety of adverse reactions, some of them serious. Head and Neck Angioedema Angioedema of the face, extremities, lips, tongue, glottis and/or larynx has been reported in patients treated with angiotensin-converting enzyme inhibitors, including Enalapril Maleate Tablets.
This may occur at any time during treatment. In such cases Enalapril Maleate Tablets should be promptly discontinued and appropriate therapy and monitoring should be provided until complete and sustained resolution of signs and symptoms has occurred. In instances where swelling has been confined to the face and lips the condition has generally resolved without treatment, although antihistamines have been useful in relieving symptoms.
Angioedema associated with laryngeal edema may be fatal. Where there is involvement of the tongue, glottis or larynx, likely to cause airway obstruction, appropriate therapy, e.g., subcutaneous epinephrine solution 1:1000 (0.3 mL to 0.5 mL) and/or measures necessary to ensure a patent airway, should be promptly provided (see ADVERSE REACTIONS ). Patients receiving coadministration of ACE inhibitor and mTOR (mammalian target of rapamycin) inhibitor (e.g., temsirolimus, sirolimus, everolimus) therapy or a neprilysin inhibitor may be at increased risk for angioedema (see PRECAUTIONS ).
Intestinal Angioedema : Intestinal angioedema has been reported in patients treated with ACE inhibitors. These patients presented with abdominal pain (with or without nausea or vomiting); in some cases there was no prior history of facial angioedema and C1 esterase levels were normal. The angioedema was diagnosed by procedures including abdominal CT scan or ultrasound, or at surgery, and symptoms resolved after stopping the ACE inhibitor.
Intestinal angioedema should be included in the differential diagnosis of patients on ACE inhibitors presenting with abdominal pain. Patients with a history of angioedema unrelated to ACE inhibitor therapy may be at increased risk of angioedema while receiving an ACE inhibitor (see INDICATIONS AND USAGE and CONTRAINDICATIONS ). Anaphylactoid Reactions During Desensitization Two patients undergoing desensitizing treatment with hymenoptera venom while receiving ACE inhibitors sustained life-threatening anaphylactoid reactions.
In the same patients, these reactions were avoided when ACE inhibitors were temporarily withheld, but they reappeared upon inadvertent rechallenge. Anaphylactoid Reactions During Membrane Exposure Anaphylactoid reactions have been reported in patients dialyzed with high-flux membranes and treated concomitantly with an ACE inhibitor. Anaphylactoid reactions have also been reported in patients undergoing low-density lipoprotein apheresis with dextran sulfate absorption.
Hypotension Excessive hypotension is rare in uncomplicated hypertensive patients treated with Enalapril Maleate Tablets alone. Patients with heart failure given Enalapril Maleate Tablets commonly have some reduction in blood pressure, especially with the first dose, but discontinuation of therapy for continuing symptomatic hypotension usually is not necessary when dosing instructions are followed; caution should be observed when initiating therapy (see DOSAGE AND ADMINISTRATION ). Patients at risk for excessive hypotension, sometimes associated with oliguria and/or progressive azotemia, and rarely with acute renal failure and/or death, include those with the following conditions or characteristics: heart failure, hyponatremia, high-dose diuretic therapy, recent intensive diuresis or increase in diuretic dose, renal dialysis, or severe volume and/or salt depletion of any etiology.
It may be advisable to eliminate the diuretic (except in patients…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Enalapril Maleate Tablets have been evaluated for safety in more than 10,000 patients, including over 1000 patients treated for one year or more. Enalapril Maleate Tablets have been found to be generally well tolerated in controlled clinical trials involving 2987 patients. For the most part, adverse experiences were mild and transient in nature.
In clinical trials, discontinuation of therapy due to clinical adverse experiences was required in 3.3 percent of patients with hypertension and in 5.7 percent of patients with heart failure. The frequency of adverse experiences was not related to total daily dosage within the usual dosage ranges. In patients with hypertension the overall percentage of patients treated with Enalapril Maleate Tablets reporting adverse experiences was comparable to placebo.
Hypertension Adverse experiences occurring in greater than one percent of patients with hypertension treated with Enalapril Maleate Tablets in controlled clinical trials are shown below. In patients treated with Enalapril Maleate Tablets, the maximum duration of therapy was three years; in placebo-treated patients the maximum duration of therapy was 12 weeks. Enalapril Maleate Tablets (n=2314) Incidence (discontinuation) Placebo (n=230) Incidence Body As A Whole Fatigue 3.0 (<0.1)
2.6Orthostatic Effects 1.2 (<0.1)
0.0Asthenia 1.1 (0.1)
0.9Digestive Diarrhea 1.4 (<0.1)
1.7Nausea 1.4 (0.2)
1.7Nervous/Psychiatric Headache 5.2 (0.3)
9.1Dizziness 4.3 (0.4)
4.3Respiratory Cough 1.3 (0.1)
0.9Skin Rash 1.4 (0.4)
0.4Heart Failure Adverse experiences occurring in greater than one percent of patients with heart failure treated with Enalapril Maleate Tablets are shown below. The incidences represent the experiences from both controlled and uncontrolled clinical trials (maximum duration of therapy was approximately one year). In the placebo-treated patients, the incidences reported are from the controlled trials (maximum duration of therapy is 12 weeks).
The percentage of patients with severe heart failure (NYHA Class IV) was 29 percent and 43 percent for patients treated with Enalapril Maleate Tablets and placebo, respectively. Enalapril Maleate Tablets (n=673) Incidence (discontinuation) Placebo (n=339) Incidence Body As A Whole Orthostatic Effects 2.2 (0.1)
0.3Syncope 2.2 (0.1)
0.9Chest Pain 2.1 (0.0)
2.1Fatigue 1.8 (0.0)
1.8Abdominal Pain 1.6 (0.4)
2.1Asthenia 1.6 (0.1)
0.3Cardiovascular Hypotension 6.7 (1.9)
0.6Orthostatic Hypotension 1.6 (0.1)
0.3Angina Pectoris 1.5 (0.1)
1.8Myocardial Infarction 1.2 (0.3)
1.8Digestive Diarrhea 2.1 (0.1)
1.2Nausea 1.3 (0.1)
0.6Vomiting 1.3 (0.0)
0.9Nervous/Psychiatric Dizziness 7.9 (0.6)
0.6Headache 1.8 (0.1)
0.9Vertigo 1.6 (0.1)
1.2Respiratory Cough 2.2 (0.0)
0.6Bronchitis 1.3 (0.0)
0.9Dyspnea 1.3 (0.1)
0.4Pneumonia 1.0 (0.0)
2.4Skin Rash 1.3 (0.0)
2.4Urogenital Urinary Tract Infection 1.3 (0.0)
2.4Other serious clinical adverse experiences occurring since the drug was marketed or adverse experiences occurring in 0.5 to 1.0 percent of patients with hypertension or heart failure in clinical trials are listed below and, within each category, are in order of decreasing severity. Body As A Whole: Anaphylactoid reactions (see WARNINGS , Anaphylactoid and Possibly Related Reactions ). Cardiovascular: Cardiac arrest; myocardial infarction or cerebrovascular accident, possibly secondary to excessive hypotension in high risk patients (see WARNINGS, Hypotension) ; pulmonary embolism and infarction; pulmonary edema; rhythm disturbances including atrial tachycardia and bradycardia; atrial fibrillation; palpitation, Raynaud’s phenomenon.
Digestive: Ileus, pancreatitis, hepatic failure, hepatitis (hepatocellular [proven on rechallenge] or cholestatic jaundice) (see WARNINGS , Hepatic Failure ), melena, anorexia, dyspepsia, constipation, glossitis, stomatitis, dry mouth. Hematologic: Rare cases of neutropenia, thrombocytopenia and bone marrow depression. Musculoskeletal: Mu…
🆘 Overdosage ▾
OVERDOSAGE Limited data are available in regard to overdosage in humans. Single oral doses of enalapril above 1,000 mg/kg and ≥1,775 mg/kg were associated with lethality in mice and rats, respectively. The most likely manifestation of overdosage would be hypotension, for which the usual treatment would be intravenous infusion of normal saline solution.
Enalaprilat may be removed from general circulation by hemodialysis and has been removed from neonatal circulation by peritoneal dialysis (see WARNINGS, Anaphylactoid Reactions During Membrane Exposure).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Enalapril, after hydrolysis to enalaprilat, inhibits angiotensin-converting enzyme (ACE) in human subjects and animals. ACE is a peptidyl dipeptidase that catalyzes the conversion of angiotensin I to the vasoconstrictor substance, angiotensin II. Angiotensin II also stimulates aldosterone secretion by the adrenal cortex.
The beneficial effects of enalapril in hypertension and heart failure appear to result primarily from suppression of the renin-angiotensin-aldosterone system. Inhibition of ACE results in decreased plasma angiotensin II, which leads to decreased vasopressor activity and to decreased aldosterone secretion. Although the latter decrease is small, it results in small increases of serum potassium.
In hypertensive patients treated with Enalapril Maleate Tablets alone for up to 48 weeks, mean increases in serum potassium of approximately 0.2 mEq/L were observed. In patients treated with Enalapril Maleate Tablets plus a thiazide diuretic, there was essentially no change in serum potassium (see PRECAUTIONS ). Removal of angiotensin II negative feedback on renin secretion leads to increased plasma renin activity.
ACE is identical to kininase, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of Enalapril Maleate Tablets remains to be elucidated. While the mechanism through which Enalapril Maleate Tablets lowers blood pressure is believed to be primarily suppression of the renin-angiotensin-aldosterone system, Enalapril Maleate Tablets are antihypertensive even in patients with low-renin hypertension.
Although Enalapril Maleate Tablets were antihypertensive in all races studied, black hypertensive patients (usually a low-renin hypertensive population) had a smaller average response to enalapril monotherapy than non-black patients. Pharmacokinetics and Metabolism Following oral administration of Enalapril Maleate Tablets, peak serum concentrations of enalapril occur within about one hour. Based on urinary recovery, the extent of absorption of enalapril is approximately 60 percent.
Enalapril absorption is not influenced by the presence of food in the gastrointestinal tract. Following absorption, enalapril is hydrolyzed to enalaprilat, which is a more potent angiotensin- converting enzyme inhibitor than enalapril; enalaprilat is poorly absorbed when administered orally. Peak serum concentrations of enalaprilat occur three to four hours after an oral dose of enalapril maleate.
Excretion of Enalapril Maleate Tablets is primarily renal. Approximately 94 percent of the dose is recovered in the urine and feces as enalaprilat or enalapril. The principal components in urine are enalaprilat, accounting for about 40 percent of the dose, and intact enalapril.
There is no evidence of metabolites of enalapril, other than enalaprilat. The serum concentration profile of enalaprilat exhibits a prolonged terminal phase, apparently representing a small fraction of the administered dose that has been bound to ACE. The amount bound does not increase with dose, indicating a saturable site of binding.
The effective half-life for accumulation of enalaprilat following multiple doses of enalapril maleate is 11 hours. The disposition of enalapril and enalaprilat in patients with renal insufficiency is similar to that in patients with normal renal function until the glomerular filtration rate is 30 mL/min or less. With glomerular filtration rate ≤30 mL/min, peak and trough enalaprilat levels increase, time to peak concentration increases and time to steady state may be delayed.
The effective half-life of enalaprilat following multiple doses of enalapril maleate is prolonged at this level of renal insufficiency (see DOSAGE AND ADMINISTRATION) . Enalaprilat is dialyzable at the rate of 62 mL/min. Studies in dogs indicate that enalapril crosses the blood-brain barrier poorly, if at all; enalaprilat does not enter th…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Enalapril Maleate Tablets NDC Strength Quantity Description 68682-710-01 68682-710-10 2.5 mg Bottles of 100 (with desiccant) Bottles of 1,000 (with desiccant) White, oval shaped tablet imprinted with “VASO 2.5” and scored on one side and scored on the other. 68682-711-01 68682-711-10 5 mg Bottles of 100 (with desiccant) Bottles of 1,000 (with desiccant) White, rounded triangle shaped tablet imprinted with “VASO 5” on one side and scored on the other. 68682-712-01 68682-712-10 10 mg Bottles of 100 (with desiccant) Bottles of 1,000 (with desiccant) Rust red, rounded triangle shaped tablet imprinted with “VASO 10” on one side and scored on the other.
68682-713-01 68682-713-10 20 mg Bottles of 100 (with desiccant) Bottles of 1,000 (with desiccant) Peach, rounded triangle shaped tablet imprinted with “VASO 20” on one side and scored on the other. Storage Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Keep container tightly closed.
Protect from moisture. Dispense in a tight container as per USP, if product package is subdivided. Distributed by : Oceanside Pharmaceuticals, a division of Bausch Health US, LLC Bridgewater, NJ 08807 USA Manufactured by : Bausch Health Companies Inc.
Steinbach, MB R5G 1Z7, Canada © 2020 Bausch Health Companies Inc. or its affiliates 9450104_20003098 Rev. 12/2020
📋 Description ▾
DESCRIPTION Enalapril Maleate Tablets are the maleate salt of enalapril, the ethyl ester of a long-acting angiotensin-converting enzyme inhibitor, enalaprilat. Enalapril maleate is chemically described as (S)-1-[ N -[1-(ethoxycarbonyl)-3-phenylpropyl]-L-alanyl]-L-proline, ( Z )-2-butenedioate salt (1:1). Its empirical formula is C 20 H 28 N 2 O 5 •C 4 H 4 O 4 , and its structural formula is: Enalapril maleate is a white to off-white, crystalline powder with a molecular weight of 492.53.
It is sparingly soluble in water, soluble in ethanol, and freely soluble in methanol. Enalapril is a pro-drug; following oral administration, it is bioactivated by hydrolysis of the ethyl ester to enalaprilat, which is the active angiotensin-converting enzyme inhibitor. Enalapril maleate is supplied as 2.5 mg, 5 mg, 10 mg, and 20 mg tablets for oral administration.
In addition to the active ingredient enalapril maleate, each tablet contains the following inactive ingredients: lactose, magnesium stearate, sodium bicarbonate, and starch. The 10 mg and 20 mg tablets also contain iron oxides. image