
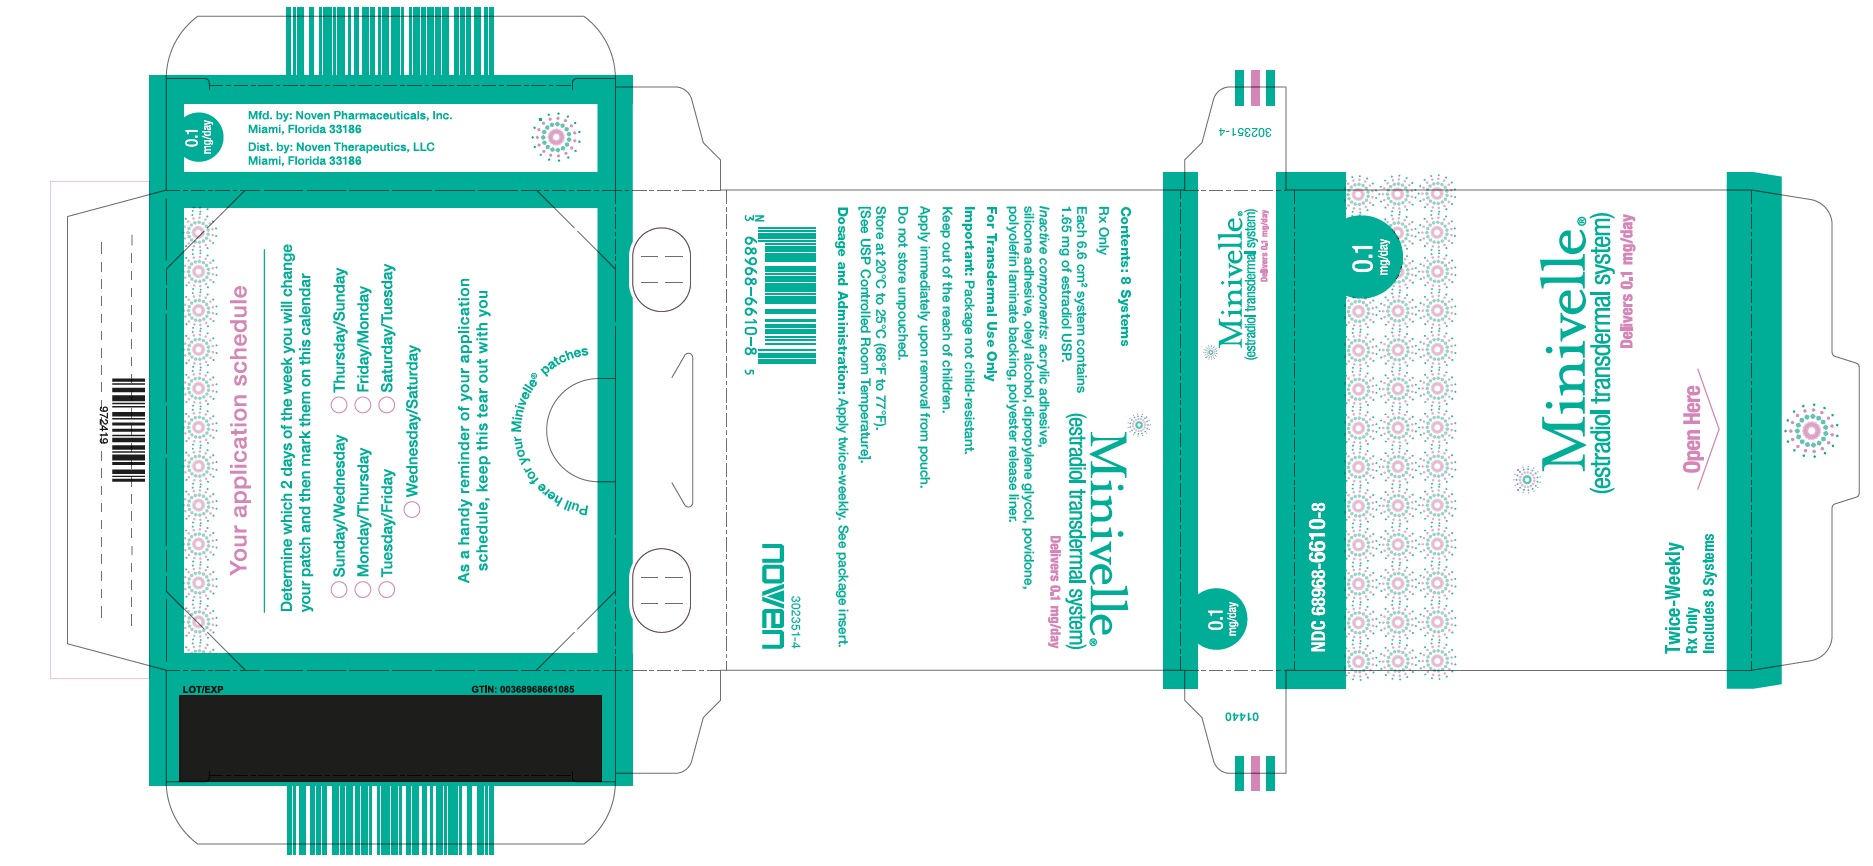
Minivelle estradiol .1 mg/d Film, Extended Release, 8 pouches — NDC 68968-6610-8 (Billing 68968-6610-08)
This is a package of 8 pouches of Minivelle estradiol .1 mg/d Film, Extended Release from Noven Therapeutics, LLC, marketed since Dec 2012 and currently FDA-listed; retail pharmacies pay about $11.58 per pouche (NADAC). It is this product's only package size.
Other active recalls for Estradiol (different manufacturers) — 4 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 003203
- GCN: 28841
- HICL (First Databank): 001421
- AHFS class code: 68:16.04.00
- RxCUI (RxNorm): 241946
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Radioactive Diagnostic Agent class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Transdermal estradiol (Climara®, Minivelle®, Vivelle-Dot®) is used to treat hot flashes (hot flushes; sudden feelings of mild or intense body heat) in women who are experiencing menopause (change of life; the end of monthly menstrual periods). Transdermal estradiol (Climara®, Vivelle-Dot®) is also used to treat vaginal dryness, itching, and burning in women who are experiencing menopause. Transdermal estradiol (Climara®, Menostar®, Minivelle®, Vivelle-Dot®) is also used to prevent osteoporosis (a condition in which the bones become thin and weak and break easily) in women who are experiencing...
Read the full MedlinePlus article ↗- It's an estrogen used mainly for menopause symptoms like hot flashes and vaginal dryness. Some patches are also used for low estrogen from ovarian problems or to prevent osteoporos...
- That depends on the form. Patches go on the skin once or twice a week depending on the brand, and the injection goes into a muscle. Use the lowest dose that works for the shortest...
- Headache, breast tenderness, spotting or irregular bleeding, cold-like symptoms and skin irritation where a patch sits are the most common. Tell your doctor if they bother you or d...
- Get urgent help for chest pain, sudden weakness or trouble speaking, a swollen painful leg, sudden shortness of breath or sudden vision changes. These could be a stroke or blood cl...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Estradiol — tap one for details:
Estradiol may be associated with lower levels of 5 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $11.576 | $92.61 / 8 d |
| Medicaid paysCMS SDUD · 12 mo | $14.74 | $117.89 / 8 d |
| Medicare drug plans payPart D · Q2 2026 | $12.15 | $97.19 / 8 d |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 68968-6610-08 You're viewing this Main listing | 8 POUCH in 1 PACKET / 1 d in 1 POUCH | 2012-12-20 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Estradiol .1 mg/d 00378-4623-26 | Mylan | 8 patches | $8.568 | AB3 | Availability likely | save 26% |
| Estradiol .1 mg/d 00378-4640-26 | Mylan | 8 patches | $8.568 | AB1 | Availability likely | save 26% |
| Lyllana .1 mg/d 65162-0228-08 | Amneal | 8 pouches | $8.568 | AB3 | Availability likely | save 26% |
| Dotti .1 mg/d 65162-0997-08 | Amneal | 8 pouches | $8.568 | AB1 | Availability likely | save 26% |
| Estradiol .1 mg/d 68968-3410-08 | Noven | 8 pouches | $8.568 | AB3 | Availability likely | save 26% |
| Estradiol .1 mg/d 70710-1195-08 | Zydus | 8 patches | $8.568 | AB1 | Availability likely | save 26% |
| Minivelle .1 mg/dthis 68968-6610-08 | Noven | 8 pouches | $11.576 | AB3 | Availability likely | — |
| Estradiol .1 mg/d 00378-3352-99 | Mylan | 4 patches | $12.767 | AB2 | Availability likely | +10% |
| Estradiol Transdermal System .1 mg/d 00781-7104-54 | Sandoz | 4 patches | $12.767 | AB2 | Availability likely | +10% |
| Climara .1 mg/d 50419-0452-04 | Bayer | 4 patches | $18.279 | AB2 | Availability likely | +58% |
| Vivelle-Dot .1 mg/d 66758-0149-83 | Sandoz | 8 patches | $18.399 | AB1 | Availability likely | +59% |
| Estradiol .1 mg/d 00781-7167-40 | Sandoz | 24 patches | — | AB1 | Discontinued | — |
| Estradiol .1 mg/d 69238-1296-07 | Amneal | 8 pouches | — | AB3 | FDA listed | — |
| Estradiol .1 mg/d 69238-1633-07 | Amneal | 8 pouches | — | AB1 | FDA listed | — |
| Estradiol .1 mg/d 70771-1567-08 | Zydus | 8 patches | — | AB1 | FDA listed | — |
| Dotti .1 mg/d 72162-2036-02 | Bryant | 8 pouches | — | AB1 | FDA listed | — |
| estradiol .1 mg/d 70771-1406-04 | Zydus | 4 patches | — | AB2 | FDA listed | — |
| Estradiol .1 mg/d 50090-7984-00 | A-S | 4 pouches | — | AB2 | FDA listed | — |
| estradiol .1 mg/d 68382-0329-04 | Zydus | 4 patches | — | AB2 | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9730900 ↗ | Method of use | U-2086 | Jul 10, 2028 |
| US 9730900 ↗ | Method of use | U-2086 | Jul 10, 2028 |
| US 9730900 ↗ | Method of use | U-2086 | Jul 10, 2028 |
| US 9730900 ↗ | Method of use | U-2086 | Jul 10, 2028 |
| US 9730900 ↗ | Method of use | U-2086 | Jul 10, 2028 |
| US 9833419 ↗ | Drug product | — | Jul 10, 2028 |
| US 9833419 ↗ | Drug product | — | Jul 10, 2028 |
| US 9833419 ↗ | Drug product | — | Jul 10, 2028 |
| US 8231906 ↗ | Drug substance | — | Jul 4, 2030 |
| US 8231906 ↗ | Drug substance | — | Jul 4, 2030 |
| US 8231906 ↗ | Drug substance | — | Jul 4, 2030 |
| US 9833419 ↗ | Drug product | — | Jul 10, 2028 |
| US 9833419 ↗ | Drug product | — | Jul 10, 2028 |
| US 9724310 ↗ | Drug substance | — | Jul 10, 2028 |
| US 8231906 ↗ | Drug substance | — | Jul 4, 2030 |
| US 8231906 ↗ | Drug substance | — | Jul 4, 2030 |
Is there a generic version of MINIVELLE 0.1 MG PATCH?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII E107L85C40
Dipropylene glycol is a clear liquid made from propylene glycol. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 172F2WN8DV
A fatty alcohol derived from animal or plant oils. It acts as an emollient and helps stabilize emulsions, allowing oil and water to mix evenly in the medication.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ENDOMETRIAL CANCER, CARDIOVASCULAR DISORDERS, PROBABLE DEMENTIA, and BREAST CANCER Estrogen-Alone Therapy Endometrial Cancer There is an increased risk of endometrial cancer in a woman with a uterus who uses unopposed estrogens. Adding a progestogen to estrogen therapy has been shown to reduce the risk of endometrial hyperplasia, which may be a precursor to endometrial cancer. Perform adequate diagnostic measures, including directed or random endometrial sampling when indicated, to rule out malignancy in postmenopausal women with undiagnosed persistent or recurring abnormal genital bleeding [see Warnings and Precautions ( 5.2 )] .
Cardiovascular Disorders and Probable Dementia The Women’s Health Initiative (WHI) estrogen-alone substudy reported increased risks of stroke and deep vein thrombosis (DVT) in postmenopausal women (50 to 79 years of age) during 7.1 years of treatment with daily oral conjugated estrogens (CE) [0.625 mg]-alone, relative to placebo [see Warnings and Precautions ( 5.1 ), and Clinical Studies ( 14.3 )] . The WHI Memory Study (WHIMS) estrogen-alone ancillary study of WHI reported an increased risk of developing probable dementia in postmenopausal women 65 years of age and older during 5.2 years of treatment with daily CE (0.625 mg)-alone, relative to placebo.
It is unknown whether this finding applies to younger postmenopausal women [see Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.5 ), and Clinical Studies ( 14.4 )]. Do not use estrogen-alone therapy for the prevention of cardiovascular disease or dementia [see Warnings and Precautions ( 5.1 , 5.3 ), and Clinical Studies ( 14.3 , 14.4 )]. Only daily oral 0.625 mg CE was studied in the estrogen-alone substudy of the WHI.
Therefore, the relevance of the WHI findings regarding adverse cardiovascular events and dementia to lower CE doses, other route of administration, or other estrogen-alone products is not known. Without such data, it is not possible to definitively exclude these risks or determine the extent of these risks for other products. Discuss with your patient the benefits and risks of estrogen-alone therapy, taking into account her individual risk profile.
Prescribe estrogens with or without progestogens at the lowest effective doses and for the shortest duration consistent with treatment goals and risks for the individual woman. Estrogen Plus Progestin Therapy Cardiovascular Disorders and Probable Dementia The WHI estrogen plus progestin substudy reported increased risks of DVT, pulmonary embolism (PE), stroke and myocardial infarction (MI) in postmenopausal women (50 to 79 years of age) during 5.6 years of treatment with daily oral CE (0.625 mg) combined with medroxyprogesterone acetate (MPA) [2.5 mg], relative to placebo [see Warnings and Precautions ( 5.1 ), and Clinical Studies ( 14.3 )].
The WHIMS estrogen plus progestin ancillary study of the WHI, reported an increased risk of developing probable dementia in postmenopausal women 65 years of age and older during 4 years of treatment with daily CE (0.625 mg) combined with MPA (2.5 mg), relative to placebo. It is unknown whether this finding applies to younger postmenopausal women [see Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.5 ), and Clinical Studies ( 14.4 )]. Do not use estrogen plus progestogen therapy for the prevention of cardiovascular disease or dementia [see Warnings and Precautions ( 5.1 , 5.3 ), and Clinical Studies ( 14.3 , 14.4 )].
Breast Cancer The WHI estrogen plus progestin substudy also demonstrated an increased risk of invasive breast cancer [see Warnings and Precautions ( 5.2 ), and Clinical Studies ( 14.3 )]. Only daily oral 0.625 mg CE and 2.5 mg MPA were studied in the estrogen plus progestin substudy of the WHI. Therefore, the relevance of the WHI findings regarding adverse cardiovascular events, dementia and breast cancer to lower CE plus other MPA doses, other routes of administration, or other estrogen plus proges… [Excerpted — this section continues on DailyMed.]
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE MINIVELLE is indicated for: MINIVELLE® is an estrogen indicated for: Treatment of moderate to severe vasomotor symptoms due to menopause ( 1.1 ) Prevention of postmenopausal osteoporosis ( 1.2 ) Limitations of Use When prescribing solely for the treatment of postmenopausal osteoporosis, first consider the use of non-estrogen medications. Consider estrogen therapy only for women at significant risk of osteoporosis.
1.1 Treatment of Moderate to Severe Vasomotor Symptoms Due to Menopause
1.2Prevention of Postmenopausal Osteoporosis Limitation of Use When prescribing solely for the prevention of postmenopausal osteoporosis, first consider the use of non-estrogen medications. Consider estrogen therapy only for women at significant risk of osteoporosis.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Generally, when estrogen is prescribed for a postmenopausal woman with a uterus, consider addition of a progestogen to reduce the risk of endometrial cancer. Generally, a woman without a uterus, does not need to use a progestogen in addition to her estrogen therapy. In some cases, however, hysterectomized women who have a history of endometriosis may need a progestogen [see Warnings and Precautions ( 5.2 , 5.14 )] .
Use estrogen-alone, or in combination with a progestogen, at the lowest effective dose and for the shortest duration consistent with treatment goals and risks for the individual woman. Reevaluate postmenopausal women periodically as clinically appropriate to determine if treatment is still necessary. Start therapy with MINIVELLE® 0.0375 mg per day applied to the skin twice weekly for the treatment of moderate to severe vasomotor symptoms due to menopause.
Dosage adjustment should be guided by the clinical response ( 2.1 ) Start therapy with MINIVELLE 0.025 mg per day applied to the skin twice weekly for the prevention of postmenopausal osteoporosis. The dose may be adjusted as necessary ( 2.2 ) Place MINIVELLE on a clean, dry area on the lower abdomen (below the umbilicus) or buttocks. Do not apply MINIVELLE to the breasts ( 2.3 )
2.1Treatment of Moderate to Severe Vasomotor Symptoms due to Menopause Start therapy with MINIVELLE 0.0375 mg per day applied to the skin twice weekly. Make dosage adjustments based on clinical response. Attempt to taper or discontinue MINIVELLE at 3 to 6 month intervals.
2.2 Prevention of Postmenopausal Osteoporosis due to Menopause
2.3Application Instructions Place the adhesive side of MINIVELLE on a clean, dry area on the lower abdomen (below the umbilicus) or buttocks. Do not apply MINIVELLE to the breasts. Replace MINIVELLE twice weekly (every 3-4 days).
Rotate the sites of application, with an interval of at least 1 week allowed between applications to a particular site. Select an area for application that is not oily, damaged, or irritated. Avoid the waistline, since tight clothing may rub the system off.
Apply the system immediately after opening the pouch and removing the protective liner. Press the system firmly in place with the palm of the hand for about 10 seconds, making sure there is good contact with the skin, especially around the edges. In the event that a system falls off, reapply the same system or apply a new system to another location.
In either case, continue the original treatment schedule. If a woman has forgotten to apply MINIVELLE, have her apply a new system as soon as possible. Apply the new system on the original treatment schedule.
The interruption of treatment in women taking MINIVELLE might increase the likelihood of breakthrough bleeding, spotting and recurrence of symptoms.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Transdermal system: 0.025 mg/day, 0.0375 mg/day, 0.05 mg/day, 0.075 mg/day, and 0.1 mg/day. Transdermal system: 0.025 mg/day, 0.0375 mg/day, 0.05 mg/day, 0.075 mg/day, and 0.1 mg/day ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS MINIVELLE is contraindicated in women with any of the following conditions: Undiagnosed abnormal genital bleeding [see Warnings and Precautions ( 5.2 )] . Breast cancer or a history of breast cancer [see Warnings and Precautions ( 5.2 )] . Estrogen-dependent neoplasia [see Warnings and Precautions ( 5.2 )] .
Active DVT, PE, or a history of these conditions [see Warnings and Precautions ( 5.1 )] . Active arterial thromboembolic disease (for example, stroke or MI), or a history of these conditions [see Warnings and Precautions ( 5.1 )] . Known anaphylactic reaction, angioedema, or hypersensitivity to MINIVELLE Hepatic impairment or disease Protein C, protein S, or antithrombin deficiency, or other known thrombophilic disorders Undiagnosed abnormal genital bleeding ( 4 , 5.2 ) Breast cancer or a history of breast cancer ( 4 , 5.2 ) Estrogen-dependent neoplasia ( 4 , 5.2 ) Active DVT, PE, or a history of these conditions ( 4 , 5.1 ) Active arterial thromboembolic disease (for example, stroke or MI), or a history of these conditions ( 4 , 5.1 ) Known anaphylactic reaction, angioedema, or hypersensitivity to MINIVELLE ( 4 ) Hepatic impairment or disease ( 4 , 5.10 ) Protein C, protein S, or antithrombin deficiency, or other known thrombophilic disorders ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Estrogens increase the risk of gallbladder disease ( 5.4 ) Discontinue estrogen if severe hypercalcemia, loss of vision, severe hypertriglyceridemia or cholestatic jaundice occurs ( 5.5 , 5.6 , 5.9 , 5.10 ) Monitor thyroid function in women on thyroid replacement therapy ( 5.11 , 5.18 )
5.1Cardiovascular Disorder Increased risks of stroke and DVT are reported with estrogen-alone therapy. Increased risks of PE, DVT, stroke and MI are reported with estrogen plus progestin therapy. Immediately discontinue estrogen with or without progestogen therapy if any of these occur or are suspected.
Manage appropriately any risk factors for arterial vascular disease (for example, hypertension, diabetes mellitus, tobacco use, hypercholesterolemia, and obesity) and/or venous thromboembolism (VTE) (for example, personal history or family history of VTE, obesity, and systemic lupus erythematosus). Stroke The WHI estrogen-alone substudy reported a statistically significant increased risk of stroke in women 50 to 79 years of age receiving daily CE (0.625 mg)-alone compared to women in the same age group receiving placebo (45 versus 33 strokes per 10,000 women-years, respectively).
The increase in risk was demonstrated in year 1 and persisted [see Clinical Studies ( 14.3 )] . Immediately discontinue estrogen-alone therapy if a stroke occurs or is suspected. Subgroup analyses of women 50 to 59 years of age suggest no increased risk of stroke for those women receiving CE (0.625 mg)-alone versus those receiving placebo (18 versus 21 per 10,000 women-years).
1 The WHI estrogen plus progestin substudy reported a statistically significant increased risk of stroke in women 50 to 79 years of age receiving CE (0.625 mg) plus MPA (2.5 mg) compared to women in the same age group receiving placebo (33 versus 25 strokes per 10,000 women-years, respectively) [see Clinical Studies, ( 14.3 )] . The increase in risk was demonstrated after the first year and persisted. 1 Immediately discontinue estrogen plus progestogen therapy if a stroke occurs or is suspected.
Subgroup analyses of women 50 to 59 years of age suggest no increased risk of stroke for those women receiving CE (0.625 mg)-alone versus those receiving placebo (18 versus 21 per 10,000 women-years). 1 The WHI estrogen plus progestin substudy reported a statistically significant increased risk of stroke in women 50 to 79 years of age receiving CE (0.625 mg) plus MPA (2.5 mg) compared to women in the same age group receiving placebo (33 versus 25 strokes per 10,000 women-years) [see Clinical Studies, ( 14.3 )] . The increase in risk was demonstrated after the first year and persisted.
1 Immediately discontinue estrogen plus progestogen therapy if a stroke occurs or is suspected. Coronary Heart Disease The WHI estrogen-alone substudy reported no overall effect on coronary heart disease (CHD) events (defined as nonfatal MI, silent MI, or CHD death) in women receiving estrogen-alone compared to placebo 2 [see Clinical Studies ( 14.3 )] . Subgroup analyses of women 50 to 59 years of age, who were less than 10 years since menopause, suggest a reduction (not statistically significant) of CHD events in those women receiving daily CE (0.625 mg)-alone compared to placebo (8 versus 16 per 10,000 women-years).
1 The WHI estrogen plus progestin substudy reported an increased risk (not statistically significant) of CHD events in women receiving daily CE (0.625 mg) plus MPA (2.5 mg) compared to women receiving placebo (41 versus 34 per 10,000 women years). 1 An increase in relative risk was demonstrated in year 1, and a trend toward decreasing relative risk was reported in years 2 through 5 [see Clinical Studies ( 14.3 )] . In postmenopausal women with documented heart disease (n = 2,763, average 66.7 years of age), in a controlled clinical trial of secondary prevention of cardiovascular disease (Heart and Estrogen/Progestin Replacement Study; HERS), treatment with daily CE (0.625 mg) plus M… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed elsewhere in labeling: Cardiovascular Disorders [see Boxed Warning , Warning and Precaution, ( 5.1 )] Malignant Neoplasms [see Boxed Warning , Warnings and Precautions ( 5.2 )] The most common adverse reactions (greater than or equal to 5 percent) with MINIVELLE are: headache, breast tenderness, back pain, pain in limb, nasopharyngitis, dyspepsia, nausea, sinusitis, and intermenstrual bleeding. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Noven at 1-800-455-8070 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. There were no clinical trials conducted with MINIVELLE. MINIVELLE is bioequivalent to Vivelle ® .
The following adverse reactions are reported with Vivelle therapy: Table 1: Summary of Most Frequently Reported Adverse Reactions (Vivelle versus Placebo) Regardless of Relationship Reported at a Frequency ≥5 Percent † Represents milligrams of estradiol delivered daily by each system * NOS represents not otherwise specified ** NEC represents not elsewhere classified *** Application site erythema and application site irritation were observed in 3.2% or less of patients across treatment groups. Vivelle 0.025 mg/day † (N=47) N (%) Vivelle 0.0375 mg/day † (N=130) N (%) Vivelle 0.05 mg/day † (N=103) N (%) Vivelle 0.075 mg/day † (N=46) N (%) Vivelle 0.1 mg/day † (N=132) 2 N (%) Placebo (N=157) N (%) Gastrointestinal disorders Constipation 2 (4.3) 5 (3.8) 4 (3.9) 3 (6.5) 2 (1.5) 4 (2.5) Dyspepsia 4 (8.5) 12 (9.2) 3 (2.9) 2 (4.3) 0 10 (6.4) Nausea 2 (4.3) 8 (6.2) 4 (3.9) 0 7 (5.3) 5 (3.2) General disorders and administration site conditions *** Influenza-like illness 3 (6.4) 6 (4.6) 8 (7.8) 0 3 (2.3) 10 (6.4) Pain NOS* 0 8 (6.2) 0 2 (4.3) 7 (5.3) 7 (4.5) Infections and infestations Influenza 4 (8.5) 4 (3.1) 6 (5.8) 0 10 (7.6) 14 (8.9) Nasopharyngitis 3 (6.4) 16 (12.3) 10 (9.7) 9 (19.6) 11 (8.3) 24 (15.3) Sinusitis NOS* 4 (8.5) 17 (13.1) 13 (12.6) 3 (6.5) 7 (5.3) 16 (10.2) Upper respiratory tract infection NOS* 3 (6.4) 8 (6.2) 11 (10.7) 4 (8.7) 6 (4.5) 9 (5.7) Investigations Weight increased 4 (8.5) 5 (3.8) 2 (1.9) 2 (4.3) 0 3 (1.9) Musculoskeletal and connective tissue disorders Arthralgia 0 11 (8.5) 4 (3.9) 2 (4.3) 5 (3.8) 9 (5.7) Back pain 4 (8.5) 10 (7.7) 9 (8.7) 4 (8.7) 14 (10.6) 10 (6.4) Neck pain 3 (6.4) 4 (3.1) 4 (3.9) 0 6 (4.5) 2 (1.3) Pain in limb 0 10 (7.7) 7 (6.8) 2 (4.3) 6 (4.5) 9 (5.7) Nervous system disorders Headache NOS* 7 (14.9) 35 (26.9) 32 (31.1) 23 (50.0) 34 (25.8) 37 (23.6) Sinus headache 0 12 (9.2) 5 (4.9) 5 (10.9) 2 (1.5) 8 (5.1) Psychiatric disorders Anxiety NEC ** 3 (6.4) 5 (3.8) 0 0 2 (1.5) 4 (2.5) Depression 5 (10.6) 4 (3.1) 7 (6.8) 0 4 (3.0) 6 (3.8) Insomnia 3 (6.4) 6 (4.6) 4 (3.9) 2 (4.3) 2 (1.5) 9 (5.7) Reproductive system and breast disorders Breast tenderness 8 (17.0) 10 (7.7) 8 (7.8) 3 (6.5) 17 (12.9) 0 Dysmenorrhea 0 0 0 3 (6.5) 0 0 Intermenstrual bleeding 3 (6.4) 9 (6.9) 6 (5.8) 0 14 (10.6) 7 (4.5) Respiratory, thoracic and mediastinal disorders Sinus congestion 0 4 (3.1) 3 (2.9) 3 (6.5) 6 (4.5) 7 (4.5) Vascular disorders Hot flushes NOS* 3 (6.4) 0 3 (2.9) 0 0 6 (3.8) Hypertension NOS* 2 (4.3) 0 3 (2.9) 0 0 2 (1.3) During the clinical pharmacology studies with MINIVELLE, 35 percent or less of subjects experienced barely perceptible erythema.
No transdermal systems were removed due to irritation. Three subjects (2.2 percent) reported mild discomfort while wearing MINIVELLE (N=136).
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of MINIVELLE. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably est… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS In vitro and in vivo studies have shown that estrogens are metabolized partially by cytochrome P450 3A4 (CYP3A4). Therefore, inducers or inhibitors of CYP3A4 may affect estrogen drug metabolism. Inducers of CYP3A4 such as St.
John’s wort (Hypericum perforatum) preparations, phenobarbital, carbamazepine and rifampin may reduce plasma concentrations of estrogens, possibly resulting in a decrease in therapeutic effects and/or changes in the uterine bleeding profile. Inhibitors of CYP3A4 such as erythromycin, clarithromycin, ketoconazole, itraconazole, ritonavir, and grapefruit juice may increase plasma concentrations of estrogens and may result in adverse reactions. Inducers and/or inhibitors of CYP3A4 may affect estrogen drug metabolism and decrease or increase the estrogen plasma concentration.
( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary MINIVELLE is not indicated for use in pregnancy. There are no data with the use of MINIVELLE in pregnant women; however, epidemiologic studies and meta-analyses have not found an increased risk of genital or nongenital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to combined hormonal contraceptives (estrogens and progestins) before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
8.2Lactation Risk Summary Estrogens are present in human milk and can reduce milk production in breast-feeding women. This reduction can occur at any time but is less likely to occur once breast-feeding is well established. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for MINIVELLE and any potential adverse effects on the breastfed child from MINIVELLE or from the underlying maternal condition.
8.4Pediatric Use MINIVELLE is not indicated for use in pediatric patients. Clinical studies have not been conducted in the pediatric population.
8.5Geriatric Use There have not been sufficient numbers of geriatric women involved in clinical studies utilizing MINIVELLE to determine whether those over 65 years of age differ from younger subjects in their response to MINIVELLE. The Women’s Health Initiative Studies In the WHI estrogen-alone substudy (daily CE [0.625 mg]-alone versus placebo), there was a higher relative risk of stroke in women greater than 65 years of age [see Clinical Studies ( 14.3 )] . In the WHI estrogen plus progestin substudy (daily CE [0.625 mg] plus MPA [2.5 mg] versus placebo), there was a higher relative risk of nonfatal stroke and invasive breast cancer in women greater than 65 years of age [see Warnings and Precautions ( 5.1 ), and Clinical Studies ( 14.3 )] .
The Women’s Health Initiative Memory Study In the WHIMS ancillary studies of postmenopausal women 65 to 79 years of age, there was an increased risk of probable dementia in women receiving estrogen-alone or estrogen plus progestin when compared to placebo [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.4 )] . Since both ancillary studies were conducted in women 65 to 79 years of age, it is unknown whether these findings apply to younger postmenopausal women 8 [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.3 )] .
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary MINIVELLE is not indicated for use in pregnancy. There are no data with the use of MINIVELLE in pregnant women; however, epidemiologic studies and meta-analyses have not found an increased risk of genital or nongenital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to combined hormonal contraceptives (estrogens and progestins) before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use MINIVELLE is not indicated for use in pediatric patients. Clinical studies have not been conducted in the pediatric population.
🧓 Geriatric Use ▾
8.5Geriatric Use There have not been sufficient numbers of geriatric women involved in clinical studies utilizing MINIVELLE to determine whether those over 65 years of age differ from younger subjects in their response to MINIVELLE. The Women’s Health Initiative Studies In the WHI estrogen-alone substudy (daily CE [0.625 mg]-alone versus placebo), there was a higher relative risk of stroke in women greater than 65 years of age [see Clinical Studies ( 14.3 )] . In the WHI estrogen plus progestin substudy (daily CE [0.625 mg] plus MPA [2.5 mg] versus placebo), there was a higher relative risk of nonfatal stroke and invasive breast cancer in women greater than 65 years of age [see Warnings and Precautions ( 5.1 ), and Clinical Studies ( 14.3 )] .
The Women’s Health Initiative Memory Study In the WHIMS ancillary studies of postmenopausal women 65 to 79 years of age, there was an increased risk of probable dementia in women receiving estrogen-alone or estrogen plus progestin when compared to placebo [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.4 )] . Since both ancillary studies were conducted in women 65 to 79 years of age, it is unknown whether these findings apply to younger postmenopausal women 8 [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.3 )] .
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of estrogen may cause nausea, vomiting, breast tenderness, abdominal pain, drowsiness and fatigue, and withdrawal bleeding may occur in women. Treatment of overdose consists of discontinuation of MINIVELLE therapy with institution of appropriate symptomatic care.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Endogenous estrogens are largely responsible for the development and maintenance of the female reproductive system and secondary sexual characteristics. Although circulating estrogens exist in a dynamic equilibrium of metabolic interconversions, estradiol is the principal intracellular human estrogen and is substantially more potent than its metabolites, estrone and estriol, at the receptor level. The primary source of estrogen in normally cycling adult women is the ovarian follicle, which secretes 70 to 500 mcg of estradiol daily, depending on the phase of the menstrual cycle.
After menopause, most endogenous estrogen is produced by conversion of androstenedione, secreted by the adrenal cortex, to estrone in the peripheral tissues. Thus, estrone and the sulfate conjugated form, estrone sulfate, are the most abundant circulating estrogens in postmenopausal women. Estrogens act through binding to nuclear receptors in estrogen responsive tissues.
To date, two estrogen receptors have been identified. These vary in proportion from tissue to tissue. Circulating estrogens modulate the pituitary secretion of the gonadotropins, luteinizing hormone (LH) and follicle stimulating hormone (FSH) through a negative feedback mechanism.
Estrogens act to reduce the elevated concentrations of these hormones seen in postmenopausal women.
12.2Pharmacodynamics Generally, a serum estrogen concentration does not predict an individual woman’s therapeutic response to MINIVELLE nor her risk for adverse outcomes. Likewise, exposure comparisons across different estrogen products to infer efficacy or safety for the individual woman may not be valid.
12.3Pharmacokinetics Absorption In a single-dose, two way-crossover clinical study conducted in 96 healthy, non-smoking postmenopausal women under fed condition, MINIVELLE (0.1 mg per day) was bioequivalent to Vivelle (0.1 mg per day) based on estradiol exposure (AUC 0-84 ) and estradiol peak concentration (C max ) following a single-dose on the lower abdomen for 84 hours. Estradiol pharmacokinetics were characterized in a separate open-label, single-center, randomized, single-dose, three-way crossover study conducted in 36 healthy, non-smoking postmenopausal women (aged 40 to 65 years).
MINIVELLE transdermal systems delivering nominal estradiol of approximately 0.025 mg, 0.05 mg, and 0.1 mg per day were applied to the lower abdomen under fed state in a crossover fashion for 84 hours. The mean estradiol pharmacokinetics parameters are summarized in Table 2 . AUC and C max are dose proportional from 0.025 mg to 0.1 mg per day.
Table 2: Mean (SD) Serum Pharmacokinetic Parameters of Baseline-Uncorrected Estradiol following a Single Dose of MINIVELLE (N=36) a Median (minimum-maximum) Parameter 0.1 mg/day 0.05 mg/day 0.025 mg/day AUC 84 (pg·hr/mL) 5875 (1857) 3057 (980) 1763 (600) AUC 120 (pg·hr/mL) 6252 (1938) 3320 (1038) 1979 (648) C max (pg/mL) 117 (39.3) 56.6 (17.6) 30.3 (11.1) T max (hr) a 24.0 (8-60) 24.0 (8-60) 36.0 (8-84) Figure 1 illustrates the mean baseline-uncorrected estradiol serum concentrations of MINIVELLE at three different strengths.
Figure 1: Mean Baseline-Uncorrected Estradiol Serum Concentration-Time Profiles Following a Single Dose of MINIVELLE 0.1 mg per day (Treatment A), 0.05 mg per day (Treatment B), and 0.025 mg per day (Treatment C) (N=36) Distribution The distribution of exogenous estrogens is similar to that of endogenous estrogens. Estrogens are widely distributed in the body and are generally found in higher concentrations in the sex hormone target organs. Estrogens circulate in the blood largely bound to sex hormone-binding globulin (SHBG) and albumin.
Metabolism Exogenous estrogens are metabolized in the same manner as endogenous estrogens. Circulating estrogens exist in a dynamic equilibrium of metabolic interconversions. These transformations take place mainly in the liver.
Estradiol is converted reversibly to estrone, and both… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Endogenous estrogens are largely responsible for the development and maintenance of the female reproductive system and secondary sexual characteristics. Although circulating estrogens exist in a dynamic equilibrium of metabolic interconversions, estradiol is the principal intracellular human estrogen and is substantially more potent than its metabolites, estrone and estriol, at the receptor level. The primary source of estrogen in normally cycling adult women is the ovarian follicle, which secretes 70 to 500 mcg of estradiol daily, depending on the phase of the menstrual cycle.
After menopause, most endogenous estrogen is produced by conversion of androstenedione, secreted by the adrenal cortex, to estrone in the peripheral tissues. Thus, estrone and the sulfate conjugated form, estrone sulfate, are the most abundant circulating estrogens in postmenopausal women. Estrogens act through binding to nuclear receptors in estrogen responsive tissues.
To date, two estrogen receptors have been identified. These vary in proportion from tissue to tissue. Circulating estrogens modulate the pituitary secretion of the gonadotropins, luteinizing hormone (LH) and follicle stimulating hormone (FSH) through a negative feedback mechanism.
Estrogens act to reduce the elevated concentrations of these hormones seen in postmenopausal women.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied MINIVELLE (estradiol transdermal system), 0.025 mg per day - each 1.65 cm 2 system contains 0.41 mg of estradiol USP for nominal* delivery of 0.025 mg of estradiol per day. Patient Calendar Pack of 8 Systems…………………………………..NDC 68968-6625-8 MINIVELLE (estradiol transdermal system), 0.0375 mg per day - each 2.48 cm 2 system contains 0.62 mg of estradiol USP for nominal* delivery of 0.0375 mg of estradiol per day. Patient Calendar Pack of 8 Systems…………………………………..NDC 68968-6637-8 MINIVELLE (estradiol transdermal system), 0.05 mg per day - each 3.3 cm 2 system contains 0.83 mg of estradiol USP for nominal* delivery of 0.05 mg of estradiol per day.
Patient Calendar Pack of 8 Systems………………………………….NDC 68968-6650-8 MINIVELLE (estradiol transdermal system), 0.075 mg per day - each 4.95 cm 2 system contains 1.24 mg of estradiol USP for nominal* delivery of 0.075 mg of estradiol per day. Patient Calendar Pack of 8 Systems………………………………….NDC 68968-6675-8 MINIVELLE (estradiol transdermal system), 0.1 mg per day - each 6.6 cm 2 system contains 1.65 mg of estradiol USP for nominal* delivery of 0.1 mg of estradiol per day. Patient Calendar Pack of 8 Systems………………………………….NDC 68968-6610-8 *See Description
16.2Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F) [ see USP Controlled Room Temperature ] Do not store unpouched. Apply immediately upon removal from the protective pouch. Used transdermal systems still contain active hormone.
To discard, fold the sticky side of the transdermal system together, place it in a sturdy child-proof container, and place this container in the trash. Used transdermal systems should not be flushed in the toilet.
📦 Storage and Handling ▾
16.2Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F) [ see USP Controlled Room Temperature ] Do not store unpouched. Apply immediately upon removal from the protective pouch. Used transdermal systems still contain active hormone.
To discard, fold the sticky side of the transdermal system together, place it in a sturdy child-proof container, and place this container in the trash. Used transdermal systems should not be flushed in the toilet.
📋 Description ▾
11 DESCRIPTION MINIVELLE (estradiol transdermal system) contains estradiol in a multipolymeric adhesive. The system is designed to release estradiol continuously upon application to intact skin. Five dosage strengths of MINIVELLE are available to provide nominal in vivo delivery rates of 0.025, 0.0375, 0.05, 0.075, or 0.1 mg of estradiol per day via the skin.
Each corresponding system has an active surface area of 1.65, 2.48, 3.30, 4.95, or 6.6 cm 2 and contains 0.41, 0.62, 0.83, 1.24, or 1.65 mg of estradiol USP, respectively. The composition of the systems per unit area is identical. Estradiol USP is a white, crystalline powder, chemically described as estra-1,3,5 (10)-triene-3,17β-diol.
The structural formula is The molecular formula of estradiol is C 18 H 24 0 2 . The molecular weight is 272.39 MINIVELLE is comprised of three layers. Proceeding from the visible surface toward the surface attached to the skin, these layers are (1) a polyolefin laminate backing (2) an adhesive formulation containing estradiol, acrylic adhesive, silicone adhesive, oleyl alcohol, NF, povidone, USP and dipropylene glycol, and (3) a polyester release liner which is attached to the adhesive surface and must be removed before the system can be used.
The active component of the system is estradiol. The remaining components of the system are pharmacologically inactive. Estradiol USP Layers of MINIVELLE
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise women to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Vaginal Bleeding Inform postmenopausal women to report unusual vaginal bleeding to their healthcare providers as soon as possible [see Warnings and Precautions ( 5.2 )] Possible Serious Adverse Reactions with Estrogen–Alone Therapy Inform postmenopausal women of possible serious adverse reactions of estrogen-alone therapy including Cardiovascular Disorders, Malignant Neoplasms, and Probable Dementia [see Warning and Precautions ( 5.1 , 5.2 , 5.3 )] .
Possible Common Adverse Reactions with Estrogen–Alone Therapy Inform postmenopausal women of less serious but common adverse reactions of estrogen-alone therapy such as headache, breast pain and tenderness, nausea and vomiting.
🍼 Nursing Mothers ▾
8.2Lactation Risk Summary Estrogens are present in human milk and can reduce milk production in breast-feeding women. This reduction can occur at any time but is less likely to occur once breast-feeding is well established. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for MINIVELLE and any potential adverse effects on the breastfed child from MINIVELLE or from the underlying maternal condition.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption In a single-dose, two way-crossover clinical study conducted in 96 healthy, non-smoking postmenopausal women under fed condition, MINIVELLE (0.1 mg per day) was bioequivalent to Vivelle (0.1 mg per day) based on estradiol exposure (AUC 0-84 ) and estradiol peak concentration (C max ) following a single-dose on the lower abdomen for 84 hours. Estradiol pharmacokinetics were characterized in a separate open-label, single-center, randomized, single-dose, three-way crossover study conducted in 36 healthy, non-smoking postmenopausal women (aged 40 to 65 years).
MINIVELLE transdermal systems delivering nominal estradiol of approximately 0.025 mg, 0.05 mg, and 0.1 mg per day were applied to the lower abdomen under fed state in a crossover fashion for 84 hours. The mean estradiol pharmacokinetics parameters are summarized in Table 2 . AUC and C max are dose proportional from 0.025 mg to 0.1 mg per day.
Table 2: Mean (SD) Serum Pharmacokinetic Parameters of Baseline-Uncorrected Estradiol following a Single Dose of MINIVELLE (N=36) a Median (minimum-maximum) Parameter 0.1 mg/day 0.05 mg/day 0.025 mg/day AUC 84 (pg·hr/mL) 5875 (1857) 3057 (980) 1763 (600) AUC 120 (pg·hr/mL) 6252 (1938) 3320 (1038) 1979 (648) C max (pg/mL) 117 (39.3) 56.6 (17.6) 30.3 (11.1) T max (hr) a 24.0 (8-60) 24.0 (8-60) 36.0 (8-84) Figure 1 illustrates the mean baseline-uncorrected estradiol serum concentrations of MINIVELLE at three different strengths.
Figure 1: Mean Baseline-Uncorrected Estradiol Serum Concentration-Time Profiles Following a Single Dose of MINIVELLE 0.1 mg per day (Treatment A), 0.05 mg per day (Treatment B), and 0.025 mg per day (Treatment C) (N=36) Distribution The distribution of exogenous estrogens is similar to that of endogenous estrogens. Estrogens are widely distributed in the body and are generally found in higher concentrations in the sex hormone target organs. Estrogens circulate in the blood largely bound to sex hormone-binding globulin (SHBG) and albumin.
Metabolism Exogenous estrogens are metabolized in the same manner as endogenous estrogens. Circulating estrogens exist in a dynamic equilibrium of metabolic interconversions. These transformations take place mainly in the liver.
Estradiol is converted reversibly to estrone, and both can be converted to estriol, which is a major urinary metabolite. Estrogens also undergo enterohepatic recirculation via sulfate and glucuronide conjugation in the liver, biliary secretion of conjugates into the intestine, and hydrolysis in the intestine followed by reabsorption. In postmenopausal women a significant portion of the circulating estrogens exist as sulfate conjugates, especially estrone sulfate, which serves as a circulating reservoir for the formation of more active estrogens.
Excretion Estradiol, estrone and estriol are excreted in the urine along with glucuronide and sulfate conjugates. The mean half-life values of estradiol calculated from treatment groups in the bioequivalence study and dose-proportionality study after dosing with MINIVELLE ranged from 6.2 to 7.9 hours. After removal of the transdermal systems, serum concentrations of estradiol and estrone returned to baseline concentrations within 24 hours.
Adhesion and Adhesive Residue Based on combined data from bioequivalence and dose proportionality studies consisting of 208 MINIVELLE observations, approximately 98 percent of the observations had an adhesion score of 0 (i.e., the skin adhesion rate was greater than or equal to 90 percent) over the 84-hour wear period. One woman had a complete detachment during the wear period. Approximately 65 percent of the transdermal systems evaluated in these studies were with MINIVELLE 0.1 mg per day (6.6 cm 2 active surface area).
After removal of MINIVELLE, women had either no adhesive residue (score of 0) or light adhesive residue (score of 1). No woman had medium adhesive residue. Of the 208 MINIVELLE observations, 54 percent had light adhesive residue an… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Generally, a serum estrogen concentration does not predict an individual woman’s therapeutic response to MINIVELLE nor her risk for adverse outcomes. Likewise, exposure comparisons across different estrogen products to infer efficacy or safety for the individual woman may not be valid.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Effects on Vasomotor Symptoms in Postmenopausal Women There have been no efficacy and safety trials conducted with MINIVELLE. In a pharmacokinetic study, MINIVELLE was shown to be bioequivalent to Vivelle. In two controlled clinical trials with Vivelle, in a total of 356 women, the 0.075 and 0.1 mg doses were superior to placebo in relieving vasomotor symptoms at Weeks 4, 8 and 12 of treatment.
In these studies, the 0.0375 and 0.05 mg doses did not differ from placebo at Week 4, therefore, a third 12-week placebo-controlled study in 255 women was performed with Vivelle to establish the efficacy of the lowest dose of 0.0375 mg. The baseline mean daily number of hot flushes in these 255 women was 11.5. Results at Weeks 4, 8, and 12 of treatment are shown in Figure 2.
Figure 2: Mean (SD) change from baseline in mean daily number of hot flushes for Vivelle 0.0375 mg versus Placebo in a 12 week trial. The 0.0375 mg dose was superior to placebo in reducing both the frequency and severity of vasomotor symptoms at Weeks 4, 8 and 12 of treatment. Figure 2: Mean (SD) change from baseline in mean daily number of hot flushes for Vivelle 0.0375 mg versus Placebo in a 12 week trial.
14.2Effects on Bone Mineral Density in Postmenopausal Women There have been no bone efficacy and safety trials conducted with MINIVELLE. In a pharmacokinetic study, MINIVELLE was shown to be bioequivalent to Vivelle. Efficacy and safety of Vivelle in the prevention of postmenopausal osteoporosis have been studied in a 2-year double-blind, randomized, placebo-controlled, parallel group study.
A total of 261 hysterectomized (161) and non-hysterectomized (100), surgically or naturally menopausal women (within 5 years of menopause), with no evidence of osteoporosis (lumbar spine bone mineral density within 2 standard deviations of average peak bone mass, i.e., ≥0.0827 g/cm 2 ) were enrolled in this study; 194 women were randomized to one of the four doses of Vivelle (0.1, 0.05, 0.0375, or 0.025 mg/day) and 67 women to placebo. Over 2 years, study systems were applied to the buttock or the abdomen twice a week.
Non-hysterectomized women received oral medroxyprogesterone acetate (2.5 mg/day) throughout the study. The study population comprised naturally (82 percent) or surgically (18 percent) menopausal, hysterectomized (61 percent) or non-hysterectomized (39 percent) women with a mean age of 52.0 years (range 27 to 62 years); the mean duration of menopause was 31.7 months (range 2 to 72 months). Two hundred thirty-two (89 percent) randomized women (173 on active drug, 59 on placebo) contributed data to the analysis of percent change from baseline in bone mineral density (BMD) of the AP lumbar spine, the primary efficacy variable.
Women were given supplemental dietary calcium (100 mg elemental calcium/day) but no supplemental vitamin D. There was an increase in BMD of the AP lumbar spine in all Vivelle dose groups; in contrast to this, a decrease in AP lumbar spine BMD was observed in placebo patients. All Vivelle doses were significantly superior to placebo (p<0.05) at all time points with the exception of Vivelle 0.05 mg/day at 6 months.
The highest dose of Vivelle was superior to the three lower doses. There were no statistically significant differences in pairwise comparisons among the three lower doses (See Figure 3 ). Figure 3: Bone mineral density – AP Lumbar spine Least squares means of percentage change from baseline All randomized women with at least one post-baseline assessment available with last post-baseline observation carried forward Analysis of percent change from baseline in femoral neck BMD, a secondary efficacy outcome variable, showed qualitatively similar results; all doses of Vivelle were significantly superior to placebo (p<0.05) at 24 months.
The highest Vivelle dose was superior to placebo at all time points. A mixture of significant and non-significant results were obtained for the lower dose groups at earlier time… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term, continuous administration of natural and synthetic estrogens in certain animal species increases the frequency of carcinomas of the breast, uterus, cervix, vagina, testis, and liver.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term, continuous administration of natural and synthetic estrogens in certain animal species increases the frequency of carcinomas of the breast, uterus, cervix, vagina, testis, and liver.
📚 References ▾
15 REFERENCES Rossouw JE, et al. Postmenopausal Hormone Therapy and Risk of Cardiovascular Disease by Age and Years Since Menopause. JAMA.
2007;297:1465-1477. Hsia J, et al. Conjugated Equine Estrogens and Coronary Heart Disease.
Arch Int Med. 2006;166:357–365. Curb JD, et al.
Venous Thrombosis and Conjugated Equine Estrogen in Women Without a Uterus. Arch Int Med. 2006; 166:772-780.
Cushman M, et al. Estrogen Plus Progestin and Risk of Venous Thrombosis. JAMA.
2004;292:1573-1580. Stefanick ML, et al. Effects of Conjugated Equine Estrogens on Breast Cancer and Mammography Screening in Postmenopausal Women with Hysterectomy.
JAMA. 2006;295:1647-1657. Chlebowski RT, et al.
Influence of Estrogen Plus Progestin on Breast Cancer and Mammography in Healthy Postmenopausal Women. JAMA. 2003;289:3234-3253.
Anderson GL, et al. Effects of Estrogen Plus Progestin on Gynecologic Cancers and Associated Diagnostic Procedures. JAMA.
2003;290:1739-1748. Shumaker SA, et al. Conjugated Equine Estrogens and Incidence of Probable Dementia and Mild Cognitive Impairment in Postmenopausal Women.
JAMA. 2004;291:2947-2958. Jackson RD, et al.
Effects of Conjugated Equine Estrogen on Risk of Fractures and BMD in Postmenopausal Women With Hysterectomy: Results From the Women's Health Initiative Randomized Trial. J Bone Miner Res. 2006;21:817-828.
Hendrix SL, et al. Effects of Conjugated Equine Estrogen on Stroke in the Women's Health Initiative. Circulation.
2006;113:2425-2434.
📄 Patient Package Insert ▾
PATIENT INFORMATION MINIVELLE (MIN-ee-vell) (estradiol transdermal system) Read this Patient Information before you start using MINIVELLE and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your menopausal symptoms or your treatment.
What is the most important information I should know about MINIVELLE (an estrogen hormone)? Using estrogen-alone may increase your chance of getting cancer of the uterus (womb). Report any unusual vaginal bleeding right away while you are using MINIVELLE.
Vaginal bleeding after menopause may be a warning sign of cancer of the uterus (womb). Your healthcare provider should check any unusual vaginal bleeding to find out the cause. Do not use estrogen-alone to prevent heart disease, heart attacks, strokes, or dementia (decline in brain function).
Using estrogen-alone may increase your chances of getting strokes or blood clots. Using estrogen-alone may increase your chance of getting dementia, based on a study of women 65 years of age and older. Do not use estrogens with progestogens to prevent heart disease, heart attacks, strokes, or dementia.
Using estrogens with progestogens may increase your chances of getting heart attacks, strokes, breast cancer, or blood clots. Using estrogens with progestogens may increase your chance of getting dementia, based on a study of women 65 years of age and older. Only one estrogen-alone product and dose have been shown to increase your chances of getting strokes, blood clots, and dementia.
Only one estrogen with progestogen product and dose have been shown to increase your chances of getting heart attacks, strokes, breast cancer, blood clots, and dementia. Because other products and doses have not been studied in the same way, it is not known how the use of MINIVELLE will affect your chances of developing these conditions. You and your healthcare provider should talk regularly about whether you still need treatment with MINIVELLE.
What is MINIVELLE? MINIVELLE is a prescription medicine patch (transdermal system) that contains the estrogen hormone estradiol. When applied to the skin, estradiol is absorbed through the skin into the bloodstream.
What is MINIVELLE ® used for? MINIVELLE is used after menopause to: Reduce moderate to severe hot flashes Estrogens are hormones made by a woman’s ovaries. The ovaries normally stop making estrogens when a woman is between 45 and 55 years old.
This drop in body estrogen levels causes the “change of life” or menopause (the end of monthly menstrual periods). Sometimes, both ovaries are removed during an operation before natural menopause takes place. The sudden drop in estrogen levels causes “surgical menopause.” When estrogen levels begin dropping, some women develop very uncomfortable symptoms, such as feelings of warmth in the face, neck, and chest or sudden intense feelings of heat and sweating (“hot flashes” or “hot flushes”).
In some women, the symptoms are mild and they will not need estrogens. In other women, symptoms can be more severe. Help reduce your chances of getting osteoporosis (thin weak bones) Osteoporosis from menopause is a thinning of the bones that makes them weaker and easier to break.
If you use MINIVELLE only to prevent osteoporosis due to menopause, talk with your healthcare provider about whether a different treatment or medicine without estrogens might be better for you. You and your healthcare provider should talk regularly about whether you should continue treatment with MINIVELLE. Who should not use MINIVELLE?
Do not start using MINIVELLE if you: have unusual vaginal bleeding Vaginal bleeding after menopause may be a warning sign of cancer of the uterus (womb). Your healthcare provider should check any unusual vaginal bleeding to find out the cause. have been diagnosed with a bleeding disorder currently have or have had certain cancers Estrogens may increase the chances of getting certain types of cancer… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE MINIVELLE ® (MIN-ee-vell) (estradiol transdermal system) Read this PATIENT INFORMATION before you start using MINIVELLE and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your menopausal symptoms or your treatment.
You will need the following supplies (See Figure A) . Figure A Step 1: Pick the days you will change your patch. You will need to change your patch 2 times a week or every 3 to 4 days.
Use the calendar printed inside your carton to choose the 2 days you will change your patch (See Figure B) . Remember to change your patch on the same 2 days you marked on your calendar. If you forget to change your patch on the correct date, apply a new patch as soon as you remember, and continue to follow your original schedule Figure B Step 2.
Remove the MINIVELLE patch from the pouch. Remove the patch from its protective pouch by tearing at the notch ( do not use scissors, See Figure C ). Do not remove your patch from the protective pouch until you are ready to apply it Figure C Step 3.
Remove half of the adhesive liner (See Figure D). Figure D Step 4. Placing the patch on your skin.
Hold the part of the patch that still has the adhesive liner on it Avoid touching the sticky half of the patch with your fingers Apply the exposed sticky half of the patch to 1 of the areas of skin shown below (See Figures E and F) . Note: Avoid the waistline, since clothing and belts may cause the patch to be rubbed off Do not apply the patch to your breasts Only apply the patch to skin that is clean, dry, and free of any powder, oil, or lotion You should not apply the patch to injured, burned, or irritated skin, or areas with skin conditions (such as birth marks, tattoos, or that is very hairy) Step 5: Press the patch firmly onto your skin.
Remove the remaining half of the adhesive liner and press the entire patch into place with the palm of your hand for 10 seconds Rub the edges of the patch with your fingers to make sure that it will stick to your skin (See Figure G) . Figure G Note: Showering will not cause your patch to fall off If your patch falls off reapply it. If you cannot reapply the patch, apply a new patch to another area (See Figures E and D) and continue to follow your original placement schedule If you stop using your MINIVELLE patch or forget to apply a new patch as scheduled, you may have spotting, or bleeding, and recurrence of symptoms Step 6: Throwing away your used patch.
When it is time to change your patch, remove the old patch before you apply a new patch To throw away the patch, fold the sticky side of the patch together, place it in a sturdy child-proof container, and place this container in the trash. Used patches should not be flushed in the toilet This Patient Information and Instructions for Use have been approved by the U.S. Food and Drug Administration.
Manufactured by: Noven Pharmaceuticals Inc. Miami, FL 33186 Approved (02/2024) Figure A Figure B Figure C Figure D Figures E and F Figure G
📄 Recent Major Changes ▾
Warnings and Precautions, Malignant Neoplasms ( 5.2 ) 02/2024
📄 Package Label / Principal Display Panel ▾
Package Label - Principal Display Panel – 0.025mg Trade Carton NDC 68968-6625-8 0.025 mg/day Minivelle ® (estradiol transdermal system) Delivers 0.025 mg/day Twice-Weekly Rx Only Includes 8 Systems Open Here Contents: 8 Systems Rx Only Each 1.65 cm 2 system contains 0.41 mg of estradiol USP. Inactive components: acrylic adhesive, silicone adhesive, oleyl alcohol, dipropylene glycol, povidone, polyolefin laminate backing, polyester release liner. For Transdermal Use Only Important: Package not child-resistant.
Apply immediate upon removal from pouch. Do not store unpouched. Store at 20°C to 25°C (68°F to 77°F). [See USP Controlled Room Temperature]. Dosage and Administration: Apply twice-weekly.
See package insert. N3 68968-6625-8 7 302348-3 Noven Your application schedule Determine which 2 days of the week you will change your patch and then mark them on this calender º Sunday/Wednesday º Thursday/Sunday º Monday/Thursday º Friday/Monday º Tuesday/Friday º Saturday/Tuesday º Wednesday/Saturday As a handy reminder of your application schedule, keep this tear out with you Pull here for your Minivelle ® patches 0.025 mg/day Mfd. by: Noven Pharmaceuticals, Inc. Miami, Florida 33186 Dist. by: Noven Therapeutics, LLC Miami, Florida 33186 0.025 mg/day Minivelle ® (estradiol transdermal system) Delivers 0.025 mg/day 01440 30248-3 LOT/EXP GTIN: 00368968662587 trade carton 0.025mg
Package Label - Principal Display Panel – 0.0375mg Carton NDC 68968-6637-8 0.0375 mg/day Minivelle ® (estradiol transdermal system) Delivers 0.0375 mg/day Twice-Weekly Rx Only Includes 8 Systems Open Here Contents: 8 Systems Rx Only Each 2.48 cm 2 system contains 0.62 mg of estradiol USP. Inactive components: acrylic adhesive, silicone adhesive, oleyl alcohol, dipropylene glycol, povidone, polyolefin laminate backing, polyester release liner. For Transdermal Use Only Important: Package not child-resistant.
Apply immediate upon removal from pouch. Do not store unpouched. Store at 20°C to 25°C (68°F to 77°F). [See USP Controlled Room Temperature].
Dosage and Administration: Apply twice-weekly. See package insert. N3 68968-6637-8 2 302360-4 Noven Your application schedule Determine which 2 days of the week you will change your patch and then mark them on this calender º Sunday/Wednesday º Thursday/Sunday º Monday/Thursday º Friday/Monday º Tuesday/Friday º Saturday/Tuesday º Wednesday/Saturday As a handy reminder of your application schedule, keep this tear out with you Pull here for your Minivelle ® patches 0.0375 mg/day Mfd. by: Noven Pharmaceuticals, Inc.
Miami, Florida 33186 Dist. by: Noven Therapeutics, LLC Miami, Florida 33186 0.0375 mg/day Minivelle ® (estradiol transdermal system) Delivers 0.025 mg/day 01440 30248-3 LOT/EXP GTIN: 00368968663782 CARTON 0.0375mg
Package Label - Principal Display Panel – 0.05mg Carton NDC 68968-6650-8 0.05 mg/day Minivelle ® (estradiol transdermal system) Delivers 0.05 mg/day Twice-Weekly Rx Only Includes 8 Systems Open Here Contents: 8 Systems Rx Only Each 3.3 cm 2 system contains 0.83 mg of estradiol USP. Inactive components: acrylic adhesive, silicone adhesive, oleyl alcohol, dipropylene glycol, povidone, polyolefin laminate backing, polyester release liner. For Transdermal Use Only Important: Package not child-resistant.
Apply immediate upon removal from pouch. Do not store unpouched. Store at 20°C to 25°C (68°F to 77°F). [See USP Controlled Room Temperature].
Dosage and Administration: Apply twice-weekly. See package insert. N3 68968-6650-8 3 302360-4 Noven Your application schedule Determine which 2 days of the week you will change your patch and then mark them on this calender º Sunday/Wednesday º Thursday/Sunday º Monday/Thursday º Friday/Monday º Tuesday/Friday º Saturday/Tuesday º Wednesday/Saturday As a handy reminder of your application schedule, keep this tear out with you Pull here for your Minivelle ® patches 0.05 mg/day Mfd. by: Noven Pharmaceuticals, Inc.
Miami, Florida 33186… [Excerpted — this section continues on DailyMed.]