
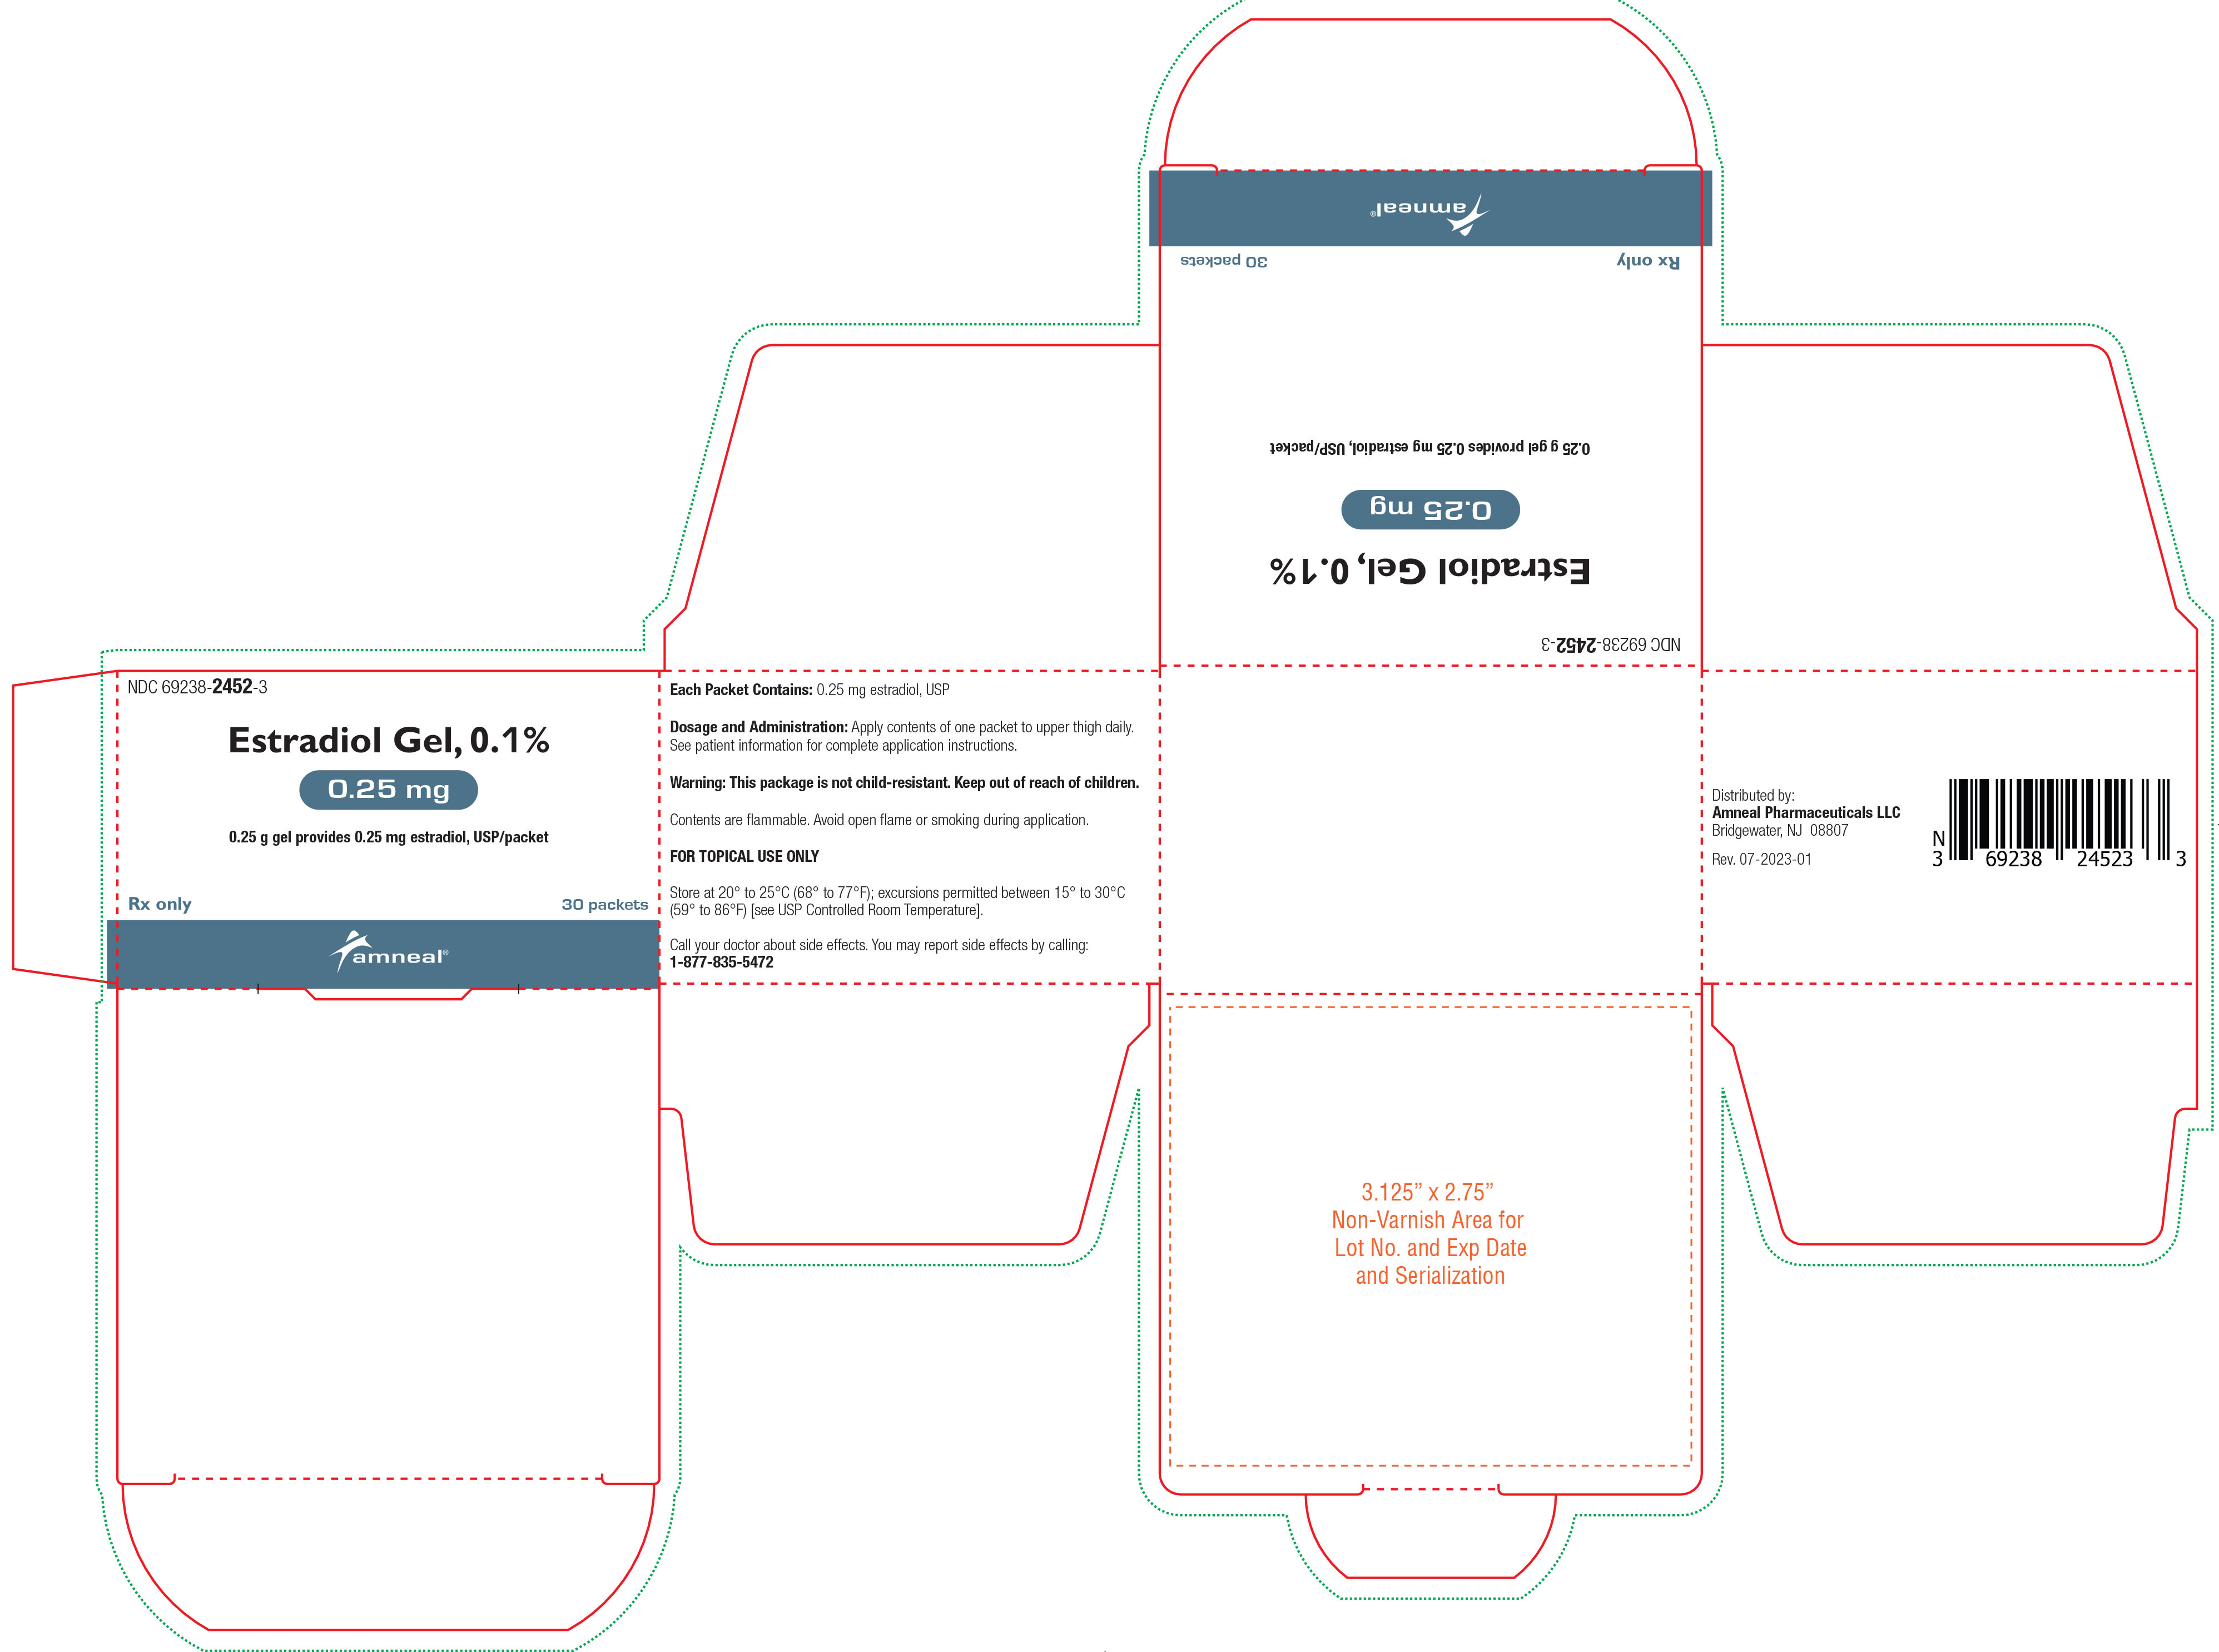
Estradiol .25 mg/.25g Gel, 30 packets
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Radioactive Diagnostic Agent class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Estradiol is a form of estrogen — the main female sex hormone. When estrogen levels fall after menopause (or due to other conditions like ovarian failure), you can get symptoms lik...
- What exactly is estradiol and why has my doctor prescribed it?
- Apply the patch to a clean, dry area of skin — usually the lower abdomen. Never put it on your breasts. Press it firmly in place and leave it on for the full wear period — once a w...
- How do I use my estradiol patch correctly?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII HHT01ZNK31
Carbomer Homopolymer Type B is a synthetic polymer made from acrylic acid. It absorbs water and forms a gel, so it's used in medicines as a thickener, suspending agent, and to help create a smooth texture in creams, gels, and lotions.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 9O3K93S3TK
Trolamine is an alkaline compound used as a pH buffer and emulsifier in medicines. It helps neutralize acids, stabilize formulations, and enable mixing of oil and water-based ingredients.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.757 | $22.71 / 30 packets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $3.26 | $97.81 / 30 packets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Estradiol .25 mg/.25g 13811-0090-32 | Trigen | 30 packets | $0.757 | AB | Availability likely | — |
| Estradiol Gel .25 mg/.25g 21922-0086-52 | Encube | 30 packets | $0.757 | AB | Availability likely | — |
| Estradiol .25 mg/.25g 45802-0134-30 | Padagis | 30 packets | $0.757 | AB | Availability likely | — |
| Estradiol .25 mg/.25gthis 69238-2452-03 | Amneal | 30 packets | $0.757 | AB | Availability likely | — |
| Estradiol .25 mg/.25g 70700-0143-35 | Xiromed, | 30 packets | $0.757 | AB | Availability likely | — |
| Estradiol .25 mg/.25g 70954-0531-20 | ANI | 30 packets | $0.757 | AB | Availability likely | — |
| Estradiol .25 mg/.25g 72603-0241-30 | NorthStar | 30 packets | $0.757 | AB | Availability likely | — |
| Divigel .25 mg/.25g 68025-0065-07 | Vertical | 7 packets | — | AB | FDA listed | — |
| Estradiol .25 mg/.25g 72162-2290-03 | Bryant | 30 packets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 69238-2452-03 You're viewing this | 30 PACKET in 1 CARTON (69238-2452-3) / .25 g in 1 PACKET (69238-2452-1) | 2024-07-15 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ENDOMETRIAL CANCER WITH UNOPPOSED ESTROGEN IN WOMEN WITH A UTERUS There is an increased risk of endometrial cancer in a woman with a uterus who uses unopposed estrogens. Adding a progestogen to estrogen-only therapy has been shown to reduce the risk of endometrial hyperplasia, which may be a precursor to endometrial cancer. Perform adequate diagnostic measures, including directed or random endometrial sampling when indicated, to rule out malignancy in menopausal women abnormal genital bleeding of unknown etiology [see Warnings and Precautions (5.2) ] .
WARNING: ENDOMETRIAL CANCER WITH UNOPPOSED ESTROGEN IN WOMEN WITH A UTERUS See full prescribing information for complete boxed warning. There is an increased risk of endometrial cancer in a woman with a uterus who uses unopposed estrogens (5.2)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Estradiol gel, 0.1% is an estrogen indicated for the treatment of moderate to severe vasomotor symptoms due to menopause (1.1) .
1.1 Treatment of Moderate to Severe Vasomotor Symptoms due to Menopause
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Daily administration of 0.25 to 1.25 grams of estradiol gel, 0.1% to the right or left upper thigh on alternating days. Women should be started with the lowest effective dose and the dose should be evaluated periodically (2) .
2.1Important Use Information The timing of estradiol gel, 0.1% initiation can affect the overall benefit-risk profile. Consider initiating estradiol gel, 0.1% in women <60 years old or <10 years since menopause onset [see Warnings and Precautions (5) , Use in Specific Populations (8.5) and Clinical Studies (14) ] . When estrogen is prescribed for a menopausal woman with a uterus, the addition of a progestogen has been shown to reduce the risk of endometrial cancer.
There are possible risks associated with the use of progestogens plus estrogens that differ from those of estrogen-alone regimens. See prescribing information for progestogens indicated for the prevention of endometrial hyperplasia in non-hysterectomized menopausal women receiving estrogens [see Warnings and Precautions (5.2 , 5.3) ] . Generally, a woman without a uterus, does not need to use a progestogen with estrogen therapy.
In some cases, however, hysterectomized women with a history of endometriosis may benefit from the addition of a progestogen [see Warnings and Precautions (5.13) ] .
2.2Treatment of Moderate to Severe Vasomotor Symptoms due to Menopause Start therapy with the 0.25 grams applied once daily on the skin of either the right or left upper thigh. Adjust the dose up to a maximum of 1.25 grams, as needed. The application surface area should be about 5 by 7 inches (approximately the size of two palm prints).
The entire contents of a unit dose packet should be applied each day. To avoid potential skin irritation, apply estradiol gel, 0.1% to the right or left upper thigh on alternating days. Do not apply estradiol gel, 0.1% on the face, breasts, or irritated skin or in or around the vagina.
Allow gel to dry after application before dressing. Do not wash the application site within 1 hour after applying estradiol gel, 0.1%. Avoid contact of the gel with eyes.
Wash hands after application.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Estradiol gel, 0.1% is available in five doses of 0.25, 0.5, 0.75, 1, and 1.25 grams for transdermal application (corresponding to 0.25, 0.5, 0.75, 1, and 1.25 mg estradiol USP, respectively). Estradiol gel, 0.1% is a clear, colorless gel, which is odorless when dry. Gel: 0.25, 0.5, 0.75, 1, and 1.25 gram-filled single-dose foil packets containing 0.25, 0.5, 0.75, 1, and 1.25 mg estradiol USP, respectively (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Estradiol gel is contraindicated in women with any of the following conditions: Abnormal genital bleeding of unknown etiology [see Warning and Precautions (5.2) ] Current or history of breast cancer [see Warning and Precautions (5.2) ] Estrogen-dependent neoplasia [see Warning and Precautions (5.2) ] Active DVT, PE, or history of these conditions [see Warning and Precautions (5.1) ] Active arterial thromboembolic disease (for example, stroke or MI), or a history of these conditions [see Warning and Precautions (5.1) ] Known anaphylactic reaction, angioedema, or hypersensitivity to estradiol gel Hepatic impairment or disease [see Warnings and Precautions (5.9) ] Protein C, protein S, or antithrombin deficiency, or other known thrombophilic disorders Undiagnosed abnormal genital bleeding (4) Breast cancer or a history of breast cancer (4 , 5.2) Estrogen-dependent neoplasia (4 , 5.2) Active DVT, PE, or history of these conditions (4 , 5.1) Active arterial thromboembolic disease (e.g., stroke and MI), or history of these conditions (4 , 5.1) Known anaphylactic reaction, angioedema, or hypersensitivity to estradiol gel (4) Hepatic impairment or disease (4 , 5.9) Protein C, protein S, or antithrombin deficiency, or other known thrombophilic disorders (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Cardiovascular Disorders: Increased risk of PE, DVT, and stroke with estrogen-alone therapy. Discontinue if an arterial or venous thrombotic or thromboembolic event occurs. (5.1) Estrogens increase the risk of gallbladder disease (5.4) Discontinue estrogen if severe hypercalcemia, loss of vision, severe hypertriglyceridemia or cholestatic jaundice occurs (5.5 , 5.6 , 5.8 , 5.9) Monitor thyroid function in women on thyroid replacement therapy (5.10 , 5.21)
5.1Cardiovascular Disorders Estradiol gel is contraindicated in women with active DVT, PE, stroke, or a history of these conditions [see Contraindications (4) ] . Immediately discontinue estradiol gel if a PE, DVT, or stroke, occurs or is suspected. If feasible, discontinue estradiol gel at least 4 to 6 weeks before surgery of the type associated with an increased risk of thromboembolism, or during periods of prolonged immobilization.
The safety and efficacy of estradiol gel for the prevention of cardiovascular disorders has not been established. The Women’s Health Initiate (WHI) estrogen-alone trial reported increased risks of pulmonary embolism (PE), deep vein thrombosis (DVT), and stroke, in postmenopausal women (50 to 79 years of age, average age 63.4 years) during 7.2 years of treatment with daily oral conjugated estrogen (CE) [0.625 mg] relative to placebo. Analyses were also conducted in women aged 50 to 59 years, a group of women more likely to present with onset of moderate to severe VMS compared to women of other age groups in the trial.
Only daily oral 0.625 mg CE was studied in the WHI estrogen-alone trial. Therefore, the relevance of the WHI findings regarding adverse cardiovascular events to lower CE doses, other routes of administration, or other estrogen products is not known. Without such data, it is not possible to definitively exclude these risks or determine the extent of these risks for other products [see Clinical Studies (14.2) ] .
Venous Thromboembolism In women aged 50 to 59 years, the WHI estrogen-alone trial reported a relative risk for PE of 1.53 (95% confidence interval [CI], 0.63, 3.75) for CE compared to placebo, with an absolute risk difference of 4 per 10,000 women-years (WYs; 10 versus 6). The relative risk for DVT was 1.66 (95% CI 0.75, 3.67) for CE compared to placebo, with a risk difference of 5 per 10,000 WYs (13 versus 8). In the overall study population of women aged 50 to 79 years, the WHI estrogen-alone trial reported a relative risk of PE of 1.35 (95% CI 0.89, 2.05) for CE compared to placebo, with a risk difference of 4 per 10,000 WYs (14 versus 10).
The relative risk for DVT was 1.48 (95% 1.06, 2.07) for CE compared to placebo, with a risk difference of 7 per 10,000 WYs (23 versus 15) [see Clinical Studies (14.2) ] . Stroke In women aged 50 to 59 years, the WHI estrogen-alone trial reported a relative risk for stroke of 0.99 (95% 0.53, 1.85) for CE compared to placebo, with a risk difference of -1 per 10,000 WYs (16 versus 17). In the overall study population of women aged 50 to 79 years, the WHI estrogen-alone trial reported a relative risk for stroke of 1.35 (95%, 1.07, 1.70) for CE compared to placebo, with a risk difference of 11 per 10,000 WYs (45 versus 34) [see Clinical Studies (14.2) ] .
5.2Malignant Neoplasms Endometrial Cancer In estradiol gel-treated menopausal women with a uterus with persistent or recurring abnormal genital bleeding of unknown etiology, perform adequate diagnostic measures, including directed or random endometrial sampling when indicated, to assess for endometrial cancer. An increased risk of endometrial cancer has been reported with the use of unopposed estrogen therapy in a woman with a uterus. The reported endometrial cancer risk among unopposed estrogen users is about 2 to 12 times greater than in non-users and appears dependent on duration of treatment and on estrogen dose.
Most studies show no significant increased risk associated with use of estrogens for less than 1…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed elsewhere in the labeling: Cardiovascular Disorders [see Boxed Warning , Warnings and Precautions (5.1) ] . Malignant Neoplasms [see Boxed Warning , Warnings and Precautions (5.2) ] . The most common adverse reactions (incidence >5 percent and greater than placebo) in any estradiol gel treatment group are metrorrhagia, breast tenderness, vaginal mycosis, nasopharyngitis, and upper respiratory tract infection (6.1) .
To report SUSPECTED ADVERSE REACTIONS, contact Amneal Pharmaceuticals at 1-877-835-5472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Estradiol gel was studied at doses of 0.25, 0.5 and 1 gram per day in a 12-week, double-blind, placebo-controlled study that included a total of 495 postmenopausal women (86.5 percent Caucasian). The adverse reactions that occurred at a rate greater than 5 percent and greater than placebo in any of the treatment groups are summarized in Table 1.
Table 1: Number (%) of Subjects with Common Adverse Reactions* in a 12-Week Placebo-Controlled Study of Estradiol Gel Estradiol Gel Placebo SYSTEM ORGAN CLASS Preferred Term 0.25 grams/day N=122 n (%) 0.5 grams/day N=123 n (%) 1 gram/day N=125 n (%) N=125 n (%) INFECTIONS & INFESTATIONS Nasopharyngitis 7 (5.7) 5 (4.1) 6 (4.8) 5 (4.0) Upper Respiratory Tract Infection 7 (5.7) 3 (2.4) 2 (1.6) 2 (1.6) Vaginal mycosis 1 (0.8) 3 (2.4) 8 (6.4) 4 (3.2) REPRODUCTIVE SYSTEM & BREAST DISORDERS Breast Tenderness 3 (2.5) 7 (5.7) 11 (8.8) 2 (1.6) Metrorrhagia 5 (4.1) 7 (5.7) 12 (9.6) 2 (1.6) *Adverse reactions reported by >5 percent of patients in any treatment group.
In a 12-week placebo-controlled study of estradiol gel, application site reactions were seen in <1 percent of participating women.
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of estradiol gel. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Genitourinary System Amenorrhea, dysmenorrhea, ovarian cyst, vaginal discharge Breasts Gynecomastia Cardiovascular Palpitations, ventricular extrasystoles Gastrointestinal Flatulence Skin Rash pruritic, urticaria Eyes Retinal vein occlusion Central Nervous System Tremor Miscellaneous Arthralgia, application site rash, asthenia, chest discomfort, fatigue, feeling abnormal, heart rate increased, insomnia, malaise, muscle spasms, pain in extremity, weight increased
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS In vitro and in vivo studies have shown that estrogens are metabolized partially by cytochrome P450 3A4 (CYP3A4). Therefore, inducers or inhibitors of CYP3A4 may affect estrogen drug metabolism. Inducers of CYP3A4, such as St.
John's wort ( Hypericum perforatum ) preparations, phenobarbital, carbamazepine, and rifampin, may reduce plasma concentrations of estrogens, possibly resulting in a decrease in therapeutic effects and/or changes in the uterine bleeding profile. Inhibitors of CYP3A4, such as erythromycin, clarithromycin, ketoconazole, itraconazole, ritonavir, and grapefruit juice, may increase plasma concentrations of estrogens and result in adverse reactions. Inducers and inhibitors of CYP3A4 may affect estrogen drug metabolism and decrease or increase the estrogen plasma concentration (7) .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Estradiol gel is not indicated for use in pregnant women. There are no data with the use of estradiol gel in pregnant women; however, epidemiologic studies and meta-analyses have not found an increased risk of genital or nongenital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to combined hormonal contraceptives (estrogen and progestins) before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
8.2Lactation Risk Summary Estrogens are present in human milk and can reduce milk production in breast-feeding women. This reduction can occur at any time but is less likely to occur once breast-feeding is well established. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for estradiol gel and any potential adverse effects on the breastfed child from estradiol gel or from the underlying maternal condition.
8.4Pediatric Use Estradiol gel is not indicated for use in pediatric patients. Clinical studies have not been conducted in the pediatric population.
8.5Geriatric Use There have not been sufficient numbers of geriatric women involved in clinical studies utilizing estradiol gel to determine whether those over 65 years of age differ from younger subjects in their response to estradiol gel. The Women’s Health Initiative Studies In the WHI estrogen-alone trial (daily CE [0.625 mg]-alone versus placebo), there was a higher relative risk of stroke in women greater than 65 years of age [see Clinical Studies (14.2) ] . The Women's Health Initiative Memory Study In the WHIMS ancillary studies of postmenopausal women 65 to 79 years of age, there was an increased risk of probable dementia in women receiving estrogen-alone [see Clinical Studies (14.3) ] .
Since the trial was conducted in women 65 to 79 years of age, it is unknown whether these findings apply to younger postmenopausal women [see Clinical Studies (14.3) ] . The safety and efficacy of estradiol gel for the prevention of dementia has not been established.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Estradiol gel is not indicated for use in pregnant women. There are no data with the use of estradiol gel in pregnant women; however, epidemiologic studies and meta-analyses have not found an increased risk of genital or nongenital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to combined hormonal contraceptives (estrogen and progestins) before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use Estradiol gel is not indicated for use in pediatric patients. Clinical studies have not been conducted in the pediatric population.
🧓 Geriatric Use ▾
8.5Geriatric Use There have not been sufficient numbers of geriatric women involved in clinical studies utilizing estradiol gel to determine whether those over 65 years of age differ from younger subjects in their response to estradiol gel. The Women’s Health Initiative Studies In the WHI estrogen-alone trial (daily CE [0.625 mg]-alone versus placebo), there was a higher relative risk of stroke in women greater than 65 years of age [see Clinical Studies (14.2) ] . The Women's Health Initiative Memory Study In the WHIMS ancillary studies of postmenopausal women 65 to 79 years of age, there was an increased risk of probable dementia in women receiving estrogen-alone [see Clinical Studies (14.3) ] .
Since the trial was conducted in women 65 to 79 years of age, it is unknown whether these findings apply to younger postmenopausal women [see Clinical Studies (14.3) ] . The safety and efficacy of estradiol gel for the prevention of dementia has not been established.
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of estrogen may cause nausea and vomiting, breast tenderness, abdominal pain, drowsiness and fatigue, and withdrawal bleeding in women. Treatment of overdose consists of discontinuation of estradiol gel therapy with institution of appropriate symptomatic care.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Endogenous estrogens are largely responsible for the development and maintenance of the female reproductive system and secondary sexual characteristics. Although circulating estrogens exist in a dynamic equilibrium of metabolic interconversions, estradiol is the principal intracellular human estrogen and is substantially more potent than its metabolites, estrone and estriol, at the receptor level. The primary source of estrogen in normally cycling adult women is the ovarian follicle, which secretes 70 to 500 mcg of estradiol daily, depending on the phase of the menstrual cycle.
After menopause, most endogenous estrogen is produced by conversion of androstenedione, which is secreted by the adrenal cortex, to estrone in the peripheral tissues. Thus, estrone and the sulfate conjugated form, estrone sulfate, are the most abundant circulating estrogens in postmenopausal women. Estrogens act through binding to nuclear receptors in estrogen-responsive tissues.
To date, two estrogen receptors have been identified. These vary in proportion from tissue to tissue. Circulating estrogens modulate the pituitary secretion of the gonadotropins, luteinizing hormone (LH) and FSH, through a negative feedback mechanism.
Estrogens act to reduce the elevated levels of these hormones seen in postmenopausal women.
12.2Pharmacodynamics Generally, a serum estrogen concentration does not predict an individual woman’s therapeutic response to estradiol gel nor her risk for adverse outcomes. Likewise, exposure comparisons across different estrogen products to infer efficacy or safety for the individual woman may not be valid.
12.3Pharmacokinetics Absorption Estradiol diffuses across intact skin and into the systemic circulation by a passive absorption process, with diffusion across the stratum corneum being the rate-limiting factor. In a 14-day, Phase 1, multiple-dose study, estradiol gel demonstrated linear and approximately dose-proportional estradiol pharmacokinetics at steady-state for both AUC 0-24 and C max following once daily dosing to the skin of either the right or left upper thigh (Table 2). Table 2: Mean (%CV) Pharmacokinetic Parameters for Estradiol (uncorrected for baseline) on Day 14 Following Multiple Daily Doses of Estradiol Gel 0.1% Parameter (units) Estradiol Gel 0.25 grams Estradiol Gel 0.5 grams Estradiol Gel 1 gram AUC 0-24 (pg•h/mL) 236 (94) 504 (149) 732 (81) C max (pg/mL) 14.7 (84) 28.4 (139) 51.5 (86) C avg (pg/mL) 9.8 (92) 21 (148) 30.5 (81) t max * (h) 16 (0, 72) 10 (0, 72) 8 (0, 48) E2:E1 ratio 0.42 0.65 0.65 *Median (Min, Max).
Steady-state serum concentration of estradiol are achieved by day 12 following daily application of estradiol gel to the skin of the upper thigh. The mean (SD) serum estradiol levels following once daily dosing at day 14 are shown in Figure 1. Figure 1: Mean (SD) Serum Estradiol Concentrations (Values Uncorrected for Baseline) on Day 14 Following Multiple Daily Doses of Estradiol Gel 0.1% The effect of sunscreens and other topical lotions on the systemic exposure of estradiol gel has not been evaluated.
Studies conducted using topical estrogen gel approved products have shown that sunscreens have the potential for changing the systemic exposure of topically applied estrogen gels. Distribution The distribution of exogenous estrogens is similar to that of endogenous estrogens. Estrogens are widely distributed in the body and are generally found in higher concentrations in the sex hormone target organs.
Estrogens circulate in the blood largely bound to SHBG and albumin. Metabolism Exogenous estrogens are metabolized in the same manner as endogenous estrogens. Circulating estrogens exist in a dynamic equilibrium of metabolic interconversions.
These transformations take place mainly in the liver. Estradiol is converted reversibly to estrone, and both can be converted to estriol, which is a major urinary metabolite. Estrogens also undergo enterohepatic recir…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Endogenous estrogens are largely responsible for the development and maintenance of the female reproductive system and secondary sexual characteristics. Although circulating estrogens exist in a dynamic equilibrium of metabolic interconversions, estradiol is the principal intracellular human estrogen and is substantially more potent than its metabolites, estrone and estriol, at the receptor level. The primary source of estrogen in normally cycling adult women is the ovarian follicle, which secretes 70 to 500 mcg of estradiol daily, depending on the phase of the menstrual cycle.
After menopause, most endogenous estrogen is produced by conversion of androstenedione, which is secreted by the adrenal cortex, to estrone in the peripheral tissues. Thus, estrone and the sulfate conjugated form, estrone sulfate, are the most abundant circulating estrogens in postmenopausal women. Estrogens act through binding to nuclear receptors in estrogen-responsive tissues.
To date, two estrogen receptors have been identified. These vary in proportion from tissue to tissue. Circulating estrogens modulate the pituitary secretion of the gonadotropins, luteinizing hormone (LH) and FSH, through a negative feedback mechanism.
Estrogens act to reduce the elevated levels of these hormones seen in postmenopausal women.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Estradiol gel, 0.1% is a clear, colorless, smooth, opalescent gel free from lumps and foreign matter filled in single-dose foil packets of 0.25, 0.5, 0.75, 1, and 1.25 grams, corresponding to 0.25, 0.5, 0.75, 1, and 1.25 mg estradiol USP, respectively. NDC 69238-2452-3, carton of 30 packets, 0.25 mg estradiol, USP per single-dose foil packet NDC 69238-2451-3, carton of 30 packets, 0.5 mg estradiol, USP per single-dose foil packet NDC 69238-2450-3, carton of 30 packets, 0.75 mg estradiol, USP per single-dose foil packet NDC 69238-2449-3, carton of 30 packets, 1 mg estradiol, USP per single-dose foil packet NDC 69238-2448-3, carton of 30 packets, 1.25 mg estradiol, USP per single-dose foil packet Keep out of the reach of children.
16.2Storage and Handling Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature.]
📋 Description ▾
11 DESCRIPTION Estradiol gel 0.1%, is a clear, colorless gel, which is odorless when dry. It is designed to deliver sustained circulating concentrations of estradiol, USP when applied once daily to the skin. The gel is applied to a small area (200 cm 2 ) of the thigh in a thin layer.
Estradiol gel is available in five doses of 0.25, 0.5, 0.75, 1, and 1.25 grams for topical application (corresponding to 0.25, 0.5, 0.75, 1, and 1.25 mg estradiol USP, respectively). The active component of the topical gel is estradiol USP, an estrogen. Estradiol, USP is a white crystalline powder, chemically described as estra-1,3,5(10)-triene-3,17ß-diol.
It has an empirical formula of C 18 H 24 O 2 and molecular weight of 272.38. The structural formula is: The remaining components of the gel (carbomer homopolymer type B, ethyl alcohol 95%, propylene glycol, purified water, and trolamine) are pharmacologically inactive. Estradiol gel, 0.1% contains 55% w/w alcohol.
Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise women to read the FDA-Approved patient labeling ( Patient Information and Instructions for Use). Vaginal Bleeding Inform postmenopausal women to report any vaginal bleeding to their healthcare provider as soon as possible [see Warnings and Precautions (5.2) ] . Unintentional Secondary Exposure to Estradiol Gel Inform women about the possibility of secondary exposure to estradiol gel: Apply estradiol gel as directed and keep children from contacting exposed application site(s).
If direct contact with the application site occurs, wash the contact area thoroughly with soap and water. Look for signs of unexpected sexual development, such as breast mass or increased breast size in prepubertal children. If signs of unintentional secondary exposure are noticed: Have the child(ren) evaluated by a healthcare provider.
Have women contact their healthcare provider to discuss the appropriate use and handling of estradiol gel when around children. Pets may also be unintentionally exposed to estradiol gel if above precautions are not followed. Possible Serious Adverse Reactions with Estrogen-Alone Therapy Inform postmenopausal women of possible serious adverse reactions of estrogen-alone therapy including Cardiovascular Disorders and Malignant Neoplasms [see Warnings and Precautions (5.1 , 5.2) ] .
Possible Less Serious but Common Adverse Reactions with Estrogen-Alone Therapy Inform postmenopausal women of possible less serious but common adverse reactions of estrogen-alone therapy such as headaches, breast pain and tenderness, nausea and vomiting. Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev. 02-2026-05
💬 Patient Medication Information ▾
PATIENT INFORMATION Estradiol (es” tra dye’ ol) Gel, 0.1% Read this Patient Information leaflet before you start using estradiol gel, 0.1% and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your menopausal symptoms or your treatment.
WHAT IS THE MOST IMPORTANT INFORMATION I SHOULD KNOW ABOUT ESTRADIOL GEL, 0.1% (AN ESTROGEN HORMONE)? Using estrogen-alone increases your chance of getting cancer of the uterus (womb). Report any unusual vaginal bleeding right away while you are using estradiol gel, 0.1%.
Vaginal bleeding after menopause may be a warning sign of cancer of the uterus (womb). Your healthcare provider should check any unusual vaginal bleeding to find out the cause. Do not use estrogen-alone to prevent heart disease, heart attacks, strokes or dementia (decline of brain function) Using estrogen-alone may increase your chances of getting strokes or blood clots Only one estrogen-alone product and dose have been shown to increase your chances of getting strokes, blood clots, and dementia.
Because other products and doses have not been studied in the same way, it is not known how the use of estradiol gel, 0.1% will affect your chances of these conditions. You and your healthcare provider should talk regularly about whether you still need treatment with estradiol gel, 0.1%. What is estradiol gel, 0.1%?
Estradiol gel, 0.1% is a prescription medicine that contains estradiol (an estrogen hormone). Estradiol gel, 0.1% is a clear, colorless, smooth gel that is odorless when dry. When applied to the skin, estradiol is absorbed through the skin into the bloodstream.
What is estradiol gel, 0.1% used for? Estradiol gel, 0.1% is used after menopause to: Reduce moderate to severe hot flashes Estrogens are hormones made by a woman's ovaries. The ovaries normally stop making estrogens when a woman is between 45 to 55 years old.
This drop in body estrogen levels causes the "change of life" or menopause (the end of monthly menstrual periods). Sometimes, both ovaries are removed during an operation before natural menopause takes place. The sudden drop in estrogen levels causes "surgical menopause." When the estrogen levels begin dropping, some women develop very uncomfortable symptoms, such as feelings of warmth in the face, neck, and chest, or sudden intense feelings of heat and sweating ("hot flashes" or "hot flushes").
In some women, the symptoms are mild, and they will not need estrogens. In other women, symptoms can be more severe. Who should not use estradiol gel, 0.1%?
Do not start using estradiol gel, 0.1% if you: have any unusual vaginal bleeding Vaginal bleeding after menopause may be a warning sign of cancer of the uterus (womb). Your healthcare provider should check any unusual vaginal bleeding to find out the cause. have been diagnosed with a bleeding disorder currently have or have had certain cancers Estrogens may increase the chances of getting certain types of cancers, including cancer of the breast or uterus (womb). If you have or have had cancer, talk with your healthcare provider about whether you should use estradiol gel, 0.1%. had a stroke or heart attack currently have or have had blood clots currently have or have had liver problems are allergic to estradiol gel, 0.1% or any of its ingredients See the list of ingredients in estradiol gel, 0.1% at the end of this leaflet.
Before you use estradiol gel, 0.1%, tell your healthcare provider about all of your medical conditions, including if you: have any unusual vaginal bleeding Vaginal bleeding after menopause may be a warning sign of cancer of the uterus (womb). Your healthcare provider should check any unusual vaginal bleeding to find out the cause. have any other medical conditions that may become worse while you are using estradiol gel, 0.1% Your healthcare provider may need to check you more carefully if you have certain conditions, such as asthma (wheezing), epilepsy (…