
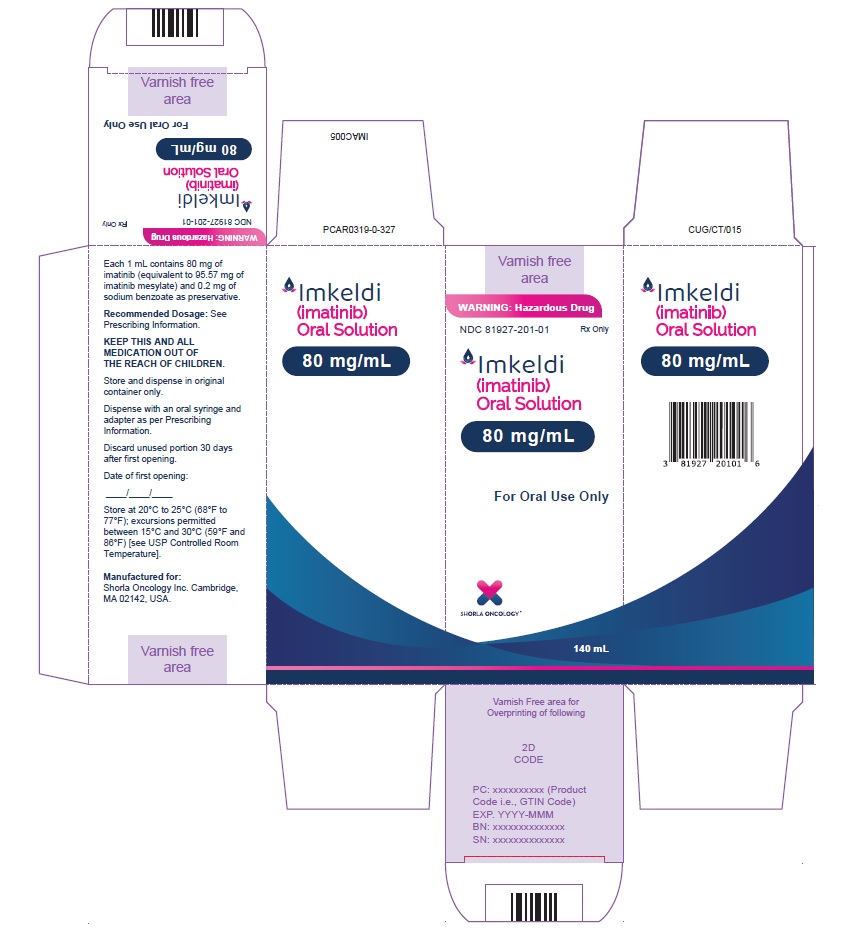
IMKELDI imatinib oral 80 mg/mL Solution, 140 mL — NDC 81927-201-01 (Billing 81927-0201-01)
This is a package of 140 mL of IMKELDI imatinib oral 80 mg/mL Solution from Shorla Oncology Inc.,, marketed since Dec 2024 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 81927-201-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 81927 labeler · 201 product · 01 package
- Package marketed since
- Dec 19, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 140 mL per package
- Barcode (UPC-A, from the NDC)
- 3 8192720101 6
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 086796
- GCN: 56566
- GPI-14 (Medi-Span): 21531835102020
- HICL (First Databank): 022096
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 2699831
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Imatinib targets specific proteins that are driving your cancer cells to grow out of control. In leukemias like CML, it blocks a faulty protein called BCR-ABL that results from a g...
- What exactly is imatinib treating in my body?
- Yes — always take imatinib with a meal and a large glass of water. Taking it on an empty stomach increases the chance of nausea and stomach irritation. If you're taking the tablet...
- Does it matter when I take it or whether I eat first?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $17.52 | $2,452.87 / 140 ml |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 81927-0201-01 You're viewing this Main listing | 140 mL in 1 BOTTLE | 2024-12-19 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Imkeldi 80 mg/mLthis 81927-0201-01 | Shorla | 140 ml | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11957681 ↗ | Drug product | — | Apr 27, 2040 |
Is there a generic version of IMKELDI 80 MG/ML SOLUTION?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 23OV73Q5G9
Acesulfame potassium is an artificial sweetener that tastes about 200 times sweeter than sugar. It's added to medicines to improve taste without adding calories or affecting blood sugar.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII 33X04XA5AT
Lactic acid is a naturally occurring organic acid derived from milk or plant sources. It lowers and maintains pH in formulations, helps preserve the product, and can enhance ingredient stability and absorption.
-
UNII D65DG142WK
Maltitol is a sugar alcohol made by hydrogenating maltose. It's used as a sweetener and filler in medicines to improve taste and add bulk to tablets and capsules.
-
UNII OJ245FE5EU
Sodium benzoate is a salt derived from benzoic acid, a preservative. It's added to medicines to prevent growth of bacteria, fungi, and other microorganisms that could spoil the product.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Shorla Oncology Inc., labeler code 81927
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Imkeldi is a kinase inhibitor indicated for the treatment of: Newly diagnosed adult and pediatric patients with Philadelphia chromosome positive chronic myeloid leukemia (Ph+ CML) in chronic phase. ( 1.1 ) Patients with Philadelphia chromosome positive chronic myeloid leukemia (Ph+ CML) in blast crisis (BC), accelerated phase (AP), or in chronic phase (CP) after failure of interferon-alpha therapy. ( 1.2 ) Adult patients with relapsed or refractory Philadelphia chromosome positive acute lymphoblastic leukemia (Ph+ ALL).
( 1.3 ) Pediatric patients with newly diagnosed Philadelphia chromosome positive acute lymphoblastic leukemia (Ph+ ALL) in combination with chemotherapy. ( 1.4 ) Adult patients with myelodysplastic/myeloproliferative diseases (MDS/MPD) associated with platelet-derived growth factor receptor (PDGFR) gene re-arrangements. ( 1.5 ) Adult patients with aggressive systemic mastocytosis (ASM) without the D816V c-Kit mutation or with c-Kit mutational status unknown.
( 1.6 ) Adult patients with hypereosinophilic syndrome (HES) and/or chronic eosinophilic leukemia (CEL) who have the FIP1L1-PDGFRα fusion kinase (mutational analysis or fluorescence in situ hybridization [FISH] demonstration of CHIC2 allele deletion) and for patients with HES and/or CEL who are FIP1L1-PDGFRα fusion kinase negative or unknown. ( 1.7 ) Adult patients with unresectable, recurrent and/or metastatic dermatofibrosarcoma protuberans (DFSP). ( 1.8 ) Patients with Kit (CD117) positive unresectable and/or metastatic malignant gastrointestinal stromal tumors (GIST).
( 1.9 ) Adjuvant treatment of adult patients following resection of Kit (CD117) positive GIST. ( 1.10 )
1.1Newly Diagnosed Philadelphia Positive Chronic Myeloid Leukemia (Ph+ CML) Newly diagnosed adult and pediatric patients with Philadelphia chromosome positive chronic myeloid leukemia (Ph+ CML) in chronic phase.
1.2Ph+ CML in Blast Crisis (BC), Accelerated Phase (AP) or Chronic Phase (CP) After Interferon-alpha (IFN) Therapy Patients with Philadelphia chromosome positive chronic myeloid leukemia in blast crisis, accelerated phase, or in chronic phase after failure of interferon-alpha therapy.
1.3Adult Patients With Ph+ Acute Lymphoblastic Leukemia (ALL) Adult patients with relapsed or refractory Philadelphia chromosome positive acute lymphoblastic leukemia (Ph+ ALL).
1.4Pediatric Patients With Ph+ Acute Lymphoblastic Leukemia (ALL) Pediatric patients with newly diagnosed Philadelphia chromosome positive acute lymphoblastic leukemia (Ph+ ALL) in combination with chemotherapy.
1.5Myelodysplastic/Myeloproliferative Diseases (MDS/MPD) Adult patients with myelodysplastic/myeloproliferative diseases associated with platelet-derived growth factor receptor (PDGFR) gene re-arrangements.
1.6Aggressive Systemic Mastocytosis (ASM) Adult patients with aggressive systemic mastocytosis without the D816V c-Kit mutation or with c-Kit mutational status unknown.
1.7Hypereosinophilic Syndrome (HES) and/or Chronic Eosinophilic Leukemia (CEL) Adult patients with hypereosinophilic syndrome and/or chronic eosinophilic leukemia who have the FIP1L1-PDGFRα fusion kinase (mutational analysis or fluorescence in situ hybridization [FISH] demonstration of CHIC2 allele deletion) and for patients with HES and/or CEL who are FIP1L1-PDGFRα fusion kinase negative or unknown.
1.8Dermatofibrosarcoma Protuberans (DFSP) Adult patients with unresectable, recurrent and/or metastatic dermatofibrosarcoma protuberans.
1.9Kit+ Gastrointestinal Stromal Tumors (GIST) Patients with Kit (CD117) positive unresectable and/or metastatic malignant gastrointestinal stromal tumors.
1.10Adjuvant Treatment of GIST Adjuvant treatment of adult patients following complete gross resection of Kit (CD117) positive GIST.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adults with Ph+ CML CP ( 2.2 ): 400 mg/day Adults with Ph+ CML AP or BC ( 2.2 ): 600 mg/day Pediatrics with Ph+ CML CP ( 2.3 ): 340 mg/m 2 /day Adults with Ph+ ALL ( 2.4 ): 600 mg/day Pediatrics with Ph+ ALL ( 2.5 ): 340 mg/m 2 /day Adults with MDS/MPD ( 2.6 ): 400 mg/day Adults with ASM ( 2.7 ): 100 mg/day or 400 mg/day Adults with HES/CEL ( 2.8 ): 100 mg/day or 400 mg/day Adults with DFSP ( 2.9 ): 800 mg/day Adults with metastatic and/or unresectable GIST ( 2.10 ): 400 mg/day Adjuvant treatment of adults with GIST ( 2.11 ): 400 mg/day Patients with mild to moderate hepatic impairment ( 2.12 ): 400 mg/day Patients with severe hepatic impairment ( 2.12 ): 300 mg/day All doses of Imkeldi should be taken with a meal and a large glass of water.
Doses of 400 mg or 600 mg should be administered once daily, whereas a dose of 800 mg should be administered as 400 mg twice a day. Imkeldi is intended for oral use only. It is important that Imkeldi be measured with an accurate measuring device.
A household teaspoon is not an accurate measuring device. A pharmacist can provide an appropriate press-in bottle adapter and oral dispensing syringe and can provide instructions for measuring the correct dose. ( 2.1 , 5.15 )
2.1Important Administration Instructions All doses of Imkeldi should be taken with a meal and a large glass of water. Doses of 400 mg or 600 mg should be administered once daily, and a dose of 800 mg should be administered as 400 mg twice a day. If a dose is missed, the patient should wait until the next scheduled dose and not take two doses at the same time.
Imkeldi is intended for oral use only. It is important that Imkeldi be measured with an accurate measuring device [see Warnings and Precautions (5.15) , Instructions for Use ]. A household teaspoon is not an accurate measuring device.
A pharmacist can provide a press-in bottle adapter and oral dispensing syringe and can provide instructions for measuring the correct dose. Recommendations for Dose Rounding Round each dose to the nearest measurable graduation mark on the oral syringe, if necessary [see Instructions for Use ] . Continue treatment until disease progression or unacceptable toxicity.
Imkeldi is a hazardous drug. Follow applicable special handling and disposal procedures 1 .
2.2Adult Patients With Ph+ CML CP, AP, or BC The recommended dosage of Imkeldi is 400 mg/day for adult patients in chronic phase CML and 600 mg/day for adult patients in accelerated phase or blast crisis. In CML, a dose increase from 400 mg to 600 mg in adult patients with chronic phase disease, or from 600 mg to 800 mg (given as 400 mg twice daily) in adult patients in accelerated phase or blast crisis may be considered in the absence of severe adverse drug reaction and severe non-leukemia related neutropenia or thrombocytopenia in the following circumstances: disease progression (at any time), failure to achieve a satisfactory hematologic response after at least 3 months of treatment, failure to achieve a cytogenetic response after 6 to 12 months of treatment, or loss of a previously achieved hematologic or cytogenetic response.
2.3Pediatric Patients With Ph+ CML CP The recommended dosage of Imkeldi for pediatric patients with newly diagnosed Ph+ CML is 340 mg/m 2 /day (not to exceed 600 mg). Imkeldi treatment can be given as a once daily dose or the daily dose may be split into two–one portion doses in the morning and one portion in the evening. There is no experience with Imkeldi treatment in children under 1 year of age.
Follow recommendations for dose rounding [see Dosage and Administration (2.1) ].
2.4Adult Patients With Ph+ ALL The recommended dosage of Imkeldi is 600 mg/day for adult patients with relapsed/refractory Ph+ ALL.
2.5Pediatric Patients With Ph+ ALL The recommended dosage of Imkeldi to be given in combination with chemotherapy to pediatric patients with newly diagnosed Ph+ ALL is 340 mg/m 2 /day (not to exceed 600 mg). Imkeldi treatment c… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Oral solution: 80 mg/mL imatinib as 140 mL of a clear yellow to brownish yellow colored solution with a strawberry flavor. Oral solution: 80 mg/mL of imatinib ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Fluid Retention and Edema: Edema and severe fluid retention have occurred. Weigh patients regularly and manage unexpected rapid weight gain by drug interruption and diuretics. ( 5.1 , 6.1 ) Hematologic Toxicity: Cytopenias, particularly anemia, neutropenia, and thrombocytopenia, have occurred.
Manage with dose reduction, dose interruption, or discontinuation of treatment. Perform complete blood counts weekly for the first month, biweekly for the second month, and periodically thereafter. ( 5.2 ) Congestive Heart Failure and Left Ventricular Dysfunction: Severe congestive heart failure and left ventricular dysfunction have been reported, particularly in patients with comorbidities and risk factors.
Monitor and treat patients with cardiac disease or risk factors for cardiac failure. ( 5.3 ) Hepatotoxicity: Severe hepatotoxicity, including fatalities may occur. Assess liver function before initiation of treatment and monthly thereafter or as clinically indicated.
Monitor liver function when combined with chemotherapy known to be associated with liver dysfunction. ( 5.4 ) Hemorrhage: Grade 3/4 hemorrhage has been reported in clinical studies in patients with newly diagnosed CML and with GIST. GI tumor sites may be the source of GI bleeds in GIST.
( 5.5 ) Gastrointestinal Disorders: Gastrointestinal (GI) perforations, some fatal, have been reported. ( 5.6 ) Hypereosinophilic Cardiac Toxicity: Cardiogenic shock/left ventricular dysfunction has been associated with the initiation of Imkeldi in patients with conditions associated with high eosinophil levels (e.g., HES, MDS/MPD, and ASM). ( 5.7 ) Dermatologic Toxicities: Bullous dermatologic reactions (e.g., erythema multiforme and Stevens-Johnson syndrome) have been reported with the use of Imkeldi.
( 5.8 ) Hypothyroidism: Hypothyroidism has been reported in thyroidectomy patients undergoing levothyroxine replacement. Closely monitor TSH levels in such patients. ( 5.9 ) Embryo-Fetal Toxicity: Can cause fetal harm.
Advise females of reproductive potential of the potential risk to the fetus, and to use effective contraception. ( 5.10 , 8.1 ) Growth Retardation in Children and Adolescents: Growth retardation occurring in children and pre-adolescents receiving Imkeldi has been reported. Close monitoring of growth in children under Imkeldi treatment is recommended.
( 5.11 , 6.2 ) Tumor Lysis Syndrome: Close monitoring is recommended. ( 5.12 ) Impairments Related to Driving and Using Machinery: Motor vehicle accidents have been reported in patients receiving imatinib. Caution patients about driving a car or operating machinery.
( 5.13 ) Renal Toxicity: A decline in renal function may occur in patients receiving Imkeldi. Evaluate renal function at baseline and during therapy, with attention to risk factors for renal dysfunction. ( 5.14 ) Measuring Device: Advise patients to measure IMKELDI with an accurate milliliter measuring device.
Inform patients that a household teaspoon is not an accurate measuring device and could lead to overdosage, which can result in serious adverse reactions. Advise patients to ask their pharmacist to recommend an appropriate press-in bottle adapter and oral dispensing syringe and for instructions for measuring the correct dose. ( 5.15 )
5.1Fluid Retention and Edema Imatinib can cause edema and occasionally serious fluid retention [see Adverse Reactions (6.1) ] . Weigh and monitor patients regularly for signs and symptoms of fluid retention. Investigate unexpected rapid weight gain carefully and provide appropriate treatment.
The probability of edema was increased with higher imatinib dose and age greater than 65 years in the CML studies. Severe superficial edema was reported in 1.5% of newly diagnosed CML patients taking imatinib, and in 2% to 6% of other adult CML patients taking imatinib. In addition, other severe fluid retention (e.g., pleural effusion, pericardial effusion, pulmonary edema, and ascites) reactions were reported in 1… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in the labeling: Fluid Retention and Edema [see Warnings and Precautions (5.1) ] Hematologic Toxicity [see Warnings and Precautions (5.2) ] Congestive Heart Failure and Left Ventricular Dysfunction [see Warnings and Precautions (5.3) ] Hepatotoxicity [see Warnings and Precautions (5.4) ] Hemorrhage [see Warnings and Precautions (5.5) ] Gastrointestinal Disorders [see Warnings and Precautions (5.6) ] Hypereosinophilic Cardiac Toxicity [see Warnings and Precautions (5.7) ] Dermatologic Toxicities [see Warnings and Precautions (5.8) ] Hypothyroidism [see Warnings and Precautions (5.9) ] Growth Retardation in Children and Adolescents [see Warnings and Precautions (5.11) ] Tumor Lysis Syndrome [see Warnings and Precautions (5.12) ] Impairments Related to Driving and Using Machinery [see Warnings and Precautions (5.13) ] Renal Toxicity [see Warnings and Precautions (5.14) ] The most frequently reported adverse reactions (≥30%) are edema, nausea, vomiting, muscle cramps, musculoskeletal pain, diarrhea, rash, fatigue, and abdominal pain.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Shorla Oncology at 844-9-SHORLA or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Chronic Myeloid Leukemia The majority of imatinib-treated patients experienced adverse reactions at some time. Imatinib was discontinued due to drug-related adverse reactions in 2.4% of patients receiving imatinib in the randomized trial of newly diagnosed patients with Ph+ CML in chronic phase comparing imatinib versus IFN+Ara-C, and in 12.5% of patients receiving imatinib in the randomized trial of newly diagnosed patients with Ph+ CML in chronic phase comparing imatinib and nilotinib.
Imatinib was discontinued due to drug-related adverse reactions in 4% of patients in chronic phase after failure of interferon-alpha therapy, in 4% of patients in accelerated phase and in 5% of patients in blast crisis. The most frequently reported drug-related adverse reactions were edema, nausea and vomiting, muscle cramps, musculoskeletal pain, diarrhea and rash (Table 2 and Table 3 for newly diagnosed CML, Table 4 for other CML patients). Edema was most frequently periorbital or in lower limbs and was managed with diuretics, other supportive measures, or by reducing the dose of imatinib [see Dosage and Administration (2.13) ] .
The frequency of severe superficial edema was 1.5%-6%. A variety of adverse reactions represent local or general fluid retention, including pleural effusion, ascites, pulmonary edema, and rapid weight gain with or without superficial edema. These reactions appear to be dose related, were more common in the blast crisis and accelerated phase studies (where the dose was 600 mg/day), and are more common in the elderly.
These reactions were usually managed by interrupting imatinib treatment and using diuretics or other appropriate supportive care measures. These reactions may be serious or life threatening. Adverse reactions, regardless of relationship to study drug, that were reported in at least 10% of the imatinib-treated patients are shown in Tables 2, 3, and 4.
Table 2: Adverse Reactions Regardless of Relationship to Study Drug Reported in Newly Diagnosed CML Clinical Trial in the Imatinib Versus IFN+Ara-C Study (Greater Than or Equal to 10% of Imatinib-Treated Patients) All adverse reactions occurring in greater than or equal to 10% of imatinib-treated patients are listed regardless of suspected relationship to treatment. All Grades CTC Grades NCI Common Terminology Criteria for Adverse Events, version 3.0. 3/4 Preferred term Imatinib N = 551 (%) IFN+Ara-C N = 533 (%) Imatinib N =… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • CYP3A4 inducers: Avoid or increase imatinib dosage if unavoidable. ( 7.1 ) • CYP3A4 inhibitors: Use caution. Avoid grapefruit juice. ( 7.2 ) • CYP3A4 substrates: Use caution. Patients who require anticoagulation should receive other anticoagulants instead of warfarin. ( 7.3 ) • CYP2D6 substrates: Use caution. ( 7.4 )
7.1Agents Inducing CYP3A Metabolism Consider alternative therapeutic agents with less enzyme induction potential in patients when rifampin or other strong CYP3A4 inducers are indicated for concomitant use with Imkeldi. The dosage of Imkeldi should be increased if concomitant use with a strong CYP3A4 inducer is required [see Dosage and Administration (2.12) ] . Imatinib is a CYP3A substrate.
Concomitant use with a strong CYP3A inducer decreases imatinib exposure [see Clinical Pharmacology (12.3) ], which may reduce imatinib efficacy .
7.2Agents Inhibiting CYP3A Metabolism Caution is recommended when administering Imkeldi with strong CYP3A4 inhibitors. Grapefruit juice should be avoided. Imatinib is a CYP3A substrate. Concomitant use with a strong CYP3A inhibitor increases imatinib exposure [see Clinical Pharmacology (12.3) ] , which may increase the risk of Imkeldi adverse reactions.
7.3Interactions With Drugs Metabolized by CYP3A4 Use caution when administering Imkeldi with CYP3A4 substrates where minimal concentration changes may lead to serious adverse reactions. Because warfarin is metabolized by both CYP2C9 and CYP3A4, use other anti-coagulants instead of warfarin in patients receiving Imkeldi who require anticoagulation. Imatinib is a CYP3A inhibitor.
Imatinib increases exposure of CYP3A substrates [see Clinical Pharmacology (12.3) ] , which may increase the risk of adverse reactions related to these substrates.
7.4Interactions With Drugs Metabolized by CYP2D6 Use caution when administering Imkeldi with CYP2D6 substrates where minimal concentration changes may lead to serious adverse reactions. Imatinib is a CYP2D6 inhibitor. Imatinib increases exposure of CYP2D6 substrates [see Clinical Pharmacology (12.3) ] , which may increase the risk of adverse reactions related to these substrates.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed.( 8.2 )
8.1Pregnancy Risk Summary Imkeldi can cause fetal harm when administered to a pregnant woman based on human and animal data. There are no clinical studies regarding use of Imkeldi in pregnant women. There have been postmarket reports of spontaneous abortions and congenital anomalies from women who have been exposed to imatinib during pregnancy.
Reproductive studies in rats have demonstrated that imatinib mesylate induced teratogenicity and increased incidence of congenital abnormalities following prenatal exposure to imatinib mesylate at doses equal to the highest recommended human dose of 800 mg/day based on BSA. Advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is not known; however, in the U.S. general population, the estimated background risk of major birth defects of clinically recognized pregnancies is 2% to 4% and of miscarriage is 15% to 20%.
Data Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received oral doses of imatinib mesylate up to 100 mg/kg/day and 60 mg/kg/day, respectively, during the period of organogenesis. In rats, imatinib mesylate was teratogenic at 100 mg/kg/day (approximately equal to the maximum human dose of 800 mg/day based on BSA), the number of fetuses with encephalocele and exencephaly was higher than historical control values and these findings were associated with missing or underdeveloped cranial bones.
Lower mean fetal body weights were associated with retarded skeletal ossifications. In rabbits, at doses 1.5 times higher than the maximum human dose of 800 mg/day based on BSA, no effects on the reproductive parameters with respect to implantation sites, number of live fetuses, sex ratio or fetal weight were observed. The examinations of the fetuses did not reveal any drug related morphological changes.
In a pre- and postnatal development study in rats, pregnant rats received oral doses of imatinib mesylate during gestation (organogenesis) and lactation up to 45 mg/kg/day. Five animals developed a red vaginal discharge in the 45 mg/kg/day group on Days 14 or 15 of gestation, the significance of which is unknown since all females produced viable litters and none had increased post-implantation loss. Other maternal effects noted only at the dose of 45 mg/kg/day (approximately one-half the maximum human dose of 800 mg/day based on BSA) included an increased number of stillborn pups and pups dying between postpartum Days 0 and 4.
In the F1 offspring at this same dose level, mean body weights were reduced from birth until terminal sacrifice and the number of litters achieving criterion for preputial separation was slightly decreased. There were no other significant effects in developmental parameters or behavioral testing. F1 fertility was not affected but reproductive effects were noted at 45 mg/kg/day, including an increased number of resorptions and a decreased number of viable fetuses.
The no-observed-effect level (NOEL) for both maternal animals and the F1 generation was 15 mg/kg/day.
8.2Lactation Risk Summary Imatinib and its active metabolite are excreted into human milk. Because of the potential for serious adverse reactions in breastfed children from Imkeldi, advise a lactating woman not to breastfeed during treatment and for 1 month after the last dose. Human Data Based on data from 3 breastfeeding women taking imatinib, the milk:plasma ratio is about 0.5 for imatinib and about 0.9 for the active metabolite.
Considering the combined concentration of imatinib and active metabolite, a breastfed child could receive up to 10% of the maternal therapeutic dose based on body weight.
8.3Females and Males of Reproductive Potential Based on human postmarketing reports and animal studies, Imkeldi can cause fetal harm [see Use in Specific Populations (8.1) ] . Pregnancy Testing Verify pregnanc… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Imkeldi can cause fetal harm when administered to a pregnant woman based on human and animal data. There are no clinical studies regarding use of Imkeldi in pregnant women. There have been postmarket reports of spontaneous abortions and congenital anomalies from women who have been exposed to imatinib during pregnancy.
Reproductive studies in rats have demonstrated that imatinib mesylate induced teratogenicity and increased incidence of congenital abnormalities following prenatal exposure to imatinib mesylate at doses equal to the highest recommended human dose of 800 mg/day based on BSA. Advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is not known; however, in the U.S. general population, the estimated background risk of major birth defects of clinically recognized pregnancies is 2% to 4% and of miscarriage is 15% to 20%.
Data Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received oral doses of imatinib mesylate up to 100 mg/kg/day and 60 mg/kg/day, respectively, during the period of organogenesis. In rats, imatinib mesylate was teratogenic at 100 mg/kg/day (approximately equal to the maximum human dose of 800 mg/day based on BSA), the number of fetuses with encephalocele and exencephaly was higher than historical control values and these findings were associated with missing or underdeveloped cranial bones.
Lower mean fetal body weights were associated with retarded skeletal ossifications. In rabbits, at doses 1.5 times higher than the maximum human dose of 800 mg/day based on BSA, no effects on the reproductive parameters with respect to implantation sites, number of live fetuses, sex ratio or fetal weight were observed. The examinations of the fetuses did not reveal any drug related morphological changes.
In a pre- and postnatal development study in rats, pregnant rats received oral doses of imatinib mesylate during gestation (organogenesis) and lactation up to 45 mg/kg/day. Five animals developed a red vaginal discharge in the 45 mg/kg/day group on Days 14 or 15 of gestation, the significance of which is unknown since all females produced viable litters and none had increased post-implantation loss. Other maternal effects noted only at the dose of 45 mg/kg/day (approximately one-half the maximum human dose of 800 mg/day based on BSA) included an increased number of stillborn pups and pups dying between postpartum Days 0 and 4.
In the F1 offspring at this same dose level, mean body weights were reduced from birth until terminal sacrifice and the number of litters achieving criterion for preputial separation was slightly decreased. There were no other significant effects in developmental parameters or behavioral testing. F1 fertility was not affected but reproductive effects were noted at 45 mg/kg/day, including an increased number of resorptions and a decreased number of viable fetuses.
The no-observed-effect level (NOEL) for both maternal animals and the F1 generation was 15 mg/kg/day.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Imkeldi have been established in pediatric patients with newly diagnosed Ph+ chronic phase CML and Ph+ ALL [see Clinical Studies (14.2 , 14.4) ] . There are no data in pediatric patients under 1 year of age. The safety and efficacy of Imkeldi have not been established in pediatric patients for all other indications [see Indications and Usage (1) ].
🧓 Geriatric Use ▾
8.5Geriatric Use In the CML clinical studies, approximately 20% of patients were older than 65 years. In the study of patients with newly diagnosed CML, 6% of patients were older than 65 years. The frequency of edema was higher in patients older than 65 years as compared to younger patients; no other difference in the safety profile was observed [see Warnings and Precautions (5.1) ] .
The efficacy of imatinib was similar in older and younger patients. In the unresectable or metastatic GIST study, 16% of patients were older than 65 years. No obvious differences in the safety or efficacy profile were noted in patients older than 65 years as compared to younger patients, but the small number of patients does not allow a formal analysis.
In the adjuvant GIST study, 221 patients (31%) were older than 65 years. No difference was observed in the safety profile in patients older than 65 years as compared to younger patients, with the exception of a higher frequency of edema. The efficacy of imatinib was similar in patients older than 65 years and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE Experience with doses greater than 800 mg is limited. Isolated cases of imatinib overdose have been reported. In the event of overdosage, observe the patient and give appropriate supportive treatment.
Adult Overdose 1,200 to 1,600 mg (duration varying between 1 to 10 days): Nausea, vomiting, diarrhea, rash erythema, edema, swelling, fatigue, muscle spasms, thrombocytopenia, pancytopenia, abdominal pain, headache, decreased appetite. 1,800 to 3,200 mg (as high as 3,200 mg daily for 6 days): Weakness, myalgia, increased CPK, increased bilirubin, GI pain. 6,400 mg (single dose): One case in the literature reported one patient who experienced nausea, vomiting, abdominal pain, pyrexia, facial swelling, neutrophil count decreased, increase transaminases.
8 to 10 g (single dose): Vomiting and GI pain have been reported. A patient with myeloid blast crisis experienced Grade 1 elevations of serum creatinine, Grade 2 ascites and elevated liver transaminase levels, and Grade 3 elevations of bilirubin after inadvertently taking 1,200 mg of imatinib daily for 6 days. Therapy was temporarily interrupted and complete reversal of all abnormalities occurred within 1 week.
Treatment was resumed at a dose of 400 mg daily without recurrence of adverse reactions. Another patient developed severe muscle cramps after taking 1,600 mg of imatinib daily for 6 days. Complete resolution of muscle cramps occurred following interruption of therapy and treatment was subsequently resumed.
Another patient that was prescribed 400 mg daily, took 800 mg of imatinib on Day 1 and 1,200 mg on Day 2. Therapy was interrupted, no adverse reactions occurred and the patient resumed therapy. Pediatric Overdose One 3 year old male exposed to a single dose of 400 mg experienced vomiting, diarrhea, and anorexia; and another 3 year old male exposed to a single dose of 980 mg experienced decreased white blood cell (WBC) count and diarrhea.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Imatinib mesylate is a protein-tyrosine kinase inhibitor that inhibits the BCR-ABL tyrosine kinase, the constitutive abnormal tyrosine kinase created by the Philadelphia chromosome abnormality in CML. Imatinib inhibits proliferation and induces apoptosis in BCR-ABL positive cell lines as well as fresh leukemic cells from Philadelphia chromosome positive chronic myeloid leukemia. Imatinib inhibits colony formation in assays using ex vivo peripheral blood and bone marrow samples from CML patients.
In vivo, imatinib inhibits tumor growth of BCR-ABL transfected murine myeloid cells as well as BCR-ABL positive leukemia lines derived from CML patients in blast crisis. Imatinib is also an inhibitor of the receptor tyrosine kinases for platelet-derived growth factor (PDGF) and stem cell factor (SCF), c-Kit, and inhibits PDGF- and SCF-mediated cellular events. In vitro, imatinib inhibits proliferation and induces apoptosis in GIST cells, which express an activating c-Kit mutation.
12.2Pharmacodynamics Imatinib exposure-response relationships and the time course of pharmacodynamic response are unknown.
12.3Pharmacokinetics The pharmacokinetics of imatinib have been evaluated in studies in healthy subjects and in population pharmacokinetic studies in over 900 patients. No clinically significant difference in imatinib pharmacokinetics were observed between CML and GIST patients. Imatinib AUC increases proportionally with increasing doses ranging from 25 mg to 1000 mg (0.06 to 1.25 times the approved recommended dosage of 400 mg).
Imatinib accumulation is 1.5- to 2.5- fold at steady state when imatinib is dosed once daily. Absorption Imatinib mean absolute bioavailability is 98%. Imatinib is well absorbed after oral administration with maximum concentration (C max ) achieved within 2-4 hours post-dose.
Distribution Imatinib and the N-demethylated metabolite (CGP74588) plasma protein binding is approximately 95% in vitro, mostly to albumin and α1-acid glycoprotein. Elimination The elimination half-life is approximately 18 hours for imatinib and 40 hours for the N-demethyl derivative metabolite (CGP74588), following oral administration in healthy volunteers. Typical imatinib clearance in a 50-year-old patient weighing 50 kg is expected to be 8 L/h, while for a 50-year-old patient weighing 100 kg the clearance will increase to 14 L/h.
The inter-patient variability of 40% in clearance does not warrant initial dose adjustment based on body weight and/or age but indicates the need for close monitoring for treatment-related toxicity. Metabolism CYP3A4 is the major enzyme responsible for metabolism of imatinib. Other cytochrome P450 enzymes, such as CYP1A2, CYP2D6, CYP2C9, and CYP2C19, play a minor role in its metabolism.
The main circulating active metabolite in humans is the N-demethylated piperazine derivative (CGP74588), formed predominantly by CYP3A4. It shows in vitro potency similar to the parent imatinib. The plasma AUC for this metabolite is about 15% of the AUC for imatinib.
Excretion Imatinib elimination is predominately in the feces, mostly as metabolites. Following an oral radio-labeled dose of imatinib, approximately 81% of the dose was eliminated within 7 days, in feces (68% of dose) and urine (13% of dose). Unchanged imatinib accounted for 25% of the dose (5% urine, 20% feces), the remainder being metabolites.
Specific Populations Hepatic Impairment The effect of hepatic impairment on the pharmacokinetics of both imatinib and its major metabolite, CGP74588, was assessed in 84 patients with cancer and varying degrees of hepatic impairment at imatinib doses ranging from 100 mg to 800 mg. Exposure to both imatinib and CGP74588 was comparable between each of the mildly (total bilirubin ≤ upper limit of normal [ULN] and aspartate aminotransferase [AST] > ULN, or total bilirubin ˃1 to 1.5 times ULN) and moderately (total bilirubin ˃ 1.5 to 3 times ULN and any value for AST) hepatically-… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Imatinib mesylate is a protein-tyrosine kinase inhibitor that inhibits the BCR-ABL tyrosine kinase, the constitutive abnormal tyrosine kinase created by the Philadelphia chromosome abnormality in CML. Imatinib inhibits proliferation and induces apoptosis in BCR-ABL positive cell lines as well as fresh leukemic cells from Philadelphia chromosome positive chronic myeloid leukemia. Imatinib inhibits colony formation in assays using ex vivo peripheral blood and bone marrow samples from CML patients.
In vivo, imatinib inhibits tumor growth of BCR-ABL transfected murine myeloid cells as well as BCR-ABL positive leukemia lines derived from CML patients in blast crisis. Imatinib is also an inhibitor of the receptor tyrosine kinases for platelet-derived growth factor (PDGF) and stem cell factor (SCF), c-Kit, and inhibits PDGF- and SCF-mediated cellular events. In vitro, imatinib inhibits proliferation and induces apoptosis in GIST cells, which express an activating c-Kit mutation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Imkeldi oral solution 80 mg/mL is supplied as 140 mL of clear yellow to brownish yellow colored solution with a strawberry flavor in an amber PET bottle with a child resistant tamper-evident closure. NDC 81927-201-01 Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F) [see USP Controlled Room Temperature]. Store and dispense in original container only.
Any open bottle should be discarded after 30 days. Imkeldi is a hazardous drug. Follow applicable special handling and disposal procedures 1 .
📋 Description ▾
11 DESCRIPTION Imkeldi oral solution contains imatinib mesylate, a kinase inhibitor. Imatinib mesylate is designated chemically as 4-[(4-Methyl-1-piperazinyl)methyl]-N-[4-methyl-3-[[4-(3-pyridinyl)-2- pyrimidinyl]amino]-phenyl]benzamide methanesulfonate and its structural formula is: The molecular formula is C 29 H 31 N 7 O · CH 4 SO 3 and its molecular weight is 589.7 g/mol. Imatinib mesylate is soluble in aqueous buffers less than or equal to pH 5.5 but is very slightly soluble to insoluble in neutral/alkaline aqueous buffers.
In non-aqueous solvents, the drug substance is freely soluble to very slightly soluble in dimethyl sulfoxide, methanol, and ethanol, but is insoluble in n-octanol, acetone, and acetonitrile. Imatinib oral solution is a clear, yellow to brownish yellow colored solution. Each mL of Imkeldi contains the equivalent of 80 mg imatinib present as 95.57 mg imatinib mesylate.
Inactive Ingredients: acesulfame potassium, citric acid monohydrate, glycerine, liquid maltitol, purified water, sodium benzoate, strawberry flavor (artificial flavors, lactic acid, triacetin). structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Instructions for Use ). Fluid Retention and Edema Inform patients of the possibility of developing edema and fluid retention. Advise patients to contact their health care provider if unexpected rapid weight gain occurs [see Warnings and Precautions (5.1) ].
Hepatotoxicity Inform patients of the possibility of developing liver function abnormalities and serious hepatic toxicity. Advise patients to immediately contact their health care provider if signs of liver failure occur, including jaundice, anorexia, bleeding, or bruising [see Warnings and Precautions (5.4) ]. Embryo-Fetal Toxicity Advise pregnant women and females of reproductive potential of the potential risk to a fetus.
Advise females of reproductive potential to inform their healthcare provider if they are pregnant or become pregnant [see Warnings and Precautions (5.10) and Use in Specific Populations (8.1) ] . Advise females of reproductive potential to use effective contraception during treatment with Imkeldi and for 14 days after the last dose [see Use in Specific Populations (8.3) ] . Lactation Advise women not to breastfeed during treatment with Imkeldi and for 1 month after the last dose [see Use in Specific Populations (8.2) ] .
Drug Interactions Imkeldi and certain other medicines, such as warfarin, erythromycin, and phenytoin, including over-the-counter medications, such as herbal products, can interact with each other. Advise patients to tell their doctor if they are taking or plan to take iron supplements. Avoid grapefruit juice and other foods known to inhibit CYP3A4 while taking Imkeldi [see Drug Interactions (7) ] .
Pediatric Advise patients that growth retardation has been reported in children and pre-adolescents receiving imatinib. The long term effects of prolonged treatment with Imkeldi on growth in children are unknown. Therefore, closely monitor growth in children under Imkeldi treatment [see Warnings and Precautions (5.11) ].
Driving and Using Machines Advise patients that they may experience side effects, such as dizziness, blurred vision, or somnolence during treatment with Imkeldi. Therefore, caution patients about driving a car or operating machinery [see Warnings and Precautions (5.13) ]. Accurate Measuring Device and Dosing and Administration Advise patients and caregivers to measure Imkeldi with an accurate milliliter measuring device.
A household teaspoon is not an accurate measuring device. Advise patients and caregivers to ask their pharmacist to recommend an appropriate press-in bottle adapter and oral dispensing syringe and for instructions for measuring the correct dose [see Warnings and Precautions (5.15) ] . Advise patients to take Imkeldi with a meal and a large glass of water.
Advise patients that, if a dose is missed, they should wait until the next scheduled dose and not take two doses at the same time. Advise patients to take Imkeldi exactly as prescribed, not to change their dose or to stop taking Imkeldi unless they are told to do so by their doctor [see Dosage and Administration (2.1) ] . Manufactured for: Shorla Oncology Inc.
Cambridge, MA 02142, USA Patent Information: U.S. Patent: 11,957,681 Version: IMAPI007
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of imatinib have been evaluated in studies in healthy subjects and in population pharmacokinetic studies in over 900 patients. No clinically significant difference in imatinib pharmacokinetics were observed between CML and GIST patients. Imatinib AUC increases proportionally with increasing doses ranging from 25 mg to 1000 mg (0.06 to 1.25 times the approved recommended dosage of 400 mg).
Imatinib accumulation is 1.5- to 2.5- fold at steady state when imatinib is dosed once daily. Absorption Imatinib mean absolute bioavailability is 98%. Imatinib is well absorbed after oral administration with maximum concentration (C max ) achieved within 2-4 hours post-dose.
Distribution Imatinib and the N-demethylated metabolite (CGP74588) plasma protein binding is approximately 95% in vitro, mostly to albumin and α1-acid glycoprotein. Elimination The elimination half-life is approximately 18 hours for imatinib and 40 hours for the N-demethyl derivative metabolite (CGP74588), following oral administration in healthy volunteers. Typical imatinib clearance in a 50-year-old patient weighing 50 kg is expected to be 8 L/h, while for a 50-year-old patient weighing 100 kg the clearance will increase to 14 L/h.
The inter-patient variability of 40% in clearance does not warrant initial dose adjustment based on body weight and/or age but indicates the need for close monitoring for treatment-related toxicity. Metabolism CYP3A4 is the major enzyme responsible for metabolism of imatinib. Other cytochrome P450 enzymes, such as CYP1A2, CYP2D6, CYP2C9, and CYP2C19, play a minor role in its metabolism.
The main circulating active metabolite in humans is the N-demethylated piperazine derivative (CGP74588), formed predominantly by CYP3A4. It shows in vitro potency similar to the parent imatinib. The plasma AUC for this metabolite is about 15% of the AUC for imatinib.
Excretion Imatinib elimination is predominately in the feces, mostly as metabolites. Following an oral radio-labeled dose of imatinib, approximately 81% of the dose was eliminated within 7 days, in feces (68% of dose) and urine (13% of dose). Unchanged imatinib accounted for 25% of the dose (5% urine, 20% feces), the remainder being metabolites.
Specific Populations Hepatic Impairment The effect of hepatic impairment on the pharmacokinetics of both imatinib and its major metabolite, CGP74588, was assessed in 84 patients with cancer and varying degrees of hepatic impairment at imatinib doses ranging from 100 mg to 800 mg. Exposure to both imatinib and CGP74588 was comparable between each of the mildly (total bilirubin ≤ upper limit of normal [ULN] and aspartate aminotransferase [AST] > ULN, or total bilirubin ˃1 to 1.5 times ULN) and moderately (total bilirubin ˃ 1.5 to 3 times ULN and any value for AST) hepatically-impaired groups and the normal group.
Patients with severe hepatic impairment (Total bilirubin ˃ 3 to 10 times ULN and any value for AST) tend to have higher exposure to both imatinib and CGP74588 than patients with normal hepatic function. At steady state, the mean C max /dose and AUC/dose for imatinib increased by about 63% and 45%, respectively, in patients with severe hepatic impairment compared to patients with normal hepatic function. The mean C max /dose and AUC/dose for CGP74588 increased by about 56% and 55%, respectively, in patients with severe hepatic impairment compared to patients with normal hepatic function.
Renal Impairment The effect of renal impairment on the pharmacokinetics of imatinib was assessed in 59 cancer patients with varying degrees of renal impairment at single and steady state imatinib doses ranging from 100 to 800 mg/day. The mean exposure to imatinib (AUC/dose) in patients with mild (CLcr = 40-59 mL/min) and moderate (CLcr = 20-39 mL/min) renal impairment increased 1.5- to 2-fold compared to patients with normal renal function. The AUCs did not increase for doses greater than 600 mg in patients with mild renal… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Imatinib exposure-response relationships and the time course of pharmacodynamic response are unknown.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Chronic Myeloid Leukemia Chronic Phase, Newly Diagnosed: An open-label, multicenter, international randomized Phase 3 study (imatinib versus IFN+Ara-C) has been conducted in patients with newly diagnosed Philadelphia chromosome positive (Ph+) chronic myeloid leukemia (CML) in chronic phase. This study compared treatment with either single-agent imatinib or a combination of interferon-alpha (IFN) plus cytarabine (Ara-C). Patients were allowed to cross over to the alternative treatment arm if they failed to show a complete hematologic response (CHR) at 6 months, a major cytogenetic response (MCyR) at 12 months, or if they lost a CHR or MCyR.
Patients with increasing WBC or severe intolerance to treatment were also allowed to cross over to the alternative treatment arm with the permission of the study monitoring committee (SMC). In the imatinib arm, patients were treated initially with 400 mg daily. Dose escalations were allowed from 400 mg daily to 600 mg daily, then from 600 mg daily to 800 mg daily.
In the IFN arm, patients were treated with a target dose of IFN of 5 MIU/m 2 /day subcutaneously in combination with subcutaneous Ara-C 20 mg/m 2 /day for 10 days/month. A total of 1106 patients were randomized from 177 centers in 16 countries, 553 to each arm. Baseline characteristics were well balanced between the two arms.
Median age was 51 years (range, 18 to 70 years), with 21.9% of patients greater than or equal to 60 years of age. There were 59% males and 41% females; 89.9% White and 4.7% Black patients. At the cut-off for this analysis (7 years after last patient had been recruited), the median duration of first-line treatment was 82 and 8 months in the imatinib and IFN arm, respectively.
The median duration of second-line treatment with imatinib was 64 months. Sixty percent of patients randomized to imatinib are still receiving first-line treatment. In these patients, the average dose of imatinib was 403 mg ± 57 mg.
Overall, in patients receiving first line imatinib, the average daily dose delivered was 406 mg ± 76 mg. Due to discontinuations and cross-overs, only 2% of patients randomized to IFN were still on first-line treatment. In the IFN arm, withdrawal of consent (14%) was the most frequent reason for discontinuation of first-line therapy, and the most frequent reason for cross over to the imatinib arm was severe intolerance to treatment (26%) and progression (14%).
The primary efficacy endpoint of the study was progression-free survival (PFS). Progression was defined as any of the following events: progression to accelerated phase or blast crisis (AP/BC), death, loss of CHR or MCyR, or in patients not achieving a CHR an increasing WBC despite appropriate therapeutic management. The protocol specified that the progression analysis would compare the intent to treat (ITT) population: patients randomized to receive imatinib were compared with patients randomized to receive IFN.
Patients that crossed over prior to progression were not censored at the time of cross-over, and events that occurred in these patients following cross-over were attributed to the original randomized treatment. The estimated rate of progression-free survival at 84 months in the ITT population was 81.2% [95% CI: 78, 85] in the imatinib arm and 60.6% [56, 65] in the IFN arm (p less than 0.0001, log-rank test), (Figure 1). With 7 years follow up there were 93 (16.8%) progression events in the imatinib arm: 37 (6.7%) progression to AP/BC, 31 (5.6%) loss of MCyR, 15 (2.7%) loss of CHR or increase in WBC and 10 (1.8%) CML unrelated deaths.
In contrast, there were 165 (29.8%) events in the IFN+Ara-C arm of which 130 occurred during first-line treatment with IFN-Ara-C. The estimated rate of patients free of progression to accelerated phase (AP) or blast crisis (BC) at 84 months was 92.5% [90, 95] in the imatinib arm compared to the 85.1%, [82, 89] (p less than or equal to 0.001) in the IFN arm, (Figure 2). The annual rates of any… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In the 2-year rat carcinogenicity study administration of imatinib at 15, 30, and 60 mg/kg/day resulted in a statistically significant reduction in the longevity of males at 60 mg/kg/day and females at greater than or equal to 30 mg/kg/day. Target organs for neoplastic changes were the kidneys (renal tubule and renal pelvis), urinary bladder, urethra, preputial and clitoral gland, small intestine, parathyroid glands, adrenal glands and non-glandular stomach. Neoplastic lesions were not seen at: 30 mg/kg/day for the kidneys, urinary bladder, urethra, small intestine, parathyroid glands, adrenal glands and non-glandular stomach, and 15 mg/kg/day for the preputial and clitoral gland.
The papilloma/carcinoma of the preputial/clitoral gland were noted at 30 and 60 mg/kg/day, representing approximately 0.5 to 4 or 0.3 to 2.4 times the human daily exposure (based on AUC) at 400 mg/day or 800 mg/day, respectively, and 0.4 to 3.0 times the daily exposure in children (based on AUC) at 340 mg/m 2 . The renal tubule adenoma/carcinoma, renal pelvis transitional cell neoplasms, the urinary bladder and urethra transitional cell papillomas, the small intestine adenocarcinomas, the parathyroid glands adenomas, the benign and malignant medullary tumors of the adrenal glands and the non-glandular stomach papillomas/carcinomas were noted at 60 mg/kg/day.
The relevance of these findings in the rat carcinogenicity study for humans is not known. Positive genotoxic effects were obtained for imatinib in an in vitro mammalian cell assay (Chinese hamster ovary) for clastogenicity (chromosome aberrations) in the presence of metabolic activation. Two intermediates of the manufacturing process, which are also present in the final product, are positive for mutagenesis in the Ames assay.
One of these intermediates was also positive in the mouse lymphoma assay. Imatinib was not genotoxic when tested in an in vitro bacterial cell assay (Ames test), an in vitro mammalian cell assay (mouse lymphoma) and an in vivo rat micronucleus assay. In a study of fertility, male rats were dosed for 70 days prior to mating and female rats were dosed 14 days prior to mating and through to gestational Day 6.
Testicular and epididymal weights and percent motile sperm were decreased at 60 mg/kg, approximately three-fourths the maximum clinical dose of 800 mg/day based on BSA. This was not seen at doses less than or equal to 20 mg/kg (one-fourth the maximum human dose of 800 mg). The fertility of male and female rats was not affected.
Fertility was not affected in the preclinical fertility and early embryonic development study although lower testes and epididymal weights as well as a reduced number of motile sperm were observed in the high dose males rats. In the preclinical pre- and postnatal study in rats, fertility in the first generation offspring was also not affected by imatinib mesylate.
13.2Animal Toxicology and/or Pharmacology Toxicities from Long-Term Use It is important to consider potential toxicities suggested by animal studies, specifically, liver, kidney, and cardiac toxicity and immunosuppression. Severe liver toxicity was observed in dogs treated for 2 weeks, with elevated liver enzymes, hepatocellular necrosis, bile duct necrosis, and bile duct hyperplasia. Renal toxicity was observed in monkeys treated for 2 weeks, with focal mineralization and dilation of the renal tubules and tubular nephrosis.
Increased blood urea nitrogen (BUN) and creatinine were observed in several of these animals. An increased rate of opportunistic infections was observed with chronic imatinib treatment in laboratory animal studies. In a 39 week monkey study, treatment with imatinib resulted in worsening of normally suppressed malarial infections in these animals.
Lymphopenia was observed in animals (as in humans). Additional long-term toxicities were identified in a 2-year rat study. Histopathological… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In the 2-year rat carcinogenicity study administration of imatinib at 15, 30, and 60 mg/kg/day resulted in a statistically significant reduction in the longevity of males at 60 mg/kg/day and females at greater than or equal to 30 mg/kg/day. Target organs for neoplastic changes were the kidneys (renal tubule and renal pelvis), urinary bladder, urethra, preputial and clitoral gland, small intestine, parathyroid glands, adrenal glands and non-glandular stomach. Neoplastic lesions were not seen at: 30 mg/kg/day for the kidneys, urinary bladder, urethra, small intestine, parathyroid glands, adrenal glands and non-glandular stomach, and 15 mg/kg/day for the preputial and clitoral gland.
The papilloma/carcinoma of the preputial/clitoral gland were noted at 30 and 60 mg/kg/day, representing approximately 0.5 to 4 or 0.3 to 2.4 times the human daily exposure (based on AUC) at 400 mg/day or 800 mg/day, respectively, and 0.4 to 3.0 times the daily exposure in children (based on AUC) at 340 mg/m 2 . The renal tubule adenoma/carcinoma, renal pelvis transitional cell neoplasms, the urinary bladder and urethra transitional cell papillomas, the small intestine adenocarcinomas, the parathyroid glands adenomas, the benign and malignant medullary tumors of the adrenal glands and the non-glandular stomach papillomas/carcinomas were noted at 60 mg/kg/day.
The relevance of these findings in the rat carcinogenicity study for humans is not known. Positive genotoxic effects were obtained for imatinib in an in vitro mammalian cell assay (Chinese hamster ovary) for clastogenicity (chromosome aberrations) in the presence of metabolic activation. Two intermediates of the manufacturing process, which are also present in the final product, are positive for mutagenesis in the Ames assay.
One of these intermediates was also positive in the mouse lymphoma assay. Imatinib was not genotoxic when tested in an in vitro bacterial cell assay (Ames test), an in vitro mammalian cell assay (mouse lymphoma) and an in vivo rat micronucleus assay. In a study of fertility, male rats were dosed for 70 days prior to mating and female rats were dosed 14 days prior to mating and through to gestational Day 6.
Testicular and epididymal weights and percent motile sperm were decreased at 60 mg/kg, approximately three-fourths the maximum clinical dose of 800 mg/day based on BSA. This was not seen at doses less than or equal to 20 mg/kg (one-fourth the maximum human dose of 800 mg). The fertility of male and female rats was not affected.
Fertility was not affected in the preclinical fertility and early embryonic development study although lower testes and epididymal weights as well as a reduced number of motile sperm were observed in the high dose males rats. In the preclinical pre- and postnatal study in rats, fertility in the first generation offspring was also not affected by imatinib mesylate.
📚 References ▾
15 REFERENCES OSHA Hazardous Drugs. OSHA. [Accessed from http://www.osha.gov/SLTC/hazardousdrugs/index.html]
📄 Patient Package Insert ▾
INSTRUCTIONS FOR USE IMKELDI (IM-KELL-DEE) (imatinib) oral solution 80 mg/mL This Instructions for Use contains information on how to take (or give) IMKELDI. Read this Instructions for Use before you (or your child) start using IMKELDI oral solution and each time you get a refill. There may be new information.
This important information does not take the place of talking to your (or your child’s) healthcare provider about your (or your child’s) medical condition or treatment. Supplies needed (Figure A) IMKELDI bottle with child resistant cap Oral dispensing syringe (not included with IMKELDI) Bottle adapter (not included with IMKELDI) Disposable gloves (not included with IMKELDI) Figure A Important Information You Need to Know Before Taking IMKELDI For oral use only (taken by mouth). Always use the oral dispensing syringe and bottle adapter provided by your pharmacist.
If you did not receive the oral dispensing syringe and bottle adapter, contact your pharmacist. Ask your pharmacist to show you how to measure your prescribed doses. Take IMKELDI exactly as prescribed by your healthcare provider.
Do not stop taking IMKELDI without first speaking with your healthcare provider. All doses of IMKELDI should be taken with a meal and a large glass of water. Taking IMKELDI with certain medicines and grapefruit juice may affect each other.
Talk to your healthcare provider about all the medicines you take. If you miss a dose of IMKELDI, do not take the missed dose. Take your next dose at your regular time.
IMKELDI is a hazardous drug. Do not prepare, withdraw, take, or give IMKELDI without wearing disposable gloves. IMKELDI may cause dizziness, blurred vision, or sleepiness during treatment.
Preparing a new bottle of IMKELDI before first time use 1. Wash hands thoroughly with soap and water ( Figure B ). Figure B 2.
Wear disposable gloves while preparing, withdrawing, taking, or giving IMKELDI to avoid direct contact with the medicine. 3. Check the expiration date on the bottle.
Do not use IMKELDI if the expiration date on the bottle has passed. Contact your healthcare provider or pharmacist. 4.
Remove the child-resistant bottle cap by pushing it down firmly and twisting it counter-clockwise (to the left) ( Figure C ). Do not throw away the child-resistant bottle cap. Figure C 5.
Place the open bottle upright on a clean flat surface. Hold the bottle firmly and push the ribbed end of the bottle adapter firmly into the neck of the bottle as far as it will go ( Figure D ). Do not remove the bottle adapter from the bottle after it is inserted.
Figure D 6. Put the child-resistant cap back on the bottle by turning it clockwise (to the right) ( Figure E ). Make sure that the child-resistant cap is tightly closed.
Figure E 7. Write the date of first opening on the bottle label. Preparing and withdrawing a dose of IMKELDI 8.
Repeat Step 1 to Step 4 above. 9. Place the IMKELDI bottle on a clean flat surface.
10. Check your prescription to find out the number of mL you are supposed to take. Find the number line on the oral dispensing syringe barrel that matches your dose.
11. Push the plunger of the oral dispensing syringe all the way up towards the tip of the oral dispensing syringe to remove air ( Figure F ). Figure F 12.
While keeping the bottle in an upright position, insert the tip of the oral dispensing syringe into the opening of the bottle adapter and push down gently ( Figure G ). Do not force the oral dispensing syringe tip into the bottler adapter opening. Figure G 13.
Hold the oral dispensing syringe tip firmly in the bottle and carefully turn the bottle upside down ( Figure H ). Slowly pull down the plunger of the oral dispensing syringe until the widest part of the oral dispensing syringe plunger lines up with the prescribed number of mL dose ( Figure I ). Figure H Figure I 14.
Leave the oral dispensing syringe tip in the bottle adapter. Check the oral dispensing syringe for air ( Figure J ). If you see air bubbles, push the plunger a… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
Principal Display Panel NDC 81927-201-01 Rx Only Imkeldi (imatinib) Oral Solution 80 mg/mL For Oral Use Only 140 mL Label Carton label carton
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |