
Folic Acid Gummies Ingredients & Drug Interactions
What is this page for?
First and foremost: checking Folic Acid Gummies against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Folic Acid Gummies is a dietary supplement by Nature's Nutrition with 2 active ingredients. Its ingredients are commonly taken for preventing neural tube birth defects, treating or preventing folate deficiency, supporting pregnancy health.Based on those ingredients, 245 medications have a known interaction with it, the most serious rated moderate. The ingredients most likely to interact are Sodium, Folic Acid. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Folic Acid Gummies by Nature's Nutrition
Ask about any prescription or over-the-counter medication and we check it for interactions with Folic Acid Gummies by Nature's Nutrition — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Folic Acid Gummies by Nature's Nutrition
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
Nature's Nutrition Folic Acid Gummies contain 2 active ingredients: folic acid, a B vitamin that helps prevent folate deficiency and may support other conditions, and sodium, an essential electrolyte. The rest of the gummy is made up of inactive ingredients—glucose syrup, sugar, pectin, natural flavors, and coloring agents like beta-carotene and fruit juice concentrates—that make the supplement taste and look appealing.
Does it work?
Strong evidence
Folic acid in this product is effective for preventing and treating folate deficiency, and it's likely effective at reducing methotrexate toxicity and preventing neural tube birth defects during pregnancy. The evidence also suggests it may possibly help with depression, gingival hyperplasia (a gum condition caused by certain seizure drugs), and cognitive impairment.
Sodium has no established role in treating the conditions this product is designed for; it's present as an ingredient but not for therapeutic purposes. The effectiveness ratings for sodium listed in the data (cystic fibrosis, heart failure) do not apply to this gummy product.
How safe is it?
Well-documented data
Folic acid is generally well tolerated at recommended doses. It's considered safe during pregnancy at standard prenatal doses to help prevent birth defects, and safe while breastfeeding at normal recommended doses.
However, at high doses (15 mg daily and above), it can cause bitter taste, confusion, sleep problems, irritability, and nausea. Very rare serious effects with long-term use include seizures and cancer risk.
Large doses can also worsen nerve damage (neuropathy) in people who are low in vitamin B12, and folic acid can mask the symptoms of pernicious anemia, a serious condition. Do not self-treat suspected anemia.
Sodium is well tolerated in normal dietary amounts. However, this product contains supplemental sodium, and high intake is linked to high blood pressure, heart strain, and kidney disease.
Avoid sodium supplements or very high intake without checking with your doctor first. Breastfeeding safety data for supplemental sodium is insufficient—talk with your pharmacist or doctor if you're nursing.
Meds to double-check
Moderate interaction found
Before taking this product, check with your pharmacist if you take seizure medications (phenobarbital, phenytoin, primidone), cancer drugs (methotrexate, capecitabine, 5-fluorouracil), blood pressure medications, lithium, corticosteroids, pyrimethamine, didanosine, sodium phosphates, or tolvaptan. All of these have Moderate severity interactions with one or both active ingredients.
The bottom line
Scorecard at a glanceFully disclosed formula with clinical evidence supporting its stated purpose. Moderate medication interactions have been identified, and safety information is well characterized.
This gummy works well for folate deficiency and may help prevent birth defects in pregnancy. If you take seizure medications, blood pressure drugs, lithium, or cancer drugs, check with your pharmacist first—folic acid and sodium can interfere with these.
Avoid high-dose folic acid if you're deficient in vitamin B12, and don't use it to treat suspected anemia without a diagnosis.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 2 of 2 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Mar 25, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Folic Acid Gummies, straight from the product label.
| Brand | Nature's Nutrition |
|---|---|
| Net contents | 120 Gummy(ies) |
| Market status | On market |
| Date entered into DSLD | Mar 25, 2025 |
| DSLD ID | 327922 |
| Product type | Single Vitamin And Mineral |
| Supplement form | Gummy Or Jelly |
| Dietary claims / uses | Nutrient, All Other, Structure/Function |
| Intended target group(s) | Pregnant Women, Lactating |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
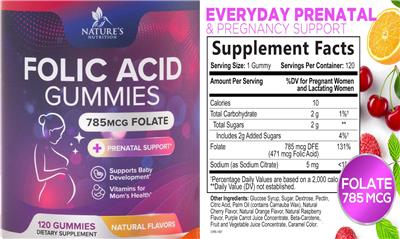
Supplement Facts
The label details for Folic Acid Gummies by Nature's Nutrition, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Calories | 10 Calorie(s) | -- |
| Total Carbohydrates | 2 Gram(s) | 1% |
| Folic Acid | 471 mcg | -- |
| Added Sugars | 2 Gram(s) | 4% |
| Total Sugars | 2 Gram(s) | -- |
| Folate | 785 mcg DFE | 131% |
| Sodium | 5 mg | 1% |
Other ingredients: Glucose Syrup, Sugar, Dextrose, Pectin, Citric Acid, Palm Oil, Cherry Flavor, Natural, Orange Flavor, Natural, Raspberry Flavor, Natural, Purple Carrot juice concentrate, Beta-Carotene, Fruit and Vegetable Juice concentrate, Caramel color
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formula
785mcg folate Vitamins for mom's health
Everyday prenatal & pregnancy support
Formulation
Prenatal support Supports baby development Everyday prenatal & pregnancy support
Natural flavors
FDA Statement of Identity
Dietary Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Folic Acid Gummies by Nature's Nutrition label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Folic Acid Gummies by Nature's Nutrition
These are the 2 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Gummie(s) Dosage formGummy Or Jelly Servings per container120 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Folate
Sodium
Interacts with205 drugs
Sodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets g...
Sodium monograph & interactionsOther (inactive) ingredients: Glucose Syrup, Sugar, Dextrose, Pectin, Citric Acid, Palm Oil, Cherry Flavor, Natural, Orange Flavor, Natural, Raspberry Flavor, Natural, Purple Carrot juice concentrate, Beta-Carotene, Fruit and Vegetable Juice concentrate, Caramel color. These complete the product’s ingredient list but are not active constituents.
Folic Acid Gummies by Nature's Nutrition Drug Interactions
HelloPharmacist Interaction Report
Nature's Nutrition Folic Acid Gummies contain two active ingredients—folic acid and sodium—and together they interact with a substantial number of medications.
The most serious concern is folic acid's effect on seizure medications: it can reverse or weaken the action of phenobarbital, phenytoin, and primidone, increasing seizure risk. This is a Moderate severity interaction that requires close monitoring.
Read the full breakdown — every affected drug type, severity by severity
Folic acid also moderately interacts with several cancer drugs. It may reduce the effectiveness of methotrexate as a cancer treatment, and high doses could increase toxicity from capecitabine or 5-fluorouracil.
Additionally, folic acid can antagonize the antiparasitic effects of pyrimethamine.
Sodium, the second active ingredient, moderately interacts with blood pressure medications, corticosteroids (a class of anti-inflammatory drugs), lithium, and several other drugs—chiefly through sodium retention or electrolyte imbalance. High sodium intake can reduce how well antihypertensive drugs work or cause dangerous sodium buildup with lithium, didanosine, or tolvaptan.
Altogether, these interactions span 243 individual medications. Use the search tool on this page to check your exact prescriptions before starting.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Folic Acid Gummies?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Folic Acid Gummies interact with 245 drugs. Click any drug to see the details.
2 of the 2 ingredients in Folic Acid Gummies interact with drugs. Each result below shows which ingredient is responsible. Sodium Folic Acid
AcebutololRhotral, Sectral
How Acebutolol interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acebutolol interactionAcetazolamideAk-Zol, Diamox
How Acetazolamide interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acetazolamide interactionAliskirenTekturna
How Aliskiren interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Aliskiren interactionAmbrisentanLetairis, Volibris
How Ambrisentan interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Ambrisentan interactionAmilorideAmilamont, Midamor
How Amiloride interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Amiloride interactionAmiloride, HydrochlorothiazideAmil-Co, Amilzide, Moduret 25, Moduretic
How Amiloride, Hydrochlorothiazide interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Amiloride, Hydrochlorothiazide interactionAmlodipineNorliqva
How Amlodipine interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Amlodipine interactionAmlodipine BenzoateKaterzia
How Amlodipine Benzoate interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Amlodipine Benzoate interactionAmlodipine BesilateIstin
How Amlodipine Besilate interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Amlodipine Besilate interactionAmlodipine BesylateNorvasc
How Amlodipine Besylate interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Amlodipine Besylate interactionAmlodipine Besylate, BenazeprilLotrel
How Amlodipine Besylate, Benazepril interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Amlodipine Besylate, Benazepril interactionAmlodipine, CelecoxibConsensi
How Amlodipine, Celecoxib interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Amlodipine, Celecoxib interactionAmmonium ChlorideAmmonium Chloride
How Ammonium Chloride interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Ammonium Chloride interactionAprobarbital, Butabarbital, PhenobarbitalTriple Barbital
How Aprobarbital, Butabarbital, Phenobarbital interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
Folic AcidPhenobarbital (luminal) Moderate
Interaction Summary
Folic acid might have antagonistic effects on phenobarbital and increase the risk for seizures.
Read the full Folic Acid + Aprobarbital, Butabarbital, Phenobarbital interactionAprocitentanTryvio
How Aprocitentan interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Aprocitentan interactionAspirin, Codeine Phosphate, PhenobarbitalPhenaphen
How Aspirin, Codeine Phosphate, Phenobarbital interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
Folic AcidPhenobarbital (luminal) Moderate
Interaction Summary
Folic acid might have antagonistic effects on phenobarbital and increase the risk for seizures.
Read the full Folic Acid + Aspirin, Codeine Phosphate, Phenobarbital interactionAtenololAtenix, Tenormin
How Atenolol interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Atenolol interactionAtenolol, ChlortalidoneAtenixCo, Tenoret 50, Totaretic
How Atenolol, Chlortalidone interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Atenolol, Chlortalidone interactionAtenolol, ChlorthalidoneTenoretic
How Atenolol, Chlorthalidone interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Atenolol, Chlorthalidone interactionAtropine, Hyoscyamine, PhenobarbitalHypnaldyne
How Atropine, Hyoscyamine, Phenobarbital interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
Folic AcidPhenobarbital (luminal) Moderate
Interaction Summary
Folic acid might have antagonistic effects on phenobarbital and increase the risk for seizures.
Read the full Folic Acid + Atropine, Hyoscyamine, Phenobarbital interactionAtropine, Hyoscyamine, Phenobarbital, ScopolamineBarbidonna No. 2, Belladonna Phenobarbital
How Atropine, Hyoscyamine, Phenobarbital, Scopolamine interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
Folic AcidPhenobarbital (luminal) Moderate
Interaction Summary
Folic acid might have antagonistic effects on phenobarbital and increase the risk for seizures.
Read the full Folic Acid + Atropine, Hyoscyamine, Phenobarbital, Scopolamine interactionAtropine, Hyoscyamine, Scopolamine, PhenobarbitalBarbeloid, Donnatal #2, Donphen
How Atropine, Hyoscyamine, Scopolamine, Phenobarbital interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
Folic AcidPhenobarbital (luminal) Moderate
Interaction Summary
Folic acid might have antagonistic effects on phenobarbital and increase the risk for seizures.
Read the full Folic Acid + Atropine, Hyoscyamine, Scopolamine, Phenobarbital interactionAtropine, PhenobarbitalAnthrocol
How Atropine, Phenobarbital interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
Folic AcidPhenobarbital (luminal) Moderate
Interaction Summary
Folic acid might have antagonistic effects on phenobarbital and increase the risk for seizures.
Read the full Folic Acid + Atropine, Phenobarbital interactionAzelastine Hydrochloride, Fluticasone PropionateDymista
How Azelastine Hydrochloride, Fluticasone Propionate interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumCorticosteroids Moderate
Interaction Summary
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Read the full Sodium + Azelastine Hydrochloride, Fluticasone Propionate interactionAzilsartanEdarbi
How Azilsartan interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Azilsartan interactionAzilsartan, ChlorthalidoneEdarbyclor
How Azilsartan, Chlorthalidone interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Azilsartan, Chlorthalidone interactionBeclometasone DipropionateBecotide
How Beclometasone Dipropionate interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumCorticosteroids Moderate
Interaction Summary
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Read the full Sodium + Beclometasone Dipropionate interactionBeclomethasoneBeclovent, Vanceril
How Beclomethasone interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumCorticosteroids Moderate
Interaction Summary
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Read the full Sodium + Beclomethasone interactionBeclomethasone DipropionateQNASL, Qvar
How Beclomethasone Dipropionate interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
SodiumCorticosteroids Moderate
Interaction Summary
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Read the full Sodium + Beclomethasone Dipropionate interactionBelladona Extract, PhenobarbitalChardonna-2
How Belladona Extract, Phenobarbital interacts with Folic Acid Gummies — through 1 ingredient. Tap an ingredient for the detail:
Folic AcidPhenobarbital (luminal) Moderate
Interaction Summary
Folic acid might have antagonistic effects on phenobarbital and increase the risk for seizures.
Read the full Folic Acid + Belladona Extract, Phenobarbital interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Folic Acid Gummies with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Sodium
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Folic Acid
5-Fluorouracil
Theoretically, high doses of folic acid might increase the toxicity of 5-fluorouracil.
Increases in gastrointestinal side effects of 5-fluorouracil, such as stomatitis and diarrhea, have been described in two clinical studies when leucovorin, a form of folic acid, was administered with 5-fluorouracil.
Capecitabine (Xeloda)
Use of high-dose folic acid might contribute to capecitabine toxicity.
Clinical research suggests that higher serum folate levels are associated with an increased risk for moderate or severe toxicity during capecitabine-based treatment for colorectal cancer. Additionally, in one case report, taking folic acid 15 mg daily might have contributed to increased toxicity, including severe diarrhea, vomiting, edema, hand-foot syndrome, and eventually death, in a patient prescribed capecitabine.
Methotrexate (Trexall, Others)
Folic acid might reduce the efficacy of methotrexate as a cancer treatment when given concurrently.
Methotrexate exerts its cytotoxic effects by preventing conversion of folic acid to the active form needed by cells. There is some evidence that folic acid supplements reduce the efficacy of methotrexate in the treatment of acute lymphoblastic leukemia, and theoretically they could reduce its efficacy in the treatment of other cancers. Advise cancer patients to consult their oncologist before using folic acid supplements. In patients treated with long-term, low-dose methotrexate for rheumatoid arthritis (RA) or psoriasis, folic acid supplements can reduce the incidence of side effects, without reducing efficacy.
Phenobarbital (Luminal)
Folic acid might have antagonistic effects on phenobarbital and increase the risk for seizures.
Folic acid can have direct convulsant activity in some people, reversing the effects of phenobarbital and worsening seizure control. Monitor closely for increased seizure activity.
Phenytoin (Dilantin)
Folic acid might reduce serum levels of phenytoin in some patients.
Folic acid may be a cofactor in phenytoin metabolism. Folic acid, in doses of 1 mg daily or more, can reduce serum levels of phenytoin in some patients. Increases in seizure frequency have been reported. If folic acid supplements are added to established phenytoin therapy, monitor serum phenytoin levels closely. If phenytoin and folic acid are started at the same time and continued together, adverse changes in phenytoin pharmacokinetics are avoided. Note that phenytoin also reduces serum folate levels.
Primidone (Mysoline)
Folic acid might have antagonistic effects on primidone and increase the risk for seizures.
Folic acid can have direct convulsant activity in some people, reversing the effects of primidone and worsening seizure control. Monitor closely for increased seizure activity. Note that primidone also reduces serum folate levels.
Pyrimethamine (Daraprim)
Folic acid might antagonize the effects of pyrimethamine.
Folic acid can antagonize the antiparasitic effects of pyrimethamine against toxoplasmosis and Pneumocystis carinii pneumonia. Folic acid doesn't antagonize the effects of pyrimethamine in the treatment of malaria, because malarial parasites cannot use exogenous folic acid. Use folinic acid as an alternative to folic acid when indicated.
Brand information
Manufacturer and brand details for Folic Acid Gummies, from the product label.
Folic Acid Gummies by Nature's Nutrition: Common Questions
Does Folic Acid Gummies by Nature's Nutrition interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Is this safe to take during pregnancy?
Can I take this while breastfeeding?
What side effects might I get from folic acid at high doses?
Does folic acid work for depression?
What is sodium doing in a folic acid gummy?
Can this mask vitamin B12 deficiency?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Folic Acid Gummies is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Folic Acid Gummies’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Folic Acid
Interacts with 40 drugsFolic acid is the man-made form of vitamin B9 and is one of the most well-studied supplements, especially for preventing serious birth defects when taken before and during early pregnancy. I...
Read the full Folic Acid monograph → Herb & supplement monographSodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph →Sources & How We Checked
Folic Acid Gummies's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 94 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Folic Acid 56 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Duhra P. Treatment of gastrointestinal symptoms associated with methotrexate therapy for psoriasis. J Am Acad Dermatol 1993;28:466-9. PubMed
- Morgan SL, Baggott JE, Vaughn WH, et al. Supplementation with folic acid during methotrexate therapy for rheumatoid arthritis. A double-blind, placebo-controlled trial. Ann Intern Med 1994;121:833-41. PubMed
- Froscher W, Maier V, Laage M, et al. Folate deficiency, anticonvulsant drugs, and psychiatric morbidity. Clin Neuropharmacol 1995;18:165-82. PubMed
- Lewis DP, Van Dyke DC, Willhite LA, et al. Phenytoin-folic acid interaction. Ann Pharmacother 1995;29:726-35. PubMed
- Berg MJ, Stumbo PJ, Chenard CA, et al. Folic acid improves phenytoin pharmacokinetics. J Am Diet Assoc 1995;95:352-6. PubMed
- Berg MJ, Fincham RW, Ebert BE, et al. Phenytoin pharmacokinetics: Before and after folic acid administration. Epilepsia 1992;33:712-20. PubMed
- Shafer RB, Nuttall FQ. Calcium and folic acid absorption in patients taking anticonvulsant drugs. J Clin Endocrinol Metab 1975;41:1125-9. PubMed
- Leeb BF, Witzmann G, Ogris E, et al. Folic acid and cyanocobalamin levels in serum and erythrocytes during low-dose methotrexate therapy of rheumatoid arthritis and psoriatic arthritis patients. Clin Exp Rheumatol 1995;13:459-63.
- Morgan SL, Baggott JE, Lee JY, Alarcón GS. Folic acid supplementation prevents deficient blood folate levels and hyperhomocysteinemia during longterm, low dose methotrexate therapy for rheumatoid arthritis: implications for cardiovascular disease preventi
- Dijkmans BA. Folate supplementation and methotrexate. Br J Rheumatol 1995;34:1172-4. PubMed
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Lambie DG, Johnson RH. Drugs and folate metabolism. Drugs 1985;30:145-55. PubMed
- Amer College of Rheumatology ad hoc committee on clinical guidelines. Guidelines for monitoring drug therapy in rheumatoid arthritis. Arthritis Rheum 1996;39:723-31. DOI
- Suitor CW, Bailey LB. Dietary folate equivalents: interpretation and application. J Am Diet Assoc 2000;100:88-94. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Sandoval M, Charbonnet RM, Okuhama NN, et al. Cat's claw inhibits TNFalpha production and scavenges free radicals: role in cytoprotection. Free Radic Biol Med 2000;29:71-78.
- Antony AC. Megaloblastic Anemias. In: Hoffman R, Benz Jr EJ, Shattil SJ, et al. Hematology: Basic Principles and Practice. 3rd ed. New York, NY: Churchill Livingstone 2000: 451-79.
- Reynolds EH. Neurological aspects of folate and vitamin B12 metabolism. Clin Haematol 1976;5:661-96. DOI
- Reynolds EH. Folate metabolism and anticonvulsant therapy. Proc R Soc Med 1974;67:68.
- Ortiz Z, Shea B, Suarez Almazor M, et al. Folic acid and folinic acid for reducing side effects in patients receiving methotrexate for rheumatoid arthritis (Cochrane Review). Cochrane Database Syst Rev 2000;2:CD000951. PubMed
- Van Delden C, Hirschel B. Folinic acid supplements to pyrimethamine-sulfadiazine for Toxoplasma encephalitis are associated with better outcome (letter). J Infect Dis 1996;173:1294-5. PubMed
- Schroder H, Clausen N, Ostergard E, Pressler T. Folic acid supplements in vitamin tablets: a determinant of hematological drug tolerance in maintenance therapy of childhood acute lymphoblastic leukemia. Ped Hematol Oncol 1986;3:241-7. PubMed
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Morris MC, Evans DA, Bienias JL, et al. Dietary folate and vitamin B12 intake and cognitive decline among community-dwelling older persons. Arch Neurol 2005;62:641-5. PubMed
- Bonaa KH, Njolstad I, Ueland PM, et al. NORVIT: Homocysteine lowering and cardiovascular events after acute myocardial infarction. N Enlg J Med 2006;354:1578-88. PubMed
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Figueiredo JC, Grau MV, Haile RW, et al. Folic acid and risk of prostate cancer: Results from a randomized clinical trial. J Natl Cancer Inst 2009;101:432-5. PubMed
- Clippe C, Freyer G, Milano G, Trillet-Lenoir V. Lethal toxicity of capecitabine due to abusive folic acid prescription. Clin Oncol (R Coll Radiol) 2003;15:299-300. PubMed
- Bedford Laboratories. Leucovorin calcium [package insert]. Bedford, OH. September 2008. Available at: http://www.bedfordlabs.com/BedfordLabsWeb/products/inserts/LCV-P02.pdf.
- Ebbing M, Bonaa KH, Nygard O, et al. Cancer incidence and mortality after treatment with folic acid and vitamin B12. JAMA 2009;302:2119-26.
- Haberg, S. E., London, S. J., Stigum, H., Nafstad, P., and Nystad, W. Folic acid supplements in pregnancy and early childhood respiratory health. Arch Dis.Child 2009;94(3):180-184. PubMed
- Whitrow, M. J., Moore, V. M., Rumbold, A. R., and Davies, M. J. Effect of supplemental folic acid in pregnancy on childhood asthma: a prospective birth cohort study. Am J Epidemiol. 12-15-2009;170(12):1486-1493. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Baggott, J. E., Oster, R. A., and Tamura, T. Meta-analysis of cancer risk in folic acid supplementation trials. Cancer Epidemiol. 2012;36(1):78-81. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Taneja S, Strand TA, Kumar T, et al. Folic acid and vitamin B-12 supplementation and common infections in 6-30-mo-old children in India: a randomized placebo-controlled trial. Am J Clin Nutr 2013;98(3):731-7. PubMed
- van Wijngaarden JP, Swart KM, Enneman AW, et al. Effect of daily vitamin B-12 and folic acid supplementation on fracture incidence in elderly individuals with an elevated plasma homocysteine concentration: B-PROOF, a randomized controlled trial. Am J Clin
- Qin X, Fan F, Cui Y, Chen F, Chen Y, Cheng X, Li Y, Wang B, Xu X, Xu X, Huo Y, Wang X. Folic acid supplementation with and without vitamin B6 and revascularization risk: a meta-analysis of randomized controlled trials. Clin Nutr. 2014;33(4):603-12. PubMed
- Crider KS, Cordero AM, Qi YP, Mulinare J, Dowling NF, Berry RJ. Prenatal folic acid and risk of asthma in children: a systematic review and meta-analysis. Am J Clin Nutr. 2013;98(5):1272-81. PubMed
- Matsubara S, Imai K, Murayama K, Higashizawa T. Severe liver dysfunction during nausea and vomiting of pregnancy: folic acid supplement as a suggested culprit. J Obstet Gynaecol. 2012;32(7):701-2. PubMed
- Qin X, Cui Y, Shen L, Sun N, Zhang Y, Li J, Xu X, Wang B, Xu X, Huo Y, Wang X. Folic acid supplementation and cancer risk: a meta-analysis of randomized controlled trials. Int J Cancer. 2013 1;133(5):1033-41. PubMed
- Tio M, Andrici J, Cox MR, Eslick GD. Folate intake and the risk of prostate cancer: a systematic review and meta-analysis. Prostate Cancer Prostatic Dis. 2014;17(3):213-9. PubMed
- Tomaszewski JJ, Richman EL, Sadetsky N, O'Keefe DS, Carroll PR, Davies BJ, Chan JM. Impact of folate intake on prostate cancer recurrence following definitive therapy: data from CaPSURE. J Urol. 2014;191(4):971-6. PubMed
- Valera-Gran D, García de la Hera M, Navarrete-Muñoz EM, Fernandez-Somoano A, Tardón A, Julvez J, Forns J, Lertxundi N, Ibarluzea JM, Murcia M, Rebagliato M, Vioque J; Infancia y Medio Ambiente (INMA) Project. Folic acid supplements during pregnancy and ch
- Van Der Woude DA, De Vries J, Van Wijk EM, Verzijl JM, Pijnenborg JM. A randomized controlled trial examining the addition of folic acid to iron supplementation in the treatment of postpartum anemia. Int J Gynaecol Obstet. 2014;126(2):101-5. PubMed
- Vila-Nova C, Wehby GL, Queirós FC, Chakraborty H, Félix TM, Goco N, Moore J, Gewehr EV, Lins L, Affonso CM, Murray JC. Periconceptional use of folic acid and risk of miscarriage - findings of the Oral Cleft Prevention Program in Brazil. J Perinat Med. 201 PubMed
- Vollset SE, Clarke R, Lewington S, Ebbing M, Halsey J, Lonn E, Armitage J, Manson JE, Hankey GJ, Spence JD, Galan P, Bønaa KH, Jamison R, Gaziano JM, Guarino P, Baron JA, Logan RF, Giovannucci EL, den Heijer M, Ueland PM, Bennett D, Collins R, Peto R; B-V
- Wehby GL, Félix TM, Goco N, Richieri-Costa A, Chakraborty H, Souza J, Pereira R, Padovani C, Moretti-Ferreira D, Murray JC. High dosage folic acid supplementation, oral cleft recurrence and fetal growth. Int J Environ Res Public Health. 2013 4;10(2):590-6 PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Liu J, Li Z, Ye R, Liu J, Ren A. Periconceptional folic acid supplementation and risk of parent-reported asthma in children at 4-6 years of age. ERJ Open Res. 2020;6(1):00250-2019. PubMed
- Houghton LA, Sherwood KL, Pawlosky R, Ito S, O'Connor DL. [6S]-5-Methyltetrahydrofolate is at least as effective as folic acid in preventing a decline in blood folate concentrations during lactation. Am J Clin Nutr. 2006 Apr;83(4):842-50. PubMed
- Houghton LA, Yang J, O'Connor DL. Unmetabolized folic acid and total folate concentrations in breast milk are unaffected by low-dose folate supplements. Am J Clin Nutr. 2009 Jan;89(1):216-20. PubMed
- Chan SL, Chan AWH, Mo F, et al. Association Between Serum Folate Level and Toxicity of Capecitabine During Treatment for Colorectal Cancer. Oncologist. 2018 Dec;23(12):1436-1445. PubMed
- Sarris J, Ravindran A, Yatham LN, et al. Clinician guidelines for the treatment of psychiatric disorders with nutraceuticals and phytoceuticals: The World Federation of Societies of Biological Psychiatry (WFSBP) and Canadian Network for Mood and Anxiety T
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC