
bosentan 62.5 mg Tablet, Film Coated, 60-count — NDC 0591-2511-60 (Billing 00591-2511-60)
This is a package of 60 tablets of bosentan 62.5 mg Tablet, Film Coated from Actavis Pharma, Inc., marketed since Jun 2019 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0591-2511-60 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0591 labeler · 2511 product · 60 package
- Package marketed since
- Jun 19, 2019
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 60 EA per package
- Barcode (UPC)
- 0305912512604, 0305912511607
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 048988
- GCN: 14979
- GPI-14 (Medi-Span): 40160015000320
- HICL (First Databank): 022990
- AHFS class code: 24:12.92.00
- RxCUI (RxNorm): 349253
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Endothelin Receptor Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Bosentan is used to treat pulmonary arterial hypertension (PAH, high blood pressure in the vessels that carry blood to the lungs). Bosentan is in a class of medications called endothelin receptor antagonists. It works by stopping the action of endothelin, a natural substance that causes blood vessels to narrow and prevents normal blood flow in people who have PAH.
Read the full MedlinePlus article ↗- It treats pulmonary arterial hypertension, or high blood pressure in the lung arteries. In adults it helps you exercise better and slows worsening. It is also used in children 3 ye...
- You take it by mouth twice a day, with or without food. Dispersible tablets get mixed in a little water right before you take them. Your dose depends on your age and weight, so fol...
- Bosentan can raise liver enzymes and, rarely, cause serious liver damage. Monthly tests catch problems early, often before you feel anything. Call us right away if you get nausea,...
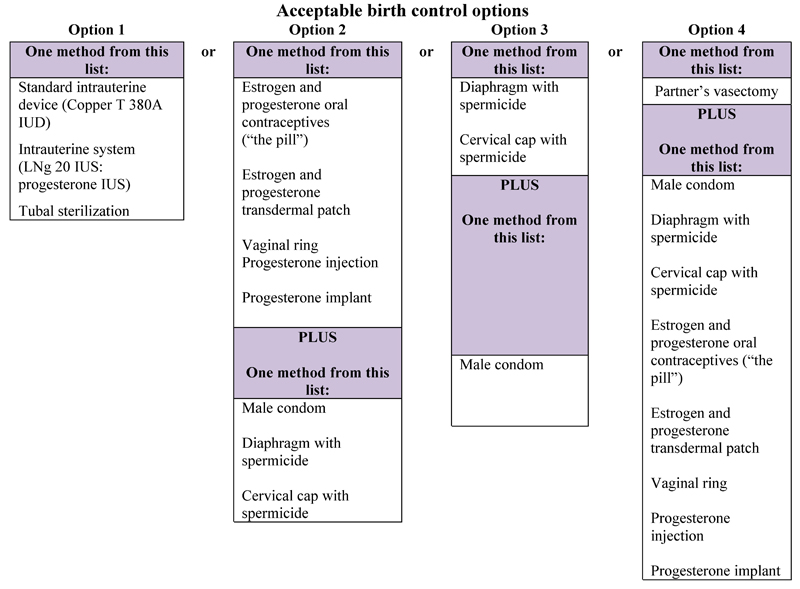
- Only with strict precautions. Bosentan is likely to cause major birth defects, so you need a negative pregnancy test first and monthly tests. You must use two reliable birth contro...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Bosentan — tap one for details:
Bosentan may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $79.22 | $4,753.24 / 60 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 6, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00591-2511-60 You're viewing this Main listing | 60 TABLET, FILM COATED in 1 BOTTLE | 2019-06-19 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| bosentan 62.5 mgthis 00591-2511-60 | Actavis | 60 tablets | — | AB | FDA listed | — |
| Bosentan 62.5 mg 47335-0038-64 | Sun | 3 tablets | — | AB | FDA listed | — |
| Tracleer 62.5 mg 66215-0101-03 | Actelion | 3 tablets | — | AB | FDA listed | — |
| Bosentan 62.5 mg 68382-0446-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Bosentan 62.5 mg 70771-1017-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Bosentan inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3DYK7UYZ62
Ethylcellulose is a plant-fiber derivative used as a binder and film-coating agent in tablets and capsules. It helps hold ingredients together and can create a protective coating that controls how quickly the medicine dissolves.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 73CJJ317SR
A waxy substance derived from plant oils, used as a binder and lubricant to help hold tablet ingredients together and improve how the medicine flows during manufacturing.
-
UNII 36SFW2JZ0W
Hypromellose 2910 is a plant-based thickening agent derived from cellulose. In medicines, it forms a protective coating on tablets or capsules and controls how quickly the drug dissolves and releases into your body.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII RDH86HJV5Z
Povidone K90 is a synthetic polymer made from a chemical called vinyl pyrrolidone. It acts as a binder to hold pill ingredients together and as a dispersant to help the medicine break down and dissolve properly in your body.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Actavis Pharma, Inc. labeler code 00591
- Tamoxifen Citrate 10 mg Tablet NDC 0591-2472-18
- Tamoxifen Citrate 20 mg Tablet NDC 0591-2473-19
- Tetracycline Hydrochloride 250 mg Capsule NDC 0591-2474-00
- Tetracycline Hydrochloride 500 mg Capsule NDC 0591-2475-00
- Isotretinoin 35 mg Capsule NDC 0591-2501-15
- Budesonide 9 mg Tablet, Film Coated, Extended Release NDC 0591-2510-30
- bosentan 125 mg Tablet, Film Coated NDC 0591-2512-60
- Chlorzoxazone 500 mg Tablet NDC 0591-2520-00
- Dalfampridine 10 mg Tablet, Film Coated, Extended Release NDC 0591-2533-60
- Valganciclovir hydrochloride for Oral 50 mg/mL Powder, For Solution NDC 0591-2579-20
- Butalbital, Acetaminophen, and Caffeine 50 mg; 300 mg; 40 mg Capsule NDC 0591-2640-01
- Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate 50 mg; 300 mg; 40 mg; 30 mg Capsule NDC 0591-2641-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISKS OF HEPATOTOXICITY and EMBRYO-FETAL TOXICITY Because of the risk of hepatotoxicity, bosentan tablets are available only through a restricted program called the Bosentan Risk Evaluation and Mitigation Strategy (REMS). Under the Bosentan REMS, prescribers, patients, and pharmacies must enroll in the program [see Warnings and Precautions (5.2) ]. Hepatotoxicity In clinical studies, bosentan caused at least 3-fold upper limit of normal (ULN) elevation of liver aminotransferases (ALT and AST) in about 11% of patients, accompanied by elevated bilirubin in a small number of cases.
Because these changes are a marker for potential serious hepatotoxicity, serum aminotransferase levels must be measured prior to initiation of treatment and then monthly [see Dosage and Administration (2.4) , Warnings and Precautions (5.1) ] . In the postmarketing period, in the setting of close monitoring, rare cases of unexplained hepatic cirrhosis were reported after prolonged (>12 months) therapy with bosentan in patients with multiple comorbidities and drug therapies. There have also been reports of liver failure.
The contribution of bosentan in these cases could not be excluded. In at least one case, the initial presentation (after >20 months of treatment) included pronounced elevations in aminotransferases and bilirubin levels accompanied by non-specific symptoms, all of which resolved slowly over time after discontinuation of bosentan tablets. This case reinforces the importance of strict adherence to the monthly monitoring schedule for the duration of treatment and the treatment algorithm, which includes stopping bosentan with a rise of aminotransferases accompanied by signs or symptoms of liver dysfunction [see Dosage and Administration (2.4) ] .
Elevations in aminotransferases require close attention [see Dosage and Administration (2.4) ] . Bosentan should generally be avoided in patients with elevated aminotransferases (>3xULN) at baseline because monitoring for hepatotoxicity may be more difficult. If liver aminotransferase elevations are accompanied by clinical symptoms of hepatotoxicity (such as nausea, vomiting, fever, abdominal pain, jaundice, or unusual lethargy or fatigue) or increases in bilirubin ≥2xULN, treatment with bosentan should be stopped.
There is no experience with the reintroduction of bosentan in these circumstances. Embryo-Fetal Toxicity Bosentan is contraindicated for use during pregnancy because it may cause fetal harm if used by pregnant females based on animal data. Therefore, for females of reproductive potential, exclude pregnancy before the start of treatment with bosentan tablets.
Advise use of effective contraception before initiation, during treatment and for one month after stopping bosentan. When pregnancy is detected, discontinue bosentan as soon as possible [see Dosage and Administration (2.1) , Contraindications (4.1) , Warnings and Precautions (5.3) , Drug Interactions (7.2) , Use in Specific Populations (8.1 , 8.3 )] . WARNING: RISKS OF HEPATOTOXICITY and EMBRYO-FETAL TOXICITY See full prescribing information for complete boxed warning.
Bosentan tablets are available only through a restricted distribution program called the Bosentan Risk Evaluation and Mitigation Strategy (REMS) because of the risk of hepatotoxicity ( 5.2 ): Elevations of liver aminotransferases (ALT, AST) and liver failure have been reported with bosentan ( 5.1 ). Measure liver aminotransferases prior to initiation of treatment and then monthly ( 2.1 , 5.1 ). Discontinue bosentan if aminotransferase elevations are accompanied by signs or symptoms of liver dysfunction or injury or increases in bilirubin ≥2xULN ( 2.4 , 5.1 ).
Based on animal data, bosentan may cause fetal harm if used during pregnancy ( 4.1 , 5.3 , 8.1) . Females of reproductive potential: Exclude pregnancy before initiating treatment. Use effective contraception prior to initiation of treatment, during treatment and for one month after stopping bosentan ( 2.1 ,… [Excerpted — this section continues on DailyMed.]
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Bosentan tablets are indicated for the treatment of pulmonary arterial hypertension (PAH) (WHO Group 1): in adults to improve exercise ability and to decrease clinical worsening. Studies establishing effectiveness included predominantly patients with WHO Functional Class II-IV symptoms and etiologies of idiopathic or heritable PAH (60%), PAH associated with connective tissue diseases (21%), and PAH associated with congenital heart disease with left-to-right shunts (18%) [see Clinical Studies (14.1) ] . in pediatric patients aged 3 years and older with idiopathic or congenital PAH to improve pulmonary vascular resistance (PVR), which is expected to result in an improvement in exercise ability.
Bosentan is an endothelin receptor antagonist indicated for the treatment of pulmonary arterial hypertension (PAH) (WHO Group 1): in adults to improve exercise ability and to decrease clinical worsening. Studies establishing effectiveness included predominantly patients with WHO Functional Class II-IV symptoms and etiologies of idiopathic or heritable PAH (60%), PAH associated with connective tissue diseases (21%), and PAH associated with congenital heart disease with left-to-right shunts (18%) ( 1 ). in pediatric patients aged 3 years and older with idiopathic or congenital PAH to improve pulmonary vascular resistance (PVR), which is expected to result in an improvement in exercise ability ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Patients older than 12 years of age: initiate at 62.5 mg orally twice daily; for patients weighing greater than 40 kg, increase to 125 mg orally twice daily after 4 weeks ( 2.2 ). Patients 12 years of age and younger: dosage is based on weight, see Table 1 ( 2.2 ). Reduce the dose and closely monitor patients developing aminotransferase elevations more than 3xUpper Limit of Normal (ULN) ( 2.4 ).
2.1Required Monitoring Healthcare professionals who prescribe bosentan tablets must enroll in the Bosentan REMS and must comply with the required monitoring to minimize the risks associated with bosentan tablets [see Warnings and Precautions (5.2) ] . Measure liver aminotransferase levels prior to initiation of treatment and then monthly [see Boxed Warning , Warnings and Precautions (5.1, 5.2 )] . Exclude pregnancy before initiating treatment with bosentan in females of reproductive potential [see Boxed Warning , Contraindications (4.1) , Warnings and Precautions ( 5.3) , Use in Specific Populations ( 8.1 , 8.3 )] .
2.2Recommended Dosage Administer bosentan tablets orally following the dosing recommendations in Table 1. Doses above 125 mg twice daily did not appear to confer additional benefit sufficient to offset the increased risk of hepatotoxicity. Table 1: Dosing Recommendations Initial 4 weeks Maintenance (after 4 weeks) Patients >12 years of age and >40 kg 62.5 mg twice daily 125 mg twice daily Patients >12 years of age and <40 kg 62.5 mg twice daily 62.5 mg twice daily Patients ≤12 years of age ≥4 to 8 kg 16 mg twice daily 16 mg twice daily ˃8 to 16 kg 32 mg twice daily 32 mg twice daily ˃16 to 24 kg 48 mg twice daily 48 mg twice daily ˃24 to 40 kg 64 mg twice daily 64 mg twice daily
2.3Administration Bosentan film-coated tablets should be administered orally twice daily.
2.4Dosage Adjustments for Aminotransferase Elevations If aminotransferase levels increase, adjust monitoring and treatment plan according to Table 2. Discontinue bosentan if liver aminotransferase elevations are accompanied by clinical symptoms of hepatotoxicity (such as nausea, vomiting, fever, abdominal pain, jaundice, or unusual lethargy or fatigue) or bilirubin ≥2xUpper Limit of Normal (ULN). There is no experience with the reintroduction of bosentan in these circumstances.
Table 2: Dosage Adjustment and Monitoring in Patients Developing Aminotransferase Elevations >3xULN ALT/AST levels Treatment and monitoring recommendations >3 and ≤5xULN Confirm by another aminotransferase test; if confirmed, in adults and pediatric patients >12 years and >40 kg , reduce the daily dose to 62.5 mg twice daily or interrupt treatment, and monitor aminotransferase levels at least every 2 weeks. If the aminotransferase levels return to pretreatment values, treatment may continue or be reintroduced at 62.5 mg twice daily, with reassessment of aminotransferase levels within 3 days. in all other pediatric patients, interrupt treatment with no prior dose reduction.
If the aminotransferase levels return to pretreatment values, reintroduce at the dose used prior to treatment interruption, with reassessment of aminotransferase levels within 3 days. >5 and ≤8xULN Confirm by another aminotransferase test; if confirmed, stop treatment and monitor aminotransferase levels at least every 2 weeks. Once the aminotransferase levels return to pretreatment values, in adults and pediatric patients >12 years and >40 kg , consider reintroduction of treatment at 62.5 mg twice daily, with reassessment of aminotransferase levels within 3 days. in all other pediatric patients , consider reintroduction at the dose used prior to treatment interruption, with reassessment of aminotransferase levels within 3 days. >8xULN Stop treatment permanently.
There is no experience with reintroduction of Bosentan in these circumstances.
2.5Use with Ritonavir Coadministration of Bosentan Tablets in Patients on Ritonavir In patients who have been receiving ritonavir for at least 10 day… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Bosentan Tablets for oral administration are available as follows: 62.5 mg - Light orange, round, biconvex, film-coated tablets, debossed with ‘WPI’ on one side and ‘62.5’ on the other side contains 64.541 mg of bosentan monohydrate, equivalent to 62.5 mg of bosentan base. 125 mg - Light orange, oval, biconvex, film-coated tablets, debossed with ‘WPI’ on one side and ‘125’ on the other side contains 129.082 mg of bosentan monohydrate, equivalent to 125 mg of bosentan base. Film-coated tablet: 62.5 mg and 125 mg ( 3 ).
⛔ Contraindications ▾
4 CONTRAINDICATIONS Pregnancy ( 4.1 ). Use with Cyclosporine A ( 4.2 ). Use with Glyburide ( 4.3 ). Hypersensitivity ( 4.4 ).
4.1Pregnancy Use of bosentan is contraindicated in females who are pregnant [see Boxed Warning , Dosage and Administration (2.1 ), Warnings and Precautions (5.3) , Use in Specific Populations (8.1) ] .
4.2Use with Cyclosporine A Coadministration of cyclosporine A and bosentan resulted in markedly increased plasma concentrations of bosentan. Therefore, concomitant use of bosentan and cyclosporine A is contraindicated [see Drug Interactions (7.1) ] .
4.3Use with Glyburide An increased risk of liver enzyme elevations was observed in patients receiving glyburide concomitantly with bosentan. Therefore coadministration of glyburide and bosentan is contraindicated [see Drug Interactions (7.1) ] .
4.4Hypersensitivity Bosentan is contraindicated in patients who are hypersensitive to bosentan or any component of the product. Observed reactions include Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS), anaphylaxis, rash, and angioedema [see Adverse Reactions (6.2) , Description (11) ] .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Fluid retention: May require intervention ( 5.4 ). Pulmonary veno-occlusive disease (PVOD): If signs of pulmonary edema occur, consider the diagnosis of associated PVOD and consider discontinuing bosentan ( 5.5 ). Decreased sperm counts ( 5.6 ). Decreases in hemoglobin and hematocrit: Monitor hemoglobin levels after 1 and 3 months of treatment, then every 3 months thereafter ( 5.7 ).
5.1Hepatotoxicity ALT or AST >3xULN were observed in 11% of bosentan-treated patients (n=658) compared to 2% of placebo-treated patients (n=280). Three-fold increases were seen in 12% of 95 pulmonary arterial hypertension (PAH) patients on 125 mg twice daily and 14% of 70 PAH patients on 250 mg twice daily. Eight-fold increases were seen in 2% of PAH patients on 125 mg twice daily and 7% of PAH patients on 250 mg twice daily.
Bilirubin increases to ≥3xULN were associated with aminotransferase increases in 2 of 658 (0.3%) of patients treated with bosentan. In a pooled analysis of four pediatric studies conducted in PAH (n=100), elevations in liver aminotransferases ≥3×ULN were observed in 2% of patients. The combination of hepatocellular injury (increases in aminotransferases of >3xULN) and increases in total bilirubin (≥2xULN) is a marker for potential serious hepatotoxicity.
Elevations of AST or ALT associated with bosentan are dose-dependent, occur both early and late in treatment, usually progress slowly, are typically asymptomatic, and usually have been reversible after treatment interruption or cessation. Aminotransferase elevations also may reverse spontaneously while continuing treatment with bosentan. Liver aminotransferase levels must be measured prior to initiation of treatment and then monthly and therapy adjusted accordingly [see Dosage and Administration (2.1 , 2.4) ] .
Discontinue bosentan if liver aminotransferase elevations are accompanied by clinical symptoms of hepatotoxicity (such as nausea, vomiting, fever, abdominal pain, jaundice, or unusual lethargy or fatigue) or increases in bilirubin ≥2xULN. Avoid initiation of bosentan in patients with elevated aminotransferases (>3xULN) prior to drug initiation because monitoring hepatotoxicity in these patients may be more difficult [see Boxed Warning , D osage and Administration (2.6) , Use in Specific Populations (8.6) ] . In WHO Functional Class II patients, consider whether the benefits of bosentan are sufficient to offset the risk of hepatotoxicity, which may preclude future use as their disease progresses.
Bosentan is only available through a restricted program under REMS [see Warnings and Precautions (5.2) ].
5.2Bosentan REMS Because of the risks of hepatotoxicity, bosentan tablets are available only through a restricted program called the Bosentan REMS. As a component of the Bosentan REMS, prescribers, patients, and pharmacies must enroll in the program [see Boxed Warning , Warnings and Precautions (5.1) ] . Required components of the Bosentan REMS are: Healthcare professionals who prescribe bosentan tablets must review the prescriber educational materials, enroll in the Bosentan REMS and comply with its requirements.
Healthcare professionals must (1) review serum aminotransferases (ALT/AST) and bilirubin, and agree to order and monitor these tests monthly. To receive bosentan tablets, all patients must understand the risks and benefits, and complete a patient enrollment form with their prescriber. Pharmacies that dispense bosentan tablets must enroll in the program and agree to comply with the Bosentan REMS requirements.
Further information about bosentan tablets and the Bosentan REMS is available at www.BosentanREMSProgram.com or 1-866-359-2612.
5.3Embryo-Fetal Toxicity Based on data from animal reproduction studies, bosentan may cause fetal harm when administered to a pregnant female and is contraindicated in females who are pregnant. The available human data for endothelin receptor antagonists do not establish the presence or absence of major b… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following important adverse reactions are described elsewhere in the labeling: Hepatotoxicity [see Boxed Warning , Warnings and Precautions (5.1) ] Embryo-fetal Toxicity [see Boxed Warning , Warnings and Precautions (5.3) ] Fluid Retention [see Warnings and Precautions (5.4) ] Common adverse reactions (≥3% more than placebo) for the film-coated tablet are respiratory tract infection and anemia ( 6.1 ). To report SUSPECTED ADVERSE REACTIONS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Safety data on bosentan were obtained from 13 clinical studies (9 placebo-controlled and 4 open-label) in 870 adult patients with PAH and other diseases. Doses up to 8 times the currently recommended clinical dose (125 mg twice daily) were administered for a variety of durations.
The exposure to bosentan in these trials ranged from 1 day to 4.1 years (n=94 for 1 year; n=61 for 1.5 years; and n=39 for more than 2 years). Exposure of PAH patients (n=328) to bosentan ranged from 1 day to 1.7 years (n=174 more than 6 months and n=28 more than 12 months). Treatment discontinuations due to adverse events other than those related to pulmonary hypertension during the clinical trials in adult patients with PAH were more frequent on bosentan (6%; 15/258 patients) than on placebo (3%; 5/172 patients).
In this database the only cause of discontinuations >1% and occurring more often on bosentan was abnormal liver function. The adverse drug events that occurred in ≥3% of the bosentan-treated patients and were more common on bosentan in placebo-controlled trials in PAH at doses of 125 or 250 mg twice daily are shown in Table 3: Table 3: Adverse Events* Occurring in ≥3% of Patients Treated with Bosentan 125 to 250 mg Twice Daily and More Common on Bosentan in Placebo-Controlled Studies in Pulmonary Arterial Hypertension Adverse Event Bosentan Placebo n=258 n=172 No. % No. % Respiratory Tract Infection** 56 22% 30 17% Headache 39 15% 25 14% Edema 28 11% 16 9% Chest Pain 13 5% 8 5% Syncope 12 5% 7 4% Flushing 10 4% 5 3% Hypotension 10 4% 3 2% Sinusitis 9 4% 4 2% Arthralgia 9 4% 3 2% Serum Aminotransferases, abnormal 9 4% 3 2% Palpitations 9 4% 3 2% Anemia 8 3% - - * Note: only AEs with onset from start of treatment to 1 calendar day after end of treatment are included.
All reported events (at least 3%) are included except those too general to be informative, and those not reasonably associated with the use of the drug because they were associated with the condition being treated or are very common in the treated population. ** Respiratory Tract Infection combines the terms "Nasopharyngitis", "Upper Respiratory Tract Infection" and "Respiratory Tract Infection". Combined data from Study 351, BREATHE-1 and EARLY Bosentan was evaluated for safety in 119 pediatric patients in uncontrolled studies.
The safety profile was similar to that observed in adult patients with PAH. Decreased Sperm Counts An open-label, single-arm, multicenter, safety study evaluated the effect on testicular function of bosentan 62.5 mg twice daily for 4 weeks, followed by 125 mg twice daily for 5 months. Twenty-five male patients with WHO functional class III and IV PAH and normal baseline sperm count were enrolled.
Twenty-three completed the study and 2 discontinued due to adverse events not related to testicular function. There was a decline in sperm count of at least 50% in 25% of the patients after 3 or 6 months of treatment with bosentan. Sperm count remained within the normal range in all 22 patients with data after 6 months and no changes in sperm morphology, sperm motility, or hormone levels were observed.
One patient developed marked oli… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Cytochrome P450: Coadministration of bosentan with drugs metabolized by CYP2C9 and CYP3A can increase exposure to bosentan and/or the coadministered drug ( 4.2 , 4.3 , 7.1 ). Hormonal contraceptives: bosentan use decreases contraceptive exposure and reduces effectiveness ( 7.2 ).
7.1Cytochrome P450 Drug Interactions Bosentan is metabolized by CYP2C9 and CYP3A. Inhibition of these enzymes may increase the plasma concentration of bosentan [see Clinical Pharmacology (12.3) ] . Concomitant administration of both a CYP2C9 inhibitor (such as fluconazole or amiodarone) and a strong CYP3A inhibitor (e.g., ketoconazole, itraconazole) or a moderate CYP3A inhibitor (e.g., amprenavir, erythromycin, fluconazole, diltiazem) with bosentan will likely lead to large increases in plasma concentrations of bosentan.
Coadministration of such combinations of a CYP2C9 inhibitor plus a strong or moderate CYP3A inhibitor with bosentan is not recommended. Bosentan is an inducer of CYP3A and CYP2C9. Consequently plasma concentrations of drugs metabolized by these two isozymes will be decreased when bosentan is coadministered.
Bosentan had no relevant inhibitory effect on any CYP isozyme in vitro (CYP1A2, CYP2C9, CYP2C19, CYP2D6, CYP3A). Consequently, bosentan is not expected to increase the plasma concentrations of drugs metabolized by these enzymes. Figure 1.
CYP3A induction-mediated effect of bosentan on other drugs Figure 2. Effect of other drugs on bosentan 1 2
7.2Hormonal Contraceptives Hormonal contraceptives, including oral, injectable, transdermal, and implantable forms, may not be reliable when bosentan is coadministered. Females should practice additional methods of contraception and not rely on hormonal contraception alone when taking bosentan [see Use in Specific Populations (8.3) ] . An interaction study demonstrated that coadministration of bosentan and a combination oral hormonal contraceptive produced average decreases of norethindrone and ethinyl estradiol levels of 14% and 31%, respectively.
However, decreases in exposure were as much as 56% and 66%, respectively, in individual subjects.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Nursing mothers: Choose breastfeeding or bosentan ( 8.2 ).
8.1Pregnancy Risk Summary Based on data from animal reproduction studies, bosentan may cause fetal harm, including birth defects and fetal death, when administered to a pregnant female and is contraindicated during pregnancy [see Contraindications (4.1)] . Available data from postmarketing reports and published literature over decades of use with endothelin receptor antagonists (ERA) in the same class as bosentan have not identified an increased risk of major birth defects; however, these data are limited. Methodological limitations of these postmarketing reports and published literature include lack of a control group; limited information regarding dose, duration, and timing of drug exposure; and missing data.
These limitations preclude establishing a reliable estimate of the risk of adverse fetal and neonatal outcomes with maternal ERA use. In animal reproduction studies, oral administration of bosentan to pregnant rats at 2-times the maximum recommended human dose (MRHD) on a mg/m 2 basis caused teratogenic effects in rats, including malformations of the head, mouth, face, and large blood vessels [see Animal Data] . Advise pregnant women of the potential risk to a fetus.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Bosentan was teratogenic in rats given oral doses two times the MRHD (on a mg/m 2 basis). In an embryo-fetal toxicity study in rats, bosentan showed dose-dependent teratogenic effects, including malformations of the head, mouth, face and large blood vessels. Bosentan increased stillbirths and pup mortality at oral doses 2 and 10 times the MRHD (on a mg/m 2 basis).
Although birth defects were not observed in rabbits given oral doses of up to the equivalent of 10.5 g/day in a 70 kg person, plasma concentrations of bosentan in rabbits were lower than those reached in the rat. The similarity of malformations induced by bosentan and those observed in endothelin-1 knockout mice and in animals treated with other endothelin receptor antagonists indicates that embryo-fetal toxicity is a class effect of these drugs.
8.2Lactation Risk Summary Data from a case report describe the presence of bosentan in human milk. There is insufficient information about the effects of bosentan on the breastfed infant and no information on the effects of bosentan on milk production. Because of the potential for serious adverse reactions, such as fluid retention and hepatotoxicity, in breastfed infants from bosentan, advise women not to breastfeed during treatment with bosentan.
8.3Females and Males of Reproductive Potential Based on data from animal reproductive toxicity studies, bosentan may cause fetal harm, including birth defects and fetal death, when administered to a pregnant patient and is contraindicated during pregnancy [see Contraindications (4.1) , Use in Specific Populations (8.1) ] . Pregnancy Testing Verify that females of reproductive potential are not pregnant prior to initiating bosentan. The patient should contact her physician immediately for pregnancy testing if onset of menses is delayed or pregnancy is suspected.
If the pregnancy test is positive, the physician and patient must discuss the risks to her, the pregnancy, and the fetus [see Dosage and Administration (2.1) , Contraindications (4.1) , Warnings and Precautions (5.3) ] . Contraception Drug interaction studies show that bosentan reduces serum levels of the estrogen and progestin in oral contraceptives. Based on these findings, hormonal contraceptives (including oral, injectable, transdermal, and implantable contraceptives) may… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on data from animal reproduction studies, bosentan may cause fetal harm, including birth defects and fetal death, when administered to a pregnant female and is contraindicated during pregnancy [see Contraindications (4.1)] . Available data from postmarketing reports and published literature over decades of use with endothelin receptor antagonists (ERA) in the same class as bosentan have not identified an increased risk of major birth defects; however, these data are limited. Methodological limitations of these postmarketing reports and published literature include lack of a control group; limited information regarding dose, duration, and timing of drug exposure; and missing data.
These limitations preclude establishing a reliable estimate of the risk of adverse fetal and neonatal outcomes with maternal ERA use. In animal reproduction studies, oral administration of bosentan to pregnant rats at 2-times the maximum recommended human dose (MRHD) on a mg/m 2 basis caused teratogenic effects in rats, including malformations of the head, mouth, face, and large blood vessels [see Animal Data] . Advise pregnant women of the potential risk to a fetus.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Bosentan was teratogenic in rats given oral doses two times the MRHD (on a mg/m 2 basis). In an embryo-fetal toxicity study in rats, bosentan showed dose-dependent teratogenic effects, including malformations of the head, mouth, face and large blood vessels. Bosentan increased stillbirths and pup mortality at oral doses 2 and 10 times the MRHD (on a mg/m 2 basis).
Although birth defects were not observed in rabbits given oral doses of up to the equivalent of 10.5 g/day in a 70 kg person, plasma concentrations of bosentan in rabbits were lower than those reached in the rat. The similarity of malformations induced by bosentan and those observed in endothelin-1 knockout mice and in animals treated with other endothelin receptor antagonists indicates that embryo-fetal toxicity is a class effect of these drugs.
🧒 Pediatric Use ▾
8.4Pediatric Use The efficacy of bosentan in patients <18 years is supported by data from an uncontrolled trial in which 19 pediatric patients were treated with bosentan. In this study, cardiopulmonary hemodynamic improvements were similar to those seen in adults treated with bosentan [see Clinical Studies (14.1) ] . Safety in pediatric patients is supported by data from 100 pediatric patients treated with bosentan for a median of 17 months [see Adverse Reactions (6.1) , Clinical Studies (14.1) ] .
Juvenile Animal Toxicity Data In a juvenile rat toxicity study, rats were treated from Day 4 postpartum to adulthood (Day 69 postpartum). Decreased body weights, absolute weights of testes and epididymides, and reduced number of sperm in epididymides were observed after weaning. No effect on testis histology or sperm morphology and function was seen.
The NOAEL was 4 times (at Day 4 postpartum) and 2 times (Day 69 postpartum) the human therapeutic exposure, respectively. No effects on general development, sensory, cognitive function and reproductive performance were detected at the highest dose tested in juvenile rats, 7 times the therapeutic exposure in children with PAH.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of bosentan did not include sufficient numbers of subjects aged 65 and older to determine whether they respond differently from younger subjects.
🆘 Overdosage ▾
10 OVERDOSAGE Bosentan has been given as a single dose of up to 2,400 mg in normal volunteers, or up to 2,000 mg/day for 2 months in patients, without any major clinical consequences. The most common side effect was headache of mild to moderate intensity. In the cyclosporine A interaction study, in which doses of 500 and 1,000 mg twice daily of bosentan were given concomitantly with cyclosporine A, trough plasma concentrations of bosentan increased 30-fold, resulting in severe headache, nausea, and vomiting, but no serious adverse events.
Mild decreases in blood pressure and increases in heart rate were observed. In the postmarketing period, there was one reported overdose of 10,000 mg of bosentan taken by an adolescent male patient. He had symptoms of nausea, vomiting, hypotension, dizziness, sweating, and blurred vision.
He recovered within 24 hours with blood pressure support. Bosentan is unlikely to be effectively removed by dialysis due to the high molecular weight and extensive plasma protein binding.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Bosentan is a specific and competitive antagonist at endothelin receptor types ET A and ET B . Bosentan has a slightly higher affinity for ET A receptors than for ET B receptors. The clinical impact of dual endothelin blockage is unknown.
Endothelin-1 (ET-1) is a neurohormone, the effects of which are mediated by binding to ET A and ET B receptors in the endothelium and vascular smooth muscle. ET-1 concentrations are elevated in plasma and lung tissue of patients with PAH, suggesting a pathogenic role for ET-1 in this disease.
12.3Pharmacokinetics General After oral administration, maximum plasma concentrations of bosentan are attained within 3 to 5 hours and the terminal elimination half-life is about 5 hours in healthy adult subjects. The exposure to bosentan after intravenous and oral administration is about twice as high in adult patients with PAH as it is in healthy adult subjects. In a relative bioavailability study in healthy adults, the peak plasma concentration and area under the plasma concentration-time curve for bosentan are on an average 14% and 11%, respectively, lower following administration of the oral dispersible tablet compared to the film-coated tablet.
Absorption The absolute bioavailability of bosentan in normal volunteers is about 50% and is unaffected by food. Bosentan is highly bound (>98%) to plasma proteins, mainly albumin. Bosentan does not penetrate into erythrocytes.
The volume of distribution is about 18 L. Elimination Metabolism Bosentan has three metabolites, one of which is pharmacologically active and may contribute 10% to 20% of the effect of bosentan. Bosentan is an inducer of CYP2C9 and CYP3A and possibly also of CYP2C19.
Upon multiple oral dosing, plasma concentrations in healthy adults decrease gradually to 50% to 65% of those seen after single dose administration, probably the effect of auto-induction of the metabolizing liver enzymes. Steady-state is reached within 3 to 5 days. Excretion Bosentan is eliminated by biliary excretion following metabolism in the liver.
Less than 3% of an administered oral dose is recovered in urine. Total clearance after a single intravenous dose is about 4 L/h in patients with PAH. Specific Populations Pediatrics The average plasma exposure to bosentan at steady state (AUC ss ) in pediatric patients with PAH aged 3 to 15 years treated with 31.25, 62.5 or 125 mg (approximately 2 mg/kg) film-coated tablet twice daily is 37% lower than that observed in adult patients with PAH receiving 125 mg film-coated tablet twice daily.
Following administration of 4 mg/kg twice daily doses of dispersible tablet in patients with PAH aged 2 to 11 years, the average systemic exposure to bosentan at steady state is similar to that observed with 2 mg/kg. The average exposure to bosentan in these pediatric patients was approximately half the exposure in adult patients treated with 125 mg film-coated tablets twice daily. The exposure to bosentan at 2 mg/kg three times daily dosing of dispersible tablet is similar to that of 2 mg/kg twice daily dosing in patients with PAH aged 3 months to 12 years.
Based on these findings, exposure to bosentan reaches a plateau at lower doses in pediatric patients than in adults, and doses higher than 2 mg/kg twice daily do not increase the exposure to bosentan in pediatric patients. Hepatic Impairment In vitro and in vivo evidence showing extensive hepatic metabolism of bosentan suggests that liver impairment could significantly increase exposure to bosentan. In a study comparing 8 patients with mild liver impairment (Child-Pugh Class A) to 8 controls, the single- and multiple-dose pharmacokinetics of bosentan were not altered in patients with mild hepatic impairment.
In another small (N=8) pharmacokinetic study, the steady-state AUC of bosentan was on average 4.7 times higher and the active metabolite Ro 48-5033 was 12.4 times higher in 5 patients with moderately impaired liver function (Child… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Bosentan is a specific and competitive antagonist at endothelin receptor types ET A and ET B . Bosentan has a slightly higher affinity for ET A receptors than for ET B receptors. The clinical impact of dual endothelin blockage is unknown.
Endothelin-1 (ET-1) is a neurohormone, the effects of which are mediated by binding to ET A and ET B receptors in the endothelium and vascular smooth muscle. ET-1 concentrations are elevated in plasma and lung tissue of patients with PAH, suggesting a pathogenic role for ET-1 in this disease.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Bosentan Tablets are available as follows: 62.5 mg – Light orange, round, biconvex, film-coated tablets, debossed with ‘WPI’ on one side and ‘62.5’ on the other side contains 64.541 mg of bosentan monohydrate, equivalent to 62.5 mg of bosentan base. Tablets are supplied in bottles of 60 (NDC 0591-2511-60) with a child-resistant closure. 125 mg – Light orange, oval, biconvex, film-coated tablets, debossed with ‘WPI’ on one side and ‘125’ on the other side contains 129.082 mg of bosentan monohydrate, equivalent to 125 mg of bosentan base.
Tablets are supplied in bottles of 60 (NDC 0591-2512-60) with a child-resistant closure. Store at 20°C to 25°C (68°F to 77°F); excursions are permitted between 15°C and 30°C (59°F and 86°F) [see USP Controlled Room Temperature]. Dispense in a tight, light-resistant container as defined in the USP.
Keep this and all medications out of the reach of children.
📋 Description ▾
11 DESCRIPTION Bosentan, an endothelin receptor antagonist that belongs to a class of highly substituted pyrimidine derivatives, with no chiral centers. It is designated chemically as 4-tert-butyl-N-[6-(2-hydroxy-ethoxy)-5-(2-methoxy-phenoxy)-[2,2´]-bipyrimidin-4-yl]-benzenesulfonamide monohydrate and has the following structural formula: C 27 H 29 N 5 O 6 S•H 2 O M.W. 569.64 Bosentan is a white to yellowish powder.
It is poorly soluble in water (1.0 mg/100 mL) and in aqueous solutions at low pH (0.1 mg/100 mL at pH 1.1 and 4.0; 0.2 mg/100 mL at pH 5.0). Solubility increases at higher pH values (43 mg/100 mL at pH 7.5). In the solid state, bosentan is very stable, is not hygroscopic and is not light sensitive.
Bosentan is available as 62.5 mg and 125 mg film-coated tablets for oral administration, and contains the following excipients: corn starch, ethyl cellulose, glyceryl behenate, hypromellose, iron oxide red, iron oxide yellow, magnesium stearate, pregelatinized corn starch, povidone K90, sodium starch glycolate, titanium dioxide and triacetin. Each bosentan 62.5 mg tablet contains 64.541 mg of bosentan monohydrate, equivalent to 62.5 mg of bosentan base. Each bosentan 125 mg tablet contains 129.082 mg of bosentan monohydrate, equivalent to 125 mg of bosentan base.
1
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide) Restricted Access Advise the patient that bosentan tablets are only available through a restricted access program called the Bosentan REMS and that bosentan is available only from certified pharmacies enrolled in the Bosentan REMS. As a component of the Bosentan REMS, prescribers must review the contents of the Bosentan Medication Guide with the patient before initiating bosentan tablets and patients must sign the Patient Enrollment Form to confirm that they understand the risks of bosentan.
Instruct patients that the risks associated with bosentan tablets include hepatotoxicity. Discuss with the patient the requirement to measure serum aminotransferases monthly [see D osage and Administration ( 2.1 , 2.4 ), Warnings and Precautions ( 5.1 , 5.2 )]. Embryo-Fetal toxicity Counsel female patients of reproductive potential about the need to use effective contraception prior to treatment, during treatment with bosentan tablets and for one month after treatment discontinuation.
Females of reproductive potential should have a negative pregnancy test prior to treatment [see Dosage and Administration (2.1) , Warnings and Precautions (5.3) , Drug Interactions (7.2 ), Use in Specific Populations ( 8.1 , 8.3 )] . Patients should be instructed to immediately contact their physician if they suspect they may be pregnant. Patients should seek additional contraceptive advice from a gynecologist or similar expert as needed.
Educate and counsel females of reproductive potential on the use of emergency contraception in the event of unprotected sex or contraceptive failure. Advise pre-pubertal females to report any changes in their reproductive status immediately to her prescriber. Lactation Advise women not to breastfeed during treatment with bosentan tablets [see Use in Specific Populations (8.2) ] .
Infertility Advise males of reproductive potential that bosentan tablets may impair fertility [see Warnings and Precautions (5.6) , Adverse Reactions (6.1) , Use in Specific Populations (8.3) and Nonclinical Toxicology (13.1) ] . Other Risks Associated with Bosentan Tablets Instruct patients that the risks associated with bosentan tablets also include the following: Decreases in hemoglobin and hematocrit – advise patients of the importance of hemoglobin testing, Decreases in sperm count, Fluid retention. Manufactured In India By: Watson Pharma Private Limited Verna, Salcette Goa 403 722 India Manufactured For: Teva Pharmaceuticals Parsippany, NJ 07054 Rev.
E 11/2025
💬 Medication Guide ▾
MEDICATION GUIDE Bosentan (boe sen' tan) Tablets Read the Medication Guide that comes with bosentan tablets before you start taking it and each time you get a refill. There may be new information. This Medication Guide does not take the place of talking with your healthcare provider about your medical condition or your treatment.
What is the most important information I should know about bosentan tablets? Bosentan tablets can cause serious side effects including: Liver damage. Liver damage may not cause symptoms at first.
Only a blood test can show if you have early liver damage. You must have your blood tested to check your liver function before you start bosentan tablets and each month after that. Your healthcare provider will order these tests.
Regular blood tests are important because they will help your healthcare provider adjust or stop your treatment before there is permanent damage. Tell your healthcare provider if you have had liver problems, including liver problems while taking other medicines. Call your healthcare provider right away if you have any of these symptoms of liver problems while taking bosentan tablets: nausea vomiting fever unusual tiredness stomach area (abdominal) pain yellowing of the skin or the whites of your eyes (jaundice) Because of the risk for liver damage, bosentan is only available through a restricted program called the Bosentan REMS.
Before you begin taking bosentan, you must read and agree to all of the requirements of the Bosentan REMS. Serious birth defects. Bosentan tablets can cause serious birth defects if taken during pregnancy.
You should not be pregnant when you start taking bosentan tablets or during bosentan tablet treatment. Serious birth defects from bosentan tablets may happen early in pregnancy. Females who are able to get pregnant should have a negative pregnancy test before starting treatment with bosentan tablets.
Talk to your healthcare provider about your menstrual cycle. Your healthcare provider will decide when to do a pregnancy test and will order a pregnancy test for you depending on your menstrual cycle. Females who are able to get pregnant are females who: have entered puberty, even if they have not started their menstrual period, and have a uterus, and have not gone through menopause.
Menopause means that you have not had a menstrual period for at least 12 months for natural reasons, or that you have had your ovaries removed. Females who are not able to get pregnant are females who: have not yet entered puberty, or do not have a uterus, or have gone through menopause. Menopause means that you have not had a menstrual period for at least 12 months for natural reasons, or that you have had your ovaries removed or are infertile for other medical reasons and this infertility is permanent and cannot be reversed.
Females who are able to get pregnant should use effective birth control prior to starting treatment with bosentan tablets, during treatment with bosentan tablets, and for one month after stopping bosentan tablets because the medicine may still be in the body. Talk with your healthcare provider or gynecologist (a doctor who specializes in female reproduction) to find out about options for effective birth control that you may use to prevent pregnancy during treatment with bosentan tablets. If you decide that you want to change the form of birth control that you use, talk with your healthcare provider or gynecologist to be sure that you choose another acceptable form of birth control.
Do not have unprotected sex. Talk to your healthcare provider or pharmacist right away if you have unprotected sex or if you think your birth control has failed. Your healthcare provider may talk with you about using emergency birth control.
Tell your healthcare provider right away if you miss a menstrual period or think you may be pregnant. If you are the parent or caregiver of a female child who started taking bosentan tablets before reaching puberty, you should check your child… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics General After oral administration, maximum plasma concentrations of bosentan are attained within 3 to 5 hours and the terminal elimination half-life is about 5 hours in healthy adult subjects. The exposure to bosentan after intravenous and oral administration is about twice as high in adult patients with PAH as it is in healthy adult subjects. In a relative bioavailability study in healthy adults, the peak plasma concentration and area under the plasma concentration-time curve for bosentan are on an average 14% and 11%, respectively, lower following administration of the oral dispersible tablet compared to the film-coated tablet.
Absorption The absolute bioavailability of bosentan in normal volunteers is about 50% and is unaffected by food. Bosentan is highly bound (>98%) to plasma proteins, mainly albumin. Bosentan does not penetrate into erythrocytes.
The volume of distribution is about 18 L. Elimination Metabolism Bosentan has three metabolites, one of which is pharmacologically active and may contribute 10% to 20% of the effect of bosentan. Bosentan is an inducer of CYP2C9 and CYP3A and possibly also of CYP2C19.
Upon multiple oral dosing, plasma concentrations in healthy adults decrease gradually to 50% to 65% of those seen after single dose administration, probably the effect of auto-induction of the metabolizing liver enzymes. Steady-state is reached within 3 to 5 days. Excretion Bosentan is eliminated by biliary excretion following metabolism in the liver.
Less than 3% of an administered oral dose is recovered in urine. Total clearance after a single intravenous dose is about 4 L/h in patients with PAH. Specific Populations Pediatrics The average plasma exposure to bosentan at steady state (AUC ss ) in pediatric patients with PAH aged 3 to 15 years treated with 31.25, 62.5 or 125 mg (approximately 2 mg/kg) film-coated tablet twice daily is 37% lower than that observed in adult patients with PAH receiving 125 mg film-coated tablet twice daily.
Following administration of 4 mg/kg twice daily doses of dispersible tablet in patients with PAH aged 2 to 11 years, the average systemic exposure to bosentan at steady state is similar to that observed with 2 mg/kg. The average exposure to bosentan in these pediatric patients was approximately half the exposure in adult patients treated with 125 mg film-coated tablets twice daily. The exposure to bosentan at 2 mg/kg three times daily dosing of dispersible tablet is similar to that of 2 mg/kg twice daily dosing in patients with PAH aged 3 months to 12 years.
Based on these findings, exposure to bosentan reaches a plateau at lower doses in pediatric patients than in adults, and doses higher than 2 mg/kg twice daily do not increase the exposure to bosentan in pediatric patients. Hepatic Impairment In vitro and in vivo evidence showing extensive hepatic metabolism of bosentan suggests that liver impairment could significantly increase exposure to bosentan. In a study comparing 8 patients with mild liver impairment (Child-Pugh Class A) to 8 controls, the single- and multiple-dose pharmacokinetics of bosentan were not altered in patients with mild hepatic impairment.
In another small (N=8) pharmacokinetic study, the steady-state AUC of bosentan was on average 4.7 times higher and the active metabolite Ro 48-5033 was 12.4 times higher in 5 patients with moderately impaired liver function (Child-Pugh Class B) and PAH associated with portal hypertension than in 3 patients with normal liver function and PAH of other etiologies. The pharmacokinetics of bosentan have not been evaluated in patients with severe liver impairment (Child-Pugh Class C) [see Dosage and Administration (2.2) , Warnings and Precautions (5.1) , Use in Specific Populations (8.6) ] .
Renal Impairment In patients with severe renal impairment (creatinine clearance 15 to 30 mL/min), plasma concentrations of bosentan were essentially unchanged and plasma concentrations of the three metabolites were incre… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Pulmonary Arterial Hypertension WHO Functional Class III-IV Two randomized, double-blind, multi-center, placebo-controlled trials were conducted in 32 and 213 patients. The larger study (BREATHE-1) compared 2 doses (125 mg twice daily and 250 mg twice daily) of bosentan with placebo. The smaller study (Study 351) compared 125 mg twice daily with placebo.
Patients had severe (WHO functional Class III–IV) PAH: idiopathic or heritable PAH (72%) or PAH associated with scleroderma or other connective tissue diseases (21%), or to autoimmune diseases (7%). There were no patients with PAH associated with other conditions such as HIV disease or recurrent pulmonary emboli. In both studies, bosentan or placebo was added to patients’ current therapy, which could have included a combination of digoxin, anticoagulants, diuretics, and vasodilators (e.g., calcium channel blockers, ACE inhibitors), but not epoprostenol.
Bosentan was given at a dose of 62.5 mg twice daily for 4 weeks and then at 125 mg twice daily or 250 mg twice daily for either 12 (BREATHE-1) or 8 (Study 351) additional weeks. The primary study endpoint was 6-minute walk distance. In addition, symptoms and functional status were assessed.
Hemodynamic measurements were made at 12 weeks in Study 351. The mean age was about 49 years. About 80% of patients were female, and about 80% were Caucasian.
Patients had been diagnosed with pulmonary hypertension for a mean of 2.4 years. Submaximal Exercise Ability Results of the 6-minute walk distance at 3 months (Study 351) or 4 months (BREATHE-1) are shown in Table 4. Table 4: Effects of bosentan on 6-Minute Walk Distance BREATHE-1 Study 351 Bosentan Bosentan Placebo Bosentan Placebo 125 mg twice daily 250 mg twice daily 125 mg twice daily (n=74) (n=70) (n=69) (n=21) (n=11) Baseline 326 ± 73 333 ± 75 344 ± 76 360 ± 86 355 ± 82 End point 353 ± 115 379 ± 101 336 ± 129 431 ± 66 350 ± 147 Change from baseline 27 ± 75 46 ± 62 -8 ± 96 70 ± 56 -6 ± 121 Placebo – subtracted 35 (a) 54 (b) 76 (c) Distance in meters: mean ± standard deviation.
Changes are to week 16 for BREATHE-1 and to week 12 for Study 351. (a) p=0.01; by Wilcoxon; (b) p=0.0001; by Wilcoxon; (c) p=0.02; by Student’s t-test. In both trials, treatment with bosentan resulted in a significant increase in exercise ability.
The improvement in walk distance was apparent after 1 month of treatment (with 62.5 mg twice daily) and fully developed by about 2 months of treatment (Figure 5). It was maintained for up to 7 months of double-blind treatment. Walking distance was somewhat greater with 250 mg twice daily, but the potential for increased hepatotoxicity causes this dose not to be recommended [see Dosage and Administration (2.2) ] .
There were no apparent differences in treatment effects on walk distance among subgroups analyzed by demographic factors, baseline disease severity, or disease etiology, but the studies had little power to detect such differences. Figure 5. Mean Change in 6-min Walk Distance (BREATHE-1) Change from baseline in 6-minute walking distance from start of therapy to week 16 in the placebo and combined bosentan (125 mg twice daily and 250 mg twice daily) groups.
Values are expressed as mean ± standard error of the mean. Hemodynamic Changes Invasive hemodynamic parameters were assessed in Study 351. Treatment with bosentan led to a significant increase in cardiac index (CI) associated with a significant reduction in pulmonary artery pressure (PAP), pulmonary vascular resistance (PVR), and mean right atrial pressure (RAP) (Table 5).
The relationship between hemodynamic effects and improvements in 6-minute walk distance is unknown. Table 5: Change from Baseline to Week 12: Hemodynamic Parameters Bosentan 125 mg twice daily Placebo CI (L/min/m 2 ) n=20 n=10 Baseline 2.35±0.73 2.48±1.03 Absolute Change 0.50±0.46 -0.52±0.48 Treatment Effect 1.02 (a) Mean PAP (mmHg) n=20 n=10 Baseline 53.7±13.4 55.7±10.5 Absolute Change -1.6±5.1 5.1±8.8 Treatmen… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis and Mutagenesis Two years of dietary administration of bosentan to mice produced an increased incidence of hepatocellular adenomas and carcinomas in males at doses as low as 450 mg/kg/day (about 8 times the maximum recommended human dose [MRHD] of 125 mg twice daily, on a mg/m 2 basis). In the same study, doses greater than 2,000 mg/kg/day (about 32 times the MRHD) were associated with an increased incidence of colon adenomas in both males and females.
In rats, dietary administration of bosentan for two years was associated with an increased incidence of brain astrocytomas in males at doses as low as 500 mg/kg/day (about 16 times the MRHD). In a comprehensive battery of in vitro tests (the microbial mutagenesis assay, the unscheduled DNA synthesis assay, the V-79 mammalian cell mutagenesis assay, and human lymphocyte assay) and an in vivo mouse micronucleus assay, there was no evidence for any mutagenic or clastogenic activity of bosentan. Impairment of Fertility/Testicular Function The development of testicular tubular atrophy and impaired fertility has been linked with the chronic administration of certain endothelin receptor antagonists in rodents.
Treatment with bosentan at oral doses of up to 1,500 mg/kg/day (50 times the MRHD on a mg/m 2 basis) or intravenous doses up to 40 mg/kg/day had no effects on sperm count, sperm motility, mating performance or fertility in male and female rats. An increased incidence of testicular tubular atrophy was observed in rats given bosentan orally at doses as low as 125 mg/kg/ day (about 4 times the MRHD and the lowest doses tested) for two years but not at doses as high as 1,500 mg/kg/day (about 50 times the MRHD) for 6 months.
Effects on sperm count and motility were evaluated only in the much shorter duration fertility studies in which males had been exposed to the drug for 4 to 6 weeks. An increased incidence of tubular atrophy was not observed in mice treated for 2 years at doses up to 4,500 mg/kg/day (about 75 times the MRHD) or in dogs treated up to 12 months at doses up to 500 mg/kg/day (about 50 times the MRHD).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis and Mutagenesis Two years of dietary administration of bosentan to mice produced an increased incidence of hepatocellular adenomas and carcinomas in males at doses as low as 450 mg/kg/day (about 8 times the maximum recommended human dose [MRHD] of 125 mg twice daily, on a mg/m 2 basis). In the same study, doses greater than 2,000 mg/kg/day (about 32 times the MRHD) were associated with an increased incidence of colon adenomas in both males and females.
In rats, dietary administration of bosentan for two years was associated with an increased incidence of brain astrocytomas in males at doses as low as 500 mg/kg/day (about 16 times the MRHD). In a comprehensive battery of in vitro tests (the microbial mutagenesis assay, the unscheduled DNA synthesis assay, the V-79 mammalian cell mutagenesis assay, and human lymphocyte assay) and an in vivo mouse micronucleus assay, there was no evidence for any mutagenic or clastogenic activity of bosentan. Impairment of Fertility/Testicular Function The development of testicular tubular atrophy and impaired fertility has been linked with the chronic administration of certain endothelin receptor antagonists in rodents.
Treatment with bosentan at oral doses of up to 1,500 mg/kg/day (50 times the MRHD on a mg/m 2 basis) or intravenous doses up to 40 mg/kg/day had no effects on sperm count, sperm motility, mating performance or fertility in male and female rats. An increased incidence of testicular tubular atrophy was observed in rats given bosentan orally at doses as low as 125 mg/kg/ day (about 4 times the MRHD and the lowest doses tested) for two years but not at doses as high as 1,500 mg/kg/day (about 50 times the MRHD) for 6 months.
Effects on sperm count and motility were evaluated only in the much shorter duration fertility studies in which males had been exposed to the drug for 4 to 6 weeks. An increased incidence of tubular atrophy was not observed in mice treated for 2 years at doses up to 4,500 mg/kg/day (about 75 times the MRHD) or in dogs treated up to 12 months at doses up to 500 mg/kg/day (about 50 times the MRHD).
📄 Recent Major Changes ▾
Boxed Warning 11/2025 Boxed Warning 11/2025 Dosage and Administration (2.1) 11/2025 Contraindications (4.1) 11/2025 Warnings and Precautions (5.1, 5.2, 5.3) 11/2025
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 0591-2511-60 Bosentan Tablets 62.5 mg PHARMACIST: Dispense the accompanying Medication Guide to each patient. Rx only 60 Tablets Label 62_5 mg, 60
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 0591-2512-60 Bosentan Tablets 125 mg PHARMACIST: Dispense the accompanying Medication Guide to each patient. Rx only 60 Tablets Label 125 mg, 601
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |