
Sunitinib Malate 37.5 mg Capsule, 28-count — NDC 43598-047-28 (Billing 43598-0047-28)
This is a package of 28 capsules of Sunitinib Malate 37.5 mg Capsule from Dr.Reddys Laboratories Inc, marketed since Nov 2022 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 43598-047-28 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 43598 labeler · 047 product · 28 package
- Package marketed since
- Nov 30, 2022
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC)
- 0343598048635, 0343598046631, 0343598045634, 0343598047638
- FDA record last changed
- Jul 24, 2026
Other active recalls for Sunitinib Malate (different manufacturers) — 2 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 071671
- GCN: 35596
- GPI-14 (Medi-Span): 21533070300135
- HICL (First Databank): 033445
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 616279
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Sunitinib is used to treat gastrointestinal stromal tumors (GIST; a type of tumor that grows in the stomach, intestine (bowel), or esophagus (tube that connects the throat with the stomach) in people with tumors that were not treated successfully with imatinib (Gleevec) or people who cannot take imatinib. Sunitinib is also used to treat advanced renal cell carcinoma (RCC, a type of cancer that begins in the cells of the kidneys). Sunitinib is also used to help prevent the return of RCC in people who have RCC that has not spread and have had a kidney removed. Sunitinib is also used to treat pan...
Read the full MedlinePlus article ↗- Sunitinib treats certain cancers in adults. These are GIST after imatinib, advanced kidney cancer (renal cell carcinoma), kidney cancer at high risk of coming back after surgery, a...
- Take your capsule by mouth once a day, with or without food. For some cancers you take it for 4 weeks and then stop for 2 weeks. For others it is daily with no break. Follow your p...
- Tiredness, diarrhea, nausea, mouth sores, loss of appetite, altered taste, and sore palms and soles are common. High blood pressure and nosebleeds or other bleeding can also occur....
- Call if you notice yellow skin or eyes, dark urine, chest pain, shortness of breath, swelling, fainting, serious bleeding, severe skin blistering or peeling, or a severe headache w...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $76.85 | $2,151.82 / 28 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 43598-0047-28 You're viewing this Main listing | 4 BLISTER PACK in 1 CARTON / 7 CAPSULE in 1 BLISTER PACK | 2022-11-30 | — | Active |
| 43598-0047-63 43598-047-63 | 28 CAPSULE in 1 BOTTLE | 2022-11-30 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 43598-0047-63?
What NDC number is used to bill for this package of Sunitinib Malate 37.5 mg Capsule?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sutent 37.5 mg 00069-0830-38 | Pfizer | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mg 00093-8229-28 | Teva | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mg 00378-6681-28 | Mylan | 28 capsules | — | AB | FDA listed | — |
| Sunitinib malate 37.5 mg 16714-0678-01 | NorthStar | 28 capsules | — | AB | Discontinued | — |
| Sunitinib Malate 37.5 mg 42291-0903-28 | AvKARE | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mgthis 43598-0047-28 | Dr.Reddys | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mg 59651-0466-28 | Aurobindo | 28 capsules | — | AB | FDA listed | — |
| Sunitinib malate 37.5 mg 63304-0093-27 | Sun | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mg 72205-0118-28 | Novadoz | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mg 82293-0016-10 | Novugen | 28 capsules | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Dr.Reddys Laboratories Inc labeler code 43598
- Fluphenazine Hydrochloride 2.5 mg Tablet, Film Coated NDC 43598-035-01
- Fluphenazine Hydrochloride 5 mg Tablet, Film Coated NDC 43598-036-01
- Fluphenazine Hydrochloride 10 mg Tablet, Film Coated NDC 43598-037-01
- Docosanol 100 mg/g Cream NDC 43598-044-02
- Sunitinib Malate 12.5 mg Capsule NDC 43598-045-28
- Sunitinib Malate 25 mg Capsule NDC 43598-046-28
- Sunitinib Malate 50 mg Capsule NDC 43598-048-28
- Thiamine Hydrochloride 100 mg/mL Injection, Solution NDC 43598-050-25
- Calcitonin Salmon 200 [USP'U]/mL Injection, Solution NDC 43598-051-11
- Acetaminophen 250 mg and Ibuprofen 125 125 mg; 250 mg Tablet, Film Coated NDC 43598-052-05
- Desmopressin Acetate 4 ug/mL Injection, Solution NDC 43598-053-11
- Nilotinib 50 mg Capsule NDC 43598-055-04
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
BOXED WARNING SECTION WARNING: HEPATOTOXICITY Hepatotoxicity may be severe, and in some cases, fatal. Monitor hepatic function and interrupt, dose reduce, or discontinue sunitinib malate as recommended [see Warnings and Precautions ( 5.1 )]. WARNING: HEPATOTOXICITY See full prescribing information for complete boxed warning.
Hepatotoxicity may be severe, and in some cases fatal. Monitor hepatic function and interrupt, dose reduce, or discontinue sunitinib malate as recommended [ see Warnings and Precautions ( 5.1 )] .
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Sunitinib malate is a kinase inhibitor indicated for: treatment of adult patients with gastrointestinal stromal tumor (GIST) after disease progression on or intolerance to imatinib mesylate. ( 1.1 ) treatment of adult patients with advanced renal cell carcinoma (RCC). ( 1.2 ) adjuvant treatment of adult patients at high risk of recurrent RCC following nephrectomy.
( 1.3 ) treatment of progressive, well-differentiated pancreatic neuroendocrine tumors (pNET) in adult patients with unresectable locally advanced or metastatic disease. ( 1.4 )
1.1Gastrointestinal Stromal Tumor Sunitinib malate capsules are indicated for the treatment of adult patients with gastrointestinal stromal tumor (GIST) after disease progression on or intolerance to imatinib mesylate.
1.2Advanced Renal Cell Carcinoma Sunitinib malate capsules are indicated for the treatment of adult patients with advanced renal cell carcinoma (RCC).
1.3Adjuvant Treatment of Renal Cell Carcinoma Sunitinib malate capsules are indicated for the adjuvant treatment of adult patients at high risk of recurrent RCC following nephrectomy.
1.4Advanced Pancreatic Neuroendocrine Tumors Sunitinib malate capsules are indicated for the treatment of progressive, well-differentiated pancreatic neuroendocrine tumors (pNET) in adult patients with unresectable locally advanced or metastatic disease.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION GIST and Advanced RCC: • The recommended dosage is 50 mg orally once daily for the first 4 weeks of each 6-week cycle (Schedule 4/2). ( 2.1 ) Adjuvant Treatment of RCC: • The recommended dosage is 50 mg orally once daily for the first 4 weeks of a 6-week cycle (Schedule 4/2) for a maximum of 9 cycles. ( 2.2 ) pNET: • The recommended dosage is 37.5 mg orally once daily. ( 2.3 )
2.1Recommended Dosage for GIST and Advanced RCC The recommended dosage of sunitinib malate for gastrointestinal stromal tumor (GIST) and advanced renal cell carcinoma (RCC) is 50 mg taken orally once daily, on a schedule of 4 weeks on treatment followed by 2 weeks off (Schedule 4/2) until disease progression or unacceptable toxicity. Sunitinib malate capsules may be taken with or without food.
2.2Recommended Dosage for Adjuvant Treatment of RCC The recommended dosage of sunitinib malate for the adjuvant treatment of RCC is 50 mg taken orally once daily, on a schedule of 4 weeks on treatment followed by 2 weeks off (Schedule 4/2), for nine 6-week cycles. Sunitinib malate capsules may be taken with or without food.
2.3Recommended Dosage for pNET The recommended dosage of sunitinib malate for pancreatic neuroendocrine tumors (pNET) is 37.5 mg taken orally once daily until disease progression or unacceptable toxicity. Sunitinib malate capsules may be taken with or without food.
2.4Dosage Modifications for Adverse Reactions To manage adverse reactions, the recommended dosage modifications are provided in Table 1. Table 2 provides the recommended dosage reductions of sunitinib malate capsules for adverse reactions. Table 1.
Recommended Dosage Reductions of Sunitinib Malate for Adverse Reactions Indications GIST RCC pNET Advanced RCC Adjuvant RCC First dose reduction 37.5 mg once daily 37.5 mg once daily 37.5 mg once daily 25 mg once daily Second dose reduction 25 mg once daily 25 mg once daily NA NA Table 2. Recommended Dosage Modifications for Sunitinib Malate for Adverse Reactions Adverse Reaction Severity Dosage Modifications for Sunitinib Malate Hepatotoxicity [see Warnings and Precautions (5.1 )] Grade 3 • Withhold until resolution to Grade 0 to 1 or baseline. • Resume at a reduced dose. • For recurring Grade 3 permanently discontinue.
Grade 4 • Permanently discontinue. Cardiovascular events[see Warnings and Precautions ( 5.2 )] Asymptomatic cardiomyopathy (left ventricular ejection fraction greater than 20% but less than 50% below baseline or below the lower limit of normal if baseline was not obtained) • Withhold until resolution to Grade 0 to 1 or baseline. • Resume at reduced dose. Clinically manifested congestive heart failure(CHF) • Permanently discontinue.
Hypertension [see Warnings and Precautions ( 5.4) ] Grade 3 • Withhold until resolution to Grade 0 to 1 or baseline. • Resume at a reduced dose. Grade 4 • Permanently discontinue. Hemorrhagic events [see Warnings and Precautions (5.5)] Grade 3 or4 • Withhold until resolution to Grade 0 to 1 or baseline. • Either resume at a reduced dose or discontinue depending on the severity andpersistence of adverse reaction.
Thrombotic microangiopathy [see Warnings and Precautions (5. 7 )] Any Grade • Permanently discontinue. Proteinuria or Nephrotic syndrome [see Warnings and Precautions ( 5.8 )] 3 or more gramsproteinuria in 24 hours in theabsence of nephrotic syndrome • Withhold until resolution to Grade 0 to 1 or baseline. • Resume at a reduced dose.
Nephrotic syndrome or recurrent proteinuria of 3 or more grams per24 hoursdespite dose reductions • Permanently discontinue. Dermatological toxicities Erythema multiforme (EM), Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), Necrotizing fasciitis [seeWarnings and Precautions( 5.9) ] Any Grade • Permanently discontinue. Reversible posterior leukoencephalopathy syndrome [see Warnings and Precautions ( 5.10 )] Any Grade • Permanently discontinue.
Osteonecrosis of the jaw [see Warnings and Precautions ( 5.13 )] An… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules, hard gelatin: 12.5 mg sunitinib: warm grey colored cap and warm grey colored body, printed with white imprinting ink “SC” on the cap and “12.5 mg” on the body. 25 mg sunitinib: black colored cap and black colored body, printed with white Imprinting ink “SC” on the cap and “25 mg” on the body. 37.5 mg sunitinib: black colored cap and grey colored body, printed with white imprinting ink “SC” on the cap and “37.5 mg” on the body.
50 mg sunitinib: grey colored cap and grey colored body, printed with white imprinting ink “SC” on the cap and “50 mg” on the body. Capsules: 12.5 mg, 25 mg, 37.5 mg, 50 mg sunitinib ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hepatotoxicity: Fatal liver failure has been observed. Monitor liver function tests at baseline, during each cycle, and as clinically indicated. Interrupt sunitinib malate for Grade 3 hepatotoxicity until resolution to Grade ≤1 or baseline and resume sunitinib malate at a reduced dose; discontinue if no resolution.
Discontinue sunitinib malate in patients with Grade 4 hepatoxicity, in patients who have subsequent severe changes in liver function tests or other signs and symptoms of liver failure. (2.4 , 5.1 ) Cardiovascular Events: Myocardial ischemia, myocardial infarction, heart failure, cardiomyopathy, and decreased left ventricular ejection fraction (LVEF) to below the lower limit of normal including death have occurred. Monitor for signs and symptoms of congestive heart failure and consider monitoring LVEF at baseline and periodically during treatment.
Discontinue sunitinib malate for clinical manifestations of congestive heart failure. Interrupt and/or dose reduce for decreased LVEF. ( 5.2 ) QT Interval Prolongation and Torsade de Pointes: Monitor patients at higher risk for developing QT interval prolongation.
Consider monitoring of electrocardiograms and electrolytes. ( 5.3 ) Hypertension: Monitor blood pressure at baseline and as clinically indicated. Initiate and/or adjust antihypertensive therapy as appropriate.
Interrupt. sunitinib malate for Grade 3 hypertension until resolution to Grade ≤1 or baseline, then resume sunitinib malate at a reduced dose. Discontinue sunitinib malate in patients who develop Grade 4 hypertension. ( 5.4 ) Hemorrhagic Events: Tumor-related hemorrhage and viscus perforation (both with fatal events) have occurred.
Perform serial complete blood counts and physical examinations. Interrupt sunitinib malate for Grade 3 or 4 hemorrhagic events until resolution to Grade ≤1 or baseline, then resume at a reduced dose; discontinue if no resolution. ( 5.5 ).
Tumor Lysis Syndrome (TLS): TLS (some fatal) has been reported primarily in patients with RCC and GIST. Monitor these patients and treat as clinically indicated. ( 5.6 ) Thrombotic microangiopathy (TMA): TMA, including thrombotic thrombocytopenic purpura and hemolytic uremic syndrome, sometimes leading to renal failure or a fatal outcome, has been reported.
Discontinue sunitinib malate for TMA. ( 5.7 ) Proteinuria: Renal failure or a fatal outcome has occurred. Monitor urine protein.
Interrupt treatment for 24-hour urine protein of 3 or more grams. Discontinue for repeat episodes of 24-hour urine protein of 3 or more grams despite dose reductions or nephrotic syndrome. ( 5.8 ) Dermatologic Toxicities: Necrotizing fasciitis, erythema multiforme, Stevens-Johnson syndrome (SJS), and toxic epidermal necrolysis (TEN) (some fatal) have occurred.
Discontinue sunitinib malate for these events. ( 5.9 ) Reversible Posterior Leukoencephalopathy Syndrome (RPLS): RPLS (some fatal) has been reported. Monitor for signs and symptoms of RPLS.
Withhold sunitinib malate until resolution. ( 5.10 ) Thyroid Dysfunction: Monitor thyroid function at baseline, periodically during treatment, and as clinically indicated. Initiate and/or adjust therapy for thyroid dysfunction as appropriate.
( 5.11 ) Hypoglycemia: Check blood glucose levels regularly and assess if antidiabetic drug dose modifications are required. ( 5.12 ) Osteonecrosis of the Jaw (ONJ): Withhold sunitinib malate for at least 3 weeks prior to invasive dental procedure and for development of ONJ until complete resolution. ( 5.13 )Impaired Wound Healing: Withhold sunitinib malate for at least 3 weeks prior to elective surgery.
Do not administer for at least 2 weeks following major surgery and until adequate wound healing. The safety of resumption of sunitinib malate after resolution of wound healing complications has not been established. ( 5.14 ) Embryo-Fetal Toxicity: Can cause fetal harm.
Advise patients of potential risk to a fetus and to use effective contraception. ( 5.15 , 8.… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling. Hepatotoxicity [see Warnings and Precautions ( 5.1 )] Cardiovascular Events [see Warnings and Precautions ( 5.2 )] QT Interval Prolongation and Torsade de Pointes [see Warnings and Precautions ( 5.3 )] Hypertension [ see Warnings and Precautions ( 5.4 ) ] Hemorrhagic Events [ see Warnings and Precautions ( 5.5 )] Tumor Lysis Syndrome [see Warnings and Precautions ( 5.6 ) ] Thrombotic Microangiopathy [ see Warnings and Precautions ( 5.7 ) ] Proteinuria [ see Warnings and Precautions ( 5.8 )] Dermatologic Toxicities [ see Warnings and Precautions ( 5.9) ] Reversible Posterior Leukoencephalopathy Syndrome [ see Warnings and Precautions ( 5.10) ] Thyroid Dysfunction [ see Warnings and Precautions (5.11) ] Hypoglycemia [ see Warnings and Precautions ( 5.12 ) ] Osteonecrosis of the Jaw [ see Warnings and Precautions ( 5.13 )] Impaired Wound Healing [ see Warnings and Precautions ( 5.14 ) ] The most common adverse reactions (≥25%) are fatigue/asthenia, diarrhea, mucositis/stomatitis, nausea, decreased appetite/anorexia, vomiting, abdominal pain, hand-foot syndrome, hypertension, bleeding events, dysgeusia/altered taste, dyspepsia, and thrombocytopenia.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Dr. Reddy’s Laboratories Inc., at 1-888-375-3784 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The pooled safety population described in the Warnings and Precautions reflect exposure to sunitinib malate in 7527 patients with GIST, RCC (advanced and adjuvant), or pNET. In this pooled safety population, the most common adverse reactions (≥25%) were fatigue/asthenia, diarrhea, mucositis/stomatitis, nausea, decreased appetite/anorexia, vomiting, abdominal pain, hand-foot syndrome, hypertension, bleeding events, dysgeusia/altered taste, dyspepsia, and thrombocytopenia.
Gastrointestinal Stromal Tumor The safety of sunitinib malate was evaluated in Study 1, a randomized, double-blind, placebo-controlled trial in which previously treated patients with GIST received sunitinib malate 50 mg daily on Schedule 4/2 (n=202) or placebo (n=102). Median duration of blinded study treatment was 2 cycles for patients on sunitinib malate (mean: 3; range: 1 to 9) and 1 cycle (mean; 1.8; range: 1 to 6) for patients on placebo at the time of the interim analysis. Permanent discontinuation due to an adverse reaction occurred in 7% of patients in the sunitinib malate arm.
Dose reductions occurred in 11% and dose interruptions occurred in 29% of patients who received sunitinib malate. Table 3 summarizes the adverse reactions for Study 1. Table 3.
Adverse Reactions Reported in ≥10% of GIST Patients Who Received Sunitinib Malate in the Double-Blind Treatment Phase and More Commonly Than in Patients Given Placebo* in Study 1 Adverse Reaction GIST Sunitinib Malate (N=202) Placebo (N=102) All Grades % Grade 3 to 4 % All Grades % Grade 3 to 4 % Any Adverse Reaction 94 56 97 51 Gastrointestinal Diarrhea Mucositis/stomatitis Constipation 40 29 20 4 1 0 27 18 14 0 2 2 Metabolism/Nutrition Anorexia a Asthenia 33 22 1 5 29 11 5 3 Dermatology Skin discoloration Rash Hand-foot syndrome 30 14 14 0 1 4 23 9 10 0 0 3 Neurology Altered taste 21 0 12 0 Cardiac Hypertension 15 4 11 0 Musculoskeletal Myalgia/limb pain 14 1 9 1 * Common Terminology Criteria for Adverse Events (CTCAE), version 3.
Abbreviations: GIST=gastrointestinal stromal tumor; N=number of patients. a Includes decreased appetite. Other clinically relevant adverse reactions included oral pain other than mucositis/stomatitis in 6%; hair color changes in 7%; alopecia in 5% of patients who received sunitinib ma… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CYP3A4 Inhibitors: Consider dose reduction of sunitinib malate when administered with strong CYP3A4 inhibitors. ( 7.1 ) CYP3A4 Inducers: Consider dose increase of sunitinib malate when administered with strong CYP3A4 inducers. ( 7.1 )
7.1Effect of Other Drugs on Sunitinib Malate Strong CYP3A4 InhibitorsCo-administration with strong CYP3A4 inhibitors may increase sunitinib plasma concentrations [ see Clinical Pharmacology ( 12.3 ) ]. Select an alternate concomitant medication with no or minimal enzyme inhibition potential. Consider a dose reduction for sunitinib malate when it is co-administered with strong CYP3A4 inhibitors [ see Dosage and Administration ( 2.5) ].
Strong CYP3A4 InducersCo-administration with strong CYP3A4 inducers may decrease sunitinib plasma concentrations [ see Clinical Pharmacology ( 12.3 ) ]. Select an alternate concomitant medication with no or minimal enzyme induction potential. Consider a dose increase for sunitinib malate when it must be co-administered with CYP3A4 inducers [ see Dosage and Administration ( 2.5 ) ].
7.2Drugs that Prolong QT Interval Sunitinib malate is associated with QTc interval prolongation [ see Warnings and Precautions ( 5.3 ) , Clinical Pharmacology ( 12.2 ) ]. Monitor the QT interval with ECGs more frequently in patients who require treatment with concomitant medications known to prolong the QT interval.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk SummaryBased on animal reproduction studies and its mechanism of action, sunitinib malate can cause fetal harm when administered to a pregnant woman [ see Clinical Pharmacology ( 12.1 )] . There are no available data in pregnant women to inform a drug-associated risk. In animal developmental and reproductive toxicology studies, oral administration of sunitinib to pregnant rats and rabbits throughout organogenesis resulted in teratogenicity (embryolethality, craniofacial and skeletal malformations) at 5.5 and 0.3 times the combined AUC (the combined systemic exposure of sunitinib plus its active metabolite) in patients administered the recommended daily doses (RDD) of 50 mg, respectively (see Data).
Advise females of reproductive potential of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal DataIn a female fertility and early embryonic development study, female rats were administered oral sunitinib (0.5, 1.5, 5 mg/kg/day) for 21 days prior to mating and for 7 days after mating. Embryolethality was observed at 5 mg/kg/day (approximately 5 times the combined AUC in patients administered the RDD of 50 mg).
In embryo-fetal developmental toxicity studies, oral sunitinib was administered to pregnant rats (0.3, 1.5, 3, 5 mg/kg/day) and rabbits (0.5, 1, 5, 20 mg/kg/day) during the period of organogenesis. In rats, embryolethality and skeletal malformations of the ribs and vertebrae were observed at the dose of 5 mg/kg/day (approximately 5.5 times the combined AUC in patients administered the RDD of 50 mg). No adverse fetal effects were observed in rats at doses ≤3 mg/kg/day (approximately 2 times the combined AUC in patients administered the RDD of 50 mg).
In rabbits, embryolethality was observed at 5 mg/kg/day (approximately 3 times the combined AUC in patients administered the RDD of 50 mg), and craniofacial malformations (cleft lip and cleft palate) were observed at ≥1 mg/kg/day (approximately 0.3 times the combined AUC in patients administered the RDD of 50 mg). Sunitinib (0.3, 1, 3 mg/kg/day) was evaluated in a pre- and postnatal development study in pregnant rats. Maternal body weight gains were reduced during gestation and lactation at doses ≥1 mg/kg/day (approximately 0.5 times the combined AUC in patients administered the RDD of 50 mg).
At 3 mg/kg/day (approximately 2 times the combined AUC in patients administered the RDD of 50 mg), reduced neonate body weights were observed at birth and persisted in the offspring of both sexes during the preweaning period and in males during postweaning period. No adverse developmental effects were observed at doses ≤1 mg/kg/day
8.2Lactation There is no information regarding the presence of sunitinib and its metabolites in human milk. Sunitinib and its metabolites were excreted in rat milk at concentrations up to 12-fold higher than in plasma (see Data). Because of the potential for serious adverse reactions in breastfed infants, advise women not to breastfeed during treatment with sunitinib malate and for at least 4 weeks after the last dose.
Data Animal Data In lactating female rats administered 15 mg/kg, sunitinib and its metabolites were excreted in milk at concentrations up to 12-fold higher than in plasma.
8.3Females and Males of Reproductive Potential Sunitinib malate can cause fetal harm when administered to a pregnant woman [ see Use in Specific Populations ( 8.1) ]. Pregnancy Testing Verify pregnancy status of females of reproductive potential prior to initiating treatment with sunitinib malate. Contraception FemalesAdvi… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk SummaryBased on animal reproduction studies and its mechanism of action, sunitinib malate can cause fetal harm when administered to a pregnant woman [ see Clinical Pharmacology ( 12.1 )] . There are no available data in pregnant women to inform a drug-associated risk. In animal developmental and reproductive toxicology studies, oral administration of sunitinib to pregnant rats and rabbits throughout organogenesis resulted in teratogenicity (embryolethality, craniofacial and skeletal malformations) at 5.5 and 0.3 times the combined AUC (the combined systemic exposure of sunitinib plus its active metabolite) in patients administered the recommended daily doses (RDD) of 50 mg, respectively (see Data).
Advise females of reproductive potential of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal DataIn a female fertility and early embryonic development study, female rats were administered oral sunitinib (0.5, 1.5, 5 mg/kg/day) for 21 days prior to mating and for 7 days after mating. Embryolethality was observed at 5 mg/kg/day (approximately 5 times the combined AUC in patients administered the RDD of 50 mg).
In embryo-fetal developmental toxicity studies, oral sunitinib was administered to pregnant rats (0.3, 1.5, 3, 5 mg/kg/day) and rabbits (0.5, 1, 5, 20 mg/kg/day) during the period of organogenesis. In rats, embryolethality and skeletal malformations of the ribs and vertebrae were observed at the dose of 5 mg/kg/day (approximately 5.5 times the combined AUC in patients administered the RDD of 50 mg). No adverse fetal effects were observed in rats at doses ≤3 mg/kg/day (approximately 2 times the combined AUC in patients administered the RDD of 50 mg).
In rabbits, embryolethality was observed at 5 mg/kg/day (approximately 3 times the combined AUC in patients administered the RDD of 50 mg), and craniofacial malformations (cleft lip and cleft palate) were observed at ≥1 mg/kg/day (approximately 0.3 times the combined AUC in patients administered the RDD of 50 mg). Sunitinib (0.3, 1, 3 mg/kg/day) was evaluated in a pre- and postnatal development study in pregnant rats. Maternal body weight gains were reduced during gestation and lactation at doses ≥1 mg/kg/day (approximately 0.5 times the combined AUC in patients administered the RDD of 50 mg).
At 3 mg/kg/day (approximately 2 times the combined AUC in patients administered the RDD of 50 mg), reduced neonate body weights were observed at birth and persisted in the offspring of both sexes during the preweaning period and in males during postweaning period. No adverse developmental effects were observed at doses ≤1 mg/kg/day
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of sunitinib malate in pediatric patients have not been established. Safety and pharmacokinetics of sunitinib were assessed in an open-label study (NCT00387920) in pediatric patients 2 years to <17 years of age (n=29) with refractory solid tumors. In addition, efficacy, safety and pharmacokinetics of sunitinib was assessed in another open-label study (NCT01462695) in pediatric patients 2 years to <17 years of age (n=27) with high-grade glioma or ependymoma.
The maximum tolerated dose (MTD) normalized for body surface area (BSA) was lower in pediatric patients compared to adults. Sunitinib was poorly tolerated in pediatric patients. The occurrence of dose-limiting cardiotoxicity prompted an amendment of the NCT00387920 study to exclude patients with previous exposure to anthracyclines or cardiac radiation.
No responses were reported in patients in either of the trials. Apparent clearance and volume of distribution normalized for BSA for sunitinib and its active major metabolite were lower in pediatrics as compared to adults. The effect on open tibial growth plates in pediatric patients who received sunitinib malate has not been adequately studied.
See Juvenile Animal Toxicity Data below. Juvenile Animal Toxicity Data Physeal dysplasia was present in cynomolgus monkeys with open growth plates treated with sunitinib for ≥3 months (3 month dosing 2, 6, 12 mg/kg/day; 8 cycles of dosing 0.3, 1.5, 6 mg/kg/day) at doses that were >0.4 times the combined AUC (the combined systemic exposure of sunitinib plus its active metabolite) in patients administered the RDD of 50 mg. The no-effect level (NOEL) was 1.5 mg/kg/day in monkeys treated intermittently for 8 cycles, but was not identified in monkeys treated continuously for 3 months.
In developing rats treated continuously for 3 months (1.5, 5, and 15 mg/kg) or 5 cycles (0.3, 1.5, and 6 mg/kg/day), bone abnormalities consisted of thickening of the epiphyseal cartilage of the femur and an increase of fracture of the tibia at doses ≥5 mg/kg (approximately 10 times the combined AUC in patients administered the RDD of 50 mg). Additionally, tooth caries were present in rats at >5 mg/kg. The incidence and severity of physeal dysplasia were dose related and reversible upon cessation of treatment; however, findings in the teeth were not.
In rats, the NOEL in bones was ≤2 mg/kg/day.
🆘 Overdosage ▾
10 OVERDOSAGE Treatment of overdose with sunitinib malate should consist of general supportive measures. There is no specific antidote for overdosage with sunitinib malate. If indicated, elimination of unabsorbed drug should be achieved by emesis or gastric lavage.
Cases of accidental overdose have been reported; these cases were associated with adverse reactions consistent with the known safety profile of sunitinib malate, or without adverse reactions. In nonclinical studies, mortality was observed following as few as 5 daily doses of 500 mg/kg (3000 mg/m 2 ) in rats. At this dose, signs of toxicity included impaired muscle coordination, head shakes, hypoactivity, ocular discharge, piloerection, and gastrointestinal distress.
Mortality and similar signs of toxicity were observed at lower doses when administered for longer durations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Sunitinib is a small molecule that inhibits multiple receptor tyrosine kinases (RTKs), some of which are implicated in tumor growth, pathologic angiogenesis, and metastatic progression of cancer. Sunitinib was evaluated for its inhibitory activity against a variety of kinases (>80 kinases) and was identified as an inhibitor of platelet-derived growth factor receptors (PDGFRα and PDGFRβ), vascular endothelial growth factor receptors (VEGFR1, VEGFR2, and VEGFR3), stem cell factor receptor (KIT), Fms-like tyrosine kinase-3 (FLT3), colony stimulating factor receptor Type 1 (CSF-1R), and the glial cell-line derived neurotrophic factor receptor (RET).
Sunitinib inhibition of the activity of these RTKs has been demonstrated in biochemical and cellular assays, and inhibition of function has been demonstrated in cell proliferation assays. The primary metabolite exhibits similar potency compared to sunitinib in biochemical and cellular assays. Sunitinib inhibited the phosphorylation of multiple RTKs (PDGFRβ, VEGFR2, KIT) in tumor xenografts expressing RTK targets in vivo and demonstrated inhibition of tumor growth or tumor regression and/or inhibited metastases in some experimental models of cancer.
Sunitinib demonstrated the ability to inhibit growth of tumor cells expressing dysregulated target RTKs (PDGFR, RET, or KIT) in vitro and to inhibit PDGFRβ- and VEGFR2-dependent tumor angiogenesis in vivo .
12.2Pharmacodynamics Exposure-Response Relationship Based on population pharmacokinetic/pharmacodynamic analyses, there were relationships between changes in different pharmacodynamic endpoints (i.e., safety and efficacy endpoints) over time and sunitinib plasma exposures. Cardiac Electrophysiology Sunitinib malate can cause QT interval prolongation in a dose-dependent manner, which may lead to an increased risk for ventricular arrhythmias including Torsade de Pointes [see Warnings and Precautions (5.3)].
12.3Pharmacokinetics The pharmacokinetics of sunitinib and sunitinib malate have been evaluated in healthy subjects and in patients with solid tumors. Sunitinib AUC and Cmax increase proportionately over a dose range of 25 mg to 100 mg (0.5 to 2 times the approved RDD of 50 mg). The pharmacokinetics were similar in healthy subjects and in patients with a solid tumor, including patients with GIST and RCC.
No significant changes in the pharmacokinetics of sunitinib or the primary active metabolite were observed with repeated daily administration or with repeated cycles. With repeated daily administration, sunitinib accumulates 3- to 4-fold while the primary metabolite accumulates 7- to 10-fold. Steady-state concentrations of sunitinib and its primary active metabolite are achieved within 10 to 14 days.
By Day 14, combined plasma concentrations of sunitinib and its active metabolite ranged from 63 to 101 ng/mL. Absorption Following oral administration of sunitinib, the time to maximum plasma concentration (Tmax) ranged from 6 to 12 hours. Effect of Food The administration of a single dose of sunitinib malate 50 mg with a high-fat, high-calorie meal (consisting of approximately 150 protein calories and 500 to 600 fat calories) in healthy subjects had no clinically significant effect on sunitinib malate or active metabolites exposure.
Distribution The apparent volume of distribution (Vd/F) for sunitinib is 2230 L. Binding of sunitinib and its primary active metabolite to human plasma protein in vitro is 95% and 90%, respectively, with no concentration dependence in the range of 100 to 4000 ng/mL. Elimination Following administration of a single oral dose in healthy subjects, the terminal half-lives of sunitinib and its primary active metabolite are approximately 40 to 60 hours and 80 to 110 hours, respectively.
Sunitinib total oral clearance (CL/F) ranged from 34 to 62 L/h with an interpatient variability of 40%. Metabolism Sunitinib is metabolized primarily by CYP3A4 to its primary active m… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Sunitinib is a small molecule that inhibits multiple receptor tyrosine kinases (RTKs), some of which are implicated in tumor growth, pathologic angiogenesis, and metastatic progression of cancer. Sunitinib was evaluated for its inhibitory activity against a variety of kinases (>80 kinases) and was identified as an inhibitor of platelet-derived growth factor receptors (PDGFRα and PDGFRβ), vascular endothelial growth factor receptors (VEGFR1, VEGFR2, and VEGFR3), stem cell factor receptor (KIT), Fms-like tyrosine kinase-3 (FLT3), colony stimulating factor receptor Type 1 (CSF-1R), and the glial cell-line derived neurotrophic factor receptor (RET).
Sunitinib inhibition of the activity of these RTKs has been demonstrated in biochemical and cellular assays, and inhibition of function has been demonstrated in cell proliferation assays. The primary metabolite exhibits similar potency compared to sunitinib in biochemical and cellular assays. Sunitinib inhibited the phosphorylation of multiple RTKs (PDGFRβ, VEGFR2, KIT) in tumor xenografts expressing RTK targets in vivo and demonstrated inhibition of tumor growth or tumor regression and/or inhibited metastases in some experimental models of cancer.
Sunitinib demonstrated the ability to inhibit growth of tumor cells expressing dysregulated target RTKs (PDGFR, RET, or KIT) in vitro and to inhibit PDGFRβ- and VEGFR2-dependent tumor angiogenesis in vivo .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Sunitinib malate 12.5 mg capsules are yellow to orange colored granules filled in hard gelatin capsules with warm grey colored cap and warm grey colored body, imprinted with ‘SC’ on the cap and ‘12.5’ on body in white ink. Bottles of 28 NDC 43598-045-63 Unit-dose blister packages of 28 NDC 43598-045-28 Sunitinib malate 25 mg capsules are yellow to orange colored granules filled in hard gelatin capsules with black colored cap and black colored body, imprinted with ‘SC’ on the cap and ‘25’ on body in white ink.
Bottles of 28 NDC 43598-046-63 Unit-dose blister packages of 28 NDC 43598-046-28 Sunitinib malate 37.5 mg capsules are yellow to orange colored granules filled in hard gelatin capsules with black colored cap and grey colored body, imprinted with ‘SC’ on the cap and ‘37.5’ on body in white ink. Bottles of 28 NDC 43598-047-63 Unit-dose blister packages of 28 NDC 43598-047-28 Sunitinib malate 50 mg capsules are yellow to orange colored granules filled in hard gelatin capsules with grey colored cap and grey colored body, imprinted with ‘SC’ on the cap and ‘50’ on body in white ink.
Bottles of 28 NDC 43598-048-63 Unit-dose blister packages of 28 NDC 43598-048-28 Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Sunitinib is a kinase inhibitor present in sunitinib malate capsules as the malate salt. Sunitinib malate is described chemically as (Z)-N-[2-(Diethylamino)ethyl]-5-[(5-fluoro-1,2-dihydro-2-oxo-3H-indol-3-ylidene)methyl]-2,4-dimethyl-1H-pyrrole-3-carboxamide(s)-2-hydroxysuccinate The molecular formula is C 22 H 27 FN 4 O 2 ● C 4 H 6 O 5 and the molecular weight is 532.6 Daltons. The chemical structure of sunitinib malate is: Sunitinib malate is a yellow to orange powder with a pKa of 8.95.
The solubility of sunitinib malate in aqueous media over the range pH 1.2 to pH 6.8 is in excess of 25 mg/mL. The log of the distribution coefficient at pH 7 is 5.2. Sunitinib malate capsules for oral administration, are supplied as printed hard shell capsules containing 12.5 mg, 25 mg, 37.5 mg or 50 mg of sunitinib (equivalent to 16.7 mg, 33.4 mg, 50.1 mg, or 66.8 mg of sunitinib malate, respectively).
The capsules contain the following inactive ingredients: croscarmellose sodium, magnesium stearate, mannitol, and povidone (K-25). The 12.5 mg capsules shells contains gelatin, iron oxide black, iron oxide red, iron oxide yellow, sodium lauryl sulfate and titanium dioxide. The 25 mg, 37.5 mg and 50 mg capsule shells contains gelatin, iron oxide black, sodium lauryl sulfate and titanium dioxide.
The white printing ink contains dehydrated alcohol, isopropyl alcohol, butyl alcohol, propylene glycol, shellac, strong ammonia solution, potassium hydroxide and titanium dioxide.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Hepatotoxicity Inform patients of the signs and symptoms of hepatotoxicity. Advise patients to contact their healthcare provider immediately for signs or symptoms of hepatotoxicity [ see Warnings and Precautions ( 5.1 ) ].
Cardiovascular Events Advise patients to contact their healthcare provider if they develop symptoms of heart failure [see Warnings and Precautions ( 5.2 )]. QT Prolongation and Torsade de Pointes Inform patients of the signs and symptoms of QT prolongation. Advise patients to contact their healthcare provider immediately in the event of syncope, pre-syncopal symptoms, and cardiac palpitations [ see Warnings and Precautions ( 5.3) ].
Hypertension Inform patients of the signs and symptoms of hypertension. Advise patients to undergo routine blood pressure monitoring and to contact their health care provider if blood pressure is elevated or if they experience signs or symptoms of hypertension [ see Warnings and Precautions ( 5.4 ) ]. Hemorrhagic EventsAdvise patients that sunitinib malate can cause severe bleeding.
Advise patients to immediately contact their healthcare provider for bleeding or symptoms of bleeding [ see Warnings and Precautions ( 5.5 ) ]. Gastrointestinal Disorders Advise patients that gastrointestinal disorders such as diarrhea, nausea, vomiting, and constipation may develop during sunitinib malate treatment and to seek immediate medical attention if they experience persistent or severe abdominal pain because cases of gastrointestinal perforation and fistula have been reported in patients taking sunitinib malate [ see Warnings and Precautions ( 5.5 ), Adverse Reactions ( 6.1 ) ].
Dermatologic Effects and Toxicities Advise patients that depigmentation of the hair or skin may occur during treatment with sunitinib malate due to the drug color (yellow). Other possible dermatologic effects may include dryness, thickness or cracking of skin, blister or rash on the palms of the hands and soles of the feet. Severe dermatologic toxicities including Stevens-Johnson syndrome, Toxic Epidermal Necrolysis, erythema multiforme, and necrotizing fasciitis have been reported.
Advise patients to immediately inform their healthcare provider if severe dermatologic reactions occur [ see Warnings and Precautions ( 5.9 ), Adverse Reactions ( 6.1 ) ]. Reversible Posterior Leukoencephalopathy Syndrome Inform patients of the signs and symptoms of reversible posterior leukoencephalopathy syndrome. Advise patients to contact their healthcare provider if they develop symptoms of reversible posterior leukoencephalopathy syndrome [ see Warnings and Precautions ( 5.10 ) ].
Thyroid Dysfunction Advise patients that sunitinib malate can cause thyroid dysfunction. Advise patient to contact their healthcare provider if symptoms of abnormal thyroid function occur [ see Warnings and Precautions ( 5.11) ]. Hypoglycemia Advise patients that sunitinib malate can cause severe hypoglycemia and may be more severe in patients with diabetes taking antidiabetic medications.
Inform patients of the signs, symptoms, and risks associated with hypoglycemia. Advise patients to immediately inform their healthcare provider if severe signs or symptoms of hypoglycemia occur [see Warnings and Precautions ( 5.12) ]. Osteonecrosis of the Jaw Advise patients regarding good oral hygiene practices and to inform their healthcare provider of any planned dental procedures.
Advise patients to immediately contact their healthcare provider for signs or symptoms associated with osteonecrosis of the jaw [ see Warnings and Precautions ( 5.13 ) ]. Impaired Wound Healing Advise patients that sunitinib malate impairs wound healing. Advise patients to inform their healthcare provider of any planned surgical procedures [see Warnings and Precautions ( 5.14 )].
Concomitant Medications Advise patients to inform their healthcare providers of all concomitant medi… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
SPL MEDGUIDE SECTION MEDICATION GUIDE Sunitinib Malate (soo ni′ ti nib mal eyt ) c apsules What is the most important information I should know about sunitinib malate capsules? sunitinib malate capsules can cause serious side effects including: •Severe liver problems, that can leadto death. Tell your healthcare provider right awayif you develop any of the following signs and symptoms of liver problems during treatment with sunitinib malate capsules: ∙itching ∙yellow eyes or skin ∙dark urine ∙pain or discomfort in the right upper stomach area Your healthcare provider should do blood tests to check your liver function before you start taking and during treatment with sunitinib malate capsules.
Your healthcare provider may temporarily stop, reduce your dose, orpermanently stop treatment with sunitinib malate capsules if you develop liver problems. See “What are the possible side effects of sunitinib malate capsules?” for more information about side effects. What is Sunitinib Malate Capsules?
Sunitinib malate capsules is a prescription medicine used to treat: • a rare cancer of the stomach, bowel, or esophagus called gastrointestinal stromal tumor (GIST) and when: ∙ you have taken the medicine imatinib mesylate and it did not stop the cancer from growing, or ∙ you cannot take imatinib mesylate. • advanced kidney cancer (advanced renal cell carcinoma or RCC). • adults with kidneycancer that has not spread(localized), and who are at high riskof RCC coming back again after having kidney surgery. • a type of pancreatic cancercalled pancreatic neuroendocrine tumors (pNET), that has progressed and cannot be treated with surgery.
It is not known if sunitinib malate capsules are safe and effective in children. Before taking sunitinib malate capsules tell your healthcare provider about all of your medical conditions, including if you: • have any heart problems •have high blood pressure •have thyroid problems •have a history of low blood sugar or diabetes •have kidney function problems (other than cancer) •have liver problems •have any bleeding problem •plan to have surgery or have had a recent surgery. You should stop taking sunitinib malate capsules at least 3 weeks before planned surgery.
See “What are the possible side effects of sunitinib malate capsules?” • have seizures •have or have had pain in the mouth, teeth or jaw, swelling or sores inside the mouth, numbness or a feeling of heaviness in the jaw, or loosening of a tooth • are pregnant or plan to become pregnant. Sunitinib malate capsules can harm your unborn baby. Females who are able to become pregnant: • Your healthcare provider should do a pregnancy test before you start treatment with sunitinib malate capsules. • You should use effective birth control (contraception) during treatment and for at least 4 weeks after your last dose of sunitinib malate capsules. •Tell your healthcare provider right away if you become pregnant or think you are pregnant during treatment with sunitinib malate capsules.
Males with female partners who are able to become pregnant should use effective birth control (contraception) during treatment and for 7 weeks after your last dose of sunitinib malate capsules. Sunitinib malate capsules may cause fertility problems in males and females. Tell your healthcare provider if this is a concern for you. •are breastfeeding or plan to breastfeed.
Do not breastfeed during treatment withsunitinib malate capsules and for at least 4 weeks (1 month) after the last dose. Tell all of your healthcare providers and dentists that you are taking sunitinib malate capsules. They should talk to the healthcare provider who prescribed sunitinib malate capsules for you, before you have any surgery, or medical or dental procedure.
Tell your healthcare provider about all the medicines you take, including prescription medicines and over-the-counter medicines, vitamins, and herbal supplements. Using sunitinib malate capsules with certain other medicines can cause serious side effe… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Sunitinib malate can cause fetal harm when administered to a pregnant woman [ see Use in Specific Populations ( 8.1) ]. Pregnancy Testing Verify pregnancy status of females of reproductive potential prior to initiating treatment with sunitinib malate. Contraception FemalesAdvise females of reproductive potential to use effective contraception during treatment with sunitinib malate and for at least 4 weeks after the last dose.
Males Based on findings in animal reproduction studies, advise males with female partners of reproductive potential to use effective contraception during treatment with sunitinib malate and for 7 weeks after the last dose. Infertility Based on findings in animals, sunitinib malate may impair male and female fertility [ see Nonclinical Toxicology ( 13.1 ) ].
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of sunitinib and sunitinib malate have been evaluated in healthy subjects and in patients with solid tumors. Sunitinib AUC and Cmax increase proportionately over a dose range of 25 mg to 100 mg (0.5 to 2 times the approved RDD of 50 mg). The pharmacokinetics were similar in healthy subjects and in patients with a solid tumor, including patients with GIST and RCC.
No significant changes in the pharmacokinetics of sunitinib or the primary active metabolite were observed with repeated daily administration or with repeated cycles. With repeated daily administration, sunitinib accumulates 3- to 4-fold while the primary metabolite accumulates 7- to 10-fold. Steady-state concentrations of sunitinib and its primary active metabolite are achieved within 10 to 14 days.
By Day 14, combined plasma concentrations of sunitinib and its active metabolite ranged from 63 to 101 ng/mL. Absorption Following oral administration of sunitinib, the time to maximum plasma concentration (Tmax) ranged from 6 to 12 hours. Effect of Food The administration of a single dose of sunitinib malate 50 mg with a high-fat, high-calorie meal (consisting of approximately 150 protein calories and 500 to 600 fat calories) in healthy subjects had no clinically significant effect on sunitinib malate or active metabolites exposure.
Distribution The apparent volume of distribution (Vd/F) for sunitinib is 2230 L. Binding of sunitinib and its primary active metabolite to human plasma protein in vitro is 95% and 90%, respectively, with no concentration dependence in the range of 100 to 4000 ng/mL. Elimination Following administration of a single oral dose in healthy subjects, the terminal half-lives of sunitinib and its primary active metabolite are approximately 40 to 60 hours and 80 to 110 hours, respectively.
Sunitinib total oral clearance (CL/F) ranged from 34 to 62 L/h with an interpatient variability of 40%. Metabolism Sunitinib is metabolized primarily by CYP3A4 to its primary active metabolite, which is further metabolized by CYP3A4. The primary active metabolite comprises 23% to 37% of the total exposure.
After a radiolabeled dose, sunitinib and its active metabolite were the major compounds identified in plasma, accounting for 92% of radioactivity. Excretion After a radiolabeled dose of sunitinib, approximately 61% of the dose was recovered in feces and 16% in urine. Sunitinib and its primary active metabolite were the major compounds identified in urine and feces, representing 86% and 74% of radioactivity, respectively.
Specific Populations No clinically significant differences in the pharmacokinetics of sunitinib or the primary active metabolite were observed based on age (18 to 84 years), body weight (34 to 168 kg), race (White, Black, or Asian), sex, Eastern Cooperative Oncology Group (ECOG) score, mild (Child-Pugh Class A) or moderate (Child-Pugh Class B) hepatic impairment. Patients with Renal Impairment No clinically significant differences in the pharmacokinetics of sunitinib or its active metabolite were predicted or observed in patients with mild (CLcr 50 to 80 mL/min), moderate (CLcr 30 to <50 mL/min), or severe (CLcr <30 mL/min) renal impairment who are not on dialysis, compared to patients with normal renal function (CLcr >80 mL/min).
Although sunitinib was not eliminated through hemodialysis, the sunitinib systemic exposure was 47% lower in patients with end stage renal disease (ESRD) on hemodialysis compared to patients with normal renal function. Drug Interaction Studies Clinical Studies Effect of strong CYP3A4 inhibitors on sunitinib : Co-administration of a single sunitinib malate dose with ketoconazole (strong CYP3A4 inhibitor) increased the combined sunitinib and its active metabolite Cmax and AUC 0-inf by 49% and 51%, respectively, in healthy subjects.
Effect of strong CYP3A4 inducers on sunitinib: Co-administration of a single sunitinib malate dose with rifampin (strong CYP3A4 inducer) reduced the co… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Exposure-Response Relationship Based on population pharmacokinetic/pharmacodynamic analyses, there were relationships between changes in different pharmacodynamic endpoints (i.e., safety and efficacy endpoints) over time and sunitinib plasma exposures. Cardiac Electrophysiology Sunitinib malate can cause QT interval prolongation in a dose-dependent manner, which may lead to an increased risk for ventricular arrhythmias including Torsade de Pointes [see Warnings and Precautions (5.3)].
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Gastrointestinal Stromal Tumor Study 1Study 1 (NCT#00075218) was a 2-arm, international, randomized, double-blind, placebo-controlled trial of sunitinib malate in patients with GIST who had disease progression during prior imatinib mesylate (imatinib) treatment or who were intolerant of imatinib. The objective was to compare time-to-tumor progression (TTP) in patients receiving sunitinib malate plus best supportive care versus patients receiving placebo plus best supportive care. Other objectives included progression-free survival (PFS), objective response rate (ORR), and overall survival (OS).
Patients were randomized (2:1) to receive either 50 mg sunitinib malate or placebo orally, once daily, on Schedule 4/2 until disease progression or withdrawal from the study for another reason. Treatment was unblinded at the time of disease progression. Patients randomized to placebo were then offered crossover to open-label sunitinib malate and patients randomized to sunitinib malate were permitted to continue treatment per investigator judgment.
At the time of a prespecified interim analysis, the intent-to-treat (ITT) population included 312 patients. Two hundred seven (207) patients were randomized to the sunitinib malate arm and 105 patients were randomized to the placebo arm. Demographics were comparable between the sunitinib malate and placebo groups with regard to age (69% versus 72% <65 years for sunitinib malate versus placebo, respectively), sex (male: 64% versus 61%), race (White: 88% both arms, Asian: 5% both arms, Black: 4% both arms, remainder not reported), and performance status (ECOG 0: 44% versus 46%, ECOG 1: 55% versus 52%, and ECOG 2: 1% versus 2%).
Prior treatment included surgery (94% versus 93%) and radiotherapy (8% versus 15%). Outcome of prior imatinib treatment was also comparable between arms with intolerance (4% versus 4%), progression within 6 months of starting treatment (17% versus 16%), or progression beyond 6 months (78% versus 80%) balanced. The planned interim efficacy and safety analysis was performed after 149 TTP events had occurred.
There was a statistically significant advantage for sunitinib malate over placebo in TTP, meeting the primary endpoint. Efficacy results are summarized in Table 10 and the Kaplan-Meier curve for TTP is shown in Figure 1. Table 10.
GIST Efficacy Results From Study 1 (Double-Blind Treatment Phase) Efficacy Parameter Sunitinib Malate (N=207) Placebo (N=105) p-value (log-rank test) HR (95% CI) Time-to-tumor progression a [median, weeks (95% CI)] 27.3 (16, 32.1) 6.4 (4.4, 10) <0.0001* 0.33 (0.23, 0.47) Progression-free survival b [median, weeks (95% CI)] 24.1 (11.1, 28.3) 6 (4.4, 9.9) <0.0001 0.33(0.24, 0.47) Objective response rate (PR) [%, (95% CI)] 6.8 (3.7, 11.1) 0 0.006 c * A comparison is considered statistically significant if the p-value is <0.00417 (O’Brien Fleming stopping boundary).
Abbreviations: CI=confidence interval; GIST=gastrointestinal stromal tumor; HR=hazard ratio; N=number of patients; PR=partial response. a Time from randomization to progression; deaths prior to documented progression were censored at time of last radiographic evaluation. b Time from randomization to progression or death due to any cause. c Pearson chi-square test. Figure 1. Kaplan-Meier Curve of TTP in GIST Study 1 (Intent-to-Treat Population) Abbreviations: CI=confidence interval; GIST=gastrointestinal stromal tumor; N=number of patients; TTP=time-to-tumor progression.
The final ITT population enrolled in the double-blind treatment phase of the study included 243 patients randomized to the sunitinib malate arm and 118 patients randomized to the placebo arm. After the primary endpoint was met at the interim analysis, the study was unblinded, and patients on the placebo arm were offered open-label sunitinib malate treatment. Ninety-nine (99) of the patients initially randomized to placebo crossed over to receive sunitinib malate in the open-label treatment phase… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility The carcinogenic potential of sunitinib has been evaluated in 2 species: rasH2 transgenic mice and Sprague-Dawley rats. There were similar positive findings in both species. In rasH2 transgenic mice, gastroduodenal carcinomas and/or gastric mucosal hyperplasia, as well as an increased incidence of background hemangiosarcomas were observed at sunitinib daily doses of ≥25 mg/kg/day in studies of 1 or 6 months duration.
No proliferative changes were observed in rasH2 transgenic mice at 8 mg/kg/day. Similarly, in a 2-year rat carcinogenicity study, administration of sunitinib in 28-day cycles followed by 7-day dose-free periods resulted in findings of duodenal carcinoma at doses as low as 1 mg/kg/day [approximately 0.9 times the combined AUC (combined systemic exposure of sunitinib plus its active metabolite) in patients administered the RDD of 50 mg]. At the high dose of 3 mg/kg/day (approximately 8 times the combined AUC in patients administered the RDD of 50 mg), the incidence of duodenal tumors was increased and was accompanied by findings of gastric mucous cell hyperplasia and by an increased incidence of pheochromocytoma and hyperplasia of the adrenal gland.
Sunitinib did not cause genetic damage when tested in in vitro assays [bacterial mutation (Ames test), human lymphocyte chromosome aberration] and an in vivo rat bone marrow micronucleus test. In a female fertility and early embryonic development study, female rats were administered oral sunitinib (0.5, 1.5, 5 mg/kg/day) for 21 days prior to mating and for 7 days after mating. Preimplantation loss was observed in females administered 5 mg/kg/day (approximately 5 times the combined AUC in patients administered the RDD of 50 mg).
No adverse effects on fertility were observed at doses ≤1.5 mg/kg/day (approximately equal to the combined AUC in patients administered the RDD of 50 mg). In addition, effects on the female reproductive system were identified in a 3-month oral repeat-dose monkey study (2, 6, 12 mg/kg/day). Ovarian changes (decreased follicular development) were noted at 12 mg/kg/day (approximately 5 times the combined AUC in patients administered the RDD of 50 mg), while uterine changes (endometrial atrophy) were noted at ≥2 mg/kg/day (approximately 0.4 times the combined AUC in patients administered the RDD of 50 mg).
With the addition of vaginal atrophy, the uterine and ovarian effects were reproduced at 6 mg/kg/day (approximately 0.8 times the combined AUC in patients administered the RDD of 50 mg) in a 9-month monkey study (0.3, 1.5, and 6 mg/kg/day administered daily for 28 days followed by a 14-day respite). In a male fertility study, no reproductive effects were observed in male rats dosed with 1, 3, or 10 mg/kg/day oral sunitinib for 58 days prior to mating with untreated females. Fertility, copulation, conception indices, and sperm evaluation (morphology, concentration, and motility) were unaffected by sunitinib at doses ≤10 mg/kg/day (approximately ≥26 times the combined AUC in patients administered the RDD of 50 mg).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility The carcinogenic potential of sunitinib has been evaluated in 2 species: rasH2 transgenic mice and Sprague-Dawley rats. There were similar positive findings in both species. In rasH2 transgenic mice, gastroduodenal carcinomas and/or gastric mucosal hyperplasia, as well as an increased incidence of background hemangiosarcomas were observed at sunitinib daily doses of ≥25 mg/kg/day in studies of 1 or 6 months duration.
No proliferative changes were observed in rasH2 transgenic mice at 8 mg/kg/day. Similarly, in a 2-year rat carcinogenicity study, administration of sunitinib in 28-day cycles followed by 7-day dose-free periods resulted in findings of duodenal carcinoma at doses as low as 1 mg/kg/day [approximately 0.9 times the combined AUC (combined systemic exposure of sunitinib plus its active metabolite) in patients administered the RDD of 50 mg]. At the high dose of 3 mg/kg/day (approximately 8 times the combined AUC in patients administered the RDD of 50 mg), the incidence of duodenal tumors was increased and was accompanied by findings of gastric mucous cell hyperplasia and by an increased incidence of pheochromocytoma and hyperplasia of the adrenal gland.
Sunitinib did not cause genetic damage when tested in in vitro assays [bacterial mutation (Ames test), human lymphocyte chromosome aberration] and an in vivo rat bone marrow micronucleus test. In a female fertility and early embryonic development study, female rats were administered oral sunitinib (0.5, 1.5, 5 mg/kg/day) for 21 days prior to mating and for 7 days after mating. Preimplantation loss was observed in females administered 5 mg/kg/day (approximately 5 times the combined AUC in patients administered the RDD of 50 mg).
No adverse effects on fertility were observed at doses ≤1.5 mg/kg/day (approximately equal to the combined AUC in patients administered the RDD of 50 mg). In addition, effects on the female reproductive system were identified in a 3-month oral repeat-dose monkey study (2, 6, 12 mg/kg/day). Ovarian changes (decreased follicular development) were noted at 12 mg/kg/day (approximately 5 times the combined AUC in patients administered the RDD of 50 mg), while uterine changes (endometrial atrophy) were noted at ≥2 mg/kg/day (approximately 0.4 times the combined AUC in patients administered the RDD of 50 mg).
With the addition of vaginal atrophy, the uterine and ovarian effects were reproduced at 6 mg/kg/day (approximately 0.8 times the combined AUC in patients administered the RDD of 50 mg) in a 9-month monkey study (0.3, 1.5, and 6 mg/kg/day administered daily for 28 days followed by a 14-day respite). In a male fertility study, no reproductive effects were observed in male rats dosed with 1, 3, or 10 mg/kg/day oral sunitinib for 58 days prior to mating with untreated females. Fertility, copulation, conception indices, and sperm evaluation (morphology, concentration, and motility) were unaffected by sunitinib at doses ≤10 mg/kg/day (approximately ≥26 times the combined AUC in patients administered the RDD of 50 mg).
📄 Recent Major Changes ▾
RECENT MAJOR CHANGES SECTION Dosage and Administration, Dosage Modifications for Adverse Reactions ( 2.4 ) 8/2021 Dosage and Administration, Dosage Modification for Drug Interactions ( 2.5 ) 8/2021 Warnings and Precautions, Hepatotoxicity ( 5.1 ) 8/2021 Warnings and Precautions, Hypertension ( 5.4 ) 8/2021 Warnings and Precautions, Hemorrhagic Events and Viscous Perforation ( 5.5 ) 8/2021 Warnings and Precautions, Reversible Posterior Leukoencephalopathy Syndrome ( 5.10 ) 8/2021 Warnings and Precautions, Hypoglycemia ( 5.12 ) 8/2021 Warnings and Precautions, Osteonecrosis of the Jaw ( 5.13 ) 8/2021
📄 Package Label / Principal Display Panel ▾
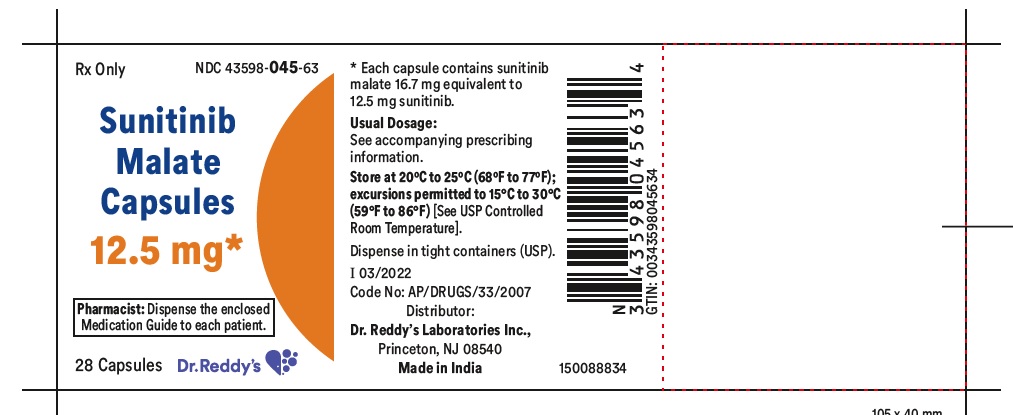
PACKAGE LABEL PRINCIPAL DISPLAY PANEL SECTION
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |