
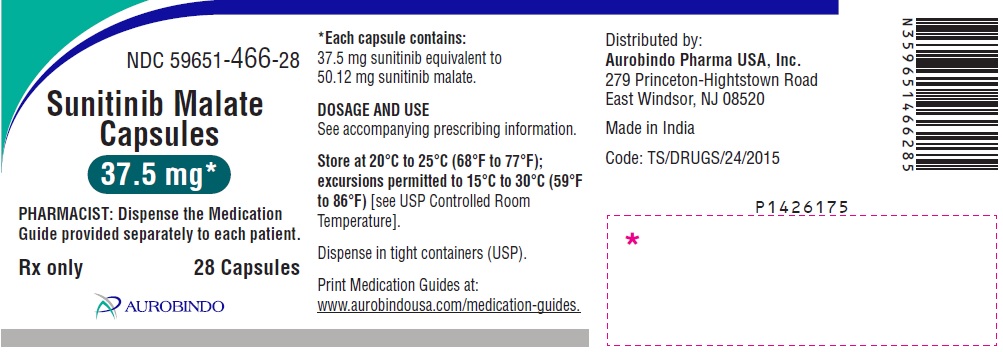
SUNITINIB MALATE 37.5 mg Capsule, 28-count
Other active recalls for Sunitinib Malate (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It's actually quite different from traditional chemotherapy. Sunitinib is what we call a targeted therapy — it blocks specific proteins on cancer cells that tell them to grow and b...
- What exactly does sunitinib do — is it like regular chemotherapy?
- That's a great question. The 4-weeks-on, 2-weeks-off schedule — called Schedule 4/2 — is used for GIST and kidney cancer to give your body a chance to recover from side effects bef...
- I noticed I take it for 4 weeks and then stop for 2 weeks. Why the break?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII K0KQV10C35
Povidone K25 is a synthetic polymer made from vinyl pyrrolidone. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach for better absorption.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $76.85 | $2,151.82 / 28 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sutent 37.5 mg 00069-0830-38 | Pfizer | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mg 00093-8229-28 | Teva | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mg 00378-6681-28 | Mylan | 28 capsules | — | AB | FDA listed | — |
| Sunitinib malate 37.5 mg 16714-0678-01 | NorthStar | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mg 42291-0903-28 | AvKARE | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mg 43598-0047-28 | Dr.Reddys | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mgthis 59651-0466-28 | Aurobindo | 28 capsules | — | AB | FDA listed | — |
| Sunitinib malate 37.5 mg 63304-0093-27 | Sun | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mg 72205-0118-28 | Novadoz | 28 capsules | — | AB | FDA listed | — |
| Sunitinib Malate 37.5 mg 82293-0016-10 | Novugen | 28 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 59651-0466-28 You're viewing this | 28 CAPSULE in 1 BOTTLE (59651-466-28) | 2024-03-14 | Active |
| 59651-0466-29 | 4 BLISTER PACK in 1 CARTON (59651-466-29) / 7 CAPSULE in 1 BLISTER PACK | 2024-03-14 | Active |
Pack size FAQ
What quantity is in NDC 59651-0466-28?
What is the difference between NDC 59651-0466-28 and NDC 59651-0466-29?
What NDC number is used to bill for this package of SUNITINIB MALATE 37.5 mg Capsule?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: HEPATOTOXICITY Hepatotoxicity may be severe, and in some cases, fatal. Monitor hepatic function and interrupt, dose reduce, or discontinue sunitinib malate as recommended [see Warnings and Precautions (5.1) ] . WARNING: HEPATOTOXICITY See full prescribing information for complete boxed warning.
Hepatotoxicity may be severe, and in some cases fatal. Monitor hepatic function and interrupt, dose reduce, or discontinue sunitinib malate as recommended [see Warnings and Precautions (5.1) ].
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Sunitinib malate is a kinase inhibitor indicated for: treatment of adult patients with gastrointestinal stromal tumor (GIST) after disease progression on or intolerance to imatinib mesylate. ( 1.1 ) treatment of adult patients with advanced renal cell carcinoma (RCC). ( 1.2 ) adjuvant treatment of adult patients at high risk of recurrent RCC following nephrectomy.
( 1.3 ) treatment of progressive, well-differentiated pancreatic neuroendocrine tumors (pNET) in adult patients with unresectable locally advanced or metastatic disease. ( 1.4 )
1.1Gastrointestinal Stromal Tumor Sunitinib malate capsules are indicated for the treatment of adult patients with gastrointestinal stromal tumor (GIST) after disease progression on or intolerance to imatinib mesylate.
1.2Advanced Renal Cell Carcinoma Sunitinib malate capsules are indicated for the treatment of adult patients with advanced renal cell carcinoma (RCC).
1.3Adjuvant Treatment of Renal Cell Carcinoma Sunitinib malate capsules are indicated for the adjuvant treatment of adult patients at high risk of recurrent RCC following nephrectomy.
1.4Advanced Pancreatic Neuroendocrine Tumors Sunitinib malate capsules are indicated for the treatment of progressive, well-differentiated pancreatic neuroendocrine tumors (pNET) in adult patients with unresectable locally advanced or metastatic disease.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION GIST and Advanced RCC: The recommended dosage is 50 mg orally once daily for the first 4 weeks of each 6-week cycle (Schedule 4/2). ( 2.1 ) Adjuvant Treatment of RCC: The recommended dosage is 50 mg orally once daily for the first 4 weeks of a 6-week cycle (Schedule 4/2) for a maximum of 9 cycles. ( 2.2 ) pNET: The recommended dosage is 37.5 mg orally once daily. ( 2.3)
2.1Recommended Dosage for GIST and Advanced RCC The recommended dosage of sunitinib malate capsules for gastrointestinal stromal tumor (GIST) and advanced renal cell carcinoma (RCC) is 50 mg taken orally once daily, on a schedule of 4 weeks on treatment followed by 2 weeks off (Schedule 4/2) until disease progression or unacceptable toxicity. Sunitinib malate capsules may be taken with or without food.
2.2Recommended Dosage for Adjuvant Treatment of RCC The recommended dosage of sunitinib malate capsules for the adjuvant treatment of RCC is 50 mg taken orally once daily, on a schedule of 4 weeks on treatment followed by 2 weeks off (Schedule 4/2), for nine 6-week cycles. Sunitinib malate capsules may be taken with or without food.
2.3Recommended Dosage for pNET The recommended dosage of sunitinib malate capsules for pancreatic neuroendocrine tumors (pNET) is 37.5 mg taken orally once daily until disease progression or unacceptable toxicity. Sunitinib malate capsules may be taken with or without food.
2.4Dosage Modifications for Adverse Reactions To manage adverse reactions, the recommended dosage modifications are provided in Table 1. Table 2 provides the recommended dosage reductions of sunitinib malate capsules for adverse reactions. Table 1.
Recommended Dosage Reductions of Sunitinib Malate Capsules for Adverse Reactions Indications GIST RCC pNET Advanced RCC Adjuvant RCC First dose reduction 37.5 mg once daily 37.5 mg once daily 37.5 mg once daily 25 mg once daily Second dose reduction 25 mg once daily 25 mg once daily NA NA Table 2. Recommended Dosage Modifications for Sunitinib Malate Capsules for Adverse Reactions Adverse Reaction Severity Dosage Modifications for Sunitinib Malate Capsules Hepatotoxicity [see Warnings and Precautions (5.1) ] Grade 3 Withhold until resolution to Grade 0 to 1 or baseline.
Resume at a reduced dose. For recurring Grade 3 permanently discontinue. Grade 4 • Permanently discontinue.
Cardiovascular events [see Warnings and Precautions (5.2) ] Asymptomatic cardiomyopathy (left ventricular ejection fraction greater than 20% but less than 50% below baseline or below the lower limit of normal if baseline was not obtained) Withhold until resolution to Grade 0 to 1 or baseline. Resume at reduced dose. Clinically manifested congestive heart failure (CHF) Permanently discontinue.
Hypertension [see Warnings and Precautions (5.4) ] Grade 3 Withhold until resolution to Grade 0 to 1 or baseline. Resume at a reduced dose. Grade 4 Permanently discontinue.
Hemorrhagic events [see Warnings and Precautions (5.5) ] Grade 3 or 4 Withhold until resolution to Grade 0 to 1 or baseline. Either resume at a reduced dose or discontinue depending on the severity and persistence of adverse reaction. Thrombotic microangiopathy [see Warnings and Precautions (5.7) ] Any Grade Permanently discontinue.
Proteinuria or Nephrotic syndrome [see Warnings and Precautions (5.8) ] 3 or more grams proteinuria in 24 hours in the absence of nephrotic syndrome Withhold until resolution to Grade 0 to 1 or baseline. Resume at a reduced dose. Nephrotic syndrome or recurrent proteinuria of 3 or more grams per 24 hours despite dose reductions Permanently discontinue.
Dermatological toxicities Erythema multiforme (EM), Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), Necrotizing fasciitis [see Warnings and Precautions (5.9) ] Any Grade Permanently discontinue. Reversible posterior leukoencephalopathy syndrome [see Warnings and Precautions (5.10) ] Any Grade Permanently discontinue. Osteonecrosis of the jaw [see Warnings and Precau…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules, hard gelatin: • 12.5 mg sunitinib: red opaque cap and red opaque body imprinted ‘S12.5’ on body with white ink and plain cap, containing yellow to orange granules. • 25 mg sunitinib: olive green opaque cap and red opaque body imprinted ‘S25’ on body with white ink and plain cap, containing yellow to orange granules. • 37.5 mg sunitinib: light green opaque cap and light green opaque body imprinted ‘S37.5’ on body with black ink and plain cap, containing yellow to orange granules. • 50 mg sunitinib: olive green opaque cap and olive green opaque body imprinted ‘S50’ on body with black ink and plain cap, containing yellow to orange granules.
Capsules: 12.5 mg, 25 mg, 37.5 mg, 50 mg sunitinib ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hepatotoxicity : Fatal liver failure has been observed. Monitor liver function tests at baseline, during each cycle, and as clinically indicated. Interrupt sunitinib malate for Grade 3 hepatotoxicity until resolution to Grade ≤1 or baseline and resume sunitinib malate at a reduced dose; discontinue if no resolution.
Discontinue sunitinib malate in patients with Grade 4 hepatoxicity, in patients who have subsequent severe changes in liver function tests or other signs and symptoms of liver failure. ( 2.4 , 5.1 ) Cardiovascular Events : Myocardial ischemia, myocardial infarction, heart failure, cardiomyopathy, and decreased left ventricular ejection fraction (LVEF) to below the lower limit of normal including death have occurred. Monitor for signs and symptoms of congestive heart failure and consider monitoring LVEF at baseline and periodically during treatment.
Discontinue sunitinib malate for clinical manifestations of congestive heart failure. Interrupt and/or dose reduce for decreased LVEF. ( 5.2 ) QT Interval Prolongation and Torsade de Pointes : Monitor patients at higher risk for developing QT interval prolongation.
Consider monitoring of electrocardiograms and electrolytes. ( 5.3 ) Hypertension : Monitor blood pressure at baseline and as clinically indicated. Initiate and/or adjust antihypertensive therapy as appropriate.
Interrupt sunitinib malate for Grade 3 hypertension until resolution to Grade ≤1 or baseline, then resume sunitinib malate at a reduced dose. Discontinue sunitinib malate in patients who develop Grade 4 hypertension. ( 5.4 ) Hemorrhagic Events : Tumor-related hemorrhage and viscus perforation (both with fatal events) have occurred.
Perform serial complete blood counts and physical examinations. Interrupt sunitinib malate for Grade 3 or 4 hemorrhagic events until resolution to Grade ≤1 or baseline, then resume at a reduced dose; discontinue if no resolution. ( 5.5 ) Tumor Lysis Syndrome (TLS) : TLS (some fatal) has been reported primarily in patients with RCC and GIST.
Monitor these patients and treat as clinically indicated. ( 5.6 ) Thrombotic microangiopathy (TMA) : TMA, including thrombotic thrombocytopenic purpura and hemolytic uremic syndrome, sometimes leading to renal failure or a fatal outcome, has been reported. Discontinue sunitinib malate for TMA.
( 5.7 ) Proteinuria : Renal failure or a fatal outcome has occurred. Monitor urine protein. Interrupt treatment for 24-hour urine protein of 3 or more grams.
Discontinue for repeat episodes of 24-hour urine protein of 3 or more grams despite dose reductions or nephrotic syndrome. ( 5.8 ) Dermatologic Toxicities : Necrotizing fasciitis, erythema multiforme, Stevens-Johnson syndrome (SJS), and toxic epidermal necrolysis (TEN) (some fatal) have occurred. Discontinue sunitinib malate for these events.
( 5.9 ) Reversible Posterior Leukoencephalopathy Syndrome (RPLS) : RPLS (some fatal) has been reported. Monitor for signs and symptoms of RPLS. Withhold sunitinib malate until resolution.
( 5.10 ) Thyroid Dysfunction : Monitor thyroid function at baseline, periodically during treatment, and as clinically indicated. Initiate and/or adjust therapy for thyroid dysfunction as appropriate. ( 5.11 ) Hypoglycemia : Check blood glucose levels regularly and assess if antidiabetic drug dose modifications are required.
( 5.12 ) Osteonecrosis of the Jaw (ONJ) : Withhold sunitinib malate for at least 3 weeks prior to invasive dental procedure and for development of ONJ until complete resolution. ( 5.13 ) Impaired Wound Healing : Withhold sunitinib malate for at least 3 weeks prior to elective surgery. Do not administer for at least 2 weeks following major surgery and until adequate wound healing.
The safety of resumption of sunitinib malate after resolution of wound healing complications has not been established. ( 5.14 ) Embryo-Fetal Toxicity : Can cause fetal harm. Advise patients of potential risk to a fetus and to use effective contracepti…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling. Hepatotoxicity [see Warnings and Precautions (5.1) ] Cardiovascular Events [see Warnings and Precautions (5.2) ] QT Interval Prolongation and Torsade de Pointes [see Warnings and Precautions (5.3) ] Hypertension [see Warnings and Precautions (5.4) ] Hemorrhagic Events [see Warnings and Precautions (5.5) ] Tumor Lysis Syndrome [see Warnings and Precautions (5.6) ] Thrombotic Microangiopathy [see Warnings and Precautions (5.7) ] Proteinuria [see Warnings and Precautions (5.8) ] Dermatologic Toxicities [see Warnings and Precautions (5.9) ] Reversible Posterior Leukoencephalopathy Syndrome [see Warnings and Precautions (5.10) ] Thyroid Dysfunction [see Warnings and Precautions (5.11) ] Hypoglycemia [see Warnings and Precautions (5.12) ] Osteonecrosis of the Jaw [see Warnings and Precautions (5.13) ] Impaired Wound Healing [see Warnings and Precautions (5.14) ] The most common adverse reactions (≥25%) are fatigue/asthenia, diarrhea, mucositis/stomatitis, nausea, decreased appetite/anorexia, vomiting, abdominal pain, hand-foot syndrome, hypertension, bleeding events, dysgeusia/altered taste, dyspepsia, and thrombocytopenia.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The pooled safety population described in the Warnings and Precautions reflect exposure to sunitinib malate in 7527 patients with GIST, RCC (advanced and adjuvant), or pNET. In this pooled safety population, the most common adverse reactions (≥25%) were fatigue/asthenia, diarrhea, mucositis/stomatitis, nausea, decreased appetite/anorexia, vomiting, abdominal pain, hand-foot syndrome, hypertension, bleeding events, dysgeusia/altered taste, dyspepsia, and thrombocytopenia.
Gastrointestinal Stromal Tumor The safety of sunitinib malate was evaluated in Study 1, a randomized, double-blind, placebo-controlled trial in which previously treated patients with GIST received sunitinib malate 50 mg daily on Schedule 4/2 (n=202) or placebo (n=102). Median duration of blinded study treatment was 2 cycles for patients on sunitinib malate (mean: 3.0; range: 1 to 9) and 1 cycle (mean; 1.8; range: 1 to 6) for patients on placebo at the time of the interim analysis. Permanent discontinuation due to an adverse reaction occurred in 7% of patients in the sunitinib malate arm.
Dose reductions occurred in 11% and dose interruptions occurred in 29% of patients who received sunitinib malate. Table 3 summarizes the adverse reactions for Study 1. Table 3.
Adverse Reactions Reported in ≥ 10% of GIST Patients Who Received Sunitinib Malate in the Double-Blind Treatment Phase and More Commonly Than in Patients Given Placebo * in Study 1 Adverse Reaction GIST Sunitinib Malate (N=202) Placebo (N=102) All Grade s % Grade 3 to 4 % All Grade s % Grade 3 to 4 % Any Adverse Reaction 94 56 97 51 Gastrointestinal Diarrhea Mucositis/stomatitis Constipation 40 29 20 4 1 0 27 18 14 0 2 2 Metabolism/Nutrition Anorexia a Asthenia 33 22 1 5 29 11 5 3 Dermatology Skindiscoloration Rash Hand-footsyndrome 30 14 14 0 1 4 23 9 10 0 0 3 Neurology Alteredtaste 21 0 12 0 Cardiac Hypertension 15 4 11 0 Musculoskeletal Myalgia/limb pain 14 1 9 1 * Common Terminology Criteria for Adverse Events (CTCAE), version 3.0.
Abbreviations: GIST=gastrointestinal stromal tumor; N=number of patients. a Includes decreased appetite. Other clinically relevant adverse reactions included oral pain other than mucositis/stomatitis in 6%; hair color changes in 7%; alopecia in 5% of patients who received sunitinib malate. Table 4 summarizes…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CYP3A4 Inhibitors : Consider dose reduction of sunitinib malate when administered with strong CYP3A4 inhibitors. ( 7.1 ) CYP3A4 Inducers : Consider dose increase of sunitinib malate when administered with strong CYP3A4 inducers. ( 7.1 )
7.1Effect of Other Drugs on Sunitinib Malate Strong CYP3A4 Inhibitors Co-administration with strong CYP3A4 inhibitors may increase sunitinib plasma concentrations [see Clinical Pharmacology (12.3) ] . Select an alternate concomitant medication with no or minimal enzyme inhibition potential. Consider a dose reduction for sunitinib malate when it is co-administered with strong CYP3A4 inhibitors [see Dosage and Administration (2.5) ] .
Strong CYP3A4 Inducers Co-administration with strong CYP3A4 inducers may decrease sunitinib plasma concentrations [see Clinical Pharmacology (12.3) ] . Select an alternate concomitant medication with no or minimal enzyme induction potential. Consider a dose increase for sunitinib malate when it must be co-administered with CYP3A4 inducers [see Dosage and Administration (2.5) ] .
7.2Drugs that Prolong QT Interval Sunitinib malate is associated with QTc interval prolongation [see Warnings and Precautions (5.3) , Clinical Pharmacology (12.2) ] . Monitor the QT interval with ECGs more frequently in patients who require treatment with concomitant medications known to prolong the QT interval.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation : Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on animal reproduction studies and its mechanism of action, sunitinib malate can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data in pregnant women to inform a drug-associated risk. In animal developmental and reproductive toxicology studies, oral administration of sunitinib to pregnant rats and rabbits throughout organogenesis resulted in teratogenicity (embryolethality, craniofacial and skeletal malformations) at 5.5 and 0.3 times the combined AUC (the combined systemic exposure of sunitinib plus its active metabolite) in patients administered the recommended daily doses (RDD) of 50 mg, respectively (see Data).
Advise females of reproductive potential of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data In a female fertility and early embryonic development study, female rats were administered oral sunitinib (0.5, 1.5, 5 mg/kg/day) for 21 days prior to mating and for 7 days after mating. Embryolethality was observed at 5 mg/kg/day (approximately 5 times the combined AUC in patients administered the RDD of 50 mg).
In embryo-fetal developmental toxicity studies, oral sunitinib was administered to pregnant rats (0.3, 1.5, 3, 5 mg/kg/day) and rabbits (0.5, 1, 5, 20 mg/kg/day) during the period of organogenesis. In rats, embryolethality and skeletal malformations of the ribs and vertebrae were observed at the dose of 5 mg/kg/day (approximately 5.5 times the combined AUC in patients administered the RDD of 50 mg). No adverse fetal effects were observed in rats at doses ≤3 mg/kg/day (approximately 2 times the combined AUC in patients administered the RDD of 50 mg).
In rabbits, embryolethality was observed at 5 mg/kg/day (approximately 3 times the combined AUC in patients administered the RDD of 50 mg), and craniofacial malformations (cleft lip and cleft palate) were observed at ≥1 mg/kg/day (approximately 0.3 times the combined AUC in patients administered the RDD of 50 mg). Sunitinib (0.3, 1, 3 mg/kg/day) was evaluated in a pre- and postnatal development study in pregnant rats. Maternal body weight gains were reduced during gestation and lactation at doses ≥1 mg/kg/day (approximately 0.5 times the combined AUC in patients administered the RDD of 50 mg).
At 3 mg/kg/day (approximately 2 times the combined AUC in patients administered the RDD of 50 mg), reduced neonate body weights were observed at birth and persisted in the offspring of both sexes during the preweaning period and in males during postweaning period. No adverse developmental effects were observed at doses ≤1 mg/kg/day.
8.2Lactation There is no information regarding the presence of sunitinib and its metabolites in human milk. Sunitinib and its metabolites were excreted in rat milk at concentrations up to 12-fold higher than in plasma (see Data) . Because of the potential for serious adverse reactions in breastfed infants, advise women not to breastfeed during treatment with sunitinib malate and for at least 4 weeks after the last dose.
Data Animal Data In lactating female rats administered 15 mg/kg, sunitinib and its metabolites were excreted in milk at concentrations up to 12-fold higher than in plasma.
8.3Females and Males of Reproductive Potential Sunitinib malate can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ]. Pregnancy Testing Verify pregnancy status of females of reproductive potential prior to initiating treatment with sunitinib malate. Contraception Females Ad…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on animal reproduction studies and its mechanism of action, sunitinib malate can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data in pregnant women to inform a drug-associated risk. In animal developmental and reproductive toxicology studies, oral administration of sunitinib to pregnant rats and rabbits throughout organogenesis resulted in teratogenicity (embryolethality, craniofacial and skeletal malformations) at 5.5 and 0.3 times the combined AUC (the combined systemic exposure of sunitinib plus its active metabolite) in patients administered the recommended daily doses (RDD) of 50 mg, respectively (see Data).
Advise females of reproductive potential of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data In a female fertility and early embryonic development study, female rats were administered oral sunitinib (0.5, 1.5, 5 mg/kg/day) for 21 days prior to mating and for 7 days after mating. Embryolethality was observed at 5 mg/kg/day (approximately 5 times the combined AUC in patients administered the RDD of 50 mg).
In embryo-fetal developmental toxicity studies, oral sunitinib was administered to pregnant rats (0.3, 1.5, 3, 5 mg/kg/day) and rabbits (0.5, 1, 5, 20 mg/kg/day) during the period of organogenesis. In rats, embryolethality and skeletal malformations of the ribs and vertebrae were observed at the dose of 5 mg/kg/day (approximately 5.5 times the combined AUC in patients administered the RDD of 50 mg). No adverse fetal effects were observed in rats at doses ≤3 mg/kg/day (approximately 2 times the combined AUC in patients administered the RDD of 50 mg).
In rabbits, embryolethality was observed at 5 mg/kg/day (approximately 3 times the combined AUC in patients administered the RDD of 50 mg), and craniofacial malformations (cleft lip and cleft palate) were observed at ≥1 mg/kg/day (approximately 0.3 times the combined AUC in patients administered the RDD of 50 mg). Sunitinib (0.3, 1, 3 mg/kg/day) was evaluated in a pre- and postnatal development study in pregnant rats. Maternal body weight gains were reduced during gestation and lactation at doses ≥1 mg/kg/day (approximately 0.5 times the combined AUC in patients administered the RDD of 50 mg).
At 3 mg/kg/day (approximately 2 times the combined AUC in patients administered the RDD of 50 mg), reduced neonate body weights were observed at birth and persisted in the offspring of both sexes during the preweaning period and in males during postweaning period. No adverse developmental effects were observed at doses ≤1 mg/kg/day.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of sunitinib malate in pediatric patients have not been established. Safety and pharmacokinetics of sunitinib were assessed in an open-label study (NCT00387920) in pediatric patients 2 years to <17 years of age (n=29) with refractory solid tumors. In addition, efficacy, safety and pharmacokinetics of sunitinib was assessed in another open-label study (NCT01462695) in pediatric patients 2 years to <17 years of age (n=27) with high-grade glioma or ependymoma.
The maximum tolerated dose (MTD) normalized for body surface area (BSA) was lower in pediatric patients compared to adults. Sunitinib was poorly tolerated in pediatric patients. The occurrence of dose-limiting cardiotoxicity prompted an amendment of the NCT00387920 study to exclude patients with previous exposure to anthracyclines or cardiac radiation.
No responses were reported in patients in either of the trials. Apparent clearance and volume of distribution normalized for BSA for sunitinib and its active major metabolite were lower in pediatrics as compared to adults. The effect on open tibial growth plates in pediatric patients who received sunitinib malate has not been adequately studied.
See Juvenile Animal Toxicity Data below. Juvenile Animal Toxicity Data Physeal dysplasia was present in cynomolgus monkeys with open growth plates treated with sunitinib for ≥3 months (3 month dosing 2, 6, 12 mg/kg/day; 8 cycles of dosing 0.3, 1.5, 6 mg/kg/day) at doses that were >0.4 times the combined AUC (the combined systemic exposure of sunitinib plus its active metabolite) in patients administered the RDD of 50 mg. The no-effect level (NOEL) was 1.5 mg/kg/day in monkeys treated intermittently for 8 cycles, but was not identified in monkeys treated continuously for 3 months.
In developing rats treated continuously for 3 months (1.5, 5, and 15 mg/kg) or 5 cycles (0.3, 1.5, and 6 mg/kg/day), bone abnormalities consisted of thickening of the epiphyseal cartilage of the femur and an increase of fracture of the tibia at doses ≥5 mg/kg (approximately 10 times the combined AUC in patients administered the RDD of 50 mg). Additionally, tooth caries were present in rats at >5 mg/kg. The incidence and severity of physeal dysplasia were dose related and reversible upon cessation of treatment; however, findings in the teeth were not.
In rats, the NOEL in bones was ≤2 mg/kg/day.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 7527 patients with GIST, RCC (advanced and adjuvant), or pNET who received sunitinib malate, 32% were 65 years and older, and 7% were 75 years and older. Patients aged 65 years of age and older had a higher incidence of Grade 3 or 4 adverse reactions (67%) than younger patients (60%). In the GIST study, 73 (30%) of the patients who received sunitinib malate were 65 years and older.
In the mRCC study, 152 (41%) of patients who received sunitinib malate were 65 years and older. No overall differences in safety or effectiveness were observed between these patients and younger patients. In the pNET study, 22 (27%) of the patients who received sunitinib malate were 65 years and older.
Clinical studies of sunitinib malate did not include sufficient numbers of patients with pNET to determine if patients 65 years of age and older respond differently than younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE Treatment of overdose with sunitinib malate should consist of general supportive measures. There is no specific antidote for overdosage with sunitinib malate. If indicated, elimination of unabsorbed drug should be achieved by emesis or gastric lavage.
Cases of accidental overdose have been reported; these cases were associated with adverse reactions consistent with the known safety profile of sunitinib malate, or without adverse reactions. In nonclinical studies, mortality was observed following as few as 5 daily doses of 500 mg/kg (3000 mg/m 2 ) in rats. At this dose, signs of toxicity included impaired muscle coordination, head shakes, hypoactivity, ocular discharge, piloerection, and gastrointestinal distress.
Mortality and similar signs of toxicity were observed at lower doses when administered for longer durations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Sunitinib is a small molecule that inhibits multiple receptor tyrosine kinases (RTKs), some of which are implicated in tumor growth, pathologic angiogenesis, and metastatic progression of cancer. Sunitinib was evaluated for its inhibitory activity against a variety of kinases (>80 kinases) and was identified as an inhibitor of platelet-derived growth factor receptors (PDGFRα and PDGFRβ), vascular endothelial growth factor receptors (VEGFR1, VEGFR2, and VEGFR3), stem cell factor receptor (KIT), Fms-like tyrosine kinase-3 (FLT3), colony stimulating factor receptor Type 1 (CSF-1R), and the glial cell-line derived neurotrophic factor receptor (RET).
Sunitinib inhibition of the activity of these RTKs has been demonstrated in biochemical and cellular assays, and inhibition of function has been demonstrated in cell proliferation assays. The primary metabolite exhibits similar potency compared to sunitinib in biochemical and cellular assays. Sunitinib inhibited the phosphorylation of multiple RTKs (PDGFRβ, VEGFR2, KIT) in tumor xenografts expressing RTK targets in vivo and demonstrated inhibition of tumor growth or tumor regression and/or inhibited metastases in some experimental models of cancer.
Sunitinib demonstrated the ability to inhibit growth of tumor cells expressing dysregulated target RTKs (PDGFR, RET, or KIT) in vitro and to inhibit PDGFRβ- and VEGFR2-dependent tumor angiogenesis in vivo .
12.2Pharmacodynamics Exposure-Response Relationship Based on population pharmacokinetic/pharmacodynamic analyses, there were relationships between changes in different pharmacodynamic endpoints (i.e., safety and efficacy endpoints) over time and sunitinib plasma exposures. Cardiac Electrophysiology Sunitinib malate can cause QT interval prolongation in a dose-dependent manner, which may lead to an increased risk for ventricular arrhythmias including Torsade de Pointes [see Warnings and Precautions (5.3) ].
12.3Pharmacokinetics The pharmacokinetics of sunitinib and sunitinib malate have been evaluated in healthy subjects and in patients with solid tumors. Sunitinib AUC and C max increase proportionately over a dose range of 25 mg to 100 mg (0.5 to 2 times the approved RDD of 50 mg). The pharmacokinetics were similar in healthy subjects and in patients with a solid tumor, including patients with GIST and RCC.
No significant changes in the pharmacokinetics of sunitinib or the primary active metabolite were observed with repeated daily administration or with repeated cycles. With repeated daily administration, sunitinib accumulates 3- to 4-fold while the primary metabolite accumulates 7- to 10-fold. Steady-state concentrations of sunitinib and its primary active metabolite are achieved within 10 to 14 days.
By Day 14, combined plasma concentrations of sunitinib and its active metabolite ranged from 63 to 101 ng/mL. Absorption Following oral administration of sunitinib, the time to maximum plasma concentration (T max ) ranged from 6 to 12 hours. Effect of Food The administration of a single dose of sunitinib malate 50 mg with a high-fat, high-calorie meal (consisting of approximately 150 protein calories and 500 to 600 fat calories) in healthy subjects had no clinically significant effect on sunitinib malate or active metabolites exposure.
Distribution The apparent volume of distribution (Vd/F) for sunitinib is 2230 L. Binding of sunitinib and its primary active metabolite to human plasma protein in vitro is 95% and 90%, respectively, with no concentration dependence in the range of 100 to 4000 ng/mL. Elimination Following administration of a single oral dose in healthy subjects, the terminal half-lives of sunitinib and its primary active metabolite are approximately 40 to 60 hours and 80 to 110 hours, respectively.
Sunitinib total oral clearance (CL/F) ranged from 34 to 62 L/h with an interpatient variability of 40%. Metabolism Sunitinib is metabolized primarily by CYP3A4 to its primary acti…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Sunitinib is a small molecule that inhibits multiple receptor tyrosine kinases (RTKs), some of which are implicated in tumor growth, pathologic angiogenesis, and metastatic progression of cancer. Sunitinib was evaluated for its inhibitory activity against a variety of kinases (>80 kinases) and was identified as an inhibitor of platelet-derived growth factor receptors (PDGFRα and PDGFRβ), vascular endothelial growth factor receptors (VEGFR1, VEGFR2, and VEGFR3), stem cell factor receptor (KIT), Fms-like tyrosine kinase-3 (FLT3), colony stimulating factor receptor Type 1 (CSF-1R), and the glial cell-line derived neurotrophic factor receptor (RET).
Sunitinib inhibition of the activity of these RTKs has been demonstrated in biochemical and cellular assays, and inhibition of function has been demonstrated in cell proliferation assays. The primary metabolite exhibits similar potency compared to sunitinib in biochemical and cellular assays. Sunitinib inhibited the phosphorylation of multiple RTKs (PDGFRβ, VEGFR2, KIT) in tumor xenografts expressing RTK targets in vivo and demonstrated inhibition of tumor growth or tumor regression and/or inhibited metastases in some experimental models of cancer.
Sunitinib demonstrated the ability to inhibit growth of tumor cells expressing dysregulated target RTKs (PDGFR, RET, or KIT) in vitro and to inhibit PDGFRβ- and VEGFR2-dependent tumor angiogenesis in vivo .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Sunitinib Malate Capsules, 12.5 mg are supplied as hard gelatin capsule with red opaque cap and red opaque body imprinted ‘S12.5’ on body with white ink and plain cap, containing yellow to orange granules; available in: Bottles of 28 capsules NDC 59651-464-28 Cartons of 28 Capsules (4 x 7 Unit-Dose) NDC 59651-464-29 Sunitinib Malate Capsules, 25 mg are supplied as hard gelatin capsule with olive green opaque cap and red opaque body imprinted ‘S25’ on body with white ink and plain cap, containing yellow to orange granules; available in: Bottles of 28 capsules NDC 59651-465-28 Cartons of 28 Capsules (4 x 7 Unit-Dose) NDC 59651-465-29 Sunitinib Malate Capsules, 37.5 mg are supplied as hard gelatin capsule with light green opaque cap and light green opaque body imprinted ‘S37.5’ on body with black ink and plain cap, containing yellow to orange granules; available in: Bottles of 28 capsules NDC 59651-466-28 Cartons of 28 Capsules (4 x 7 Unit-Dose) NDC 59651-466-29 Sunitinib Malate Capsules, 50 mg are supplied as hard gelatin capsule with olive green opaque cap and olive green opaque body imprinted ‘S50’ on body with black ink and plain cap, containing yellow to orange granules; available in: Bottles of 28 capsules NDC 59651-467-28 Cartons of 28 Capsules (4 x 7 Unit-Dose) NDC 59651-467-29 Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Sunitinib is a kinase inhibitor present in sunitinib malate capules as the malate salt. Sunitinib malate is described chemically as (2 S )-2-hydroxybutanedoic acid with N -[2-(diethylamino)ethyl]-5-[( Z )-(5-fluoro-1,2-dihydro-2-oxo- 3H -indol-3-ylidine)methyl]-2,4-dimethyl- 1H -pyrrole-3-carboxamide (1:1). The molecular formula is C 22 H 27 FN 4 O 2 • C 4 H 6 O 5 and the molecular weight is 532.6 Daltons.
The chemical structure of sunitinib malate is: Sunitinib malate is a yellow to orange powder with a pKa of 8.95. The solubility of sunitinib malate in aqueous media over the range pH 1.2 to pH 6.8 is in excess of 25 mg/mL. The log of the distribution coefficient (octanol/water) at pH 7 is 5.2.
Sunitinib malate capsules are supplied as printed hard shell capsules containing 12.5 mg, 25 mg, 37.5 mg or 50 mg of sunitinib (equivalent to 16.71 mg, 33.41 mg, 50.12 mg, or 66.83 mg of sunitinib malate, respectively). The capsules contain the following inactive ingredients: croscarmellose sodium, magnesium stearate, mannitol, and povidone. The red opaque gelatin capsule shells contain gelatin, iron oxide red, and titanium dioxide; the olive green opaque gelatin capsule shells contain FD&C Blue 2, gelatin, iron oxide red, iron oxide yellow, and titanium dioxide; and the light green opaque gelatin capsule shells contain FD&C Blue 2, gelatin, iron oxide yellow, and titanium dioxide.
The white printing ink contains potassium hydroxide, propylene glycol, shellac, and titanium dioxide and the black printing ink contains black iron oxide, potassium hydroxide, propylene glycol, and shellac. sunitinib-str
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Hepatotoxicity Inform patients of the signs and symptoms of hepatotoxicity. Advise patients to contact their healthcare provider immediately for signs or symptoms of hepatotoxicity [see Warnings and Precautions (5.1) ] .
Cardiovascular Events Advise patients to contact their healthcare provider if they develop symptoms of heart failure [see Warnings and Precautions (5.2) ] . QT Prolongation and Torsade de Pointes Inform patients of the signs and symptoms of QT prolongation. Advise patients to contact their healthcare provider immediately in the event of syncope, pre-syncopal symptoms, and cardiac palpitations [see Warnings and Precautions (5.3) ] .
Hypertension Inform patients of the signs and symptoms of hypertension. Advise patients to undergo routine blood pressure monitoring and to contact their health care provider if blood pressure is elevated or if they experience signs or symptoms of hypertension [see Warnings and Precautions (5.4) ] . Hemorrhagic Events Advise patients that sunitinib malate can cause severe bleeding.
Advise patients to immediately contact their healthcare provider for bleeding or symptoms of bleeding [see Warnings and Precautions (5.5) ] . Gastrointestinal Disorders Advise patients that gastrointestinal disorders such as diarrhea, nausea, vomiting, and constipation may develop during sunitinib malate treatment and to seek immediate medical attention if they experience persistent or severe abdominal pain because cases of gastrointestinal perforation and fistula have been reported in patients taking sunitinib malate [see Warnings and Precautions (5.5), Adverse Reactions (6.1) ].
Dermatologic Effects and Toxicities Advise patients that depigmentation of the hair or skin may occur during treatment with sunitinib malate due to the drug color (yellow). Other possible dermatologic effects may include dryness, thickness or cracking of skin, blister or rash on the palms of the hands and soles of the feet. Severe dermatologic toxicities including Stevens-Johnson syndrome, Toxic Epidermal Necrolysis, erythema multiforme, and necrotizing fasciitis have been reported.
Advise patients to immediately inform their healthcare provider if severe dermatologic reactions occur [see Warnings and Precautions (5.9) , Adverse Reactions (6.1 )]. Reversible Posterior Leukoencephalopathy Syndrome Inform patients of the signs and symptoms of reversible posterior leukoencephalopathy syndrome. Advise patients to contact their healthcare provider if they develop symptoms of reversible posterior leukoencephalopathy syndrome [see Warnings and Precautions (5.10) ] .
Thyroid Dysfunction Advise patients that sunitinib malate can cause thyroid dysfunction. Advise patient to contact their healthcare provider if symptoms of abnormal thyroid function occur [see Warnings and Precautions (5.11) ] . Hypoglycemia Advise patients that sunitinib malate can cause severe hypoglycemia and may be more severe in patients with diabetes taking antidiabetic medications.
Inform patients of the signs, symptoms, and risks associated with hypoglycemia. Advise patients to immediately inform their healthcare provider if severe signs or symptoms of hypoglycemia occur [see Warnings and Precautions (5.12) ] . Osteonecrosis of the Jaw Advise patients regarding good oral hygiene practices and to inform their healthcare provider of any planned dental procedures.
Advise patients to immediately contact their healthcare provider for signs or symptoms associated with osteonecrosis of the jaw [see Warnings and Precautions (5.13) ] . Impaired Wound Healing Advise patients that sunitinib malate impairs wound healing. Advise patients to inform their healthcare provider of any planned surgical procedures [see Warnings and Precautions (5.14) ] .
Concomitant Medications Advise patients to inform their healthcare providers of all concomitant medications, including o…
💬 Medication Guide ▾
MEDICATION GUIDE Sunitinib Malate Capsules (soo ni’ ti nib mal’ ate) What is the most important information I should know about sunitinib malate capsules? Sunitinib malate capsules can cause serious side effects including: • Severe liver problems, that can lead to death. Tell your healthcare provider right away if you develop any of the following signs and symptoms of liver problems during treatment with sunitinib malate capsules: o itching o yellow eyes or skin o dark urine o pain or discomfort in the right upper stomach area Your healthcare provider should do blood tests to check your liver function before you start taking and during treatment with sunitinib malate capsules.
Your healthcare provider may temporarily stop, reduce your dose, or permanently stop treatment with sunitinib malate capsules if you develop liver problems. See “What are the possible side effects of sunitinib malate capsules?” for more information about side effects. What are sunitinib malate capsules?
Sunitinib malate capsule is a prescription medicine used to treat: • a rare cancer of the stomach, bowel, or esophagus called gastrointestinal stromal tumor (GIST) and when: you have taken the medicine imatinib mesylate and it did not stop the cancer from growing, or you cannot take imatinib mesylate . • advanced kidney cancer (advanced renal cell carcinoma or RCC). • adults with kidney cancer that has not spread (localized), and who are at high risk of RCC coming back again after having kidney surgery. • a type of pancreatic cancer called pancreatic neuroendocrine tumors (pNET), that has progressed and cannot be treated with surgery.
It is not known if sunitinib malate capsules are safe and effective in children. Before taking sunitinib malate capsules tell your healthcare provider about all of your medical conditions, including if you: • have any heart problems • have high blood pressure • have thyroid problems • have a history of low blood sugar or diabetes • have kidney function problems (other than cancer) • have liver problems • have any bleeding problem • plan to have surgery or have had a recent surgery. You should stop taking sunitinib malate capsules at least 3 weeks before planned surgery.
See “ What are the possible side effects of sunitinib malate capsules?” • have seizures • have or have had pain in the mouth, teeth or jaw, swelling or sores inside the mouth, numbness or a feeling of heaviness in the jaw, or loosening of a tooth • are pregnant or plan to become pregnant. Sunitinib malate capsules can harm your unborn baby. Females who are able to become pregnant: Your healthcare provider should do a pregnancy test before you start treatment with sunitinib malate capsules.
You should use effective birth control (contraception) during treatment and for at least 4 weeks after your last dose of sunitinib malate capsules. Tell your healthcare provider right away if you become pregnant or think you are pregnant during treatment with sunitinib malate capsules. Males with female partners who are able to become pregnant should use effective birth control (contraception) during treatment and for 7 weeks after your last dose of sunitinib malate capsules.
Sunitinib malate capsules may cause fertility problems in males and females. Tell your healthcare provider if this is a concern for you. are breastfeeding or plan to breastfeed. Do not breastfeed during treatment with sunitinib malate capsules and for at least 4 weeks (1 month) after the last dose.
Tell all of your healthcare providers and dentists that you are taking sunitinib malate capsules. They should talk to the healthcare provider who prescribed sunitinib malate capsules for you, before you have any surgery, or medical or dental procedure. Tell your healthcare provider about all the medicines you take, including prescription medicines and over-the-counter medicines, vitamins, and herbal supplements.
Using sunitinib malate capsules with certain other medicines can cause serious side effects. You…