
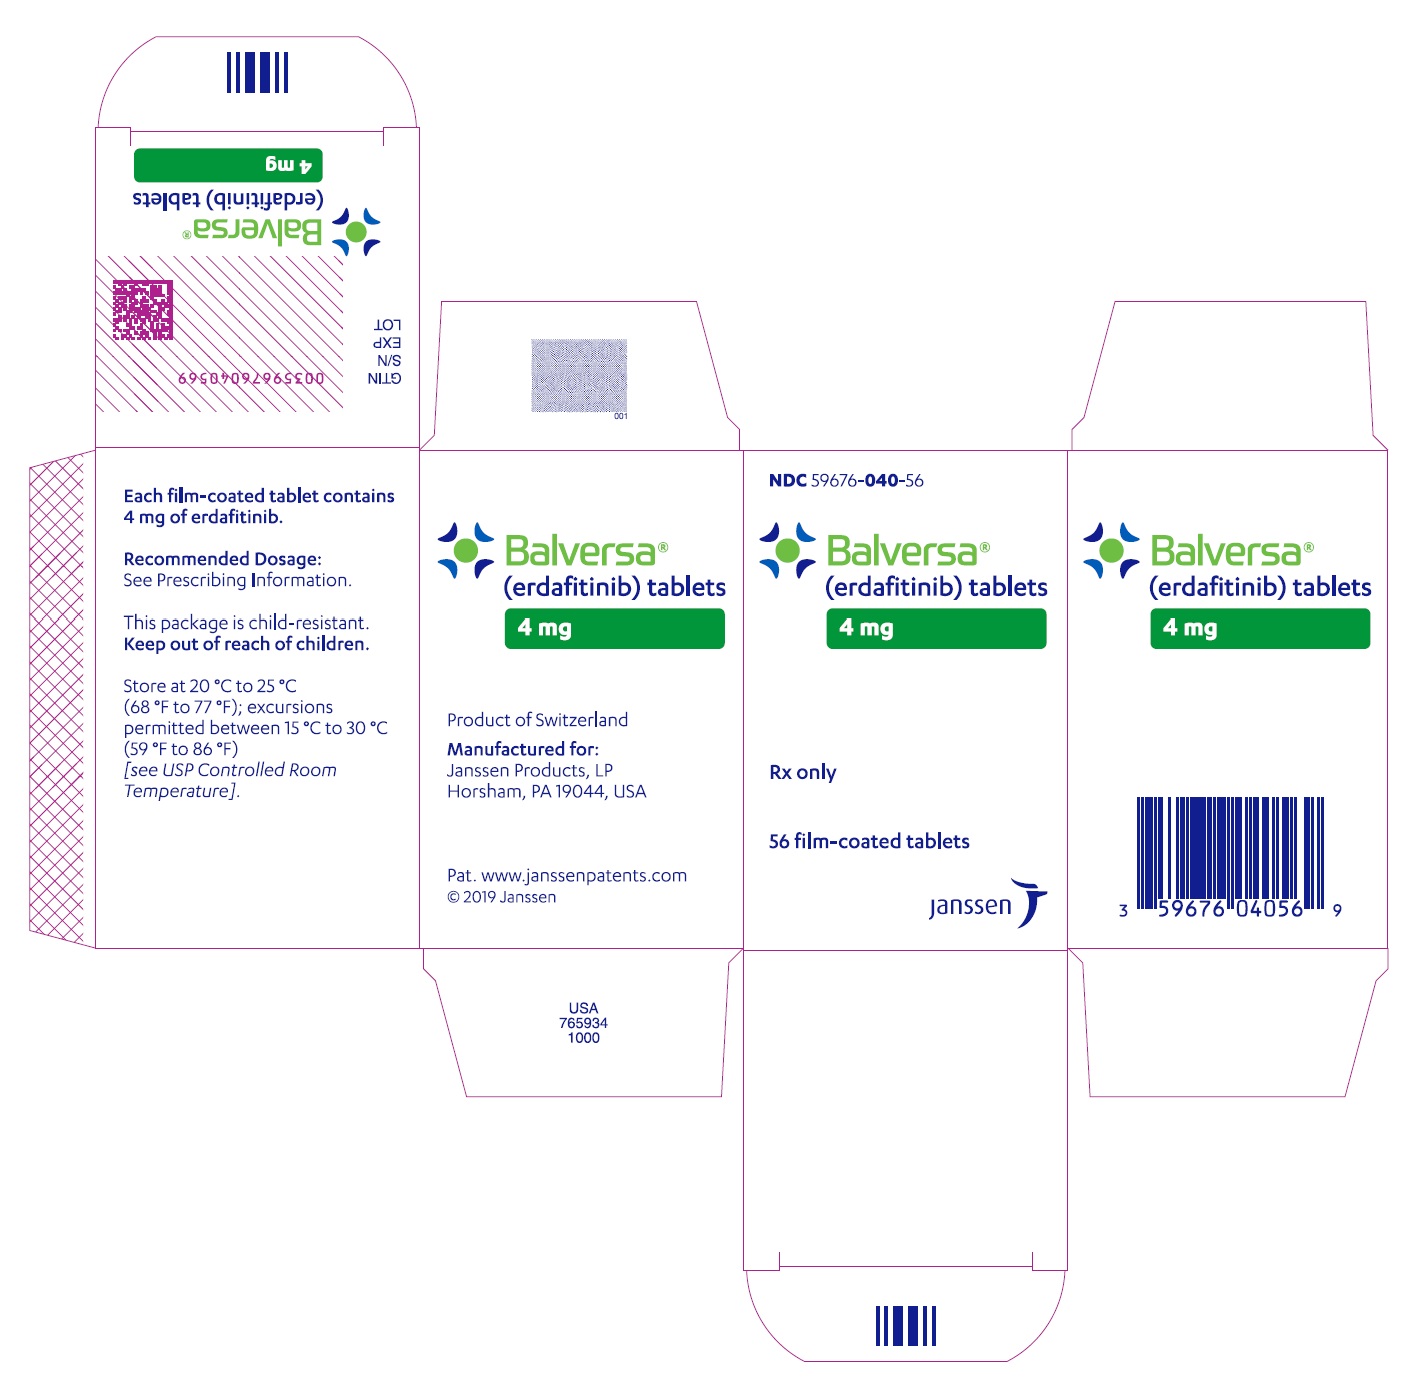
BALVERSA Erdafitinib 4 mg Tablet, Film Coated, 28-count — NDC 59676-040-28 (Billing 59676-0040-28)
This is a package of 28 tablets of BALVERSA Erdafitinib 4 mg Tablet, Film Coated from Janssen Products LP, marketed since Apr 2019 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 59676-040-28 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 59676 labeler · 040 product · 28 package
- Package marketed since
- Apr 12, 2019
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 28 EA per package
- Barcode (UPC-A, from the NDC)
- 3 5967604028 6
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 079651
- GCN: 46192
- GPI-14 (Medi-Span): 21532225000325
- HICL (First Databank): 045687
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 2123131
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Erdafitinib is used to treat certain types of urothelial cancer (cancer of the lining of the bladder and other parts of the urinary tract). Erdafitinib is in a class of medications called kinase inhibitors. It works by blocking the action of an abnormal protein that signals cancer cells to multiply. This helps slow or stop the spread of cancer cells.
Read the full MedlinePlus article ↗- It treats adults with advanced bladder or urinary tract cancer (urothelial carcinoma) that has a certain FGFR3 gene change. It's used after at least one earlier treatment has stopp...
- Swallow the tablets whole once a day, with or without food. If you vomit, wait until the next day for your next dose. If you miss one, take it later that same day, then go back to...
- Common ones include nail changes, mouth sores, diarrhea, dry mouth, dry skin, dry eyes, tiredness, appetite loss and taste changes. Many people need dose adjustments, so tell your...
- Balversa can cause a retina problem called central serous retinopathy, which may affect your vision. You'll have exams monthly for the first four months and then every three months...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Erdafitinib — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $391.01 | $10,948.40 / 28 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 59676-0040-28 You're viewing this Main listing | 1 BOTTLE in 1 CARTON / 28 TABLET, FILM COATED in 1 BOTTLE | 2019-04-12 | — | Active |
| 59676-0040-56 59676-040-56 | 1 BOTTLE in 1 CARTON / 56 TABLET, FILM COATED in 1 BOTTLE | 2019-04-12 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 59676-0040-56?
What NDC number is used to bill for this package of BALVERSA Erdafitinib 4 mg Tablet, Film Coated?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Balversa 4 mgthis 59676-0040-28 | Janssen | 28 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10898482 ↗ | Method of use | U-3066 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3065 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3067 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-2518 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3067 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3066 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-2518 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3065 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3067 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3066 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-2518 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3065 | Feb 9, 2036 |
| US 12037644 ↗ | Method of use | U-3972 | Oct 18, 2035 |
| US 12037644 ↗ | Method of use | U-3972 | Oct 18, 2035 |
| US 12037644 ↗ | Method of use | U-3972 | Oct 18, 2035 |
| US 11077106 ↗ | Method of use | U-3196 | Feb 2, 2038 |
| US 11077106 ↗ | Method of use | U-3196 | Feb 2, 2038 |
| US 11077106 ↗ | Method of use | U-3196 | Feb 2, 2038 |
| US 10478494 ↗ | Method of use | U-3902 | Aug 13, 2036 |
| US 10478494 ↗ | Method of use | U-3902 | Aug 13, 2036 |
| US 10478494 ↗ | Method of use | U-3902 | Aug 13, 2036 |
| US 10898482 ↗ | Method of use | U-3805 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3807 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3806 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3806 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3807 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3805 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3807 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3805 | Feb 9, 2036 |
| US 10898482 ↗ | Method of use | U-3806 | Feb 9, 2036 |
| US 9464071 ↗ | Method of use | U-3805 | Apr 28, 2031 |
| US 9464071 ↗ | Method of use | U-3805 | Apr 28, 2031 |
| US 9464071 ↗ | Method of use | U-3805 | Apr 28, 2031 |
| US 11684620 ↗ | Method of use | U-3805 | Feb 9, 2036 |
| US 11684620 ↗ | Method of use | U-3805 | Feb 9, 2036 |
| US 11684620 ↗ | Method of use | U-3805 | Feb 9, 2036 |
| US 11077106 ↗ | Method of use | U-3808 | Feb 2, 2038 |
| US 11684620 ↗ | Method of use | U-3807 | Feb 9, 2036 |
| US 11684620 ↗ | Method of use | U-3806 | Feb 9, 2036 |
| US 11684620 ↗ | Method of use | U-3807 | Feb 9, 2036 |
| US 11684620 ↗ | Method of use | U-3806 | Feb 9, 2036 |
| US 11077106 ↗ | Method of use | U-3808 | Feb 2, 2038 |
| US 11077106 ↗ | Method of use | U-3808 | Feb 2, 2038 |
| US 11684620 ↗ | Method of use | U-3807 | Feb 9, 2036 |
| US 11684620 ↗ | Method of use | U-3806 | Feb 9, 2036 |
| US 12678498 ↗ | Method of use | U-4584 | Jun 13, 2036 |
| US 12678498 ↗ | Method of use | U-4584 | Jun 13, 2036 |
| US 12678498 ↗ | Method of use | U-4584 | Jun 13, 2036 |
| US 8895601 ↗ | Drug substance | — | Apr 12, 2033 |
| US 9902714 ↗ | Drug product | — | Mar 26, 2035 |
| US 8895601 ↗ | Drug substance | — | Apr 12, 2033 |
| US 9902714 ↗ | Drug product | — | Mar 26, 2035 |
| US 9902714 ↗ | Drug product | — | Mar 26, 2035 |
| US 8895601 ↗ | Drug substance | — | Apr 12, 2033 |
| Code | What it grants | Expires |
|---|---|---|
| I-930 | New indication (3-year) | Jan 19, 2027 |
| I-930 | New indication (3-year) | Jan 19, 2027 |
| I-930 | New indication (3-year) | Jan 19, 2027 |
Is there a generic version of BALVERSA 4 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Erdafitinib inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII G7515SW10N
A waxy liquid derived from vegetable oil and fatty acids. It works as an emulsifier and solubilizer to help blend oil and water-based ingredients together and improve how the medicine dissolves and is absorbed in the body.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 6HG8UB2MUY
Meglumine is a sugar-alcohol compound used as a solubilizer and pH buffer in medicines. It helps dissolve drugs that don't mix well in water and maintains stable acidity levels in the formulation.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Janssen Products LP labeler code 59676
- BALVERSA Erdafitinib 3 mg Tablet, Film Coated NDC 59676-030-56
- BALVERSA Erdafitinib 5 mg Tablet, Film Coated NDC 59676-050-28
- Edurant rilpivirine hydrochloride 25 mg Tablet, Film Coated NDC 59676-278-01
- Edurant Ped rilpivirine hydrochloride 2.5 mg Tablet, For Suspension NDC 59676-280-90
- PROCRIT Erythropoietin 2000 [iU]/mL Injection, Solution NDC 59676-302-01
- PROCRIT Erythropoietin 3000 [iU]/mL Injection, Solution NDC 59676-303-01
- PROCRIT Erythropoietin 4000 [iU]/mL Injection, Solution NDC 59676-304-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BALVERSA is indicated for the treatment of adult patients with locally advanced or metastatic urothelial carcinoma (mUC) with susceptible FGFR3 genetic alterations whose disease has progressed on or after at least one line of prior systemic therapy. Select patients for therapy based on an FDA-approved companion diagnostic for BALVERSA [see Dosage and Administration (2.1) and Clinical Studies (14.1) ] . BALVERSA is a kinase inhibitor indicated for the treatment of adult patients with locally advanced or metastatic urothelial carcinoma (mUC) with susceptible FGFR3 genetic alterations whose disease has progressed on or after at least one line of prior systemic therapy.
Select patients for therapy based on an FDA-approved companion diagnostic for BALVERSA. ( 1 , 2.1 ) Limitations of Use BALVERSA is not recommended for the treatment of patients who are eligible for and have not received prior PD-1 or PD-L1 inhibitor therapy. ( 1 , 14.1 ) Limitations of Use BALVERSA is not recommended for the treatment of patients who are eligible for and have not received prior PD-1 or PD-L1 inhibitor therapy [see Clinical Studies (14.1) ] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Confirm the presence of FGFR3 genetic alterations in tumor specimens prior to initiation of treatment with BALVERSA. ( 2.1 ) Recommended initial dosage: 8 mg orally once daily with a dose increase to 9 mg daily if criteria are met. ( 2.2 ) Swallow whole with or without food. ( 2.2 )
2.1Patient Selection Select patients for the treatment of locally advanced or metastatic urothelial carcinoma with BALVERSA based on the presence of susceptible FGFR3 genetic alterations in tumor specimens as detected by an FDA-approved companion diagnostic [see Clinical Studies (14.1) ] . Information on FDA-approved tests for the detection of FGFR3 genetic alterations in urothelial cancer is available at: http://www.fda.gov/CompanionDiagnostics.
2.2Recommended Dosage and Schedule The recommended starting dose of BALVERSA is 8 mg (two 4 mg tablets) orally once daily, with a dose increase to 9 mg (three 3 mg tablets) once daily based on tolerability, including hyperphosphatemia, at 14 to 21 days [see Dosage and Administration (2.3) ]. Swallow tablets whole with or without food. If vomiting occurs any time after taking BALVERSA, the next dose should be taken the next day.
Treatment should continue until disease progression or unacceptable toxicity occurs. If a dose of BALVERSA is missed, it can be taken as soon as possible on the same day. Resume the regular daily dose schedule for BALVERSA the next day.
Extra tablets should not be taken to make up for the missed dose. Dose Increase based on Serum Phosphate Levels Assess serum phosphate levels 14 to 21 days after initiating treatment. Increase the dose of BALVERSA to 9 mg once daily if serum phosphate level is < 9.0 mg/dL and there are no ocular disorders or Grade 2 or greater adverse reactions.
If the phosphate level is 9.0 mg/dL or higher follow the relevant dose modifications in Table 2. Monitor phosphate levels monthly for hyperphosphatemia [see Pharmacodynamics (12.2) ] .
2.3Dose Modifications for Adverse Reactions The recommended dose modifications for adverse reactions are listed in Table 1. Table 1: BALVERSA Dose Reduction Schedule Dose 1 st dose reduction 2 nd dose reduction 3 rd dose reduction 4 th dose reduction 5 th dose reduction 9 mg ➞ (three 3 mg tablets) 8 mg (two 4 mg tablets) 6 mg (two 3 mg tablets) 5 mg (one 5 mg tablet) 4 mg (one 4 mg tablet) Stop 8 mg ➞ (two 4 mg tablets) 6 mg (two 3 mg tablets) 5 mg (one 5 mg tablet) 4 mg (one 4 mg tablet) Stop Table 2 summarizes recommendations for dose interruption, reduction, or discontinuation of BALVERSA in the management of specific adverse reactions.
Table 2: Dose Modifications for Adverse Reactions Adverse Reaction BALVERSA Dose Modification Hyperphosphatemia In all patients, restrict phosphate intake to 600–800 mg daily. <6.99 mg/dL Continue BALVERSA at current dose. 7–8.99 mg/dL Continue BALVERSA at current dose. Start phosphate binder with food until phosphate level is <7 mg/dL.
Reduce the dose if serum phosphate remains ≥7 mg/dL for a period of 2 months or if clinically necessary. 9–10 mg/dL Withhold BALVERSA with weekly reassessments until level returns to <7 mg/dL. Then restart BALVERSA at the same dose level.
Start phosphate binder with food until serum phosphate level returns to <7 mg/dL. Reduce the dose if serum phosphate remains ≥9 mg/dL for a period of 1 month or if clinically necessary. >10 mg/dL Withhold BALVERSA with weekly reassessments until level returns to <7 mg/dL. Then may restart BALVERSA at the first reduced dose level.
If hyperphosphatemia (≥10 mg/dL) for >2 weeks, discontinue BALVERSA permanently. Medical management of symptoms as clinically relevant. Serum phosphate with life-threatening consequences; urgent intervention indicated (e.g., dialysis) Discontinue BALVERSA permanently.
Central Serous Retinopathy (CSR) Any Withhold BALVERSA and perform an ophthalmic evaluation within 2 weeks: If improving within 14 days, restart BALVERSA at the current dose. If not improving within 14 day… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 3 mg, 4 mg, and 5 mg. ( 3 ) Tablets: 3 mg: Yellow, round biconvex, film-coated, debossed with "3" on one side; and "EF" on the other side. 4 mg: Orange, round biconvex, film-coated, debossed with "4" on one side; and "EF" on the other side. 5 mg: Brown, round biconvex, film-coated, debossed with "5" on one side; and "EF" on the other side.
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Ocular disorders: BALVERSA can cause central serous retinopathy/retinal pigment epithelial detachment (CSR/RPED). Perform monthly ophthalmological examinations during the first four months of treatment, every 3 months afterwards, and at any time for visual symptoms. Withhold BALVERSA when CSR/RPED occurs and permanently discontinue if it does not resolve within 4 weeks or if Grade 4 in severity.
( 2.3 , 5.1 ) Hyperphosphatemia: Increases in phosphate levels are a pharmacodynamic effect of BALVERSA. Monitor for hyperphosphatemia and manage with dose modifications when required. ( 2.3 , 5.2 ) Embryo-fetal toxicity: Can cause fetal harm.
Advise patients of the potential risk to the fetus and to use effective contraception ( 5.3 , 8.1 , 8.3)
5.1Ocular Disorders BALVERSA can cause ocular disorders, including central serous retinopathy/retinal pigment epithelial detachment (CSR/RPED) resulting in visual field defect. In the pooled safety population [see Adverse Reactions (6) ] , CSR/RPED occurred in 22% of patients treated with BALVERSA, with a median time to first onset of 46 days. In 104 patients with CSR, 40% required dose interruptions and 56% required dose reductions; 2.9% of BALVERSA-treated patients required permanent discontinuation for CSR.
Of the 24 patients who restarted BALVERSA after dose interruption with or without dose reduction, 67% had recurrence and/or worsening of CSR after restarting. CSR was ongoing in 41% of the 104 patients at the time of last evaluation. Dry eye symptoms occurred in 26% of BALVERSA-treated patients.
All patients should receive dry eye prophylaxis with ocular demulcents as needed. Perform monthly ophthalmological examinations during the first 4 months of treatment and every 3 months afterwards, and urgently at any time for visual symptoms. Ophthalmological examination should include assessment of visual acuity, slit lamp examination, fundoscopy, and optical coherence tomography.
Withhold or permanently discontinue BALVERSA based on severity and/or ophthalmology exam findings [see Dosage and Administration (2.3) ] .
5.2Hyperphosphatemia and Soft Tissue Mineralization BALVERSA can cause hyperphosphatemia leading to soft tissue mineralization, cutaneous calcinosis, non-uremic calciphylaxis and vascular calcification. Increases in phosphate levels are a pharmacodynamic effect of BALVERSA [see Pharmacodynamics (12.2) ]. In the pooled safety population [see Adverse Reactions (6) ], increased phosphate occurred in 73% of BALVERSA-treated patients.
The median onset time of increased phosphate was 16 days (range: 8–421) after initiating BALVERSA. Twenty-four percent of patients received phosphate binders during treatment with BALVERSA. Vascular calcification was observed in 0.2% of patients treated with BALVERSA.
Monitor for hyperphosphatemia throughout treatment. Restrict dietary phosphate intake (600–800 mg daily) and avoid concomitant use of agents that may increase serum phosphate levels. If serum phosphate is above 7.0 mg/dL, consider adding an oral phosphate binder until serum phosphate level returns to <7.0 mg/dL.
Withhold, dose reduce, or permanently discontinue BALVERSA based on duration and severity of hyperphosphatemia according to Table 2 [see Dosage and Administration (2.3) ].
5.3Embryo-Fetal Toxicity Based on the mechanism of action and findings in animal reproduction studies, BALVERSA can cause fetal harm when administered to a pregnant woman. In an embryo-fetal toxicity study, oral administration of erdafitinib to pregnant rats during the period of organogenesis caused malformations and embryo-fetal death at maternal exposures that were less than the human exposures at the maximum human recommended dose based on area under the curve (AUC). Advise pregnant women of the potential risk to the fetus.
Advise female patients of reproductive potential to use effective contraception during treatment with BALVERSA and for one month after the last dose. Advise male… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are also described elsewhere in the labeling: Ocular Disorders [see Warnings and Precautions (5.1) ] . Hyperphosphatemia [see Warnings and Precautions (5.2) ] . The most common (>20%) adverse reactions, including laboratory abnormalities, were increased phosphate, nail disorders, stomatitis, diarrhea, increased creatinine, increased alkaline phosphatase, increased alanine aminotransferase, decreased hemoglobin, decreased sodium, increased aspartate aminotransferase, fatigue, dry mouth, dry skin, decreased phosphate, decreased appetite, dysgeusia, constipation, increased calcium, dry eye, palmar-plantar erythrodysesthesia syndrome, increased potassium, alopecia, and central serous retinopathy.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Janssen Products, LP. at 1-800-526-7736 (1-800-JANSSEN and www.BALVERSA.com) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The pooled safety population described in the WARNINGS AND PRECAUTIONS reflects exposure to BALVERSA as a single agent at the recommended dose (8 to 9 mg orally daily) in 479 patients with advanced urothelial cancer and FGFR alterations in 42756493BLC3001 (NCT03390504), 42756493BLC2001 (NCT02365597), 42756493BLC2002 (NCT 03473743), and 42756493EDI1001 (NCT01703481).
Among 479 patients who received BALVERSA, the median duration of treatment was 4.8 months (range: 0.1 to 43 months). In this pooled safety population, the most common (>20%) adverse reactions, including laboratory abnormalities, were increased phosphate, nail disorders, stomatitis, diarrhea, increased creatinine, increased alkaline phosphatase, increased alanine aminotransferase, decreased hemoglobin, decreased sodium, increased aspartate aminotransferase, fatigue, dry mouth, dry skin, decreased phosphate, decreased appetite, dysgeusia, constipation, increased calcium, dry eye, palmar-plantar erythrodysesthesia syndrome, increased potassium, alopecia, and central serous retinopathy.
BLC3001 The safety of BALVERSA was evaluated in Cohort 1 of the BLC3001 study that included patients with locally advanced unresectable or metastatic urothelial carcinoma which had susceptible FGFR3 genetic alterations and were previously treated with a PD-1 or PD-L1 inhibitor [see Clinical Studies (14.1) ] . Patients received either BALVERSA (8 mg orally once daily with individualized up-titration to 9 mg) (n=135) or chemotherapy (docetaxel 75 mg/m 2 once every 3 weeks or vinflunine 320 mg/m 2 once every 3 weeks) (n=112).
Among patients who received BALVERSA, median duration of treatment was 4.8 months (range: 0.2 to 38 months). Serious adverse reactions occurred in 41% of patients who received BALVERSA. Serious reactions in >2% of patients included urinary tract infection (4.4%), hematuria (3.7%), hyponatremia (2.2%), and acute kidney injury (2.2%).
Fatal adverse reactions occurred in 4.4% of patients who received BALVERSA, including sudden death (1.5%), pneumonia (1.5%), renal failure (0.7%), and cardiorespiratory arrest (0.7%). Permanent discontinuation of BALVERSA due to an adverse reaction occurred in 14% of patients. Adverse reactions which resulted in permanent discontinuation of BALVERSA in >2% of patients included nail disorders (3%) and eye disorders (2.2%).
Dosage interruptions of BALVERSA due to an adverse reaction occurred in 72% of patients. Adverse reactions which required dosage interruption in >4% of patients included nail disorders (22%), stomatitis (19%), eye disorders (16%), palmar-plantar erythrodysesthesia syndrome (15%), diarrhea (10%), hyperphosphatemia (7%), increased aspartate aminotransferase (6%), and increased alanine aminotransferase (5%).… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Moderate CYP2C9 or strong CYP3A4 inhibitors: Consider alternative agents or monitor closely for adverse reactions. ( 7.1 ) Strong CYP3A4 inducers: Avoid concomitant use with BALVERSA. ( 7.1 ) Moderate CYP3A4 inducers: Administer BALVERSA at a dose of 9 mg.
( 7.1 ) Serum phosphate level-altering agents: Avoid concomitant use with agents that can alter serum phosphate levels before the initial dose modification period. ( 2.3 , 7.1 ) P-gp substrates: Separate BALVERSA administration by at least 6 hours before or after administration of P-gp substrates with narrow therapeutic indices. ( 7.2 )
7.1Effect of Other Drugs on BALVERSA Table 7 summarizes drug interactions that affect the exposure of BALVERSA or serum phosphate level and their clinical management. Table 7: Drug Interactions that Affect BALVERSA Moderate CYP2C9 or Strong CYP3A4 Inhibitors Clinical Impact Co-administration of BALVERSA with moderate CYP2C9 or strong CYP3A4 inhibitors increased erdafitinib plasma concentrations [see Clinical Pharmacology (12.3) ]. Increased erdafitinib plasma concentrations may lead to increased drug-related toxicity [see Warnings and Precautions (5) ].
Clinical Management Consider alternative therapies that are not moderate CYP2C9 or strong CYP3A4 inhibitors during treatment with BALVERSA. If co-administration of a moderate CYP2C9 or strong CYP3A4 inhibitor is unavoidable, monitor closely for adverse reactions and consider dose modifications accordingly [see Dosage and Administration (2.3) ]. If the moderate CYP2C9 or strong CYP3A4 inhibitor is discontinued, resume the BALVERSA dose before dose modifications in the absence of drug-related toxicity.
Strong CYP3A4 Inducers Clinical Impact Co-administration of BALVERSA with strong CYP3A4 inducers decreased erdafitinib plasma concentrations [see Clinical Pharmacology (12.3) ]. Decreased erdafitinib plasma concentrations may lead to decreased activity. Clinical Management Avoid co-administration of strong CYP3A4 inducers with BALVERSA.
Moderate CYP3A4 Inducers Clinical Impact Co-administration of BALVERSA with moderate CYP3A4 inducers may decrease erdafitinib plasma concentrations [see Clinical Pharmacology (12.3) ]. Decreased erdafitinib plasma concentrations may lead to decreased activity. Clinical Management If a moderate CYP3A4 inducer must be co-administered at the start of BALVERSA treatment, administer BALVERSA at a dose of 9 mg daily.
When a moderate CYP3A4 inducer is discontinued, continue BALVERSA at the same dose, in the absence of drug-related toxicity. Serum Phosphate Level-Altering Agents Clinical Impact Co-administration of BALVERSA with other serum phosphate level-altering agents may increase or decrease serum phosphate levels [see Pharmacodynamics (12.2) ]. Changes in serum phosphate levels due to serum phosphate level-altering agents (other than erdafitinib) may interfere with serum phosphate levels needed for the determination of initial dose increased based on serum phosphate levels [see Dosage and Administration (2.3) ].
Clinical Management Avoid co-administration of serum phosphate level-altering agents with BALVERSA before initial dose increase period based on serum phosphate levels (Days 14 to 21) [see Dosage and Administration (2.3) ].
7.2Effect of BALVERSA on Other Drugs Table 8 summarizes the effect of BALVERSA on other drugs and their clinical management. Table 8: BALVERSA Drug Interactions that Affect Other Drugs P-glycoprotein (P-gp) Substrates Clinical Impact Co-administration of BALVERSA with P-gp substrates may increase the plasma concentrations of P-gp substrates [see Clinical Pharmacology (12.3) ]. Increased plasma concentrations of P-gp substrates may lead to increased toxicity of the P-gp substrates.
Clinical Management If co-administration of BALVERSA with P-gp substrates is unavoidable, separate BALVERSA administration by at least 6 hours before or after administration of P-gp substrates with narrow therapeutic index.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on the mechanism of action and findings in animal reproduction studies, BALVERSA can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data on BALVERSA use in pregnant women to inform a drug-associated risk. Oral administration of erdafitinib to pregnant rats during organogenesis caused malformations and embryo-fetal death at maternal exposures that were less than the human exposures at the maximum recommended human dose based on AUC (see Data ) .
Advise pregnant women and females of reproductive potential of the potential risk to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Data Animal Data In an embryo-fetal toxicity study, erdafitinib was orally administered to pregnant rats during the period of organogenesis. Doses ≥4 mg/kg/day (at total maternal exposures <0.1% of total human exposures at the maximum recommended human dose based on AUC) produced embryo-fetal death, major blood vessel malformations and other vascular anomalies, limb malformations (ectrodactyly, absent or misshapen long bones), an increased incidence of skeletal anomalies in multiple bones (vertebrae, sternebrae, ribs), and decreased fetal weight.
8.2Lactation Risk Summary There are no data on the presence of erdafitinib in human milk, or the effects of erdafitinib on the breastfed child, or on milk production. Because of the potential for serious adverse reactions from erdafitinib in a breastfed child, advise lactating women not to breastfeed during treatment with BALVERSA and for one month following the last dose.
8.3Females and Males of Reproductive Potential BALVERSA can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to initiating treatment with BALVERSA. Contraception Females Advise females of reproductive potential to use effective contraception during treatment with BALVERSA and for one month after the last dose.
Males Advise male patients with female partners of reproductive potential to use effective contraception during treatment with BALVERSA and for one month after the last dose. Infertility Females Based on findings from animal studies, BALVERSA may impair fertility in females of reproductive potential [see Nonclinical Toxicology (13.1) ] .
8.4Pediatric Use Safety and effectiveness of BALVERSA in pediatric patients have not been established. Skeletal adverse reactions have occurred in pediatric patients treated with BALVERSA. In a study of BALVERSA that included pediatric patients ages 6 to <18 years with FGFR-positive advanced solid tumors, epiphysiolysis and bone fractures occurred.
In the postmarket setting and in literature reports, cases of slipped capital femoral epiphysis and accelerated linear growth in patients treated with BALVERSA have been reported. Juvenile Animal Toxicity Data In 4 and 13-week repeat-dose toxicology studies in rats and dogs, toxicities in bone and teeth were observed at an exposure less than the human exposure (AUC) at the maximum recommended human dose. Chondroid dysplasia/metaplasia were reported in multiple bones in both species, and tooth abnormalities included abnormal/irregular denting in rats and dogs and discoloration and degeneration of odontoblasts in rats.
8.5Geriatric Use Of the 479 patients treated with BALVERSA in clinical studies, 40% of patients were less than 65 years old, 40% of patients were 65 years to 74 years old, and 20% were 75 years old and over. Pati… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on the mechanism of action and findings in animal reproduction studies, BALVERSA can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data on BALVERSA use in pregnant women to inform a drug-associated risk. Oral administration of erdafitinib to pregnant rats during organogenesis caused malformations and embryo-fetal death at maternal exposures that were less than the human exposures at the maximum recommended human dose based on AUC (see Data ) .
Advise pregnant women and females of reproductive potential of the potential risk to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Data Animal Data In an embryo-fetal toxicity study, erdafitinib was orally administered to pregnant rats during the period of organogenesis. Doses ≥4 mg/kg/day (at total maternal exposures <0.1% of total human exposures at the maximum recommended human dose based on AUC) produced embryo-fetal death, major blood vessel malformations and other vascular anomalies, limb malformations (ectrodactyly, absent or misshapen long bones), an increased incidence of skeletal anomalies in multiple bones (vertebrae, sternebrae, ribs), and decreased fetal weight.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of BALVERSA in pediatric patients have not been established. Skeletal adverse reactions have occurred in pediatric patients treated with BALVERSA. In a study of BALVERSA that included pediatric patients ages 6 to <18 years with FGFR-positive advanced solid tumors, epiphysiolysis and bone fractures occurred.
In the postmarket setting and in literature reports, cases of slipped capital femoral epiphysis and accelerated linear growth in patients treated with BALVERSA have been reported. Juvenile Animal Toxicity Data In 4 and 13-week repeat-dose toxicology studies in rats and dogs, toxicities in bone and teeth were observed at an exposure less than the human exposure (AUC) at the maximum recommended human dose. Chondroid dysplasia/metaplasia were reported in multiple bones in both species, and tooth abnormalities included abnormal/irregular denting in rats and dogs and discoloration and degeneration of odontoblasts in rats.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 479 patients treated with BALVERSA in clinical studies, 40% of patients were less than 65 years old, 40% of patients were 65 years to 74 years old, and 20% were 75 years old and over. Patients 65 years of age and older treated with BALVERSA experienced a higher incidence of adverse reactions requiring treatment discontinuation than younger patients. In clinical trials, the incidence of treatment discontinuations of BALVERSA due to adverse reactions was 10% in patients younger than 65 years, 20% in patients ages 65–74 years, and 35% in patients 75 years or older.
No overall difference in efficacy was observed between these patients and younger patients [see Clinical Studies (14.1) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Erdafitinib is a kinase inhibitor that binds to and inhibits enzymatic activity of FGFR1, FGFR2, FGFR3 and FGFR4 based on in vitro data. Erdafitinib inhibited FGFR phosphorylation and signaling and decreased cell viability in cell lines expressing FGFR genetic alterations, including point mutations, amplifications, and fusions. Erdafitinib demonstrated antitumor activity in FGFR-expressing cell lines and xenograft models derived from tumor types, including bladder cancer.
12.2Pharmacodynamics Cardiac Electrophysiology Based on evaluation of QTc interval in an open-label, dose escalation and dose expansion study in 187 patients with cancer, erdafitinib had no large effect (i.e., > 20 ms) on the QTc interval. Serum Phosphate FGFR inhibition by BALVERSA increases serum phosphate level [see Dosage and Administration (2.3) and Drug Interactions (7.1) ].
12.3Pharmacokinetics Following administration of BALVERSA 8 mg once daily, the mean (coefficient of variation [CV%]) erdafitinib steady-state maximum plasma concentration (C max ), area under the curve (AUC tau ), and minimum plasma concentration (C min ) were 1,399 ng/mL (51%), 29,268 ng∙h/mL (60%), and 936 ng/mL (65%), respectively. Following single and repeat once daily dosing of BALVERSA, erdafitinib exposure (C max and AUC) increased proportionally across the dose range of 0.5 to 12 mg (0.06 to 1.3 times the maximum approved recommended dose).
Steady state was achieved after 2 weeks with once daily dosing with a mean accumulation ratio was 4-fold. Absorption Median time to achieve peak plasma concentration (t max ) was 2.5 hours (range: 2 to 6 hours). Effect of Food No clinically meaningful differences in erdafitinib exposure was observed following administration of BALVERSA with a high-fat and high-calorie meal (800 calories to 1,000 calories with approximately 50% of total caloric content of the meal from fat).
Distribution The mean apparent volume of distribution of erdafitinib was 29 L. Erdafitinib protein binding was 99.7% in patients, primarily to alpha-1-acid glycoprotein. Elimination The mean total apparent clearance (CL/F) of erdafitinib was 0.362 L/h.
The mean effective half-life of erdafitinib was 59 hours. Metabolism Erdafitinib is primarily metabolized by CYP2C9 and CYP3A4. The contribution of CYP2C9 and CYP3A4 in the total clearance of erdafitinib is estimated to be 39% and 20%, respectively.
Unchanged erdafitinib was the major drug-related moiety in plasma, there were no circulating metabolites. Excretion Following a single oral dose of radiolabeled erdafitinib, approximately 69% of the dose was recovered in feces (19% as unchanged) and 19% in urine (13% as unchanged). Specific Populations No clinically meaningful effects on erdafitinib exposure were observed based on age (21–92 years), sex, race (White, Hispanic or Asian), body weight (36–166 kg), mild (Child-Pugh A) or moderate (Child-Pugh B) hepatic impairment, or mild to moderate renal impairment (eGFR 30 to 89 mL/min/1.73 m²).
Limited data are available in patients with severe (Child-Pugh C) hepatic impairment and in patients with severe renal impairment. The pharmacokinetics of erdafitinib in patients with renal impairment requiring dialysis is unknown. Drug Interaction Studies Clinical Studies Effect of Other Drugs on Erdafitinib Moderate CYP2C9 Inhibitors Erdafitinib mean ratios for C max and AUC inf were 121% and 148%, respectively, when BALVERSA was co-administered with fluconazole, a moderate CYP2C9 and CYP3A4 inhibitor, relative to BALVERSA administered alone.
Strong CYP3A4 Inhibitors Erdafitinib mean ratios for C max and AUC inf were 105% and 134%, respectively, when BALVERSA was co-administered with itraconazole (a strong CYP3A4 inhibitor and P-gp inhibitor) relative to BALVERSA alone. CYP3A4/2C9 Inducers Erdafitinib mean ratios for C max and AUC inf were 78% and 45%, respectively, when BALVERSA was co-administered with carbamazepine (a strong CYP3… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Erdafitinib is a kinase inhibitor that binds to and inhibits enzymatic activity of FGFR1, FGFR2, FGFR3 and FGFR4 based on in vitro data. Erdafitinib inhibited FGFR phosphorylation and signaling and decreased cell viability in cell lines expressing FGFR genetic alterations, including point mutations, amplifications, and fusions. Erdafitinib demonstrated antitumor activity in FGFR-expressing cell lines and xenograft models derived from tumor types, including bladder cancer.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING BALVERSA ® (erdafitinib) tablets are available in the strengths and packages listed below: 3 mg tablets: Yellow, round biconvex, film-coated, debossed with "3" on one side and "EF" on the other side. Bottle of 56-tablets with child resistant closure (NDC 59676-030-56). Bottle of 84-tablets with child resistant closure (NDC 59676-030-84).
4 mg tablets: Orange, round biconvex, film-coated, debossed with "4" on one side and "EF" on the other side. Bottle of 28-tablets with child resistant closure (NDC 59676-040-28). Bottle of 56-tablets with child resistant closure (NDC 59676-040-56).
5 mg tablets: Brown, round biconvex, film-coated, debossed with "5" on one side and "EF" on the other side. Bottle of 28-tablets with child resistant closure (NDC 59676-050-28). Store at 20 °C to 25 °C (68 °F to 77 °F); excursions permitted between 15 °C to 30 °C (59 °F to 86 °F) [see USP Controlled Room Temperature] .
📦 Storage and Handling ▾
Store at 20 °C to 25 °C (68 °F to 77 °F); excursions permitted between 15 °C to 30 °C (59 °F to 86 °F) [see USP Controlled Room Temperature] .
📋 Description ▾
11 DESCRIPTION Erdafitinib, the active ingredient in BALVERSA, is a kinase inhibitor. The chemical name is N-(3,5-dimethoxyphenyl)-N'-(1-methylethyl)-N-[3-(1-methyl-1H-pyrazol-4-yl)quinoxalin-6-yl]ethane-1,2-diamine. Erdafitinib is a yellow powder.
It is practically insoluble, or insoluble to freely soluble in organic solvents, and slightly soluble to practically insoluble, or insoluble in aqueous media over a wide range of pH values. The molecular formula is C 25 H 30 N 6 O 2 and molecular weight is 446.56. Chemical structure of erdafitinib is as follows: BALVERSA ® (erdafitinib) tablets are supplied as 3 mg, 4 mg or 5 mg film-coated tablets for oral administration and contains the following inactive ingredients: Tablet Core: Croscarmellose sodium, Magnesium stearate (from vegetable source), Mannitol, Meglumine, and Microcrystalline Cellulose.
Film Coating: (Opadry amb II): Glycerol monocaprylocaprate Type I, Polyvinyl alcohol-partially hydrolyzed, Sodium lauryl sulfate, Talc, Titanium dioxide, Iron oxide yellow, Iron oxide red (for the orange and brown tablets only), Ferrosoferric oxide/iron oxide black (for the brown tablets only). Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). FGFR Genetic Alterations Advise patients that evidence of a susceptible FGFR3 mutation or gene fusion within the tumor specimen is necessary to identify patients for whom treatment is indicated [see Dosage and Administration (2.1) ] . Ocular Disorders Advise patients to contact their healthcare provider if they experience any visual changes [see Warnings and Precautions (5.1) ].
In order to prevent or treat dry eyes, advise patients to use artificial tear substitutes, hydrating or lubricating eye gels or ointments frequently, at least every 2 hours during waking hours [see Dosage and Administration (2.3) ]. Skin, Mucous or Nail Disorders Advise patients to contact their healthcare provider if they experience progressive or intolerable skin, mucous or nail disorders [see Adverse Reactions (6.1) ] . Hyperphosphatemia and Soft Tissue Mineralization Inform patients that BALVERSA may cause hyperphosphatemia and soft tissue mineralization.
Advise patients to immediately inform their healthcare provider of painful skin lesions or any symptoms related to acute change in phosphate levels such as muscle cramps, numbness, or tingling around the mouth [see Warnings and Precautions (5.2) ] . Advise patients that their healthcare provider will assess their serum phosphate level between 14 and 21 days of initiating treatment and will adjust the dose if needed [see Warnings and Precautions (5.2) ] . Advise patients to restrict phosphate intake to 600–800 mg daily.
During this initial phosphate-assessment period, advise patients to avoid concomitant use with agents that can alter serum phosphate levels. Advise patients that, after the initial phosphate assessment period, monthly phosphate level monitoring for hyperphosphatemia should be performed during treatment with BALVERSA [see Drug Interactions (7.1) ]. Drug Interactions Advise patients to inform their healthcare providers of all concomitant medications, including prescription medicines, over-the-counter drugs, and herbal products [see Drug Interactions (7.1 , 7.2) ] .
Dosing Instructions Instruct patients to swallow the tablets whole once daily with or without food. If vomiting occurs any time after taking BALVERSA, advise patients to take the next dose the next day [see Dosage and Administration (2.2) ] . Missed Dose If a dose is missed, advise patients to take the missed dose as soon as possible.
Resume the regular daily dose schedule for BALVERSA the next day. Extra tablets should not be taken to make up for the missed dose [see Dosage and Administration (2.3) ] . Embryo-Fetal Toxicity Advise pregnant women and females of reproductive potential of the potential risk to the fetus.
Advise females to inform their healthcare providers of a known or suspected pregnancy [see Warnings and Precautions (5.3) and Use in Specific Populations (8.1) ] . Advise female patients of reproductive potential to use effective contraception during treatment and for one month after the last dose of BALVERSA. Advise male patients with female partners of reproductive potential to use effective contraception during treatment and for one month after the last dose of BALVERSA [see Use in Specific Populations (8.3) ].
Lactation Advise females not to breastfeed during treatment with BALVERSA and for one month after the last dose [see Use in Specific Populations (8.2) ]. Infertility Advise females of reproductive potential that BALVERSA may impair fertility [see Use in Specific Populations (8.3) ].
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following administration of BALVERSA 8 mg once daily, the mean (coefficient of variation [CV%]) erdafitinib steady-state maximum plasma concentration (C max ), area under the curve (AUC tau ), and minimum plasma concentration (C min ) were 1,399 ng/mL (51%), 29,268 ng∙h/mL (60%), and 936 ng/mL (65%), respectively. Following single and repeat once daily dosing of BALVERSA, erdafitinib exposure (C max and AUC) increased proportionally across the dose range of 0.5 to 12 mg (0.06 to 1.3 times the maximum approved recommended dose).
Steady state was achieved after 2 weeks with once daily dosing with a mean accumulation ratio was 4-fold. Absorption Median time to achieve peak plasma concentration (t max ) was 2.5 hours (range: 2 to 6 hours). Effect of Food No clinically meaningful differences in erdafitinib exposure was observed following administration of BALVERSA with a high-fat and high-calorie meal (800 calories to 1,000 calories with approximately 50% of total caloric content of the meal from fat).
Distribution The mean apparent volume of distribution of erdafitinib was 29 L. Erdafitinib protein binding was 99.7% in patients, primarily to alpha-1-acid glycoprotein. Elimination The mean total apparent clearance (CL/F) of erdafitinib was 0.362 L/h.
The mean effective half-life of erdafitinib was 59 hours. Metabolism Erdafitinib is primarily metabolized by CYP2C9 and CYP3A4. The contribution of CYP2C9 and CYP3A4 in the total clearance of erdafitinib is estimated to be 39% and 20%, respectively.
Unchanged erdafitinib was the major drug-related moiety in plasma, there were no circulating metabolites. Excretion Following a single oral dose of radiolabeled erdafitinib, approximately 69% of the dose was recovered in feces (19% as unchanged) and 19% in urine (13% as unchanged). Specific Populations No clinically meaningful effects on erdafitinib exposure were observed based on age (21–92 years), sex, race (White, Hispanic or Asian), body weight (36–166 kg), mild (Child-Pugh A) or moderate (Child-Pugh B) hepatic impairment, or mild to moderate renal impairment (eGFR 30 to 89 mL/min/1.73 m²).
Limited data are available in patients with severe (Child-Pugh C) hepatic impairment and in patients with severe renal impairment. The pharmacokinetics of erdafitinib in patients with renal impairment requiring dialysis is unknown. Drug Interaction Studies Clinical Studies Effect of Other Drugs on Erdafitinib Moderate CYP2C9 Inhibitors Erdafitinib mean ratios for C max and AUC inf were 121% and 148%, respectively, when BALVERSA was co-administered with fluconazole, a moderate CYP2C9 and CYP3A4 inhibitor, relative to BALVERSA administered alone.
Strong CYP3A4 Inhibitors Erdafitinib mean ratios for C max and AUC inf were 105% and 134%, respectively, when BALVERSA was co-administered with itraconazole (a strong CYP3A4 inhibitor and P-gp inhibitor) relative to BALVERSA alone. CYP3A4/2C9 Inducers Erdafitinib mean ratios for C max and AUC inf were 78% and 45%, respectively, when BALVERSA was co-administered with carbamazepine (a strong CYP3A4 and weak CYP2C9 inducer) relative to BALVERSA alone. Effect of Erdafitinib on Other Drugs CYP3A4 Substrates: No clinically meaningful effect on the exposure of midazolam (a CYP3A4 substrate) was observed following coadministration with BALVERSA.
OCT2 Substrates : No clinically meaningful effect on the exposure of metformin (an OCT2 substrate) was observed following coadministration with BALVERSA. In Vitro Studies CYP Substrates Erdafitinib is a time dependent inhibitor and inducer of CYP3A4. Erdafitinib is not an inhibitor of other major CYP isozymes at clinically relevant concentrations.
Transporters Erdafitinib is a substrate and inhibitor of P-gp. P-gp inhibitors are not expected to affect erdafitinib exposure to a clinically relevant extent. Erdafitinib is an inhibitor of OCT2.
Erdafitinib does not inhibit BCRP, OATP1B, OATP1B3, OAT1, OAT3, OCT1, MATE-1, or MATE-2K at clinically relevant conc… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology Based on evaluation of QTc interval in an open-label, dose escalation and dose expansion study in 187 patients with cancer, erdafitinib had no large effect (i.e., > 20 ms) on the QTc interval. Serum Phosphate FGFR inhibition by BALVERSA increases serum phosphate level [see Dosage and Administration (2.3) and Drug Interactions (7.1) ].
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Urothelial Carcinoma with Susceptible FGFR3 Genetic Alterations The efficacy of BALVERSA was evaluated in Study BLC3001 (NCT03390504) Cohort 1, a randomized, open-label, multicenter study in which 266 patients with advanced urothelial cancer harboring selected FGFR3 alterations were randomized 1:1 to receive BALVERSA (8 mg with titration up to 9 mg) versus chemotherapy (docetaxel 75 mg/m 2 once every 3 weeks or vinflunine 320 mg/m 2 once every 3 weeks) until unacceptable toxicity or progression. Randomization was stratified by region (North America vs.
Europe vs. rest of world), Eastern Cooperative Oncology Group (ECOG) performance status (0 or 1 vs. 2) and visceral or bone metastases (yes vs. no). All patients needed to have had disease progression after 1 or 2 prior treatments, at least 1 of which included a PD-1 or PD-L1 inhibitor.
FGFR3 genetic alterations were identified from tumor tissue in a central laboratory by the QIAGEN therascreen ® FGFR RGQ RT-Polymerase Chain Reaction (PCR) kit in 75% of patients while the remainder (25%) were identified by local next generation sequencing (NGS) assays. The major efficacy outcome measures were overall survival (OS), progression-free survival (PFS), and objective response rate (ORR) assessed by investigator using RECIST (Response Evaluation Criteria in Solid Tumors) Version 1.1. The median age was 67 years (range: 32 to 86 years) and 71% were male; 54% were White, 29% Asian, 0.4% Black, 0.4% multiple races, 16% not reported; 2% were Hispanic/Latino; and baseline ECOG performance status was 0 (43%), 1 (48%), or 2 (9%).
Eighty-one percent of patients had FGFR3 mutations, 17% had fusions, and 2% had both mutations and fusions. Ninety-five percent of patients had pure transitional cell carcinoma (TCC) and 5% had TCC with other histologic variants. The primary tumor location was the upper tract for 33% of subjects and lower tract for 67%; 74% of patients had visceral or bone metastases.
Eighty-eight percent of patients received platinum-containing chemotherapy previously. PD-1 or PD-L1 inhibitor therapy was received only in the neoadjuvant or adjuvant setting in 7% of patients. Statistically significant improvements in OS, PFS, and ORR were demonstrated for BALVERSA compared with chemotherapy.
Table 9 and Figures 1 and 2 summarize the efficacy results for BLC3001 Cohort 1. Table 9: Efficacy Results for Study BLC3001 Cohort 1 BALVERSA N=136 Chemotherapy N=130 All p-values reported are 2-sided and compared with 0.019 of the allocated alpha for the interim analysis. ORR = confirmed objective response (CR + PR) CI = Confidence Interval Overall Survival (OS) Number of events (%) 77 (56.6%) 78 (60.0%) Median Based on Kaplan-Meier estimates , months (95% CI) 12.1 (10.3, 16.4) 7.8 (6.5, 11.1) Hazard ratio Based on an unstratified Cox proportional hazard model (95% CI) 0.64 (0.47, 0.88) p-value Based on an unstratified log-rank test 0.0050 Progression-free survival (PFS) Number of events (%) 101 (74.3%) 90 (69.2%) Median , months (95% CI) 5.6 (4.4, 5.7) 2.7 (1.8, 3.7) Hazard ratio (95% CI) 0.58 (0.44, 0.78) p-value 0.0002 Objective response rate (ORR) ORR (95% CI) 35.3% (27.3, 43.9) 8.5% (4.3, 14.6) p-value p-value is estimated using Cochran-Haenszel (CMH) test with ECOG performance status (0 or 1 vs 2) as a stratification factor. <0.001 Complete response, CR (%) 5.1% 0.8% Partial response, PR (%) 30.1% 7.7% Figure 1: Kaplan-Meier Plot of Overall Survival (Study BLC3001 Cohort 1) Figure 2: Kaplan-Meier Plot of Progression-free Survival (Study BLC3001 Cohort 1) Figure 1 Figure 2 Study BLC3001 Cohort 2 Study BLC3001 (NCT03390504) Cohort 2 was a multicenter, open-label, randomized study in 351 patients with locally advanced or metastatic urothelial carcinoma with selected FGFR3 alterations who received 1 prior line of systemic therapy and no prior PD-1 or PD-L1 inhibitor.
Patients were randomized 1:1 to receive BALVERSA (8 mg with titration up to 9 mg) or pembrolizumab 200… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, and Impairment of Fertility Carcinogenicity studies have not been conducted with erdafitinib. Erdafitinib was not mutagenic in a bacterial reverse mutation (Ames) assay and was not clastogenic in an in vitro micronucleus or an in vivo rat bone marrow micronucleus assay. Fertility studies in animals have not been conducted with erdafitinib.
In the 3-month repeat-dose toxicity study, erdafitinib showed effects on female reproductive organs (necrosis of the ovarian corpora lutea) in rats at an exposure less than the human exposure (AUC) at maximum recommended human dose.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, and Impairment of Fertility Carcinogenicity studies have not been conducted with erdafitinib. Erdafitinib was not mutagenic in a bacterial reverse mutation (Ames) assay and was not clastogenic in an in vitro micronucleus or an in vivo rat bone marrow micronucleus assay. Fertility studies in animals have not been conducted with erdafitinib.
In the 3-month repeat-dose toxicity study, erdafitinib showed effects on female reproductive organs (necrosis of the ovarian corpora lutea) in rats at an exposure less than the human exposure (AUC) at maximum recommended human dose.
📄 Patient Package Insert ▾
PATIENT INFORMATION BALVERSA ® (bal-VER-sah) (erdafitinib) tablets This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: 10/2024 What is BALVERSA?
BALVERSA is a prescription medicine used to treat adults with bladder cancer (urothelial cancer) that has spread or cannot be removed by surgery: which has a certain type of abnormal FGFR gene, and who have tried at least one other medicine by mouth or injection (systemic therapy) that did not work or is no longer working. Your healthcare provider will test your cancer for certain types of abnormal FGFR genes and make sure that BALVERSA is right for you. BALVERSA is not recommended for the treatment of people who are eligible for and have not received prior PD-1 or PD-L1 inhibitor therapy.
It is not known if BALVERSA is safe and effective in children. Before taking BALVERSA tell your healthcare provider about all of your medical conditions, including if you: have vision or eye problems. are pregnant or plan to become pregnant. BALVERSA can harm your unborn baby.
You should not become pregnant during treatment with BALVERSA. Females who can become pregnant: Your healthcare provider may do a pregnancy test before you start treatment with BALVERSA. You should use effective birth control during treatment and for 1 month after the last dose of BALVERSA.
Talk to your healthcare provider about birth control methods that may be right for you. Tell your healthcare provider right away if you become pregnant or think you may be pregnant. Males with female partners who can become pregnant: You should use effective birth control when sexually active during treatment with BALVERSA and for 1 month after the last dose. are breastfeeding or plan to breastfeed.
Do not breastfeed during treatment and for 1 month after the last dose of BALVERSA. Tell your healthcare provider about all the medicines you take , including prescription and over-the-counter medicines, vitamins, and herbal supplements. How should I take BALVERSA?
Take BALVERSA exactly as your healthcare provider tells you. Take BALVERSA 1 time each day. Swallow BALVERSA tablets whole with or without food.
Your healthcare provider may change your dose of BALVERSA, temporarily stop or completely stop treatment if you get certain side effects. If you miss a dose of BALVERSA, take the missed dose as soon as possible on the same day. Take your regular dose of BALVERSA the next day.
Do not take more BALVERSA than prescribed to make up for the missed dose. If you vomit after taking BALVERSA, do not take another BALVERSA tablet. Take your regular dose of BALVERSA the next day.
What are the possible side effects of BALVERSA? BALVERSA may cause serious side effects, including: Eye problems. Eye problems are common with BALVERSA but can also be serious.
Eye problems include dry or inflamed eyes, inflamed cornea (front part of the eye) and disorders of the retina, an internal part of the eye. Tell your healthcare provider right away if you develop blurred vision, loss of vision or other visual changes. You should use artificial tear substitutes, hydrating or lubricating eye gels or ointments at least every 2 hours during waking hours to help prevent dry eyes.
During treatment with BALVERSA, your healthcare provider will send you to see an eye specialist. High phosphate levels in the blood (hyperphosphatemia). Hyperphosphatemia is common with BALVERSA but can also be serious.
High levels of phosphate in your blood may lead to build-up of minerals such as calcium in different tissues in your body. Your healthcare provider will check your blood phosphate level between 14 and 21 days after starting treatment with BALVERSA, and then monthly. Your healthcare provider may prescribe changes in your diet or phosphate lowering therapy, or change or stop treatment with BALVERSA if needed.
Tell your healthcare provider right away if you develop painful skin lesions, any muscle cramps, or numbness or tingling around your mouth… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 3 mg Tablet Bottle Carton NDC 59676-030-56 Balversa ® (erdafitinib) tablets 3 mg Each film-coated tablet contains 3 mg of erdafitinib. Rx only 56 film-coated tablets 3 mg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - 4 mg Tablet Bottle Carton NDC 59676-040-56 Balversa ® (erdafitinib) tablets 4 mg Each film-coated tablet contains 4 mg of erdafitinib. Rx only 56 film-coated tablets 4 mg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - 5 mg Tablet Bottle Carton NDC 59676-050-28 Balversa ® (erdafitinib) tablets 5 mg Each film-coated tablet contains 5 mg of erdafitinib. Rx only 28 film-coated tablets 5 mg Tablet Bottle Carton
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |