
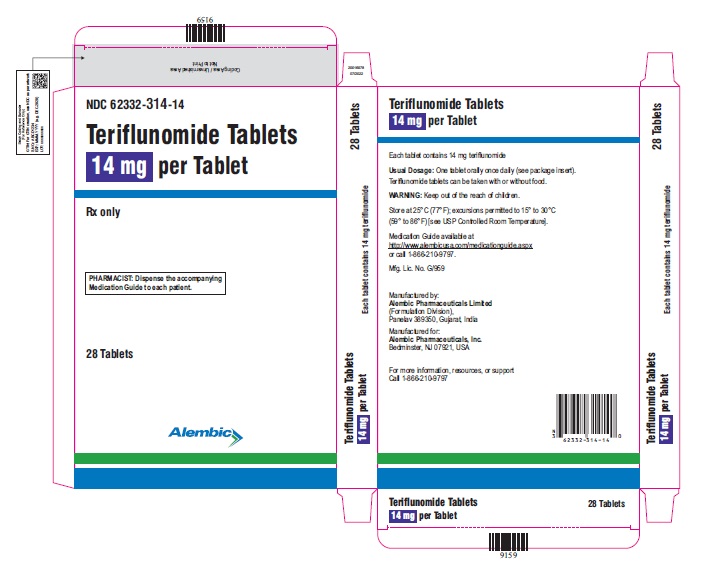
TERIFLUNOMIDE 14 mg Tablet, Film Coated
Other active recalls for Teriflunomide (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Pyrimidine Synthesis Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Teriflunomide helps reduce relapses in adults with relapsing forms of MS — including relapsing-remitting MS, clinically isolated syndrome, and active secondary progressive MS. It w...
- What exactly does teriflunomide do for my MS?
- No — teriflunomide cannot be taken during pregnancy. It has been shown to cause serious birth defects and fetal death in animal studies. Before you start, your doctor will confirm...
- Can I take this medication if I'm pregnant or planning to become pregnant?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Teriflunomide — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII UKE75GEA7F
Hydroxypropyl cellulose is a plant-based polymer used as a binder and thickener. It helps hold tablet ingredients together, controls how fast the medicine dissolves, and improves the texture of liquid formulations.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $4.21 | $117.89 / 28 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Teriflunomide 14 mg 00480-3156-56 | Teva | 30 tablets | $0.242 | AB | Availability likely | — |
| Teriflunomide 14 mg 31722-0247-30 | Camber | 30 tablets | $0.242 | AB | Availability likely | — |
| Teriflunomide 14 mg 70377-0018-11 | Biocon | 30 tablets | $0.242 | AB | Availability likely | — |
| Teriflunomide 14 mg 70710-1115-03 | Zydus | 30 tablets | $0.242 | AB | Availability likely | — |
| Teriflunomide 14 mg 16729-0400-10 | Accord | 30 tablets | $0.693 | AB | FDA listed | — |
| Teriflunomide 14 mg 00378-0628-93 | Mylan | 30 tablets | — | — | FDA listed | — |
| Teriflunomide 14 mg 42291-0831-30 | AvKARE | 30 tablets | — | AB | FDA listed | — |
| Teriflunomide 14 mg 46708-0314-14 | Alembic | 14 tablets | — | AB | FDA listed | — |
| Aubagio 14 mg 58468-0210-01 | Genzyme | 5 tablets | — | AB | FDA listed | — |
| Teriflunomide 14 mg 59651-0055-28 | Aurobindo | 28 tablets | — | AB | FDA listed | — |
| Teriflunomide 14 mgthis 62332-0314-14 | Alembic | 14 tablets | — | AB | FDA listed | — |
| Teriflunomide 14 mg/141 68254-5010-01 | CONCORD | 30 tablets | — | AB | FDA listed | — |
| teriflunomide 14 mg 68462-0424-15 | Glenmark | 14 tablets | — | AB | FDA listed | — |
| Teriflunomide 14 mg 69339-0170-03 | Natco | 30 tablets | — | AB | FDA listed | — |
| Teriflunomide 14 mg 69539-0033-41 | MSN | 14 tablets | — | AB | FDA listed | — |
| Teriflunomide 14 mg 69539-0316-30 | MSN | 30 tablets | — | AB | FDA listed | — |
| Teriflunomide 14 mg 70771-1011-03 | Zydus | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 62332-0314-14 You're viewing this | 2 BLISTER PACK in 1 CARTON (62332-314-14) / 14 TABLET, FILM COATED in 1 BLISTER PACK | — | — | 2023-01-25 | Active |
| 62332-0314-30 | 30 TABLET, FILM COATED in 1 BOTTLE (62332-314-30) | $0.2415 / ea | $7.25 | 2023-01-25 | Active |
| 62332-0314-91 | 1000 TABLET, FILM COATED in 1 BOTTLE (62332-314-91) | — | — | 2023-01-25 | Active |
This pack shows little to no recent Medicaid volume — the 30 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 62332-0314-14?
What NDC number is used to bill for this package of TERIFLUNOMIDE 14 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: HEPATOTOXICITY and EMBRYOFETAL TOXICITY • Hepatotoxicity Clinically significant and potentially life-threatening liver injury, including acute liver failure requiring transplant, has been reported in patients treated with teriflunomide in the postmarketing setting [see Warnings and Precautions (5.1)] . Concomitant use of teriflunomide with other hepatotoxic drugs may increase the risk of severe liver injury. Obtain transaminase and bilirubin levels within 6 months before initiation of teriflunomide tablets therapy.
Monitor ALT levels at least monthly for six months after starting teriflunomide tablets [see Warnings and Precautions (5.1)]. If drug induced liver injury is suspected, discontinue teriflunomide tablets and start an accelerated elimination procedure with cholestyramine or charcoal [see Warnings and Precautions (5.3)]. Teriflunomide tablets are contraindicated in patients with severe hepatic impairment [see Contraindications (4)].
Patients with pre-existing liver disease may be at increased risk of developing elevated serum transaminases when taking teriflunomide tablets. • Embryofetal Toxicity Teriflunomide tablets are contraindicated for use in pregnant women and in females of reproductive potential who are not using effective contraception because of the potential for fetal harm. Teratogenicity and embryolethality occurred in animals at plasma teriflunomide exposures lower than that in humans. Exclude pregnancy before the start of treatment with teriflunomide tablets in females of reproductive potential.
Advise females of reproductive potential to use effective contraception during teriflunomide tablets treatment and during an accelerated drug elimination procedure after teriflunomide tablets treatment. Stop teriflunomide tablets and use an accelerated drug elimination procedure if the patient becomes pregnant [see Contraindications (4), Warnings and Precautions (5.2, 5.3), Use in Specific Populations (8.1, 8.3), and Clinical Pharmacology (12.3)]. WARNING: HEPATOTOXICITY and EMBRYOFETAL TOXICITY See full prescribing information for complete boxed warning. • Hepatotoxicity Clinically significant and potentially life-threatening liver injury, including acute liver failure requiring transplant, has been reported in patients treated with teriflunomide in the postmarketing setting ( 5.1 ).
Concomitant use of teriflunomide with other hepatotoxic drugs may increase the risk of severe liver injury. Obtain transaminase and bilirubin levels within 6 months before initiation of teriflunomide tablets and monitor ALT levels at least monthly for six months ( 5.1 ). If drug induced liver injury is suspected, discontinue teriflunomide tablets and start accelerated elimination procedure ( 5.3 ). • Embryofetal Toxicity Teratogenicity and embryolethality occurred in animals administered teriflunomide ( 5.2 , 8.1 ).
Exclude pregnancy prior to initiating teriflunomide therapy ( 4 , 5.2 , 8.1 , 8.3 ). Advise use of effective contraception in females of reproductive potential during treatment and during an accelerated drug elimination procedure ( 4 , 5.2 , 5.3 , 8.1 , 8.3 ). Stop teriflunomide tablets and use an accelerated drug elimination procedure if the patient becomes pregnant ( 5.2 , 5.3 , 8.1 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Teriflunomide tablets are indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in adults. Teriflunomide tablet is a pyrimidine synthesis inhibitor indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in adults. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dose of teriflunomide tablet is 7 mg or 14 mg orally once daily. Teriflunomide tablets can be taken with or without food. Monitoring to Assess Safety Obtain transaminase and bilirubin levels within 6 months before initiation of teriflunomide tablets therapy.
Monitor ALT levels at least monthly for six months after starting teriflunomide tablets [see Warnings and Precautions (5.1)] . Obtain a complete blood cell count (CBC) within 6 months before the initiation of treatment with teriflunomide tablets. Further monitoring should be based on signs and symptoms of infection [see Warnings and Precautions (5.4)] .
Prior to initiating teriflunomide tablets, screen patients for latent tuberculosis infection with a tuberculin skin test or blood test for mycobacterium tuberculosis infection [see Warnings and Precautions (5.4)] . Exclude pregnancy prior to initiation of treatment with teriflunomide tablets in females of reproductive potential [see Warnings and Precautions (5.2)] . Check blood pressure before start of teriflunomide tablets treatment and periodically thereafter [see Warnings and Precautions (5.10)] .
7 mg or 14 mg orally once daily, with or without food. ( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Teriflunomide tablets are available as 7 mg and 14 mg tablets. The 7 mg tablet is pale blue to pastel blue, hexagonal film-coated tablet debossed with “L” on one side and “597” on other side. Each tablet contains 7 mg of teriflunomide.
The 14 mg tablet is pale blue to pastel blue, pentagonal film-coated tablet debossed with “L” on one side and “598” on other side. Each tablet contains 14 mg of teriflunomide. 7 mg and 14 mg film-coated tablets ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Teriflunomide tablet is contraindicated in/with: ● Patients with severe hepatic impairment [see Warnings and Precautions (5.1)] . ● Pregnant women and females of reproductive potential not using effective contraception. Teriflunomide tablet may cause fetal harm [see Warnings and Precautions (5.2, 5.3) and Use in Specific Populations (8.1)] . ● Patients with a history of a hypersensitivity reaction to teriflunomide, leflunomide, or to any of the inactive ingredients in teriflunomide tablet. Reactions have included anaphylaxis, angioedema, and serious skin reactions [see Warnings and Precautions (5.5)]. ● Coadministration with leflunomide [see Clinical Pharmacology (12.3)]. • Severe hepatic impairment ( 4 , 5.1 ) • Pregnancy ( 4 , 5.2 , 8.1 ) • Hypersensitivity ( 4 , 5.5 ) • Current leflunomide treatment ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Elimination of teriflunomide tablets can be accelerated by administration of cholestyramine or activated charcoal for 11 days. ( 5.3 ) • Teriflunomide tablets may decrease WBC. A recent CBC should be available before starting teriflunomide tablets.
Monitor for signs and symptoms of infection. Consider suspending treatment with teriflunomide tablets in case of serious infection. Do not start teriflunomide tablets in patients with active infections.
( 5.4 ) • Stop teriflunomide tablets if patient has anaphylaxis, angioedema, Stevens-Johnson syndrome, toxic epidermal necrolysis, drug reaction with eosinophilia and systemic symptoms; initiate rapid elimination. ( 5.3 , 5.5 , 5.6 , 5.7 ) • Cutaneous or mucocutaneous ulcers/impaired wound healing: If ulcer or impaired wound healing is suspected, consider discontinuation of teriflunomide tablets treatment and an accelerated drug elimination procedure. ( 5.8 ) • If patient develops symptoms consistent with peripheral neuropathy, evaluate patient and consider discontinuing teriflunomide tablets.
( 5.9 ) • Teriflunomide tablets may increase blood pressure. Measure blood pressure at treatment initiation and monitor blood pressure during treatment. ( 5.10 )
5.1Hepatotoxicity Clinically significant and potentially life-threatening liver injury, including acute liver failure requiring transplant, has been reported in patients treated with teriflunomide tablets in the postmarketing setting. Patients with pre-existing liver disease and patients taking other hepatotoxic drugs may be at increased risk for developing liver injury when taking teriflunomide tablets. Clinically significant liver injury can occur at any time during treatment with teriflunomide tablets.
Patients with pre-existing acute or chronic liver disease, or those with serum alanine aminotransferase (ALT) greater than two times the upper limit of normal (ULN) before initiating treatment, should not normally be treated with teriflunomide tablets. Teriflunomide tablets are contraindicated in patients with severe hepatic impairment [see Contraindications (4)] . In placebo-controlled trials in adult patients, ALT greater than three times the ULN occurred in 61/1,045 (5.8%) and 62/1,002 (6.2%) of patients receiving teriflunomide tablets 7 mg and 14 mg, respectively, and 38/997 (3.8%) of patients receiving placebo, during the treatment period.
These elevations occurred mostly within the first year of treatment. Half of the cases returned to normal without drug discontinuation. In clinical trials, if ALT elevation was greater than three times the ULN on two consecutive tests, teriflunomide tablet was discontinued and patients underwent an accelerated elimination procedure [see Warnings and Precautions (5.3)] .
Of the patients who underwent discontinuation and accelerated elimination in controlled trials, half returned to normal or near normal values within 2 months. One patient in the controlled trials in adult patients developed ALT 32 times the ULN and jaundice 5 months after initiation of teriflunomide tablets 14 mg treatment. The patient was hospitalized for 5 weeks and recovered after plasmapheresis and cholestyramine accelerated elimination procedure.
Teriflunomide tablets-induced liver injury in this patient could not be ruled out. Obtain serum transaminase and bilirubin levels within 6 months before initiation of teriflunomide tablets therapy. Monitor ALT levels at least monthly for six months after starting teriflunomide tablets.
Consider additional monitoring when teriflunomide tablets are given with other potentially hepatotoxic drugs. Consider discontinuing teriflunomide tablets if serum transaminase increase (greater than three times the ULN) is confirmed. Monitor serum transaminase and bilirubin on teriflunomide tablets therapy, particularly in patients who develop symptoms suggestive of hepatic dysfunction, such as unexplained nausea, vomiting, abdominal pain, fatigue, anorexia, or jaundice…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the prescribing information: • Hepatotoxicity [see Contraindications (4) and Warnings and Precautions (5.1)] • Bone Marrow Effects/Immunosuppression Potential/Infections [see Warnings and Precautions (5.4)] • Hypersensitivity Reactions [see Contraindications (4) and Warnings and Precautions (5.5)] • Serious Skin Reactions [see Warnings and Precautions (5.6)] • Drug Reaction with Eosinophilia and Systemic Symptoms [see Warnings and Precautions (5.7)] • Cutaneous or Mucocutaneous Ulcers and Impaired Wound Healing [see Warnings and Precautions (5.8)] • Peripheral Neuropathy [see Warnings and Precautions (5.9)] • Increased Blood Pressure [see Warnings and Precautions (5.10)] • Respiratory Effects [see Warnings and Precautions (5.11)] • Pancreatitis in Pediatric Patients [see Warnings and Precautions (5.12)] Most common adverse reactions (≥10% and ≥2% greater than placebo): headache, diarrhea, nausea, alopecia, increase in ALT.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Alembic Pharmaceuticals Limited at 1-866-210-9797 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. A total of 2,047 patients receiving teriflunomide tablets (7 mg or 14 mg once daily) constituted the safety population in the pooled analysis of placebo-controlled studies in patients with relapsing forms of multiple sclerosis; of these, 71% were female.
The average age was 37 years. Table 1 lists adverse reactions in placebo-controlled trials with rates that were at least 2% for teriflunomide tablets patients and also at least 2% above the rate in placebo patients. The most common were headache, an increase in ALT, diarrhea, alopecia, and nausea.
The adverse reaction most commonly associated with discontinuation was an increase in ALT (3.3%, 2.6%, and 2.3% of all patients in the teriflunomide tablets 7 mg, teriflunomide tablets 14 mg, and placebo treatment arms, respectively). Table 1: Adverse Reactions in Pooled Placebo-Controlled Studies in Patients with Relapsing Forms of Multiple Sclerosis Adverse Reaction Teriflunomide Tablets 7 mg (N=1,045) Teriflunomide Tablets 14 mg (N=1,002) Placebo (N=997) Headache 18% 16% 15% Increase in Alanine aminotransferase 13% 15% 9% Diarrhea 13% 14% 8% Alopecia 10% 13% 5% Nausea 8% 11% 7% Paresthesia 8% 9% 7% Arthralgia 8% 6% 5% Neutropenia 4% 6% 2% Hypertension 3% 4% 2% Cardiovascular Deaths Four cardiovascular deaths, including three sudden deaths, and one myocardial infarction in a patient with a history of hyperlipidemia and hypertension were reported among approximately 2,600 patients exposed to teriflunomide tablets in the premarketing database.
These cardiovascular deaths occurred during uncontrolled extension studies, one to nine years after initiation of treatment. A relationship between teriflunomide tablets and cardiovascular death has not been established. Acute Renal Failure In placebo-controlled studies, creatinine values increased more than 100% over baseline in 8/1,045 (0.8%) patients in the 7 mg teriflunomide tablets group and 6/1,002 (0.6%) patients in the 14 mg teriflunomide tablets group versus 4/997 (0.4%) patients in the placebo group.
These elevations were transient. Some elevations were accompanied by hyperkalemia. Teriflunomide tablets may cause acute uric acid nephropathy with transient acute renal failure because teriflunomide tablets increases renal uric acid clearance.
Hypophosphatemia In clinical trials, 18% of teriflunomide tablets-treated patients had hypophosphatemia with serum phosphorus levels of at least 0.6 mmol/L, compared to 7% of placebo-treated patients; 4% of teriflunomide tablets-tr…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Effect of Teriflunomide Tablets on CYP2C8 Substrates Teriflunomide is an inhibitor of CYP2C8 in vivo . In patients taking teriflunomide tablets, exposure of drugs metabolized by CYP2C8 (e.g., paclitaxel, pioglitazone, repaglinide, rosiglitazone) may be increased. Monitor these patients and adjust the dose of the concomitant drug(s) metabolized by CYP2C8 as required [see Clinical Pharmacology (12.3)] .
Effect of Teriflunomide Tablets on Warfarin Coadministration of teriflunomide tablets with warfarin requires close monitoring of the international normalized ratio (INR) because teriflunomide tablets may decrease peak INR by approximately 25%. Effect of Teriflunomide Tablets on Oral Contraceptives Teriflunomide tablets may increase the systemic exposures of ethinylestradiol and levonorgestrel. Consideration should be given to the type or dose of contraceptives used in combination with teriflunomide tablets [see Clinical Pharmacology (12.3)] .
Effect of Teriflunomide Tablets on CYP1A2 Substrates Teriflunomide may be a weak inducer of CYP1A2 in vivo . In patients taking teriflunomide tablets, exposure of drugs metabolized by CYP1A2 (e.g., alosetron, duloxetine, theophylline, tizanidine) may be reduced. Monitor these patients and adjust the dose of the concomitant drug(s) metabolized by CYP1A2 as required [see Clinical Pharmacology (12.3)] .
Effect of Teriflunomide Tablets on Organic Anion Transporter 3 (OAT3) Substrates Teriflunomide inhibits the activity of OAT3 in vivo . In patients taking teriflunomide tablets, exposure of drugs which are OAT3 substrates (e.g., cefaclor, cimetidine, ciprofloxacin, penicillin G, ketoprofen, furosemide, methotrexate, zidovudine) may be increased. Monitor these patients and adjust the dose of the concomitant drug(s) which are OAT3 substrates as required [see Clinical Pharmacology (12.3)] .
Effect of Teriflunomide Tablets on BCRP and Organic Anion Transporting Polypeptide B1 and B3 (OATP1B1/1B3) Substrates Teriflunomide inhibits the activity of BCRP and OATP1B1/1B3 in vivo . For a patient taking teriflunomide tablets, the dose of rosuvastatin should not exceed 10 mg once daily. For other substrates of BCRP (e.g., mitoxantrone) and drugs in the OATP family (e.g., methotrexate, rifampin), especially HMG-Co reductase inhibitors (e.g., atorvastatin, nateglinide, pravastatin, repaglinide, and simvastatin), consider reducing the dose of these drugs and monitor patients closely for signs and symptoms of increased exposures to the drugs while patients are taking teriflunomide tablets [see Clinical Pharmacology (12.3)] . • Drugs metabolized by CYP2C8 and OAT3 transporters: Monitor patients because teriflunomide may increase exposure of these drugs.
( 7 ) • Teriflunomide may increase exposure of ethinylestradiol and levonorgestrel. Choose an appropriate oral contraceptive. ( 7 ) • Drugs metabolized by CYP1A2: Monitor patients because teriflunomide may decrease exposure of these drugs.
( 7 ) • Warfarin: Monitor INR as teriflunomide may decrease INR. ( 7 ) • Drugs metabolized by BCRP and OATP1B1/B3 transporters: Monitor patients because teriflunomide may increase exposure of these drugs. ( 7 ) • Rosuvastatin: The dose of rosuvastatin should not exceed 10 mg once daily in patients taking teriflunomide tablets.
( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Teriflunomide tablets are contraindicated for use in pregnant women and females of reproductive potential not using effective contraception because of the potential for fetal harm based on animal data [see Contraindications (4) and Warnings and Precautions (5.2)]. In animal reproduction studies in rat and rabbit, oral administration of teriflunomide during organogenesis caused teratogenicity and embryolethality at plasma exposures (AUC) lower than that at the maximum recommended human dose (MRHD) of 14 mg/day [see Data].
Available human data from pregnancy registries, clinical trials, pharmacovigilance cases, and published literature are too limited to draw any conclusions, but they do not clearly indicate increased birth defects or miscarriage associated with inadvertent teriflunomide exposure in the early first trimester when followed by an accelerated elimination procedure [see Clinical Considerations and Data]. There are no human data pertaining to exposures later in the first trimester or beyond. In the US general population, the estimated backgrou nd risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
The background risk of major birth defects and miscarriage in the indicated population is unknown. Clinical Considerations Fetal/Neonatal adverse reactions Lowering the plasma concentration of teriflunomide by instituting an accelerated drug elimination procedure as soon as pregnancy is detected may decrease the risk to the fetus from teriflunomide tablets. The accelerated drug elimination procedure includes verification that the plasma teriflunomide concentration is less than 0.02 mg/L [see Warnings and Precautions (5.3) and Clinical Pharmacology (12.3)].
Data Human data Available human data are limited. Prospectively reported data (from clinical trials and postmarketing reports) from >150 pregnancies in patients treated with teriflunomide and > 300 pregnancies in patients treated with leflunomide have not demonstrated an increased rate of congenital malformations or miscarriage following teriflunomide exposure in the early first trimester when followed by an accelerated elimination procedure. Specific patterns of major congenital malformations in humans have not been observed.
Limitations of these data include an inadequate number of reported pregnancies from which to draw conclusions, the short duration of drug exposure in reported pregnancies, which precludes a full evaluation of the fetal risks, incomplete reporting, and the inability to control for confounders (such as underlying maternal disease and use of concomitant medications). Animal data When teriflunomide (oral doses of 1, 3, or 10 mg/kg/day) was administered to pregnant rats throughout the period of organogenesis, high incidences of fetal malformation (primarily craniofacial, and axial and appendicular skeletal defects) and fetal death were observed at doses not associated with maternal toxicity.
Adverse effects on fetal development were observed following dosing at various stages throughout organogenesis. Maternal plasma exposure at the no-effect level (1 mg/kg/day) for fetal developmental toxicity in rats was less than that in humans at the maximum recommended human dose (MRHD, 14 mg/day). Administration of teriflunomide (oral doses of 1, 3.5, or 12 mg/kg/day) to pregnant rabbits throughout organogenesis resulted in high incidences of fetal malformation (primarily craniofacial, and axial and appendicular skeletal defects) and fetal death at doses associated with minimal maternal toxicity.
Maternal plasma exposure at the no-effect dose (1 mg/kg/day) for fetal developmental toxicity in rabbits was less than that in humans at the MRHD. In studies in which teriflunomide (oral doses of 0.05, 0.1, 0.3, 0.6, or 1 mg/kg/day) was administered to rats during gestation and lactation, decreased growth, eye and skin abnormalities, and high inci…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Teriflunomide tablets are contraindicated for use in pregnant women and females of reproductive potential not using effective contraception because of the potential for fetal harm based on animal data [see Contraindications (4) and Warnings and Precautions (5.2)]. In animal reproduction studies in rat and rabbit, oral administration of teriflunomide during organogenesis caused teratogenicity and embryolethality at plasma exposures (AUC) lower than that at the maximum recommended human dose (MRHD) of 14 mg/day [see Data].
Available human data from pregnancy registries, clinical trials, pharmacovigilance cases, and published literature are too limited to draw any conclusions, but they do not clearly indicate increased birth defects or miscarriage associated with inadvertent teriflunomide exposure in the early first trimester when followed by an accelerated elimination procedure [see Clinical Considerations and Data]. There are no human data pertaining to exposures later in the first trimester or beyond. In the US general population, the estimated backgrou nd risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
The background risk of major birth defects and miscarriage in the indicated population is unknown. Clinical Considerations Fetal/Neonatal adverse reactions Lowering the plasma concentration of teriflunomide by instituting an accelerated drug elimination procedure as soon as pregnancy is detected may decrease the risk to the fetus from teriflunomide tablets. The accelerated drug elimination procedure includes verification that the plasma teriflunomide concentration is less than 0.02 mg/L [see Warnings and Precautions (5.3) and Clinical Pharmacology (12.3)].
Data Human data Available human data are limited. Prospectively reported data (from clinical trials and postmarketing reports) from >150 pregnancies in patients treated with teriflunomide and > 300 pregnancies in patients treated with leflunomide have not demonstrated an increased rate of congenital malformations or miscarriage following teriflunomide exposure in the early first trimester when followed by an accelerated elimination procedure. Specific patterns of major congenital malformations in humans have not been observed.
Limitations of these data include an inadequate number of reported pregnancies from which to draw conclusions, the short duration of drug exposure in reported pregnancies, which precludes a full evaluation of the fetal risks, incomplete reporting, and the inability to control for confounders (such as underlying maternal disease and use of concomitant medications). Animal data When teriflunomide (oral doses of 1, 3, or 10 mg/kg/day) was administered to pregnant rats throughout the period of organogenesis, high incidences of fetal malformation (primarily craniofacial, and axial and appendicular skeletal defects) and fetal death were observed at doses not associated with maternal toxicity.
Adverse effects on fetal development were observed following dosing at various stages throughout organogenesis. Maternal plasma exposure at the no-effect level (1 mg/kg/day) for fetal developmental toxicity in rats was less than that in humans at the maximum recommended human dose (MRHD, 14 mg/day). Administration of teriflunomide (oral doses of 1, 3.5, or 12 mg/kg/day) to pregnant rabbits throughout organogenesis resulted in high incidences of fetal malformation (primarily craniofacial, and axial and appendicular skeletal defects) and fetal death at doses associated with minimal maternal toxicity.
Maternal plasma exposure at the no-effect dose (1 mg/kg/day) for fetal developmental toxicity in rabbits was less than that in humans at the MRHD. In studies in which teriflunomide (oral doses of 0.05, 0.1, 0.3, 0.6, or 1 mg/kg/day) was administered to rats during gestation and lactation, decreased growth, eye and skin abnormalities, and high incidences of malformation (limb d…
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Effectiveness of teriflunomide tablets for the treatment of relapsing form of multiple sclerosis in pediatric patients (10 to 17 years of age) was not established in an adequate and well-controlled clinical study in 166 patients (109 patients received once-daily doses of teriflunomide tablets and 57 patients received placebo) for up to 96 weeks. Pancreatitis has been reported in adults in the postmarketing setting, but appears to occur at higher frequency in the pediatric population.
In this pediatric study, cases of pancreatitis were reported in 1.8% (2/109) of patients who received teriflunomide tablets compared to no patients in the placebo group. All patients in the pediatric trial recovered or were recovering after treatment discontinuation and accelerated elimination procedure [see Warnings and Precautions (5.12)] . Additionally, elevated or abnormal blood creatine phosphokinase was reported in 6.4% of pediatric patients who received teriflunomide tablets compared to no patients in the placebo group.
Juvenile Animal Toxicity Data Oral administration of teriflunomide (0, 0.3, 3, or 6 mg/kg/day) to young rats on postnatal days 21 to 70 resulted in suppression of immune function (T-cell dependent antibody response) at the mid and high doses, and adverse effects on male reproductive organs (reduced sperm count) and altered neurobehavioral function (increased locomotor activity) at the high dose. At the no-effect dose (0.3 mg/kg/day) for developmental toxicity in juvenile rats, plasma exposures were less than those in pediatric patients at the doses of teriflunomide tablets tested in the clinical study.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of teriflunomide tablets did not include patients over 65 years old.
🆘 Overdosage ▾
10 OVERDOSAGE There is no experience regarding teriflunomide overdose or intoxication in humans. Teriflunomide 70 mg daily up to 14 days was well tolerated by healthy subjects. In the event of clinically significant overdose or toxicity, cholestyramine or activated charcoal is recommended to accelerate elimination [see Warnings and Precautions (5.3)] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Teriflunomide, an immunomodulatory agent with anti-inflammatory properties, inhibits dihydroorotate dehydrogenase, a mitochondrial enzyme involved in de novo pyrimidine synthesis. The exact mechanism by which teriflunomide exerts its therapeutic effect in multiple sclerosis is unknown but may involve a reduction in the number of activated lymphocytes in CNS.
12.2Pharmacodynamics Potential to Prolong the QT Interval In a placebo-controlled thorough QT study performed in healthy adult subjects, there was no evidence that teriflunomide caused QT interval prolongation of clinical significance (i.e., the upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc was below 10 ms).
12.3Pharmacokinetics Teriflunomide is the principal active metabolite of leflunomide and is responsible for leflunomide’s activity in vivo . At recommended doses, teriflunomide and leflunomide result in a similar range of plasma concentrations of teriflunomide. Based on a population analysis of teriflunomide in healthy adult volunteers and adult MS patients, median t 1/2 was approximately 18 and 19 days after repeated doses of 7 mg and 14 mg respectively.
It takes approximately 3 months respectively to reach steady-state concentrations. The estimated AUC accumulation ratio is approximately 30 after repeated doses of 7 or 14 mg. Absorption Median time to reach maximum plasma concentrations is between 1 to 4 hours post dose following oral administration of teriflunomide.
Food does not have a clinically relevant effect on teriflunomide pharmacokinetics. Distribution Teriflunomide is extensively bound to plasma protein (>99%) and is mainly distributed in plasma. The volume of distribution is 11 L after a single intravenous (IV) administration.
Metabolism Teriflunomide is the major circulating moiety detected in plasma. The primary biotransformation pathway to minor metabolites of teriflunomide is hydrolysis, with oxidation being a minor pathway. Secondary pathways involve oxidation, N-acetylation and sulfate conjugation.
Elimination Teriflunomide is eliminated mainly through direct biliary excretion of unchanged drug as well as renal excretion of metabolites. Over 21 days, 60.1% of the administered dose is excreted via feces (37.5%) and urine (22.6%). After an accelerated elimination procedure with cholestyramine, an additional 23.1% was recovered (mostly in feces).
After a single IV administration, the total body clearance of teriflunomide is 30.5 mL/h. Drug Interaction Studies Teriflunomide is not metabolized by Cytochrome P450 or flavin monoamine oxidase enzymes. The potential effect of teriflunomide tablets on other drugs CYP2C8 substrates There was an increase in mean repaglinide C max and AUC (1.7-and 2.4-fold, respectively) following repeated doses of teriflunomide and a single dose of 0.25 mg repaglinide, suggesting that teriflunomide is an inhibitor of CYP2C8 in vivo .
The magnitude of interaction could be higher at the recommended repaglinide dose [see Drug Interactions (7)] . CYP1A2 substrates Repeated doses of teriflunomide decreased mean C max and AUC of caffeine by 18% and 55%, respectively, suggesting that teriflunomide may be a weak inducer of CYP1A2 in vivo [see Drug Interactions (7)] . OAT3 substrates There was an increase in mean cefaclor C max and AUC (1.43-and 1.54-fold, respectively), following repeated doses of teriflunomide, suggesting that teriflunomide is an inhibitor of organic anion transporter 3 (OAT3) in vivo [see Drug Interactions (7)] .
BCRP and OATP1B1/1B3 substrates There was an increase in mean rosuvastatin C max and AUC (2.65-and 2.51-fold, respectively) following repeated doses of teriflunomide, suggesting that teriflunomide is an inhibitor of BCRP transporter and organic anion transporting polypeptide 1B1 and 1B3 (OATP1B1/1B3) [see Drug Interactions (7)] . Oral contraceptives There was an increase in mean ethinylestradiol C max and…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Teriflunomide, an immunomodulatory agent with anti-inflammatory properties, inhibits dihydroorotate dehydrogenase, a mitochondrial enzyme involved in de novo pyrimidine synthesis. The exact mechanism by which teriflunomide exerts its therapeutic effect in multiple sclerosis is unknown but may involve a reduction in the number of activated lymphocytes in CNS.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Teriflunomide tablets are available as 7 mg and 14 mg tablets. The 7 mg tablet is pale blue to pastel blue, hexagonal film-coated tablet debossed with “L” on one side and “597” on other side. Each tablet contains 7 mg of teriflunomide.
Teriflunomide tablets 7 mg are supplied as: NDC 62332-313-14 Carton of 28 tablets containing 1 wallet composed of 2 folded blister cards of 14 tablets per blister card NDC 62332-313-30 Bottle of 30 tablets with child-resistant closure The 14 mg tablet is pale blue to pastel blue, pentagonal film-coated tablet debossed with “L” on one side and “598” on other side. Each tablet contains 14 mg of teriflunomide. Teriflunomide tablets 14 mg are supplied as: NDC 62332-314-14 Carton of 28 tablets containing 1 wallet composed of2 folded blister cards of 14 tablets per blister card NDC 62332-314-30 Bottle of 30 tablets with child-resistant closure NDC 62332-314-91 Bottle of 1,000 tablets Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature] .
📋 Description ▾
11 DESCRIPTION Teriflunomide is an oral de novo pyrimidine synthesis inhibitor of the DHO-DH enzyme, with the chemical name (Z)-2-Cyano-3-hydroxy-but-2-enoic acid-(4-trifluoromethylphenyl)-amide. Its molecular weight is 270.21, and the empirical formula is C 12 H 9 F 3 N 2 O 2 with the following chemical structure: Teriflunomide is a white to off-white powder that is soluble in N, N – Dimethyl formamide and practically insoluble in water. Teriflunomide is formulated as film-coated tablets for oral administration.
Teriflunomide tablets contain 7 mg or 14 mg of teriflunomide and the following inactive ingredients: colloidal silicon dioxide, corn starch, hydroxypropyl cellulose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, and sodium starch glycolate. The film coating for the 14 mg tablet is made of FD&C Blue#2 Aluminium Lake, hypromellose, polyethylene glycol 8000, talc, and titanium dioxide. In addition to these, the 7 mg tablet film coating includes iron oxide yellow.
Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). A Medication Guide is required for distribution with teriflunomide tablets. Hepatotoxicity Inform patients that teriflunomide tablets may cause liver injury, which can be life-threatening, and that their liver enzymes will be checked before starting teriflunomide tablets and at least monthly for 6 months after starting teriflunomide tablets [see Dosage and Administration (2) and Warnings and Precautions (5.1)].
Advise patients that they should contact their physician if they have any unexplained nausea, vomiting, abdominal pain, fatigue, anorexia, or jaundice and/or dark urine. Embryofetal Toxicity • Advise females of reproductive potential o of the potential for fetal harm if teriflunomide tablets are taken during pregnancy o to notify their healthcare provider immediately if a pregnancy occurs or is suspected o to use effective contraception during treatment with teriflunomide tablets and until the teriflunomide plasma concentration is verified to be less than 0.02 mg/L [see Warnings and Precautions (5.2, 5.3), Use in Specific Populations (8.1, 8.3), Clinical Pharmacology (12.3)]. • Instruct men taking teriflunomide tablets and not wishing to father a child to use effective contraception to minimize any possible risk to the fetus; their female partners should also use effective contraception. • Advise men wishing to father a child to discontinue use of teriflunomide tablets and undergo an accelerated elimination procedure.
Availability of an Accelerated Elimination Procedure Advise patients that teriflunomide tablets may stay in the blood for up to 2 years after the last dose and that an accelerated elimination procedure may be used if needed [see Warnings and Precautions (5.3)] . Risk of Infections Inform patients that they may develop a lowering of their white blood cell counts and that their blood counts will be checked before starting teriflunomide tablets. Inform patients that they may be more likely to get infections when taking teriflunomide tablets and that they should contact their physician if they develop symptoms of infection, particularly in case of fever [see Warnings and Precautions (5.4)].
Advise patients that the use of some vaccines should be avoided during treatment with teriflunomide tablets and for at least 6 months after discontinuation. Hypersensitivity Reactions Advise patients to discontinue teriflunomide tablets and seek immediate medical attention if any signs or symptoms of a hypersensitivity reaction occur [see Contraindications (4) and Warnings and Precautions (5.5)]. Signs and symptoms can include dyspnea, urticaria, angioedema involving the lips, eyes, throat, or tongue, or skin rash.
Serious Skin Reactions Advise patients to discontinue teriflunomide tablets and seek immediate medical attention if any signs of a serious skin reaction, such as SJS or TEN, occur [see Warnings and Precautions (5.6)] . Signs and symptoms can include rash, mouth sores, blisters, or peeling skin. DRESS/Multi-organ Hypersensitivity Instruct patients and caregivers that a fever or rash associated with signs of other organ system involvement (e.g., lymphadenopathy, hepatic dysfunction) may be drug-related and should be reported to their healthcare provider immediately.
Teriflunomide tablets should be discontinued immediately if a serious hypersensitivity reaction is suspected [see Warnings and Precautions (5.7)] . Cutaneous and Mucocutaneous Ulcers and Impaired Wound Healing Advise patients to seek medical attention if they develop cutaneous or mucocutaneous ulcers or experience impaired wound healing after a surgery [see Warnings and Precautions (5.8)] . Peripheral Neuropathy Inform patients that they may develop peripheral neuropathy.
Advise patients that they should contact their physician if they develop symptoms of peripheral neuropathy, such as numbness or tingling of hands or feet [see Warnings and…
💬 Medication Guide ▾
Medication Guide Teriflunomide (ter” i floo’ noe mide) Tablets, for oral use Read this Medication Guide before you start using teriflunomide tablets and each time you get a refill. There may be new information. This information does not take the place of talking with your healthcare provider about your medical condition or your treatment.
What is the most important information I should know about teriflunomide tablets? Teriflunomide tablets may cause serious side effects, including: ● Liver problems: Teriflunomide tablets may cause serious liver problems, including liver failure that can be life-threatening and may require a liver transplant. Your risk of developing serious liver problems may be higher if you already have liver problems or take other medicines that also affect your liver.
Your healthcare provider should do blood tests to check your liver: o within 6 months before you start taking teriflunomide tablets o 1 time a month for 6 months after you start taking teriflunomide tablets Call your healthcare provider right away if you have any of the following symptoms of liver problems: o nausea o vomiting o stomach pain o loss of appetite o tiredness o your skin or the whites of your eyes turn yellow o dark urine ● Harm to your unborn baby: Teriflunomide tablets may cause harm to your unborn baby.
Do not take teriflunomide tablets if you are pregnant. Do not take teriflunomide tablets unless you are using effective birth control. o If you are a female, you should have a pregnancy test before you start taking teriflunomide tablets. Use effective birth control during your treatment with teriflunomide tablets. o After stopping teriflunomide tablets, continue using effective birth control until you have blood tests to make sure your blood levels of teriflunomide tablets are low enough. o If you become pregnant while taking teriflunomide tablets or within 2 years after you stop taking it, tell your healthcare provider right away. o For men taking teriflunomide tablets: ● If your female partner plans to become pregnant, you should stop taking teriflunomide tablets and ask your healthcare provider how to quickly lower the levels of teriflunomide tablets in your blood. ● If your female partner does not plan to become pregnant, you and your female partner should use effective birth control during your treatment with teriflunomide tablets.
Teriflunomide tablets remains in your blood after you stop taking it, so continue using effective birth control until teriflunomide tablets blood levels have been checked and they are low enough. Teriflunomide tablets may stay in your blood for up to 2 years after you stop taking it. Your healthcare provider can prescribe a medicine to help lower your blood levels of teriflunomide tablets more quickly.
Talk to your healthcare provider if you want more information about this. What is teriflunomide tablet? ● Teriflunomide tablet is a prescription medicine used to treat relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in adults. ● It is not known if teriflunomide tablets are safe and effective in children. Who should not take teriflunomide tablets?
Do not take teriflunomide tablet if you: ● have severe liver problems. ● are pregnant or are of childbearing age and not using effective birth control. ● have had an allergic reaction to leflunomide, teriflunomide or any other ingredients in teriflunomide tablets. Please see the end of this Medication Guide for a complete list of ingredients in teriflunomide tablets. ● take a medicine called leflunomide. Before you take teriflunomide tablets, tell your healthcare provider about all of your medical conditions, including if you : ● have liver or kidney problems. ● have a fever or infection, or you are unable to fight infections. ● have numbness or tingling in your hands or feet that is different from your MS symptoms. ● have diabetes. ● have had serio…