
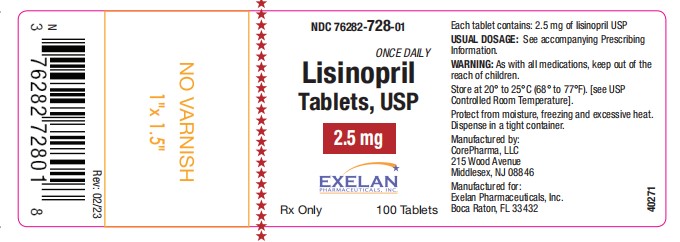
LISINOPRIL 2.5 mg Tablet, 45-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Angiotensin Converting Enzyme Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Lisinopril is used alone or in combination with other medications to treat high blood pressure in adults and children 6 years of age and older. It is used in combination with other medications to treat heart failure. Lisinopril is also used to improve survival after a heart attack. Lisinopril is in a class of medications called angiotensin-converting enzyme (ACE) inhibitors. It works by decreasing certain chemicals that tighten the blood vessels, so blood flows more smoothly and the heart can pump blood more efficiently. High blood pressure is a common condition and when not treated, can cause...
Read the full MedlinePlus article ↗- Lisinopril is mainly prescribed to treat high blood pressure — it relaxes your blood vessels so your heart doesn't have to work as hard. It's also used to help manage heart failure...
- Good news — food doesn't affect how lisinopril works, so you can take it with or without a meal. What matters most is taking it at roughly the same time each day. Once a day is the...
- Can I take lisinopril with food, or does it have to be on an empty stomach?
- Yes, that cough is one of the most well-known side effects of ACE inhibitors like lisinopril. It happens because the medicine also affects a chemical in the lungs called bradykinin...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Lisinopril — tap one for details:
Lisinopril may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
1 inactive ingredient listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1245 | $5.60 / 45 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lisinopril 2.5 mg 00591-0405-01 | Actavis | 100 tablets | $0.014 | — | Availability likely | — |
| lisinopril 2.5 mg 23155-0876-01 | Heritage | 100 tablets | $0.014 | AB | Availability likely | — |
| Lisinopril 2.5 mg 31722-0172-01 | Camber | 100 tablets | $0.014 | AB | Availability likely | — |
| Lisinopril 2.5 mg 43547-0414-10 | Solco | 100 tablets | $0.014 | AB | Availability likely | — |
| Lisinopril 2.5 mg 60687-0656-21 | American | 30 tablets | $0.014 | AB | Availability likely | — |
| Lisinopril 2.5 mg 62135-0640-31 | Chartwell | 300 tablets | $0.014 | AB | Availability likely | — |
| Lisinopril 2.5 mg 68001-0332-00 | BluePoint | 100 tablets | $0.014 | AB | Availability likely | — |
| Lisinopril 2.5 mg 68180-0512-01 | Lupin | 100 tablets | $0.014 | AB | Availability likely | — |
| Lisinopril 2.5 mg 68645-0608-90 | Legacy | 90 tablets | $0.014 | AB | Availability likely | — |
| lisinopril 2.5 mg 76282-0417-01 | Exelan | 100 tablets | $0.014 | AB | Availability likely | — |
| Lisinopril 2.5 mg 82009-0062-05 | Quallent | 500 tablets | $0.014 | AB | Availability likely | — |
| Lisinopril 2.5 mg 00615-8252-05 | NCS | 15 tablets | — | AB | FDA listed | — |
| Zestril 2.5 mg 24979-0238-07 | Upsher-Smith | 90 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 43063-0810-01 | PD-Rx | 100 tablets | — | AB | FDA listed | — |
| lisinopril 2.5 mg 43353-0270-60 | Aphena | 90 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 43547-0351-03 | Solco | 30 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 50090-2431-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 50090-6860-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 51655-0729-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 51655-0999-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 63187-0780-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 63629-5247-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 63629-8736-01 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 63629-8823-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 65862-0037-00 | Aurobindo | 100 tablets | — | — | FDA listed | — |
| Lisinopril 2.5 mg 68071-1894-03 | NuCare | 30 tablets | — | — | FDA listed | — |
| Lisinopril 2.5 mg 68071-5046-01 | NuCare | 100 tablets | — | — | FDA listed | — |
| Lisinopril 2.5 mg 68788-6820-01 | Preferred | 100 tablets | — | — | FDA listed | — |
| Lisinopril 2.5 mg 70518-1316-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 70518-1790-01 | REMEDYREPACK | 100 tablets | — | — | Discontinued | — |
| Lisinopril 2.5 mg 71335-0498-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Lisinopril 2.5 mg 71335-1380-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| lisinopril 2.5 mg 71335-3008-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 71610-0726-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 71610-0741-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 71610-0748-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 72789-0101-01 | PD-Rx | 100 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 72865-0208-01 | XLCare | 100 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mgthis 76282-0728-45 | Exelan | 45 tablets | — | AB | FDA listed | — |
| Lisinopril 2.5 mg 76420-0340-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 76282-0728-01 | 100 TABLET in 1 BOTTLE (76282-728-01) | $0.0142 / ea | $1.42 | 2023-04-07 | Active |
| 76282-0728-05 | 500 TABLET in 1 BOTTLE (76282-728-05) | $0.0142 / ea | $7.12 | 2023-04-07 | Active |
| 76282-0728-10 | 1000 TABLET in 1 BOTTLE (76282-728-10) | — | — | 2023-04-07 | Active |
| 76282-0728-18 | 180 TABLET in 1 BOTTLE (76282-728-18) | — | — | 2023-04-07 | Active |
| 76282-0728-30 | 30 TABLET in 1 BOTTLE (76282-728-30) | — | — | 2023-04-07 | Active |
| 76282-0728-45 You're viewing this | 45 TABLET in 1 BOTTLE (76282-728-45) | — | — | 2023-04-07 | Active |
| 76282-0728-90 | 90 TABLET in 1 BOTTLE (76282-728-90) | — | — | 2023-04-07 | Active |
You're viewing one of 7 pack sizes for this product.
This pack shows little to no recent Medicaid volume — the 500 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 76282-0728-45?
What is the difference between NDC 76282-0728-45 and NDC 76282-0728-30?
What NDC number is used to bill for this package of LISINOPRIL 2.5 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue Lisinopril as soon as possible [see WARNINGS AND PRECAUTIONS (5.1)]. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [see WARNINGS AND PRECAUTIONS (5.1)]. WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning. • When pregnancy is detected, discontinue lisinopril as soon as possible.
(5.1) • Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. (5.1)
🎯 Indications and Usage ▾
1.-INDICATIONS AND USAGE- Lisinopril is an angiotensin converting enzyme (ACE) inhibitor indicated for: Treatment of hypertension in adults and pediatric patients 6 years of age and older ( 1.1) Adjunct therapy for heart failure (1.2) Treatment of Acute Myocardial Infarction (1.3)
1.1Hypertension Lisinopril tablets are indicated for the treatment of hypertension in adult patients and pediatric patients 6 years of age and older to lower blood pressure. Lowering blood pressure lowers the risk offatal and non-fatal cardiovascular events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologicclasses.Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation,exercise, and limited sodium intake.
Many patients will require more than 1 drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as thoseof the National High Blood Pressure Education Program’s Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC).Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidityand mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits.
The largest and mostconsistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly.Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severehypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patientswho are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to alower blood pressure goal.Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., onangina, heart failure, or diabetic kidney disease).
These considerations may guide selection of therapy.Lisinopril may be administered alone or with other antihypertensive agents [see Clinical Studies (14.1)].
1.2Heart Failure Lisinopril tablets are indicated to reduce signs and symptoms of systolic heart failure [see CLINICAL STUDIES (14.2)].
1.3Reduction of Mortality in Acute Myocardial Infarction Lisinopril tablets are indicated for the reduction of mortality in treatment of hemodynamically stable patients within 24 hours of acute myocardial infarction. Patients should receive, as appropriate, the standard recommended treatments such as thrombolytics, aspirin and beta-blockers [see CLINICAL STUDIES (14.3)].
⏱️ Dosage and Administration ▾
2.DOSAGE AND ADMINISTRATION • Hypertension: Initial adult dose is 10 mg once daily. Titrate up to 40 mg daily based on bloodpressure response. Initiate patients on diuretics at 5 mg once daily (2.1) • Pediatric patients with glomerular filtration rate > 30 mL/min/1.73m2 : Initial dose in patients 6years of age and older is 0.07 mg per kg (up to 5 mg total) once daily (2.1) • Heart Failure: Initiate with 5 mg once daily.
Increase dose as tolerated to 40 mg daily (2.2) • Acute Myocardial Infarction (MI): Give 5 mg within 24 hours of MI. Followed by 5 mg after 24hours, then 10 mg once daily (2.3) • Renal Impairment: For patients with creatinine clearance ≥10 mL/min and ≤ 30 mL/min, halveusual initial dose. For patients with creatinine clearance < 10 mL/min or on hemodialysis, therecommended initial dose is 2.5 mg (2.4)
2.1Hypertension Initial Therapy in adults: The recommended initial dose is 10 mg once a day. Dosage should be adjusted according to blood pressure response. The usual dosage range is 20 mg to 40 mg per day administered in a single daily dose.
Doses up to 80 mg have been used but do not appear to give greater effect. Use with diuretics in adults If blood pressure is not controlled with lisinopril alone, a low dose of a diuretic may be added (e.g. hydrochlorothiazide, 12.5 mg). After the addition of a diuretic, it may be possible to reduce the dose of lisinopril.
The recommended starting dose in adult patients with hypertension taking diuretics is 5 mg once per day. Pediatric Patients 6 years of age and older with hypertension For pediatric patients with glomerular filtration rate > 30 mL/min/1.73m2, the recommended starting dose is 0.07 mg per kg once daily (up to 5 mg total). Dosage should be adjusted according to blood pressure response up to a maximum of 0.61 mg per kg (up to 40 mg) once daily.
Doses above 0.61 mg per kg (or in excess of 40 mg) have not been studied in pediatric patients [see CLINICAL PHARMACOLOGY (12.3)]. Lisinopril is not recommended in pediatric patients < 6 years or in pediatric patients with glomerular filtration rate < 30 mL/min/1.73 m2 [see USE IN SPECIFIC POPULATIONS (8.4) and CLINICAL STUDIES (14.1)].
2.2Heart Failure The recommended starting dose for lisinopril, when used with diuretics and (usually) digitalis as adjunctive therapy for systolic heart failure, is 5 mg once daily. The recommended starting dose in these patients with hyponatremia (serum sodium < 130 mEq/L) is 2.5 mg once daily. Increase as tolerated to a maximum of 40 mg once daily.
Diuretic dose may need to be adjusted to help minimize hypovolemia, which may contribute to hypotension [see WARNINGS AND PRECAUTIONS (5.4), and DRUG INTERACTIONS (7.1)]. The appearance of hypotension after the initial dose of lisinopril does not preclude subsequent careful dose titration with the drug, following effective management of the hypotension.
2.3Reduction of Mortality in Acute Myocardial Infarction In hemodynamically stable patients within 24 hours of the onset of symptoms of acute myocardial infarction, give lisinopril 5 mg orally, followed by 5 mg after 24 hours, 10 mg after 48 hours and then 10 mg once daily. Dosing should continue for at least six weeks. Initiate therapy with 2.5 mg in patients with a low systolic blood pressure (≤ 120 mmHg and > 100 mmHg) during the first 3 days after the infarct [see WARNINGS AND PRECAUTIONS (5.4)].
If hypotension occurs (systolic blood pressure ≤ 100 mmHg) a daily maintenance dose of 5 mg may be given with temporary reductions to 2.5 mg if needed. If prolonged hypotension occurs (systolic blood pressure < 90 mmHg for more than 1 hour) lisinopril should be withdrawn.
2.4Dose in Patients with Renal Impairment No dose adjustment of lisinopril is required in patients with creatinine clearance > 30 mL/min. In patients with creatinine clearance ≥ 10 mL/min and ≤ 30 mL/min, reduce the initial dose of lisinopril to half of the usual recommended dose i.e., hypertension, 5 mg; systolic heart failure…
💊 Dosage Forms and Strengths ▾
3. DOSAGE FORMS AND STRENGTHS 2.5 mg Tablets : White to off-white, round, unscored tablets, debossed with "C52" on one side and plain on other side. 5 mg Tablets: Reddish brown colored, over shaped tablets, debossed with bisect between "C" and "53" on one side and plain on other side.
10 mg Tablets: Reddish brown colored, ovel shaped, unscored tablets, debossed with "C54" on one side and plain on other side. 20 mg Tablets: Reddish brown colored, ovel shaped, unscored tablets, debossed with "C55" on one side and plain on other side. 30 mg Tablets: Reddish brown colored, ovel shaped, unscored tablets, debossed with "C56" on one side and plain on other side.
40 mg Tablets: Yellow colore, oval shaped, unscored tablets, debossed with "C57" on one side and plain on other side. Tablets: 2.5 mg, 5 mg, 10 mg, 20 mg, 30 mg, 40 mg (3)
⛔ Contraindications ▾
4. CONTRAINDICATIONS Lisinopril is contraindicated in combination with a neprilysin inhibitor (e.g., sacubitril). Do not administer lisinopril within 36 hours of switching to or from sacubitril/valsartan, a neprilysin inhibitor [seeWarnings and Precautions (5.2)].Lisinopril is contraindicated in patients with: • a history of angioedema or hypersensitivity related to previous treatment with an angiotensin converting enzyme inhibitor • hereditary or idiopathic angioedemaDo not co-administer aliskiren with lisinopril in patients with diabetes [see Drug Interactions (7.4)] • Angioedema or a history of hereditary or idiopathic angioedema (4) • Hypersensitivity (4) • Co-administration of aliskiren with lisinopril in patients with diabetes (4, 7.4)
⚠️ Warnings and Cautions ▾
5. WARNINGS AND PRECAUTIONS • Angioedema: Discontinue lisinopril, provide appropriate therapy and monitor until resolved(5.2) • Renal impairment: Monitor renal function periodically (5.3) • Hypotension: Patients with other heart or renal diseases have increased risk, monitor bloodpressure after initiation (5.4) • Hyperkalemia: Monitor serum potassium periodically (5.5) • Cholestatic jaundice and hepatic failure: Monitor for jaundice or signs of liver failure (5.6)
5.1Fetal Toxicity Lisinopril can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue lisinopril as soon as possible [see Use in specific Populations (8.1)].
5.2Angioedema and Anaphylactoid Reactions Patients taking concomitant mTOR inhibitor (e.g. temsirolimus, sirolimus, everolimus) therapy may be at increased risk for angioedema. [see DRUG INTERACTIONS (7.7)]. Angioedema Head and Neck Angioedema Angioedema of the face, extremities, lips, tongue, glottis and/or larynx, including some fatal reactions, have occurred in patients treated with angiotensin converting enzyme inhibitors, including lisinopril, at any time during treatment. Patients with involvement of the tongue, glottis or larynx are likely to experience airway obstruction, especially those with a history of airway surgery.
Lisinopril should be promptly discontinued and appropriate therapy and monitoring should be provided until complete and sustained resolution of signs and symptoms of angioedema has occurred. Patients with a history of angioedema unrelated to ACE inhibitor therapy may be at increased risk of angioedema while receiving an ACE inhibitor [see CONTRAINDICATIONS (4)]. ACE inhibitors have been associated with a higher rate of angioedema in black than in non-black patients.
Intestinal Angioedema Intestinal angioedema has occurred in patients treated with ACE inhibitors. These patients presented with abdominal pain (with or without nausea or vomiting); in some cases there was no prior history of facial angioedema and C-1 esterase levels were normal. In some cases, the angioedema was diagnosed by procedures including abdominal CT scan or ultrasound, or at surgery, and symptoms resolved after stopping the ACE inhibitor.
Anaphylactoid Reactions Anaphylactoid Reactions During Desensitization Two patients undergoing desensitizing treatment with hymenoptera venom while receiving ACE inhibitors sustained life-threatening anaphylactoid reactions. Anaphylactoid Reactions During Dialysis Sudden and potentially life threatening anaphylactoid reactions have occurred in some patients dialyzed with high-flux membranes and treated concomitantly with an ACE inhibitor. In such patients, dialysis must be stopped immediately, and aggressive therapy for anaphylactoid reactions must be initiated.
Symptoms have not been relieved by antihistamines in these situations. In these patients, consideration should be given to using a different type of dialysis membrane or a different class of antihypertensive agent. Anaphylactoid reactions have also been reported in patients undergoing low-density lipoprotein apheresis with dextran sulfate absorption.
5.3Impaired Renal Function Monitor renal function periodically in patients treated with lisinopril. Changes in renal function including acute renal failure can be caused by drugs that inhibit the renin-angiotensin system. Patients whose renal function may depend in part on the activity of the renin-angiotensin system (e.g., patients with renal artery stenosis, chronic kidney disease, severe congestive heart failure, post-myocardial infarction or…
🤒 Adverse Reactions ▾
6. ADVERSE REACTIONS Common adverse reactions (events 2% greater than placebo) by use: Hypertension: headache, dizziness and cough ( 6.1) Heart Failure: hypotension and chest pain (6.1) Acute Myocardial Infarction: hypotension (6.1) To report SUSPECTED ADVERSE REACTIONS, contact CorePharma, LLC. at 1-732-419-8800 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Hypertension In clinical trials in patients with hypertension treated with lisinopril, 5.7% of patients on lisinopril discontinued with adverse reactions. The following adverse reactions (events 2% greater on lisinopril than on placebo) were observed with lisinopril alone: headache (by 3.8%), dizziness (by 3.5%), cough (by 2.5%).
Heart Failure In patients with systolic heart failure treated with lisinopril for up to four years, 11% discontinued therapy with adverse reactions. In controlled studies in patients with heart failure, therapy was discontinued in 8.1% of patients treated with lisinopril for 12 weeks, compared to 7.7% of patients treated with placebo for 12 weeks. The following adverse reactions (events 2% greater on lisinopril than on placebo) were observed with lisinopril: hypotension (by 3.8%), chest pain (by 2.1%).
In the two-dose ATLAS trial [see CLINICAL STUDIES (14.2)] in heart failure patients, withdrawals due to adverse reactions were not different between the low and high groups, either in total number of discontinuation (17% to 18%) or in rare specific reactions (< 1%). The following adverse reactions, mostly related to ACE inhibition, were reported more commonly in the high dose group: Table 1 Dose-related Adverse Drug Reactions: ATLAS trial High Dose (n=1568) Low Dose (n=1596) Dizziness 19% 12% Hypotension 11% 7% Creatinine increased 10% 7% Hyperkalemia 6% 4% Syncope 7% 5% Acute Myocardial Infarction Patients treated with lisinopril had a higher incidence of hypotension (by 5.3%) and renal dysfunction (by 1.3%) compared with patients not taking lisinopril.
Other clinical adverse reactions occurring in 1% or higher of patients with hypertension or heart failure treated with lisinopril in controlled clinical trials and do not appear in other sections of labeling are listed below: Body as a whole : Fatigue, asthenia, orthostatic effects. Digestive : Pancreatitis, constipation, flatulence, dry mouth, diarrhea. Hematologic: Rare cases of bone marrow depression, hemolytic anemia, leukopenia/neutropenia and thrombocytopenia.
Endocrine : Diabetes mellitus, inappropriate antidiuretic hormone secretion. Metabolic: Gout. Skin : Urticaria, alopecia, photosensitivity, erythema, flushing, diaphoresis, cutaneous pseudolymphoma, toxic epidermal necrolysis, Stevens - Johnson syndrome, and pruritus.
Special Senses: Visual loss, diplopia, blurred vision, tinnitus, photophobia, taste disturbances, olfactory disturbance. Urogenital: Impotence. Miscellaneous: A symptom complex has been reported which may include a positive ANA, an elevated erythrocyte sedimentation rate, arthralgia/arthritis, myalgia, fever, vasculitis, eosinophilia, leukocytosis, paresthesia and vertigo.
Rash, photosensitivity or other dermatological manifestations may occur alone or in combination with these symptoms. Clinical Laboratory Test Findings Serum Potassium : In clinical trials hyperkalemia (serum potassium greater than 5.7 mEq/L) occurred in 2.2% and 4.8% of lisinopril-treated patients with hypertension and heart failure, respectively [see WARNINGS AND PRECAUTIONS (5.5) ]. Creatinine, Blood Urea Nitrogen: Minor increases in blood urea nitrogen and serum creatinine, reversible upon discontinuation of therapy, were observed in about 2% of patients with hypertension treated with lisinopril alone.
Incr…
🔄 Drug Interactions ▾
7. DRUG INTERACTIONS • Diuretics: Excessive drop in blood pressure (7.1) • NSAIDS: Increased risk of renal impairment and loss of antihypertensive efficacy (7.3) • Dual inhibition of the renin-angiotensin system: Increased risk of renal impairment, hypotensionand hyperkalemia (7.4) • Lithium: Symptoms of lithium toxicity (7.5) • Gold: Nitritoid reactions have been reported (7.6) • Concomitant mTOR inhibitor or neprilysin inhibitor use may increase angioedema risk (7.7, 7.8)
7.1Diuretics Initiation of lisinopril in patients on diuretics may result in excessive reduction of blood pressure. The possibility of hypotensive effects with lisinopril can be minimized by either decreasing or discontinuing the diuretic or increasing the salt intake prior to initiation of treatment with lisinopril. If this is not possible, reduce the starting dose of lisinopril [see Dosage and Administration (2.2) and Warnings and Precautions (5.4)].
Lisinopril attenuates potassium loss caused by thiazide-type diuretics. Potassium-sparing diuretics (spironolactone, amiloride, triamterene, and others) can increase the risk of hyperkalemia. Therefore, if concomitant use of such agents is indicated, monitor the patient’s serum potassium frequently.
7.2Antidiabetics Concomitant administration of lisinopril and antidiabetic medicines (insulins, oral hypoglycemic agents) may cause an increased blood-glucose-lowering effect with risk of hypoglycemia.
7.3Non-Steroidal Anti-Inflammatory Agents Including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors) In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with ACE inhibitors, including lisinopril, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving lisinopril and NSAID therapy.
The antihypertensive effect of ACE inhibitors, including lisinopril, may be attenuated by NSAIDs.
7.4Dual Blockade of the Renin-Angiotensin System (RAS) Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. The VA NEPHRON trial enrolled 1448 patients with type 2 diabetes, elevated urinary-albumin-to-creatinine ratio, and decreased estimated glomerular filtration rate (GFR 30 to 89.9 ml/min), randomized them to lisinopril or placebo on a background of losartan therapy and followed them for a median of 2.2 years.
Patients receiving the combination of losartan and lisinopril did not obtain any additional benefit compared to monotherapy for the combined endpoint of decline in GFR, end state renal disease, or death, but experienced an increased incidence of hyperkalemia and acute kidney injury compared with the monotherapy group. In general, avoid combined use of RAS inhibitors. Closely monitor blood pressure, renal function and electrolytes in patients on lisinopril and other agents that affect the RAS.
Do not co-administer aliskiren with lisinopril in patients with diabetes. Avoid use of aliskiren with lisinopril in patients with renal impairment (GFR <60 ml/min).
7.5Lithium Lithium toxicity has been reported in patients receiving lithium concomitantly with drugs, which cause elimination of sodium, including ACE inhibitors. Lithium toxicity was usually reversible upon discontinuation of lithium and the ACE inhibitor. Monitor serum lithium levels during concurrent use.
7.6Gold Nitritoid reactions (symptoms include facial flushing, nausea, vomiting and hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy including lisinopril. 7.7 mTOR Inhibitors Patients taking concomitant mTOR inhibitor (e.g. temsir…
👥 Use in Specific Populations ▾
8. USE IN SPECIFIC POPULATIONS • Lactation: Advise not to breastfeed. (8.2) • Race: Less antihypertensive effect in blacks than non blacks (8.6)
8.1Pregnancy Risk Summary Lisinopril can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue lisinopril as soon as possible. The estimated background risk of major birth defects and miscarriage for the indicated population(s) are unknown. In the general U.S. population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Clinical ConsiderationsDisease-associated maternal and/or embryo/fetal riskHypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly.
Fetal/Neonatal Adverse ReactionsOligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia and skeletal deformations, including skull hypoplasia, hypotension, and death. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of pregnancy. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
Closely observe infants with histories of in utero exposure to lisinopril for hypotension, oliguria, and hyperkalemia. If oliguria or hypotension occur in neonates with a history of in utero exposure to lisinopril, support blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and substituting for disordered renal function.
8.2Lactation Risk Summary No data are available regarding the presence of lisinopril in human milk or the effects of lisinopril on the breast fed infant or on milk production. Lisinopril is present in rat milk. Because of the potential for severe adverse reactions in the breastfed infant, advise women not to breastfeed during treatment with lisinopril
8.4Pediatric Use Antihypertensive effects and safety of lisinopril have been established in pediatric patients aged 6 to 16 years [see Dosage and Administration (2.1) and Clinical Studies (14.1)]. No relevant differences between the adverse reaction profile for pediatric patients and adult patients were identified. Safety and effectiveness of lisinopril have not been established in pediatric patients under the age 6 or in pediatric patients with glomerular filtration rate < 30 mL/min/1.73 m2 [see Dosage and Administration (2.1), Clinical Pharmacology (12.3), and Clinical Studies (14.1)].
Neonates with a history of in utero exposure to lisinopril If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function.
8.5 Geriatric Use N…
🆘 Overdosage ▾
10 OVERDOSAGE Following a single oral dose of 20 g/kg no lethality occurred in rats, and death occurred in one of 20 mice receiving the same dose. The most likely manifestation of overdosage would be hypotension, for which the usual treatment would be intravenous infusion of normal saline solution. Lisinopril can be removed by hemodialysis [see Clinical Pharmacology (12.3)].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Lisinopril inhibits angiotensin-converting enzyme (ACE) in human subjects and animals. ACE is a peptidyl dipeptidase that catalyzes the conversion of angiotensin I to the vasoconstrictor substance,angiotensin II. Angiotensin II also stimulates aldosterone secretion by the adrenal cortex.
The beneficial effects of lisinopril in hypertension and heart failure appear to result primarily from suppressionof the renin-angiotensin-aldosterone system. Inhibition of ACE results in decreased plasma angiotensin II which leads to decreased vasopressor activity and to decreased aldosterone secretion. The latterdecrease may result in a small increase of serum potassium.
In hypertensive patients with normal renal function treated with lisinopril alone for up to 24 weeks, the mean increase in serum potassiumwas approximately 0.1 mEq/L; however, approximately 15% of patients had increases greater than 0.5 mEq/L and approximately 6% had a decrease greater than 0.5 mEq/L. In the same study,patients treated with lisinopril and hydrochlorothiazide for up to 24 weeks had a mean decrease in serum potassium of 0.1 mEq/L; approximately 4% of patients had increases greater than 0.5 mEq/Land approximately 12% had a decrease greater than 0.5 mEq/L [see Clinical Studies (14.1)].
Removal of angiotensin II negative feedback on renin secretion leads to increased plasma renin activity.ACE is identical to kininase, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of lisinopril remains tobe elucidated.While the mechanism through which lisinopril lowers blood pressure is believed to be primarily suppression of the renin-angiotensin-aldosterone system, lisinopril is antihypertensive even in patientswith low-renin hypertension.
Although lisinopril was antihypertensive in all races studied, Black hypertensive patients (usually a low-renin hypertensive population) had a smaller average response tomonotherapy than non Black patients.Concomitant administration of lisinopril and hydrochlorothiazide further reduced blood pressure in Black and non-Black patients and any racial differences in blood pressure response were no longerevident.
12.2Pharmacodynamics Hypertension Adult Patients: Administration of lisinopril to patients with hypertension results in a reduction of both supine and standing blood pressure to about the same extent with no compensatory tachycardia.Symptomatic postural hypotension is usually not observed although it can occur and should be anticipated in volume and/or salt-depleted patients [see Warnings and Precautions (5.4)]. When giventogether with thiazide-type diuretics, the blood pressure lowering effects of the two drugs are approximately additive.In most patients studied, onset of antihypertensive activity was seen at one hour after oral administration of an individual dose of lisinopril, with peak reduction of blood pressure achieved by 6 hours.Although an antihypertensive effect was observed 24 hours after dosing with recommended single daily doses, the effect was more consistent and the mean effect was considerably larger in some studieswith doses of 20 mg or more than with lower doses; however, at all doses studied, the mean antihypertensive effect was substantially smaller 24 hours after dosing than it was 6 hours after dosing.The antihypertensive effects of lisinopril are maintained during long-term therapy.
Abrupt withdrawal of lisinopril has not been associated with a rapid increase in blood pressure, or a significant increasein blood pressure compared to pretreatment levels.Non-Steroidal Anti-Inflammatory AgentsIn a study in 36 patients with mild to moderate hypertension where the antihypertensive effects of lisinopril alone were compared to lisinopril given concomitantly with indomethacin, the use ofindomethacin was associated with a reduced effect, although the difference between the two…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Lisinopril inhibits angiotensin-converting enzyme (ACE) in human subjects and animals. ACE is a peptidyl dipeptidase that catalyzes the conversion of angiotensin I to the vasoconstrictor substance,angiotensin II. Angiotensin II also stimulates aldosterone secretion by the adrenal cortex.
The beneficial effects of lisinopril in hypertension and heart failure appear to result primarily from suppressionof the renin-angiotensin-aldosterone system. Inhibition of ACE results in decreased plasma angiotensin II which leads to decreased vasopressor activity and to decreased aldosterone secretion. The latterdecrease may result in a small increase of serum potassium.
In hypertensive patients with normal renal function treated with lisinopril alone for up to 24 weeks, the mean increase in serum potassiumwas approximately 0.1 mEq/L; however, approximately 15% of patients had increases greater than 0.5 mEq/L and approximately 6% had a decrease greater than 0.5 mEq/L. In the same study,patients treated with lisinopril and hydrochlorothiazide for up to 24 weeks had a mean decrease in serum potassium of 0.1 mEq/L; approximately 4% of patients had increases greater than 0.5 mEq/Land approximately 12% had a decrease greater than 0.5 mEq/L [see Clinical Studies (14.1)].
Removal of angiotensin II negative feedback on renin secretion leads to increased plasma renin activity.ACE is identical to kininase, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of lisinopril remains tobe elucidated.While the mechanism through which lisinopril lowers blood pressure is believed to be primarily suppression of the renin-angiotensin-aldosterone system, lisinopril is antihypertensive even in patientswith low-renin hypertension.
Although lisinopril was antihypertensive in all races studied, Black hypertensive patients (usually a low-renin hypertensive population) had a smaller average response tomonotherapy than non Black patients.Concomitant administration of lisinopril and hydrochlorothiazide further reduced blood pressure in Black and non-Black patients and any racial differences in blood pressure response were no longerevident.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING 2.5 mg Tablets: White to off-white, round, unscored tablets, debossed with “C52” on one side and plain on other side are supplied in bottle of 30 tablets (NDC 76282-728-30), bottle of 45 tablets(NDC 76282-728-45), bottle of 90 tablets (NDC 76282-728-90), bottle of 100 tablets (NDC 76282-728-01), bottle of 180 tablets (NDC 76282-728-18), bottle of 500 tablets (NDC 76282-728-05) and 1000 tablets (NDC76282-728-10). 5 mg Tablets: Reddish brown colored, oval shaped tablets, debossed with bisect between “C” and “53” on one side and plain on other side are supplied in bottles of 30 tablets (NDC 76282-729-30), bottle of 45 tablets (NDC 76282-729-45), bottle of 90 tablets (NDC 76282-729-90), bottle of 100 tablets (NDC 76282-729-01), bottle of 180 tablets (NDC 76282-729-18), bottle of 500tablets (NDC 76282-729-05) and 1000 tablets (NDC 76282-729-10).
10 mg Tablets: Reddish brown colored, oval shaped, unscored tablets, debossed with “C54” on one side and plain on other side are supplied in bottles of 30 tablets (NDC 76282-730-30), bottleof 45 tablets (NDC 76282-730-45), bottle of 90 tablets (NDC 76282-730-90), bottle of 100 tablets (NDC 76282-730-01), bottle of 180 tablets (NDC 76282-730-18), bottle of 500 tablets (NDC76282-730-05), bottle of 1000 tablets (NDC 76282-730-10) and bottle of 5000 tablets (NDC 76282-730-50). 20 mg Tablets: Reddish brown colored, oval shaped, unscored tablets, debossed with “C55” on one side and plain on other side are supplied in bottles of 30 tablets (NDC 76282-731-30), bottleof 45 tablets (NDC 76282-731-45), bottle of 90 tablets (NDC 76282-731-90), bottle of 100 tablets (NDC 76282-731-01), bottle of 180 tablets (NDC 76282-731-18), bottle of 500 tablets (NDC76282-731-05), bottle of 1000 tablets (NDC 76282-731-10) and bottle of 5000 tablets (NDC 76282-731-50).
30 mg Tablets: Reddish brown colored, oval shaped, unscored tablets, debossed with “C56” on one side and plain on other side are supplied in bottles of 30 tablets (NDC 76282-732-30), bottleof 45 tablets (NDC 76282-732-45), bottle of 90 tablets (NDC 76282-732-90), bottle of 100 tablets (NDC 76282-732-01), bottle of 180 tablets (NDC 76282-732-18), bottle of 500 tablets (NDC76282-732-05) and 1000 tablets (NDC 76282-732-10). 40 mg Tablets: Yellow colored, oval shaped, unscored tablets, debossed with “C57” on one side and plain on other side are supplied in bottles of 30 tablets (NDC 76282-733-30), bottle of 45tablets (NDC 76282-733-45), bottle of 90 tablets (NDC 76282-733-90), bottle of 100 tablets (NDC 76282-733-01), bottle of 180 tablets (NDC 76282-733-18), bottle of 500 tablets (NDC 76282-733-05) and 1000 tablets (NDC 76282-733-10).Store at controlled room temperature, 20° to 25°C (68° to 77°F) [see USP].
Protect from moisture, freezing and excessive heat. Dispense in a tight container.
📋 Description ▾
11. DESCRIPTION Lisinopril is an oral long-acting angiotensin converting enzyme (ACE) inhibitor. Lisinopril a synthetic peptide derivative, is chemically described as (S)-1-[N2-(1-carboxy-3-phenylpropyl)-L-lysyl]-L-proline dihydrate.
Its empirical formula is C21H31N3O52H2O and its structural formula is: Lisinopril, USP is a white to off-white, crystalline powder, with a molecular weight of 441.53. It is soluble in water and sparingly soluble in methanol and practically insoluble in ethanol. Lisinopril tablets, USP are supplied as 2.5 mg, 5 mg, 10 mg, 20 mg, 30 mg and 40 mg tablets for oral administration.
Inactive Ingredients: 2.5 mg tablets – anhydrous lactose, magnesium stearate. 5 mg, 10 mg, 20 mg and 30 mg tablets – anhydrous lactose, magnesium stearate, iron oxide red. 40 mg tablets – anhydrous lactose, magnesium stearate, iron oxide yellow.
Lisinopril structure.jpg